Bladder Neck Contracture
Bladder neck contracture (BNC) is pathologic narrowing of the native bladder neck that causes bladder outlet obstruction. Postprocedural BNC can follow TURP, bipolar TURP, HoLEP / endoscopic enucleation, laser vaporization, bladder-neck incision, or radiation-treated outlet tissue. Narrowing at the post-radical-prostatectomy vesicourethral anastomosis is handled separately as vesicourethral anastomotic stenosis (VUAS).
In BNC, the prostate or prostatic fossa may still be present and the external sphincter is usually distal and intact. In VUAS, the prostate is absent and the scar sits immediately proximal to the membranous urethra, so every incision or reconstruction carries a higher continence penalty.
BNC vs VUAS
| Feature | Bladder neck contracture | Vesicourethral anastomotic stenosis |
|---|---|---|
| Typical setting | TURP, HoLEP, laser prostate surgery, simple prostatectomy, radiation/outlet manipulation | Radical prostatectomy or radical cystectomy with orthotopic neobladder |
| Anatomy | Native bladder neck / proximal prostatic fossa | Surgical bladder-to-urethra anastomosis |
| Sphincter relationship | External sphincter distal to the scar | Scar abuts the rhabdosphincter |
| Continence risk with incision | Lower, but not zero | Higher; stress incontinence may be unmasked or worsened |
| Usual first treatment | Endoscopic incision, resection, or dilation | Endoscopic dilation/incision; early reconstruction threshold when recurrent |
| Reconstruction | Y-V plasty, bladder-neck plasty, robotic/open local reconstruction | Robotic/open vesicourethral reconstruction, bladder flap, graft, or combined abdominoperineal repair |
Epidemiology
BNC incidence depends on the index outlet procedure, definition, and follow-up. Contemporary series after transurethral prostate surgery report BNC in roughly 1-6% of patients (2% overall in one 1,008-patient series, 6.4% needing further surgery after TURP in another), with higher rates after bipolar TURP than enucleation in some cohorts.[1][2][4] In a 28-RCT meta-analysis, only eight trials reported BNC; their pooled comparison did not resolve a difference between enucleation and TURP (RR 0.61, 95% CI 0.22-1.66).[14]
Typical reported rates:
| Index procedure | Approximate BNC range | Comments |
|---|---|---|
| Monopolar / bipolar TURP | 4.7% after bipolar TURP in one series; 6.4% requiring further surgery after primary TURP in another[1][2] | Highest risk in small glands, infection, limited adenoma volume, and repeat instrumentation |
| Transurethral enucleation / HoLEP-family procedures | 1.3% after transurethral enucleation in one series[1] | Risk persists but may be lower when the fossa is widely opened |
| Laser vaporization / bladder-neck incision | Variable | Thermal injury and small-gland anatomy |
| Radiated outlet | Variable, higher complexity | Tissue is ischemic, poorly compliant, and more likely to recur |
BNC usually presents within the first postoperative year, but late presentation occurs when progressive fibrosis, infection, repeat instrumentation, or radiation injury is present.[1][2]
Pathophysiology
BNC is a circumferential scar response at the bladder neck. The reconstructive mechanism is familiar: ischemic mucosa, failed epithelial apposition, inflammation, urinary extravasation, infection, and repeated trauma heal by contraction rather than a stable epithelialized lumen.
Contributors:
- Small gland / small resection cavity. Less tissue removed, less funneling, and a tighter healing ring after TURP
- Thermal injury. Coagulation at the bladder neck creates deeper ischemic fibrosis
- Positive urine culture / UTI. Inflammation during healing increases scar burden
- Repeat instrumentation. Catheter trauma, secondary transurethral intervention, and early reoperation add injury
- Microvascular disease. Smoking, diabetes, hypertension, coronary disease, and radiation reduce tissue reserve
- Under-treated outlet obstruction. Persistent high-pressure voiding can worsen symptoms even with a moderate scar
Risk Factors
| Category | Risk factors |
|---|---|
| Patient | Smoking, diabetes, hypertension, coronary artery disease, chronic kidney disease, high comorbidity burden |
| Anatomic | Small prostate volume, low resected tissue weight, high bladder-neck tone, bladder diverticulum |
| Infectious | Preoperative positive urine culture, postoperative UTI, untreated bacteriuria before instrumentation |
| Procedural | TURP or vaporization in a small gland, excess cautery at bladder neck, secondary transurethral procedure, catheter trauma |
| Radiation | Brachytherapy / EBRT-exposed outlet, especially combined-modality treatment |
In TURP cohorts, smaller prostate volume, positive urine culture or preoperative UTI, and secondary transurethral intervention repeatedly emerge as practical warning signs.[1][2][3][4]
Clinical Presentation
Symptoms are obstructive:
- Weak or slow urinary stream
- Straining, hesitancy, intermittency
- Incomplete emptying or elevated PVR
- Acute urinary retention
- Recurrent UTI
- Overflow leakage or worsening urgency from chronic obstruction
- Difficulty passing a catheter after prior outlet surgery
The symptom pattern can resemble recurrent BPH, urethral stricture, detrusor underactivity, or dysfunctional voiding. Cystoscopy localizes the obstruction.
Diagnosis
Core evaluation
- Urinalysis and culture. Treat infection before incision
- Uroflowmetry and PVR. Obstructive curve, low Qmax, elevated residual
- Cystoscopy. Diagnostic test; defines lumen caliber, tissue quality, proximity to sphincter, stones, false passages, and catheterizability
- RUG / VCUG. Useful when posterior urethral stricture, VUAS, or complex anatomy is possible
- Urodynamics. Selected cases with underactive bladder, severe urgency, neurogenic concern, or discordant symptoms
Treatment decisions should follow symptoms and functional obstruction, not cystoscope caliber alone.[9]
Do not miss VUAS
If the patient has had radical prostatectomy, radical cystectomy with orthotopic neobladder, or a prostate-absent outlet, use the VUAS framework. A "bladder neck contracture" label after prostatectomy often hides a different continence and reconstruction problem.
Management
See the Bladder Neck Contracture treatment atlas for endoscopic and open reconstructive options.
First-line: endoscopic incision, resection, or dilation
The 2023 AUA urethral stricture guideline states, as Expert Opinion, that dilation, bladder-neck incision or transurethral resection may be performed for BNC after endoscopic prostate procedures; it leaves technique choice to surgeon preference and notes that repeat treatment may be needed.[6] EAU 2026 strongly recommends transurethral resection or hot-knife incision as first-line treatment for non-obliterative BNC after surgery for benign prostatic obstruction (58.3% patency after resection in 60 BNS patients at median 27 months; 72% after hot-knife incision in a separate 50-person cohort comprising 74% VUAS and 26% BNS at 16 months), and weakly recommends repeat endoluminal treatment to stabilise the stenosis.[9] EAU gives a weak recommendation to warn about de novo or worsened incontinence after endoluminal treatment.[9] Its level 3 summary reports de novo incontinence up to 25% and worsening of existing incontinence up to 15% across non-traumatic posterior stenosis series; these are upper bounds across mixed sites.[9] EAU separately reports de novo incontinence of 0-14% after Y-V/T-plasty for post-benign-surgery BNC and incontinence up to 25% after bulbomembranous reconstruction following benign prostate surgery.[9]
Common techniques:
| Technique | Use |
|---|---|
| Balloon dilation + incision | Thin annular BNC; often 24 Fr dilation followed by deep bilateral incision |
| Cold knife / Collins knife incision | Classic approach; incisions often at 3 and 9 o'clock to open the ring while avoiding rectal and dorsal venous injury |
| Laser incision | Holmium or thulium incision for precise hemostatic cutting |
| Transurethral resection | Dense shelf-like scar or asymmetric contracture; avoid aggressive distal resection near sphincter |
In a retrospective 123-patient series labeled BNC by its authors, 76 had prior radical prostatectomy with or without radiation (VUAS). After balloon dilation and deep bilateral Collins-knife incisions without intralesional agents, a 16 Fr cystoscope passed at approximately two months in 101/123 (82.1%) after one procedure and 116/123 (94.3%) after up to two; median clinical follow-up was 12 months. Two or more prior endoscopic treatments was associated with failure.[5]
Adjunctive agents
Adjuncts attempt to reduce scar recurrence but remain practice-variable:
- Triamcinolone or other intralesional corticosteroid. Triamcinolone is an anti-inflammatory corticosteroid, and injection into the incised scar has been described as an antifibrotic adjunct in two small retrospective posterior-stenosis series; benefit over incision alone is unproven.[9]
- Mitomycin C. Off-label antifibrotic adjunct with heterogeneous retrospective results and potentially severe tissue injury
Mitomycin C has reported cumulative patency of about 75-90% after repeat procedures in recurrent BNC/VUAS series (65% and 58% after the first incision), with lower efficacy in radiated patients.[7][11] Serious events (7%) in the multicenter TURNS series included osteitis pubis, bladder-neck necrosis and rectourethral fistula, sometimes requiring cystectomy and diversion.[11] The EAU states that MMC should not be used outside a clinical trial for non-traumatic posterior stenosis because of these serious events.[9]
Self-catheterization
Short-term clean intermittent catheterization after incision can maintain patency in selected patients, but long-term dependence is a quality-of-life burden and can cause false passage, infection, bleeding, and progressive instrumentation trauma. For recurrent posterior stenosis after dilation or incision, EAU describes intermittent self-dilatation as a maintenance option when reconstruction is unsuitable or declined, but notes reduced quality of life and poor adherence; for patients pursuing reconstruction it can remain a bridge.[9]
Refractory BNC
Refractory BNC means recurrent obstruction after technically adequate endoscopic treatment. Before repeating another incision, define:
- Number and type of prior endoscopic procedures
- Radiation history
- Distance from sphincter
- Incontinence status
- Bladder capacity, compliance, and detrusor function
- Ability to tolerate reconstruction versus chronic catheter / suprapubic tube
Reconstructive options:
| Option | Best use |
|---|---|
| Y-V plasty | Moderate recurrent BNC with usable local bladder-neck tissue |
| Robotic/open bladder-neck plasty | Dense recurrent BNC after multiple endoscopic failures |
| Transurethral incision with transverse mucosal realignment (TUITMR) | Selected short-segment BNC/VUAS where endoscopic suturing can advance healthy mucosa across the scar |
| Bladder flap / posterior urethral reconstruction | Obliterative or radiated stenosis, usually managed in a high-volume reconstructive center |
| Urinary diversion | Devastated outlet, poor bladder, radiation necrosis, fistula, or patient preference after repeated failures |
TUITMR adapts a Y-V-plasty concept endoscopically: scar is incised and healthy bladder mucosa is advanced transversely across the defect with endoscopic suturing. In a retrospective series of 19 patients (9 BNC, 10 VUAS; median follow-up six months), a 17 Fr cystoscope passed at the four-month assessment in 17/19 (89%) after one TUITMR and 19/19 (100%) after up to two; no de novo incontinence was reported, and comparative and long-term data are lacking.[8] A retrospective series from a prospectively maintained registry of 92 men with BNC after BPH surgery reported primary anatomic success (cystoscopic patency) in 93.5% and freedom from reintervention after one procedure in 83.7%; median follow-up was 15.9 months.[18]
For fit patients with treatment-refractory BNC after benign prostate surgery, EAU weakly recommends Y-V or T-plasty reconstruction; open, laparoscopic and robotic approaches are described, with approach selected by anatomy, tissue quality, continence and surgeon expertise.[9] A systematic review of ten small robotic case series (119 men with BNC, VUAS, radiation-associated and rarer posterior defects) reported pooled patency of 95/119 (80%) across variable success definitions and de novo incontinence in 8/47 (17%) men without preexisting incontinence in studies with usable reporting; follow-up across series was about 5-23 months.[15] A 2026 etiology-stratified meta-analysis of 33 reconstructive studies (667 men) found pooled robotic patency of 92% (95% CI 82-97%; n = 95) for BNS and 75% (95% CI 65-82%; n = 96) for VUAS across heterogeneous techniques, endpoints and follow-up.[19] In a 21-patient robotic Y-V plasty series, the 15 men with BNC had no de novo stress incontinence and all de novo cases occurred after VUAS repair; stricture recurrence was 9.5% overall.[16] Counsel that continence risk after repair is higher for VUAS, radiated tissue and prior sphincter compromise.
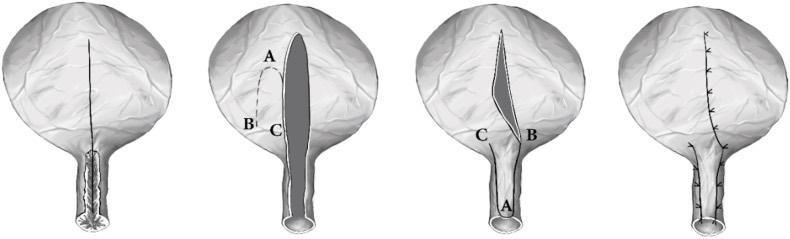
Falling-down rotated bladder flap for recalcitrant bladder neck contracture (schematic, left to right): a midline longitudinal cystotomy on the anterior bladder wall is extended across the outlet to the bulbar urethra; a rectangular or triangular anterior bladder wall flap is outlined (corners A, B and C) and mobilized; the flap is elevated and rotated downward to reconstruct the defect; and the flap is inset with final closure. From Taha T, et al. Urol Case Rep. 2026;66:103435, Fig. 1 (CC BY 4.0).[17]
BNC in the Radiated Prostate
Stenosis of a radiated bladder neck or prostatic urethra follows radiotherapy alone, or outlet surgery before or after radiotherapy. The tissue is ischemic, and relieving obstruction can expose incontinence because the external sphincter may also be damaged. Bulbomembranous stenosis, radiation biology, AUS risk and the devastated outlet are covered on Posterior Urethral Stenosis.
Guidance:[10]
| Situation | Guideline position |
|---|---|
| Non-obliterative | Dilation or incision/resection. EAU supports repeat endoluminal treatment to stabilize patency; SIU suggests one TUR after a failed first incision or resection.[9][10] |
| Repeated failure | Consider reconstructive assessment after repeated failure. AUA conditionally allows robotic or open reconstruction for recalcitrant BNC.[6] SIU grade-C guidance supports open reconstruction for recalcitrant radiation-induced BNC. In a radiated outlet, reconstruction or diversion depends on site, tissue viability, bladder function and continence.[9][10] |
| Obliterative | EAU strongly recommends against endoluminal treatment for completely obliterative VUAS, BMS or BNS. Reconstructive options depend on the stenosis site and bladder function; diversion is reserved for recurrent or complex disease with loss of bladder capacity or incapacitating local symptoms.[9] |
| Fit man with a functional bladder | Reconstructive salvage prostatectomy for a prostatic stricture after irradiation or high-energy treatment (EAU weak; patency in 6/9 men [67%] in one series, substantial morbidity).[9] |
| Incapacitated bladder or disabling local symptoms | Urinary diversion, with cystectomy for intractable pain, spasms or hematuria .[9] |
Evidence and cautions:
- In recurrent BNC or VUAS treated by incision with low-dose mitomycin C, overall success was 94% without radiation versus 76% with it.[7]
- Avoid deep incisions at 6 and 12 o'clock after radiation. They risk rectourethral and urosymphyseal fistula.[10]
- In the TURNS mitomycin series, serious adverse events (7%) included cases leading to cystectomy. Review summaries attribute the osteitis pubis cases to irradiated patients.[11][12]
- Radionecrosis, cavitation, dystrophic calcification or fistula should shift the discussion toward diversion or subtotal prostatectomy rather than further endoscopy.[13]
- TUITMR relies on healthy, mobile mucosa. Long stenoses with radionecrosis may lack the laxity needed for realignment.[13]
Prevention
Practical prevention after benign outlet surgery:
- Treat positive urine cultures before surgery.
- Avoid excessive thermal injury at the bladder neck.
- Create a wide, smooth, epithelialized outlet in small glands.
- Minimize secondary instrumentation and traumatic catheterization.
- Counsel high-risk patients: small prostate volume, smoking, infection, prior radiation, and microvascular disease.
Follow-Up and Failure Patterns
Follow with symptoms, uroflow/PVR, and cystoscopy when symptoms recur. Failure patterns:
- Early recurrence after one incision. Repeat incision may be reasonable.
- Recurrence after two or more endoscopic procedures. Higher failure risk; begin reconstructive counseling.
- Radiated recurrent BNC. Lower threshold for suprapubic diversion, urethral rest, imaging, and referral.
- BNC plus incontinence. Stabilize the outlet after incision and rule out recurrent stenosis by cystoscopy before staged incontinence surgery; the EAU advises a three- to four-month wait after posterior DVIU, while some series wait 12 months.[9]
See Also
- Posterior Urethral Stenosis
- Radiation-Induced Posterior Urethral Stenosis
- Vesicourethral Anastomotic Stenosis
- Benign Prostatic Hyperplasia
- RUG / VCUG
- Bladder Neck Contracture treatment atlas
- Transurethral Incision of BNC (TUIBNC)
- Y-V Plasty
- Bladder Neck Reconstruction
- JNW UrTrac Sheath
Videos
References
1. Wu MH, Liu JX, Zhang YF, et al. "Bladder Neck Contracture Following Transurethral Surgery of Prostate: A Retrospective Single-Center Study." World J Urol. 2024;42(1):14. doi:10.1007/s00345-023-04715-2
2. Gossler C, Pfander F, Haas M, et al. "Risk Factors for Bladder Neck Contracture After Transurethral Resection of the Prostate." Prostate. 2023;83(11):1020-1027. doi:10.1002/pros.24543
3. Garza-Montufar ME, Cobos-Aguilar H, Trevino-Baez JD, Perez-Cortez P. "Factors Associated With Urethral and Bladder Neck Stricture After Transurethral Resection of the Prostate." J Endourol. 2021;35(9):1400-1404. doi:10.1089/end.2020.0847
4. Tao H, Jiang YY, Jun Q, et al. "Analysis of Risk Factors Leading to Postoperative Urethral Stricture and Bladder Neck Contracture Following Transurethral Resection of Prostate." Int Braz J Urol. 2016;42(2):302-311. doi:10.1590/S1677-5538.IBJU.2014.0500
5. Nealon SW, Bhanvadia RR, Badkhshan S, et al. "Transurethral Incisions for Bladder Neck Contracture: Comparable Results Without Intralesional Injections." J Clin Med. 2022;11(15):4355. doi:10.3390/jcm11154355
6. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. "Urethral Stricture Disease Guideline Amendment (2023)." J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482
7. Rozanski AT, Zhang LT, Holst DD, et al. "The Effect of Radiation Therapy on the Efficacy of Internal Urethrotomy With Intralesional Mitomycin C for Recurrent Vesicourethral Anastomotic Stenoses and Bladder Neck Contractures: A Multi-Institutional Experience." Urology. 2021;147:294-298. doi:10.1016/j.urology.2020.09.035
8. Abramowitz DJ, Balzano FL, Ruel NH, Chan KG, Warner JN. "Transurethral Incision With Transverse Mucosal Realignment for the Management of Bladder Neck Contracture and Vesicourethral Anastomotic Stenosis." Urology. 2021;152:102-108. doi:10.1016/j.urology.2021.02.035
9. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Males. 2026. Section 6.3.5.a: non-traumatic posterior urethral stenosis (endoluminal treatment, intralesional injections, reconstruction, diversion). Guideline.
10. Abbasi B, Shaw NM, Lui JL, et al. "Posterior urethral stenosis: a comparative review of the guidelines." World J Urol. 2022;40(11):2591-2600. doi:10.1007/s00345-022-04131-y
11. Redshaw JD, Broghammer JA, Smith TG 3rd, et al. "Intralesional injection of mitomycin C at transurethral incision of bladder neck contracture may offer limited benefit: TURNS Study Group." J Urol. 2015;193(2):587-92. doi:10.1016/j.juro.2014.08.104
12. Naser-Tavakolian A, Lee Z. "A review of management options for vesicourethral anastomotic stenosis and the emergence of robotic reconstruction." Transl Androl Urol. 2025;14(8):2405-2418. doi:10.21037/tau-24-503
13. Ivan SJ, Lee M, Simhan J. "Contemporary management of radiation-associated posterior urethral stenosis: a narrative review." Transl Androl Urol. 2025;14(10):3377-3386. doi:10.21037/tau-2025-183
14. Vo LT, Armany D, Chalasani V, et al. "Endoscopic enucleation of the prostate versus transurethral resection of the prostate for benign prostatic hyperplasia: a systematic review and meta-analysis." Prostate Cancer Prostatic Dis. 2025;28(4):845-858. doi:10.1038/s41391-025-00970-z
15. Zhang TR, Alford A, Zhao LC. "Summarizing the evidence for robotic-assisted bladder neck reconstruction: Systematic review of patency and incontinence outcomes." Asian J Urol. 2024;11(3):341-347. doi:10.1016/j.ajur.2023.08.007
16. Viegas V, Freton L, Richard C, et al. "Robotic YV plasty outcomes for bladder neck contracture vs. vesico-urethral anastomotic stricture." World J Urol. 2024;42(1):172. doi:10.1007/s00345-024-04814-8
17. Taha T, Sidi AA, Tsivian A. "Falling-down bladder flap reconstruction for recalcitrant bladder neck contracture: One complex case and stepwise technique." Urol Case Rep. 2026;66:103435. doi:10.1016/j.eucr.2026.103435
18. Curtis J, Schrup S, Moring N, et al. "Transurethral Incision With Transverse Mucosal Realignment for the Treatment of Bladder Neck Contractures After Benign Prostate Surgery; Mid-term Outcomes." Urology. Published online July 16, 2026. doi:10.1016/j.urology.2026.07.018
19. Roessler N, Klemm J, Fisch M, Dahlem R, Vetterlein MW. "A Systematic Review and Meta-analysis of Surgical Reconstruction for Bladder Neck and Vesicourethral Anastomotic Stenosis: The Case for Etiology-specific Definitions and Reporting." Eur Urol Focus. 2026;12(3):360-372. doi:10.1016/j.euf.2026.06.012