Female Urethral & Periurethral Masses
Female urethral and periurethral masses include benign cystic lesions, benign solid tumors, urethral mucosal lesions, urethral diverticula, and rare malignancies. They are diagnostically tricky because symptoms overlap: recurrent UTI, dysuria, dyspareunia, post-void dribbling, urethral bleeding, vaginal discharge, obstructive voiding, incontinence, and "anterior vaginal wall mass" can all describe different pathologies.[1][2]
The practical frame is: most lesions are benign, but malignancy must stay in the differential. In an academic treatment series, malignancy occurred in 2/126 women with periurethral or anterior vaginal wall masses.[3] In selected tertiary cohorts, malignancy was found in 4/66 urethral diverticula identified during evaluation, and invasive carcinoma in 5/90 excised diverticula.[3][4][18]
Epidemiology and Etiology
The dominant etiologies are urethral diverticulum, Skene gland cyst / abscess, urethral caruncle, and other periurethral cysts.[3][5]
| Lesion | Typical location | Clue |
|---|---|---|
| Urethral diverticulum | Posterior / posterolateral periurethral tissue, often mid-urethral | Communicates with urethra; post-void dribbling, recurrent UTI, dyspareunia, expressible discharge |
| Skene gland cyst / abscess | Distal paraurethral glands flanking the meatus | Anterolateral distal periurethral mass; pain or purulent drainage if infected |
| Urethral caruncle | Posterior lip of urethral meatus | Postmenopausal, red friable meatal polyp |
| Urethral mucosal prolapse | Circumferential meatal mucosal eversion | "Doughnut" mass around central meatus |
| Gartner / Mullerian / inclusion cyst | Anterior or anterolateral vaginal wall | No urethral communication; may mimic urethral diverticulum |
| Leiomyoma | Urethral or paraurethral smooth muscle | Solid, well-defined, vascular lesion |
| Primary urethral carcinoma | Distal or proximal urethra, sometimes within diverticulum | Solid / fixed / bleeding mass, hematuria, obstructive symptoms, suspicious imaging |
In a 126-patient academic series of periurethral and anterior vaginal wall masses, urethral diverticula accounted for 39.7%, Skene gland cysts / abscesses for 30.2%, and malignancy for 1.6%.[3] In a tertiary series of 79 women with periurethral masses, 84% were urethral diverticula (6% of which contained malignancy), 5% leiomyomas, and 2.5% vaginal squamous cell carcinomas.[4] In a 95-patient ultrasound series (98 masses), 39 were urethral diverticula, 35 paraurethral cysts, 13 leiomyomas, 8 caruncles (one with malignant transformation), 2 carcinomas and 1 condyloma.[5]
Diagnostic Approach
Start with anatomy
The first diagnostic move is anatomic: decide whether the lesion is meatal, urethral-dependent, periurethral, or vaginal wall / paravaginal.[1][15][26][40]
| Finding | Most likely diagnoses | Next step |
|---|---|---|
| Posterior meatal polyp | Caruncle, carcinoma mimicking caruncle | Trial estrogen if classic and mild; biopsy / excise if atypical, persistent, bleeding, growing, or painful |
| Circumferential meatal ring | Urethral prolapse | Estrogen / sitz baths if mild; excise if thrombosed, necrotic, obstructing, or refractory |
| Anterior vaginal wall mass with expressible urethral fluid | Urethral diverticulum | Pelvic MRI for surgical mapping; cystoscopy as needed |
| Distal anterolateral periurethral mass | Skene gland cyst / abscess | MRI or ultrasound if uncertain; excision or drainage / excision if symptomatic |
| Well-circumscribed solid or vascular mass without fixation, rapid growth, or bleeding | Leiomyoma, condyloma, other tumor | Ultrasound or MRI; consider cystourethroscopy and biopsy before observation.[5][28] |
| Fixed, rapidly growing, or bleeding mass | Carcinoma or other tumor | MRI, cystourethroscopy, and biopsy.[38] |
| Noncommunicating anterior vaginal wall cyst | Gartner duct, Mullerian, inclusion cyst | See Vaginal Cysts & Masses |
In a 126-woman surgical series, clinical assessment that included pelvic examination and cystoscopy predicted the broad pathology category in 102/126 cases (81%), but the exact pathological diagnosis in 83/126 (66%).[17] The examination should include palpation of the anterior vaginal wall along the entire urethra, inspection of the meatus, attempt to express fluid or debris, cough stress testing if prolapse / mass reduction changes continence, and documentation of tenderness, fixation, bleeding, ulceration, or rapid growth.
Imaging
MRI is the preferred modality for most complex periurethral masses because it can show urethral communication, cystic or solid composition, suspicious enhancing components, and the relationship to the continence mechanism.[1][12][15][26][40] Alternative imaging may be needed when MRI is unavailable or contraindicated.
Transvaginal or transperineal ultrasound is a useful imaging alternative when expertise is available. It can separate cystic from solid lesions, show vascularity on Doppler, and identify common masses such as diverticula, paraurethral cysts, leiomyomas, caruncles, and carcinomas.[5][17]
Cystourethroscopy and biopsy
Cystourethroscopy helps identify diverticular ostia, intraluminal lesions, stones, mucosal irregularity, and lesions requiring biopsy. Obtain tissue diagnosis when carcinoma is suspected, including a fixed, ulcerated, rapidly growing, or recurrent mass or significant or persistent bleeding. For a benign-appearing solid lesion such as presumed leiomyoma, imaging and cystourethroscopy can guide whether biopsy is needed before observation.[28][38] All excised urethral diverticula and periurethral masses should be sent for pathologic examination.[1][18][24]
Benign Urethral and Periurethral Masses
Urethral caruncle
Urethral caruncle is the most common urethral mass in postmenopausal women. It is a benign polypoid outgrowth at the urethral meatus, usually from the posterior lip.[6][7]
| Feature | Practical point |
|---|---|
| Presentation | Often incidental; when symptomatic, pain, hematuria, bleeding, dysuria, or local irritation are common.[7] |
| Histology | Hyperplastic urothelial / squamous lining over inflamed, edematous, vascular stroma; pseudoneoplastic stromal atypia can mimic lymphoma or sarcoma.[7][8] |
| Cancer mimic | Urothelial carcinoma can resemble a caruncle clinically. In a 41-case caruncle series, 5 patients had concurrent or subsequent urothelial carcinoma, but none developed urethral carcinoma.[7][9] |
| Initial treatment | Topical estrogen and observation for classic, mild lesions.[1][10] |
| Biopsy / excision threshold | Thrombosis, significant or recurrent bleeding, urinary retention, persistent pain, atypical appearance, progression, recurrence, or symptoms persisting despite conservative therapy.[1][7][10][11] |
| Postoperative care after excision | Jackson and Adelstein describe a Foley catheter for 3-5 days as a way to reduce meatal-stricture risk, topical vaginal estrogen to support healing in postmenopausal patients, and closure that preserves mucosal eversion; these are the chapter authors' operative recommendations rather than a validated protocol, and the interval should not be extended to circumferential urethral prolapse excision.[47] |
Urethral mucosal prolapse
Urethral prolapse is circumferential eversion of urethral mucosa through the meatus, classically in prepubertal girls and postmenopausal women. The exam finding is a doughnut-shaped edematous mass around the central urethral opening. Mild cases are treated with topical estrogen, sitz baths, and local care; thrombosed, necrotic, obstructing, or refractory prolapse is treated surgically.[1] See Urethral Prolapse.
Urethral diverticulum
Urethral diverticulum is the most common periurethral mass overall and is covered in detail in Urethral Diverticulum. The classic "3 Ds" - dysuria, dyspareunia, and post-void dribbling - are memorable but insensitive. More useful symptom clusters include recurrent UTI, post-void dribbling, dyspareunia, discharge, anterior vaginal wall mass, and urinary incontinence.[3][4][12][13]
MRI is the preferred preoperative test. Before diverticulectomy, EAU 2026 strongly recommends evaluation for coexisting voiding dysfunction and urinary incontinence; pressure-flow or video-urodynamic testing may clarify obstruction, detrusor dysfunction, and stress incontinence in selected women.[49] In a selected 60-patient surgical series, MRI had 100% sensitivity and negative predictive value, with 83% specificity and 92% positive predictive value; cystourethroscopy detected 33% and expressible urethral fluid on palpation was highly predictive.[14] In another operative cohort, MRI differed from surgery in 10/41 women, missing three diverticula and two diverticular cancers; persistent clinical concern warrants further evaluation despite a reassuring scan.[53] MRI maps size, number, configuration, ostium, sphincter relationship, circumferential involvement, and suspicious wall features.[15][12] For recurrent complicated UTI, ACR guidance supports imaging when structural disease is suspected: renal and bladder ultrasound can screen for obstruction and residual urine, while CT urography is generally preferred for comprehensive evaluation when the cause is unclear; MR urography remains an option for selected patients.[16][52] Ultrasound is a cost-effective alternative when expertise is available.[5][17]
Classification
The Leach L/N/S/C3 system records Location (distal, mid, proximal, with or without extension beneath the bladder neck), Number, Size, and Configuration (single, multiloculated, saddle), Communication (site of the ostium), and Continence (presence of stress incontinence).[41] In one MRI-classified series, initial cure after transvaginal diverticulectomy was 100% for simple, 75% for U-shaped and 64% for circumferential diverticula, and circumferential shape independently predicted failure.[23]
Diverticulectomy outcomes
Transvaginal diverticulectomy with layered closure is the standard operation for symptomatic female diverticulum.[19] For women choosing observation, EAU 2026 weakly recommends counseling about the reported 1–6% risk of cancer within a diverticulum.[49]
| Outcome | Typical range / signal |
|---|---|
| Symptoms and continence after surgery | A systematic review found 717/1,044 patients with reported symptom outcomes (69%) completely symptom-free. Separate series found 88/121 (73%) continent at mean 10 months and 72% of 89 women both dry and cured at 3-20 months. A 21-woman series using complete or partial resection reported 76.2% symptom cure despite residual or recurrent diverticula on imaging in 9/21. Narrative reviews cite 83-97% success using heterogeneous definitions.[19][20][21][24][42][43] |
| Recurrence | Cited series reported 3.4% in 89 women at 3-20 months, 4% in 121 at mean 10 months, and 10.1% in a 485-woman cohort; follow-up and ascertainment differ. In a separate 114-woman surgical cohort, estimated 5-year recurrence was 23.4% (95% CI 13.9-37.0) and reoperation was 17.0%. Complex, circumferential, or previously treated lesions may have higher risk.[20][22][23][24][42][48] |
| De novo SUI | Rates vary by definition and timing: a 121-woman diverticulectomy series reported 16/121 (13%) de novo SUI, while a 2026 systematic review summarizes approximately 2-33%. In a 70-woman series, 10/41 previously continent women (24%) reported new SUI immediately after surgery and 5/41 (12%) at 12 months.[19][20][22][43][54] |
| Other postoperative complications | EAU 2026 summarizes early UTI in 0–39% and de novo urinary retention in 0–9% (particularly with concomitant autologous pubovaginal sling), delayed urethral stricture in 0–5.2%, and urethrovaginal fistula in 0.9–8.3% across published series.[49] |
| Carcinoma in excised diverticula | 1/89 (1.1%) and 5/90 (5.6%) in two selected diverticulectomy cohorts.[18][24] |
Surgical principles include a well-vascularized vaginal flap, preservation of periurethral fascia, complete excision of the sac and ostium, watertight urethral closure, multilayer non-overlapping closure, preservation of the continence mechanism, and Martius flap interposition for complex or recurrent defects.[49] Submit excised tissue for histopathologic assessment.[18][24] Distal diverticula may be candidates for marsupialization in selected cases, but this is not the default for mid-urethral or complex lesions.[18][20][22][23][24][25]
In a 485-woman retrospective cohort, concomitant pubovaginal sling was associated with greater resolution of pre-existing SUI (adjusted OR 2.27, 95% CI 1.02-5.03) and higher odds of short- and long-term retention and recurrent UTI; associations with de novo SUI (adjusted OR 0.86, 95% CI 0.25-2.92) and diverticulum recurrence (adjusted OR 1.38, 95% CI 0.67-2.82) were imprecise and not statistically significant.[22] Staged continence treatment remains reasonable, but timing should be individualized: EAU 2026 notes no consensus and weakly recommends a concomitant non-synthetic sling for selected women with bothersome SUI after counseling.[49] It advises against a synthetic midurethral sling at diverticulectomy because of erosion, extrusion, and fistula risks. In one tertiary series, 20/37 women (54%) with pre-existing SUI symptoms were continent after excision at a mean 10-month follow-up.[20][22][49]
Skene gland cysts and abscesses
Skene glands flank the distal urethra and can form cysts or abscesses that mimic urethral diverticulum, Bartholin cyst, or anterior vaginal wall cyst. They usually present as distal anterolateral periurethral masses with pain, dyspareunia, discharge, obstructive voiding, urinary spraying, or recurrent infection.[1][3]
MRI can help distinguish a distal Skene gland lesion from diverticulum by assessing urethral communication. For a symptomatic Skene gland cyst, excision or marsupialization can be considered. For an infected gland or abscess, antibiotics are initial treatment, with drainage or excision if a large abscess does not improve. In a 34-patient excision series for abscess or infection, 9/30 initial responders (30%) had recurrent symptoms requiring further treatment.[1][3][15][26][50][51]
Other periurethral cysts
Gartner duct cysts, Mullerian duct cysts, and dermoid or epidermal inclusion cysts can present as anterior vaginal wall or periurethral masses. The anatomic distinction from diverticulum is absence of urethral communication. MRI is the best single modality when anatomy is uncertain.[15][26] See Vaginal Cysts & Masses.
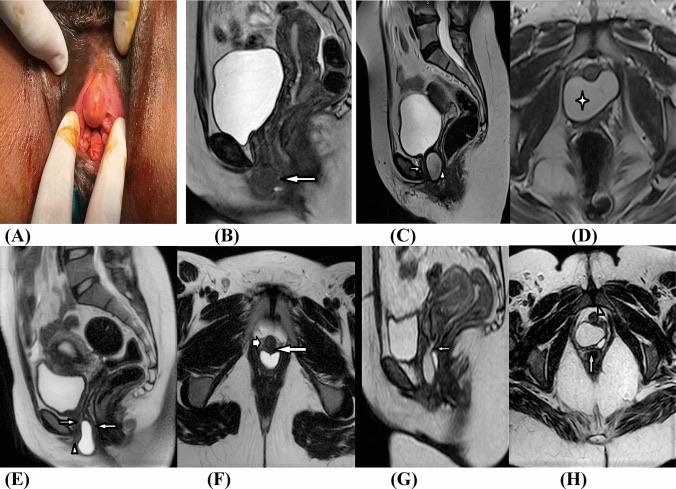
Cystic periurethral and anterior vaginal wall swellings without urethral communication. (A) Skene gland cyst on examination, in its juxtameatal position, everting the urethral meatus. (B) Sagittal T2-weighted MRI: a globular Skene gland cyst (arrow) in the midline just below the external meatus and symphysis, separable from the vagina, with no definite connection to the urethra. (C, D) Sagittal and axial oblique T2: a saddlebag cyst just behind and below the trigone, between the urethra (arrow in C) and the vagina (arrowhead in C), partially encasing the urethra from 3 to 9 o'clock with no connection identified; proteinaceous contents (asterisk in D). (E, F) Sagittal and axial oblique T2: a primary vaginal cyst within the lower third of the vagina splaying its walls (arrows), effacing the urethra (short arrow in F) and meatus (arrowhead in E), with no connection, which excludes urethral origin. (G, H) Sagittal and axial oblique T2: a primary vaginal cyst in the upper two thirds of the vagina with intact walls (arrow in H) and no urethral connection (arrowhead in H); a linear vestigial tract to the vaginal fornix suggested a Gartner duct cyst. From Mahfouz W, et al. World J Urol. 2022;40(6):1587–1594, Fig. 1 (CC BY).[15]
Urethral leiomyoma
Urethral and paraurethral leiomyomas are rare benign smooth-muscle tumors. Ultrasound typically shows a well-defined hypoechoic solid mass with Doppler blood flow.[5][27] Asymptomatic, nonobstructive lesions can be observed with imaging and cystoscopy; symptomatic or obstructing lesions are usually excised transvaginally. In a six-patient paraurethral series there were no recurrences at 32-72 months, but two women developed stress incontinence needing a sling and one needed fascial sling repair of an intraoperative urethral injury.[28][29]
Condyloma acuminatum
HPV-related condyloma can involve the urethral meatus or distal urethra and may appear as a hypoechoic solid mass with Doppler blood flow on ultrasound.[5] Management depends on extent, symptoms, and exclusion of dysplasia or carcinoma.
Malignant Urethral Masses
Primary female urethral carcinoma
Primary urethral carcinoma is extremely rare, and women often present with nonspecific symptoms: hematuria, urethral bleeding, obstructive or irritative LUTS, palpable mass, dysuria, pain, or vaginal discharge.[30][31][32][33] Diagnostic delay is common because benign urethral masses produce the same symptoms.
Female histologic subtypes include adenocarcinoma, squamous cell carcinoma, and urothelial carcinoma. Contemporary pathology reviews emphasize that adenocarcinoma, including clear cell and Skene gland-type adenocarcinoma, is particularly important in women.[30]
In a 32-woman retrospective cohort, tumor size ≥3 cm, stage >T2, and nodal involvement were associated with poorer overall survival on univariate analysis; adenocarcinoma had the poorest outcomes by histology.[31] In older reports, including a 33-woman retrospective series, proximal location was associated with poorer survival.[32][34][38] In an 88-patient mixed-sex cohort, nonurothelial histology was associated with shorter recurrence-free survival and nodal involvement with worse overall survival.[35] Five-year overall survival was 41% in both a 33-woman cohort and a 165-patient mixed-sex series (5-year disease-specific survival 48% in the latter), with better outcomes for early-stage or distal disease than for advanced proximal disease.[34][36][37]
Workup for suspected carcinoma
For suspected urethral carcinoma, EAU strongly recommends urethrocystoscopy with biopsy and urinary cytology, and CT and pelvic MRI for staging:[38]
- Urethrocystoscopy with biopsy and urinary cytology; in women, EAU cites cytology sensitivities of 50% for urothelial carcinoma and 77% for squamous carcinoma.[38]
- Pelvic examination, including assessment of inguinal nodes; examination under anesthesia when needed.
- CT chest, abdomen, and pelvis for distant staging, including CT urography for urothelial evaluation.[38]
- Pelvic MRI for local extent and regional nodes.
Treatment depends on stage, location and histology. Organ preservation is possible in selected distal tumors with clear margins. EAU 2026 strongly recommends academic-center referral for advanced urethral carcinoma and multidisciplinary discussion for locally advanced disease.[38] For locally advanced disease treated with curative intent, it weakly recommends selecting perioperative treatment by histology; it also weakly recommends curative radiotherapy with radiosensitizing chemotherapy for genital preservation in locally advanced squamous cell carcinoma.[38] In EAU-cited series, transurethral resection or laser treatment of small distal urethral tumors had 16% local failure; distal sleeve resection of >2 cm was followed by secondary urinary incontinence requiring reconstruction in 42% of women.[38] For women with localized primary urethral carcinoma, EAU 2026 strongly recommends radical urethrectomy unless organ-preservation criteria are met.[38] For selected distal tumors, urethra-sparing surgery with negative intraoperative margins is a weakly recommended option; local radiotherapy is a separate weak option for localized disease. After urethra-sparing surgery, EAU 2026 describes risk-adapted surveillance with urinary cytology, urethrocystoscopy, and cross-sectional imaging.[38] In long-term female series (median follow-up 153–175 months), partial urethrectomy with intraoperative frozen sections had 22–60% local recurrence.[38][44] Older radiotherapy series reported pelvic toxicity in 49% of patients with local control, including fistula, delayed urethral stenosis, necrosis, cystitis, and hemorrhage; 30% of reported complications were severe.[38][45][46]
Carcinoma arising in urethral diverticulum
Carcinoma arising within a urethral diverticulum is rare but high consequence. Adenocarcinoma, including clear cell adenocarcinoma, is the dominant histology. In a 90-patient diverticulectomy series, 5 women (6%) had invasive carcinoma (one clear-cell and four other adenocarcinomas); intestinal metaplasia and high-grade dysplasia coexisted in some specimens, without establishing a temporal precursor relationship.[18] An invasive carcinoma found in a diverticulum warrants multidisciplinary urethral-cancer treatment planning rather than assuming simple diverticulectomy is sufficient; the operation's extent depends on stage, location, and histology. All five invasive cases in the cited 90-woman series underwent anterior exenteration with urinary diversion; a separate case report describes urethrectomy.[18][38][39]
Red Flags
Biopsy or urgent specialist evaluation is warranted for:
- Solid, fixed, ulcerated, friable, or rapidly enlarging lesion.
- Hematuria, urethral bleeding, or recurrent bleeding from a presumed caruncle.
- Persistent pain or symptoms despite conservative caruncle treatment.
- Suspicious MRI findings: enhancing solid component, irregular wall thickening, restricted diffusion, invasion, or lymphadenopathy.
- Recurrent mass after excision.
- Urethral diverticulum with stones, firm wall, hematuria, or atypical symptoms.
- Any excised diverticulum or periurethral mass without pathology review.
Clinical Pearls
- Urethral diverticulum and Skene gland cyst account for most periurethral / anterior vaginal wall masses in women.[3]
- A meatal lesion that looks like a caruncle can still be cancer; progression, bleeding, recurrence, atypical appearance, or failure to improve should trigger biopsy.[7][9][11]
- MRI is the best preoperative test when a lesion may communicate with the urethra or when surgery is planned.[15][26][40]
- Asymptomatic, nonobstructive benign masses such as small leiomyomas or cysts can be observed if malignancy has been reasonably excluded.[28][2]
- Diverticulectomy pathology is not optional: unexpected malignancy is rare but real.[18][24]
See Also
- Urethral Diverticulum - dedicated diagnostic and surgical planning article.
- Urethral Diverticulum Repair - operative diverticulectomy technique in the treatment atlas.
- Urethral Prolapse Repair - excision technique for circumferential mucosal prolapse.
- Urethral Prolapse - circumferential meatal mucosal eversion.
- Vaginal Cysts & Masses - non-urethral anterior vaginal wall and vaginal masses.
- Female Urethral Stricture - obstructive symptoms and urethral caliber disease.
- Female Pelvic Examination - exam documentation and pelvic assessment.
- MRI - pelvic MRI principles.
Videos
References
1. Zuo SW, Napoe GS. Evaluation and management of urethral and periurethral masses in women. Curr Opin Obstet Gynecol. 2023;35(6):517-524. doi:10.1097/GCO.0000000000000914
2. Serrell EC, McAchran SE. Urethral masses. Obstet Gynecol Clin North Am. 2021;48(3):599-616. doi:10.1016/j.ogc.2021.05.011
3. Jacox N, Yao HH, Baverstock R, Trpkov K, Carlson K. Periurethral and anterior vaginal wall masses: etiology, presentation, and treatment outcomes. Obstet Gynecol. 2022;140(5):778-783. doi:10.1097/AOG.0000000000004956
4. Blaivas JG, Flisser AJ, Bleustein CB, Panagopoulos G. Periurethral masses: etiology and diagnosis in a large series of women. Obstet Gynecol. 2004;103(5 Pt 1):842-847. doi:10.1097/01.AOG.0000124848.63750.e6
5. Yang H, Gu JJ, Jiang L, et al. Ultrasonographic imaging features of female urethral and peri-urethral masses: a retrospective study of 95 patients. Ultrasound Med Biol. 2020;46(8):1896-1907. doi:10.1016/j.ultrasmedbio.2020.03.024
6. Liu Z, Wang X, Shui W, et al. Ultrasonographic features of female urethral caruncle: a retrospective study of 20 patients. Sci Rep. 2024;14(1):17431. doi:10.1038/s41598-024-68355-1
7. Conces MR, Williamson SR, Montironi R, et al. Urethral caruncle: clinicopathologic features of 41 cases. Hum Pathol. 2012;43(9):1400-1404. doi:10.1016/j.humpath.2011.10.015
8. Young RH, Oliva E, Garcia JA, Bhan AK, Clement PB. Urethral caruncle with atypical stromal cells simulating lymphoma or sarcoma: a distinctive pseudoneoplastic lesion of females. Am J Surg Pathol. 1996;20(10):1190-1195. doi:10.1097/00000478-199610000-00003
9. Tatemichi Y, Oikawa H, Maesawa C, et al. Detection of human papillomavirus in a urothelial carcinoma mimicking urethral caruncle. Int J Urol. 2010;17(2):189-191. doi:10.1111/j.1442-2042.2009.02434.x
10. Verma V, Pradhan A. Management of urethral caruncle - a systematic review of the current literature. Eur J Obstet Gynecol Reprod Biol. 2020;248:5-8. doi:10.1016/j.ejogrb.2020.03.001
11. Bolduan JP, Farah RN. Primary urethral neoplasms: review of 30 cases. J Urol. 1981;125(2):198-200. doi:10.1016/s0022-5347(17)54965-4
12. Greenwell TJ, Spilotros M. Urethral diverticula in women. Nat Rev Urol. 2015;12(12):671-680. doi:10.1038/nrurol.2015.230
13. Barakat B, Franke K, Hijazi S, et al. Correlation between symptoms and imaging findings including pelvic floor ultrasound to improve the symptom-based diagnosis of female urethral diverticulum (CHECK-UD Study). Int Urogynecol J. 2022;33(8):2267-2274. doi:10.1007/s00192-021-04770-6
14. Pathi SD, Rahn DD, Sailors JL, et al. Utility of clinical parameters, cystourethroscopy, and magnetic resonance imaging in the preoperative diagnosis of urethral diverticula. Int Urogynecol J. 2013;24(2):319-323. doi:10.1007/s00192-012-1841-9
15. Mahfouz W, Hassan HHM, Gubbiotti M, Elbadry M, Moussa A. Does a tailored magnetic resonance imaging technique affect the surgical planning and outcomes for different cystic urethral and periurethral swellings in females? Seven years tertiary center experience. World J Urol. 2022;40(6):1587-1594. doi:10.1007/s00345-022-03973-w
16. Venkatesan AM, Oto A, Allen BC, et al. ACR Appropriateness Criteria recurrent lower urinary tract infections in females. J Am Coll Radiol. 2020;17(11S):S487-S496. doi:10.1016/j.jacr.2020.09.003
17. Touma N, Yao HH, Shamout S, et al. Peri-urethral and anterior vaginal wall masses: does radiological imaging change the predicted diagnosis? Neurourol Urodyn. 2023;42(4):746-750. doi:10.1002/nau.25147
18. Thomas AA, Rackley RR, Lee U, et al. Urethral diverticula in 90 female patients: a study with emphasis on neoplastic alterations. J Urol. 2008;180(6):2463-2467. doi:10.1016/j.juro.2008.08.040
19. Bodner-Adler B, Halpern K, Hanzal E. Surgical management of urethral diverticula in women: a systematic review. Int Urogynecol J. 2016;27(7):993-1001. doi:10.1007/s00192-015-2862-y
20. Osman NI, Mangir N, Reeves FA, et al. The modified prone jack-knife position for the excision of female urethral diverticula. Eur Urol. 2021;79(2):290-297. doi:10.1016/j.eururo.2020.11.016
21. Chen X, Ang X, Xu X, et al. Experience in conversion of symptomatic urethral diverticulum to asymptomatic status through surgery. Sci Rep. 2025;15(1):7533. doi:10.1038/s41598-025-90748-z
22. Bradley SE, Leach DA, Panza J, et al. A multicenter retrospective cohort study comparing urethral diverticulectomy with and without pubovaginal sling. Am J Obstet Gynecol. 2020;223(2):273.e1-273.e9. doi:10.1016/j.ajog.2020.06.002
23. Ko KJ, Suh YS, Kim TH, et al. Surgical outcomes of primary and recurrent female urethral diverticula. Urology. 2017;105:181-185. doi:10.1016/j.urology.2017.02.040
24. Reeves FA, Inman RD, Chapple CR. Management of symptomatic urethral diverticula in women: a single-centre experience. Eur Urol. 2014;66(1):164-172. doi:10.1016/j.eururo.2014.02.041
25. Welch EK, Dengler KL, Welgoss JA. Urethral diverticulum marsupialization with modified Spence-Duckett procedure. Urology. 2023;176:248. doi:10.1016/j.urology.2023.02.040
26. Itani M, Kielar A, Menias CO, et al. MRI of female urethra and periurethral pathologies. Int Urogynecol J. 2016;27(2):195-204. doi:10.1007/s00192-015-2790-x
27. Wu S, Min Z, Wu L, Zhang M, Wu L. A urethral leiomyoma presenting with dysuria: a rare case report. Medicine (Baltimore). 2024;103(20):e37893. doi:10.1097/MD.0000000000037893
28. Cornella JL, Larson TR, Lee RA, Magrina JF, Kammerer-Doak D. Leiomyoma of the female urethra and bladder: report of twenty-three patients and review of the literature. Am J Obstet Gynecol. 1997;176(6):1278-1285. doi:10.1016/s0002-9378(97)70346-6
29. Migliari R, Buffardi A, Mosso L. Female paraurethral leiomyoma: treatment and long-term follow-up. Int Urogynecol J. 2015;26(12):1821-1825. doi:10.1007/s00192-015-2776-8
30. Lagarde-Lenon MS, Aron M. Female urethral carcinoma: a contemporary review of the clinicopathologic features, with emphasis on the histoanatomic landmarks and potential staging issues. Hum Pathol. 2022;129:71-80. doi:10.1016/j.humpath.2022.08.003
31. Lee W, Yu J, Lee JL, Kim YS, Hong B. Clinical features and oncological outcomes of primary female urethral cancer. J Surg Oncol. 2022;125(5):907-915. doi:10.1002/jso.26790
32. Levine RL. Urethral cancer. Cancer. 1980;45 Suppl 7:1965-1972. doi:10.1002/cncr.1980.45.s7.1965
33. Dayyani F, Hoffman K, Eifel P, et al. Management of advanced primary urethral carcinomas. BJU Int. 2014;114(1):25-31. doi:10.1111/bju.12630
34. Grigsby PW, Corn BW. Localized urethral tumors in women: indications for conservative versus exenterative therapies. J Urol. 1992;147(6):1516-1520. doi:10.1016/s0022-5347(17)37614-0
35. Wang B, Nandwana D, Davis LE, et al. Clinical and histological predictors of treatment outcomes in primary urethral carcinoma. Urol Oncol. 2025;43(12):700-705. doi:10.1016/j.urolonc.2025.09.003
36. Kobayashi K, Daizumoto K, Tsujino T, et al. Clinical outcomes and clinicopathological features of primary urethral carcinoma: a multicenter retrospective study in Japan. Int J Urol. 2026;33(2):e70367. doi:10.1111/iju.70367
37. Mano R, Vertosick EA, Sarcona J, et al. Primary urethral cancer: treatment patterns and associated outcomes. BJU Int. 2020;126(3):359-366. doi:10.1111/bju.15095
38. European Association of Urology. EAU Guidelines on Primary Urethral Carcinoma. 2026. Diagnostic evaluation and staging; Disease management.
39. Li D, Meng FH, Yang X. Female urethral diverticular carcinoma: a case report and review of the literature. Front Oncol. 2024;14:1503116. doi:10.3389/fonc.2024.1503116
40. Saidman JM, Aineseder M, Garratt J, et al. Imaging the female urethra: US and MRI in cystic and solid pathologic conditions. Radiographics. 2025;45(3):e240064. doi:10.1148/rg.240064
41. Leach GE, Sirls LT, Ganabathi K, Zimmern PE. L N S C3: a proposed classification system for female urethral diverticula. Neurourol Urodyn. 1993;12(6):523-31. doi:10.1002/nau.1930120602
42. Daniels C, Wong TR, Isali I. Rethinking urethral diverticulum: a narrative review of clinical outcomes and cancer associations. Int Urogynecol J. 2025;36(11):2169-2176. doi:10.1007/s00192-025-06244-5
43. Shadyan G, Al-Jamal J, McCormick KM, et al. Surgical techniques for female urethral diverticulectomy: a systematic review and educational video presentation. Int Urogynecol J. 2026;37(7):2193-2197. doi:10.1007/s00192-026-06690-9
44. Dimarco DS, Dimarco CS, Zincke H, et al. Surgical treatment for local control of female urethral carcinoma. Urol Oncol. 2004;22(5):404-409. doi:10.1016/S1078-1439(03)00174-1
45. Janisch F, Abufaraj M, Fajkovic H, et al. Current Disease Management of Primary Urethral Carcinoma. Eur Urol Focus. 2019;5(5):722-734. doi:10.1016/j.euf.2019.07.001
46. Son CH, Liauw SL, Hasan Y, Solanki AA. Optimizing the Role of Surgery and Radiation Therapy in Urethral Cancer Based on Histology and Disease Extent. Int J Radiat Oncol Biol Phys. 2018;102(2):304-313. doi:10.1016/j.ijrobp.2018.06.007
47. Jackson JC, Adelstein SA. Vaginal Surgery Complications. In: Martins FE, Holm HV, Sandhu JS, McCammon KA, eds. Female Genitourinary and Pelvic Floor Reconstruction. Springer; 2023:657-673. doi:10.1007/978-3-031-19598-3_39
48. El-Nashar SA, Singh R, Bacon MM, et al. "Female Urethral Diverticulum: Presentation, Diagnosis, and Predictors of Outcomes After Surgery." Female Pelvic Med Reconstr Surg. 2016;22(6):447-452. doi:10.1097/SPV.0000000000000312
49. European Association of Urology. EAU Guidelines on Non-neurogenic Female LUTS. 2026. Urethral diverticulum disease management, §4.9.
50. Tamburrini S, Vascone C, Marrone V, et al. "Skene's glands abscess an overlooked diagnosis in acute lower urinary symptoms." Radiol Case Rep. 2021;16(12):3751-3756. doi:10.1016/j.radcr.2021.09.006
51. Shah SR, Biggs GY, Rosenblum N, Nitti VW. "Surgical management of Skene's gland abscess/infection: a contemporary series." Int Urogynecol J. 2012;23(2):159-164. doi:10.1007/s00192-011-1488-y
52. Expert Panel on Urological Imaging; Ward RD, Allen BC, Turkbey B, et al. "ACR Appropriateness Criteria® Recurrent Lower Urinary Tract Infections in Females: Update 2026." J Am Coll Radiol. 2026;23(8):1753-1767. doi:10.1016/j.jacr.2026.03.006
53. Chung DE, Purohit RS, Girshman J, Blaivas JG. "Urethral diverticula in women: discrepancies between magnetic resonance imaging and surgical findings." J Urol. 2010;183(6):2265-2269. doi:10.1016/j.juro.2010.02.016
54. Malde S, Sihra N, Naaseri S, et al. "Urethral diverticulectomy with Martius labial fat pad interposition improves symptom resolution and reduces recurrence." BJU Int. 2017;119(1):158-163. doi:10.1111/bju.13579