Female Urethral Stricture
Female urethral stricture (FUS) is a fixed anatomical narrowing of the female urethra. It is uncommon, diagnosis may be delayed, and some patients undergo repeated dilation before reconstruction is considered.[6] Bladder outlet obstruction (BOO) is uncommon in women (about 2.7–8% of those referred for voiding problems in one review[1]), and stricture is one of its less frequent causes. The EAU pools 2–29% of women with refractory lower urinary tract symptoms as having BOO, of whom 4–20% have a urethral stricture, a true FUS prevalence of roughly 0.08–5.4% of women with refractory LUTS.[2][6] It is easily overlooked in this group.
Epidemiology
FUS is considered rare but is substantially underdiagnosed due to non-specific presentation, lack of a standardized diagnostic definition, and historical tendency to attribute obstructive voiding symptoms in women to functional rather than anatomical causes.[3] There is no high-quality population prevalence data. Incidence rises markedly in women over 64 years, and diagnosis is often delayed by years (mean 4.3–12 years from symptom onset in the series pooled by the EAU).[6] Waterloos and Verla estimate that about 10% of women with obstructive voiding have a true anatomical stricture.[4]
The evidence base remains dominated by small surgical series with inconsistent definitions and follow-up.[2][3]
Etiology
| Category | Key Causes |
|---|---|
| Iatrogenic | Traumatic or repeated urethral catheterization; urethral dilation itself causing fibrosis; pelvic surgery; radiation therapy; prior anti-incontinence procedures |
| Lichen sclerosus (LS) | Progressive inflammatory fibrosis; typically distal/meatal; genital mucosa is avoided in LS-related reconstruction and oral mucosa is favored when substitution is needed (expert advice extrapolated in part from male urethroplasty).[4] |
| Inflammatory | Recurrent UTIs; urethritis; sexually transmitted infections |
| Traumatic | Blunt pelvic trauma; obstetric injury (cephalopelvic disproportion, instrumented delivery) |
| Idiopathic | No identifiable cause; diagnosis of exclusion |
| Other | Malignancy; radiation; urethral or vaginal atrophy; lichen planus |
Pooled etiology. In the series pooled by the EAU, FUS was idiopathic in 48.5% and iatrogenic in 24.1% (prior dilation, difficult or traumatic catheterization, and urethral surgery such as diverticulum surgery, fistula repair and anti-incontinence procedures); trauma (mainly pelvic fracture) accounted for 16.4%.[17] Radiation and infection are rare causes. The mid or mid-to-distal urethra is most often involved (58%); panurethral disease is rare (4%).[6] The AUA lists blunt pelvic trauma, obstetric injury, malignancy, radiation, atrophy, recurrent infection and lichen planus or lichen sclerosus among other causes.[8]
Catheterization and dilation as a cause. The EAU lists prior urethral dilation and difficult or traumatic catheterization among reported iatrogenic causes of FUS.[17] Urethral dilation has been described as "often overused and unnecessary, leading to significant healthcare costs" in the management of FUS.[2]
Diagnostic Criteria and Workup
Diagnosis is challenging because symptoms are non-specific and no definition is universally accepted. Most authors define FUS as a fixed anatomical narrowing that reduces urethral calibre.[6] Published cut-offs range from <10 Fr to <20 Fr (most often <14 Fr), against a normal calibre of about 18–30 Fr.[6] Combine symptoms, flow and residual, and endoscopic or radiographic evidence of narrowing.[6]
Clinical Presentation
Women with FUS present with mixed storage and voiding symptoms:[4][3][6]
- Weak or reduced urinary stream
- Urinary hesitancy and straining to void
- Incomplete bladder emptying
- Post-void dribbling
- Urinary frequency, urgency and nocturia
- Recurrent urinary tract infections
- Urinary retention (acute or chronic)
- Dysuria, urethral pain
In pooled series, frequency (63%), urgency (55%), incomplete emptying (36%), poor flow (32%) and urinary incontinence (31%) were most common; urethral pain, terminal dribble and haematuria were rare.[6]
Diagnostic Challenge. In contrast to men, obstructive voiding symptoms in women are frequently attributed to overactive bladder or functional voiding dysfunction. FUS should be considered in any woman with persistent obstructive voiding symptoms refractory to behavioral and pharmacological management, prior to labeling the condition as idiopathic or functional.
Diagnostic Modalities
| Test | Findings in FUS | Notes |
|---|---|---|
| Uroflowmetry | Reduced Qmax; a plateau-shaped curve may be seen | Screens for impaired flow.[4][7] |
| Post-void residual (PVR) | Elevated | Confirms incomplete emptying |
| Urethral calibration | Difficulty passing a small catheter (often 14 Fr) raises suspicion | Supportive, not diagnostic; Waterloos and Verla call inability to pass 14 Fr "almost pathognomonic" but no accepted threshold exists.[4] Distinguish fixed scar from pain, guarding, functional obstruction or difficult access; do not force calibration |
| Cystourethroscopy | Direct visualization of narrowing, epithelial pallor, scarring | Confirms luminal narrowing; does not reliably assess stricture length[6] |
| Voiding Cystourethrography (VCUG) | Proximal urethral dilation tapering to distal narrowing ("wine glass" appearance) may occur with stricture or pelvic-floor hypertonicity | Helps define the site and extent of narrowing for operative planning when a fixed stricture is confirmed by examination and cystourethroscopy.[4][6][7] |
| Video-urodynamics | Combines pressure-flow study with real-time fluoroscopy | Best for complex cases, especially when neurogenic or functional component suspected |
| Pelvic MRI | Evaluates periurethral fibrosis, urethral diverticulum, pelvic anatomy | Indicated for complex anatomy, recurrent strictures, suspected diverticulum |
| Urodynamics | Pressure-flow testing helps distinguish bladder outlet obstruction from detrusor underactivity, which may coexist.[7] | Consider when symptoms exceed anatomical findings or treatment response is unexpected; suspected neurologic disease requires history and examination, with further evaluation as indicated.[7] |
A pelvic examination assesses the meatus, prolapse, masses, scarring, vulval dermatoses and the quality of tissue available for reconstruction.[4][6] The EAU strongly recommends urinalysis in the initial assessment of female LUTS and reassessment after treatment when UTI is present; urine culture is obtained when needed.[18] The EAU strongly recommends uroflowmetry, PVR and VCUG or video-urodynamics in all women with refractory LUTS.[6] VCUG, VUDS and urodynamics need a 6 Fr catheter, and cystoscopy often needs prior dilation to pass, even with a paediatric ureteroscope. Cystoscopy defines the distal end of the stricture and helps exclude functional obstruction.[6] The AUA lists urethrocystoscopy, retrograde urethrography, VCUG or ultrasound urethrography for diagnosis; VCUG demonstrates the whole female urethra.[8]
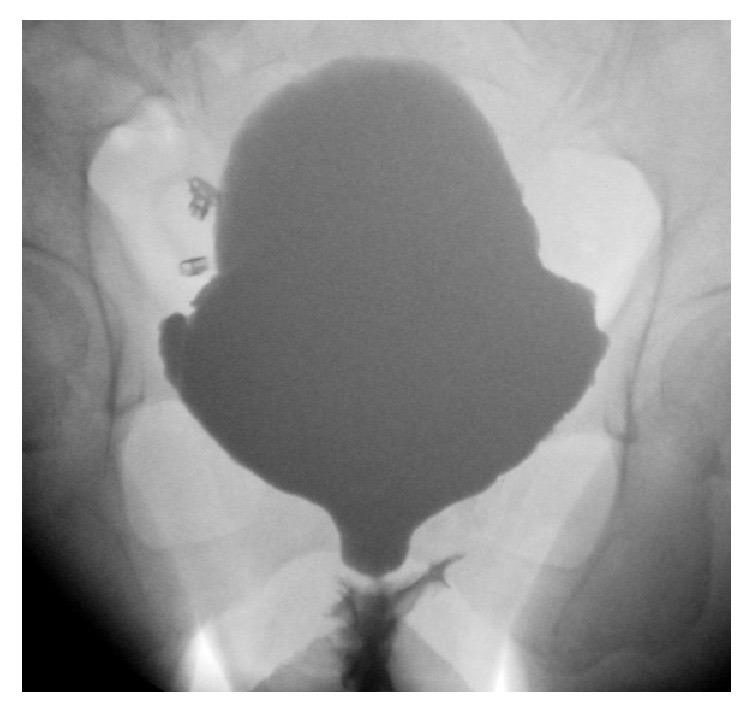
"Wine glass" appearance on voiding cystourethrography: a distal female urethral stricture with prestenotic dilation of the proximal urethra. From Waterloos M, Verla W. Biomed Res Int. 2019;2019:6715257, Figure 2 (CC BY).[4]
Gel-infused translabial ultrasound distends the urethra with 20 mL of lidocaine jelly while high-frequency transducers image it from meatus to bladder neck, recording stricture location, length, caliber and periurethral fibrosis.[14] In a series of eight women with suspected stricture, it identified the stricture and periurethral fibrosis in all eight, findings were confirmed at repair in six, and cystoscopy and video-urodynamics were less complete in identifying and assessing the strictures; two healthy volunteers had a patent urethra without fibrosis. Its role in preoperative planning and in equivocal cases remains to be defined.[14] In a later cross-sectional series of 60 women with urodynamic outlet obstruction, ultrasound detected 27 of 40 cystoscopy-confirmed strictures but missed all 13 meatal strictures.[15]
Interpret fluoroscopy with the rest of the study. Proximal urethral ballooning can occur above a fixed stricture, but a spinning-top appearance is not specific and may reflect dysfunctional voiding. Confirm anatomical scar with examination or endoscopy and use pressure-flow findings and EMG when functional obstruction is possible.[6][7]
Cystourethroscopic technique. A scope narrower than a short, flimsy narrowing can pass without making the stricture obvious; signs to look for instead include a parched mucosal appearance, resistance to advancing the scope, and mucosal telescoping. Lubricating jelly is applied only to the instrument tip, and keeping the bladder near full during assessment limits irrigation loss into it and helps avoid mistaking a voluntary squeeze from a full bladder for a fixed stricture. Inspecting the urethra before advancing the cystoscope, and using a compact sheath with forward flow and a 0-degree lens to distend it, has been described; examination under general anesthesia has been recommended when pelvic-floor spasm or anxiety could confound office assessment.[12][13]
Classification
FUS is classified by anatomical location and stricture length:
By Location
| Location | Characteristics |
|---|---|
| Distal / Meatal | Meatal narrowing may be visible on examination; very short isolated meatal strictures may be suitable for meatoplasty, and short distal strictures may be treated with a local flap when tissue is suitable. Waterloos and Verla advise against Heineke–Mikulicz meatoplasty when lichen sclerosus affects the meatus.[4][6] |
| Mid-urethral | Mid or mid-to-distal involvement accounted for 58% of strictures in the EAU-pooled series.[17] |
| Proximal (near bladder neck) | Least common; most complex; associated with pelvic surgery or radiation |
| Multifocal / Panurethral | Multiple levels or extensive urethral involvement; evaluate lichen sclerosus and prior radiation as possible factors without assuming either is the typical cause at this location.[4][8] |
By Length
- Very short (<0.5 cm). Heineke–Mikulicz meatoplasty may suffice for isolated meatal disease.[4]
- Short (<2 cm). Anterior vaginal wall or vestibular flaps may be used for meatal or distal strictures when local tissue is suitable.[4][6]
- Long (>2 cm). Graft augmentation or a lateral vaginal wall flap may be used when local tissue permits.[4][6] Complex cases may need staged repair.
Treatment
Treatment Options
For procedural selection and the full range of repairs, see the Urethral Reconstruction treatment atlas and its female urethroplasty techniques.
Confirm a fixed anatomical stricture before intervention. Discuss the durability and burden of dilation, intermittent self-dilation and urethroplasty. The AUA supports offering urethroplasty because endoscopic durability is limited.[8] The EAU (2026) urethral-stricture guideline weakly recommends initial dilation to 24–41 Fr, then repeat dilation with planned weekly self-dilation (16–18 Fr catheter) for the first recurrence, and strongly recommends urethroplasty for a second recurrence in women who cannot self-dilate or want definitive treatment.[6] The EAU Female LUTS guideline weakly recommends against dilation or urethrotomy for outlet obstruction after synthetic midurethral tape because of a theoretical risk of mesh extrusion.[7] For short isolated meatal disease, the EAU weakly recommends meatoplasty; Waterloos and Verla advise against Heineke–Mikulicz meatoplasty when lichen sclerosus affects the meatus.[6][4] The AUA (2023 amendment) states that urethroplasty should be offered to women with urethral stricture because endoscopic treatment has low efficacy; oral mucosa grafts, vaginal flaps or both may be used .[8]
Observation
Asymptomatic, incidentally discovered urethral narrowing without obstructive symptoms or elevated PVR may be observed. Active surveillance with uroflowmetry and PVR is appropriate.
Urethral Dilation and DVIU
Urethral dilation remains the most commonly performed first-line treatment despite limited long-term efficacy.[4]
- Waterloos and Verla's narrative review reports a composite success rate of about 47% (58% without prior dilation, 27% after prior dilation)[4]
- EAU pooled series: mean stricture-free rate 40.1% (range 7.5–51%) at 12–59 months after dilation alone; new-onset stress incontinence about 1.4%[6]
- Dilation followed by intermittent self-dilation or planned repeat dilation kept 97% patent (range 57–100%) at 6–21 months in small series (109 women), but this is palliation: the urethra is patent because instrumentation continues[6]
- Isolated repeat dilation yielded 26.6% reported patency in the EAU synthesis and is unlikely to be curative.[6]
- Prior urethral dilation is among reported iatrogenic causes of FUS.[17]
After recurrence. Repeated dilation alone has poor durability. Planned dilation or self-dilation may maintain patency. Allow about 3 months after the last dilation or urethrotomy before urethroplasty.[4] The EAU urethral-stricture guideline found no FUS-specific urethrotomy outcome study, and the AUA recommends offering urethroplasty to women with FUS because endoscopic efficacy is low.[6][8] The EAU Female LUTS guideline weakly recommends internal urethrotomy with postoperative self-dilation for women with stricture-related BOO, with counseling about limited long-term improvement and postoperative incontinence.[7]
Drug-Coated Balloon (Optilume DCB)
Female use remains off-label in the United States: FDA approval covers adult men with anterior urethral strictures no longer than 3 cm.[9] The device labeling contraindicates Optilume in patients with paclitaxel hypersensitivity or urologic implants, including an artificial urinary sphincter, and warns against use during an active UTI until infection resolves.[9] A 2025 single-center report treated 14 patients and analyzed 12 after exclusions; 11/12 avoided recurrence or repeat intervention at a mean 12 months.[5] No new incontinence was observed.[5] The series was uncontrolled.[5]
Urethroplasty
Urethroplasty offers a durable reconstructive option for FUS. Discuss it early for recurrent or complex disease and for patients who prefer definitive repair over ongoing dilation. Counseling must include recurrence, fistula, altered stream, donor-site morbidity and new or unmasked urinary incontinence.[1][2][8]
Choosing a Reconstruction
Technique selection depends on stricture location and extent, the quality of the urethra and surrounding tissues, previous surgery and surgeon experience. Oral mucosa and healthy vaginal flaps are established options; diseased or scarred donor tissue needs a different plan.[3][6][8]
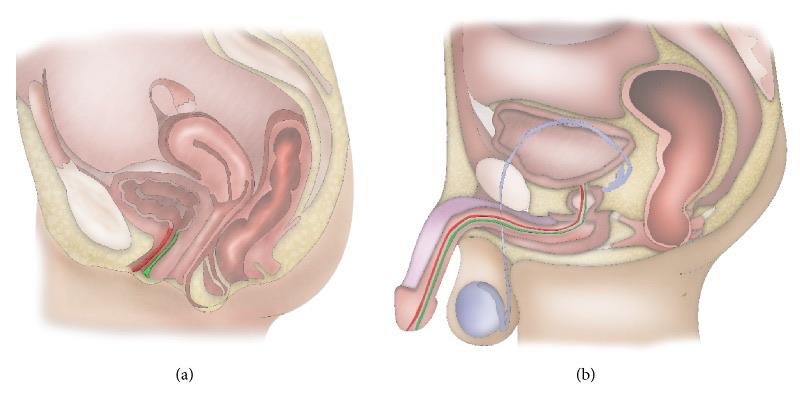
Female versus male urethral anatomy in sagittal section. (a) Female urethra; (b) male urethra. Green marks the ventral urethra and red the dorsal urethra. From Waterloos M, Verla W. Biomed Res Int. 2019;2019:6715257, Figure 1 (CC BY).[4]
A short isolated meatal stenosis may be treated with meatoplasty. Longer disease generally needs augmentation with a flap or graft. Lichen sclerosus, atrophy, radiation, prior fistula and future continence surgery materially affect tissue selection; avoid a rigid length-only algorithm.[1][4]
For graft placement, Martius interposition, catheter duration and operative details, use the female urethroplasty techniques.
Outcomes and Follow-Up
The EAU pooled 29 series (917 women) by tissue type. The reported follow-up spans about 6–81 months, most series are retrospective, and "patency" definitions differ.[6]
| Technique | Women | Patency (range) | New-onset incontinence |
|---|---|---|---|
| Dorsal vaginal graft | 75 | 85.3% (73–94%) | 0% |
| Ventral vaginal flap | 161 | 81.4% (67–100%) | 9.3% |
| Ventral labial/vestibular graft | 30 | 93% (75–95%) | 26.7% (urgency incontinence; resolved within 6 months) |
| Dorsal labial/vestibular graft | 27 | 100% | 3.7% |
| Labial/vestibular flap | 29 | 93% (88–100%) | 0% |
| Dorsal onlay oral mucosal graft | 319 | 83% (69–95%) | 2.2% |
| Ventral oral mucosal graft (177 onlay, 70 inlay) | 247 | 90.7% (86–98%) | 3.2% |
Vaginal flap complications included intravaginal direction of the urinary stream and urinary infection. Two small randomized trials compared buccal mucosal graft placement.[6] The 2021 12-per-arm trial compared ventral and dorsal onlay, reported one recurrence in each arm, and found improved flow, post-void residual and symptoms in both groups. The 2025 trial compared ventral inlay with dorsal onlay in 20 analyzed women per arm and found one failure per arm at one year (median follow-up 21 months).[16] Two meta-analyses address different comparisons: dorsal versus ventral oral mucosa (25 studies, mostly level 4) showed no significant difference in success in the four comparative cohorts (OR 0.84, 95% CI 0.30–2.36),[10] while buccal versus vaginal graft (18 studies) showed similar reported success (86.2% versus 89.8%), Qmax and PVR; the review defined success as Qmax >15 mL/s at three months, PVR <30 mL and improvement in AUA symptom score.[11] Choose the technique by tissue quality, stricture site, lichen sclerosus or atrophy, and surgeon experience.
Interpret reported patency with its definition, denominator and follow-up.[2][3] A urethra kept open by repeated instrumentation is different from a repair that remains open without further treatment.
Track symptoms, uroflow and PVR, and investigate recurrent obstruction or new incontinence. In a multicentre cohort of 165 women (median follow-up 29 months), prior radiotherapy was independently associated with recurrence after urethroplasty (P = 0.015).[19] Surveillance should reflect the operation, prior recurrence and tissue disease. Discuss anatomical patency and patient-reported urinary and sexual outcomes separately.
Standardization gap. Turchi and colleagues’ 2025 review of 22 studies describes variable outcome definitions that limit comparisons and supports more consistent patient-reported follow-up.[2]
See Also
- Urethral Reconstruction treatment atlas
- Female Urethroplasty
- Female Dorsal Onlay Urethroplasty
- Female DVIU & Dilation
Videos
References
1. Chakraborty JN, Enganti B, Nayak P. "Female Urethroplasty: A Critical Review of Indications, Techniques and Concerns." Int Urogynecol J. 2026;37(4):823-833. [PMID: 41204975]. doi:10.1007/s00192-025-06415-4
2. Turchi B, Lumen N, Verla W, Waterloos M. "Female urethral stricture disease: a narrative review on diagnosis, surgical techniques and outcomes." Int J Impot Res. 2026;38(4):286-295. [PMID: 40348941]. doi:10.1038/s41443-025-01079-6
3. West C, Lawrence A. "Female urethroplasty: contemporary thinking." World J Urol. 2019;37(4):619–629. [PMID: 30456711]. doi:10.1007/s00345-018-2564-4
4. Waterloos M, Verla W. "Female Urethroplasty: A Practical Guide Emphasizing Diagnosis and Surgical Treatment of Female Urethral Stricture Disease." Biomed Res Int. 2019;2019:6715257. [PMID: 30906779]. doi:10.1155/2019/6715257
5. Jelisejevas LA, Tulchiner G, Kink P, Rehder P. "Does Optilume drug-coated balloon dilation compromise female sphincter function?" Int Urol Nephrol. 2025. [PMID: 40244519]. doi:10.1007/s11255-025-04513-2
6. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Females. 2026. Guideline.
7. European Association of Urology. EAU Guidelines on Non-neurogenic Female LUTS: Disease Management. 2026. Functional and anatomical bladder outlet obstruction. Guideline.
8. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. "Urethral Stricture Disease Guideline Amendment (2023)." J Urol. 2023;210(1):64–71. doi:10.1097/JU.0000000000003482.
9. US Food and Drug Administration. Optilume Urethral Drug Coated Balloon: PMA P210020. Approved indication and labeling. FDA record.
10. Ortac M, Ozervarli MF, Ergul RB, et al. "Comparing ventral and dorsal oral mucosal graft urethroplasty in female urethral stricture: a systematic review and meta-analysis." World J Urol. 2025;43(1):397. [PMID: 40569457]. doi:10.1007/s00345-025-05773-4
11. Kumar L, Thakur A, Agarwal S, et al. "Buccal versus Vaginal Graft Urethroplasty in Female Urethral Stricture: A Systematic Review and Meta-Analysis." Int Urogynecol J. 2025;36(11):2121-2132. [PMID: 40504250]. doi:10.1007/s00192-025-06171-5
12. Khattar N. Female Bladder Outlet Obstruction: Whom to Work Up and What to Look for? In: Khattar N, Nayyar R, Panda A, eds. Female Bladder Outlet Obstruction and Urethral Reconstruction. Springer; 2021:9-22. doi:10.1007/978-981-15-8521-0_2
13. Nayyar R, Bansal D, Nayyar BU. Female Urethral Stricture. In: Khattar N, Nayyar R, Panda A, eds. Female Bladder Outlet Obstruction and Urethral Reconstruction. Springer; 2021:87-98. doi:10.1007/978-981-15-8521-0_8
14. Sussman RD, Kozirovsky M, Telegrafi S, Peyronnet B, Palmerola R, Smilen S, et al. "Gel-Infused Translabial Ultrasound in the Evaluation of Female Urethral Stricture." Female Pelvic Med Reconstr Surg. 2020;26(12):737-741. doi:10.1097/SPV.0000000000000699
15. Mahmoudnejad N, Abrishami A, Sharifiaghdas F, et al. "The role of gel-infused translabial ultrasound as a new modality in evaluation of female urethral stricture." Cent European J Urol. 2024;77(1):152-156. doi:10.5173/ceju.2024.168
16. Mandal S, Gaur AS, Singh K, et al. "Comparative Efficacy of Dorsal-Onlay and Ventral-1 Inlay Buccal Mucosal Graft Urethroplasty in Female Urethral Stricture: A Randomized Clinical Trial." Urology. 2025;200:52-58. doi:10.1016/j.urology.2025.01.064
17. European Association of Urology. EAU Guidelines on Urethral Strictures: Definition, Epidemiology, Aetiology and Prevention. 2026. Guideline.
18. European Association of Urology. EAU Guidelines on Non-neurogenic Female LUTS: Diagnosis. 2026. Guideline.
19. Waterloos M, Lumen N, Ockrim JL, et al. "Diagnostics, reconstructive approaches, and outcomes in female urethroplasty patients." BJU Int. 2025;135(6):1025-1030. doi:10.1111/bju.16701