Primary Bladder Neck Obstruction
Primary bladder neck obstruction (PBNO) is inadequate opening of the bladder neck during voiding in the absence of an identifiable neurologic, anatomic, or iatrogenic cause. The obstruction is functional but mechanically real: the detrusor contracts against a closed or poorly funneling bladder neck, producing low flow, elevated voiding pressure, incomplete emptying, and sometimes upper-tract risk.[1][2][3]
The diagnosis requires localization of obstruction to the bladder neck.
When medication fails and definitive outlet treatment is chosen, see TUIP — Transurethral Incision of the Prostate, an AUA-listed procedural option for suspected PBNO[24], within the BPH & Male LUTS treatment atlas.
Definition and Terminology
PBNO describes failure of bladder-neck opening during voiding without a secondary cause. Related terms include:
| Term | Use |
|---|---|
| Primary bladder neck obstruction (PBNO) | Adult term; emphasizes outlet obstruction localized to the bladder neck |
| Primary bladder neck dysfunction (PBND) | Common pediatric term; often diagnosed by delayed pelvic-floor EMG lag time and urodynamic / fluoroscopic findings |
| Marion's disease | Historical eponym for congenital or primary obstruction at the bladder neck |
| Functional bladder neck obstruction | Descriptive phrase emphasizing non-neurogenic, non-stricture obstruction |
Urodynamic definition. The core finding is high detrusor pressure with low flow while the bladder neck stays closed or fails to funnel on fluoroscopy, with a relaxed external sphincter and no anatomic or neurologic cause. There is no single universal threshold, so published series define it differently:
| Setting | Criteria used |
|---|---|
| Men (Suri 2005) | Qmax <10 mL/s, poor bladder-neck funneling, opening pressure >40 cmH2O with a relaxed external sphincter, PVR >100 mL, normal urethral caliber[9] |
| Men (Sureka 2023) | BOOI >40 with videourodynamic obstruction at the bladder neck[15] |
| Women (Nitti 1999; all-cause BOO cohort) | Radiographic obstruction between bladder neck and distal urethra during a sustained detrusor contraction; strict pressure-flow cutoffs were not used. Of 76 obstructed women, 12 had PBNO. Mean Qmax 9 versus 20.2 mL/s and Pdet at Qmax 42.8 versus 22.1 cmH2O compare all obstructed with unobstructed women.[10] |
| Women (EAU 2026) | Pressure-flow studies show low flow with high detrusor pressure, but no female cutoff is validated (Blaivas-Groutz and Solomon-Greenwell nomograms are the commonly used); videourodynamics is the standard test[23] |
PBNO must be separated from dysfunctional voiding. In PBNO, the smooth-muscle bladder neck or internal sphincter fails to open while the striated sphincter and pelvic floor are typically quiet. In dysfunctional voiding, the external urethral sphincter or pelvic floor contracts during voiding in a neurologically normal patient.[4][5] EMG alone separates them imperfectly: in one female series it misclassified about 21% of dysfunctional voiding and 14% of PBNO.[4][5]
Epidemiology
Prevalence is uncertain because PBNO is underdiagnosed and because many series include only patients selected for videourodynamics.[2][7]
In men, PBNO primarily affects young and middle-aged patients (AUA 2026 cites estimates of 28-54% among men aged 18-50 with LUTS who undergo urodynamic evaluation).[24] In Nitti's prospective videourodynamic study of 85 men aged 18-45, PBNO was the most common diagnosis (47%).[3][24] In a single-center retrospective cohort of 1,229 men with voiding or mixed LUTS, excluding prior prostate surgery or urethral stricture, Schifano and colleagues found a clinical profile consistent with possible PBNO in 136 (11%); these patients were younger, had smaller prostates, lower PSA, fewer comorbidities, and more severe symptoms than men with LUTS from other causes.[8] Classic videourodynamic series similarly frame PBNO as an important cause of obstructive symptoms in younger men.[1][9]
In women, PBNO is much less common and likely underrecognized. In Nitti's series, PBNO accounted for 12 of 76 obstructed women (16%)[10]; EAU 2026 estimates that 4.6-16% of women with voiding symptoms have PBNO.[23] Modern reviews emphasize that female bladder outlet obstruction lacks a universally accepted definition or diagnostic threshold.[7][10][23] In a 50-woman videourodynamic series, the 16 women with PBNO had a mean age of 59.2 years.[4] A separate six-woman series selected for severe urinary tract damage had a median age of 56.5 years; women with PBNO may present with poor emptying, large residuals, or recurrent UTI.[21]
In children and adolescents, PBND is reported more often in boys and is commonly evaluated among children with refractory LUTS, urinary incontinence, VUR, or recurrent UTI.[5][11][12]
Pathophysiology
The exact mechanism is incompletely understood. Proposed mechanisms include:
- High-tone bladder-neck smooth muscle mediated through alpha-adrenergic tone
- Smooth-muscle hypertrophy or hypertrophy of the posterior bladder-neck lip
- Increased collagen deposition or fibrotic stiffness at the bladder neck
- Asymmetric bladder-neck configuration or focal anatomic variants such as cystic change
- Histologic heterogeneity, including reports of skeletal muscle fibers within bladder-neck tissue in men historically labeled as Marion's disease[2][6][14]
Some patients respond well to alpha-blockers, suggesting dynamic smooth-muscle tone. Others have severe obstruction despite medication, suggesting fixed morphology, mixed tissue composition, or non-adrenergic contributors.[2][13][15]
Postural and pelvic-floor biomechanical hypotheses have also been proposed in young men and remain investigational.[13][16]
Clinical Presentation
PBNO presents as mixed lower urinary tract symptoms, usually with a voiding-predominant pattern.
Adults
Common symptoms include:
- Hesitancy
- Weak or intermittent stream
- Straining to void
- Prolonged voiding time
- Incomplete emptying
- Frequency and urgency
- Nocturia
- Recurrent UTI or retention in more severe cases[1][8][9]
Women with PBNO may have mixed LUTS, retention, recurrent UTI or renal impairment. In a selected 50-woman videourodynamic series, storage symptoms trended more often with dysfunctional voiding than PBNO, while PBNO had greater mean PVR (400 versus 125 mL).[4][21][23]
In men, the clinical clue is discordance: a younger patient with severe voiding symptoms, low flow, elevated PVR, and a small prostate.[8]
Children
Pediatric PBND may present with hesitancy, weak stream, frequency, urgency, daytime incontinence, nocturnal enuresis, recurrent UTI, or VUR.[5][11][12]
Diagnosis
Initial Assessment
Initial evaluation should include:
- Detailed voiding history and symptom score when age-appropriate
- Medication and prior instrumentation history
- Focused neurologic examination
- Physical examination, including DRE in men when relevant
- Urinalysis and culture when infection is possible
- Uroflowmetry
- Post-void residual measurement
- Prostate volume assessment in men with possible BPH
- Cystoscopy or urethral imaging when stricture or anatomic narrowing is possible
PBNO is suspected when low flow and obstructive symptoms are disproportionate to prostate size, urethral anatomy, neurologic findings, or pelvic organ prolapse.
Video-Urodynamics
Video-urodynamics is the diagnostic test of choice. It localizes obstruction to the bladder neck during voiding and distinguishes PBNO from dysfunctional voiding, urethral stricture, detrusor underactivity, and neurogenic DSD.[1][3][7][10]
Typical diagnostic features include:
- Poor or absent bladder-neck funneling during voiding
- Elevated detrusor pressure at maximum flow
- Low maximum flow rate
- Elevated post-void residual
- Quiet pelvic-floor EMG during voiding
- No urethral stricture, obstructing prostate, prolapse obstruction, or neurologic cause
EAU 2026 makes a weak recommendation to perform videourodynamics, or standard urodynamics with voiding cystourethrography where videourodynamics is unavailable, with or without EMG, in young men with suspected PBNO or dysfunctional voiding.[25] It notes that no urodynamic threshold parameters are commonly accepted, that a Qmax below 15 mL/s and an elevated PVR are frequent but not specific (mean Qmax 12.0, 11.8 and 9.8 mL/s in PBNO, dysfunctional voiding and BPO in one trial), and that increased surface EMG activity alone should not exclude PBNO because surface EMG reflects pelvic floor rather than sphincter activity.[25] Recent male data emphasize that voiding cystourethrography helps grade PBNO severity: complete absence of bladder-neck opening is associated with higher voiding pressures, higher BOOI, and stronger contractility than incomplete opening.[18]
Non-Invasive Pediatric Screening
In children, pelvic-floor EMG lag time is a useful non-invasive marker. EMG lag time measures the interval between pelvic-floor relaxation and flow initiation. A prolonged lag time suggests delayed bladder-neck opening and supports PBND, while active EMG during flow suggests dysfunctional voiding.[5][12]
Additional Imaging
MRI and MR voiding cystourethrography have been explored for male PBNO and may identify posterior lip hypertrophy, lateral asymmetry, bladder-neck cysts, or a normal-appearing bladder neck.[14]
Differential Diagnosis
| Diagnosis | Key distinction |
|---|---|
| BPH / benign prostatic obstruction | Older age, enlarged prostate, transition-zone obstruction |
| Dysfunctional voiding | Active pelvic-floor / external-sphincter EMG during voiding |
| Detrusor underactivity | Low-pressure low-flow emptying rather than high-pressure outlet obstruction |
| Urethral stricture | Anatomic narrowing on cystoscopy, calibration, RUG/VCUG, or VUDS |
| Bladder neck contracture / VUAS | Iatrogenic scar after prostate/outlet surgery or radical prostatectomy |
| Female prolapse-related obstruction | Obstruction improves with prolapse reduction |
| Fowler's syndrome | Young women with retention, high urethral closure pressure, characteristic sphincter EMG |
| Neurogenic DSD | Neurologic disease with involuntary sphincter contraction during detrusor contraction |
In women, PBNO must be considered within the broader female bladder outlet obstruction differential: dysfunctional voiding, DSD, Fowler's syndrome, prolapse, prior anti-incontinence surgery, urethral stricture, urethral diverticulum, and periurethral cyst or abscess.[7]
Management
Alpha-Blockers
For symptomatic PBNO in men aged 18–50 years, alpha-adrenergic blockers are the first-line approach.[22] They reduce bladder-neck smooth-muscle tone and may improve flow, residual urine, and symptoms. The evidence is observational; there are no placebo-controlled trials. A 2025 meta-analysis of young men (Creta) found pooled improvements at 3 months of about 7 IPSS points and 4 mL/s Qmax, with ejaculatory dysfunction in 47-50% and treatment failure in 23-52%.[2][15][17][22] In women, EAU 2026 weakly recommends uroselective alpha-blockers off label for functional bladder outlet obstruction.[23] A 2025 systematic review of female PBNO studies estimated alpha-blocker success at approximately 50%, with heterogeneous diagnostic and treatment-success definitions.[40]
Common options include:
| Agent | Typical adult dosing |
|---|---|
| Tamsulosin | 0.4 mg daily[35] |
| Alfuzosin | 10 mg extended-release once daily with food after the same meal; contraindicated in Child-Pugh B/C hepatic impairment or with potent CYP3A4 inhibitors; counsel about postural hypotension/syncope.[36] |
| Doxazosin | Start 1 mg at bedtime; increase to 2 mg after 1–2 weeks if needed, with blood-pressure monitoring for at least 6 hours after the first dose and each increase.[17][38] |
Young men with PBNO have variable durability on medication. Yang and colleagues reported improvement in symptom score and Qmax with alpha-blockers, while Trockman found that only 30% of men who started an alpha-blocker were still taking it long term, mostly for inadequate benefit (AUA 2026 cites 24-30% continuation at 1 year).[1][17][24] Benefit was greater in men with higher-grade obstruction in Yang's series.[15][17] In a separate 99-man cohort, younger age, higher detrusor pressure at Qmax, and BOOI >60 were associated with alpha-blocker failure; this conflicts with Yang's high-grade subgroup result.[15][17]
In an uncontrolled 15-woman pilot of functional bladder outlet obstruction, terazosin (1 mg daily, titrated to 5 mg over 2 weeks) was associated with symptomatic and urodynamic improvement in 10 (67%) at 3–4 weeks, including higher Qmax and lower post-void residual; functional urethral length and cystometric capacity did not change.[26] In an 8-week placebo-controlled trial of women classified as obstructed by the Blaivas–Groutz pressure-flow nomogram, alfuzosin (n = 58) did not show significantly different IPSS, Qmax, or PVR changes from placebo (n = 59).[23][39]
In children and adolescents, alpha-blockers can improve symptoms, flow, and EMG lag time, but treatment may be prolonged and recurrence can occur when medication is stopped.[11][12][19]
OnabotulinumtoxinA
Injection of onabotulinumtoxinA is experimental second-line therapy in men with PBNO. Pooled 2-month improvements were about 14 IPSS points and 9 mL/s Qmax with no ejaculatory dysfunction, but the gains fade over time and the data are limited to small series.[22] In women, EAU 2026 summarizes small female functional-obstruction series of periurethral or intrasphincteric botulinum toxin; one reported a mean symptom-free interval of 16.8 weeks, UTI or transient catheter need occurred, no SUI was reported, and three nonresponders in a ten-woman series proceeded to bladder-neck incision.[23] In a 2026 uncontrolled pilot of 22 women given bladder-neck onabotulinumtoxinA, median Female GUPI fell from 34.5 to 26 and median PVR from 126 to 28 mL at 4–6 weeks.[30] Sixteen also received injections at other sites and postoperative Qmax was not collected.[30]
Bladder Neck Incision
Transurethral bladder neck incision (BNI) is an established option after alpha-blocker failure in men with PBNO.[9] In a small series of women with severe PBNO and retention or upper-tract damage, BNI followed drainage and evaluation; patients may also choose a procedure after counseling about alternatives.[21][24] AUA 2026 states that clinicians may offer TUIP, transurethral resection of the bladder neck (TURBN), or TIPD (an athermal pressure implant with struts at 5, 7 and 12 o'clock) for suspected PBNO ; it notes limited long-term data for these procedures in PBNO.[1][9][24] Technique varies: unilateral 12 o'clock or bilateral incisions (for example 5 and 7 o'clock), made with a Collins knife, cold knife or laser, with or without limited resection.
In men, endoscopic incision can produce durable improvement in symptom scores, Qmax, PVR, and voiding pressure. In Suri's 45-man series (mean age 33), 18 underwent BNI after initial management; in these 18, symptom score fell from 26.9 to 3.6 and Qmax rose from 8.5 to 19.6 mL/s, with benefit persisting in more than 80% at a mean 96 months and two men requiring repeat incision.[9] Trockman reported a mean 87% self-rated improvement.[1][9] A 2025 meta-analysis pooled a mean IPSS improvement of 11.2 points and Qmax gain of 6.9 mL/s at three months after surgery, with failure reported in 11.1%–13.3% across surgical series.[22] Across heterogeneous series, reported ejaculatory dysfunction ranged from 0% to 88.8%, with a pooled estimate of 3% after BNI.[25] Single- and bilateral-incision subgroups pooled to 0% and 9%, respectively, without a statistically significant difference (p = 0.128).[22][25] Counseling must still include retrograde ejaculation and the possibility of recurrent obstruction; bladder-neck contracture is the other concern when tissue is resected.
In women, bladder-neck incision or resection can be effective after videourodynamic localization of PBNO, but continence and fistula risks require separate counseling. EAU 2026 weakly recommends offering bladder-neck incision for female PBNO and strongly recommends counseling about postoperative SUI, vesicovaginal fistula, and urethral stricture.[23] Blaivas reported cure or improvement in all 7 women after transurethral resection (one with mild SUI), and Freitas reported no complications in 6 women with severe damage after incision at 4-5 and 7-8 o'clock.[20][21] EAU 2026 summarizes success of 76–100% in noncomparative series and postoperative SUI of 3–33%.[23] In an 84-woman BNI series, 71/84 (84.5%) achieved recovery without serious complications over mean 27.4-month follow-up (range 6–78); vesicovaginal fistula occurred in 3/84 (3.6%), SUI in 4/84 (4.7%), and urethral stricture in 3/84 (3.6%).[37] Fistula and SUI occurred only in women incised at 5 and 7 o'clock, not those incised at 2 and 10 o'clock. These risks make precise diagnosis and conservative incision planning important.[23] A 2026 systematic review of 16 studies (612 women undergoing incision or resection) reported de novo SUI in 8.7% and vesicovaginal fistula in 2.3%.[31] Female BNI techniques vary in incision position and depth; EAU 2026 found no direct comparison establishing an optimal approach.[23] Sinha, Singla and Krishnamoorthy recommend 2 and 10 o'clock incisions limited to the proximal third of the urethra and carried through bladder-neck muscle to fat, with uroflowmetry every 3 months and long-term follow-up for recurrence.[27] In a noncomparative 20-woman series, Bhatia and colleagues divided circular fibers at 5 and 7 o'clock without entering fat.[29]
Refractory or High-Risk Presentations
Severe retention, hydronephrosis, renal insufficiency, recurrent febrile UTI, or bladder decompensation warrants evaluation of renal function and the outlet. In a six-woman PBNO series, those with hydronephrosis or renal impairment first received Foley drainage, followed by laboratory, imaging, and video-urodynamic evaluation after 3–4 weeks.[21] Severe female PBNO has been reported with bladder wall thickening, diverticula, bilateral hydronephrosis, and renal impairment; renal function may improve after relief of obstruction when treated before irreversible damage.[21] In a retrospective 26-woman BNI series, 23 were cured or improved, but only 56% of preoperative catheter users became catheter-independent; cure was 62.5% among catheter users versus 90% among nonusers.[32]
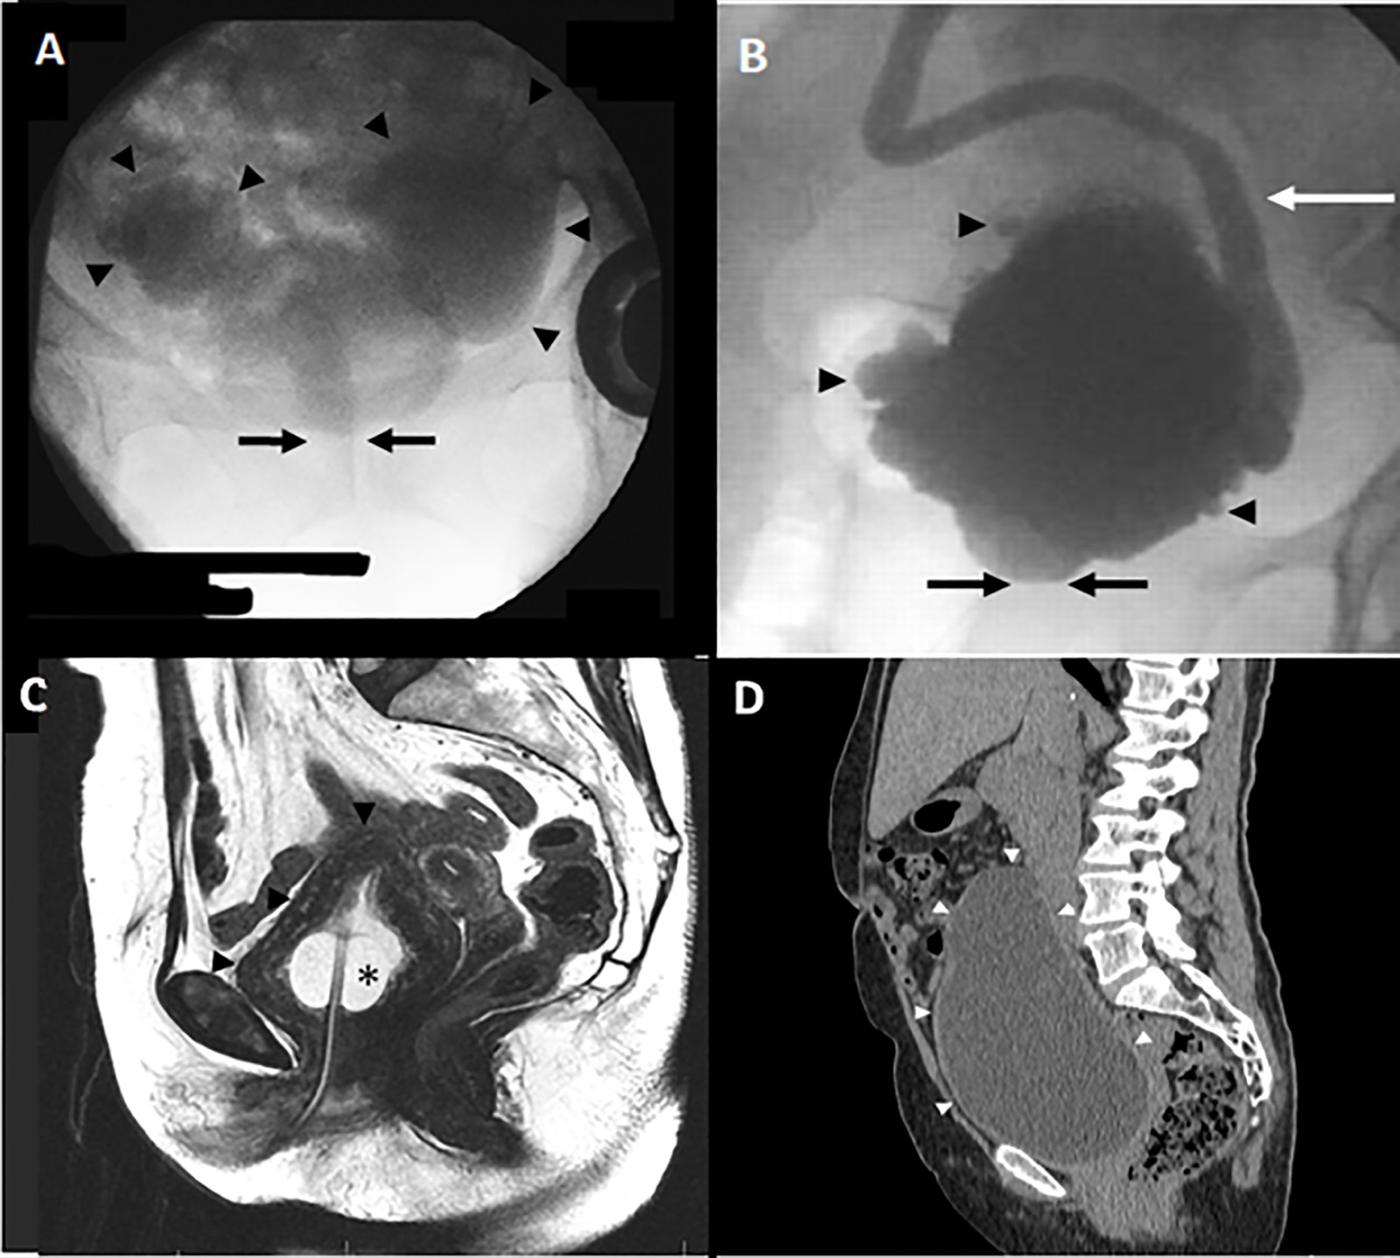
Bladder damage from primary bladder neck obstruction in women. (A) Voiding cystourethrogram with two large diverticula (arrowheads) and a narrow, nonfunneling bladder neck (arrows). (B) Voiding cystourethrogram with multiple diverticula (arrowheads), high-grade left vesicoureteral reflux (white arrow) and a nonfunneling bladder neck (black arrows). (C) Sagittal T2-weighted pelvic MRI with severe bladder wall thickening (arrowheads) around a Foley catheter (asterisk). (D) Sagittal noncontrast CT with massive bladder distention (arrowheads) in acute urinary retention. From Freitas PFS, et al. PLoS One. 2021;16(3):e0248938, Fig 1 (CC BY 4.0).
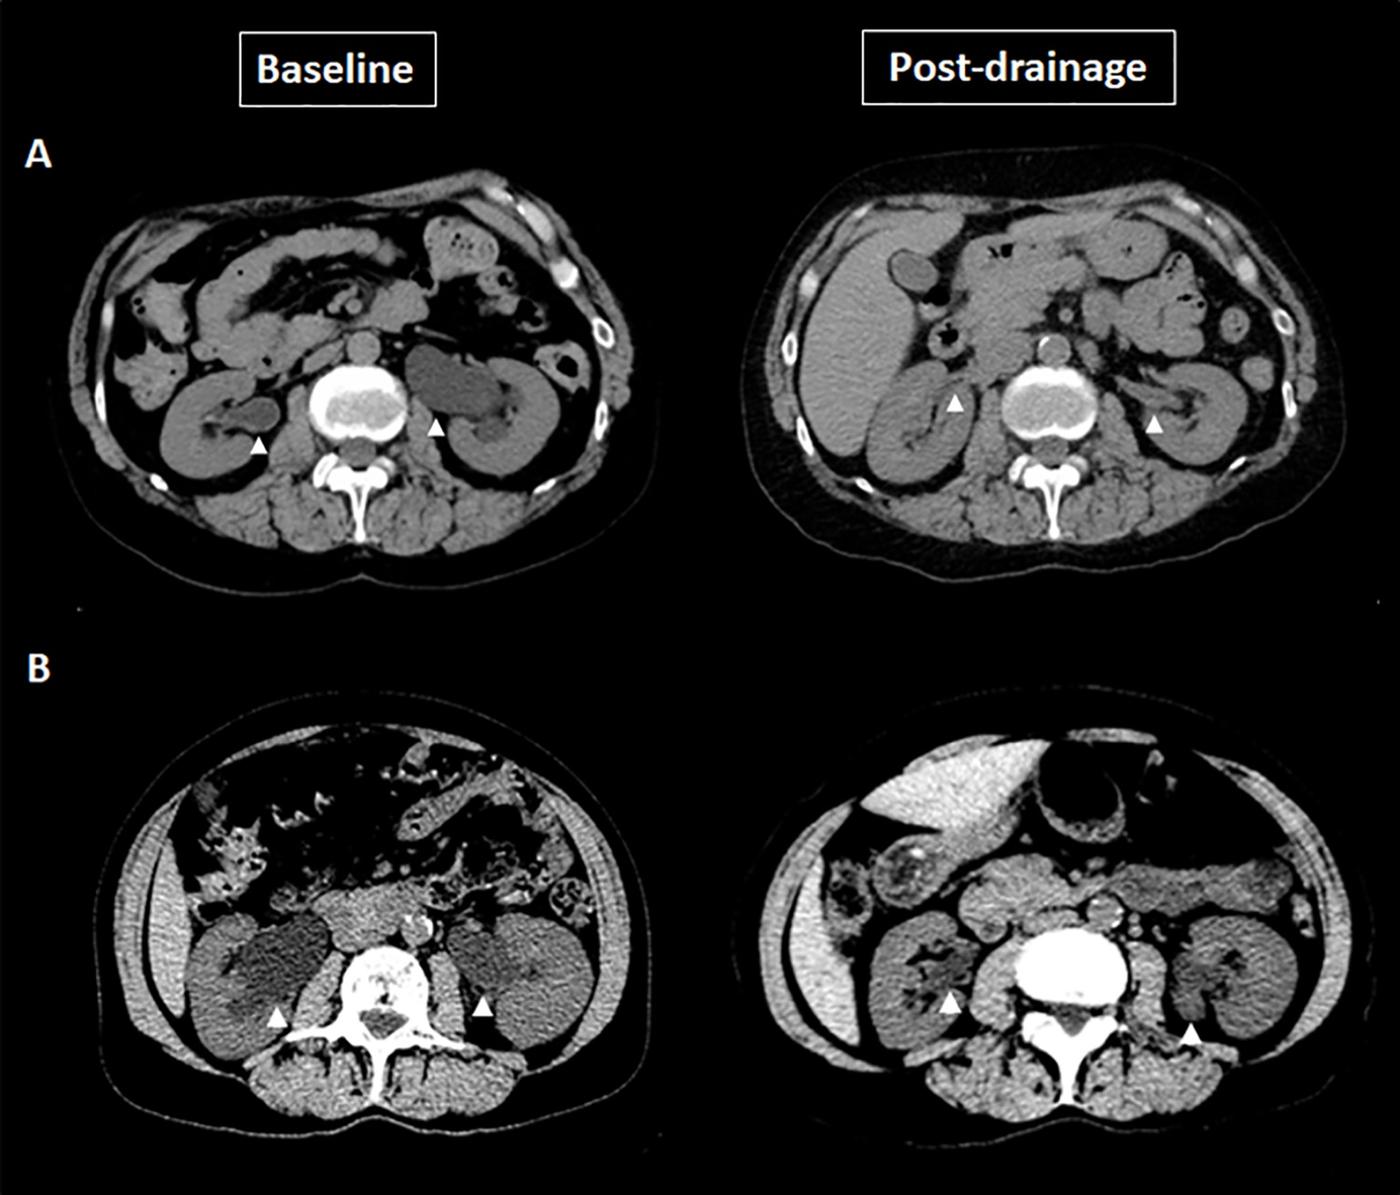
Upper-tract deterioration from primary bladder neck obstruction in two women, baseline (left) and after drainage (right). (A) Bilateral hydronephrosis (arrowheads) with preserved renal parenchyma, resolved after three weeks of Foley catheter drainage; creatinine fell from 1.60 to 0.65 mg/dL. (B) Bilateral hydronephrosis (arrowheads) with preserved parenchyma, resolved after three weeks of Foley drainage; creatinine decreased after drainage. From Freitas PFS, et al. PLoS One. 2021;16(3):e0248938, Fig 2 (CC BY).[21]
EAU 2026 Recommendations in Young Men
EAU 2026 rates the evidence on PBNO and dysfunctional voiding in young men at level 3 to 4 and makes only weak recommendations.[25]
- Suspect PBNO or dysfunctional voiding in young men with long-lasting LUTS. EAU cites a mean symptom duration of up to 53.8 months in men with PBNO or dysfunctional voiding before diagnosis, chronic pelvic pain in up to 24.5% of men with PBNO and recurrent UTI in 28%.[25]
- EAU 2026 weakly recommends considering an alpha blocker as first-line treatment for young men with PBNO.[25] EAU cites a pooled 3-month IPSS improvement of 7.0 points, Qmax gain of 4.0 mL/s and PVR reduction of 31.1 mL, discontinuation of 4.7% to 55%, and retrograde ejaculation reported in 47% to 50%.[25]
- Consider bladder neck incision, or intermittent catheterization, in well-informed young men with PBNO who do not respond to alpha blockers. EAU cites a pooled 3-month IPSS improvement of 11.2 points and Qmax gain of 6.9 mL/s across surgical series that included bladder neck incision, TURP and bladder-neck resection, with unsuccessful outcomes in 0% to 15.3%; pooled ejaculatory dysfunction after bladder neck incision was 3.0% (0% after single and 9% after bilateral incision, not significantly different).[25] In a retrospective comparison of 67 men under 40, surgery gave larger IPSS and Qmax gains at 6 months than alpha blockers.[25]
- Observation has been proposed for men with PBNO, minimal bother, and no decompensation; EAU describes nine men who did not respond to alpha blockers and declined surgery, followed for a mean of 36 months.[25] In young men with dysfunctional voiding, EAU weakly recommends considering behavioral modification with biofeedback first and intermittent catheterization if that fails.[25] In the original retrospective series of 43 men unresponsive to alpha blockers, 35 were reported to have decreased symptoms at 6 months.[34] EAU calls bladder neck onabotulinumtoxinA and sacral neuromodulation experimental.
Follow-Up and Prognosis
Follow-up should track:
- Symptom score and bother
- Uroflowmetry
- PVR
- UTIs or retention episodes
- Renal function and renal-bladder ultrasound when baseline upper-tract risk exists
- Medication tolerance and ongoing need
PBNO is often chronic.[25] In Suri’s 18-man BNI subgroup, improvement persisted in more than 80% at a mean 96 months; incision also carries sexual and continence tradeoffs.[9][25] The core management principle is localization: treat the bladder neck only when the bladder neck has actually been proven to be the obstructing segment.
Special Considerations
Children
PBND in children is commonly managed medically first. EMG lag time offers a low-burden way to screen and monitor response, but refractory cases, VUR, recurrent UTI, and upper-tract changes require pediatric urology follow-up and selective invasive evaluation.[5][11][12]
Women
Female PBNO is rare enough that overdiagnosis is dangerous, but underdiagnosis is also real. Videourodynamics is necessary before irreversible bladder-neck incision, especially in women with coexisting pelvic-floor hypertonicity, prior sling surgery, prolapse, or detrusor underactivity.[7][10][21]
Men Seeking Fertility
Bladder-neck incision can affect ejaculation.[28] Men who are trying to conceive should be counseled carefully about retrograde ejaculation risk, alternatives, and sperm banking when appropriate. A 2026 retrospective series of 53 men with videourodynamically confirmed PBNO reported preserved antegrade ejaculation in all 51 with available data at a median 13 months after a single 6 o'clock incision stopped about 10 mm proximal to the verumontanum; the series had no comparison group or fertility outcome.[33]
See Also
- TUIP — Transurethral Incision of the Prostate
- BPH & Male LUTS treatment atlas
- Benign Prostatic Hyperplasia
- Dysfunctional Voiding
- Urodynamics
References
1. Trockman BA, Gerspach J, Dmochowski R, Haab F, Zimmern PE, Leach GE. "Primary bladder neck obstruction: urodynamic findings and treatment results in 36 men." The Journal of Urology. 1996;156(4):1418-1420. doi:10.1016/S0022-5347(01)65605-2
2. Nitti VW. "Primary bladder neck obstruction in men and women." Reviews in Urology. 2005;7 Suppl 8:S12-S17. PubMed
3. Nitti VW, Lefkowitz G, Ficazzola M, Dixon CM. "Lower urinary tract symptoms in young men: videourodynamic findings and correlation with noninvasive measures." The Journal of Urology. 2002;168(1):135-138. PubMed. doi:10.1016/s0022-5347(05)64846-x
4. Brucker BM, Fong E, Shah S, et al. "Urodynamic differences between dysfunctional voiding and primary bladder neck obstruction in women." Urology. 2012;80(1):55-60. doi:10.1016/j.urology.2012.04.011
5. Glassberg KI, Combs AJ, Horowitz M. "Nonneurogenic voiding disorders in children and adolescents: clinical and videourodynamic findings in 4 specific conditions." The Journal of Urology. 2010;184(5):2123-2127. doi:10.1016/j.juro.2010.07.011
6. Billis A, D'Ancona C, Pereira T, Zaidan B, Achermann A. "A novel histologic finding in male patients with bladder outlet obstruction: a possible etiopathogenesis of Marion's disease?" World Journal of Urology. 2021;39(9):3497-3501. doi:10.1007/s00345-021-03596-7
7. Bouchard B, Campeau L. "Bladder outlet obstruction in women: scope of the problem and differential diagnosis." Neurourology and Urodynamics. 2025;44(1):63-68. doi:10.1002/nau.25359
8. Schifano N, Capogrosso P, Matloob R, et al. "Patients presenting with lower urinary tract symptoms who most deserve to be investigated for primary bladder neck obstruction." Scientific Reports. 2021;11:4167. doi:10.1038/s41598-021-83672-5
9. Suri A, Srivastava A, Singh KJ, et al. "Endoscopic incision for functional bladder neck obstruction in men: long-term outcome." Urology. 2005;66(2):323-326. doi:10.1016/j.urology.2005.03.041
10. Nitti VW, Tu LM, Gitlin J. "Diagnosing bladder outlet obstruction in women." The Journal of Urology. 1999;161(5):1535-1540. PubMed. doi:10.1016/s0022-5347(05)68947-1
11. Donohoe JM, Combs AJ, Glassberg KI. "Primary bladder neck dysfunction in children and adolescents II: results of treatment with alpha-adrenergic antagonists." The Journal of Urology. 2005;173(1):212-216. doi:10.1097/01.ju.0000135735.49099.8c
12. Combs AJ, Grafstein N, Horowitz M, Glassberg KI. "Primary bladder neck dysfunction in children and adolescents I: pelvic floor electromyography lag time--a new noninvasive method to screen for and monitor therapeutic response." The Journal of Urology. 2005;173(1):207-211. doi:10.1097/01.ju.0000147269.93699.5a
13. Camerota TC, Zago M, Pisu S, Ciprandi D, Sforza C. "Primary bladder neck obstruction may be determined by postural imbalances." Medical Hypotheses. 2016;97:114-116. doi:10.1016/j.mehy.2016.10.028
14. Di Girolamo M, Mariani S, Barelli GM, et al. "MRI and MR voiding cystourethrography in the evaluation of male primary bladder neck obstruction: preliminary experience." Abdominal Radiology. 2022;47(2):746-756. doi:10.1007/s00261-021-03362-8
15. Sureka SK, Misra A, Baid A, et al. "Clinical and urodynamic predictors for failure of medical management with alpha blockers in PBNO: a retrospective cohort analysis." Urology. 2023;179:101-105. doi:10.1016/j.urology.2023.06.003
16. Zago M, Camerota TC, Pisu S, Ciprandi D, Sforza C. "Gait analysis of young male patients diagnosed with primary bladder neck obstruction." Journal of Electromyography and Kinesiology. 2017;35:69-75. doi:10.1016/j.jelekin.2017.05.005
17. Yang SS, Wang CC, Hsieh CH, Chen YT. "Alpha1-adrenergic blockers in young men with primary bladder neck obstruction." The Journal of Urology. 2002;168(2):571-574. PubMed. doi:10.1016/s0022-5347(05)64682-4
18. El Khoury J, Hermieu N, Chesnel C, et al. "Primary bladder neck obstruction in men: the importance of urodynamic assessment and cystourethrography in measuring its severity." Neurourology and Urodynamics. 2024;43(4):874-882. doi:10.1002/nau.25429
19. Van Batavia JP, Combs AJ, Horowitz M, Glassberg KI. "Primary bladder neck dysfunction in children and adolescents III: results of long-term alpha-blocker therapy." The Journal of Urology. 2010;183(2):724-730. doi:10.1016/j.juro.2009.10.032
20. Blaivas JG, Flisser A, Tash JA. "Treatment of primary bladder neck obstruction in women with transurethral resection of the bladder neck." The Journal of Urology. 2004;171(3):1172-1175. doi:10.1097/01.ju.0000112929.34864.2c
21. Freitas PFS, Coelho AQ, Bruschini H, Rovner ES, Gomes CM. "Severe urinary tract damage secondary to primary bladder neck obstruction in women." PLOS One. 2021;16(3):e0248938. doi:10.1371/journal.pone.0248938
22. Creta M, Baboudjian M, Sakalis V, et al. "Management of primary bladder neck obstruction and dysfunctional voiding in young men: a systematic review and meta-analysis." European Urology Focus. 2025;11(3):496-507. doi:10.1016/j.euf.2025.01.011
23. European Association of Urology. Management of Non-Neurogenic Female Lower Urinary Tract Symptoms (LUTS), limited update March 2026 (sections 4.5.2, 4.5.3, 4.5.4).
24. American Urological Association. Management of Lower Urinary Tract Symptoms Attributed to Benign Prostatic Hyperplasia: AUA Guideline (2026). Special Cases: Primary Bladder Neck Obstruction (statement 56).
25. European Association of Urology. EAU Guidelines on the Management of Non-neurogenic Male LUTS. 2026 (March update). Official full guideline. See section 5.8.
26. Kessler TM, Studer UE, Burkhard FC. "The effect of terazosin on functional bladder outlet obstruction in women: a pilot study." The Journal of Urology. 2006;176(4 Pt 1):1487-1492. doi:10.1016/j.juro.2006.06.009
27. Sinha M, Singla A, Krishnamoorthy V. Primary Bladder Neck Obstruction in Women. In: Khattar N, Nayyar R, Panda A, eds. Female Bladder Outlet Obstruction and Urethral Reconstruction. Springer; 2021:53-59. doi:10.1007/978-981-15-8521-0_5
28. Shindel AW, Althof SE, Carrier S, et al. Disorders of Ejaculation: An AUA/SMSNA Guideline. J Urol. 2022;207(3):504-512. doi:10.1097/JU.0000000000002392 (2020 guideline).
29. Bhatia S, Kurmi N, Vyas S, et al. "Managing Primary Bladder Neck Obstruction in Females: Is Bladder Neck Incision the Best Way Forward?" Cureus. 2025;17(4):e82976. doi:10.7759/cureus.82976
30. Roberts BL, Bibicheff D, De EJB. "Onabotulinum Toxin A Is a Viable Intervention for Bladder Neck Obstruction in Women: A Prospective Pilot Study of Patient Reported Outcomes." Neurourol Urodyn. 2026;45(3):466-471. doi:10.1002/nau.70240
31. Mittal A, Subramanyam ADS, Panwar VK, Rana K. "Surgical Outcomes of Transurethral Bladder Neck Incision and Resection in Female Primary Bladder Neck Obstruction: A Systematic Review." Neurourol Urodyn. 2026;45(3):472-485. doi:10.1002/nau.70257
32. Drain A, Volkin D, Rosenblum N, Brucker BM, Nitti VW. "Outcomes of women diagnosed with primary bladder neck obstruction based on video urodynamic criteria." Neurourol Urodyn. 2025;44(1):44-50. doi:10.1002/nau.25349
33. Sinha S, Lakhani D, Prasad CR. "Ejaculation Sparing Bladder Neck Incision for Young Men With Primary Bladder Neck Obstruction." Int J Urol. 2026;33(5):e70478. doi:10.1111/iju.70478
34. Kaplan SA, Santarosa RP, D’Alisera PM, et al. "Pseudodyssynergia (Contraction of the External Sphincter During Voiding) Misdiagnosed as Chronic Nonbacterial Prostatitis and the Role of Biofeedback as a Therapeutic Option." J Urol. 1997;157(6):2234-2237. doi:10.1016/S0022-5347(01)64727-X
35. Sudrania MK, Dangi AD, Kumar S, Kumar B, Kekre NS. "Urodynamic outcomes of tamsulosin in the treatment of primary bladder neck obstruction in men." Indian J Urol. 2018;34(1):34-38. doi:10.4103/iju.IJU_123_17
36. DailyMed. Alfuzosin hydrochloride extended-release tablets: prescribing information. Revised January 2026. Label
37. Zhang P, Wu ZJ, Xu L, Yang Y, Zhang N, Zhang XD. "Bladder neck incision for female bladder neck obstruction: long-term outcomes." Urology. 2014;83(4):762-766. doi:10.1016/j.urology.2013.10.084
38. DailyMed. Doxazosin tablets: prescribing information. Apotex Corp.; updated September 10, 2026. Official label
39. Lee YS, Lee KS, Choo MS, et al. "Efficacy of an alpha-blocker for the treatment of nonneurogenic voiding dysfunction in women: an 8-week, randomized, double-blind, placebo-controlled trial." Int Neurourol J. 2018;22(1):30-40. doi:10.5213/inj.1834904.452
40. Jericevic Schwartz D, Parkinson M, Brucker BM. "Primary bladder neck obstruction in women: a systematic review." Curr Urol Rep. 2025;26(1):67. doi:10.1007/s11934-025-01295-z