Urethral Diverticulum
Urethral diverticulum (UD) is a benign, epithelium-lined outpouching of urethral mucosa into the periurethral tissues. In women, the diverticulum usually lies between the urethra and the anterior vaginal wall and communicates with the urethral lumen through an ostium or neck.[1][2][3]
Symptomatic UD is usually treated surgically after imaging defines its configuration. Standard transvaginal repair includes complete sac excision, watertight layered urethral closure, continence preservation, and assessment for rare malignancy.[46] In a 45-woman retrospective cohort, partial excision was used for complex lesions involving >75% of the urethral circumference.[4]
For the broader differential diagnosis of meatal, urethral, and periurethral masses, see Female Urethral & Periurethral Masses. For the operative repair, see Urethral Diverticulum Repair in the Urethral Reconstruction treatment atlas.
Definition and Terminology
UDs are best described by morphology, location, relationship to the sphincter or bladder neck, and circumferential involvement.
| Term | Meaning | Surgical implication |
|---|---|---|
| Simple UD | Single, unilocular sac with a discrete ostium | Usually more straightforward excision |
| Complex UD | Multiloculated, horseshoe, circumferential, recurrent, proximal, large, or associated with stones/infection/malignancy | Higher risk of recurrence, SUI, urethral injury, and need for interposition |
| Horseshoe UD | Diverticulum extends around both sides of the urethra | Requires careful lateral dissection and complete sac removal |
| Circumferential / saddlebag UD | Circumferential UD nearly or fully encases the urethra; saddlebag UD partially encases it.[45] | Circumferential involvement raises continence and fistula concern |
| Distal UD | Near meatus / distal urethra | May be amenable to marsupialization in selected cases |
| Male acquired UD | Outpouching of male urethra, usually after stricture, hypospadias repair, trauma, or catheter injury | Managed like a urethral reconstruction problem |
Two classification frameworks are in use. The Leach L/N/S/C3 system records Location (distal, mid, proximal, with or without extension beneath the bladder neck), Number, Size, and Configuration (single, multiloculated, saddle), Communication (site of the ostium) and Continence (presence of stress incontinence).[34] MRI-based schemes grade configuration: simple, U-shaped or horseshoe, or circumferential. In one single-surgeon series classified this way (68 women), initial cure by MRI-confirmed absence of residual diverticulum and symptom resolution was 100% for simple, 75% for U-shaped and 64% for circumferential diverticula, and circumferential configuration independently predicted failure (OR 7.97); of 15 recurrences, four resolved symptomatically without reoperation; eight of 11 reoperated women were cured (seven with Martius interposition and one with repeat excision alone).[36] Another MRI scheme defines complex UD as more than 75% circumferential urethral involvement.[4]
Epidemiology
UD is uncommon but underdiagnosed. In selected cohorts, female UD prevalence is often cited around 1–6%; a population-based study in Olmsted County, Minnesota (1980–2011), found an age-adjusted annual diagnosed incidence of 17.9 per million adult women.[1][2][53] The yield is higher when imaging is targeted at women with lower urinary tract symptoms: in a series of 140 women who underwent endorectal-coil MRI for LUTS, 10% had a urethral diverticulum, and MRI alone made the diagnosis in just over half of that group.[41] In women evaluated for stress urinary incontinence, the prevalence is lower but clinically important because a missed UD can complicate sling planning.[6]
Typical age at diagnosis is midlife, often in the 40s or 50s, but reported ranges span young adulthood to older age.[7][8] UD has been reported more often in Black women in several series.[7][8]
Delay is common. Symptoms overlap with cystitis, OAB, pelvic floor pain, vaginitis, urethral pain syndrome, and stress incontinence, so patients often cycle through antibiotics or bladder medications before pelvic examination and MRI reveal the diagnosis.[1][8] In one referral series of 46 women, mean time from symptom onset to diagnosis was 5.2 years, and the number of physicians previously consulted ranged from 3 to 20.[40]
Male UD is rare and usually acquired rather than congenital.[9]
Etiology and Pathogenesis
The dominant theory is the periurethral gland infection/abscess model. Obstruction and infection of periurethral glands lead to abscess formation; rupture into the urethral lumen creates an epithelialized cavity that persists as a diverticulum.[1][2][10]
Other contributors include:
- Obstetric trauma. Vaginal delivery injury may disrupt periurethral tissues.
- Iatrogenic trauma. Prior periurethral surgery, urethral dilation, urethral instrumentation, and anti-incontinence procedures.[42] Transurethral bulking-agent injection has also been reported, in a single case, as a cause of diverticulum formation.[42] A distinct postoperative urethral pseudodiverticulum has also been described: a mucosal herniation through an acquired periurethral fascial defect, for example where a suspension suture has torn the fascia or fascia was excised during a prior diverticulectomy, rather than a true epithelialized diverticular sac. It can produce postvoid leakage that resembles stress incontinence. Distinguishing it from a true diverticulum on imaging and endoscopy, and repairing the fascial defect rather than only excising mucosa, has been described as central to cure in reoperative cases.[44]
- Chronic inflammation and stasis. They support recurrent infection, stones, epithelial metaplasia, and rare malignancy.
- Functional high-tone sphincter hypothesis. Women with apparently idiopathic UD may have larger urethra-sphincter complex volumes, suggesting high-pressure voiding or nonrelaxing sphincter activity could contribute in some patients.[11]
- Congenital remnants. These are rare and difficult to prove in adult presentations.
Prior sling, prior urethral surgery, radiation, active infection, high-tone pelvic floor, or coexisting SUI should all change counseling and planning.
Clinical Presentation
The classic triad of dysuria, dyspareunia, and post-void dribbling (the "3 D's") is memorable but insensitive. In 54 women undergoing diverticulectomy, all three were present together in only 5%, and 27% had none of them; recurrent UTI (70%), stress incontinence (60%) and dyspareunia (60%) were the most common presenting symptoms.[8] In a 78-woman series, 21% of diverticula were asymptomatic.[7]
Common presentations include:
| Symptom / finding | Clinical clue |
|---|---|
| Recurrent UTI | Relapsing infections, persistent pyuria, post-void discharge |
| Stress urinary incontinence | May be true SUI, pseudo-incontinence from retained urine, or both |
| Post-void dribbling | Residual urine empties from the sac after voiding |
| Dyspareunia | Anterior vaginal wall tenderness or mass effect |
| Urethral pain / dysuria | Often misdiagnosed as cystitis or urethral pain syndrome |
| Frequency / urgency | Can mimic OAB |
| Anterior vaginal wall mass | Tender periurethral mass; may express urine or pus with compression |
| Hematuria or bloody discharge | Raises concern for stone, inflammation, or malignancy |
| Asymptomatic mass | Found during pelvic exam or imaging |
On examination, palpate the anterior vaginal wall along the urethra.[12] Compression may express urine, pus, or debris from the meatus.[12] Only 54% of periurethral masses were palpable in one large series.[12] Expressible urethral fluid on palpation and recurrent UTI are the most predictive clinical findings.[33]
Anatomy and Morphology
UD most commonly arises from the posterolateral mid-urethra, but distal, proximal, and full-length diverticula occur.[1][7]
Important MRI descriptors:
- Location: distal, mid-urethral, proximal, or full-length
- Size: maximum diameter; larger lesions increase complexity
- Configuration: simple, multiloculated, horseshoe, or circumferential
- Ostium: number and position when visible
- Sphincter or bladder-neck relationship: predicts continence risk
- Complications: stone, infection, wall thickening, solid enhancement, suspected malignancy
Circumferential configuration predicts a lower initial cure rate,[36] and most women who develop de novo urodynamic SUI after excision have more than 270° of circumferential involvement (67% in one 100-woman series), although diverticular volume did not predict it.[5] Complex and simple diverticula had similar postoperative outcomes in a smaller series that tailored the excision (complete for simple, partial for complex).[4]
Diagnostic Evaluation
Clinical Assessment
Evaluation starts with history, pelvic examination, urinalysis and culture, and careful assessment for coexisting SUI, OAB, pelvic floor hypertonicity, prolapse, and prior urethral or anti-incontinence surgery.[1][14]
Preoperative questions:
- Is there a palpable mass?
- Does compression express discharge through the meatus?
- Are UTIs culture-proven and recurrent?
- Is leakage stress-related, urgency-related, post-void dribbling, or mixed?
- Is there prior sling, bulking agent, urethral surgery, radiation, or childbirth trauma?
- Is there hematuria, stone, firm mass, or suspicious imaging?
MRI
Pelvic MRI is the preferred imaging study for suspected female UD. T2-weighted sequences define the fluid-filled sac, ostium, size, location, multiloculation, circumferential extension, and relationship to the urethra, bladder neck, and sphincter.[3][15][16]
In surgical series MRI has been highly accurate: 100% sensitivity and negative predictive value with 83% specificity and 92% positive predictive value in 60 women undergoing excision of periurethral masses,[33] and 100% sensitivity and specificity in a 60-woman referral series in which the ostium was identified in 85% of diverticula.[15] Older, non-dedicated MRI was less reliable (70% of diverticula depicted, ostium not identified).[16] In a separate operative cohort, MRI and surgery disagreed in 10 of 41 women (24.4%), including three diverticula and two diverticular cancers missed on MRI; persistent clinical concern warrants further evaluation despite a reassuring MRI.[48]
MRI can:
- Confirm UD when examination is equivocal
- Distinguish UD from Skene gland cyst, Gartner duct cyst, urethral leiomyoma, bulking agent, or malignancy
- Identify the ostium in many cases
- Show stones, debris, wall thickening, or enhancing solid components
- Alter the surgical plan in complex or recurrent disease[15][16][17]
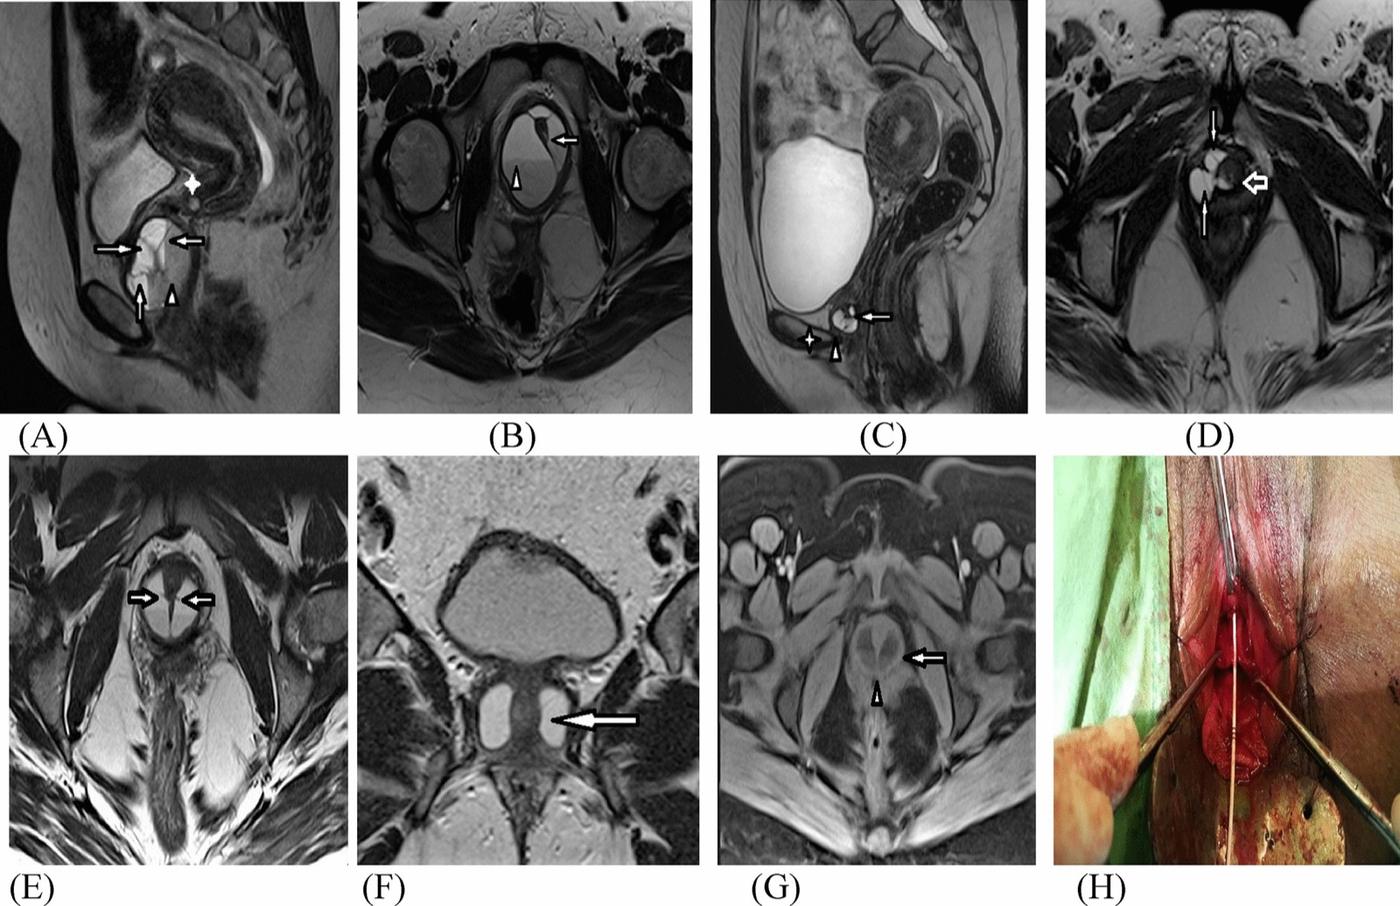
Complex urethral diverticula on MRI. (A, B) T2-weighted sagittal and axial oblique: circumferential diverticulum above and behind the symphysis pubis, totally encasing the urethra, with a connection to the urethral lumen (arrow in B), multiple thick septa (long arrows in A) and a protein–urine debris level (arrowheads) with inflammatory changes. (C, D) Sagittal and axial oblique: saddlebag diverticulum (arrowhead in C; symphysis marked by the asterisk) partially encasing the urethra, with its ostium at 6 o'clock (hollow arrow in D) and thick septa, containing clear urine. (E–G) Axial oblique and coronal oblique T2 and axial oblique fat-suppressed T1: a large recurrent circumferential biloculated septated diverticulum nearly encasing the whole urethral length (arrow in F), with a thick central septum at 6 o'clock (arrowhead in G), bilateral connections to the urethral lumen (arrows in E) and a debris level (arrow in G). (H) After dissection, both loculi exposed with the midline septum between them; the ostium was calibrated with a ureteric catheter placed at cystoscopy before surgery. From Mahfouz W, et al. World J Urol. 2022;40(6):1587–1594, Fig. 2 (CC BY).[45]
Ultrasound and Contrast Studies
Pelvic floor ultrasound can detect UD and periurethral masses in experienced hands. In a retrospective cohort of 196 symptomatic women, pelvic floor ultrasound had reported sensitivity of 94% versus 78% for VCUG (p<0.01; NPV 88% versus 68%), with the final diagnosis incorporating both tests.[18] In a separate retrospective series of 95 women with urethral or periurethral masses, ultrasound characterized 39 urethral diverticula.[19] Transvaginal sonography can also help characterize complex paraurethral abnormalities.[20]
VCUG historically demonstrated the contrast-filled sac (95% of 63 women in an older tertiary series),[23] but performance is variable in later series (78% sensitivity above) because the ostium must fill during the study. A VCUG without voiding or postvoid images cannot exclude a diverticulum: pain after catheterization, situational inhibition or inadequate flow may prevent sufficient filling and can underestimate the sac's size and complexity.[21][23] If the patient cannot void during fluoroscopy, allowing voiding in a private bathroom and then obtaining the postvoid image is a practical rescue step.[21][23] Double-balloon positive-pressure urethrography is more sensitive than standard VCUG but is invasive and rarely used now.[21]
Cystourethroscopy and Urodynamics
Cystourethroscopy may identify the ostium, exclude stones or tumor, and assess the urethra before reconstruction.[1][16] The ostium may be small, hidden, or intermittently obstructed.[1][16]
Urodynamics are valuable when symptoms suggest SUI, urgency incontinence, high PVR, voiding dysfunction, prior sling complication, or neurogenic disease. Preoperative urodynamics can clarify whether leakage is true SUI, urgency-related, or pseudo-incontinence from retained urine within the sac.[22][23]
Differential Diagnosis
| Diagnosis | Distinguishing features |
|---|---|
| Urethral diverticulum | Communicates with urethra; T2-bright periurethral sac; often mid-urethral |
| Skene gland cyst / abscess | Paraurethral, usually distal; does not communicate with urethral lumen |
| Gartner duct cyst | Anterolateral vaginal wall; embryologic remnant; no urethral communication |
| Urethral caruncle | Distal meatal polypoid lesion, often postmenopausal |
| Urethral leiomyoma | Solid mass, vascularity on ultrasound/MRI |
| Periurethral bulking agent | Prior injection history; characteristic location and MRI signal |
| Urethral malignancy | Solid enhancing mass, irregular wall, bleeding, pain, firm fixation |
| Anterior vaginal wall cyst / inclusion cyst | No urethral ostium; separate from urethral lumen |
MRI is especially helpful in separating UD from bulking agents and noncommunicating periurethral cysts.[17][24][25]
Management
Conservative Management
Observation is reasonable for asymptomatic or minimally symptomatic UD, patients who decline surgery, or patients whose operative risk exceeds symptom burden; EAU 2026 weakly recommends counseling women who choose observation about the reported 1–6% cancer risk within the diverticulum.[46] Conservative care may include UTI treatment, post-void manual decompression, office aspiration or incision and drainage for acute symptom relief, and surveillance when malignancy is not suspected.[1][7][9] Aspiration or drainage may relieve pressure or drain an acute infection when definitive surgery is deferred; it leaves the epithelialized sac in place and yields no excision specimen. After stabilization, consider diverticulectomy with pathologic evaluation according to symptoms, recurrence, and concern for malignancy.
Diverticula diagnosed during pregnancy can generally be managed conservatively through delivery, with diverticulectomy deferred to the postpartum period and performed with the same technique and care pathway used outside pregnancy. In a retrospective series of 12 pregnant women managed conservatively until delivery, 11 delivered vaginally; postpartum diverticulectomy at roughly three months was followed by low-grade complications in 3 of 12 (25%) and no reported recurrence. No infectious mother-to-child transmission was reported.[39]
Antibiotics may quiet infection but do not remove the reservoir, and recurrent symptoms are common when the sac persists. Diverticula with stones, a solid enhancing component, hematuria or a firm wall should not be observed without excluding neoplasm, because chronic stasis and infection are associated with stone formation and rare malignant change.
Transvaginal Diverticulectomy
Transvaginal urethral diverticulectomy is the standard operation for symptomatic female UD.[1][2][6][26]
Core principles:
- Mobilize the diverticulum circumferentially and excise the entire wall when feasible; a 45-woman retrospective cohort used partial excision for diverticula with >75% circumferential involvement.[4]
- Identification and closure of the urethral ostium
- Watertight urethral closure
- Multilayer, non-overlapping closure
- Preserve a well-vascularized vaginal flap and periurethral fascia for layered closure while protecting urethral support and sphincter function.[46]
- Interposition flap when tissue quality, size, recurrence, infection, prior surgery, or fistula risk warrants it
A Martius labial fat pad flap is commonly used for complex, recurrent, proximal, infected, or large diverticula, or when a large defect remains after excision.[6][26] In a 70-woman series with routine Martius interposition, all diverticula were completely excised and one symptomatic recurrence occurred (1.4%); there was no comparison group, so the benefit is inferred.[26] Martius was used in 30% of cases in a 121-woman series.[28]
Distal diverticula may be treated with Spence-Duckett marsupialization in selected cases, but this can shorten or alter the distal urethra, carries a theoretical urethrovaginal fistula risk, and is not appropriate for most mid-urethral or complex lesions.[27][46]
Outcomes and Complications
Most women improve after complete excision, but reported success depends heavily on definition and follow-up. Among the 56 of 108 studies that reported symptom resolution, 717 of 1,044 women (69%) were completely symptom-free.[37] Only 50 of 108 studies reported follow-up duration.[37] Single-center series report 72% dry and cured among 89 women followed for 3–20 months and 73% continent among 121 women followed for a mean 10 months; narrative and systematic reviews quote 83–97% success using varying endpoints.[6][28][31][35] With an MRI-defined endpoint, initial cure was 77.9% and overall cure after reoperation 92.6%.[36]
| Outcome | Reported range (denominators) |
|---|---|
| Recurrence | Several series report 3–10%: 3.4% (3/89), 4% (5/121), 7.5% (3/40), and 10.1% of 485 in a multicenter cohort. One MRI-defined series had 22% (15/68); reviews report 2–22%. In a separate retrospective cohort of 114 operated women, postoperative follow-up was available for 82 (71.9%); 14/114 (12.3%) had observed recurrence, with five-year estimated risks of 23.4% for recurrence and 17.0% for reoperation by survival analysis.[6][7][28][29][36][31][49] |
| De novo SUI | Initial de novo SUI was reported in 13% (16/121), 15% (13/89), and 16% (16/100) after diverticulectomy in separate series. The 5.6% rate came from a mixed cohort of periurethral and anterior vaginal wall masses; 12% (5/41) was SUI persisting at 12 months among previously continent women, not initial incidence. In one 70-woman series, 10 of 41 previously continent women (24%) reported new SUI immediately after surgery, falling to five of 41 (12%) at 12 months. In a separate 100-woman cohort, 12 of 16 de novo SUI cases resolved after pelvic floor muscle training.[5][6][13][22][26][28][35] |
| Urethrovaginal fistula | Reported in 0.9–8.3% of series reviewed by EAU; an older 56-woman cohort with three-layer closure reported 1/56 (1.8%).[46][23] |
| Malignancy in excised diverticula | 1/89 (1.1%), 1/40 (2.5%), and 5/90 (5.6%) in selected series.[6][7][30] |
Recurrence requiring repeat surgical excision was higher after surgery for recurrent UD: in a 122-woman cohort, it occurred in 9.1% (10/110) without prior diverticulectomy versus 25% (3/12) operated on for recurrent UD, and prior pelvic or vaginal surgery excluding prior diverticulectomy was associated with the same endpoint (p<0.001).[43]
Other potential complications include:
- Urethral stricture or voiding dysfunction with retention
- Recurrent UTI
- Persistent pain or dyspareunia
- Intraoperative blood loss, greater with diverticula over 3 cm[31]
Larger size, proximal or sphincteric involvement, circumferential configuration, prior surgery, and malignancy suspicion increase operative difficulty; circumferential configuration is the best-documented predictor of failure.[31][36]
Stress Urinary Incontinence
SUI is common before UD surgery. Some patients leak from post-void sac emptying, urgency, or infection-related bladder irritability.
Management principles:
- Clarify the leakage mechanism preoperatively.
- Counsel that SUI may improve after diverticulectomy alone.
- Avoid reflex concomitant sling in every patient.
- Consider staged anti-incontinence surgery when SUI persists after healing.
Excision alone resolves much of the preoperative SUI: 54% of women with preoperative SUI were continent after excision in one series,[28] and in another, 16 of 27 with preoperative urodynamic SUI resolved (8 after excision, 8 after pelvic floor therapy), leaving 13.9% of all women needing an anti-incontinence operation, which cured 92%.[22]
In a multicenter cohort of 485 diverticulectomies (96 with a concomitant pubovaginal sling), concomitant sling was associated with greater SUI resolution (aOR 2.27), was not significantly associated with de novo SUI or diverticulum recurrence, and was associated with higher odds of short-term (aOR 2.5) and long-term (aOR 6.98) urinary retention and recurrent UTI (aOR 3.27); the slings were placed in older women with more preoperative SUI and more prior diverticulectomy.[29] Excision first with delayed continence surgery after healing remains an option; two series deferred anti-incontinence surgery to about 6–12 months for persistent SUI.[22][28] For bothersome, confirmed SUI, counsel on a concomitant non-synthetic sling versus staged treatment: EAU 2026 weakly recommends concomitant treatment after counseling, while CUA 2024 permits simultaneous non-mesh surgery for significant true SUI as a Clinical Principle and cautions against prophylactic surgery solely to prevent de novo SUI.[46][47]
Synthetic midurethral mesh sling is generally avoided at the time of diverticulectomy because urethral entry, infection, and future fistula or erosion risk make autologous or staged strategies safer. The 2023 AUA/SUFU female SUI guideline states that clinicians should not place a synthetic midurethral sling during concomitant diverticulectomy and SUI surgery , citing concern about mesh near a fresh urethral opening.[38][51]
Malignancy and Pathology
Malignancy within UD is rare (about 1-6% of excised diverticula) but clinically important.[6][30] Reported rates include 6% (5 of 90, all invasive and glandular, including four adenocarcinomas and one clear-cell carcinoma) with a further 3 women showing extensive intestinal metaplasia,[30] 6% (4 of 66) in a tertiary urogynecology practice,[12] 2.5% (1/40 excised diverticula, an adenocarcinoma) in an urban center series of 78 diagnosed women,[7] and 1.1% (one squamous cell carcinoma among 89 excisions); the 2.2% figure included a benign leiomyoma.[6] Adenocarcinoma is the most frequent histology.[31] All excised diverticula require pathologic examination.[7][30] In the 90-woman series, invasive carcinoma was treated with anterior pelvic exenteration and diversion, and two women died of metastatic disease.[30]
Pathologic findings may include:
- Squamous, glandular, intestinal, or nephrogenic metaplasia
- Dysplasia
- Nephrogenic adenoma
- Adenocarcinoma, squamous cell carcinoma, or urothelial carcinoma
- Clear cell adenocarcinoma arising in or near a diverticulum[30][31][32]
Red flags include hematuria, firm or fixed mass, rapid growth, enhancing solid component on MRI, irregular wall thickening, stones with chronic infection, and recurrent or atypical symptoms. When a solid or fixed component raises concern for carcinoma, evaluate as suspected urethral cancer with urethrocystoscopy, urinary cytology, and biopsy of suspicious tissue before planning routine diverticulectomy. If carcinoma is confirmed, stage it as urethral cancer and arrange multidisciplinary oncologic planning when indicated.[50]
In a single-center series of 35 urinary tract clear-cell adenocarcinomas, clear-cell dysplasia was found beside invasive tumor in 15 of 25 assessable resections. In one diverticulum-associated case, dysplasia and carcinoma shared somatic mutations, while adjacent intestinal metaplasia did not; chronic inflammation remains a proposed contributor.[32]
Male Urethral Diverticulum
Acquired male UD is rare and usually follows urethral injury or reconstruction. Causes include prior hypospadias repair, urethral stricture, trauma, prolonged catheterization, infection, and prior urethroplasty.[9]
In a 22-man reconstructive referral cohort, 12 (55%) underwent diverticulectomy with urethroplasty, three (14%) ileal conduit diversion, and seven (32%) nonoperative care with post-void manual decompression; 10 of 11 followed after diverticulectomy were recurrence-free at a median cohort follow-up of 2.3 years.[9] In a later three-site retrospective series of 52 men with UD, 22 underwent diverticulectomy; four developed urethrocutaneous fistula and one had recurrence during a median 1.5 years of postoperative follow-up.[52] Presentation includes recurrent UTI, dribbling, post-void pooling, weak stream, stones, incontinence, or a ventral penile or perineal swelling. Management depends on size, symptoms, emptying, and tissue quality:
- Manual decompression or observation for small, asymptomatic, well-emptying diverticula
- Diverticulectomy with urethral reconstruction for symptomatic or poorly emptying lesions
- Urinary diversion in severe, irradiated, neurogenic, or multiply failed cases
Follow-Up and Prognosis
Follow-up should assess:
- Symptom resolution: UTI, pain, dyspareunia, dribbling, discharge
- Recurrent anterior vaginal wall mass
- Stress or urgency incontinence
- Voiding dysfunction and PVR
- Urethrovaginal fistula or stricture symptoms
- Pathology results
Most patients do well after complete excision, but recurrence can occur years later, especially after complex, circumferential, proximal, infected, or recurrent diverticula. Persistent SUI can usually be treated successfully after the urethra has healed and the new baseline continence phenotype is clear.
See Also
- Female Urethral & Periurethral Masses
- Female Urethral Stricture
- Urethral Diverticulum Repair
- Urethral Reconstruction treatment atlas
- Female Pelvic Examination
- MRI
- Stress Urinary Incontinence (Female)
Videos
References
1. Greenwell TJ, Spilotros M. "Urethral diverticula in women." Nature Reviews Urology. 2015;12(12):671-680. doi:10.1038/nrurol.2015.230
2. Rovner ES. "Urethral diverticula: a review and an update." Neurourology and Urodynamics. 2007;26(7):972-977. doi:10.1002/nau.20434
3. Chou CP, Levenson RB, Elsayes KM, et al. "Imaging of female urethral diverticulum: an update." Radiographics. 2008;28(7):1917-1930. doi:10.1148/rg.287075076
4. Cao M, Zhang J, Chen Y, Liang Y. "A single-center retrospective cohort study comparing complex and simple female urethral diverticulum classified based on magnetic resonance imaging features." Urology. 2025;199:68-74. doi:10.1016/j.urology.2025.02.034
5. Seth JH, Naaseri S, Solomon E, et al. "Correlation of MRI features of urethral diverticulum and pre- and post-operative stress urinary incontinence." Neurourology and Urodynamics. 2019;38(1):180-186. doi:10.1002/nau.23820
6. Reeves FA, Inman RD, Chapple CR. "Management of symptomatic urethral diverticula in women: a single-centre experience." European Urology. 2014;66(1):164-172. doi:10.1016/j.eururo.2014.02.041
7. Pincus JB, Laudano M, Leegant A, Downing K. "Female urethral diverticula: diagnosis, pathology, and surgical outcomes at an academic, urban medical center." Urology. 2019;128:42-46. doi:10.1016/j.urology.2018.12.052
8. Baradaran N, Chiles LR, Freilich DA, et al. "Female urethral diverticula in the contemporary era: is the classic triad of the '3Ds' still relevant?" Urology. 2016;94:53-56. doi:10.1016/j.urology.2016.04.005
9. Cinman NM, McAninch JW, Glass AS, Zaid UB, Breyer BN. "Acquired male urethral diverticula: presentation, diagnosis and management." The Journal of Urology. 2012;188(4):1204-1208. doi:10.1016/j.juro.2012.06.036
10. Peters W, Vaughan ED. "Urethral diverticulum in the female. Etiologic factors and postoperative results." Obstetrics and Gynecology. 1976;47(5):549-552. PMID 817239
11. Mukhtar BMB, Solomon E, Naaseri S, et al. "Urethral diverticula in women are associated with increased urethra-sphincter complex volumes: a potential role for high-tone nonrelaxing sphincter in their etiology?" Neurourology and Urodynamics. 2019;38(7):1859-1865. doi:10.1002/nau.24080
12. Blaivas JG, Flisser AJ, Bleustein CB, Panagopoulos G. "Periurethral masses: etiology and diagnosis in a large series of women." Obstetrics and Gynecology. 2004;103(5 Pt 1):842-847. doi:10.1097/01.AOG.0000124848.63750.e6
13. Jacox N, Yao HH, Baverstock R, Trpkov K, Carlson K. "Periurethral and anterior vaginal wall masses: etiology, presentation, and treatment outcomes." Obstetrics and Gynecology. 2022;140(5):778-783. doi:10.1097/AOG.0000000000004956
14. Zuo SW, Napoe GS. "Evaluation and management of urethral and periurethral masses in women." Current Opinion in Obstetrics & Gynecology. 2023;35(6):517-524. doi:10.1097/GCO.0000000000000914
15. Dwarkasing RS, Dinkelaar W, Hop WC, et al. "MRI evaluation of urethral diverticula and differential diagnosis in symptomatic women." AJR American Journal of Roentgenology. 2011;197(3):676-682. doi:10.2214/AJR.10.6144
16. Kim B, Hricak H, Tanagho EA. "Diagnosis of urethral diverticula in women: value of MR imaging." AJR American Journal of Roentgenology. 1993;161(4):809-815. doi:10.2214/ajr.161.4.8372765
17. Chulroek T, Wangcharoenrung D, Cattapan K, et al. "Can magnetic resonance imaging differentiate among transurethral bulking agent, urethral diverticulum, and periurethral cyst?" Abdominal Radiology. 2019;44(8):2852-2863. doi:10.1007/s00261-019-02052-w
18. Barakat B, Gauger U, Rehme C, et al. "Diagnosis of female urethral diverticulum using pelvic floor ultrasound and comparison with voiding cystourethrogram (imaging study)." International Urogynecology Journal. 2023;34(2):563-569. doi:10.1007/s00192-022-05340-0
19. Yang H, Gu JJ, Jiang L, et al. "Ultrasonographic imaging features of female urethral and peri-urethral masses: a retrospective study of 95 patients." Ultrasound in Medicine & Biology. 2020;46(8):1896-1907. doi:10.1016/j.ultrasmedbio.2020.03.024
20. Yang JM, Huang WC, Yang SH. "Transvaginal sonography in the diagnosis, management and follow-up of complex paraurethral abnormalities." Ultrasound in Obstetrics & Gynecology. 2005;25(3):302-306. doi:10.1002/uog.1811
21. Jacoby K, Rowbotham RK. "Double balloon positive pressure urethrography is a more sensitive test than voiding cystourethrography for diagnosing urethral diverticulum in women." The Journal of Urology. 1999;162(6):2066-2069. doi:10.1016/S0022-5347(05)68102-5
22. Barratt R, Malde S, Pakzad M, et al. "The incidence and outcomes of urodynamic stress urinary incontinence in female patients with urethral diverticulum." Neurourology and Urodynamics. 2019;38(7):1889-1900. doi:10.1002/nau.24090
23. Ganabathi K, Leach GE, Zimmern PE, Dmochowski R. "Experience with the management of urethral diverticulum in 63 women." The Journal of Urology. 1994;152(5 Pt 1):1445-1452. doi:10.1016/S0022-5347(17)32442-4
24. Itani M, Kielar A, Menias CO, et al. "MRI of female urethra and periurethral pathologies." International Urogynecology Journal. 2016;27(2):195-204. doi:10.1007/s00192-015-2790-x
25. Porten S, Kielb S. "Diagnosis of female diverticula using magnetic resonance imaging." Advances in Urology. 2008;2008:213516. doi:10.1155/2008/213516
26. Malde S, Sihra N, Naaseri S, et al. "Urethral diverticulectomy with Martius labial fat pad interposition improves symptom resolution and reduces recurrence." BJU International. 2017;119(1):158-163. doi:10.1111/bju.13579
27. Welch EK, Dengler KL, Welgoss JA. "Urethral diverticulum marsupialization with modified Spence-Duckett procedure." Urology. 2023;176:248. doi:10.1016/j.urology.2023.02.040
28. Osman NI, Mangir N, Reeves FA, et al. "The modified prone jack-knife position for the excision of female urethral diverticula." European Urology. 2021;79(2):290-297. doi:10.1016/j.eururo.2020.11.016
29. Bradley SE, Leach DA, Panza J, et al. "A multicenter retrospective cohort study comparing urethral diverticulectomy with and without pubovaginal sling." American Journal of Obstetrics and Gynecology. 2020;223(2):273.e1-273.e9. doi:10.1016/j.ajog.2020.06.002
30. Thomas AA, Rackley RR, Lee U, et al. "Urethral diverticula in 90 female patients: a study with emphasis on neoplastic alterations." The Journal of Urology. 2008;180(6):2463-2467. doi:10.1016/j.juro.2008.08.040
31. Daniels C, Wong TR, Isali I. "Rethinking urethral diverticulum: a narrative review of clinical outcomes and cancer associations." International Urogynecology Journal. 2025;36(11):2169-2176. doi:10.1007/s00192-025-06244-5
32. Rammal R, Koll FJ, Chen Z, et al. "Comprehensive molecular, pathological, and clinical characterization of clear cell adenocarcinoma of the urinary tract." Modern Pathology. 2025;38(10):100821. doi:10.1016/j.modpat.2025.100821
33. Pathi SD, Rahn DD, Sailors JL, et al. "Utility of clinical parameters, cystourethroscopy, and magnetic resonance imaging in the preoperative diagnosis of urethral diverticula." International Urogynecology Journal. 2013;24(2):319-323. doi:10.1007/s00192-012-1841-9
34. Leach GE, Sirls LT, Ganabathi K, Zimmern PE. "L N S C3: a proposed classification system for female urethral diverticula." Neurourology and Urodynamics. 1993;12(6):523-531. doi:10.1002/nau.1930120602
35. Shadyan G, Al-Jamal J, McCormick KM, et al. "Surgical techniques for female urethral diverticulectomy: a systematic review and educational video presentation." International Urogynecology Journal. 2026;37(7):2193-2197. doi:10.1007/s00192-026-06690-9
36. Ko KJ, Suh YS, Kim TH, et al. "Surgical outcomes of primary and recurrent female urethral diverticula." Urology. 2017;105:181-185. doi:10.1016/j.urology.2017.02.040
37. Bodner-Adler B, Halpern K, Hanzal E. "Surgical management of urethral diverticula in women: a systematic review." International Urogynecology Journal. 2016;27(7):993-1001. doi:10.1007/s00192-015-2862-y
38. Kobashi KC, Vasavada S, Bloschichak A, et al. "Updates to surgical treatment of female stress urinary incontinence (SUI): AUA/SUFU guideline (2023)." The Journal of Urology. 2023;209(6):1091-1098. doi:10.1097/JU.0000000000003435
39. Aoun R, Hermieu N, Schoentgen N, et al. "Urethral Diverticulum During Pregnancy Managed With Primum Non Nocere Principle: Conservative Treatment During Pregnancy and Diverticulectomy After Child Birth." Urology. 2023;180:93-97. doi:10.1016/j.urology.2023.07.004
40. Romanzi LJ, Groutz A, Blaivas JG. "Urethral diverticulum in women: diverse presentations resulting in diagnostic delay and mismanagement." The Journal of Urology. 2000;164(2):428-433. doi:10.1016/s0022-5347(05)67377-6
41. Lorenzo AJ, Zimmern P, Lemack GE, Nurenberg P. "Endorectal coil magnetic resonance imaging for diagnosis of urethral and periurethral pathologic findings in women." Urology. 2003;61(6):1129-1133. doi:10.1016/s0090-4295(03)00260-7
42. Clemens JQ, Bushman W. "Urethral diverticulum following transurethral collagen injection." The Journal of Urology. 2001;166(2):626. doi:10.1016/s0022-5347(05)66010-7
43. Ingber MS, Firoozi F, Vasavada SP, et al. "Surgically corrected urethral diverticula: long-term voiding dysfunction and reoperation rates." Urology. 2011;77(1):65-69. doi:10.1016/j.urology.2010.06.004
44. Leng WW, McGuire EJ. "Management of female urethral diverticula: a new classification." The Journal of Urology. 1998;160(4):1297-1300. doi:10.1016/s0022-5347(01)62520-5. PMID 9751339
45. Mahfouz W, Hassan H, Gubbiotti M, Elbadry M, Moussa A. "Does a tailored magnetic resonance imaging technique affect the surgical planning and outcomes for different cystic urethral and periurethral swellings in females? Seven years tertiary center experience." World J Urol. 2022;40(6):1587-1594. doi:10.1007/s00345-022-03973-w
46. European Association of Urology. EAU Guidelines on Non-neurogenic Female LUTS: Disease Management. 2026, section 4.9. Official guideline.
47. Carlson K, et al. "2024 Canadian Urological Association guideline: Female stress urinary incontinence." Can Urol Assoc J. 2024;18(4):83-102. doi:10.5489/cuaj.8751
48. Chung DE, Purohit RS, Girshman J, Blaivas JG. "Urethral diverticula in women: discrepancies between magnetic resonance imaging and surgical findings." J Urol. 2010;183(6):2265-2269. doi:10.1016/j.juro.2010.02.016
49. El-Nashar SA, Singh R, Bacon MM, et al. "Female urethral diverticulum: presentation, diagnosis, and predictors of outcomes after surgery." Female Pelvic Med Reconstr Surg. 2016;22(6):447-452. doi:10.1097/SPV.0000000000000312
50. European Association of Urology. EAU Guidelines on Primary Urethral Carcinoma: Diagnostic Evaluation and Staging. 2026. Official guideline.
51. American Urological Association and Society of Urodynamics, Female Pelvic Medicine & Urogenital Reconstruction. Surgical Treatment of Female Stress Urinary Incontinence: AUA/SUFU Guideline. 2023, statement 17. Official guideline.
52. Olson K, Vaidya R, Khan A. "Characterization of urethral diverticula in males." Can J Urol. 2022;29(2):11046-11051. PMID 35429421
53. El-Nashar SA, Bacon MM, Kim-Fine S, Weaver AL, Gebhart JB, Klingele CJ. "Incidence of female urethral diverticulum: a population-based analysis and literature review." Int Urogynecol J. 2014;25(1):73-79. doi:10.1007/s00192-013-2155-2