Male Urethral Stricture
Male urethral stricture is any pathological narrowing of the anterior urethra caused by scar tissue formation within the urethral epithelium and surrounding corpus spongiosum.[1]
For procedural selection and the full range of repairs, see the Urethral Reconstruction treatment atlas. Narrowing proximal to the corpus spongiosum (bladder neck, prostatic and membranous urethra) is termed stenosis rather than stricture; see Posterior Urethral Stenosis, including its radiation-induced stenosis section.
Epidemiology
The estimated prevalence of urethral stricture in developed countries is approximately 0.9%, though this likely underestimates the true burden of disease given underdiagnosis.[2] US administrative datasets reported urethral-stricture diagnoses in 229–627 per 100,000 males, with higher rates after age 55.[23] In a 1,439-man surgical referral series, 92.2% of strictures were anterior and 46.9% bulbar.[3]
Age distribution varies by cause and referral population; iatrogenic disease becomes particularly relevant with age.[4]
Anatomic Distribution
In two surgical referral cohorts, 80% of 899 Brazilian cases and 92.2% of 1,439 Italian cases involved the anterior urethra.[5][3]
| Location | Share in the cited surgical referral cohorts |
|---|---|
| Bulbar urethra | 46.9% of 1,439 Italian surgical cases (most common site)[3] |
| Penile urethra | ~30%[3] |
| Multifocal / panurethral | 10–15%[3] |
| Posterior urethra (stenosis or distraction injury) | 8–20% in the cited all-site surgical cohorts[3][5] |
The bulbar urethra's predominance reflects its susceptibility to perineal trauma, instrumentation, and the unique vascularity of the bulbospongiosus region. In a 135-man urethrography cohort, all posterior urethral stenoses (membranous or prostatic) had an iatrogenic or external-trauma etiology.[4]
Etiology
The etiology of urethral stricture disease has shifted dramatically in the modern era. In developed countries, iatrogenic and idiopathic causes account for most cases, with iatrogenic disease leading in surgical series; in low-income countries, trauma remains the leading cause due to road traffic injuries and limited healthcare infrastructure. The AUA guideline cites idiopathic (41%) then iatrogenic (35%) causes in high-income countries and trauma (36%) in low- and middle-income countries.[1][30]
Etiology Overview
| Category | Proportion | Key Causes |
|---|---|---|
| Iatrogenic | 38–52% | Urethral catheterization, transurethral prostate surgery, hypospadias repair, prostatectomy, and ablative focal therapy (cryotherapy, HIFU). Cohort shares have different denominators: catheterization (16.3%), transurethral surgery (9.1%), and hypospadias repair (12.2%) were shares of all 1,439 cases in Palminteri; among Astolfi’s iatrogenic cases, 59% followed instrumentation (60% catheterization, 40% transurethral procedures) and 16.2% followed failed hypospadias repair; prostatectomy accounted for 20.7% of all 135 cases (25.2% among men >45 yr) in de Farias.[3][4][5] |
| Idiopathic | 20–36%[3][4] | Unknown; once attributed to subclinical repeated perineal trauma (SRPT), now challenged[7] |
| Inflammatory | 14–16% | STIs (gonorrhea historically dominant); penile location in 47.6% of inflammatory strictures in one cohort[4][5] |
| Lichen sclerosus (LS) | 13–14%[3] | Mean stricture length 7.45 cm; penile predominance[3]; possible urethral cancer association |
| Traumatic | 11–22% | Pelvic fracture caused 62.7% of trauma-related strictures in the Brazilian cohort; posterior urethra predominates[3][5] |
Ablative focal therapy for prostate cancer. Cryotherapy and HIFU are reported causes of posterior urethral stricture alongside their other genitourinary complications (fistula, incontinence, thermal or mucosal injury). Complications, including stricture, are consistently reported as more frequent after salvage treatment of radiation-recurrent disease than after primary ablative therapy, and are generally harder to manage and slower to recover from than post-prostatectomy strictures.[31] A national English HIFU cohort found stricture in 133/1290 patients (10.3%) and urinary fistula in 16/1240 (1.3%) before further intervention among patients with at least one year of follow-up, with more recent treatment years associated with lower stricture risk.[32]
Idiopathic Strictures: Rethinking "Microtrauma". Historically, idiopathic strictures were attributed to subclinical and repeated perineal trauma (SRPT). Among 132 men in a five-center anterior urethroplasty cohort, reported subacute or repeated perineal trauma did not differ significantly across idiopathic, traumatic/iatrogenic, and lichen sclerosus etiologies.[7] In the same study, idiopathic and lichen sclerosus strictures showed similar tissue inflammation; serum IL-9, PDGF-BB and CCL5 were higher than in controls but did not differ significantly by stricture etiology.[7]
Catheter-Related Ischemic Injury. Catheter-associated stricture has been attributed to compression and ischemia at urethral segments that are relatively fixed or narrow — the bulbomembranous junction, the penoscrotal junction, and the fossa navicularis/meatus.[33]
Etiology by Age and Location
Etiology varies significantly by patient age and stricture location:[6][5]
| Population | Predominant Etiologies |
|---|---|
| Age <45 years | Idiopathic, hypospadias surgery, pelvic fracture trauma |
| Age ≥45 years | Iatrogenic (68% in those over 60): TURP, prostatectomy[5] |
| Penile strictures | Hypospadias repair, idiopathic, urethral catheterization, lichen sclerosus |
| Bulbar strictures | Idiopathic, TURP |
| Membranous/prostatic | Iatrogenic (post-prostatectomy), pelvic fracture |
| Multifocal/panurethral | Urethral catheterization |
Pediatric strictures and what the adult inherits. A stricture presenting in a young adult with a childhood catheterization, hypospadias repair, or pelvic-fracture history can be a pediatric stricture carrying into adult care rather than a new process. Pediatric practice limits endoscopic treatment to short, minimally fibrotic bulbar strictures and discourages repeating a failed dilation or urethrotomy; a posterior stricture from pediatric pelvic trauma is generally managed with delayed, tension-free anastomotic repair once the patient has stabilized. Because a child's pelvis is smaller and the urethra shorter, that original repair may have needed a transpubic or partial-pubectomy exposure to achieve a tension-free anastomosis rather than a purely perineal one.[40]
Pathophysiology
Tissue-Level Mechanism
Urethral stricture formation results from fibrosis and scar tissue development in response to injury, whether traumatic, inflammatory, or ischemic.[8] The pathophysiologic cascade:
- Epithelial injury leads to bleeding and extravasation of urine into the corpus spongiosum
- Inflammatory cell infiltration leads to myofibroblasts and multinucleated giant cells
- Altered collagen composition. The classic human biochemical study found a higher proportion of type I and lower proportion of type III collagen in stricture scar than normal spongiosum, consistent with reduced compliance; total collagen content did not differ significantly.[26]
- Progressive spongiofibrosis: the scar encases and compresses the urethral lumen
Spongiofibrosis contributes to stricture complexity. Treatment selection also depends on length, site, lumen/obliteration, cause, previous treatment and patient goals.[1]
Histopathology
Recent detailed histopathologic studies have clarified stricture biology:[9]
- Chronic inflammation was present in 44% of 100 anterior urethroplasty specimens; among the 44 inflamed specimens, lymphocytes predominated in 86% and plasma cells in 12%.[9]
- Among 44 inflamed anterior urethroplasty specimens, inflammation severity was minimal in 20%, mild in 39%, moderate in 39%, and severe in 2%.[9]
- Inflammation patterns differ by etiology: mild-to-severe inflammation in 27% of trauma strictures, 54% of idiopathic, and 48% of LS strictures (P = 0.036)[7]
- Isolated bulbomembranous strictures showed inflammation in 1 of 11 specimens (9%) in this retrospective series; the mechanism remains uncertain.[9]
- Fibrosis does not significantly differ between etiologies.[7]
Molecular Biomarkers
Deep phenotyping has identified systemic inflammatory and fibrotic biomarkers elevated in stricture patients versus controls:[7]
- Interleukin-9 (IL-9). Elevated in inflamed strictures; correlates with inflammation severity (Spearman's ρ 0.224, P = 0.014)
- Platelet-derived growth factor-BB (PDGF-BB)
- CCL5
These cytokines are implicated in fibrotic conditions in other organ systems and may represent future therapeutic targets for scar prevention or modulation.
Clinical Presentation
Symptoms
Men most commonly present with obstructive voiding symptoms (LUTS); AUA also lists UTI, epididymitis, rising post-void residual, reduced ejaculatory force, spraying and dysuria:[1][8][30]
- Weak or reduced urinary stream
- Incomplete bladder emptying
- Urinary hesitancy and straining to void
- Intermittent or split stream
- Post-void dribbling
- Spraying of urine
Irritative symptoms may also occur: dysuria, urinary frequency, urgency, and nocturia.
Additional presentations include:
- Acute urinary retention (AUR). Present in 32.6% of 1,023 men with complete data referred for suspected stricture at specialist presentation[10]
- Recurrent urinary tract infections (particularly with elevated post-void residuals)
- Rising post-void residual volumes
- Hematuria
- Urinary incontinence (overflow or post-void dribbling)
- Ejaculatory dysfunction (minority of patients)
- Rare: urethral carcinoma, Fournier's gangrene, bladder atonia[8]
Physical Examination
- Palpable urethral thickening or induration. May suggest spongiofibrosis, but palpation and endoscopic tissue appearance are imperfect surrogates for its extent[33]
- White plaques or patches on the glans/prepuce. Characteristic of lichen sclerosus
- Palpably distended bladder. Chronic urinary retention
- Perineal/scrotal fluctuance: urethral abscess or extravasation (urgent)
Complications and Natural History
In a retrospective cohort of 1,023 men with complete data referred for suspected stricture, 415 (40.6%) had at least one stricture-related complication at presentation.[10]
| Complication at specialist presentation | Proportion of 1,023 complete-case referrals |
|---|---|
| Acute urinary retention | 32.6% |
| Difficult catheterization requiring emergent intervention | 16.0% |
| Urethral abscess or urosepsis | 5.0% |
| Renal failure | 3.1% |
| Life-threatening complication (any) | 7.0% |
Risk factors for complications (multivariate analysis):[10]
- Longer stricture length (OR 1.1 per cm)[10]
- Absence of preceding LUTS (OR 3.8): strictures presenting acutely without warning[10]
- Posterior stenosis (OR 3.0)[10]
- Trauma etiology (OR 1.6)[10]
Severe stricture obstruction can impair renal function. In one institution's urethrography cohort of 135 men, 112 (83%) had narrowing of more than two-thirds of the urethral lumen.[2][4]
Female Urethral Stricture
The AUA 2023 guideline describes female urethral strictures as most commonly iatrogenic, often after traumatic catheterization or repeated dilations.[1] In female series pooled by EAU 2026, idiopathic causes were most common (48.5%), followed by iatrogenic injury (24.1%).[23] See Female Urethral Stricture.[23] Other causes include blunt pelvic trauma, obstetric complications (cephalopelvic disproportion), malignancy, radiation, urethrovaginal atrophy, recurrent infections, and skin diseases (lichen planus, lichen sclerosus).
Diagnosis is challenging due to non-specific presentation and unclear diagnostic criteria. Patients present with LUTS, recurrent UTIs, hesitancy, poor flow, frequency, urgency, urethral pain, elevated PVR, or AUR. Inability to pass even a small catheter due to distal stenosis is strongly suggestive.
Diagnosis & Workup
Confirm suspected stricture endoscopically or radiographically, document baseline erectile and ejaculatory function with validated tools before surgery, and examine the oral cavity when planning mucosal graft harvest.[1][23] Stricture length and location are necessary for treatment planning. Obtain urinalysis and culture urine when infection is suspected; before urethral surgery that breaches mucosa, screen for and treat bacteriuria, including asymptomatic bacteriuria.[23]
Imaging
| Modality | Role | Key Points |
|---|---|---|
| Retrograde Urethrography (RUG) | EAU strongly recommends it to assess location and length before reconstruction[23] | Identifies location, length, severity; performed with fluoroscopy |
| Voiding Cystourethrography (VCUG) | Posterior urethra; functional significance | Combined RUG+VCUG for complete urethral mapping |
| Sonourethrography (SUG) | Anterior stricture length and spongiofibrosis assessment | Estimates length more accurately than RUG in cited studies and can assess spongiofibrosis; operator dependent, with lower sensitivity for bulbar disease[23] |
| MRI | Ancillary imaging for selected complex PFUI or posterior stenosis | Adds defect and associated-pathology detail alongside RUG and VCUG; not routine first-line imaging[23] |
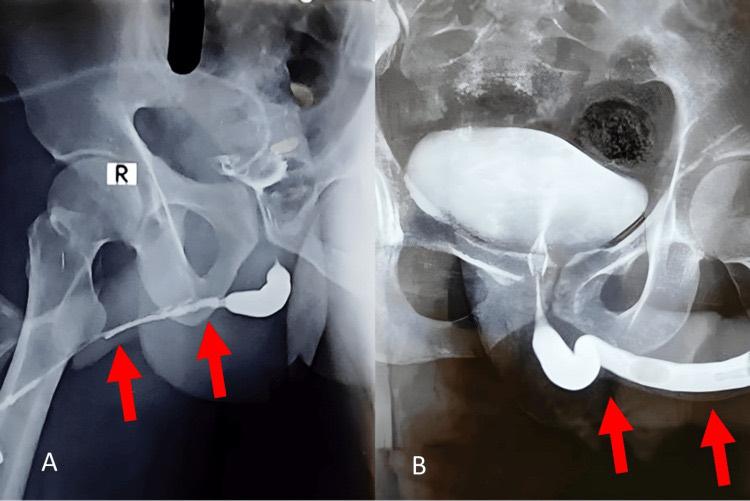
(A) Preoperative retrograde urethrogram showing bulbar and penile urethral stricture (arrows). (B) Postoperative urethrogram after buccal mucosal graft anterior urethroplasty showing the augmented urethral segment (arrows). From Gupta R, et al. Cureus. 2024;16(9):e70379, Figure 1 (CC BY).[41]
Diagnostic Procedures
Uroflowmetry: A flat-topped or plateau-shaped tracing with low peak flow (Qmax) can raise suspicion but is not a reliable stand-alone stricture screen. Measure post-void residual and confirm suspected disease anatomically.[23]
Urethrocystoscopy: Provides direct visualization of the urethral lumen. Endoscopic findings:
- Epithelial pallor
- Reduced tissue elasticity
- Inability to advance the scope (tight strictures)
- Scarring pattern and distribution
Urodynamics: Generally not routinely indicated unless coexisting bladder dysfunction (e.g., neurogenic bladder, OAB, DUA) is suspected.
Classification & Grading
EAU Lumen-Based Grading System
| Category | Description | Lumen Caliber |
|---|---|---|
| 1 | Subclinical | >16 Fr |
| 2 | Low grade | 11–15 Fr |
| 3 | High grade | 4–10 Fr |
| 4 | Nearly obliterative | 1–3 Fr |
| 5 | Obliterative | 0 Fr |
Devine Classification (Spongiofibrosis Depth)
Grades strictures by depth of fibrosis from mucosal-only involvement to full-thickness fibrosis extending outside the corpus spongiosum.
LSE Classification System
Erickson et al. (2020) developed the system for the Trauma and Urologic Reconstruction Network of Surgeons (TURNS). LSE stands for Length (L), Segment (S) and Etiology (E), not "severity."[17] It uses the retrograde urethrogram, physical examination and stricture history:
| Element | Categories |
|---|---|
| L — Length | L1 (<2 cm; short bulbar segments may suit excision) / L2 (2–7 cm; one substitution graft) / L3 (>7 cm; often two graft sources or a fasciocutaneous flap) |
| S — Segment | S1 bulbar (S1a proximal or mid bulb only; S1b involves the distal bulb) / S2 penile (S2a penile extending into the bulb, sparing the fossa and meatus; S2b isolated penile; S2c penile plus fossa or meatus; S2d isolated fossa or meatus) / S3 bulbar, penile and fossa or meatus together (pan-urethral), or a series of strictures managed with one technique |
| E — Etiology | E1 traumatic (for example straddle injury) / E2 idiopathic / E3 iatrogenic (E3a intraurethral instrumentation such as TURP; E3b in a previously reconstructed segment; E3c pelvic radiation) / E4 infectious / E5 after hypospadias repair / E6 lichen sclerosus |
Modifiers add detail. p marks extension into the membranous or prostatic urethra (not a pelvic fracture distraction defect or bladder neck contracture), m marks two or more separate strictures repaired with different techniques, and x marks an obliterative segment that will need excision. An obliterative proximal bulbar straddle stricture shorter than 2 cm is L1Sx1aE1.[17]
The authors tested three versions on clinical vignettes read by 20 reconstructive urologists and fellows. The final version had an overall kappa of 0.79 (L 0.76, S 0.70, E 0.93). Retrospective classification of 2,162 strictures in the TURNS database showed that segment was associated with both urethroplasty type (p = 0.0005) and presumed etiology (p = 0.0005). Prediction of outcomes was not tested in this paper.[17] The derived numeric LSE score correlates with surgical complexity and recurrence.[18]
LSE Staging System (Erickson 2025)
A subsequent formal staging system built on the LSE classification, validated with TURNS longitudinal outcomes data. The five stages and 10 substages were ranked by a Urethroplasty Triad Score combining freedom from secondary repair, whether planned reconstruction needs multiple operations, and planned final meatal location.[19]
| Stage | Description |
|---|---|
| I | Short bulbar with favorable etiology (E1, E2 or E3a) |
| II | Longer bulbar with favorable etiology, or bulbar of any length with adverse etiology (E3b, E3c, E4/6, E5) or m/p modifier |
| III | Penile / fossa navicularis with favorable etiology |
| IV | Penile / fossa navicularis with adverse pathology |
| V | Panurethral (three segments) |
LS and failed hypospadias repair require tissue-specific assessment, and some complex strictures remain suitable for a single-stage reconstruction.[1][19]
The LSE staging system is superior to both the LSE score and the U-score in predicting need for multiple stages or a nonorthotopic meatus.[19] The staging system separates penile strictures by etiology (Stage III versus IV). Favorable-etiology penile strictures are often suitable for one-stage reconstruction; selected LS strictures may undergo single-stage oral-mucosa graft repair, while an inadequate urethral plate after failed hypospadias repair may require staging. Perineal urethrostomy remains an option for selected complex cases.[23]
Comparison with Other Anterior-Stricture Classification Systems
A 2021 systematic review by John & Kahokehr identified five anterior-stricture classification systems with varying validation depth:[20]
| System | Basis | Components | Validation |
|---|---|---|---|
| U-Score (Urethral Stricture Score) | RUG + history | Length (1–3) + number (1–2) + location (1–2) + etiology (1–2); total 4–9 | Multiple external validations; predicts surgical complexity and OR time[21][22] |
| LSE | RUG + exam + history | L (1–3), S (1–3), E (1–6) | TURNS-developed; interrater reliability 0.79; segment associated with urethroplasty type[17]; the LSE score was associated with complexity and recurrence in a later comparison[18] |
| ULTRA Score | Sonourethrogram | Ultrasound stricture characteristics | Limited |
| Cystoscopy-based | Endoscopy | Endoscopic appearance | Limited |
| Gombe Urethrographic Score | RUG | Urethrographic features | Limited |
The U-score is a simplified refinement of the UREThRAL stricture score.[21] Wiegand and Brandes (2012) derived the original score from 95 consecutive open urethroplasties by a single surgeon, combining etiology, total number of strictures, retention (luminal obliteration), anatomic location and length; mean scores rose with surgical complexity, from 5.78 for excision and primary anastomosis to 14.97 for combined flaps and grafts (p < 0.0001).[42]
LSE versus U-score. In a retrospective single-surgeon cohort of 187 single-stage anterior urethroplasties (mean follow-up 21 months; 46 recurrences), both scores correlated with surgical complexity, but only LSE was associated with recurrence; LSE ≥7 carried HR 2.7 versus lower scores.[18] The U-score and LSE system both incorporate etiology.[18][42] In a retrospective comparison of 187 anterior urethroplasty patients, both scores correlated with surgical complexity, while only the LSE score was associated with recurrence risk.[18]
Management
Indications for Intervention. Intervention is indicated for any of the following:
- Symptomatic LUTS attributable to stricture
- Acute urinary retention
- Recurrent urinary tract infections
- Bladder calculi
- Rising post-void residual threatening upper tract function
- Subclinical strictures in patients undergoing transurethral procedures (to facilitate access)
Contraindications.
- Avoid DVIU as definitive treatment for penile or long (>2 cm) strictures; durable success is poor.[1]
- Avoid genital skin grafts or flaps for LS-associated reconstruction. EAU 2026 strongly recommends against genital skin in augmentation penile urethroplasty for men with lichen sclerosus-related strictures; reported recurrence after genital-skin graft or flap augmentation in this population is 50–100%.[23]
- Avoid hair-bearing skin for urethral substitution because intraurethral hair can cause calculi, infection and obstructed flow. Guidelines reserve an exception only when no suitable alternative exists.[1][23]
- Single-stage tubularized graft urethroplasty: AUA advises against an unsupported tubularized graft , but distinguishes a graft fully supported by vascular tissue, such as a buccal graft in the fossa navicularis supported by glanular spongiosum. EAU recommends against single-stage tubularized grafts ; onlay or staged repair generally provides a better-supported graft bed.[1][23]
Observation
Asymptomatic, subclinical strictures may be managed with active surveillance. Intervention is deferred until symptoms develop or lumen narrows to a clinically relevant degree.
Endoscopic Management: Dilation and DVIU
Direct Visual Internal Urethrotomy (DVIU) and urethral dilation are the most commonly performed procedures for stricture disease. AUA 2023 allows either, or urethroplasty, as initial treatment of a short (<2 cm) bulbar stricture [1]; EAU 2026 limits endoscopy to a primary, single, short (<2 cm), non-obliterative bulbar stricture and, separately, a short veil-like recurrence after bulbar urethroplasty[23].
Limitations:
- Repeated standard endoscopic treatment has poor durability. AUA advises urethroplasty rather than repeated endoscopic management after failed dilation or DVIU , noting failure rates above 80% for another endoscopic procedure; EAU advises against more than two DVIU/dilatations when urethroplasty is viable .[1][11][23][30]
- Longer strictures are poor candidates for standard dilation/DVIU: AUA reports about 20% success for bulbar strictures over 4 cm versus over 80% for buccal mucosa graft urethroplasty; EAU advises against DVIU/dilatation as sole treatment for strictures over 2 cm .[1][23][30]
- Penile strictures are unlikely to respond to dilation or urethrotomy
- Repeated DVIU or dilation can increase stricture length and complexity and delay urethroplasty.[23]
Urethroplasty may be offered as primary treatment even for short bulbar strictures when the patient prefers definitive repair, understands the trade-off of higher short-term morbidity for superior durability.[1]
Drug-Coated Balloons
Optilume’s FDA indication covers adult men with symptomatic anterior strictures ≤3 cm.[27] Guideline selection is narrower: AUA 2023 allows dilation or DVIU with a DCB for recurrent bulbar strictures <3 cm ,[30] and EAU 2026 strongly recommends DCB for recurrent bulbar strictures <3 cm after at least two endoscopic treatments when urethroplasty is unsuitable or declined.[28] ROBUST III compared DCB with standard endoscopy, not urethroplasty. In the initially randomized DCB arm (n = 79), three-year Kaplan–Meier freedom from reintervention was 71.9%; among 56 participants with three-year IPSS data, 27 (48%) had at least 30% symptom-score improvement without retreatment, and the control arm had no follow-up beyond one year.[24][27][28][29][46]
The label requires abstinence or condom use for 30 days, plus highly effective contraception and avoiding fathering a child for at least six months when the partner could become pregnant. Treat active UTI first; paclitaxel hypersensitivity and urologic implants such as an AUS or penile implant are contraindications. Repeated treatment of the same stricture is insufficiently studied.[27] Paclitaxel was detectable in semen for up to six months in ROBUST III, which is the basis for the contraception advice; EAU considers evidence outside the ROBUST indications (penile, membranous, bladder-neck, VUAS, longer or first-time strictures) too limited for recommendations.[28] See the DCB technique and counseling page.
Intralesional adjuncts such as mitomycin C are a different intervention. EAU advises their use only within clinical trials because dose, volume, technique and long-term safety are uncertain. AUA notes lower recurrence with steroid injection at DVIU (not statistically significant, short follow-up) and with mitomycin (limited long-term data).[28][30]
Urethroplasty
Urethroplasty is a reconstructive treatment for urethral stricture disease; AUA also permits initial dilation or DVIU for a selected short (<2 cm) bulbar stricture.[1] It is recommended upfront for long bulbar strictures, penile strictures, and recurrent strictures after failed endoscopic management.
By Stricture Location and Length
| Stricture pattern | Treatment discussion | Evidence boundary |
|---|---|---|
| Primary, single, short non-obliterative bulbar | Dilation/DVIU or urethroplasty after counselling | Options are not equivalent in long-term durability |
| Long bulbar | Usually graft augmentation/substitution; tailor to scar and viable plate | — |
| Penile / LS-associated | Tailored single-stage or staged reconstruction; avoid genital skin in LS | — |
| Recurrent after standard endoscopy | Urethroplasty; selected short bulbar cases may consider drug-coated balloon | OPEN favoured urethroplasty for reintervention; ROBUST III did not compare with urethroplasty |
| Panurethral / complex | Specialist reconstruction or perineal urethrostomy according to goals | Discuss morbidity and the possibility of staged treatment |
Excision and Primary Anastomosis (EPA)
Anastomotic repair is an option for selected short bulbar strictures when a tension-free repair is feasible. Transecting EPA is particularly relevant to short traumatic obliteration; non-transecting or graft-based approaches may reduce penile complications in other short bulbar strictures. Prior TURP alone is not an indication to transect the urethra.[1]
At 12 months in the Scandinavian randomized trial of 151 men with bulbar strictures ≤2 cm and no prior urethroplasty, transecting EPA produced more patient-reported penile complaints on a trial-specific questionnaire, particularly shortening and reduced glans filling, than BMG.[25] Postoperative IIEF-5 scores did not differ.[25]
Substitution (Graft/Flap) Urethroplasty
Indicated for longer strictures, multiple prior repairs, compromised local tissue, and penile involvement.
Oral mucosa is the first-choice graft material:[1]
- Buccal mucosal graft (BMG) and lingual mucosal graft (LMG) are alternatives; pooled success did not differ significantly (RR 1.03, 95% CI 0.96–1.10)[1]
- Lingual mucosa is thinner and may offer advantages for distal urethral and meatal reconstruction[1][14]
- Buccal mucosa has a thick epithelium resistant to a wet environment, a thin vascularized lamina propria, and an accessible harvest site. Counsel about donor-site tightness, numbness, swelling, and difficulty opening the mouth.[23]
Technique selection by stricture characteristics:[14]
| Technique | Indication |
|---|---|
| Ventral or dorsal onlay BMG | Bulbar strictures; an eight-study meta-analysis of 655 patients found similar reported success (RR 1.00, 95% CI 0.94–1.06) and an association between ventral onlay and less transient ED (RR 0.24, 95% CI 0.08–0.67)[47] |
| Barbagli dorsal onlay | Bulbar; graft quilted to tunica albuginea |
| Two-sided dorsal + ventral onlay (Palminteri) | Obliterative bulbar segments |
| Augmented anastomotic urethroplasty | Combining excision with onlay for moderate-length bulbar strictures |
| Asopa technique (dorsal inlay via ventral sagittal urethrotomy) | Penile strictures |
| Kulkarni technique (dorsolateral onlay, one-sided dissection) | Penile and panurethral strictures |
| Penile fasciocutaneous flap (Orandi) | Penile strictures — especially without LS |
For complex multi-segment strictures (>10 cm spanning penile and bulbar urethra), reconstruction uses one-stage or multi-stage techniques with OMG, penile fasciocutaneous flaps, or combinations. These cases should be performed at high-volume reconstructive centers.[1]
The OPEN Trial. The landmark OPEN trial (Goulao et al., Eur Urol 2020) randomized men with recurrent bulbar urethral stricture to open urethroplasty versus endoscopic urethrotomy. While both treatments improved voiding symptoms similarly at 24 months, urethroplasty resulted in significantly fewer reinterventions (hazard ratio 0.52, 95% CI 0.31–0.89).[11][12] Superiority was not shown for the primary symptom endpoint.
Alternative Management
Perineal urethrostomy, a permanent perineal stoma, may be offered as a definitive alternative to urethroplasty for patients with complex strictures, multiple failed repairs, significant medical comorbidities precluding long surgery, or patient preference. The stoma provides a new outlet, but can develop stenosis and requires follow-up; revision may be needed over time.[1]
Suprapubic cystostomy can provide urethral rest before reconstruction for men dependent on a urethral catheter or intermittent self-dilation. EAU 2026 summarizes a minimum three-month rest interval after urethral manipulation before urethroplasty, with longer rest when infection or inflammation persists.[1][23]
Outcomes & Efficacy
Compare like-for-like outcomes: anatomic patency, absence of reintervention, symptom improvement and sexual function answer different questions. OPEN demonstrated fewer reinterventions with urethroplasty in recurrent bulbar disease without superiority on its primary symptom endpoint; ROBUST III demonstrated better short-term anatomy than standard endoscopy in a selected recurrent population.[11][24]
An international modified Delphi consensus under the EAU Young Academic Urologists Trauma and Reconstructive Urology Working Party (87 experts in round 1, 65 in round 2) proposed the "stricture-fecta" as a standardized definition of success after urethral reconstruction: freedom from stricture retreatment, no significant impact on continence or sexual function assessed with validated instruments, and patient satisfaction.[43]
Use the study comparison and linked technique pages for the relevant population and follow-up interval.
Complications
Minor postoperative events (common): UTI, perineal pain, hematuria, dysuria, temporary urinary retention.
Serious postoperative harms:
- Sexual/penile complications. Counsel about erectile symptoms, shortening, glans filling and ejaculation separately; no technique guarantees preservation[25]
- Urethrocutaneous fistula. Possible after urethroplasty; assess drainage, infection and distal obstruction. Persistent fistula may require repair.
Complications of neglected or long-standing stricture:
- Fournier's gangrene. Rare; from urinary extravasation in neglected or infected strictures
- Renal failure. From chronic obstructive uropathy
- Malignant degeneration. Rare squamous cell carcinoma arising in long-standing inflammatory strictures (particularly LS-associated); biopsy has been suggested when examination, cystoscopy, imaging or the clinical course of a refractory stricture is atypical, to avoid mistaking a primary urethral cancer for advanced scar[34]
Follow-Up
Before catheter removal after urethroplasty, EAU 2026 strongly recommends urethrography to assess for extravasation; persistent, significant extravasation calls for continued or renewed catheter drainage and repeat imaging after one week.[23]
After urethroplasty, EAU 2026 recommends at least one year of follow-up , flexible cystoscopy at three months , and subsequent surveillance adjusted to recurrence risk . In the EAU protocol, low-risk repairs (bulbar or bulbomembranous anastomotic urethroplasty without prior radiotherapy, hypospadias or LS) get uroflowmetry and PROMs at 3, 12 and 24 months with cystoscopy or RUG at three months, and may stop at two years. Standard-risk repairs (graft or flap urethroplasty, penile, LS, post-radiation, non-traumatic posterior) add anatomic evaluation at 12 and 24 months and follow-up to five years, longer after penile and substitution repairs. Uroflowmetry, post-void residual and patient-reported urinary and sexual outcomes complement anatomic assessment; worsening symptoms or flow warrant reassessment.[23]
Change in maximum flow rate from the preoperative value has been studied as a noninvasive screen for recurrence. In 125 men with uroflowmetry before and after urethroplasty (2000 to 2009), maximum flow rose by a mean of 19.2 ± 11.7 mL/s in men without recurrence on retrograde urethrography and by 0.2 ± 6.4 mL/s in failed repairs; a rise of less than 10 mL/s would have detected recurrence with 92% sensitivity and 78% specificity.[44]
Record anatomic patency, freedom from further intervention, and the patient's functional outcome separately. Most recurrences appear in the first year; EAU reports that recurrence after five years has been observed in up to 15% of cases, particularly after augmentation urethroplasty, so tell patients to return if symptoms recur.[23] A small-caliber (<17 Fr) recurrence at three-month cystoscopy predicts later intervention risk. Continue longer surveillance when the repair, tissue quality or clinical course warrants it.[23]
In an older single-center review of 107 bulbar substitution repairs (45 dorsal skin graft, 50 buccal mucosal graft, 12 augmented end-to-end urethroplasty; mean follow-up 74 months), 22 (20%) failed: 12 (11% of the cohort) across the entire grafted area and 10 (9%) as a focal fibrous ring at the graft-to-urethral-plate junction, evenly split between the distal and proximal anastomosis. Urethrography, sonourethrography and urethroscopy distinguished the two patterns.[35] Recording whether a recurrence is focal or spans the graft can help decide between a limited and a full repeat repair.
Patient-Reported Outcomes
In a retrospective cohort of 214 men who underwent anterior urethroplasty, 21% reported presenting voiding symptoms not addressed by the AUASI, most often spraying of the stream (13%) and dysuria (10%).[36] A disease-specific instrument (PROM-USS) was developed and piloted in 85 men undergoing urethroplasty at five centers to address this gap and has since had an Italian-language validation; it does not assess erectile or ejaculatory function.[37][38]
A prospective cohort of 357 patients assessed before and 6 months after urethroplasty (2012 to 2018) paired cystoscopic patency with satisfaction, voiding, urinary quality of life, sexual function, penile appearance and genitourinary pain. At 6 months, 95.9% were stricture-free on cystoscopy and 80% were satisfied; IPSS fell from 19.3 to 6.0 and pain scores improved. Among the 357 questionnaire completers (of 828 patients undergoing urethroplasty), mean erectile function did not change at six months, but 12.0% reported new erectile dysfunction, 7.1% new ejaculatory dysfunction, and 6.7% and 3.1% bothersome loss of penile length or curvature.[45]
Ejaculatory function is assessed separately from erectile function (IIEF/SHIM), for example with the seven-item ejaculatory domain of the Male Sexual Health Questionnaire (MSHQ-EjD), which covers frequency, force, volume, pleasure, pain and bother. In a prospective cohort of 43 men undergoing anterior urethroplasty, 25% had poor ejaculatory function before surgery; the overall ejaculatory score did not change significantly at a mean follow-up of 8.1 ± 6.0 months (25.54 to 26.94, p = 0.17), but nearly 36% of men with reduced baseline function reported improvement.[39]
Practice Patterns and Guideline Adherence
In a survey of Turkish urologists conducted in 2021 and published in 2026, 222 of 2,078 members responded. For primary 1–2 cm bulbar strictures, 7% selected urethroplasty and 72% DVIU with dilation[16]; current AUA and EAU guidance permits initial endoscopy in selected short bulbar disease[1][23]. For recurrent cases, 76.5% reported DVIU at least four times, contrary to guidance against repeated standard endoscopy when urethroplasty is viable.[1][16][23]
In a 2005–2022 claims cohort, the proportion receiving urethroplasty after failed initial endoscopic treatment rose by 0.62 percentage points per year; receipt of urethroplasty was higher after the 2016 AUA guideline (adjusted HR 2.57, 95% CI 2.07–3.19).[13]
In an international survey of ESGURS members (49/88 responded), 45/49 respondents (91.8%) had performed graft urethroplasty in the preceding two years, and 26/47 (55.3%) who answered the volume question reported performing >20 urethroplasties in the preceding year.[15] Academic urologists demonstrate better guideline adherence than non-academic peers.[16]
Selected evidence
OPEN · 2020[11]; ROBUST III · 1 year[24]. The comparison below preserves the study-specific population, denominator, endpoint and uncertainty.
| Study and population | Comparison and results | Use and limitations |
|---|---|---|
| OPEN · 2020 Men with recurrent bulbar stricture after at least one prior intervention. Randomized n=222 | Urethroplasty vs urethrotomy Repeated patient-reported voiding symptom score · Over 24 months Symptoms improved in both groups. Mean difference −0.36; 95% CI −1.74 to 1.02; no superiority on the primary symptom endpoint. Reintervention · 24 months 15 men after urethroplasty vs 29 after urethrotomy. Hazard ratio 0.52; 95% CI 0.31–0.89. | Urethroplasty offers a durability advantage despite similar short-term symptom improvement.
|
| ROBUST III · 1 year Adult men with recurrent anterior stricture ≤3 cm and ≤12 Fr after ≥2 endoscopic treatments; IPSS ≥11 and Qmax <15 mL/s. Randomized n=127 | Paclitaxel-coated balloon vs dilation/direct-vision internal urethrotomy Anatomic success: passage of ≥14 Fr instrument · 6 months 75% vs 27%. P<.001. | An option for selected recurrent short bulbar disease.
|
See Also
- Urethral Reconstruction treatment atlas
- Male Urethroplasty
- Excision and Primary Anastomosis (EPA)
- Direct Visual Internal Urethrotomy (DVIU)
- Drug-Coated Balloon
- Blandy Perineal Urethrostomy
- Posterior Urethral Stenosis
- History of Urethral Surgery
- On WHITWIKI, the sister site for GU oncology: Pelvic Radiation Late Effects.
Podcasts
References
1. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. "Urethral Stricture Disease Guideline Amendment." J Urol. 2023;210(1):64–71. doi:10.1097/JU.0000000000003482
2. Tritschler S, Roosen A, Füllhase C, Stief CG, Rübben H. "Urethral Stricture: Etiology, Investigation and Treatments." Dtsch Arztebl Int. 2013;110(13):220–226. doi:10.3238/arztebl.2013.0220
3. Palminteri E, Berdondini E, Verze P, et al. "Contemporary Urethral Stricture Characteristics in the Developed World." Urology. 2013;81(1):191–196. doi:10.1016/j.urology.2012.08.062
4. de Farias RB, Neto FTL, de Aguiar Cavalcanti G, Martins FE, Lima SVC. "Evaluation of the Etiological Profile, Age and Findings in Retrograde and Voiding Urethrocystography of Men With Urethral Stricture." Sci Rep. 2025;15(1):5935. doi:10.1038/s41598-025-89389-z
5. Astolfi RH, Lebani BR, Krebs RK, et al. "Specific Characteristics of Urethral Strictures in a Developing Country (Brazil)." World J Urol. 2019;37(4):661–666. doi:10.1007/s00345-019-02696-9
6. Lumen N, Hoebeke P, Willemsen P, et al. "Etiology of Urethral Stricture Disease in the 21st Century." J Urol. 2009;182(3):983–987. doi:10.1016/j.juro.2009.05.023
7. Gutierrez WR, Luo Y, Dahmoush L, et al. "Deep Phenotyping the Anterior Urethral Stricture: Characterizing the Relationship Between Inflammation, Fibrosis, Patient History, and Disease Pathophysiology." J Urol. 2024;212(1):153–164. doi:10.1097/JU.0000000000003962
8. Wong SS, Aboumarzouk OM, Narahari R, O'Riordan A, Pickard R. "Simple Urethral Dilatation, Endoscopic Urethrotomy, and Urethroplasty for Urethral Stricture Disease in Adult Men." Cochrane Database Syst Rev. 2012;12:CD006934. doi:10.1002/14651858.CD006934.pub3
9. Grimes MD, Tesdahl BA, Schubbe M, et al. "Histopathology of Anterior Urethral Strictures: Toward a Better Understanding of Stricture Pathophysiology." J Urol. 2019;202(4):748–756. doi:10.1097/JU.0000000000000340
10. King C, Rourke KF. "Urethral Stricture Is Frequently a Morbid Condition: Incidence and Factors Associated With Complications Related to Urethral Stricture." Urology. 2019;132:189–194. doi:10.1016/j.urology.2019.07.013
11. Goulao B, Carnell S, Shen J, et al. "Surgical Treatment for Recurrent Bulbar Urethral Stricture: A Randomised Open-Label Superiority Trial of Open Urethroplasty Versus Endoscopic Urethrotomy (The OPEN Trial)." Eur Urol. 2020;78(4):572–580. doi:10.1016/j.eururo.2020.06.003
12. Pickard R, Goulao B, Carnell S, et al. "Open Urethroplasty Versus Endoscopic Urethrotomy for Recurrent Urethral Stricture in Men: The OPEN RCT." Health Technol Assess. 2020;24(61):1–110. doi:10.3310/hta24610
13. Cabral JD, Alkassis M, Khalafalla K, et al. "Contemporary Trends in the Management of Urethral Stricture Disease in the Era of the AUA Guidelines." Urology. 2025. doi:10.1016/j.urology.2025.07.054
14. Horiguchi A. "Substitution Urethroplasty Using Oral Mucosa Graft for Male Anterior Urethral Stricture Disease: Current Topics and Reviews." Int J Urol. 2017;24(7):493–503. doi:10.1111/iju.13356
15. Campos-Juanatey F, Fes-Ascanio E, Adamowicz J, et al. "Contemporary Management of Male Anterior Urethral Strictures by Reconstructive Urology Experts — Results From an International Survey Among ESGURS Members." J Clin Med. 2022;11(9):2353. doi:10.3390/jcm11092353
16. Kaçtan Ç, Abali T, Vosoughi O, et al. "Management of Urethral Stricture: Translating Guidelines Into Clinical Practice." World J Urol. 2026;44(1):212. doi:10.1007/s00345-026-06312-5
17. Erickson BA, Flynn KJ, Hahn AE, et al. Development and validation of a male anterior urethral stricture classification system. Urology. 2020;143:241-247. doi:10.1016/j.urology.2020.03.072
18. Kurtzman JT, Kosber R, Kerr P, Brandes SB. Evaluating tools for characterizing anterior urethral stricture disease: a comparison of the LSE system and the urethral stricture score. J Urol. 2022;208(5):1083-1089. doi:10.1097/JU.0000000000002880
19. Erickson BA, Tuong MN, Zorn AN, et al. Development and validation of the Length, Segment, and Etiology anterior urethral stricture disease staging system using longitudinal urethroplasty outcomes data from the Trauma and Urologic Reconstructive Network of Surgeons. J Urol. 2025;213(4):512-523. doi:10.1097/JU.0000000000004369
20. John A, Kahokehr AA. Classification systems for anterior urethral stricture disease in men: a systematic review. World J Urol. 2021;39(3):761-769. doi:10.1007/s00345-020-03250-8
21. Eswara JR, Han J, Raup VT, et al. Refinement and validation of the urethral stricture score in categorizing anterior urethral stricture complexity. Urology. 2015;85(2):474-7. doi:10.1016/j.urology.2014.10.011
22. Alwaal A, Sanford TH, Harris CR, et al. Urethral stricture score is associated with anterior urethroplasty complexity and outcome. J Urol. 2016;195(6):1817-21. doi:10.1016/j.juro.2015.12.100
23. European Association of Urology. EAU Guidelines on Urethral Strictures. 2026, sections 3, 5, 6, 9, 10 and 11. Official full guideline.
24. Elliott SP et al. One-Year Results for the ROBUST III Randomized Controlled Trial Evaluating the Optilume Drug-Coated Balloon for Anterior Urethral Strictures. 2022. doi:10.1097/JU.0000000000002346.
25. Nilsen OJ, Holm HV, Ekerhult TO, et al. "To Transect or Not Transect: Results from the Scandinavian Urethroplasty Study, a Multicentre Randomised Study of Bulbar Urethroplasty Comparing Excision and Primary Anastomosis Versus Buccal Mucosal Grafting." Eur Urol. 2022;81(4):375–382. doi:10.1016/j.eururo.2021.12.017.
26. Baskin LS, Constantinescu SC, Howard PS, et al. Biochemical characterization and quantitation of the collagenous components of urethral stricture tissue. J Urol. 1993;150(2 Pt 2):642–647. doi:10.1016/S0022-5347(17)35572-6.
27. FDA. Optilume Urethral Drug Coated Balloon: Instructions for Use, P210020. Indications, contraindications, warnings and precautions. Approved labeling.
28. European Association of Urology. Urethral Strictures: Disease Management in Males. 2026. Drug-coated balloon dilatation and intralesional injections. Guideline.
29. Srikanth P, DeLong J, Virasoro R, Elliott SP. "A Drug-Coated Balloon Treatment for Urethral Stricture Disease: Three-Year Results from the ROBUST III Study." J Endourol. 2025;39(9):968-974. doi:10.1089/end.2024.0718
30. American Urological Association. Urethral Stricture Disease: AUA Guideline (published 2016; amended 2023), unabridged version. Guideline.
31. Mundy AR, Andrich DE. Posterior urethral complications of the treatment of prostate cancer. BJU Int. 2012;110(3):304-325. doi:10.1111/j.1464-410X.2011.10864.x
32. Dosanjh A, Harvey P, Baldwin S, et al. High-intensity Focused Ultrasound for the Treatment of Prostate Cancer: A National Cohort Study Focusing on the Development of Stricture and Fistulae. Eur Urol Focus. 2021;7(2):340-346. doi:10.1016/j.euf.2019.11.014
33. Elliot S, Brandes SB. Etiology, Histology, and Classification of Urethral Stricture Disease. In: Brandes SB, Morey AF, eds. Advanced Male Urethral and Genital Reconstructive Surgery. 2nd ed. Humana Press; 2014:95-102. doi:10.1007/978-1-4614-7708-2_8
34. Hudak SJ, Morey AF. Reconstruction of Failed Urethroplasty. In: Brandes SB, Morey AF, eds. Advanced Male Urethral and Genital Reconstructive Surgery. 2nd ed. Humana Press; 2014:373-386. doi:10.1007/978-1-4614-7708-2_25
35. Barbagli G, Guazzoni G, Palminteri E, Lazzeri M. "Anastomotic Fibrous Ring as Cause of Stricture Recurrence After Bulbar Onlay Graft Urethroplasty." J Urol. 2006;176(2):614-619. doi:10.1016/j.juro.2006.03.097
36. Nuss GR, Granieri MA, Zhao LC, Thum DJ, Gonzalez CM. "Presenting Symptoms of Anterior Urethral Stricture Disease: A Disease Specific, Patient Reported Questionnaire to Measure Outcomes." J Urol. 2012;187(2):559-562. doi:10.1016/j.juro.2011.10.043
37. Jackson MJ, Sciberras J, Mangera A, et al. "Defining a Patient-Reported Outcome Measure for Urethral Stricture Surgery." Eur Urol. 2011;60(1):60-68. doi:10.1016/j.eururo.2011.03.003
38. Barbagli G, Romano G, Sansalone S, Lazzeri M. "Italian Validation of the English PROM-USS-Q Questionnaire in Patients Undergoing Anterior Urethroplasty." Urologia. 2011;78(2):98-107. doi:10.5301/RU.2011.8334
39. Erickson BA, Granieri MA, Meeks JJ, McVary KT, Gonzalez CM. "Prospective Analysis of Ejaculatory Function After Anterior Urethral Reconstruction." J Urol. 2010;184(1):238-242. doi:10.1016/j.juro.2010.03.038
40. Johnson MH, Brandes SB, Coplen DE. Pediatric Urethral Strictures. In: Brandes SB, Morey AF, eds. Advanced Male Urethral and Genital Reconstructive Surgery. 2nd ed. Humana Press; 2014:519-529. doi:10.1007/978-1-4614-7708-2_37
41. Gupta R, Wang H, Gupta S, An W, Xu T, Lal N, et al. "Current Potential Outcomes of Buccal Mucosal Graft Anterior Urethroplasty for Male Urethral Stricture: A Single-Centre Study in Nepal." Cureus. 2024;16(9):e70379. doi:10.7759/cureus.70379
42. Wiegand LR, Brandes SB. "The UREThRAL Stricture Score: A Novel Method for Describing Anterior Urethral Strictures." Can Urol Assoc J. 2012;6(4):260-264. doi:10.5489/cuaj.12048
43. Mantica G, Verla W, Frankiewicz M, Cocci A, Chierigo F, Białek Ł, et al. "Toward Standardized Outcome Reporting in Urethral Reconstruction: Development of the 'Stricture-fecta' Through an International Modified Delphi Consensus." Eur Urol Open Sci. 2026;83:120-124. doi:10.1016/j.euros.2025.11.008
44. Erickson BA, Breyer BN, McAninch JW. "Changes in Uroflowmetry Maximum Flow Rates After Urethral Reconstructive Surgery as a Means to Predict for Stricture Recurrence." J Urol. 2011;186(5):1934-1937. doi:10.1016/j.juro.2011.07.010
45. Redmond E, Bekkema J, Rourke K. "Comprehensive Prospective Assessment of Patient-reported Outcomes Following Urethroplasty." Urology. 2020;141:162-167. doi:10.1016/j.urology.2020.02.034
46. Ontario Health (Quality). "Paclitaxel-Coated Balloon Dilation for Adults With Recurrent Bulbar Urethral Stricture: A Health Technology Assessment." Ont Health Technol Assess Ser. 2026;26(4):1–160. PMID:42311576.
47. Hassan AA, Soliman AM, Shouman HA, et al. "Dorsal- vs ventral-onlay buccal mucosal graft urethroplasty for urethral strictures: a meta-analysis." BJU Int. 2025;136(3):385–394. doi:10.1111/bju.16811.