Vesicourethral Anastomotic Stenosis
Vesicourethral anastomotic stenosis (VUAS) is fibrotic narrowing at the surgical anastomosis between the bladder neck and urethra after radical prostatectomy, or less commonly after radical cystectomy with orthotopic neobladder. It is often mislabeled "bladder neck contracture," but it is anatomically and reconstructively different from native bladder neck contracture after benign outlet surgery.
The reconstructive issue is proximity to the external sphincter. A millimeter too distal can convert obstruction into severe stress urinary incontinence; repeated endoscopic procedures can make later reconstruction and artificial urinary sphincter (AUS) implantation harder.
For endoscopic and robotic/open reconstructive options and the treatment database, see the VUAS treatment atlas.
VUAS vs BNC
| Feature | VUAS | Native BNC |
|---|---|---|
| Setting | Radical prostatectomy, salvage prostatectomy, neobladder anastomosis | TURP, HoLEP, vaporization, simple prostatectomy, bladder-neck incision |
| Anatomy | Scar at neovesicourethral anastomosis | Scar at native bladder neck / proximal prostatic fossa |
| Prostate | Absent | Present or surgically excavated |
| Sphincter risk | High; rhabdosphincter immediately distal | Lower; sphincter usually farther distal |
| Endoscopic durability | Often temporizing; recurrence common | Patency varies by technique and follow-up; repeat treatment may be needed[14] |
| Reconstruction | Robotic/open reanastomosis, bladder flap, graft, combined abdominoperineal repair | Y-V plasty or bladder-neck plasty |
Epidemiology
Some comparative prostatectomy cohorts report lower VUAS rates after robotic than open surgery, and VUAS remains a consequential survivorship complication; a nine-study meta-analysis of suturing during radical prostatectomy did not detect a stricture-rate difference between continuous and interrupted anastomoses (OR 1.00, 95% CI 0.42–2.40).[1][2][3][36] Reported rates depend on the definition: series that define stenosis as inability to pass a 16-18 Fr scope, or that count only symptomatic cases needing treatment, give different numbers. A single-institution registry of 17,904 men after prostatectomy (1987–2013; prior pelvic radiotherapy excluded) found symptomatic VUAS that blocked a 17 Fr cystoscope in 851 (4.8%); robotic surgery was associated with lower odds (OR 0.39).[1]
Approximate ranges from individual series:
| Setting | Typical incidence |
|---|---|
| Open radical prostatectomy | About 2-11% (2.6%, 9% and 11% in three single-center series);[2][3][28] many modern series are lower |
| Laparoscopic / minimally invasive (running single-knot suture) | About 1.4% (2,115 men, mixed laparoscopic and robotic)[4] |
| Robot-assisted radical prostatectomy | About 0-1.4% in single-center comparisons[2][3] |
| Salvage prostatectomy / radiated field | Higher risk, higher recurrence, higher complication burden |
Most cases present within the first year after prostatectomy (median 3.4 months in the registry above; 78% within a year in a running-suture series); late presentation suggests progressive radiation injury, recurrent instrumentation, infection, or a missed earlier stenosis.[1][4]
Pathophysiology
VUAS is an anastomotic healing failure. The scar is usually circumferential and reflects some combination of:
- Poor mucosal apposition at the bladder-to-urethra suture line
- Ischemia of bladder neck or urethral stump
- Anastomotic urine leak and secondary-intention healing
- Hematoma, infection, or pelvic collection
- Excessive suture tension or tissue devascularization
- Radiation-induced endarteritis and progressive fibrosis
- Repeated endoscopic manipulation
Protective technical principles are the same as every GU anastomosis: healthy bleeding edges, mucosa-to-mucosa approximation, no tension, no urinary leak, and catheter drainage long enough for epithelial healing.[5]
As a historical example from open retropubic prostatectomy, one single-surgeon series compared sequential, non-randomized cohorts before and after three technical changes — reconstructing the bladder neck to about 28 Fr, placing the posterior 6-o'clock vesicourethral suture on mild traction before its bladder bites so the existing suture line could be inspected and corrected, and displacing the bladder to keep the anastomosis in view while tying — and reported BNC in 31 of 548 men (5.7%) beforehand versus 1 of 429 (0.2%) afterward.[29]
Risk Factors
| Category | Risk factors |
|---|---|
| Patient | Current smoking (the strongest independent predictor in one series), diabetes, hypertension, coronary artery disease, higher BMI, larger prostate volume[1][28] |
| Preoperative | Prior pelvic radiation, salvage prostatectomy setting; prior TURP is a risk factor in some series but not others[4][28] |
| Operative | Blood loss, transfusion, prolonged operative time, non-nerve-sparing surgery, poor mucosal apposition |
| Postoperative | Urine leak, pelvic hematoma/collection, infection, prolonged catheterization |
| Oncologic treatment | Adjuvant or salvage radiation, brachytherapy plus EBRT, local recurrence requiring additional treatment |
Retrospective series associate radiation, surgical approach, transfusion or blood loss, anastomotic urine leak, comorbidity, and operative era with VUAS; in Webb et al.’s 200-patient prostatectomy comparison, ordinary leakage with intact mucosal apposition was considered unlikely to contribute to BNC, whereas prolonged leakage from an anastomotic gap was proposed as a scarring mechanism.[1][2][3][6]
Clinical Presentation
Common presentations:
- Slow stream, straining, hesitancy
- Acute or chronic urinary retention
- Recurrent UTI
- Overflow leakage
- Worsening urgency from obstruction
- Difficulty passing catheter after prostatectomy
- Incontinence that becomes obvious after the obstruction is opened
VUAS can mask stress incontinence. A severely stenotic anastomosis may function as a pathologic "cork"; once opened, sphincteric incompetence becomes apparent.
Diagnosis
Core evaluation
- Cystoscopy. Diagnostic; documents caliber, length, obliteration, sphincter proximity, radiation changes, stones, and catheterizability
- RUG / VCUG. Maps the anastomosis, bladder neck funneling, urethral length, and whether a lumen permits endoscopic access; combine RUG with VCUG for nearly or completely obliterative stenosis to visualize the proximal urethra and estimate defect length.[37]
- Uroflowmetry and PVR. Functional obstruction baseline
- Urinalysis / culture. Infection must be treated before incision or reconstruction
- PSA / cancer status. Biochemical recurrence can alter priorities and radiation planning
- Urodynamics. When incontinence, poor compliance, detrusor underactivity, or mixed storage symptoms will affect reconstruction or AUS planning
- Cross-sectional imaging. Selected radiated, recurrent, fistula, pelvic collection, or salvage cases
For reconstructive planning, define three things: is there a lumen, where is the sphincter, and what is the continence plan?
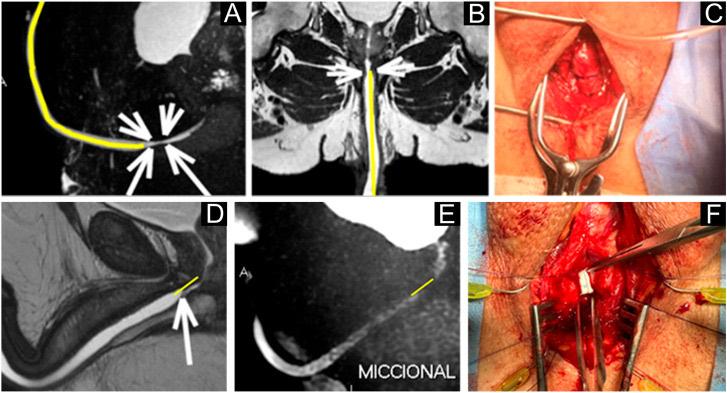
Dynamic magnetic resonance imaging of the urethra used for surgical planning of vesicourethral anastomotic stenosis. (A, B, D, E) Images in different planes show the stenotic segment (arrows), with its length and caliber measured (yellow lines). (C, F) Intraoperative views confirm the location and extent of the stenosis, consistent with the MRI measurements. From Fiedler G, et al. Int Braz J Urol. 2026;52(1):e20250264, Figure 4 (CC BY 4.0).[32]
Management
Initial endoscopic treatment
Endoscopic therapy is first-line for first-time nonobliterative VUAS: the EAU weakly recommends visually controlled dilation or DVIU and strongly recommends avoiding deep incisions at 6 and 12 o’clock;[14] the AUA states that surgeons may perform dilation, vesicourethral incision, or transurethral resection .[7] The EAU strongly recommends against endoluminal treatment of complete obliteration.[7][14] Expect temporizing results. Across 40 studies (1,452 men), pooled freedom from recurrence at end of follow-up (median 23.7 months) was 72.8%, falling to 62.9% after publication-bias adjustment; radiotherapy was associated with lower success.[19] Among men treated for VUAS in the registry cohort, retreatment was needed in 34% at 1 year and 42% at 5 years.[1]
| Technique | Role |
|---|---|
| Dilation | Least invasive; useful for short, soft, traversable stenosis; high recurrence if used alone for dense scar |
| Cold knife / Collins knife incision | Incisions commonly placed at 3 and 9 o'clock to open the ring while avoiding rectum and dorsal venous complex |
| Laser incision | Precise cutting and hemostasis; avoid thermal excess near sphincter |
| Resection | Selective use for bulky scar; repeated aggressive resection risks sphincter injury |
Patients must be counseled before the first incision that relief of obstruction can reveal or worsen stress incontinence.
Older series explored a different strategy for an obliterated anastomosis: endoscopic recanalization followed by a permanent urethral stent (UroLume) across the repair, then staged AUS once the stent had epithelialized. In one series, 9 men treated this way after multiple failed incisions had pad use fall from a mean of 6.5 to 0.7 per day, with one recurrent contracture managed by placing a second, overlapping stent.[30] In a second series, 12 men with total outlet obliteration underwent recanalization; 10 re-obliterated, 9 were restented, and of the 8 who went on to AUS placement, 2 needed repeat endoscopic treatment for stent tissue ingrowth.[31] This recanalize-and-stent approach is dated. EAU 2026 strongly recommends against endoluminal treatment of a completely obliterated VUAS and weakly recommends against stents for posterior urethral stenosis.[14]
Adjuncts and endoscopic reconstruction
Adjunctive techniques are most relevant for recurrent VUAS:
- Mitomycin C: retrospective series report patency but also severe necrosis/fistula complications, and data for VUAS conflict. The AUA describes conflicting data for mitomycin in recurrent VUAS and calls for further study.[38] The EAU found no trial comparing endoluminal treatment with and without injections in posterior stenosis, cites serious grade 3 events in 4 of 55 patients (7%: osteitis pubis, bladder-neck necrosis, rectourethral fistula, three needing diversion), and states that mitomycin should not be used outside a clinical trial.[8][14][15][20] A separate uncontrolled 123-patient BNC series reported 82.1% patency at 12 months after one balloon dilation plus incision without injections.[10]
- Triamcinolone: used by some centers to reduce scar recurrence; evidence remains heterogeneous.
- TUITMR: transurethral incision with transverse mucosal realignment advances healthy mucosa across the scar using an endoscopic suturing device; in a single-surgeon series of 10 VUAS and 9 BNC patients, 17/19 (89%) passed a 17 Fr cystoscope after one procedure at the four-month assessment; median overall follow-up was six months, and no de novo incontinence was reported.[9] VUAS-specific success was not separately reported.[9]
- Endoscopic BMG / mucosal resurfacing: emerging strategy for selected short-segment recurrent stenosis; limited comparative data.
When to stop repeating endoscopy
Recurrent stenosis after one well-performed endoscopic treatment may justify a second attempt. Repeated cycles of incision/resection can injure the rhabdosphincter, create false passages, worsen incontinence, and compromise future AUS cuff sites. A history of two or more prior endoscopic procedures predicts failure in BNC/VUAS cohorts.[10]
Refer early when:
- Obliterative VUAS or no safe lumen
- Radiation-associated stenosis
- Recurrent VUAS after one or two endoscopic procedures
- Concurrent rectovesical fistula, pubic osteomyelitis, stones, or severe radiation cystitis
- Need for staged AUS planning
- Poor bladder compliance or devastated outlet
Robotic and Open Reconstruction
The 2023 AUA urethral stricture guideline conditionally recommends that surgeons may perform open or robotic reconstruction for recalcitrant bladder-neck stenosis or post-prostatectomy VUAS (Grade C evidence).[7] Reconstruction should be done in high-volume reconstructive settings because the operation is about both patency and continence.
Robotic reconstruction
Robotic approaches include scar excision with primary reanastomosis, anterior bladder flap / Y-V-type reconstruction, transvesical posterior bladder-neck reconstruction, dorsal buccal grafting, and combined approaches.
| Series / approach | Key outcome |
|---|---|
| TURNS robotic reconstruction | In 32 refractory VUAS patients, 24/32 (75%) met study-defined patency (17 Fr cystoscope passage or Qmax >15 mL/s) at median 12 months; 26/32 (81%) voided per urethra, and 11/13 men without preexisting SUI remained continent.[11] |
| Extraperitoneal robotic repair | Six-patient series: extraperitoneal access was feasible, but 3/6 recurred (treated endoscopically) and 3/6 required an AUS for incontinence.[12] |
| Robotic transvesical bladder-neck reconstruction | In one 11-patient single-center series (all stenoses <2 cm; two previously radiated), circumferential scar excision and posterior mucosa-to-mucosa anastomosis left 10/11 free of further surgery for recurrent stenosis at median 22 months; no de novo SUI was reported.[13] |
Open and combined reconstruction
Open perineal, retropubic, and combined abdominoperineal approaches remain important when:
- The VUAS is obliterative or extends into membranous/bulbar urethra
- Prior radiation may warrant a gracilis or peritoneal support flap for redo VUA when bladder function is adequate and periurethral necrosis, calcification, and fistulation are absent.[14]
- Robotic abdominal access cannot achieve a tension-free urethral stump
- Pubectomy, corporal splitting, or extensive posterior urethral mobilization is required
Open or combined reconstruction often trades patency for continence. Many patients require staged AUS after urethral healing is proven. EAU 2026 weakly recommends redo vesicourethral anastomosis for obliterative or endoluminal-refractory VUAS in non-irradiated men and in irradiated men with adequate bladder function (patency 60-91% non-irradiated, 67% irradiated). It strongly advises warning that incontinence is inevitable after transperineal redo VUA, with anti-incontinence surgery considered after three to six months, and weakly suggests a retropubic approach when the man is continent beforehand.[14]
Open series report durable patency, but most men are incontinent afterward:
- Transperineal reanastomosis (15 men). Patency 14 of 15. Fourteen were incontinent beforehand, incontinence worsened in 9, and 10 received an AUS.[26]
- Abdominal, perineal or combined repair (12 men, 43% obliterated, 25% radiated). 92% were patent at median 75.5 months, but only 25% were continent.[27]
One center's VUAS algorithm
Naser-Tavakolian and Lee choose a robotic VUAS repair by stenosis caliber and whether it involves the external urinary sphincter (EUS):[5]
| Finding | Repair |
|---|---|
| Stenosis 10 Fr or wider, EUS not involved | Non-transecting bladder flap: Y-V plasty or T-plasty |
| Stenosis narrower than 10 Fr, EUS not involved | Excision with primary reanastomosis |
| Anastomosis not achievable because of fibrosis or length | Tanagho-type closure of the bladder neck with a tubularized anterior bladder flap |
| Stenosis involving or extending beyond the EUS | Combined robotic transabdominal and open transperineal repair, expecting incontinence and a later AUS |
This is a single institution's approach. The review's senior author consults for a robotic manufacturer, and its suggestion that robotic repair may have lower reported rates of de novo incontinence than open repair drew on separate early series.[5] A 2025 retrospective comparison of 18 open perineal and 10 robot-assisted VUAS repairs reported patency of 77.8% versus 80.0% (passage of a 16 Fr cystoscope or maximum flow >15 mL/s) and less de novo incontinence after robotic repair.[34] A 2026 meta-analysis pooled VUAS patency at 75% for robotic (n = 96) and 80% for open (n = 85) reconstruction; heterogeneity in techniques, endpoints, and follow-up prevents ranking the approaches.[35]
VUAS After Radiation
Radiation changes both the risk and the treatment of VUAS. It may be adjuvant or salvage radiotherapy after prostatectomy, or a salvage prostatectomy after primary radiotherapy. Bulbomembranous stenosis after primary radiotherapy is covered on Posterior Urethral Stenosis, along with radiation biology, AUS risk and the devastated outlet.
Endoscopic treatment after radiation
Avoid deep incisions at 6 o'clock (rectal injury and rectourethral fistula) and 12 o'clock (urosymphyseal fistula). Do not treat an obliterated radiated anastomosis endoscopically.[15]
| Series | Population | Outcome |
|---|---|---|
| Veerman 2022 | 90 bladder-neck incisions for VUAS after robotic prostatectomy | Recurrence 12% without radiation, versus 57% (VUAS before salvage RT), 29% (VUAS after salvage RT) and 50% (after salvage prostatectomy). Severe incontinence (more than 1 pad per day): 6% versus 16%, 10% and 29%[16] |
| Rozanski 2021 | 86 recurrent BNC or VUAS; DVIU with low-dose mitomycin C | Overall success 94% without radiation versus 76% with radiation[8] |
| Neu 2021 | 18 recalcitrant VUAS (78% radiated; median 5 prior failed treatments); incision with triamcinolone | 83% success at mean 16.3 months; complications in 28%[17] |
| Pfalzgraf 2021 | 103 endoscopically treated VUAS, 37% radiated | Success 42% with radiation versus 43% without; new incontinence 18% in both groups[18] |
The effect of radiation on endoscopic results is inconsistent across series, but meta-regression of 40 studies associated radiotherapy with lower success.[19] In the TURNS bladder-neck-contracture series treated with transurethral incision plus mitomycin C, 4/55 patients (7%) had serious adverse events, and three required or planned cystectomy.[20] The Naser-Tavakolian review attributes the osteitis pubis cases to previously irradiated patients.[20][5]
Reconstruction after radiation
- Dorsal onlay buccal graft (perineal). This is an option for selected nonobliterative stenoses: all patients in the 8-center series had a guidewire-traversable lumen.[21] The authors would not offer this repair for complete obliteration, anastomotic disruption, bladder capacity <100 cc, fistula, or radionecrosis.[21] Among 45 men after prostatectomy plus radiation (21 anastomotic and 24 bulbomembranous stenoses), 7 recurred; median follow-up among those without recurrence was 21 months. No new incontinence was reported, but 28 men were incontinent before and after repair.[21] A 2025 technique review summarizes Nikolavsky’s 18-man VUAS cohort after prostatectomy and radiation: 89% success at median 39.9 months with no de novo incontinence; the review cites a meeting video abstract for these data.[22] See Dorsal Onlay BMG for BNC / VUAS; the technique is detailed under Posterior Urethral Stenosis.
- Robotic reconstruction. A robotic transabdominal repair can limit perineal dissection, though some radiated cases still require a perineal counterincision; outcomes after radiation vary across small series:
- Bearrick 2022 (single surgeon, 15 VUAS cases within 21 posterior-obstruction repairs). The 5 radiated men had 40% complications at 30 days and 80% reintervention. Functional success was 60%, with a median of 10.5 pads per day, and 80% later received an AUS. After prostatectomy without radiation, the figures were 20% complications, 10% reintervention, 100% functional success, a median of 0 pads per day and 30% AUS placement.[23]
- TURNS series. Half of the 32 men were radiated.[11] Ivan and colleagues note that 7 of the 16 radiated men needed a perineal counterincision that could not be predicted before surgery. Counsel patients that one may be added.[24]
- Single-port robotic buccal graft urethroplasty (Liu 2022). Nine patients, eight after prostate cancer treatment; mean defect length 3.9 cm.[25] Five needed flaps (rectus abdominis in 3, omental in 1, gracilis in 1). Median operative time was 377 minutes. One recurrent stricture and one small-bowel obstruction requiring surgery occurred within 30 days; by median 11.7-month follow-up, restenosis had occurred in 3 of the 7 VUAS patients.[25][5]
- One center's routine adjuncts. Naser-Tavakolian and Lee interpose omentum between the repair and the pubic bone (rectus if omentum is unavailable). They add a gracilis flap for combined approaches and give hyperbaric oxygen (40 sessions at 2.5 ATA) to every radiated patient.[5] See Hyperbaric Oxygen Therapy for the trial evidence.
- Continence and AUS. Radiation and prior urethroplasty, especially transecting repair, increase AUS failure and explantation. See Continence, AUS and Follow-Up.
Continence Strategy
The outlet must be patent before continence surgery. The common sequence:
- Establish drainage and urethral rest, often with suprapubic tube.
- Treat or reconstruct VUAS.
- Confirm stable patency by cystoscopy and symptoms.
- Reassess stress incontinence.
- Implant AUS only after the anastomosis is stable.
The 2024 AUA/GURS/SUFU guideline calls for treatment of symptomatic VUAS before incontinence surgery and interval cystoscopy at least four to six weeks later to document improvement and stability.[33] EAU 2026 notes that AUS timing after redo VUA lacks consensus; most reports wait at least three to six months until patency is stable.[14] Evidence is insufficient to determine when synchronous VUAS treatment and AUS are preferable to staging.[33]
Follow-Up and Failure Patterns
Track:
- Stream, PVR, infections, catheterization difficulty
- Cystoscopic caliber, often 16-17 Fr passage
- Stress incontinence severity after patency
- Radiation complications: hematuria, pain, fistula, poor compliance
- PSA and oncologic treatment plan
Failure patterns:
- Early recurrence after dilation/incision. Repeat endoscopic treatment or referral depending on radiation and lumen.
- Recurrent stenosis after two endoscopic procedures. Reconstructive consultation.
- Obliterative VUAS. Reconstruction, not blind dilation.
- VUAS plus severe SUI. Staged outlet reconstruction then AUS.
- VUAS plus fistula/radiation necrosis. Multidisciplinary reconstruction or diversion.
See Also
- Posterior Urethral Stenosis
- Radiation-Induced Posterior Urethral Stenosis
- Bladder Neck Contracture
- Stress Urinary Incontinence (Male)
- RUG / VCUG
- VUAS treatment atlas
- Transurethral Incision of BNC (TUIBNC)
- Primary Re-anastomosis
- Bladder Neck Reconstruction
- Buccal Mucosa Graft
- Artificial Urinary Sphincter
- On WHITWIKI, the sister site for GU oncology: Radical Prostatectomy, Prostate Continence.
References
1. Britton CJ, Sharma V, Fadel AE, et al. "Vesicourethral Anastomotic Stenosis Following Radical Prostatectomy: Risk Factors, Natural History, and Treatment Outcomes." J Urol. 2023;210(2):312-322. doi:10.1097/JU.0000000000003488
2. Webb DR, Sethi K, Gee K. "An Analysis of the Causes of Bladder Neck Contracture After Open and Robot-Assisted Laparoscopic Radical Prostatectomy." BJU Int. 2009;103(7):957-963. doi:10.1111/j.1464-410X.2008.08278.x
3. Breyer BN, Davis CB, Cowan JE, Kane CJ, Carroll PR. "Incidence of Bladder Neck Contracture After Robot-Assisted Laparoscopic and Open Radical Prostatectomy." BJU Int. 2010;106(11):1734-1738. doi:10.1111/j.1464-410X.2010.09333.x
4. Ouzaid I, Xylinas E, Ploussard G, et al. "Anastomotic Stricture After Minimally Invasive Radical Prostatectomy: What Should Be Expected From the Van Velthoven Single-Knot Running Suture?" J Endourol. 2012;26(8):1020-1025. doi:10.1089/end.2011.0650
5. Naser-Tavakolian A, Lee Z. "A Review of Management Options for Vesicourethral Anastomotic Stenosis and the Emergence of Robotic Reconstruction." Transl Androl Urol. 2025;14(8):2405-2418. doi:10.21037/tau-24-503
6. Elliott SP, Meng MV, Elkin EP, et al. "Incidence of Urethral Stricture After Primary Treatment for Prostate Cancer: Data From CaPSURE." J Urol. 2007;178(2):529-534. doi:10.1016/j.juro.2007.03.126
7. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. "Urethral Stricture Disease Guideline Amendment (2023)." J Urol. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482
8. Rozanski AT, Zhang LT, Holst DD, et al. "The Effect of Radiation Therapy on the Efficacy of Internal Urethrotomy With Intralesional Mitomycin C for Recurrent Vesicourethral Anastomotic Stenoses and Bladder Neck Contractures: A Multi-Institutional Experience." Urology. 2021;147:294-298. doi:10.1016/j.urology.2020.09.035
9. Abramowitz DJ, Balzano FL, Ruel NH, Chan KG, Warner JN. "Transurethral Incision With Transverse Mucosal Realignment for the Management of Bladder Neck Contracture and Vesicourethral Anastomotic Stenosis." Urology. 2021;152:102-108. doi:10.1016/j.urology.2021.02.035
10. Nealon SW, Bhanvadia RR, Badkhshan S, et al. "Transurethral Incisions for Bladder Neck Contracture: Comparable Results Without Intralesional Injections." J Clin Med. 2022;11(15):4355. doi:10.3390/jcm11154355
11. Shakir NA, Alsikafi NF, Buesser JF, et al. "Durable Treatment of Refractory Vesicourethral Anastomotic Stenosis via Robotic-Assisted Reconstruction: A Trauma and Urologic Reconstructive Network of Surgeons Study." Eur Urol. 2022;81(2):176-183. doi:10.1016/j.eururo.2021.08.013
12. Lavollé A, de la Taille A, Chahwan C, et al. "Extraperitoneal Robot-Assisted Vesicourethral Reconstruction to Manage Anastomotic Stricture Following Radical Prostatectomy." Urology. 2019;133:129-134. doi:10.1016/j.urology.2019.07.027
13. Lee M, Lesgart M, McPartland C, Lee R, Eun DD. "Robotic Transvesical Bladder Neck Reconstruction: A Novel Approach to Managing Vesicourethral Anastomotic Stenosis." Eur Urol. 2025;88(5):519-524. doi:10.1016/j.eururo.2025.04.026
14. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Males. 2026. Endoluminal management of non-traumatic posterior urethral stenosis; post-dilatation/DVIU strategies for anterior strictures. Guideline.
15. Abbasi B, Shaw NM, Lui JL, et al. "Posterior urethral stenosis: a comparative review of the guidelines." World J Urol. 2022;40(11):2591-2600. doi:10.1007/s00345-022-04131-y
16. Veerman H, Vis AN, Hagens MJ, et al. "Surgical and Functional Outcomes of Bladder Neck Incision for Primary Vesico-Urethral Anastomosis Stricture after Robot-assisted Radical Prostatectomy are Influenced by the Presence of Pre- or Postoperative Radiotherapy." Urology. 2022;166:216-222. doi:10.1016/j.urology.2022.03.015
17. Neu S, Vigil H, Locke JA, et al. "Triamcinolone acetonide injections for the treatment of recalcitrant post-radical prostatectomy vesicourethral anastomotic stenosis: A retrospective look at efficacy and safety." Can Urol Assoc J. 2021;15(3):E175-E179. doi:10.5489/cuaj.6644
18. Pfalzgraf D, Worst T, Kranz J, et al. "Vesico-urethral anastomotic stenosis following radical prostatectomy: a multi-institutional outcome analysis with a focus on endoscopic approach, surgical sequence, and the impact of radiation therapy." World J Urol. 2021;39(1):89-95. doi:10.1007/s00345-020-03157-4
19. Delchet O, Nourredine M, González Serrano A, et al. "Post-prostatectomy anastomotic stenosis: systematic review and meta-analysis of endoscopic treatment." BJU Int. 2024;133(3):237-245. doi:10.1111/bju.16141
20. Redshaw JD, Broghammer JA, Smith TG 3rd, et al. "Intralesional injection of mitomycin C at transurethral incision of bladder neck contracture may offer limited benefit: TURNS Study Group." J Urol. 2015;193(2):587-92. doi:10.1016/j.juro.2014.08.104
21. Sterling J, Simhan J, Flynn BJ, et al. "Multi-Institutional Outcomes of Dorsal Onlay Buccal Mucosal Graft Urethroplasty in Patients With Postprostatectomy, Postradiation Anastomotic Stenosis." J Urol. 2024;211(4):596-604. doi:10.1097/JU.0000000000003848
22. Kaldany A, Cedars B, Nikolavsky D. "Substitution urethroplasty for posterior urethral stenosis." Transl Androl Urol. 2025;14(12):3962-3974. doi:10.21037/tau-2025-566
23. Bearrick EN, Findlay BL, Maciejko LA, et al. "Robotic Urethral Reconstruction Outcomes in Men With Posterior Urethral Stenosis." Urology. 2022;161:118-124. doi:10.1016/j.urology.2021.11.035
24. Ivan SJ, Lee M, Simhan J. "Contemporary management of radiation-associated posterior urethral stenosis: a narrative review." Transl Androl Urol. 2025;14(10):3377-3386. doi:10.21037/tau-2025-183
25. Liu W, Shakir N, Zhao LC. "Single-Port Robotic Posterior Urethroplasty Using Buccal Mucosa Grafts: Technique and Outcomes." Urology. 2022;159:214-221. doi:10.1016/j.urology.2021.07.049
26. Reiss CP, Pfalzgraf D, Kluth LA, et al. "Transperineal reanastomosis for the treatment for highly recurrent anastomotic strictures as a last option before urinary diversion." World J Urol. 2014;32(5):1185-90. doi:10.1007/s00345-013-1180-6
27. Nikolavsky D, Blakely SA, Hadley DA, et al. "Open reconstruction of recurrent vesicourethral anastomotic stricture after radical prostatectomy." Int Urol Nephrol. 2014;46(11):2147-52. doi:10.1007/s11255-014-0816-9
28. Borboroglu PG, Sands JP, Roberts JL, Amling CL. "Risk Factors for Vesicourethral Anastomotic Stricture After Radical Prostatectomy." Urology. 2000;56(1):96-100. doi:10.1016/s0090-4295(00)00556-2
29. Orvieto MA, Zorn KC, Gofrit ON, et al. "Surgical Modifications in Bladder Neck Reconstruction and Vesicourethral Anastomosis During Radical Retropubic Prostatectomy to Reduce Bladder Neck Contractures." Can J Urol. 2006;13(6):3353-3357. PMID 17187702
30. Elliott DS, Boone TB. "Combined Stent and Artificial Urinary Sphincter for Management of Severe Recurrent Bladder Neck Contracture and Stress Incontinence After Prostatectomy: A Long-Term Evaluation." J Urol. 2001;165(2):413-415. doi:10.1097/00005392-200102000-00014
31. Anger JT, Raj GV, Delvecchio FC, Webster GD. "Anastomotic Contracture and Incontinence After Radical Prostatectomy: A Graded Approach to Management." J Urol. 2005;173(4):1143-1146. doi:10.1097/01.ju.0000155624.48337.a5
32. Fiedler G, Cavalcanti AG, Bittencourt LK, Goldman SM. "Use of Dynamic Magnetic Resonance of the Urethra in Surgical Planning of Vesicourethral Anastomotic Stenosis Urethroplasty." Int Braz J Urol. 2026;52(1):e20250264. doi:10.1590/s1677-5538.ibju.2025.0264
33. American Urological Association, Society of Genitourinary Reconstructive Surgeons, Society of Urodynamics, Female Pelvic Medicine and Urogenital Reconstruction. Incontinence after Prostate Treatment: AUA/GURS/SUFU Guideline (2019; Amended 2024). 2024. Statement 38 and Future Directions. Official full guideline.
34. Savun M, Çolakoğlu Y, Özdemir H, et al. "Comparison of open perineal and robot-assisted reconstruction in vesicourethral anastomotic stenosis." World J Urol. 2025;43(1):413. doi:10.1007/s00345-025-05808-w
35. Roessler N, Klemm J, Fisch M, Dahlem R, Vetterlein MW; Trauma and Reconstructive Urology Working Party of the European Association of Urology Young Academic Urologists. "A Systematic Review and Meta-analysis of Surgical Reconstruction for Bladder Neck and Vesicourethral Anastomotic Stenosis: The Case for Etiology-specific Definitions and Reporting." Eur Urol Focus. 2026;12(3):360-372. doi:10.1016/j.euf.2026.06.012
36. Kowalewski KF, Tapking C, Hetjens S, et al. "Interrupted versus Continuous Suturing for Vesicourethral Anastomosis During Radical Prostatectomy: A Systematic Review and Meta-analysis." Eur Urol Focus. 2019;5(6):980-991. doi:10.1016/j.euf.2018.05.009
37. European Association of Urology. EAU Guidelines on Urethral Strictures: Diagnostic Evaluation. 2026. Guideline.
38. Wessells H, Angermeier KW, Elliott S, et al. "Male Urethral Stricture: American Urological Association Guideline." J Urol. 2017;197(1):182-190. doi:10.1016/j.juro.2016.07.087