Posterior Compartment Prolapse
Posterior compartment pelvic organ prolapse is descent of the posterior vaginal wall (usually from rectovaginal support failure) allowing the rectum, peritoneal cul-de-sac, small bowel, or a deficient perineal body to protrude toward the vaginal lumen.[1][2] The most common posterior defect is a rectocele; enterocele and perineal deficiency commonly coexist and are easy to miss when the exam focuses only on the visible posterior bulge.
Posterior prolapse is rarely a pure mechanical problem. Symptoms sit at the intersection of vaginal support, stool consistency, pelvic-floor coordination, rectal emptying, anal sphincter function, and apical support.
See also: POP Overview for the DeLancey framework, POP-Q, pessary management, and shared surgical principles. The functional overlap is in Defecatory Disorders.
Definition and Terminology
| Term | Meaning | Operative relevance |
|---|---|---|
| Posterior compartment prolapse | Descent of the posterior vaginal wall | POP-Q point Bp captures the leading posterior wall point |
| Rectocele | Anterior rectal-wall bulging into the posterior vagina | Most common posterior defect; may cause bulge, splinting, stool trapping, obstructed defecation |
| Enterocele | Peritoneal sac (often containing small bowel) descending between rectum and vagina | Apex-related; may mimic or coexist with rectocele |
| Perineal deficiency | Weakness / shortening / disruption of the perineal body | Widened genital hiatus, gaping introitus, distal rectocele, stool trapping |
| Obstructed defecation syndrome (ODS) | Difficulty evacuating despite urge and effort | May be structural, functional, or both — rectocele repair helps selected patients only |
POP-Q uses point Bp for the most distal point of the posterior vaginal wall. Point Ap is the fixed posterior point 3 cm proximal to the hymen; GH and PB measurements are necessary because a widened genital hiatus or deficient perineal body changes repair planning.[3]
Compartment-Specific Pathophysiology
Posterior support comes from the posterior vaginal fibromuscular layer / rectovaginal septum, lateral attachments to the pelvic sidewall and levator ani, the perineal body, and Level I apical support.[4][27] The generic DeLancey framework lives in the parent. Whether a discrete histologic "rectovaginal fascia" exists as a separate layer is debated; operatively, the useful concept is plication or reattachment of the posterior fibromuscular layer without levator over-tightening or rectal injury.
Defect patterns — posterior-specific
| Defect | Pattern | Clues |
|---|---|---|
| Midline rectocele | Central attenuation of posterior support | Smooth posterior bulge; stool trapping; treated with midline plication |
| Transverse / apical posterior defect | Separation near the vaginal apex or cul-de-sac | Enterocele, high posterior wall descent, apical descent on POP-Q |
| Distal perineal defect | Perineal body deficiency | Short PB, widened GH, gaping introitus, distal stool trapping |
| Enterocele / sigmoidocele | Peritoneal sac descent between rectum and vagina | Often occult; rectovaginal exam, defecography, or MRI helpful |
| Functional outlet disorder | Dyssynergic contraction or nonrelaxing puborectalis | ODS out of proportion to anatomy; abnormal balloon expulsion / manometry |
Posterior-specific causality problem
Rectoceles exist in nulliparous and asymptomatic women, while many patients with ODS have pelvic-floor dyssynergia, constipation, rectal intussusception, or other anorectal disorders that will not improve with vaginal-wall repair alone.[5][6] This is the dominant posterior-compartment counseling point:
- A rectocele on examination alone is not a reason to operate; correlate it with symptoms and address concomitant bowel dysfunction before rectocele repair.[6]
- The operation treats the vaginal wall. Whether it helps the bowel depends on which mechanism is driving the symptoms.
A cross-sectional study of 279 women scheduled for pelvic organ prolapse surgery defined a true rectocele on translabial ultrasound as a discontinuity in the anterior contour of the internal anal sphincter and anterior anorectal muscularis, distinguishing it from posterior vaginal wall descent without that discontinuity. True rectocele on translabial ultrasound and an enlarged levator hiatus were independently associated with obstructed defecation on logistic regression; true rectocele was also associated with straining, digitation and incomplete emptying.[21]
Clinical Presentation
Defecatory symptoms — the posterior-specific dimension
| Symptom | Association with posterior prolapse |
|---|---|
| Splinting / digitation | Strongest practical clue for a symptomatic rectocele — vaginal, perineal, or rectal pressure to evacuate |
| Stool trapping | Rectocele that fills but fails to empty on defecography |
| Incomplete evacuation | May reflect stool trapping or functional outlet obstruction |
| Straining | Common but nonspecific — also reflects constipation and dyssynergia |
| Pain with defecation | Fissure, pelvic-floor spasm, levator pain, difficult evacuation |
| Fecal urgency / liquid FI | Can coexist; evaluate stool form and sphincter function |
| Constipation | Common in women with rectocele |
Defecatory symptoms most linked to posterior-wall anatomy (particularly splinting, straining, and incomplete evacuation) are the ones most likely to improve after posterior repair.[7][8] In this longitudinal cohort, posterior prolapse was associated with persistence of difficult bowel movements but was not significantly associated with onset of new defecatory symptoms; among women with posterior prolapse, difficulty with bowel movements at baseline was associated with faster worsening of posterior wall support.[8]
Sexual function — posterior-specific concerns
Symptomatic prolapse is associated with worse sexual function than asymptomatic anatomic prolapse.[9][10] Posterior-specific drivers of dyspareunia or avoidance: posterior bulge protrusion, body-image concern, fear of soiling. Posterior repair has a recognized risk of de novo dyspareunia, particularly with levatorplasty, aggressive introital narrowing, untreated GSM, or pelvic-floor hypertonicity.
Compartment-Specific Evaluation
Generic exam framework is in the parent.
- Split speculum isolation. Retract the anterior wall to isolate posterior descent.
- Rectovaginal and digital rectal exams. Distinguish rectocele, enterocele, perineocele and stool trapping; assess rectovaginal septum integrity, anal tone and puborectalis relaxation during simulated defecation.[6]
- Apex reduction. If posterior descent improves when the apex is reduced, the posterior defect is apex-driven.
- Perineal body and GH. Record PB and GH; a widened GH prompts assessment for perineal-body attenuation or a defect, the anatomic target of perineorrhaphy.[35]
Adjunctive imaging and physiology — when to get it
| Test | Use |
|---|---|
| Defecography (fluoroscopic) | Complex ODS, suspected stool trapping, intussusception, enterocele, sigmoidocele, or recurrent posterior repair |
| MR defecography | Multicompartment pelvic-floor disorder, or distinguishing rectocele from cul-de-sac hernia (enterocele) |
| Translabial ultrasound | Dynamic rectocele depth, levator avulsion, hiatal area, enterocele |
| Anorectal physiology (ARM + BET) | ODS out of proportion to anatomy, suspected dyssynergia, fecal incontinence, or colorectal co-management |
Defecography can show preferential filling, failure to empty, contrast trapping and rectocele size. In 98 women undergoing reconstructive pelvic surgery, fluoroscopic contrast retention was unrelated to symptoms[28]; in 89 women undergoing combined transvaginal and transanal rectocele repair for obstructed defecation, rectocele size, barium trapping, and poor evacuation did not predict symptom-defined success (zero or one of five residual bowel symptoms) at a median 52 months.[29] Size cut-offs vary between centers and rectoceles are common in asymptomatic women. In one 215-patient surgical series, most women operated on had a rectocele larger than 4 cm, or a medium-sized one with contrast trapping.[13] In women with obstructed defecation, dynamic MRI and transperineal ultrasound met the Cochrane review's triage-test criteria but not its criteria to replace evacuation proctography.[5]
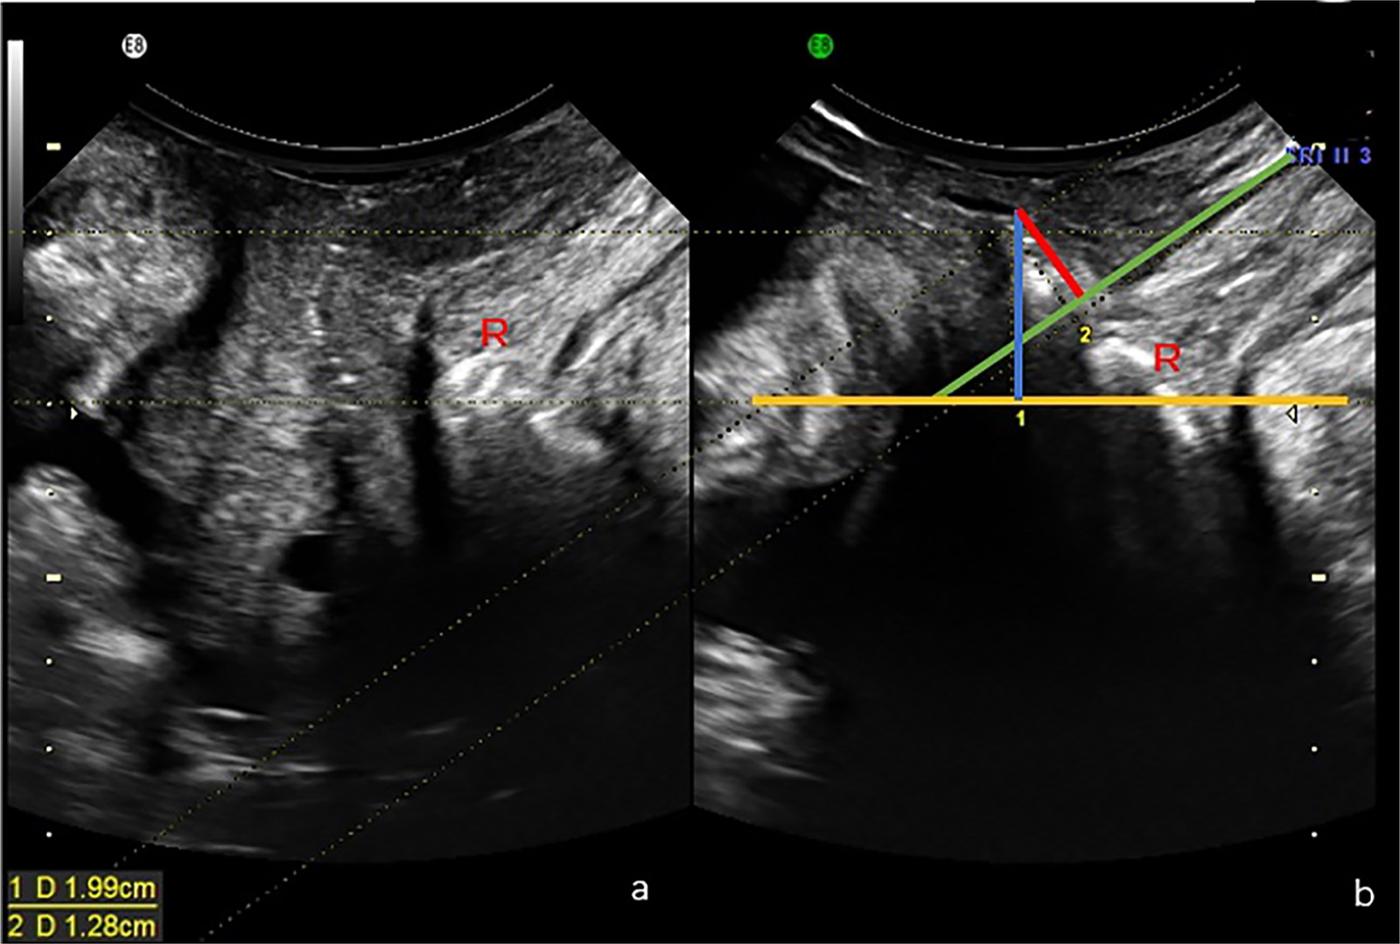
Translabial ultrasound measurement of rectocele depth. (a) Rest and (b) Valsalva, with the rectum (R) labeled. The yellow line is the horizontal line from the lower margin of the pubis, and the green line is the extended ventral line of the internal anal sphincter. Rectocele depth is the distance from the farthest point of the ampulla to the green line, and a true rectocele is diagnosed as a discontinuity in the ventral contour of the anorectal muscularis. From Tan C, et al. Sci Rep. 2020;10(1):5599, Figure 1 (CC BY).[21]
One research group's dynamic-ultrasound work quantifies rectal mobility with a rectovaginal-septum compression ratio — the change in septal length from rest to Valsalva, divided by the resting length — and reports that greater rectal mobility is associated with ODS independently of vaginal bulge or rectocele size. In a 62-woman case-control study, a compression ratio of 14% or more carried 32-fold greater odds of ODS than a ratio below 14% (OR 32.5, 95% CI 4.8–217.1), adjusted for age, BMI, parity, stool type and bowel-movement frequency; in a separate retrospective study of 121 women with constipation, the severe-versus-mild ODS analysis concerned 73 women with pelvic constipation, among whom a ratio of 20% or more carried about fourfold greater odds of severe symptoms (OR 4.2, 95% CI 1.4–12.6), adjusted for age, BMI and levator-plate descent angle.[22][23] These thresholds come from one research group and have not been externally validated.[22][23]
See Defecatory Dysfunction for anorectal-physiology framing.
Surgical Management
See the Prolapse Repair atlas for operative options and comparative outcomes.
Generic pessary management and non-surgical options are in the parent. What follows is posterior-specific.
Indication — who benefits from surgery
Surgery is for bothersome posterior vaginal bulge, pressure or sexual dysfunction when nonsurgical treatment has failed or been declined, and for defecatory dysfunction that persists despite appropriate conservative treatment.[1][6][11] ASCRS 2024 allows repair for significant outlet dysfunction from a rectocele once concomitant functional causes such as a nonrelaxing puborectalis are addressed .[6] It notes that 30% to 70% of patients with a rectocele report obstructed-defecation symptoms, that incidental rectoceles are common on workup, and that no approach has been shown to be best.[6] Stronger selection features for rectocele repair in ODS:
- Bothersome vaginal bulge or protrusion
- Need for vaginal or perineal splinting
- Large rectocele (surgical series commonly select rectoceles >4 cm, or smaller ones with trapping)
- Symptom-concordant trapping / non-emptying on defecography, considered with bowel-function findings[11][29]
- Failure of bowel optimization and pelvic-floor biofeedback; measure colonic transit before surgery for constipation-dominant symptoms .[6][29]
- Dyssynergia, intussusception, and severe sphincter dysfunction addressed (or excluded) first
Posterior colporrhaphy and perineorrhaphy
Posterior colporrhaphy is the standard transvaginal native-tissue repair for symptomatic rectocele: midline plication of the posterior vaginal fibromuscular tissue after separating vaginal epithelium from rectum. Perineorrhaphy reconstructs the perineal body when distal support is deficient.[2][12]
| Step | Principle |
|---|---|
| Posterior midline vaginal incision | From distal posterior wall toward the apex as needed |
| Rectovaginal dissection | Develop the safe plane; avoid rectal entry |
| Fibromuscular plication | Midline delayed-absorbable plication; avoid excessive narrowing |
| Enterocele repair if present | Reduce sac, restore apical / cul-de-sac support |
| Perineorrhaphy if needed | Reapproximate perineal muscles; normalize GH/PB, do not over-tighten |
| Rectal exam at closure | Confirm no rectal suture or injury |
Midline fascial plication without levatorplasty is the usual choice. Levatorplasty narrows the introitus, and higher dyspareunia rates are reported with it (ICI review, grade C).[12] The ICI review graded midline plication without levatorplasty as possibly superior to site-specific repair on objective outcomes (grade B), on limited evidence.[12] Some centers still combine levatorplasty with transvaginal repair for large rectoceles.[13]
Transvaginal repair improves bulge in most selected patients and ODS symptoms in many. In a 215-patient single-center series of transvaginal repair with levatorplasty (mean follow-up 12.7 months), 80% reported improved vaginal bulge and 58% improved ODS symptoms; 8.4% had postoperative urinary retention.[13] Reoperation risk accumulates with time. In a Swedish register cohort, 5,846 women had isolated native-tissue posterior repair; reoperation in any compartment was 11.5% at 5 years and 16.4% at 10 years, and reoperation in the posterior compartment was 3.5% and 4.4%.[17]
Randomized comparison of techniques. In the Paraiso RCT (106 women, stage II or greater posterior prolapse), posterior colporrhaphy, site-specific repair and site-specific repair with a porcine small-intestinal-submucosa graft were compared. At 1 year, anatomic failure (Bp ≥ −2) was 4/28 (14%) with colporrhaphy, 6/27 (22%) with site-specific repair and 12/26 (46%) with graft augmentation (P = .02). Functional failure (15% overall) and symptom, quality-of-life and sexual-function improvement did not differ between groups.[16]
Approach comparison
| Approach | Role | Tradeoffs |
|---|---|---|
| Transvaginal native tissue | Standard for symptomatic posterior vaginal wall prolapse | Best anatomic posterior data; dyspareunia risk if over-tightened |
| Transanal | Selected colorectal use when rectal mucosal pathology dominates | More recurrent posterior vaginal wall prolapse than transvaginal repair in small RCTs; postoperative ODS may be more frequent (low-quality evidence); complication differences remain uncertain.[2] |
| Transperineal | Distal rectocele / perineal body deficiency; limited data | Useful for perineal reconstruction; less standardized evidence |
| Ventral mesh rectopexy | Rectal intussusception, rectal prolapse, complex ODS with colorectal indication | Abdominal mesh; colorectal collaboration; longer op time |
Transvaginal is favored over transanal for posterior vaginal wall prolapse. In the Cochrane review (4 RCTs, 191 women for the comparison), transanal repair had more recurrent posterior prolapse on examination (RR 4.12, 95% CI 1.56–10.88; 2 RCTs, 87 women; moderate-quality evidence), probably more postoperative obstructed defecation (RR 1.67, 95% CI 1.00–2.79; 3 RCTs, 113 women) and probably more awareness of prolapse (RR 2.78, 95% CI 1.00–7.70; 2 RCTs, 87 women).[2] Repeat surgery, dyspareunia and complications were not conclusively different.[2] FIGO reached the same conclusion for the transvaginal route without mesh.[14] STARR (stapled transanal rectal resection) is a colorectal operation with its own complication profile. ASCRS 2024 recommends against it for rectocele or internal rectal intussusception because of high complication rates .[6]
Mesh and biologic grafts — the posterior-specific stance
Synthetic mesh and biologic grafts have not improved posterior vaginal wall repair and add risk. The Cochrane review found no clear benefit of graft augmentation, and in the Paraiso RCT porcine-graft augmentation had the highest 1-year anatomic failure rate (12/26).[2][16] ACOG Practice Bulletin 214 likewise concludes that mesh or biologic grafts in transvaginal posterior repair do not improve outcomes (Level A).[1] NICE NG123 recommends posterior vaginal repair without mesh (1.8.23), and NICE interventional procedures guidance 599 limits transvaginal mesh repair of anterior or posterior wall prolapse to research.[18] In April 2019 the US FDA ordered manufacturers to stop selling transvaginal mesh for prolapse repair, so no such mesh is marketed in the United States.[19] This is separate from abdominal mesh procedures for selected indications (ventral mesh rectopexy, sacrocolpopexy) where risk–benefit counseling differs.
Ventral mesh rectopexy — when to collaborate with colorectal
Laparoscopic ventral mesh rectopexy suspends the anterior rectal wall to the sacral promontory; primarily a colorectal operation for rectal prolapse or internal intussusception with ODS. ASCRS 2017 gives ventral mesh rectopexy a strong recommendation on low-quality evidence (1C) as an alternative repair for rectal prolapse with acceptable short- and long-term complication rates.[20] It found insufficient evidence that posterior suture rectopexy is better or worse than ventral rectopexy, and noted that ventral rectopexy has not yet been fully adopted in the United States because long-term data are limited and mesh complications are possible.[20] The same guideline reports that 20% to 35% of patients with rectal prolapse have urinary incontinence and about 15% to 30% have significant vaginal vault prolapse, and it advises a multidisciplinary approach to multivisceral prolapse.[20] For obstructed defecation from intussusception, ASCRS 2024 permits repair only when severe symptoms persist after nonoperative treatment .[6] In one nonrandomized comparison (72 ventral rectopexy versus 159 colporrhaphy), rectopexy had better defecographic correction and greater improvement in constipation, sexual symptoms and quality of life at 1 year, with a longer operative time. The FIGO group found no conclusions possible from earlier trials comparing colporrhaphy and laparoscopic rectopexy.[14][15] A subsequent single-center RCT randomized 40 selected women (20 per arm); both routes improved constipation scores at 12 months without a significant between-group difference.[33] A 2025 international expert consensus says ventral rectopexy may be inappropriate with active pelvic malignancy, pregnancy, fistulizing rectovaginal disease, or pelvic sepsis and requires case-by-case consideration.[32] The 2026 Pelvic Floor Consortium consensus recommends timely surgery as first-line treatment for full-thickness external rectal prolapse; ventral rectopexy is one operative option.[31][32] For ODS from internal intussusception, a 2025 expert consensus identifies Oxford grade IV or selected grade III with high takeoff or associated enterocele, sigmoidocele or solitary rectal ulcer syndrome after failed nonoperative treatment.[32]
Operative sequence when both procedures are planned. When a rectal-prolapse operation and a vaginal posterior-compartment repair are performed together, addressing the rectal prolapse first has been described as the preferred order, because the rectum can become difficult to prolapse into the operative field once the posterior vaginal repair is complete; lithotomy positioning for the combined case avoids repositioning between the two parts.[24]
Combined apical and rectal support. For a patient with apical prolapse and concomitant rectal prolapse or intussusception, a combined abdominal sacrocolpopexy and ventral rectopexy with a colorectal team has been described: posterior dissection is carried to the perineal body, synthetic mesh is secured distally to the bilateral levator muscles at that level, delayed-absorbable sutures are placed along the anterior rectum, and the mesh is then attached to the posterior cuff or cervix, the anterior vagina and the sacral promontory. When the colorectal team prefers a biologic graft for the rectopexy, a Y-shaped synthetic graft for vaginal suspension with a separate biologic rectal graft has been described, fixing both sacral arms to the anterior longitudinal ligament.[25]
Transvaginal sacrospinous suture rectopexy — a mesh-free alternative. One group has described a mesh-free transvaginal technique for selected obstructed defecation associated with rectal laxity, performed through the standard posterior vaginal incision rather than abdominally: an anchoring suture is placed in each sacrospinous ligament about 2–2.5 cm medial to the ischial spine, and with a finger in the rectum, a two-bite running suture is passed through the lateral rectal ligament and rectal muscularis about 7–8 cm above the anal verge; one side is tied before the other is placed and tied, to assess suspension and avoid excess rectal tension. In an initial 20-patient cohort, mean subjective improvement was reported as 94.7% (± 13.4) at 2 months and 90.6% (± 18) at 12 months; Table 1 reports 19 participants assessed at 2 months and 16 at 12 months, with two composite failures among the 16 assessed at one year.[26] Two patients also required early sacrospinous suture removal for severe gluteal pain.[26] A later 190-case retrospective cohort reported four rectal injuries, postoperative urinary retention in 29.8% (associated with concomitant repairs), and six reoperations within 30 days.[30] The initial 20-patient single-group series reported outcomes through 1 year.[26] In a later prospective cohort, 65 of 135 eligible women were recruited at a median 29 months after surgery; among those assessed for each outcome, 18 (28.1%) reported ODS symptoms in more than half of bowel movements and seven (12.7%) met the study's anatomic-failure definition.[34]
Sexual Function Outcomes — Posterior-Specific Counseling
Sexual dysfunction and avoidance can accompany symptomatic prolapse and body-image concerns.[9][10] In a 2020 systematic review, overall sexual-function scores were similar before and after posterior repair.[37] A 2026 narrative review estimated de novo dyspareunia after posterior repair at about 14% from limited data.[38] De novo dyspareunia risk is real, especially with levatorplasty or aggressive narrowing. Counseling must cover:
- Baseline dyspareunia and pelvic-floor tenderness
- Desire for future penetrative vaginal intercourse
- Planned degree of perineorrhaphy / introital narrowing
- GSM treatment when indicated (see parent — hypoestrogenic tissue)
Long-Term Outcomes and Recurrence
| Outcome | Pattern |
|---|---|
| Bulge | Usually improves substantially after posterior colporrhaphy in selected patients |
| Splinting / stool trapping | Most likely to improve when rectocele is large and traps stool |
| Global constipation | Less predictable; depends on stool form, transit, and dyssynergia |
| Dyspareunia | May improve if prolapse-related; may worsen if repair is over-tightened |
| Recurrence | Increases with longer follow-up and uncorrected apical / hiatal support failure |
Defecatory symptoms most strongly associated with degree of posterior-wall descent tend to improve most after surgery.[7] Reoperation accumulates over 5–10 years (see above), and bowel symptoms can persist.[17]
Key Recommendations
- Treat only symptomatic posterior prolapse. Incidental rectocele on exam or imaging does not mandate repair.
- Use POP-Q Ap, Bp, GH, PB, C/D, and a rectovaginal exam to define anatomy.
- Look for apical prolapse and enterocele before calling a defect "isolated rectocele."
- Treat constipation and stool-form problems before surgery for ODS-predominant symptoms. For posterior prolapse with ODS and high tone or dyssynergia, provide pelvic-floor PT before rectocele repair; with reduced tone, PT can be offered before or after repair.[31]
- Favor transvaginal native-tissue posterior colporrhaphy for symptomatic posterior vaginal wall prolapse.
- Consider perineorrhaphy when the perineal body is deficient. For a widened genital hiatus, discuss risks and potential benefits of narrowing; evidence is insufficient to determine whether prophylactic narrowing prevents future prolapse.[36]
- Avoid routine levatorplasty. Dyspareunia risk.
- Do not routinely place synthetic mesh or biologic grafts through posterior vaginal wall incisions.
- For women with ODS and no clinically significant rectocele or enterocele on vaginal examination, refer to gastroenterology or colorectal surgery for further evaluation.[39] Collaborate with colorectal surgery for rectal prolapse, intussusception, complex ODS, fecal incontinence, or failed posterior repairs.
See Also
- POP Overview
- Anterior Compartment Prolapse
- Apical Prolapse
- Female Pelvic Examination
- Chronic Constipation
- Defecatory Dysfunction
- Fecal Incontinence
- Posterior Colporrhaphy
- Perineorrhaphy
- McCall Culdoplasty
- Prolapse Repair
Videos
References
1. Committee on Practice Bulletins—Gynecology and American Urogynecologic Society. "Pelvic Organ Prolapse: ACOG Practice Bulletin, Number 214." Obstet Gynecol. 2019;134(5):e126-e142. doi:10.1097/AOG.0000000000003519
2. Mowat A, Maher D, Baessler K, et al. "Surgery for Women With Posterior Compartment Prolapse." Cochrane Database Syst Rev. 2018;3(3):CD012975. doi:10.1002/14651858.CD012975
3. Bump RC, Mattiasson A, Bo K, et al. "The Standardization of Terminology of Female Pelvic Organ Prolapse and Pelvic Floor Dysfunction." Am J Obstet Gynecol. 1996;175(1):10-17. doi:10.1016/s0002-9378(96)70243-0. PMID:8694033
4. Bordeianou LG, Carmichael JC, Paquette IM, et al. "Consensus Statement of Definitions for Anorectal Physiology Testing and Pelvic Floor Terminology (Revised)." Dis Colon Rectum. 2018;61(4):421-427. doi:10.1097/DCR.0000000000001070
5. van Gruting IM, Stankiewicz A, Thakar R, et al. "Imaging Modalities for the Detection of Posterior Pelvic Floor Disorders in Women With Obstructed Defaecation Syndrome." Cochrane Database Syst Rev. 2021;9(9):CD011482. doi:10.1002/14651858.CD011482.pub2
6. Alavi K, Thorsen AJ, Fang SH, et al. "The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Evaluation and Management of Chronic Constipation." Dis Colon Rectum. 2024;67(10):1244-1257. doi:10.1097/DCR.0000000000003430
7. Karjalainen PK, Mattsson NK, Nieminen K, Tolppanen AM, Jalkanen JT. "The Relationship of Defecation Symptoms and Posterior Vaginal Wall Prolapse in Women Undergoing Pelvic Organ Prolapse Surgery." Am J Obstet Gynecol. 2019;221(5):480.e1-480.e10. doi:10.1016/j.ajog.2019.05.027
8. Handa VL, Munoz A, Blomquist JL. "Temporal Relationship Between Posterior Vaginal Prolapse and Defecatory Symptoms." Am J Obstet Gynecol. 2017;216(4):390.e1-390.e6. doi:10.1016/j.ajog.2016.10.021
9. Fatton B, de Tayrac R, Letouzey V, Huberlant S. "Pelvic Organ Prolapse and Sexual Function." Nat Rev Urol. 2020;17(7):373-390. doi:10.1038/s41585-020-0334-8
10. Handa VL, Cundiff G, Chang HH, Helzlsouer KJ. "Female Sexual Function and Pelvic Floor Disorders." Obstet Gynecol. 2008;111(5):1045-1052. doi:10.1097/AOG.0b013e31816bbe85
11. Wald A, Bharucha AE, Limketkai B, et al. "ACG Clinical Guidelines: Management of Benign Anorectal Disorders." Am J Gastroenterol. 2021;116(10):1987-2008. doi:10.14309/ajg.0000000000001507
12. Karram M, Maher C. "Surgery for Posterior Vaginal Wall Prolapse." Int Urogynecol J. 2013;24(11):1835-1841. doi:10.1007/s00192-013-2174-z
13. Ferrari L, Cuinas K, Hainsworth A, et al. "Transvaginal Rectocoele Repair for the Surgical Treatment of a Symptomatic Rectocoele When Conservative Measures Fail: A 12 Year Experience of 215 Patients." Neurogastroenterol Motil. 2022;34(11):e14343. doi:10.1111/nmo.14343
14. Doumouchtsis SK, Raheem AA, Milhem Haddad J, et al. "An Update of a Former FIGO Working Group Report on Management of Posterior Compartment Prolapse." Int J Gynaecol Obstet. 2020;148(2):135-144. doi:10.1002/ijgo.13006
15. Abdelnaby M, Fathy M, Abdallah E, et al. "Laparoscopic Ventral Mesh Rectopexy Versus Transvaginal Posterior Colporrhaphy in Management of Anterior Rectocele." J Gastrointest Surg. 2021;25(8):2035-2046. doi:10.1007/s11605-020-04823-z
16. Paraiso MF, Barber MD, Muir TW, et al. "Rectocele Repair: A Randomized Trial of Three Surgical Techniques Including Graft Augmentation." Am J Obstet Gynecol. 2006;195(6):1762-71. doi:10.1016/j.ajog.2006.07.026
17. Nüssler E, Granåsen G, Bixo M, et al. "Long-Term Outcome After Routine Surgery for Pelvic Organ Prolapse: A National Register-Based Cohort Study." Int Urogynecol J. 2022;33(7):1863-1873. doi:10.1007/s00192-022-05156-y
18. National Institute for Health and Care Excellence. Urinary Incontinence and Pelvic Organ Prolapse in Women: Management (NG123). Recommendation 1.8.23 and note on interventional procedures guidance 599. 2019 (updated).
19. US Food and Drug Administration. "FDA's Activities: Urogynecologic Surgical Mesh Implants" (order to stop sale of transvaginal mesh for prolapse, April 2019). fda.gov
20. Bordeianou L, Paquette I, Johnson E, et al. "Clinical Practice Guidelines for the Treatment of Rectal Prolapse." Dis Colon Rectum. 2017;60(11):1121-1131. doi:10.1097/DCR.0000000000000889
21. Tan C, Geng J, Tang J, Yang X. "The Relationship Between Obstructed Defecation and True Rectocele in Patients With Pelvic Organ Prolapse." Sci Rep. 2020;10(1):5599. doi:10.1038/s41598-020-62376-2
22. Rostaminia G, Abramowitch S, Chang C, Goldberg RP. "Descent and Hypermobility of the Rectum in Women With Obstructed Defecation Symptoms." Int Urogynecol J. 2020;31(2):337-349. doi:10.1007/s00192-019-03934-9
23. Routzong MR, Abramowitch SD, Chang C, Goldberg RP, Rostaminia G. "Obstructed Defecation Symptom Severity and Degree of Rectal Hypermobility and Folding Detected by Dynamic Ultrasound." Ultrasound Q. 2021;37(3):229-236. doi:10.1097/RUQ.0000000000000565
24. Davis BR. Transperineal repair of rectal prolapse. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:1181-1188.
25. Chang OH, Sutherland SE. Management of vaginal posterior compartment prolapse: is there ever a case for graft/mesh? In: Martins FE, Holm HV, Sandhu JS, McCammon KA, eds. Female Genitourinary and Pelvic Floor Reconstruction. Springer; 2023:643-655. doi:10.1007/978-3-031-19598-3_38
26. Rostaminia G, Abramowitch S, Chang C, Goldberg RP. "Transvaginal Sacrospinous Ligament Suture Rectopexy for Obstructed Defecation Symptoms: 1-Year Outcomes." Int Urogynecol J. 2021;32(11):3045-3052. doi:10.1007/s00192-020-04611-y
27. DeLancey JO. "Structural Anatomy of the Posterior Pelvic Compartment as It Relates to Rectocele." Am J Obstet Gynecol. 1999;180(4):815-823. doi:10.1016/s0002-9378(99)70652-6
28. Kenton K, Shott S, Brubaker L. "The Anatomic and Functional Variability of Rectoceles in Women." Int Urogynecol J Pelvic Floor Dysfunct. 1999;10(2):96-99. doi:10.1007/pl00004019
29. van Dam JH, Hop WC, Schouten WR. "Analysis of Patients With Poor Outcome of Rectocele Repair." Dis Colon Rectum. 2000;43(11):1556-1560. doi:10.1007/BF02236738
30. Hadizadeh A, Chill HH, Leffelman A, et al. "Short-Term Complications Following Transvaginal Sacrospinous Ligament Rectopexy: A Retrospective Cohort Study." Int Urogynecol J. 2025;36(5):1037-1044. doi:10.1007/s00192-025-06098-x
31. Traugott AL, Barten J, Bordeianou L, et al. "Incorporating Pelvic Floor Physical Therapy in the Treatment of Obstructed Defecation Syndrome and Posterior Compartment Pelvic Organ and Rectal Prolapse: Proceedings of the Consensus Meeting of the Pelvic Floor Consortium of the American Society of Colon and Rectal Surgeons, the International Continence Society, the International Urogynecological Association, the American Urogynecologic Society, and the American Physical Therapy Association." Int Urogynecol J. 2026;37(3):537-551. doi:10.1007/s00192-026-06549-z
32. Perry WRG, Christensen P, Collinson RJ, et al. "Ventral Rectopexy: An International Expert Panel Consensus and Review of Contemporary Literature." Dis Colon Rectum. 2025;68(5):593-607. doi:10.1097/DCR.0000000000003656
33. Sanad A, Sakr A, Elfeki H, et al. "Outcomes of Laparoscopic Ventral Mesh Rectopexy Versus Trans-Vaginal Repair in Management of Anterior Rectocele, a Randomized Controlled Trial." Tech Coloproctol. 2025;29(1):125. doi:10.1007/s10151-025-03145-z
34. Chill HH, Hadizadeh A, Leffelman A, et al. "Long-Term Outcomes of Transvaginal Sacrospinous Ligament Suture Rectopexy." Int Urogynecol J. 2025;36(7):1425-1433. doi:10.1007/s00192-025-06099-w
35. Developed by the Joint Writing Group of the American Urogynecologic Society and the International Urogynecological Association. "Joint Report on Terminology for Surgical Procedures to Treat Pelvic Organ Prolapse." Female Pelvic Med Reconstr Surg. 2020;26(3):173-201. doi:10.1097/SPV.0000000000000846
36. Kikuchi JY, Muñiz KS, Handa VL. "Surgical Repair of the Genital Hiatus: A Narrative Review." Int Urogynecol J. 2021;32(8):2111-2117. doi:10.1007/s00192-021-04680-7
37. Antosh DD, Kim-Fine S, Meriwether KV, et al. "Changes in Sexual Activity and Function After Pelvic Organ Prolapse Surgery: A Systematic Review." Obstet Gynecol. 2020;136(5):922-931. doi:10.1097/AOG.0000000000004125
38. Antosh DD, McSpedden H. "Sexual Function Following Surgical Approaches for Pelvic Organ Prolapse." J Minim Invasive Gynecol. 2026;33(1):74-80. doi:10.1016/j.jmig.2025.08.001
39. Rachaneni S, Dietz HP, Latthe P, Sirany A, Spivak A, Dua A. "IUGA Opinion Paper on Obstructed Defecation: Management of Clinical and Proctographic Rectoceles." Int Urogynecol J. 2026;37(1):75-85. doi:10.1007/s00192-025-06288-7