Ureteropelvic Junction Obstruction
Ureteropelvic junction obstruction (UPJO) is a functionally significant impairment of urine flow from the renal pelvis into the proximal ureter that can cause progressive hydronephrosis, parenchymal loss, recurrent pyelonephritis, and stone formation.[1][2] It is the most common cause of congenital obstructive uropathy (incidence about 1 in 1,500 births, with a 2:1 male-to-female ratio in newborns; usually unilateral, more often left-sided).[21][7]
For operative selection and comparative repair options, see the Upper Tract Reconstruction database and the Pyeloplasty technique page.
Classification
UPJO is split first by timing, then by mechanism:[1][3]
- Primary (congenital). Developmental intrinsic or extrinsic UPJ obstruction, often diagnosed antenatally or in childhood but sometimes first presenting in adulthood.[1][21]
- Secondary (acquired). Develops later from stones, prior endoscopic or open surgery, ischemic or radiation stricture, malignancy, retroperitoneal fibrosis, or endometriosis
| Mechanism | Pathology | Examples |
|---|---|---|
| Mural (intrinsic) | Aperistaltic UPJ segment with abnormal smooth muscle, increased collagen, and disordered innervation | Adynamic segment is a common congenital cause[5] |
| Intramural (intraluminal) | Obstruction within the lumen | Fibroepithelial polyp, impacted stone |
| Extramural (extrinsic) | External compression, often intermittent | Lower-pole crossing vessel, kinks, fibrous bands, high ureteral insertion, malrotated or fused kidney |
In a selected robot-assisted pyeloplasty series, anterior crossing vessels were identified in 48/107 patients (44.9%) with UPJO and affected operative planning.[22] A causative crossing vessel favors pyeloplasty over endopyelotomy; preserve it and select the final vessel–UPJ relationship according to intraoperative anatomy, rather than requiring transposition in every case.[22][14][17]
Pathophysiology
In intrinsic congenital UPJO, an aperistaltic segment may fail to propagate the peristaltic wave, impairing pelvic emptying despite a grossly patent lumen.[5] Histology shows smooth-muscle disarray, increased collagen deposition, and stroma-like cells at the obstructing segment; activated Hedgehog–Gli signaling has been implicated in the developmental defect.[4]
The clinical course reflects the renal pelvis acting first as a hydraulic buffer and then as a failed one:[5]
- Compensated phase. The compliant pelvis dilates and damps intrapelvic pressure, sparing parenchyma
- Decompensated phase. Sustained tubular stretch drives interstitial inflammation, myofibroblast activation, tubulointerstitial fibrosis, and tubular apoptosis, with progressive loss of differential function
The underlying hemodynamics of acute obstruction follow a triphasic time-course, established in canine studies of complete unilateral ureteral occlusion: renal blood flow and ureteral pressure both rise for the first 1.5 hours; renal blood flow then falls while ureteral pressure continues to rise, from about 1.5 to 5 hours; and from about 5 hours onward renal blood flow and ureteral pressure decline together, reflecting a shift toward preglomerular vasoconstriction that dominates in chronic occlusion.[27] In a direct canine comparison, renal blood flow rose and then fell in both models, but ureteral pressure returned toward control levels by 24 hours with unilateral occlusion while it stayed elevated at 24 hours with bilateral occlusion, implying a different balance of preglomerular versus postglomerular vascular resistance between the two states.[28] In bilateral upper-tract obstruction or obstruction of a solitary kidney, assess promptly for infection and renal compromise. NICE NG148 calls for immediate urology referral for suspected pyonephrosis, bilateral upper-tract obstruction, or an obstructed solitary kidney; when nephrostomy or stenting is used for obstruction with acute kidney injury, drainage should occur as soon as possible and within 12 hours of diagnosis.[35] An infected obstructed kidney requires urgent drainage.[42]
Pyeloplasty aims to improve drainage, relieve symptoms and preserve remaining function.[23][19] Recovery of split function is variable; poor baseline function does not reliably predict a larger gain.[23][19]
Clinical Presentation
Pediatric
Most cases are now identified on prenatal or neonatal ultrasound for antenatal hydronephrosis, which is detected in up to 4.5% of pregnancies.[3][7] Postnatal symptoms when present include flank or abdominal pain, palpable mass in the neonate, febrile UTI, hematuria, and failure to thrive.
Adult
In adults UPJO is typically symptomatic or detected incidentally on imaging for unrelated complaints:[1][2]
- Flank pain. The classic presentation; often intermittent, exacerbated by diuresis (high fluid intake, alcohol, caffeine; "Dietl's crisis")
- Recurrent pyelonephritis from urinary stasis
- Stone formation. Both a presenting sign and a downstream complication
- Hematuria (gross or microscopic)
- Renal insufficiency when bilateral or in a solitary kidney
- Asymptomatic hydronephrosis found on cross-sectional imaging for an unrelated indication
For adults with incidentally detected asymptomatic unilateral hydronephrosis of unknown cause, the 2024 ACR Appropriateness Criteria rate MAG3 renography, MR urography without and with IV contrast, and CT urography without and with IV contrast as usually appropriate alternative initial studies.[6]
Diagnostic Evaluation
The reconstructive workup pairs anatomic imaging (to identify crossing vessels, stones, malrotation, and the level of obstruction) with functional imaging (to confirm true obstruction and quantify split function).[2][6][9]
| Modality | Role | Strengths | Limitations |
|---|---|---|---|
| Renal ultrasound | Initial radiation-free imaging option in selected contexts; assess collecting-system dilation and parenchyma (SFU or UTD grade in children) | Non-invasive, no radiation | Does not directly measure drainage or split function |
| CT urography | Adult anatomic assessment when indicated | Crossing vessels, stones, malrotation, parenchymal thickness | Radiation; no function |
| MR urography | Anatomic imaging with selected functional data; radiation-free option when indicated, using noncontrast MRU in pregnancy | No radiation; soft-tissue detail | Availability, cost, scan time |
| Diuretic renography (Tc-99m MAG3) | Commonly used functional assessment | Quantifies drainage and split function | Radiation; needs adequate hydration and bladder drainage |
| Retrograde pyelogram | Maps stricture length and confirms anatomy at the time of intervention | Direct anatomic detail | Invasive; usually combined with the operation itself |
| Whitaker test | Direct pressure–flow measurement when renography is equivocal | Can clarify selected equivocal cases[30] | Invasive; rarely needed in modern practice |
Diuretic renography
MAG3 (preferred) or DTPA is administered intravenously; furosemide may precede, coincide with, or follow tracer injection, and delayed protocols can allow collecting-system filling before washout is assessed.[20] Time–activity curves yield two outputs that drive operative decision-making:[2]
- T½ of drainage. Prompt clearance (<10 minutes) is reassuring, but a prolonged half-time, including >20 minutes, is not diagnostic by itself. Review the images, curve, renal function, hydration, bladder emptying and postvoid or gravity-assisted drainage.[20]
- Differential renal function. Compare standardized serial studies. In children, EAU criteria include obstruction with split function <40% or a fall of >10 percentage points, alongside symptoms and imaging progression.[21]
Whitaker test
The original description perfuses the collecting system via a percutaneous nephrostomy or renal-pelvis puncture at a constant 5–10 mL/min while recording pressures in the renal pelvis and a Foley-catheterized bladder: a nonobstructed system tolerates this flow without a progressive rise and has a pelvis-to-bladder pressure difference below 12 cm H₂O; an obstructed system often has a difference above 15–20 cm H₂O or a continually rising difference.[29] A historical account of Whitaker’s three-zone convention at 10 mL/min uses the pelvis-to-bladder pressure differential: <15 cm H₂O unobstructed, 15–22 cm H₂O equivocal, and >22 cm H₂O obstructed.[40] Jaffe and Middleton recommended terminating infusion when renal pelvic pressure reached 30 cm H₂O because higher pressure could induce pyelotubular backflow and sepsis.[29]
In a single-center 25-year experience (143 patients, 145 studies), pressure-flow and diuretic-renography results agreed in 72% of patients with idiopathic hydronephrosis, and the test determined or contributed to management in 84% of cases studied. It correctly predicted outcome in 77% of cases diagnosed as obstructed and in 77% of nonobstructed cases. The authors reserved the test for equivocal results on less invasive tests, suspected obstruction with poor kidney function, loin pain with a negative diuretic renogram, suspected intermittent obstruction, and gross dilatation despite a positive diuretic renogram.[30]
Pediatric grading — UTD classification
The 2014 multidisciplinary Urinary Tract Dilation (UTD) consensus proposed a unified pre- and postnatal score, used alongside the older SFU grading (grades 0–4), based on anteroposterior renal pelvis diameter, calyceal dilation, parenchymal thickness, parenchymal appearance, ureter, and bladder findings.[10][11] Anteroposterior renal pelvic diameter (APRPD) is the most useful single ultrasound predictor of needing intervention; cutoffs of roughly 16–24 mm have been reported, and a sizeable minority of high-grade hydronephrosis (SFU 3–4 or UTD P3) progresses to surgery on conservative management.[7][11] The EAU 2026 text lists SFU grade III–IV dilatation among the features that inform the decision to operate, while its formal recommendation names grade IV. It states that no single grading system has been shown superior.[21]
Management
Indications for intervention
Surgery is indicated for:[1][2][10]
- Symptomatic obstruction (pain, recurrent infection)
- Substantially impaired or declining differential renal function attributable to obstruction, interpreted with serial imaging and symptoms; see the pediatric thresholds above
- Progressive hydronephrosis
- Stone formation in the obstructed system
- Pyelonephritis attributable to obstruction
Active surveillance
Active surveillance with symptom review and serial renography is a reasonable initial option for asymptomatic or mildly symptomatic adults with stable function.[12] In a series of 27 minimally symptomatic adults followed with renography every 6–12 months (21 with adequate follow-up), 71% (15/21) remained on surveillance at a mean of 48 months, and 29% (6/21) crossed over to surgery at an average of 34 months. Progression was mostly pain; 2 of 21 (9.5%) lost function. Failure criteria were >10% loss of relative function, pyelonephritis, or repeated pain.[12]
Surgical options
| Procedure | Success rate | Best fit | Caveats |
|---|---|---|---|
| Open dismembered (Anderson–Hynes) pyeloplasty | 14/15 (93%) by postoperative imaging at mean 21.9 months in one comparative series | Historic gold standard; redo pyeloplasty, complex anatomy | Larger incision; longer recovery |
| Laparoscopic pyeloplasty | >90% in an adult review; 88.8% at mean 20 months in one institutional series | Centers without robotic access | Steep learning curve; longer operative time |
| Robot-assisted laparoscopic pyeloplasty (RALP) | 125/129 (96.9%; symptom or imaging composite) at mean 33.8 months in one mixed-technique adult series; 95.4% mean success across pediatric studies with varied definitions | Established minimally invasive option in appropriately selected adults and children, including infants at experienced centers | Cost; equipment availability |
| Endopyelotomy (antegrade or retrograde) | 42–90% across approaches in an adult review; 60.2% at mean 20 months in one institutional series and 72.6% in another laser-endopyelotomy series | Short intrinsic stenosis without crossing vessel; salvage after failed pyeloplasty | Inferior to pyeloplasty; generally unfavorable with a causative crossing vessel, long stricture, severe hydronephrosis, or poor function |
Pyeloplasty technique
The Anderson–Hynes dismembered pyeloplasty is the reference operation when pelvic and ureteral tissue permit a tension-free anastomosis.[13][14] In a 21-patient pediatric series, an intrarenal pelvis or short ureter was among indications to consider ureterocalicostomy.[43] Dismembered pyeloplasty proceeds as follows:
- Expose the UPJ (transperitoneal or retroperitoneal; open, laparoscopic, or robotic)
- Identify and preserve any crossing vessel
- Excise the diseased aperistaltic segment
- Spatulate the proximal ureter laterally for about 1.5–2 cm
- Reduce the redundant pelvis if needed
- Construct a tension-free, watertight, dependent anastomosis over a JJ stent when selected. A largely adult laparoscopic series used either 2 or 4–6 weeks of stenting.[36] In an 82-patient single-surgeon randomized trial of primary minimally invasive pyeloplasty, two versus six weeks of JJ stenting yielded unobstructed 24-month scintigraphy in 29/30 versus 30/31 patients with imaging follow-up.[46] In a network meta-analysis of 26 pediatric studies (3,298 children), success was high with JJ, external, and no stent, but stented approaches had lower odds of major urine leak or urinoma than stentless repair (both OR 0.20), whereas JJ stents had higher odds of UTI or pyelonephritis than no stent; certainty was low or very low for most outcomes.[37] A separate three-study duration meta-analysis associated four-week stenting with more complications than stenting for at most two weeks, without a detected difference in six-month renographic success.[38]
- Preserve crossing vessels and position the anastomosis to avoid compression or kinking; anterior transposition is selected when the anatomy requires it.[22]
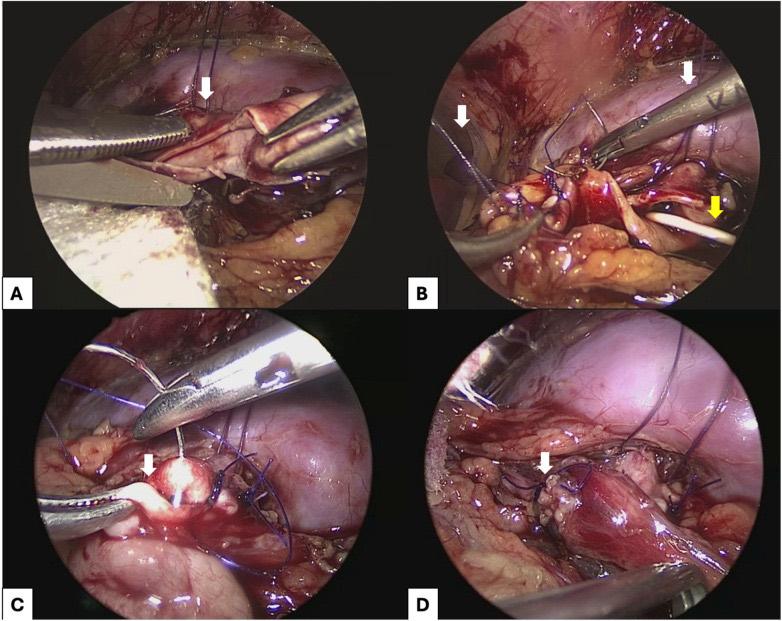
Transabdominal laparoscopic dismembered pyeloplasty in a child. (A) Excision of the redundant renal pelvis (white arrow). (B) Reduction pyeloplasty with 5-0 polydioxanone sutures over a previously placed double-J stent (yellow arrow); a transabdominal stay suture suspends the ureter to facilitate the anastomosis (white arrows). (C) Pelviureteric reanastomosis (white arrow). (D) Completed anastomosis (white arrow). From Nguyen Thi Mai T, Nguyen Phuong T. Front Pediatr. 2026;14:1735651, Figure 1 (CC BY 4.0).[34]
Non-dismembered alternatives are reserved for specific anatomy and rarely used today:[14]
- Foley Y-V plasty. High ureteral insertion with an adequate pelvic flap and no causative crossing vessel; an anterior Y-V modification has been described for a small or intrarenal pelvis without a dorsal crossing vessel.[45]
- Fenger plasty. Short stricture, Heineke–Mikulicz principle
- Culp–DeWeerd or Scardino flap. Long strictures with a generous pelvis
Endopyelotomy
Antegrade or retrograde incision of the stenotic segment through a single full-thickness cut, stented for 4–6 weeks. Long-term failure rates substantially exceed pyeloplasty (adjusted hazard ratio for treatment failure 1.78 versus open pyeloplasty, 1.9 versus minimally invasive pyeloplasty, from claims data in adults aged 18–64), and a causative crossing vessel, stricture >2 cm, high-grade hydronephrosis, or poor split function generally favors reconstruction instead. These are selection and failure-risk factors, not interchangeable absolute contraindications.[14][17][18]
Comparative outcomes
A systematic review and meta-analysis of robot-assisted versus laparoscopic versus open pyeloplasty showed equivalent success and complication rates across approaches, with shorter hospital stay favoring minimally invasive surgery in adults.[13] A 2023 network meta-analysis of six small RCTs (381 patients) favored transperitoneal RALP, but concluded all four minimally invasive approaches were comparable and that retroperitoneal versus transperitoneal access is a matter of surgeon preference.[15] A single-institution series of 129 RALPs reported broad success (symptom resolution, improved hydronephrosis, or unobstructed follow-up imaging) in 125/129 (96.9%) at mean 33.8-month follow-up and estimated 8-year failure-free survival of 91.5%, and a claims-based comparative-effectiveness analysis found endopyelotomy inferior (15% failure versus 7% MIS pyeloplasty versus 9% open).[16][18]
Pediatric considerations
Most antenatally detected hydronephrosis does not need surgery; only a minority requires it. In the Cochrane review of infants (two small, high-risk-of-bias trials, 107 infants under 6 months), about one in five managed non-surgically crossed over to surgery and split function did not differ at 6–12 months, but follow-up was short.[3] Operative thresholds for the pediatric reconstructive surgeon:
- Open pyeloplasty remains common in young infants but is no longer mandatory
- Robotic or laparoscopic pyeloplasty can be performed in selected infants at experienced centers. EAU reports comparable success and complications to open surgery but longer operative times.[21]
- Indications mirror adult practice: declining split function, recurrent infection, symptoms, or progressive UTD/SFU grade. The EAU 2026 text recommends surgery for impaired split function (<40%) or a fall of more than 10 percentage points on serial studies. The formal recommendation is weak: offer surgery for impaired split function from obstruction or a decrease on subsequent studies, with increased anteroposterior diameter and SFU grade IV dilatation, and decide on the time course of hydronephrosis and renal function.[21]
- Poorly functioning kidneys and supranormal function. For split function below 20%, the EAU calls the choice between primary pyeloplasty and nephrectomy controversial, and a staged approach after temporary diversion does not appear advantageous. Supranormal split function (55% or more, about 15% of suspected obstruction) does not by itself predict need for surgery.[21]
- Antibiotic prophylaxis and imaging. The EAU does not recommend continuous antibiotic prophylaxis for asymptomatic PUJ obstruction and gives a weak recommendation to offer it only to high-risk antenatal hydronephrosis subgroups (uncircumcised infants, hydroureteronephrosis, high-grade hydronephrosis). It advises VCUG selectively and states that routine VCUG before pyeloplasty does not change surgical outcomes.[21]
- A meta-analysis of 46 mostly retrospective pediatric RALP series reported a mean success rate of 95.4% and a mean overall complication rate of 12%; among studies reporting complications by Clavien grade, the mean grade 3 or higher rate was 6.5%.[24]
Urinary biomarker panels (NGAL, KIM-1, MCP-1, and broader urinary proteomic screens) have been proposed to predict which equivocal cases will progress, but none is yet clinical-grade.[7]
Special situations
Crossing vessel
Identify and preserve lower-pole vessels during planning and surgery. Dismembered pyeloplasty can address both intrinsic narrowing and extrinsic compression; whether to transpose the UPJ relative to a vessel depends on the reconstructed anatomy.[22] Pure vascular hitch (Hellström-style transposition without dismemberment) risks leaving an undiagnosed intrinsic component and is generally avoided in adults.[14][17]
Failed pyeloplasty
A pediatric redo-pyeloplasty review cites primary-series redo rates of about 3% for recurrent UPJO.[25] In a meta-analysis of 287 pediatric redo pyeloplasties, success was 93.1% open, 92.1% laparoscopic and 89.4% robotic, without significant differences.[25] Adult-specific redo evidence remains limited. A 2026 meta-analysis of 12 comparative studies (549 adults and children) associated redo pyeloplasty with higher odds of study-defined success than endopyelotomy or balloon dilation (OR 6.32, 95% CI 3.25–12.32); definitions and follow-up varied, and risk of bias was high to serious.[39] Endopyelotomy is a selective salvage option for short recurrent strictures without a crossing vessel; longer redo strictures may require redo dismembered pyeloplasty or ureterocalicostomy.[1][39] Buccal mucosa onlay ureteroplasty has been described for selected nonobliterative recurrences after failed pyeloplasty, with surgical success (no flank pain and no imaging obstruction) in 8/10 patients at median 10.3 months in one retrospective series.[44]
Concomitant stones
Stones in an obstructed pelvis or calyces can be cleared at the time of pyeloplasty, including through a nephroscope during laparoscopic repair; the evidence is small case series.[26]
Fibroepithelial polyp
A fibroepithelial polyp is a rare intraluminal cause of UPJO: in one pediatric institutional series spanning 1967–2002, it accounted for 0.5% of all UPJOs seen during that period.[31] All 9 patients (11 renal units) underwent dismembered pyeloplasty; one later required nephrectomy for progressive functional loss, while no polyp recurred over a mean 44-month follow-up.[31] A polyp confined to the UPJ is usually removed along with the aperistaltic segment during pyeloplasty; whether endoscopic resection alone is adequate for a UPJ polyp remains unresolved because few cases have been reported.[32] A polyp elsewhere in the ureter, away from the UPJ, is generally managed by ureteroscopic excision: a systematic review of 134 adult ureteral-polyp cases across all ureteral locations found that the endoscopically resected share rose from 0% before 1985 to 67% after 2005, with recurrent complaints in 7.0% of the 57 patients with follow-up data, most within a year of endoscopic resection.[33] Earlier reports favored segmental sleeve resection and reanastomosis to prevent recurrence.[33]
Anatomic anomalies
UPJO is over-represented in horseshoe and malrotated kidneys; aberrant rotation or fusion alters the location of the crossing vessel and the dependent point of the pelvis, and dismembered pyeloplasty must be tailored accordingly.[8]
Outcomes
A systematic review of adults with baseline differential function ≤30% found symptom improvement in 73.3–93.3% of 141 assessed adults, while a >5-point functional gain occurred in 13.3–53.8% of 160 with paired scans; evidence quality was low and no recovery predictor was consistent.[23] In a 129-case retrospective RALP cohort, mean follow-up was 33.8 months (range 1–147), with estimated 8-year failure-free survival of 91.5% (96.3% for stented repairs).[16] In claims data from adults aged 18–64, most secondary procedures after endopyelotomy or pyeloplasty occurred within two years.[18] A long-term institutional series reported endopyelotomy and laparoscopic-pyeloplasty failures after five years.[17]
See Also
- Upper Tract Reconstruction database: full operative atlas indexed by location and technique
- Pyeloplasty: Anderson–Hynes dismembered and non-dismembered repairs; reference operation for UPJO
- Endoureterotomy: endopyelotomy for short intrinsic stenosis without a crossing vessel
- Balloon Dilation: minimally invasive option for select short strictures
- Ureterocalicostomy: salvage for failed pyeloplasty with an intrarenal pelvis
- BMG Onlay Ureteroplasty: buccal mucosa onlay for long or redo proximal strictures
- Ureteral Stricture: acquired strictures of the upper, mid, and distal ureter
References
1. Rai A, Hsieh A, Smith A. "Contemporary diagnosis and management of pelvi-ureteric junction obstruction." BJU Int. 2022;130(3):285–290. doi:10.1111/bju.15689
2. Khan F, Ahmed K, Lee N, et al. "Management of ureteropelvic junction obstruction in adults." Nat Rev Urol. 2014;11(11):629–638. doi:10.1038/nrurol.2014.240
3. Weitz M, Portz S, Laube GF, Meerpohl JJ, Bassler D. "Surgery versus non-surgical management for unilateral ureteric-pelvic junction obstruction in newborns and infants less than two years of age." Cochrane Database Syst Rev. 2016;7:CD010716. doi:10.1002/14651858.CD010716.pub2
4. Sheybani-Deloui S, Chi L, Staite MV, et al. "Activated Hedgehog-Gli signaling causes congenital ureteropelvic junction obstruction." J Am Soc Nephrol. 2018;29(2):532–544. doi:10.1681/ASN.2017050482
5. Alberti C. "Congenital ureteropelvic junction obstruction: physiopathology, decoupling of tout court pelvic dilatation-obstruction semantic connection, biomarkers to predict renal damage evolution." Eur Rev Med Pharmacol Sci. 2012;16(2):213–219. PMID 22428472
6. Whitworth P, Courtney KG, Oto A, et al. "ACR Appropriateness Criteria® Hydronephrosis on prior imaging — unknown cause." J Am Coll Radiol. 2024;21(6S):S144–S167. doi:10.1016/j.jacr.2024.02.020
7. Diamond DA, Chan IHY, Holland AJA, et al. "Advances in paediatric urology." Lancet. 2017;390(10099):1061–1071. doi:10.1016/S0140-6736(17)32282-1
8. Meshaka R, Biassoni L, Leung G, Mushtaq I, Hiorns MP. "Radiological and surgical correlation of pelviureteric junction obstruction in positional anomalies of the kidney in children." Pediatr Radiol. 2023;53(3):544–557. doi:10.1007/s00247-022-05557-7
9. Wolf JS, Siegel CL, Brink JA, Clayman RV. "Imaging for ureteropelvic junction obstruction in adults." J Endourol. 1996;10(2):93–104. doi:10.1089/end.1996.10.93
10. Cai PY, Lee RS. "Ureteropelvic junction obstruction / hydronephrosis." Urol Clin North Am. 2023;50(3):361–369. doi:10.1016/j.ucl.2023.04.001
11. Kohno M, Ogawa T, Kojima Y, et al. "Pediatric congenital hydronephrosis (ureteropelvic junction obstruction): medical management guide." Int J Urol. 2020;27(5):369–376. doi:10.1111/iju.14207
12. Gurbuz C, Best SL, Donnally C, et al. "Intermediate term outcomes associated with the surveillance of ureteropelvic junction obstruction in adults." J Urol. 2011;185(3):926–929. doi:10.1016/j.juro.2010.10.082
13. Autorino R, Eden C, El-Ghoneimi A, et al. "Robot-assisted and laparoscopic repair of ureteropelvic junction obstruction: a systematic review and meta-analysis." Eur Urol. 2014;65(2):430–452. doi:10.1016/j.eururo.2013.06.053
14. Rassweiler JJ, Subotic S, Feist-Schwenk M, et al. "Minimally invasive treatment of ureteropelvic junction obstruction: long-term experience with an algorithm for laser endopyelotomy and laparoscopic retroperitoneal pyeloplasty." J Urol. 2007;177(3):1000–1005. doi:10.1016/j.juro.2006.10.049
15. Li P, Ma Y, Jin X, et al. "Comparative efficacy and safety of different minimal invasive pyeloplasty in treating patients with ureteropelvic junction obstruction: a network meta-analysis." World J Urol. 2023;41(10):2659–2669. doi:10.1007/s00345-023-04559-w
16. Hopf HL, Bahler CD, Sundaram CP. "Long-term outcomes of robot-assisted laparoscopic pyeloplasty for ureteropelvic junction obstruction." Urology. 2016;90:106–110. doi:10.1016/j.urology.2015.12.050
17. Yanke BV, Lallas CD, Pagnani C, McGinnis DE, Bagley DH. "The minimally invasive treatment of ureteropelvic junction obstruction: a review of our experience during the last decade." J Urol. 2008;180(4):1397–1402. doi:10.1016/j.juro.2008.06.020
18. Jacobs BL, Lai JC, Seelam R, et al. "The comparative effectiveness of treatments for ureteropelvic junction obstruction." Urology. 2018;111:72–77. doi:10.1016/j.urology.2017.09.002
19. O'Reilly PH. "Functional outcome of pyeloplasty for ureteropelvic junction obstruction: prospective study in 30 consecutive cases." J Urol. 1989;142(2 Pt 1):273–276. doi:10.1016/s0022-5347(17)38728-1
20. Taylor AT, Brandon DC, de Palma D, et al. SNMMI procedure standard/EANM practice guideline for diuretic renal scintigraphy in adults with suspected upper urinary tract obstruction 1.0. Semin Nucl Med. 2018;48:377–390. doi:10.1053/j.semnuclmed.2018.02.010
21. European Association of Urology. Paediatric Urology guideline: dilatation of the upper urinary tract / PUJ obstruction. 2026.
22. Boylu U, Oommen M, Lee BR, Thomas R. Ureteropelvic junction obstruction secondary to crossing vessels—to transpose or not? The robotic experience. J Urol. 2009;181:1751–1755. doi:10.1016/j.juro.2008.11.114
23. Freitas PFS, Barbosa JABA, Andrade HS, et al. Pyeloplasty in adults with ureteropelvic junction obstruction in poorly functioning kidneys: a systematic review. Urology. 2021;156:e66–e73. doi:10.1016/j.urology.2021.05.017
24. Greenwald D, Mohanty A, Andolfi C, et al. Systematic Review and Meta-Analysis of Pediatric Robot-Assisted Laparoscopic Pyeloplasty. J Endourol. 2022;36(4):448-461. doi:10.1089/end.2021.0363
25. Chandrasekharam VVS, Babu R. A systematic review and metaanalysis of open, conventional laparoscopic and robot-assisted laparoscopic techniques for re-do pyeloplasty for recurrent uretero pelvic junction obstruction in children. J Pediatr Urol. 2022;18(5):642-649. doi:10.1016/j.jpurol.2022.08.025
26. An L, Xiong L, Chen L, et al. Concomitant Treatment of Ureteropelvic Junction Obstruction Complicated by Renal Calculi with Laparoscopic Pyeloplasty and Pyelolithotomy via 19.5F Rigid Nephroscope: A Report of 12 Cases. J Invest Surg. 2022;35(1):77-82. doi:10.1080/08941939.2020.1824248
27. Moody TE, Vaughn ED Jr, Gillenwater JY. Relationship between renal blood flow and ureteral pressure during 18 hours of total unilateral uretheral occlusion. Implications for changing sites of increased renal resistance. Invest Urol. 1975;13(3):246-251. PMID 1193822
28. Moody TE, Vaughan ED Jr, Gillenwater JY. Comparison of the renal hemodynamic response to unilateral and bilateral ureteral occlusion. Invest Urol. 1977;14(6):455-459. PMID 858664
29. Jaffe RB, Middleton AW Jr. Whitaker test: differentiation of obstructive from nonobstructive uropathy. AJR Am J Roentgenol. 1980;134(1):9-15. doi:10.2214/ajr.134.1.9
30. Lupton EW, George NJ. The Whitaker test: 35 years on. BJU Int. 2010;105(1):94-100. doi:10.1111/j.1464-410X.2009.08609.x
31. Adey GS, Vargas SO, Retik AB, et al. "Fibroepithelial polyps causing ureteropelvic junction obstruction in children." J Urol. 2003;169(5):1834-1836. doi:10.1097/01.ju.0000061966.21966.94
32. Li R, Lightfoot M, Alsyouf M, et al. "Diagnosis and management of ureteral fibroepithelial polyps in children: a new treatment algorithm." J Pediatr Urol. 2015;11(1):22.e1-22.e6. doi:10.1016/j.jpurol.2014.08.004
33. Ludwig DJ, Buddingh KT, Kums JJ, et al. "Treatment and outcome of fibroepithelial ureteral polyps: a systematic literature review." Can Urol Assoc J. 2015;9(9-10):E631-E637. doi:10.5489/cuaj.2878
34. Nguyen Thi Mai T, Nguyen Phuong T. "Laparoscopic dismembered pyeloplasty for ureteropelvic junction obstruction in children: a single-surgeon experience." Front Pediatr. 2026;14:1735651. doi:10.3389/fped.2026.1735651
35. National Institute for Health and Care Excellence. Acute kidney injury: prevention, detection and management (NG148), recommendations 1.5.1–1.5.2. Published 2019; updated 2024.
36. Dong J, Wong J, Al-Enezi A, et al. "Laparoscopic pyeloplasty: the updated McMaster University experience." Can Urol Assoc J. 2008;2(4):388–391. doi:10.5489/cuaj.806
37. Aubert O, M’Tiri S, Kühnapfel A, et al. "The optimal stent-strategy in paediatric pyeloplasty: a systematic review and network meta-analysis." BJU Int. 2026 Aug 16. Online ahead of print. doi:10.1111/bju.70423
38. Wiratma MKY, Ghinorawa T, Yuri P. "The outcome of stenting and its duration after pyeloplasty in children with ureteropelvic junction obstruction (UPJO): a systematic review and meta-analysis." BMC Urol. 2025;25(1):227. doi:10.1186/s12894-025-01841-4
39. Chua ME, Wong MM, Gouwtama M, et al. "Challenging recurrent ureteropelvic junction obstructions: endoscopic procedures versus redo-pyeloplasty—a systematic review and meta-analysis." World J Urol. 2026;44(1):256. doi:10.1007/s00345-026-06339-8
40. Tchetgen MB, Bloom DA. "Robert H. Whitaker and the Whitaker test: a pressure-flow study of the upper urinary tract." Urology. 2003;61(1):253–256. doi:10.1016/S0090-4295(02)01545-5
41. Klingler HC, Remzi M, Janetschek G, et al. "Comparison of open versus laparoscopic pyeloplasty techniques in treatment of uretero-pelvic junction obstruction." Eur Urol. 2003;44(3):340–345. doi:10.1016/S0302-2838(03)00297-5
42. Ryan AG, Irvine I, Bardgett H, van der Meer R, Rea D, Carrafiello G. "CIRSE Standards of Practice on Nephrostomy and Ureteric Stent Placement and Exchange." Cardiovasc Intervent Radiol. 2026;49(3):464–479. doi:10.1007/s00270-025-04328-9
43. Mesrobian HG, Kelalis PP. "Ureterocalicostomy: indications and results in 21 patients." J Urol. 1989;142(5):1285–1287. doi:10.1016/S0022-5347(17)39058-4
44. Lee M, Nagoda E, Strauss D, Loecher M, Stifelman M, Zhao L. "Role of buccal mucosa graft ureteroplasty in the surgical management of pyeloplasty failure." Asian J Urol. 2024;11(3):373–376. doi:10.1016/j.ajur.2023.09.001
45. Szydelko T, Kasprzak J, Apoznanski W, Zdrojowy R. "Laparoscopic anterior Y-V pyeloplasty: a valuable treatment option in patients with small or intrarenal pelvis." J Laparoendosc Adv Surg Tech A. 2010;20(7):627–630. doi:10.1089/lap.2010.0223
46. Birkhäuser FD, von Rütte T, Moltzahn F, Huber P, Zehnder P. "A Short Double-J Ureteral Stent Indwelling Time Is Safe and Effective Following Minimally Invasive Pyeloplasty: Long-term Results from a Prospective Randomized Controlled Trial." Eur Urol Open Sci. 2025;74:28–33. doi:10.1016/j.euros.2025.01.014