Ureterovaginal Fistula
A ureterovaginal fistula (UVF) is an abnormal connection between the ureter and the vagina.[29] UVF commonly follows ureteral injury during hysterectomy or other pelvic surgery; its share of referred urogenital fistulas varies by setting and era.[1][2][3] A characteristic presentation is continuous vaginal urinary leakage with preserved normal voiding per urethra, because one ureter leaks while the contralateral kidney drains normally into an intact bladder. Early endoscopic stent placement, when feasible, is AUA-recommended initial management.[3]
For the operative settings that produce UVF, see Cesarean Section, Hysterectomy, Radical Hysterectomy and Pelvic Lymphadenectomy and Intraoperative Consultation. Reimplantation, psoas hitch, and Boari flap technique are covered in detail in Ureteral Stricture — distal reconstruction. For operative selection see the Female Fistula Repair database; the definitive repair pages are Ureteral Reimplantation and Boari Flap & Psoas Hitch.
Epidemiology
- UVF accounted for 11/67 (16.4%) confirmed fistulas in a French tertiary-center cohort from 2010–2024 and 21/68 (30.9%) in a historical UCLA referral series reported in 1980.[1][2]
- Ureteral injury complicates about 1.0% of hysterectomies for benign indications; 18.6% of these injuries are recognized only in delayed fashion, a subset of which evolve into UVF.[4]
- After radical hysterectomy for cervical cancer, UVF occurs in about 2.4% of cases.[5]
- In a meta-analysis of radical hysterectomy for early-stage cervical cancer, minimally invasive surgery was associated with higher odds of UVF than open surgery (OR 4.44).[6]
Etiology and Anatomy of Injury
| Setting | Notes |
|---|---|
| Hysterectomy (benign or radical) | Dominant cause across all routes — abdominal, vaginal, laparoscopic, robotic[1][2][3] |
| Cesarean section | Increasingly recognized; left-sided predominance with adhesions from prior cesarean[9][10] |
| Pelvic prolapse / incontinence surgery | Concurrent prolapse or sling adds risk[1] |
| Colorectal surgery | LAR, APR, sigmoidectomy near the pelvic brim |
| Obstetric obstructed labor | Rare in HIC; classical setting in low-resource environments |
| Pelvic radiation / malignancy | Ischemic, often delayed fistulae; repair success is lower in irradiated tissue across urinary fistulae[25] |
| Penetrating pelvic trauma | Rare |
Three anatomic danger zones during pelvic surgery
- Pelvic brim. The ureter crosses the iliac vessels near the common iliac bifurcation; the crossing may be over the common or external iliac artery.[32]
- Uterine artery crossing. "Water under the bridge," 1–2 cm lateral to the cervix
- Cardinal ligament / vaginal cuff. Ureter enters the bladder just lateral to the upper vagina
Mechanisms include ligation, transection, crush, kinking, devascularization, and thermal injury, the last especially during laparoscopic or robotic dissection. In one 19-patient UVF series, no ureteral injury was recognized at the index operation.[4][6][7]
Risk factors
The hysterectomy associations below concern urinary tract injury in an observational cohort; the radical-hysterectomy comparison concerns UVF.[4][6]
| Risk factor | OR |
|---|---|
| Concurrent prolapse repair[4] | 1.44 |
| Concurrent incontinence procedure[4] | 1.40 |
| Mesh-augmented prolapse repair[4] | 1.55 |
| Endometriosis[4] | 1.46 |
| Low-volume facility[4] | 1.37 |
| Minimally invasive vs open radical hysterectomy[6] | 4.44 |
Clinical Presentation
The hallmark is sudden continuous vaginal urinary leakage 1–4 weeks after pelvic surgery in a patient who continues to void normally per urethra.[7][8][9]
| Feature | UVF | VVF |
|---|---|---|
| Vaginal leakage | Continuous | Continuous |
| Voiding per urethra | Preserved | Often diminished or absent |
| Ipsilateral flank pain | Reported in 5/8 women with post-cesarean UVF in one series[9] | Uncommon |
| Hematuria | May be absent | Sometimes present |
Normal voiding with continuous vaginal leakage should prompt evaluation for UVF, including the upper tracts.
Diagnostic Evaluation
The workup answers three questions: Is it UVF or VVF? Where is the injury? Is the upper tract obstructed or infected?
Double-dye test (the bedside discriminator)
Begin with a complete history and focused examination, including direct vaginal inspection; measure fluid creatinine if the urinary origin of leakage is uncertain.[25] The double-dye test can then help localize leakage:[2][12][13]
- Methylene blue / indigo carmine instilled into the bladder via Foley
- Oral phenazopyridine given for 1–2 days before the test until urine is bright orange[29]
- A vaginal tampon is placed for 30–60 minutes
| Tampon staining | Interpretation |
|---|---|
| Blue | Supports a bladder communication |
| Orange without blue | Supports UVF; confirm anatomy with upper-tract imaging |
| Mixed staining | Orally colored urine also reaches the bladder |
Imaging and endoscopy
| Modality | Role | Notes |
|---|---|---|
| CT urography | Used in 58% of 19 UVF cases in one retrospective series | Hydronephrosis, contrast extravasation into vagina, fistula tract; delayed images essential[7][12] |
| Renal ultrasound | Rapid screen for hydronephrosis | Drives decision to drain the upper tract[9] |
| Retrograde pyelogram + cystoscopy | Helps define the ureteral injury and permits attempted retrograde stenting | May be performed when planning endoscopic intervention[2][8] |
| Antegrade pyelogram | When retrograde access fails | Pairs naturally with PCN and antegrade stent placement[14][17] |
Management
AUA recommends initial stent placement when feasible and permits additional surgical intervention if stenting fails (Statement 11c; Recommendation, Grade C). Its discussion reports stent success of 64–100% in six series of 11–46 patients.[3]
Step 1 — protect the upper tract
If hydronephrosis is significant, the kidney is infected, or there is a coexistent urinoma, percutaneous nephrostomy decompresses the system and serves as the access for antegrade stenting if retrograde fails. An infected obstructed collecting system requires urgent drainage and antibiotics; drainage may require a retrograde stent or PCN, and an infected or persistent urinoma may need separate drainage.[10][18]
Step 2 — endoscopic ureteral stent (first-line)
| Approach | Notes |
|---|---|
| Retrograde JJ stent | Cystoscopic; guidewire passed across the injured segment into the renal pelvis; reported dwell times include 6 weeks in a post-cesarean series, at least 4–8 weeks in another series, and a mean 66 days (range 27–92) in Chen et al.[9][14][27] |
| Antegrade JJ stent | Via PCN when retrograde fails[14][17] |
Earlier stenting was associated with higher success in a systematic review of 799 UVFs drawn entirely from retrospective studies. Selection, injury severity and timing were heterogeneous:[16]
| Time to stent | Pooled success |
|---|---|
| < 2 weeks | 95% (95% CI 87–100%) |
| 2–6 weeks | 46% (95% CI 0–100%) |
| > 6 weeks | 20% (95% CI 1–49%) |
Individual series report 64–100% success when stent passage is feasible (for example 5 of 7 in Shaw et al.; a stent could be passed in 13 of 17 in Rajamaheswari et al.; Chen et al. placed stents successfully in 11/12 patients, but ultimate conservative management succeeded in 10/12; stents remained a mean 66 days (range 27–92), with pyelonephritis in 2/11 and stricture in 1/11).[3][7][14][15][27] The meta-analysis pooled stenting success across all timings at only 32% (95% CI 7–64), so failure is common and the surgical plan should be ready.[16] The pragmatic rule is to attempt retrograde stenting at the first encounter and proceed antegrade through PCN if retrograde fails. Delayed referral compounds the problem, both because tissue inflammation matures and because the injured segment may have completed its sloughing.
Step 3 — surgical reconstruction (when stenting fails or is infeasible)
Reconstruction is indicated for complete transection, inability to traverse the injury, or persistent fistula after stenting; in Chen et al.'s 19-case series, concurrent VVF, prior ureteral repair at the index operation, or a one-year diagnostic delay led to primary reimplantation.[3][7][15][27]
The reconstruction follows the same distal-ureter ladder used for any iatrogenic stricture — see Ureteral Stricture — distal reconstruction:
| Defect | Procedure |
|---|---|
| Short distal | Ureteroneocystostomy (anti-refluxing or refluxing) |
| Distal with insufficient reach | Psoas hitch with reimplantation can bridge selected longer lower-ureter defects; a 24-patient adult series included defects of 3–10 cm.[33] |
| Mid-to-distal defect beyond psoas-hitch reach | Boari flap ± psoas hitch when bladder capacity and tissue quality permit; a mixed-etiology retrospective cohort reported new LUTS in 8/29 women at mean 22.3-month follow-up.[31][34] |
| Mid ureteral, both ends viable | Ureteroureterostomy |
| Long defect, no bladder reach, contralateral ureter healthy | Transureteroureterostomy (rarely chosen today) |
| Poorly functioning ipsilateral kidney with a normal contralateral kidney | Nephrectomy as a last resort after reconstructive options are assessed[25] |
Timing of surgical repair is individualized. In retrospective UVF series, pooled surgical closure was 100% (95% CI 99–100) whether repair occurred within or after 6 weeks of diagnosis; the EAU female LUTS guideline gives a weak recommendation to tailor fistula repair timing after oedema, inflammation, tissue necrosis, or infection have resolved.[16][25] In a small retrospective series (n = 22), early reimplantation had shorter operative time and less blood loss than delayed repair, with no significant difference in stricture rate.[26] An obstructed or infected system needs drainage regardless of the repair schedule.
Open, laparoscopic and robotic reconstruction are options selected by anatomy, tissue quality, resources and surgeon experience. In Kidd et al., all 12 UVF patients (all after failed stent or nephrostomy drainage; 10 reimplantations and two ureteroureterostomies) were free of leakage off drains or stents at mean 29.3 months, with no reported complications.[11]
Approach selection
| Approach | Role | Evidence |
|---|---|---|
| Robotic | Selected patients at centers with reconstructive expertise | Small series demonstrate feasibility and good reported outcomes[11][19][20] |
| Laparoscopic | Similar reconstructive principles where expertise is available | Case series and technical reports; no established equivalence or superiority over other routes[22][23] |
| Open | Established option, including complex or combined reconstruction | Route individualized[1][2][3] |
| Transvaginal | Highly selected low fistula with accessible distal ureter | Limited case-series evidence[24] |
Operative principles (any approach)
- Identify healthy ureter and mobilize only as needed, preserving adventitia and periureteral blood supply
- Transect above the injured segment; distal management varies by operative findings. Linder et al. described ligating the distal ureteral remnant, whereas Yuan et al. excised the fibrous tract and cauterized its remainder.[19][30]
- Spatulation of the proximal ureter
- Posterior / posterolateral cystotomy
- Tension-free, mucosa-to-mucosa anastomosis over a JJ stent
- Test integrity with retrograde bladder fill
- Pelvic drain; cystogram before catheter removal in selected cases; stent removed at about 6 weeks
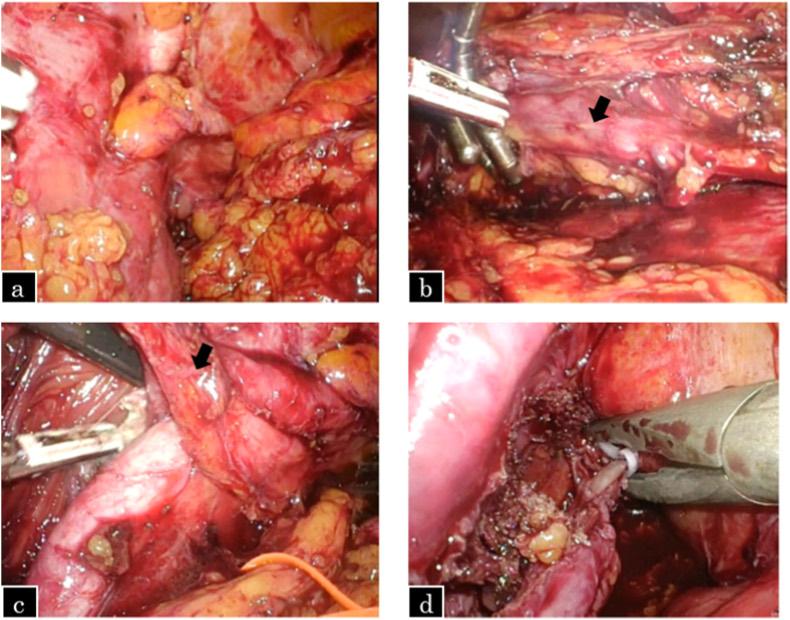
Laparoscopic ureteroneocystostomy for iatrogenic ureterovaginal fistula after modified radical hysterectomy, dissection: (a) scarred area around the injured distal ureter; (b) proximal ureter (arrow) lifted by the retractor; (c) dissection between the strongly adherent iliac artery and the ureter (arrow); (d) clipping the end of the distal ureter. From Machida Y, et al. Urol Case Rep. 2022;44:102144, Fig. 2 (CC BY 4.0).[28]
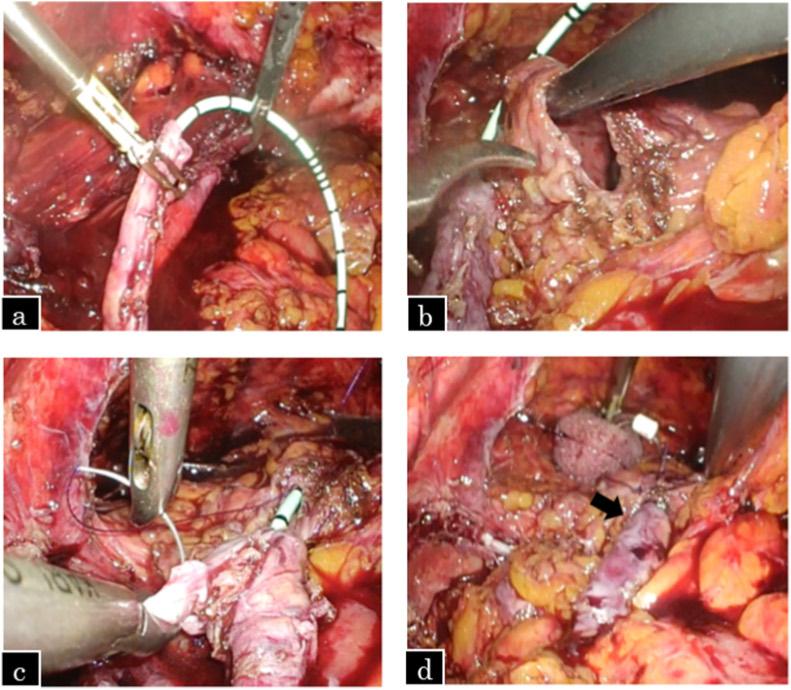
The same repair, reimplantation: (a) ureteral stent being placed; (b) bladder opened; (c) ureter anastomosed to the bladder; (d) end of the anastomosis and submucosal tunnel (arrow). From Machida Y, et al. Urol Case Rep. 2022;44:102144, Fig. 3 (CC BY 4.0).[28]
Postoperative care and follow-up
- Foley catheter 7–14 d; cystogram before removal in selected cases[19]
- JJ stent removed at about 6 weeks
- Renal ultrasound about 6 weeks after stent removal to exclude hydronephrosis
- Use anatomical and functional imaging after repair to monitor for ureteric stricture and deterioration in renal function.[25] Routine repeated CT urography is not necessary for every uncomplicated repair
- Long-term surveillance for late stricture is advisable
Outcomes
| Management | Success | Notes |
|---|---|---|
| Stent placed < 2 wk | 95% | Retrospective pooled estimate[16] |
| Stent placed at 2–6 wk | 46% | Very imprecise pooled estimate[16] |
| Stent placed > 6 wk | 20% | Lower reported success; assess feasibility individually[16] |
| Surgical reconstruction | High reported closure | Selected series; definitions and follow-up differ[1][2][16] |
| Robotic UVF repair (multi-inst.) | 12/12 at mean 29.3 mo | Selected cohort, including two ureteroureterostomies[11] |
Immediate vs Delayed Recognition
In a retrospective cohort of benign hysterectomies, immediate recognition of ureteral injury was associated with fewer subsequent fistulas.[4]
| Timing of recognition | Subsequent fistula rate | Stent alone without subsequent ureteral repair |
|---|---|---|
| Immediate (intraoperative) | 0.7% | 99.0% |
| Delayed (postoperative) | 3.4% | 39.8% |
The stent endpoint was avoidance of a second ureteral repair after injury, not closure of established UVF. Cystoscopy and assessment of ureteral efflux can identify some injuries; a normal examination does not exclude delayed thermal or ischemic injury.
Concurrent Fistulas
In Chen et al.'s 19-case UVF series, 3 patients had concurrent VVF and underwent primary reimplantation; Binstock et al. reported one combined case repaired with vaginal VVF closure and abdominal ureteroneocystostomy.[27][21] Assess for contralateral ureteric injury before a unilateral repair plan. For suspected UVF, the EAU weakly recommends contrast-enhanced CT with a late excretory phase and/or MRI to assess urinary-tract anatomy.[25]
Prevention
- Intraoperative cystoscopy when injury is suspected or indicated by the procedure; interpret ureteral efflux alongside the operative findings[4]
- Prophylactic ureteral stents may help identify the ureter in selected difficult dissections, but have not been shown to prevent injury and are not routinely recommended solely for that purpose[25]
- Anatomic identification of the ureter at the three danger zones during every dissection
- Avoid excessive thermal energy near the ureter on laparoscopic / robotic platforms[6]
- Refer high-complexity cases to higher-volume centers[4]
- Among identified ureteral injuries during benign hysterectomy, immediate recognition and repair was associated with a subsequent genitourinary fistula rate of 0.7% versus 3.4% after delayed recognition and repair; this is an observational association[4]
Algorithm summary
- Suspect UVF: vaginal leakage with normal voiding, with or without flank pain, after pelvic surgery
- Confirm: double-dye test, CT urography, cystoscopy with retrograde pyelogram
- Protect the upper tract: drain significant obstruction, urgently when infected, with a retrograde stent when feasible or PCN when stenting fails or is impossible.[3][10]
- Attempt retrograde JJ stenting promptly when feasible, ideally at diagnostic cystoscopy; consider antegrade stenting through PCN if retrograde access fails
- Remove the stent after the planned dwell interval; one post-cesarean series used 6 weeks, followed by upper-tract imaging.[9][27]
- If stenting fails or fistula persists: robotic or open ureteroneocystostomy, with or without psoas hitch or Boari flap
See Also
- Female Fistula Repair database
- Principles of Fistula Repair
- Ureteral Reimplantation
- Boari Flap & Psoas Hitch
Videos
References
1. Zhang C, Saussine C, Tricard T. "Urogenital fistulas: surgical management, outcomes, and prognostic factors — a 14-year monocentric experience." Int Urogynecol J. 2026. doi:10.1007/s00192-026-06580-0
2. Goodwin WE, Scardino PT. "Vesicovaginal and ureterovaginal fistulas: a summary of 25 years of experience." J Urol. 1980;123(3):370–374. doi:10.1016/s0022-5347(17)55941-8
3. Morey AF, Broghammer JA, Hollowell CMP, et al. Urotrauma Guideline 2020: AUA Guideline. J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408. Full guideline, published 2014; amended April 2017 and August 2020.
4. Dallas KB, Rogo-Gupta L, Elliott CS. "Urologic injury and fistula after hysterectomy for benign indications." Obstet Gynecol. 2019;134(2):241–249. doi:10.1097/AOG.0000000000003353
5. Likic IS, Kadija S, Ladjevic NG, et al. "Analysis of urologic complications after radical hysterectomy." Am J Obstet Gynecol. 2008;199(6):644.e1–644.e3. doi:10.1016/j.ajog.2008.06.034
6. Hwang JH, Kim B. "Postoperative urinary complications in minimally invasive versus abdominal radical hysterectomy: a meta-analysis with a focus on ureterovaginal fistula." J Minim Invasive Gynecol. 2025;32(6):502–511. doi:10.1016/j.jmig.2024.12.009
7. Shaw J, Tunitsky-Bitton E, Barber MD, Jelovsek JE. "Ureterovaginal fistula: a case series." Int Urogynecol J. 2014;25(5):615–621. doi:10.1007/s00192-013-2272-y
8. Murphy DM, Grace PA, O'Flynn JD. "Ureterovaginal fistula: a report of 12 cases and review of the literature." J Urol. 1982;128(5):924–925. doi:10.1016/s0022-5347(17)53279-6
9. Rabani SM, Rabani S. "Early detection and endoscopic management of post cesarean section ureterovaginal fistula: a case series study." Int Urogynecol J. 2021;32(9):2537–2541. doi:10.1007/s00192-020-04589-7
10. Meirow D, Moriel EZ, Zilberman M, Farkas A. "Evaluation and treatment of iatrogenic ureteral injuries during obstetric and gynecologic operations for nonmalignant conditions." J Am Coll Surg. 1994;178(2):144–148.
11. Kidd LC, Lee M, Lee Z, et al. "A multi-institutional experience with robotic vesicovaginal and ureterovaginal fistula repair after iatrogenic injury." J Endourol. 2021;35(11):1659–1664. doi:10.1089/end.2020.0993
12. Rogers RG, Jeppson PC. "Current diagnosis and management of pelvic fistulae in women." Obstet Gynecol. 2016;128(3):635–650. doi:10.1097/AOG.0000000000001519
13. Hanash KA, Al Zahrani H, Mokhtar AA, Aslam M. "Retrograde vaginal methylene blue injection for localization of complex urinary fistulas." J Endourol. 2003;17(10):941–943. doi:10.1089/089277903772036334
14. Selzman AA, Spirnak JP, Kursh ED. "The changing management of ureterovaginal fistulas." J Urol. 1995;153(3 Pt 1):626–628. doi:10.1016/S0022-5347(01)67668-7
15. Rajamaheswari N, Chhikara AB, Seethalakshmi K. "Management of ureterovaginal fistulae: an audit." Int Urogynecol J. 2013;24(6):959–962. doi:10.1007/s00192-012-1959-9
16. Bahuguna G, Panwar VK, Mittal A, et al. "Management strategies and outcome of ureterovaginal fistulae: a systematic review and meta-analysis." Neurourol Urodyn. 2022;41(2):562–572. doi:10.1002/nau.24874
17. Lang EK. "Diagnosis and management of ureteral fistulas by percutaneous nephrostomy and antegrade stent catheter." Radiology. 1981;138(2):311–317. doi:10.1148/radiology.138.2.7455109
18. Mueller PR, vanSonnenberg E. "Interventional radiology in the chest and abdomen." N Engl J Med. 1990;322(19):1364–1374. doi:10.1056/NEJM199005103221906
19. Linder BJ, Frank I, Occhino JA. "Extravesical robotic ureteral reimplantation for ureterovaginal fistula." Int Urogynecol J. 2018;29(4):595–597. doi:10.1007/s00192-017-3459-4
20. Laungani R, Patil N, Krane LS, et al. "Robotic-assisted ureterovaginal fistula repair: report of efficacy and feasibility." J Laparoendosc Adv Surg Tech A. 2008;18(5):731–734. doi:10.1089/lap.2008.0037
21. Binstock MA, Semrad N, Dubow L, Watring W. "Combined vesicovaginal-ureterovaginal fistulas associated with a vaginal foreign body." Obstet Gynecol. 1990;76(5 Pt 2):918–921. doi:10.1097/00006250-199011000-00045
22. Abdel-Karim A, Elmissiry M, Moussa A, et al. "Laparoscopic repair of female genitourinary fistulae: 10-year single-center experience." Int Urogynecol J. 2020;31(7):1357–1362. doi:10.1007/s00192-019-04002-y
23. Hudry D, El Hajj H, Narducci F, Leblanc E. "Laparoscopic ureteral reimplantation applying the modified psoas hitch and Lich-Gregoir onlay technique: a 10-step surgical video." Int Urogynecol J. 2022;33(9):2577–2579. doi:10.1007/s00192-021-04990-w
24. Boateng AA, Eltahawy EA, Mahdy A. "Vaginal repair of ureterovaginal fistula may be suitable for selected cases." Int Urogynecol J. 2013;24(6):921–924. doi:10.1007/s00192-013-2070-6
25. European Association of Urology. Non-neurogenic Female LUTS Guidelines: Disease Management — Urinary Fistula. 2026. Guideline.
26. Long G, Ouyang W, Huang D, et al. "Management for ureterovaginal fistula: a retrospective study comparing early and delayed ureteral reimplantation." Urol Int. 2023;107(4):377–382. doi:10.1159/000522550
27. Chen YB, Wolff BJ, Kenton KS, Mueller ER. "Approach to ureterovaginal fistula: examining 13 years of experience." Female Pelvic Med Reconstr Surg. 2019;25(2):e7–e11. doi:10.1097/SPV.0000000000000690
28. Machida Y, Yoshiuchi H, Kitano Y, Kamizuru M, Uchida J. "Laparoscopic ureteroneocystostomy for iatrogenic ureterovaginal fistula after modified radical hysterectomy: a case report." Urol Case Rep. 2022;44:102144. doi:10.1016/j.eucr.2022.102144
29. Elneil S, Romanzi L, Goh J, et al. "An International Continence Society (ICS) report on the terminology for female pelvic floor fistulas." Neurourol Urodyn. 2020;39(8):2040–2071. doi:10.1002/nau.24508
30. Yuan C, Wang J, Cheng S, et al. "Robotic ureteral reimplantation for the management of ureterovaginal fistula: four cases at a single center." Transl Androl Urol. 2021;10(10):3705–3713. doi:10.21037/tau-21-454
31. Hardesty JK, Burns RT, Soyster ME, Jansen NE, Mellon M. "Female bladder dysfunction following Boari bladder flap ureteral reconstruction." Urology. 2024;186:31–35. doi:10.1016/j.urology.2024.01.020
32. Kostov S, Kornovski Y, Watrowski R, Slavchev S, Ivanova Y, Yordanov A. "Internal iliac artery ligation in obstetrics and gynecology: surgical anatomy and surgical considerations." Clin Pract. 2024;14(1):32–51. doi:10.3390/clinpract14010005
33. Manassero F, Mogorovich A, Fiorini G, Di Paola G, De Maria M, Selli C. "Ureteral reimplantation with psoas bladder hitch in adults: a contemporary series with long-term followup." ScientificWorldJournal. 2012;2012:379316. doi:10.1100/2012/379316
34. Bourillon A, Peyronnet B, McGuire BB, et al. "Ureteral stricture: current treatment algorithm and key surgical principles in the robotic upper urinary tract reconstruction era." World J Urol. 2026;44(1):102. doi:10.1007/s00345-025-06181-4