Vesicovaginal Fistula
A vesicovaginal fistula (VVF) is an epithelialized communication between the bladder and vagina that produces continuous, painless urinary leakage per vaginum. In high-income countries it is overwhelmingly iatrogenic, most commonly after benign gynecologic surgery, while in low-resource settings it is dominated by prolonged obstructed labor and remains a global public-health problem.[1][2][3]
For the operative settings that produce VVF, see Cesarean Section, Hysterectomy, Radical Hysterectomy and Pelvic Lymphadenectomy and Intraoperative Consultation. Cross-compartment and complex-fistula principles are kept on the Fistulas section landing. For operative selection across all repair routes, see the Female Fistula Repair database.
Epidemiology and Etiology
VVF is the most common acquired GU fistula in women.[1][4]
| Etiology | Setting | Notes |
|---|---|---|
| Benign gynecologic surgery | Hysterectomy is the dominant cause in high-income countries; hysterectomy for benign disease accounts for roughly 60–75% of post-surgical VVF and cesarean about 6%[37] | In English NHS data the overall vesicovaginal or urethrovaginal fistula rate within 1 year was about 1 in 788 (0.13%), ranging from 1 in 3,861 after vaginal hysterectomy for prolapse to 1 in 87 (~1.1%) after radical hysterectomy for cervical cancer.[5] EAU quotes 0.1–4% across hysterectomy types and about 9-fold higher risk after radical than simple hysterectomy.[37] Randomized trials show more urinary tract (mainly ureteric) injury with laparoscopic than abdominal hysterectomy (OR 2.16); fistula rates by route are not established in trials[41] |
| Cesarean delivery | Uterine incision into the bladder, bladder-flap injury, placenta accreta spectrum | Often vesicouterine rather than vesicovaginal; see Vesicouterine Fistula |
| Obstetric — prolonged obstructed labor | Dominant cause in sub-Saharan Africa and South Asia | Pressure necrosis of the anterior vaginal wall and bladder against the symphysis; addressed in detail in Obstetric Fistula |
| Pelvic radiation | Cervical, endometrial, vaginal, rectal cancer treatment | Late presentation (months to years); poor tissue quality; high recurrence; strongly favors vascularized tissue interposition or diversion discussion. Fistula after primary radiotherapy may signal tumor recurrence. EAU reports fistula proportions of about 1.9% after postoperative external-beam radiation and 0.8% after intravaginal brachytherapy; tumor, stage, radiation-site and dose heterogeneity limits direct comparison.[6][37] |
| Pelvic malignancy | Direct invasion or post-treatment necrosis | Workup must rule out recurrence before reconstruction |
| Mesh erosion | Synthetic midurethral sling or transvaginal mesh erosion through bladder | Mesh excision concurrent with repair |
| Trauma | Penetrating, foreign body, sexual violence | Rare in high-income settings |
Risk factors for VVF after incidental cystotomy
Two academic-center case-control series of incidental cystotomy during benign hysterectomy identify a consistent dominant predictor. A higher-grade cystotomy (AAST grade V bladder injury) carried the strongest association with subsequent VVF in both: grade V injury was present in 75% of the four VVF cases versus 7% of 30 cystotomies without VVF in a 1,317-hysterectomy single-center cohort (p = 0.004), and grade V injury carried an OR of 93.0 (95% CI 10.3–838.9) in a 5,698-hysterectomy multicenter cohort.[46][47] In the multicenter series, larger uterine weight (>250 g, 83% vs 36%, p = 0.03) and longer operative time (317 vs 208 minutes, p = 0.02) were also associated with VVF formation; tobacco use and greater blood loss trended toward association without reaching significance in the smaller series.[46][47] A Swedish national registry found hysterectomy increased the risk of pelvic-organ fistula surgery roughly fourfold overall (23.8 versus 6.3 per 100,000 person-years), with the highest fistula rates after laparoscopic hysterectomy, the lowest after subtotal abdominal hysterectomy, and higher rates among older women.[48]
Pathophysiology
Three injury mechanisms drive VVF formation, and they predict tissue quality at the time of repair:[1][2]
- Direct surgical injury. Unrecognized cystotomy at the time of hysterectomy or cesarean, or a suture placed through bladder wall during cuff closure. Tissue is otherwise healthy; fistula declares itself 1–3 weeks postoperatively as the suture line breaks down.
- Ischemic. Devascularization of the bladder base from electrothermal injury, hemostatic suture, or compressive packing. Presents at 2–6 weeks; surrounding tissue may be inflamed but generally heals well after excision.
- Pressure necrosis. Sustained compression of the vesicovaginal septum between the fetal head and the symphysis pubis (obstetric) or by retained foreign body. Tissue loss is broader than the visible defect; calcification, fibrosis, and field damage extend well beyond the fistula edge.
Radiation VVF is a fourth category. Endarteritis obliterans produces progressive ischemia, the tissue bed is hostile and worsens with time, and recurrence risk is high. Vascularized interposition is often considered, but comparative evidence is limited.[6]
Classification
Simple vs complex (operative phenotype)
The single most important categorization at the bedside:[7][8]
| Feature | Simple | Complex |
|---|---|---|
| Number | Single | Multiple |
| Size | Small (cutoffs vary: about 2–2.5 cm in urologic series; WHO/EAU adapted classification uses < 4 cm) | Larger (≥ 2.5 cm, or > 4 cm by WHO/EAU criteria) |
| Location | Supratrigonal, away from ureteral orifices | Trigonal / juxta-ureteral, involving bladder neck |
| Etiology | Iatrogenic (post-hysterectomy), non-irradiated | Obstetric, post-radiation, malignancy-related, mesh |
| Prior repair | None | One or more failed |
| Tissue | Healthy | Scarred, ischemic, irradiated |
Goh classification (most widely used global system)
Goh's system grades fistulas on three axes: distance from external urethral meatus, fistula size, and degree of fibrosis / vaginal length. It predicts continence outcome after closure.[9]
| Axis | Grades |
|---|---|
| Distance from meatus | I > 3.5 cm; II 2.5–3.5 cm; III 1.5–2.5 cm; IV < 1.5 cm |
| Fistula size (largest diameter) | a < 1.5 cm; b 1.5–3 cm; c > 3 cm |
| Special considerations | i none/mild fibrosis and preserved vaginal length; ii moderate/severe fibrosis and/or reduced vaginal length; iii special circumstances such as ureteric involvement, circumferential defect, radiation or previous repair |
Waaldijk classification (obstetric-fistula-focused)
Type I fistulas do not involve the urethral closing mechanism; Type II fistulas do (subdivided A/B by absence or presence of subtotal or total urethral involvement and a/b by absence or presence of a circumferential defect); Type III covers ureteric and other exceptional fistulas. Closure and continence worsen progressively from Type I to Type IIBb. Used primarily in obstetric-fistula practice and outcome reporting in low-resource settings.[10]
EAU notes that Waaldijk and Goh were designed for obstetric fistula and are less relevant to iatrogenic fistula; it strongly recommends a detailed anatomic description that distinguishes simple from complex fistula and presents adapted WHO criteria (simple: single, < 4 cm, no sphincter, ureter or circumferential involvement, minimal tissue loss, first repair; complex: larger, multiple, scarred, radiation-related, or previously repaired).[37]
Clinical Presentation
- Continuous, painless urinary leakage per vaginum beginning 1–3 weeks postoperatively (iatrogenic) or after a difficult delivery (obstetric)
- Leakage may be positional, worse supine and sometimes provoked by bladder filling
- Reduced or absent voiding per urethra when the fistula is large
- Recurrent UTI, vaginal candidiasis, vulvar excoriation
- Psychosocial morbidity, particularly in obstetric fistula, where social isolation and depression are part of the syndrome[3]
- In a retrospective series of 31 patients with post-hysterectomy VVF, clinical anxiety and depression each affected 51.6% before repair and 16.1% and 12.9%, respectively, at the 3- or 6-month assessment; none had fistula leakage after repair.[55]
A surgeon called to evaluate "post-hysterectomy incontinence" must rule out VVF before attributing leakage to detrusor overactivity, sphincter injury, or ureterovaginal fistula.
Diagnostic Evaluation
The workup answers four questions: Is it VVF? Where is it relative to the ureters? Is the upper tract involved? Is there cancer recurrence?
Office maneuvers
- Speculum exam: pooled urine in the vault, visible fistula tract on the anterior vaginal wall (often after reduction of inflammation)
- Dye test (single-tampon or three-swab): intravesical blue dye appearing in the vagina supports a bladder communication. Oral phenazopyridine may help distinguish orange upper-tract urine from blue bladder fluid. Confirm suspected upper-tract involvement with appropriate imaging.[11]
- Vaginoscopy with a cystoscope: useful when the fistula is small or covered by granulation tissue
Endoscopy and imaging
- Cystoscopy helps confirm and map the fistula. EAU weakly recommends cystoscopy with retrograde colored bladder filling for diagnostic confirmation. Cystoscopy defines the tract relative to both ureteral orifices, identifies multiple tracts, and assesses for mesh, foreign bodies or intravesical lesions.[2][37]
- CT urogram: assesses for synchronous ureterovaginal fistula or upper-tract obstruction; in Hilton’s 348-referral urogenital fistula series, 13 women (3.7%) had combined vesicovaginal and ureterovaginal lesions[1]. EAU weakly recommends contrast-enhanced CT with a late excretory phase and/or MRI when the diagnosis is difficult or ureterovaginal fistula is suspected; the guideline also notes that creatinine testing of collected fluid can confirm it is urine[37]
- Pelvic MRI: preferred for radiation VVF, recurrent fistula, and suspected malignancy recurrence; characterizes tissue quality and defect anatomy
- Retrograde or antegrade pyelogram: when CT urogram is equivocal for ureteral involvement
Adjuncts
- Urine culture before any repair attempt
- EUA when in-office examination is non-diagnostic, particularly for the small, late-presenting fistula
- Biopsy of the fistula edge if there is any concern for malignancy or recurrence in the radiated patient
- Videourodynamics is not a routine part of the fistula workup but is considered selectively when a suspected or confirmed fistula coexists with lower urinary tract symptoms, or when bladder or urethral function could change counseling or reconstruction; it can help distinguish stress or urgency incontinence and other causes of leakage from fistula, and it can assess capacity, compliance, and urethral function relevant to augmentation, diversion, or continence planning. For a large fistula that prevents adequate bladder filling, vaginal packing, supine positioning, or temporary occlusion of the tract with a catheter or balloon have been described to allow the study to proceed[49]
Management
Conservative — bladder drainage alone
A small (about < 1 cm), early-recognized, non-irradiated VVF may close with continuous catheter drainage, usually assessed after 2–4 weeks and extended selectively to 4–8 weeks if the leak is clearly improving. Reported spontaneous closure averages about 13% (± 23%) and applies mainly to small fistulas; across reviewed reports it ranged from 0 to 100%, with a shorter interval from injury to drainage the best predictor of success, before the tract epithelializes.[12][37] Antimuscarinics may help bladder spasms. Conservative catheter drainage is reasonable for selected small, recent fistulas, but most fistulas require operative closure; persistent leakage after a limited drainage trial warrants reassessment for repair.[12][37]
Timing of repair
The classic teaching of a 3–6 month delay to allow inflammation to resolve has been challenged by contemporary series and guideline review.[8][37][38][4] Repair when infection is controlled, necrosis has declared itself, exposure is adequate, and the tissue will hold sutures.[8][37][38]
| Timing | Indication |
|---|---|
| Immediate (intraoperative recognition) | Iatrogenic injury identified at the index operation — repair on the table after urologic consult |
| Brief drainage trial (2–4 wk, extend to 4–8 wk if improving) | Small, fresh, non-irradiated VVF with healthy surrounding tissue and no distal obstruction (early catheter-and-close data come largely from a 170-patient obstetric series)[13] |
| Early repair (within 4 wk in the cited guideline comparison) | Simple post-hysterectomy or post-cesarean VVF once acute inflammation is quiet and exposure is good; a 16-patient post-hysterectomy series reported complete continence at 1 month[21], while EAU cites small uncontrolled series suggesting no difference in success rates between early (within 4 wk) and delayed (after 3 mo) repair[37] |
| Delayed repair (often ≥ 3 mo) | Persistent inflammation, large or multiple fistulas, prior failed repair, complex anatomy, malnutrition, infection, or uncertain tissue viability |
| Long delay / diversion discussion (6–12 mo or longer) | Radiation VVF or malignancy-related field injury — tissue quality dominates, recurrence risk is high, and urinary diversion may be the most durable endpoint[6][20] |
EAU cites small uncontrolled series showing no difference in success between early (within 4 weeks) and delayed (after 3 months) closure, and a 2026 retrospective laparoscopic comparison (n = 23) found leak-free, cystoscopically confirmed closure at 3 months in 10/11 early repairs (within 3 weeks) and 11/12 delayed repairs (at ≥ 3 months).[37][43] Retrospective timing comparisons are vulnerable to confounding because complex or inflamed fistulas are more likely to be delayed. Prioritize tissue readiness and patient circumstances.[20][37]
Surgical principles (apply to every approach)
- Cystoscopic mapping. Confirm fistula location and rule out ureteral involvement; place ureteral stents if either orifice is within 1 cm of the tract
- Exposure with viable tissue preservation. Mobilize bladder and vagina for a flap-splitting repair; Latzko repair instead denudes the surrounding vaginal epithelium while retaining the tract.[36][37]
- Selective fistula-edge / tract management. EAU describes one RCT, while a 2024 systematic review identified two RCTs (140 women); the trials did not show improved closure with trimming, and failed trimmed repairs may leave larger recurrent defects. Tailor trimming, freshening or excision to approach, fibrosis, tissue viability and defect size.[22][24][37][38]
- Tension-free closure suited to the approach. Flap-splitting repair closes bladder mucosa and detrusor/fibromuscular tissue separately from vaginal wall, with offset suture lines; Latzko repair retains the tract, places a purse-string outside it, imbricates denuded vaginal tissue, then closes the vaginal epithelium.[36][37]
- Vascularized tissue interposition when indicated. Not routine for simple, non-irradiated primary VVF; strongly favored for radiation, recurrent, large, mesh-associated, or tissue-deficient fistulas[7][18][26][27]
- Continuous catheter drainage. WHO recommends 7–10 days as an alternative to longer drainage after repair of a simple obstetric urinary fistula, supported by a noninferiority RCT that randomized 524 women with simple female genital fistulas (mostly obstetric) whose repairs remained closed at postoperative day 7; by 3 months, repair breakdown in the 501-patient per-protocol analysis was 10/250 (4.0%) after 7-day versus 8/251 (3.2%) after 14-day drainage (radiation and complex fistulas excluded).[39][40] A 2026 IUGA/ICS Delphi consensus advises a minimum of 10–14 days of catheter drainage after obstetric VVF repair and a dye test at catheter removal.[58] For post-surgical and complex repairs, EAU states that no high-level evidence determines catheter duration and weakly recommends continuous drainage until healing is confirmed; expert opinion suggests 10–14 days for simple or post-surgical and 14–21 days for complex or post-radiation fistulas.[37] Individualize duration and leak testing; a cystogram can miss a persistent fistula if it has no voiding phase or if the fistula is at the bladder neck.[37]
- Bladder rest. Anticholinergics to suppress detrusor activity and avoid suture-line stress
Fistula Tract Excision: Not a Universal Rule
The evidence on fistula tract excision is mixed, and no high-quality comparative trial has definitively shown that excision improves VVF closure compared with non-excision techniques.[25][38]
| Setting | Typical tract strategy | Evidence signal |
|---|---|---|
| Latzko partial colpocleisis | No tract excision; vaginal epithelium around the fistula is denuded and the tract is inverted / imbricated | In selected postsurgical apical VVF series, 11/11 fistulas closed after Latzko repair and 100/108 after the initial modified Latzko repair; eight recurrences closed after repeat repair, giving 108/108 eventual closure at mean 41 months.[15][35] A video description of the technique is also available.[36] |
| Transvaginal multilayered closure | Variable: mobilize bladder and vagina widely; freshen or trim edges only if needed | Edge freshening remains debated; trimming can enlarge the defect or weaken an already scarred suture line.[24][38] |
| Open / laparoscopic / robotic abdominal repair | Tract excision is commonly performed because exposure permits separation of bladder and vagina around the fistula | Robotic and laparoscopic series using systematic excision report high closure, but they usually combine excision with meticulous mobilization, multilayer closure, drainage, and frequent interposition.[22][23] |
| Scarred, recurrent, or obstetric tissue | Preserve viable tissue; avoid converting a small tract into a large defect | A 1,185-repair multinational experience (12 countries; 64% VVF) reported overall closure of 82%, 91% in simple fistulas and 85% in primary repairs; complexity was the dominant determinant of closure.[24] |
The operative endpoint is healthy, mobile, watertight tissue layers under no tension. If excision helps achieve that, it is reasonable; if it enlarges the hole or compromises blood supply, non-excision or minimal freshening is more reconstructive.
Surgical Approach
The choice of approach depends on fistula location, vaginal access, surgeon expertise, tissue quality, and the need for concurrent ureteral reimplant or augmentation.[8][14][15][25]
| Approach | Best fit | Caveats |
|---|---|---|
| Transvaginal — classic flap repair (Sims-style) | Most simple supratrigonal VVFs with good vaginal access | Mobilizes bladder and vagina for layered closure; fistula edges may be freshened, but routine wide excision is debated |
| Transvaginal — Latzko partial colpocleisis | Small, post-hysterectomy, vault-apex fistula in a patient with a deep vagina | Inverts the fistula without tract excision; possible vaginal shortening; the cited apical series reported 11/11 closure and 100/108 closure after initial study repair in the modified Latzko cohort (108/108 after repeat repair)[15][35] |
| Transabdominal — open or laparoscopic O'Conor | Large, juxta-ureteral, complex, or recurrent VVF; concurrent need for ureteral reimplant or augmentation | Sagittal cystotomy carried down to the fistula; tract usually excised; bladder closed in two layers with omental or peritoneal interposition between bladder and vagina[16][23] |
| Robotic O'Conor / extravesical repair | Same indications as open abdominal repair, especially when high or peri-orifice anatomy is hard to expose vaginally | A four-patient robotic series reported no recurrence and mean LOS 1.75 days; a 22-patient series reported no recurrence at median 15 months; an earlier laparoscopic review reported 80–100% success across heterogeneous series at 1–74 months; techniques vary between transvesical and extravesical routes[14][17][22] |
Transvaginal repair — operative pearls
- Position. High lithotomy or prone jackknife (the latter for the difficult-to-expose vault fistula in a foreshortened vagina)
- Schuchardt incision to widen vaginal access when needed
- Hold the fistula edge with stay sutures. Convert a hole into a slit by tagging at 12 and 6 o'clock to deliver the edges
- Avoid aggressive tract excision in the small fistula; Latzko-style mucosal denudation and inverting closure preserves bladder tissue but may shorten the vagina
- Martius flap: labial fat-pad flap mobilized on its inferior pedicle, tunneled subcutaneously to the fistula bed (see Martius flap)
- Test with retrograde fill of dilute methylene blue before closing the vaginal layer
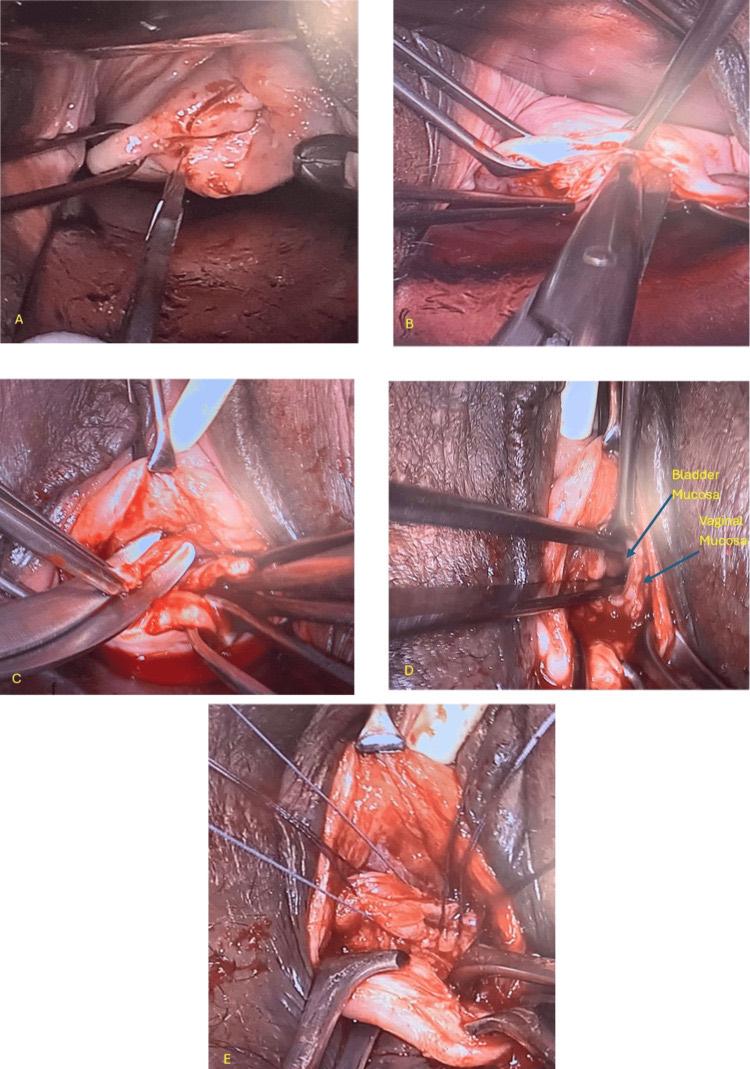
Transvaginal repair of a post-hysterectomy vesicovaginal fistula: (A) ovoid incision in the vaginal mucosa around the fistula; (B) deep excision of the fistulous tract with Metzenbaum scissors until healthy bladder mucosa is reached; (C) excision of fibrous tissue and freshening of the margins; (D) healthy bladder mucosa (labeled) visible after debridement, deep to the vaginal mucosa; (E) single-layer interrupted closure of the bladder mucosa with polyglactin 3-0. From Silva DO, et al. Cureus. 2026;18(6):e110195, Figure 2 (CC BY 4.0).[54]
Transabdominal (O'Conor) repair — operative pearls
- Bladder bivalving. Sagittal cystotomy from the dome down to (but not through) the fistula
- Tract excision or controlled edge freshening when it helps create healthy margins; avoid unnecessary enlargement of a small defect
- Wide bladder–vagina dissection to allow non-overlapping closure
- Omental pedicle interposition between the closed bladder and vagina is the standard interposition for the abdominal approach; alternatives are peritoneal flap (laparoscopic / robotic) or rectus muscle flap
- Robotic reports include transvesical and extravesical or transvaginal approaches; select exposure and interposition tissue to fit anatomy[14][17]
Tissue interposition
Vascularized tissue between the closed bladder and vagina ismost useful when the tissue bed is irradiated, recurrent, mesh-injured, ischemic, large, or difficult to close without tension.[6][7][18][26][27]
| Tissue | Best use | Notes |
|---|---|---|
| Martius flap | Selected transvaginal repairs of vaginal or perineal fistulas when the pedicle reaches the defect | Often low morbidity, but a mixed 97-patient vaginal-reconstruction series (20 VVF) reported labial numbness in 13, pain in five and distortion in nine at mean 85 months; counsel about these donor-site effects.[26][56] |
| Omental pedicle | Transabdominal / robotic O'Conor; radiation cases | Excellent bulk; depends on omental reach |
| Peritoneal flap | Robotic / laparoscopic; when omentum unavailable | Limited bulk; reliable for non-radiated repair |
| Gracilis muscle flap | Recurrent, large, or radiated VVF; failed prior interposition | Requires medial-thigh harvest; substantial bulk |
| Urachal flap | Transabdominal / robotic O'Conor, when omentum is unavailable or hard to reach | Ligated below the umbilicus and mobilized with its lateral peritoneal wings before being folded between bladder and vagina; a 13-patient series reported success in 12 (92%)[51] |
The Martius flap deserves a specific caveat in obstetric-fistula practice: Browning's retrospective study of 440 repairs found no significant difference in breakdown rates and more residual incontinence in three Martius subgroups. Nonrandomized allocation prevents a causal conclusion that the flap itself caused those differences. This reinforces that interposition is a tool for specific indications (radiation, recurrence, large defect, hostile bed), not a default for every repair.[18]
Emerging adjuncts
Adjunct materials are most useful when ordinary layered closure lacks a healthy second layer. For a full flap-and-adjunct selection framework, see Tissue Interposition Flaps.
| Adjunct | Potential role | Evidence signal |
|---|---|---|
| Buccal mucosal graft (BMG) | Second layer for scarred, shortened, or tissue-deficient vaginal repairs; robotic interposition when vaginal tissue is inadequate | Small contemporary series and case reports suggest feasibility, including 100% closure in a 10-patient transvaginal series and successful robotic BMG interposition with omentum.[28][29] |
| Platelet-rich plasma / fibrin | Biological adjunct for recurrent or poorly healing tissue; peri-fistula injection and/or interposition after de-epithelialization | Small uncontrolled VVF series report high closure, including 11/12 standalone PRP/PRF cures and recurrent-case neoadjuvant PRP before Latzko repair; evidence remains low quality.[30][31][32] |
| Small intestinal submucosa (SIS) | Off-the-shelf acellular matrix for complicated VVF when local tissue is thin or scarred | A 23-patient complicated-VVF pilot reported 21/23 women dry through 6 months after SIS interposition, without reported allergic or inflammatory reactions.[33] |
| Fibrin glue / sealant interposition | Interposed layer between bladder and vaginal closures in transvaginal repair | In an RCT of complicated obstetric VVF, 13/19 (68.4%) were dry with glue and 11/19 (57.9%) with a Martius flap through 3 months, without a statistically significant difference[57], and a 64-patient prospective randomized study reported leak-free status on postoperative day 21, after catheter removal, of 90.9% with glue, 90.5% with Martius and 81% with primary repair alone (p = 0.541); a systematic review found no significant improvement in cure with fibrin glue.[37][38][44] |
| Regenerative bioglues / scaffolds | Investigational sealants or matrices | Preclinical bioglue models are promising but not ready to replace vascularized tissue in irradiated or recurrent human VVF.[34] |
Outcomes
Reported closure rates span 58–100% across VVF series (EAU), and a review reported 70–100% success for non-radiated fistulas; these series include mixed repair histories and fistula complexity. Prior failed repair and adverse fistula characteristics are associated with lower success.[2][7][8][19] A large multinational experience illustrates the gradient: anatomic closure was 91% for simple fistulas, 79% for recurrent fistulas, and 68% for complex fistulas.[24]
| Setting | Typical first-attempt closure | Notes |
|---|---|---|
| Non-radiated VVF, vaginal or abdominal | No comparable first-attempt estimate | Reviewed series reported 70–100% success (mean 91% vaginal, 97% abdominal); a four-patient robotic series reported no recurrence[8][14] |
| Robotic / laparoscopic abdominal repair | No comparable first-attempt estimate (14 robotic series, 206 patients: recurrence 2.91%; earlier laparoscopic/robotic review: reported success 80–100% at 1–74 months) | Most stays under 5 days; transvesical and extravesical routes similar; no randomized comparison with open repair[14][17][22][42] |
| Latzko (selected vault VVF) | No pooled first-procedure estimate (11/11 in one selected series; 100/108 after initial study repair in the modified Latzko cohort, with eight additional closures after repeat repair) | Possible vaginal shortening; preserves bladder[15][35] |
| Obstetric VVF (high-volume centers) | ~80–95% closure; continence lower | Among Malawi women who returned for follow-up within 120 days after first VVF repair and had successful closure, 85/372 (23%) had residual incontinence; a separate multinational series of mixed female genital fistulas (64% VVF; 59% obstetric) reported 12% after successful closure.[3][24][45] |
| Radiation VVF | 48.1% at first repair, 66.6% cumulatively after a second repair, and 80.4% after all operations (216 patients treated; 210 vaginal repairs are the outcome denominator); permanent diversion is a legitimate alternative | Tissue quality dominates outcome; results with the same techniques are consistently poorer than for surgical fistulas[6][37] |
A retrospective ACS-NSQIP database analysis of 200 VVF repairs from 2006 to 2013 (65% vaginal, the remainder abdominal) found the abdominal approach associated with higher 30-day morbidity than the vaginal approach: overall complications 22% versus 7%, sepsis 4.3% versus 0%, transfusion 7.1% versus 0.8%, and readmission about 10% versus 1% (p ≤ 0.02 for each).[50] In the 2006–2013 ACS-NSQIP analysis, fistula anatomy and closure were unrecorded, leaving the adjusted route–morbidity association susceptible to confounding by case complexity.[50] In a larger, partly overlapping ACS-NSQIP cohort of 449 repairs (2009–2020), open abdominal repair had more unadjusted major complications (4.7% versus 0.8% vaginal and 0% laparoscopic/robotic), but approach was not associated with major or minor complications after adjustment (p = 0.76); prolonged hospitalization remained associated with open repair.[59]
Residual incontinence occurred in 85/372 women (23%) within 120 days of successful VVF closure in a Malawi cohort; a separate mixed female genital-fistula series reported 12% after closure. Urethral involvement, vaginal scarring and circumferential defects were associated with poorer continence outcomes; some patients underwent bulking or pubovaginal sling treatment.[19][24][45] After repair, EAU also lists de novo overactive bladder, ureteric obstruction, bladder contracture, vaginal stenosis and dyspareunia among complications to counsel about.[37]
In selected obstetric fistulas with bladder-neck or urethral involvement, a concomitant continence procedure at the time of repair is an option. A retrospective comparison of a pubococcygeal sling, refixation of the pubocervical fascia, or both reported negative postoperative dye tests in 142/169 (84.0%), 62/69 (89.9%), and 30/32 (93.8%) of those tested, respectively; clinical stress incontinence was recorded in 74/157 (47.1%), 32/67 (47.8%), and 14/32 (43.8%) with continence assessments, respectively. The dye-test and overall continence-status comparisons were not statistically significant, and there was no repair-only comparison arm.[52] A small randomized trial comparing a pubococcygeal sling with an autologous fascial sling at the time of repair found no significant difference in pad weight or quality of life between the two, and was stopped early after repair breakdowns in both arms.[53]
Special Situations
Radiation VVF
Tissue quality is the rate-limiting factor.[6]
- Wait for tissue stabilization after radiation and complete malignancy workup before attempting repair; many cases require 6–12 months or longer
- Hyperbaric oxygen may be considered for selected radiation tissue injury, but evidence does not establish a standard regimen that improves VVF closure
- Use tissue interposition ;[37] vascularized options include omentum, Martius, gracilis, or rectus flap depending on route and defect
- Counsel about recurrence and about permanent urinary diversion as an alternative when reconstruction is not feasible; if bowel is used, EAU weakly recommends avoiding irradiated segments.[37]
Mesh-erosion VVF
- Concurrent mesh excision with VVF repair
- Avoid leaving residual synthetic material at the suture line
- Tissue interposition recommended even for "simple"-appearing mesh-related VVFs
Recurrent VVF
- Reassess exposure and tissue quality. EAU weakly recommends repairing persistent urogenital fistulas by an abdominal approach (open, laparoscopic or robotic, according to availability and competence);[37] one institutional review considers repeat vaginal repair acceptable after a failed vaginal repair[8]
- Vascularized interposition or another healthy second layer is usually required
- Diversion (continent or incontinent) is a valid endpoint after multiple failures
Large or trigonal VVF involving the ureteral orifice
- Stent both ureters preoperatively if either is within 1 cm of the tract
- Consider concurrent ureteral reimplant at the time of repair when the fistula involves the ureteral orifice
- Consider an abdominal or robotic approach when reimplantation or adequate exposure requires it; selected high fistulas remain accessible vaginally
See Also
- Female Fistula Repair database
- Principles of Fistula Repair
- Transvaginal Latzko Repair
- Transvaginal Sims-Simon Multilayered Closure
- O'Conor (Transabdominal Transvesical) VVF Repair
- Extravesical Transabdominal VVF Repair
- Endoscopic VVF Management
- Conservative VVF Management
- Martius Flap for VVF
Videos
References
1. Hilton P. "Urogenital fistula in the UK: a personal case series managed over 25 years." BJU Int. 2012;110(1):102–110. doi:10.1111/j.1464-410X.2011.10630.x
2. Bodner-Adler B, Hanzal E, Pablik E, Koelbl H, Bodner K. "Management of vesicovaginal fistulas in women following benign gynaecologic surgery: a systematic review and meta-analysis." PLoS One. 2017;12(2):e0171554. doi:10.1371/journal.pone.0171554
3. Wall LL. "Obstetric vesicovaginal fistula as an international public-health problem." Lancet. 2006;368(9542):1201–1209. doi:10.1016/S0140-6736(06)69476-2
4. Stamatakos M, Sargedi C, Stasinou T, Kontzoglou K. "Vesicovaginal fistula: diagnosis and management." Indian J Surg. 2014;76(2):131–136. doi:10.1007/s12262-012-0787-y
5. Hilton P, Cromwell DA. "The risk of vesicovaginal and urethrovaginal fistula after hysterectomy performed in the English National Health Service: a retrospective cohort study." BJOG. 2012;119(12):1447–1454. doi:10.1111/j.1471-0528.2012.03474.x
6. Pushkar DY, Dyakov VV, Kasyan GR. "Management of radiation-induced vesicovaginal fistula." Eur Urol. 2009;55(1):131–137. doi:10.1016/j.eururo.2008.04.044
7. Eilber KS, Kavaler E, Rodríguez LV, Rosenblum N, Raz S. "Ten-year experience with transvaginal vesicovaginal fistula repair using tissue interposition." J Urol. 2003;169(3):1033–1036. doi:10.1097/01.ju.0000049723.57485.e7
8. Angioli R, Penalver M, Muzii L, et al. "Guidelines of how to manage vesicovaginal fistula." Crit Rev Oncol Hematol. 2003;48(3):295–304. doi:10.1016/s1040-8428(03)00123-9
9. Goh JTW. "A new classification for female genital tract fistula." Aust N Z J Obstet Gynaecol. 2004;44(6):502–504. doi:10.1111/j.1479-828X.2004.00315.x
10. Waaldijk K. "Surgical classification of obstetric fistulas." Int J Gynaecol Obstet. 1995;49(2):161–163. doi:10.1016/0020-7292(95)02350-l
11. Raghavaiah NV. "Double-dye test to diagnose various types of vaginal fistulas." J Urol. 1974;112(6):811–812. doi:10.1016/s0022-5347(17)59857-2
12. Bazi T. "Spontaneous closure of vesicovaginal fistulas after bladder drainage alone: review of the evidence." Int Urogynecol J Pelvic Floor Dysfunct. 2007;18(3):329–333. doi:10.1007/s00192-006-0194-7
13. Waaldijk K. "The immediate surgical management of fresh obstetric fistulas with catheter and/or early closure." Int J Gynaecol Obstet. 1994;45(1):11–16. doi:10.1016/0020-7292(94)90759-5
14. Bragayrac LA, Azhar RA, Fernandez G, et al. "Robotic repair of vesicovaginal fistulae with the transperitoneal-transvaginal approach: a case series." Int Braz J Urol. 2014;40(6):810–815. doi:10.1590/S1677-5538.IBJU.2014.06.12
15. Ansquer Y, Mellier G, Santulli P, et al. "Latzko operation for vault vesicovaginal fistula." Acta Obstet Gynecol Scand. 2006;85(10):1248–1251. doi:10.1080/00016340600804589
16. O'Conor VJ Jr, Sokol JK, Bulkley GJ, Nanninga JB. "Suprapubic closure of vesicovaginal fistula." J Urol. 1973;109(1):51–54. doi:10.1016/s0022-5347(17)60345-8
17. Miklos JR, Moore RD, Chinthakanan O. "Laparoscopic and robotic-assisted vesicovaginal fistula repair: a systematic review of the literature." J Minim Invasive Gynecol. 2015;22(5):727–736. doi:10.1016/j.jmig.2015.03.001
18. Browning A. "Lack of value of the Martius fibrofatty graft in obstetric fistula repair." Int J Gynaecol Obstet. 2006;93(1):33–37. doi:10.1016/j.ijgo.2006.01.003
19. Frajzyngier V, Ruminjo J, Barone MA. "Factors influencing urinary fistula repair outcomes in developing countries: a systematic review." Am J Obstet Gynecol. 2012;207(4):248–258. doi:10.1016/j.ajog.2012.02.006
20. Zhang C, Saussine C, Tricard T. "Urogenital fistulas: surgical management, outcomes, and prognostic factors: a 14-year monocentric experience." Int Urogynecol J. 2026;37(8):2535–2542. doi:10.1007/s00192-026-06580-0
21. Giusti G, Lucci Chiarissi M, Abate D, et al. "Early repair of post-hysterectomy vesicovaginal fistulae through a laparoscopic transperitoneal extravesical approach: experience of a single center." Urology. 2018;119:44–48. doi:10.1016/j.urology.2018.05.021
22. Lecoanet P, Madanelo M, Tricard T, et al. "Robot-assisted vesicovaginal fistula repair: comparison of the extravesical and transvesical techniques." Int Urogynecol J. 2023;34(10):2479–2485. doi:10.1007/s00192-023-05565-7
23. Abdel-Karim A, Elmissiry M, Moussa A, et al. "Laparoscopic repair of female genitourinary fistulae: 10-year single-center experience." Int Urogynecol J. 2020;31(7):1357–1362. doi:10.1007/s00192-019-04002-y
24. Mourad MS, Malallah M, Mahfouz W, et al. "Sixteen years of multinational experience in female genital fistula repair: integrating traditional and innovative surgical approaches across 12 countries." Neurourol Urodyn. 2026;45(3):583–590. doi:10.1002/nau.70226
25. Rafetto AN, Wei N, Linder BJ. "Principles and techniques of vesicovaginal fistula repair." Int Urogynecol J. 2026. doi:10.1007/s00192-026-06576-w
26. Kapriniotis K, Loufopoulos I, Gresty HCM, Greenwell TJ, Ockrim JL. "The utility of Martius fat pad in the repair of urogenital fistulae: review of current evidence." BJU Int. 2024;134(3):365–374. doi:10.1111/bju.16350
27. Neu S, Matta R, Herschorn S. "Transvaginal vesicovaginal fistula repair-high success with low morbidity despite radiation or prior repair." World J Urol. 2026;44(1):150. doi:10.1007/s00345-026-06233-3
28. Taha KM, Mohamed MI, Desoky E, et al. "Buccal mucosal graft as a second layer in the vaginal repair of vesicovaginal fistulas." Neurourol Urodyn. 2025;44(2):287–293. doi:10.1002/nau.25657
29. Rafetto AN, Lehner KP, Reynolds EA, Langstraat CL, Warner JN. "Robotic vesicovaginal fistula repair with buccal graft interposition." Int Urogynecol J. 2026. doi:10.1007/s00192-026-06717-1
30. Shirvan MK, Alamdari DH, Ghoreifi A. "A novel method for iatrogenic vesicovaginal fistula treatment: autologous platelet-rich plasma injection and platelet-rich fibrin glue interposition." J Urol. 2013;189(6):2125–2129. doi:10.1016/j.juro.2012.12.064
31. Streit-Ciećkiewicz D, Futyma K, Miotła P, et al. "Platelet-rich plasma as adjuvant therapy for recurrent vesicovaginal fistula: a preliminary report." J Clin Med. 2019;8(12):2122. doi:10.3390/jcm8122122
32. Streit-Ciećkiewicz DE, Knapik A, Rechberger T, et al. "Influence of platelet-rich plasma on recurrent vesicovaginal fistula: histological and immunohistochemical study." J Clin Med. 2024;13(2):370. doi:10.3390/jcm13020370
33. Farahat YA, Elbendary MA, Elgamal OM, et al. "Application of small intestinal submucosa graft for repair of complicated vesicovaginal fistula: a pilot study." J Urol. 2012;188(3):861–864. doi:10.1016/j.juro.2012.05.019
34. Kim HJ, Turner D, Shi R, et al. "Preclinical evaluation of a regenerative immiscible bioglue for vesico-vaginal fistula." Acta Biomater. 2021;125:183–196. doi:10.1016/j.actbio.2021.02.037
35. Luo DY, Shen H. "Transvaginal repair of apical vesicovaginal fistula: a modified Latzko technique-outcomes at a high-volume referral center." Eur Urol. 2019;76(1):84–88. doi:10.1016/j.eururo.2019.04.010
36. Kieserman-Shmokler C, Sammarco AG, English EM, Swenson CW, DeLancey JO. "The Latzko: a high-value, versatile vesicovaginal fistula repair." Am J Obstet Gynecol. 2019;221(2):160.e1–160.e4. doi:10.1016/j.ajog.2019.05.021
37. European Association of Urology. Non-neurogenic Female LUTS Guidelines: Disease Management — Urinary Fistula. 2026. Guideline.
38. Thompson JC, Halder GE, Jeppson PC, et al. "Repair of vesicovaginal fistulae: a systematic review." Obstet Gynecol. 2024;143(2):229–241. doi:10.1097/AOG.0000000000005468
39. World Health Organization. Recommendation on duration of bladder catheterization after surgical repair of simple obstetric urinary fistula. 2018. WHO recommendation.
40. Barone MA, Widmer M, Arrowsmith S, et al. "Breakdown of simple female genital fistula repair after 7 day versus 14 day postoperative bladder catheterisation: a randomised, controlled, open-label, non-inferiority trial." Lancet. 2015;386(9988):56–62. doi:10.1016/S0140-6736(14)62337-0
41. Pickett CM, Seeratan DD, Mol BWJ, et al. "Surgical approach to hysterectomy for benign gynaecological disease." Cochrane Database Syst Rev. 2023;8(8):CD003677. doi:10.1002/14651858.CD003677.pub6
42. Tavares M, do Carmo Pinto M, Conde Carvalho G, et al. "Vesicovaginal fistula robotics-assisted repair: a systematic review and quantitative synthesis." Int Urogynecol J. 2026. doi:10.1007/s00192-026-06578-8
43. Wang M, Yin F, Guan X, Li Q. "Early versus delayed laparoscopic repair of surgically induced vesicovaginal fistula." Urogynecology (Phila). 2026. doi:10.1097/SPV.0000000000001900
44. Choudhury S, Biswas P, Patel P, Sasmal S, Ahmed S. "Use of fibrin glue versus Martius flap interposition in transvaginal vesicovaginal fistula repair: a prospective randomized trial." Urologia. 2026;93(3):519–526. doi:10.1177/03915603261418997
45. Bengtson AM, Kopp D, Tang JH, et al. "Identifying patients with vesicovaginal fistula at high risk of urinary incontinence after surgery." Obstet Gynecol. 2016;128(5):945–953. doi:10.1097/AOG.0000000000001687
46. Duong TH, Gellasch TL, Adam RA. "Risk factors for the development of vesicovaginal fistula after incidental cystotomy at the time of a benign hysterectomy." Am J Obstet Gynecol. 2009;201(5):512.e1–4. doi:10.1016/j.ajog.2009.06.046
47. Duong TH, Taylor DP, Meeks GR. "A multicenter study of vesicovaginal fistula following incidental cystotomy during benign hysterectomies." Int Urogynecol J. 2011;22(8):975–979. doi:10.1007/s00192-011-1375-6
48. Forsgren C, Lundholm C, Johansson ALV, Cnattingius S, Altman D. "Hysterectomy for benign indications and risk of pelvic organ fistula disease." Obstet Gynecol. 2009;114(3):594–599. doi:10.1097/AOG.0b013e3181b2a1df
49. Brandon CA, Enemchukwu EA, Brucker BM. Diagnosis of Urogenital Fistula. In: Cardozo L, Staskin D, eds. Textbook of Female Urology and Urogynecology. Vol 2: Surgical Perspectives. 5th ed. CRC Press; 2023:1134-1145. doi:10.1201/9781003144243-115
50. Theofanides MC, Sui W, Sebesta EM, Onyeji I, Matulay JT, Chung DE. "Vesicovaginal fistulas in the developed world: an analysis of disease characteristics, treatments, and complications of surgical repair using the ACS-NSQIP database." Neurourol Urodyn. 2017;36(6):1622–1628. doi:10.1002/nau.23167
51. James MH, Tisdale BE, Davies TO, McCammon KA. "The urachal flap: a previously unreported tissue flap in vesicovaginal fistula repair." Female Pelvic Med Reconstr Surg. 2013;19(3):148–151. doi:10.1097/SPV.0b013e3182830b67
52. Pope R, Ganesh P, Wilkinson J. "Pubococcygeal sling versus refixation of the pubocervical fascia in vesicovaginal fistula repair: a retrospective review." Obstet Gynecol Int. 2018;2018:6396387. doi:10.1155/2018/6396387
53. Pope R, Browning A, Chipungu E, George JOM, Tamimu M, Wilkinson J. "Prophylactic autologous slings at the time of obstetric fistula repair: a randomized clinical trial." Female Pelvic Med Reconstr Surg. 2021;27(2):78–84. doi:10.1097/SPV.0000000000000745
54. Silva DO, Almeida R, Lima D, Paiva MB, Sarmento R. "Vaginal repair of post-hysterectomy vesicovaginal fistula with a Martius flap: a case report." Cureus. 2026;18(6):e110195. doi:10.7759/cureus.110195
55. Fujisaki A, Kinjo M, Shimoinaba M, Honda S, Yoshimura Y. "An evaluation of the impact of post-hysterectomy vesicovaginal fistula repair on the mental health of patients in a developed country." Int Urogynecol J. 2020;31(7):1371–1375. doi:10.1007/s00192-019-04131-4
56. Lee D, Dillon BE, Zimmern PE. "Long-term morbidity of Martius labial fat pad graft in vaginal reconstruction surgery." Urology. 2013;82(6):1261–1266. doi:10.1016/j.urology.2013.08.032
57. Safan A, Shaker H, Abdelaal A, Mourad MS, Albaz M. "Fibrin glue versus Martius flap interpositioning in the repair of complicated obstetric vesicovaginal fistula. A prospective multi-institution randomized trial." Neurourol Urodyn. 2009;28(5):438–441. doi:10.1002/nau.20754
58. Maljaars LP, Corcos J, Ghoniem G, et al. "Consensus statements on the definition of surgical success following obstetric urinary pelvic floor fistula repair: an IUGA-ICS proposal." Int Urogynecol J. 2026;37(5):1193–1205. doi:10.1007/s00192-025-06413-6
59. Jefferson FA, Hanson KT, Robinson MO, et al. "Perioperative outcomes of vesicovaginal fistula repair by surgical approach." Urogynecology (Phila). 2024;30(2):114–122. doi:10.1097/SPV.0000000000001394