Rectovesical Fistula
A rectovesical fistula (RVF) is an epithelialized communication between the rectal lumen and the bladder. In contemporary practice the condition is rare but devastating, and is most often the consequence of prostate cancer treatment: radical prostatectomy (open, laparoscopic, or robotic), external-beam radiation, brachytherapy, or ablative salvage therapies (HIFU, cryotherapy). Less common etiologies include inflammatory bowel disease, pelvic trauma, rectal or pelvic malignancy with direct invasion, perirectal sepsis, and Fournier's gangrene sequelae.[1][2][6]
A rectovesical fistula enters the bladder; a rectourethral fistula (RUF) enters the urethra. After prostatectomy, a tract at the vesicourethral anastomosis may be described under either term in published series. Record its actual location, outlet function, rectal condition and tissue quality.[1][2][10][15]
Repair planning depends on etiology and complexity, with individualized urinary or fecal diversion and selective vascularized interposition. Anatomic closure, stoma reversal, continence and sexual function are separate outcomes.[1][16][19] Nonirradiated cohorts generally have better results.[1][16][19] Radiation-associated disease may require complex reconstruction or permanent diversion.[1][16][19]
For operative selection across all repair routes, see the Male Fistula Repair database.
See also: Rectourethral Fistula, The Bladder, Gracilis Flap, Omental Flap, Buccal Mucosa Graft, Radiation Tissue Effects, Fistulas landing page.
Epidemiology & Etiology
Prostate Cancer Treatment (Dominant)
Prostate cancer treatment accounts for the majority of contemporary RVFs.
| Modality | Incidence |
|---|---|
| Radical prostatectomy (open, laparoscopic, robotic) | A systematic review reported rectourinary fistula incidence from <0.01% to 1.5% after prostatectomy[32]. Among 40 patients in Mundy's selected fistula-repair series, 23 followed prostatectomy[1]; Sadighian evaluated radiotherapy-associated fistulas[4] |
| Pelvic radiotherapy for prostate cancer (pelvic fistulas of any type; six cohorts, median follow-up 35.5 months) | Pooled fistula prevalence 0.2% (95% CI 0.1–0.4); no RVF-specific estimate[4] |
| Low-dose-rate 125I brachytherapy (4,690 men) | Rectoprostatic fistula in 12/4,690 (0.26%) and rectal ulcer in 9/4,690 (0.19%) at median 53 months[3] |
| Combined-modality RT + brachytherapy | Reported in referral series as producing more complex fistulas; incidence is not well defined[1] |
| Salvage HIFU or cryotherapy after radiotherapy | In a selected 40-patient urorectal-fistula repair series, these treatments preceded some fistulas; cavitation was particularly common after salvage HIFU following combined external-beam radiotherapy and brachytherapy.[1] |
Sequential energy treatments (e.g., EBRT, then brachytherapy, then salvage HIFU) create the most complex fistulas, typically with tissue cavitation, extensive ischemia, and associated bladder-neck contracture.[1]
Iatrogenic Interventions Post-Treatment
Post-treatment interventions were reported among 12 rectoprostatic-fistula cases in a 4,690-man brachytherapy cohort and among 12 pubovesical-fistula cases in a separate post-radiotherapy series:[3][5]
- Urinary interventions after radiation (e.g., TURP): performed in 5 of 12 fistula patients in one brachytherapy series versus 0 of 9 ulcer-only patients[3]
- Bladder-neck-contracture (BNC) treatment: endoscopic incision or dilation in radiated patients is a well-documented precipitant[1][5]
- Rectal biopsy of a post-brachytherapy rectal ulcer: 3 of 8 patients biopsied in one series went on to develop a fistula[3]
- Argon plasma coagulation for rectal bleeding was reported in 3 of 12 fistula patients after prostate brachytherapy.[3] The 2025 British Society of Gastroenterology practice guidance states that argon plasma coagulation is absolutely contraindicated on the anterior rectal wall after prostate brachytherapy because of fistula risk.[33]
The teaching point: be cautious with any instrumentation, urinary or rectal, in an irradiated pelvis, and counsel patients that even "minor" endoscopic maneuvers can precipitate catastrophic complications.
Other Etiologies
- Trauma: penetrating pelvic injury, pelvic fracture, combat-related injury[6]
- Inflammatory bowel disease: Crohn's disease
- Colorectal malignancy: direct invasion by locally advanced rectal or sigmoid cancer, and its treatment (resection, radiation)[2]
- Perirectal sepsis
- Fournier's gangrene
Diverticular disease and other sigmoid-origin enterovesical fistulas usually reach the bladder dome or posterior wall as colovesical fistulas; see Colovesical and Small-Bowel Fistulas for that pathway.
Classification
By Etiology[2]
- Benign fistulas: Crohn's, trauma, perirectal sepsis, iatrogenic surgical injury
- Malignancy-related fistulas: neoplasm, radiation, surgery for cancer, or combined tumor/treatment effects
By Complexity — Mundy & Andrich[1]
Simple fistulas:
- Post-surgical, non-irradiated
- Small, well-defined single tract
- No cavitation
- No associated bladder neck contracture
Complex fistulas (one or more):
- Post-irradiation (complex even without cavitation or BNC)
- Cavitation (tissue loss with cavity formation)
- Associated bladder neck contracture
- Extensive ischemia from serial energy applications
- Wide, tough scar tissue from multiple prior repair attempts[7]
By Size and Repair History — Contemporary Refinement
A contemporary working classification used by the Sotelo group further subdivides complexity:[15]
Simple: single tract, size <2 cm, no prior failed repair, no energy treatment.
Complex: multiple tracts, size ≥2 cm, prior failed repair, prior energy treatment, or associated bladder-neck stricture.
By Anatomic Location
The anatomic distinction between RVF and RUF is the bladder neck:[2][10]
- A tract into the bladder is rectovesical; document the relation to the ureteral orifices and reconstructed bladder neck
- A tract into the urethra is rectourethral; terminology overlaps for vesicourethral-anastomotic fistulas after prostatectomy
In a mixed-etiology series of 41 acquired rectourinary fistulas (37 men and four women), 22 involved the bladder and 19 the urethra.[2]
Clinical Presentation
Symptoms
Urine per rectum and recurrent infection dominate. In a series of 29 mostly post-prostatectomy fistulas, presenting symptoms were:[8]
- Urinary leakage per rectum: 48%
- Pneumaturia: 24%
- Fecaluria: 10%
- Recurrent UTIs: 21%
- Dysuria: 21%
- Suprapubic or groin pain (especially if pubovesical fistula coexists)[5]
Time to Presentation
- Interval from prostatectomy to repair: median 10 months (IQR 4–13) among 29 open urorectal-fistula repairs, including five patients with prior pelvic radiotherapy[8]
- Post-radiation fistulas: 6 months to 20 years after last radiation treatment[13]
Diagnosis
History, pelvic examination, and digital rectal examination establish the suspicion. Targeted workup:[6][10][11][12]
- Cystourethroscopy: visualize the fistula orifice; characterize surrounding mucosa; catheterize the tract
- Urethroscopy with DRE under anesthesia was reported as the most reliable diagnostic study in a 30-man post-traumatic rectourethral fistula series.[11]
- Colonoscopy / proctoscopy: identify rectal orifice; rule out malignancy or IBD
- Cystography / retrograde urethrography (with a contrast enema when the rectal side is in question): delineate the tract and exclude distal obstruction
- CT urogram: assess size, cavitation, relation to surrounding structures, concurrent ureteral injury
- MRI: high-resolution tract characterization, especially in complex or multi-tract fistulas
- Biopsy: indicated when tissue or imaging is suspicious for malignancy; prior radiation alone does not require indiscriminate biopsy
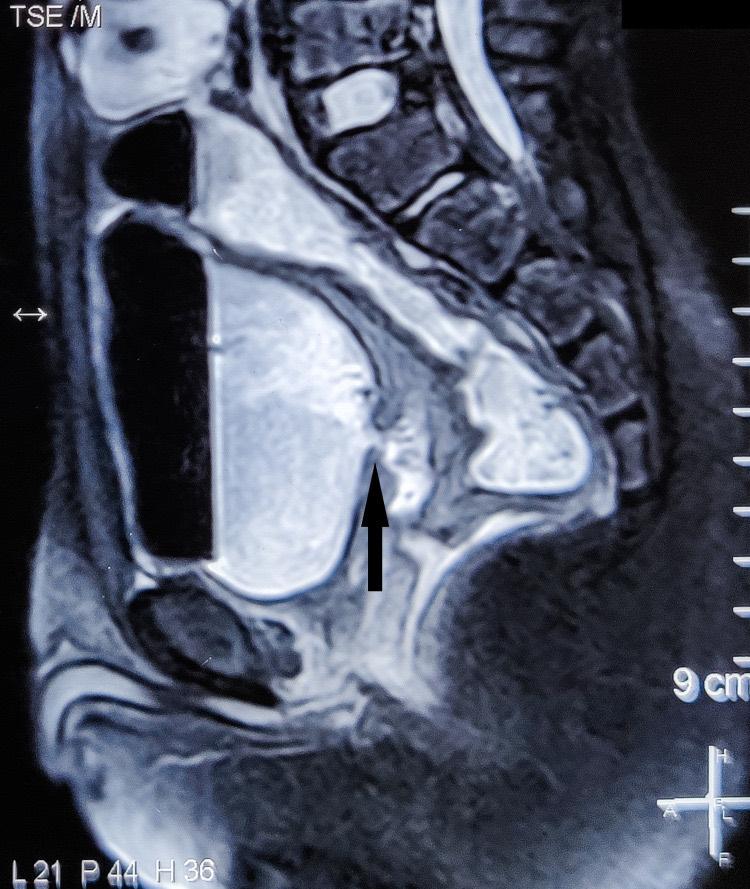
Sagittal MRI of the pelvis showing the rectovesical fistulous tract (arrow) after blunt trauma in a child. From Rajan YRD, Priyanka C. Cureus. 2021;13(10):e18931, Figure 2 (CC BY).[29]
Management Principles
Conservative Management — Limited Role
Spontaneous closure of a complex urorectal fistula is uncommon to nonexistent.[14] In one series of 3 patients managed non-operatively, none required formal closure over follow-up but all required ongoing symptomatic and episodic care.[14] Conservative care may be appropriate for palliation or a monitored trial in a small, recent, nonirradiated fistula; control infection and obstruction and reassess persistent leakage.
A distinct finding: post-brachytherapy rectal ulcers healed with conservative management in 8 of 15 patients (53%), although six of the 15 ulcer cases progressed to fistulas; no established fistula closed without surgery in the same series.[3] The distinction between pre-fistula rectal ulcer and established RVF is therefore prognostically meaningful.
Fecal and Urinary Diversion
Urinary drainage and, when indicated, fecal diversion are common initial measures, particularly for sepsis, large defects or irradiated tissue. For complex traumatic fistulas, the cited series used fecal and urinary diversion; selected post-surgical fistulas can be repaired without a covering colostomy when circumstances are appropriate.[6][11][1] Rationale: decompress the inflamed field and allow edema and inflammation to resolve. In a two-patient post-prostatectomy report, the authors proposed 3–6 months of fecal and urinary diversion before posterior repair if the fistula remained open.[30]
- Previous fecal diversion was present in 96% of 24 patients in a contemporary minimally invasive repair series[15]
- In post-traumatic rectourethral fistulas (23 of 30 missile-related), double diversion alone healed 14 of 30 (46.7%), mainly small, less-fibrous fistulas[11]
- GI tract continuity restored after anterior transperineal repair: non-radiated 94% (45/48) versus radiation- or ablation-associated 65% (30/46)[16]; digestive stoma closed after transperineal gracilis repair in 83% (10/12) of diverted patients[9]
Surgical Approaches
Approach selection reflects etiology, tract location, tissue quality and the reconstruction required.[1][19]
Transperineal Approach
An established option for accessible low fistulas, including selected irradiated cases; route depends on anatomy and reconstructive needs.[1][9][17]
Technique:
- Vertical perineal incision
- Fistula dissection, tract excision, and debridement of non-viable margins
- Separate closure of bladder / urethral and rectal defects in non-overlapping suture lines
- Gracilis muscle flap interposition between the two suture lines[18][9]
- Wide drain placement
Outcomes:
- Post-surgical fistulas: 98% (48/49) closed with one procedure[16]
- Radiation- or ablation-associated RUF: 86% (42/49) closed with one procedure at median cohort follow-up of 14.5 months (range 3–144)[16]
- Open repair (26 transperineal, three transabdominal): 5-year recurrence-free survival 96% among 23 patients in the survival analysis[8]
- Transperineal gracilis: 95% (20/21)[9]
- Significant urinary incontinence: 61% (11/18 postoperative questionnaire respondents in the gracilis series)[9]
- Mild fecal incontinence (mean St Mark's 5/24 among 18/21 postoperative questionnaire respondents in the gracilis series)[9]
- Patient satisfaction: high (mean 9/10 among 18/21 postoperative questionnaire respondents in the gracilis series)[9]
- Voiding restored (median six-item LUTS score 4 among 17/29 patient-reported-outcome respondents)[8]
Transabdominal / Abdominoperineal Approach
Consider for high or complex defects requiring abdominal access, extirpation, bladder-neck reconstruction or bowel resection.[1][13][19] In Beddy’s series, 90.6% of definitive repairs in radiated patients used an abdominal approach.[19]
Selected reconstructive options for radiation-induced RUF. In Lane's 22-man series, nine underwent urethral reconstruction with fistula closure; six had BMG repair.[13]
- Proctectomy when rectal tissue is severely damaged
- Salvage radical prostatectomy if a discrete prostate still exists[1]
- Buccal mucosa graft to reconstruct the urethral defect[13][16]
- Staged colo-anal pull-through for rectal reconstruction
- Gracilis muscle interposition
Outcomes, radiated versus non-radiated (Beddy et al.):[19]
| Outcome | Non-radiated | Radiated | P |
|---|---|---|---|
| Successful primary repair | 80.9% | 0% | <0.05 |
| Permanent colostomy | 0% | 83% | <0.05 |
| Permanent urostomy | 19% | 100% | <0.05 |
The Mundy series included mixed surgical and irradiated urorectal fistulas and used different reconstructions.[1]
York Mason Posterior Transsphincteric Approach
Posterior, transanal, transrectal sphincter-splitting approach with direct visualization of the fistula from the rectal side and a rectal-wall advancement closure.[20] In a 2026 four-center retrospective RUF cohort (27 York–Mason, 30 transperineal gracilis repairs), first-attempt success was 44% versus 77% and 12-month reintervention-free survival was 68.2% versus 94.7%; median follow-up was 27 versus 53 months.[34]
Outcomes:[20]
- Overall: >50% fistula-free at follow-up
- Single prior procedure: almost 90% fistula-free
- Multiple prior procedures: significantly lower success
- Diabetes and concurrent infection did not influence outcome
- Most common etiology in contemporary series: laparoscopic prostate procedures
Advantages: good visualization, minimal bleeding, less postoperative pain than transperineal or transabdominal.
Limitations: deliberate sphincter division (with careful reconstruction), not a preferred approach for radiated fistulas.
Robotic / Laparoscopic Transabdominal Repair
Minimally invasive transabdominal RVF repair after radical prostatectomy has been described in case reports and small series from surgeons experienced in laparoscopic or robotic pelvic reconstruction.[10][12][15][21]
Outcomes (Medina et al., 24 patients, 22 men; 19 robotic, 5 laparoscopic; 20 post-surgical, 4 after radiotherapy or combined energy):[15]
- Fistula closure (imaging plus symptom resolution) in all 24 at 12 months
- Median operative time: 180 min (140–282)
- Median blood loss: 50 mL (40–125)[15]
- Median hospital stay: 2 days (2–3)
- No intraoperative complications
- Clavien II: 2 patients; Clavien IIIb: 1 patient
Step-by-Step — Sotelo-Group Robotic Technique[15]
Positioning. Low lithotomy and steep Trendelenburg.
Cystoscopy and tract cannulation. Cystourethroscopy is performed first. Both ureters are catheterized; this simultaneously facilitates later identification and provides protection during excision and closure at the trigone. The fistulous tract is cannulated with a different-color open-ended ureteral catheter, passed through the fistula into the rectum, and retrieved through the anus to serve as an intraoperative locator.
Omental harvesting. An intact omentum of sufficient length can be brought directly to the pelvis. If length is inadequate, an omental flap based on the right gastroepiploic artery is created, replicating the open omentoplasty technique. Coloepiploic detachment is followed by careful dissection along the gastrocolic ligament with an energy device (Harmonic ACE or robotic Vessel Sealer Extend). If length remains inadequate, a longitudinal perpendicular incision through the omentum, carefully avoiding vascular arcades, further lengthens the flap. The patient is then placed in Trendelenburg for the pelvic phase.
Dissection of the fistulous tract. Technique depends on whether the prostate is present:
- Absent prostate (post-prostatectomy RVF, the most common scenario): localize and dissect the rectovesical space. Perform a downward vertically oriented posterior cystotomy (bladder bivalving), advancing the incision until it reaches the fistulous tract. If concurrent bladder-neck contracture is present, anterior dissection through the space of Retzius permits bladder-neck reconstruction and a new vesicourethral anastomosis.
- Prostate in situ (post-radiation with salvage intent): salvage prostatectomy is performed concurrently. A retrovesical incision is made; dissection advances distally with monopolar scissors until the fistulous tract's proximal border is encountered. Anterior dissection through the Retzius space exposes the prostatic anterior capsule. The prostatic apex is dissected, the bladder neck freed, and the prostatectomy completed. The posterior bladder-neck plane is then followed distally until it meets the distal end of the fistulous tract.
Further rectovesical dissection with a combination of hook cautery and robotic monopolar scissors ensures clean separation of the rectum from the bladder.
Rectal closure. The fistulous tract is debrided with cold scissors; approximately 2 mm of non-viable tissue is removed circumferentially. Rectal closure is two-layer with the initial knot placed on the outer surface of the rectum, outside the defect area:
- Laparoscopic: interrupted UR-6 3-0 poliglecaprone (Monocryl)
- Robotic: running 3-0 barbed absorbable (V-Loc)
Indocyanine green (ICG) fluorescence imaging confirms adequate rectal perfusion. Anorectoscopy with a bubble test confirms watertight closure and appropriate rectal caliber.
Tissue interposition. The harvested omental flap is advanced through the rectovesical space and anchored distal to the rectal suture line (3-0 V-Loc). If omentum is unavailable or too short, alternatives include gracilis muscle, rectus abdominis, or a peritoneal flap from the nearest anatomic location.
Bladder closure and vesicourethral anastomosis. Bladder-trigone reconstruction in two layers with 3-0 V-Loc, ensuring non-overlapping suture lines relative to the rectal closure and to the omental flap. A tension-free vesicourethral anastomosis is then performed (running single-knot technique).
Postoperative care. Maintain reliable urinary drainage and monitor for clot obstruction. Remove the pelvic drain when output and leak assessment permit. Urinary catheters commonly remain for several weeks, with leak testing before removal according to the repair plan; do not remove urethral drainage on postoperative day three as a general rule. Stoma reversal follows confirmed healing and colorectal assessment.
Follow-up: assess symptoms, continence, bowel function and healing. Medina’s 24-patient minimally invasive series defined repair success by imaging-confirmed closure and resolution of fistula symptoms at 12 months.[15]
Transanal Endoscopic Microsurgery (TEM)
Minimally invasive transanal approach for simple fistulas without radiation or cavitation.[7]
Technique: magnified 3D stereoscopic visualization; precise resection of the fistula and surrounding rectal mucosa; four-layer hand-sewn closure of the rectal defect and muscle.
Outcomes (10 patients): 7 of 10 (70%) success; 3 failures all had wide, tough scar tissue from prior radiation, HIFU, or multiple repairs.[7]
Selection limitation: All three TEM recurrences followed wide, tough scarring after prior radiation, HIFU, or repeated repair attempts; the authors advise against TEM for that scar pattern.[7]
Tissue Interposition
Vascularized tissue interposition between the repaired bladder / urethral and rectal suture lines is commonly used for complex or compromised tissue; some selected simple repairs succeed without a flap. Interposed tissue separates the urinary and rectal suture lines.[9]
Gracilis Muscle Flap — the Workhorse
The gracilis muscle flap is the most commonly used interposition for RVF and RUF repair.[9][17][18][22]
Outcomes:
- Rectourethral fistulas: 78% initial success, 97% overall after secondary procedures (Wexner series, 36 men)[18]; a later 53-man Cleveland Clinic Florida series reported 53% primary healing and 81% after additional procedures, with wound dehiscence the only factor linked to failure[28]
- Transperineal repair with gracilis: 95% (20/21)[9]
- Colorectal-surgeon series (18 patients, mixed complex pelvic fistulas and perineal wounds; only 2 rectourethral): postoperative complications 16.7%, flap failure 16.6% (3/18)[22]
- Lower-extremity dysfunction among 18/21 postoperative questionnaire respondents: minimal (mean score 2/20)[9]
- Donor-site scarring among 18/21 postoperative questionnaire respondents: acceptable (mean POSAS 19/70)[9]
Omental Flap
The omental pedicle flap is well suited to transabdominal repairs and to fistulas with cavitation that require dead-space obliteration; supporting data are case series and reviews.[23][24]
Outcomes: in a series of nonhealing perineal sinuses after proctectomy (mostly IBD), 7 of 8 omental transpositions gave good results; this is indirect evidence for fistula repair.[24]
Limitations: requires laparotomy or transabdominal access, not available in patients with prior omentectomy or short mesentery, adds operative complexity.
VRAM Flap
The vertical rectus abdominis myocutaneous (VRAM) flap has been used for complex urogenital fistulas for recurrent fistulas after tumor or trauma.[25]
Outcomes (12 patients, mixed urogenital fistulas):[25]
- Fistula eradicated in all 12 (men and women, at least two prior repair attempts; 5 VRAM and 8 gracilis flaps, mean follow-up 6.3 years)
- Mean operative time 5 h 31 min for VRAM versus 3 h 11 min for gracilis
- Continence preserved in all gracilis patients; VRAM patients showed slight residual incontinence
- Quality of life restored in both groups
Selection: gracilis and VRAM suit different defect sizes and tissue needs.
Perivesical Fat Rotational Flap
A novel alternative described when omentum is unavailable:[26] a wide-based pedicled flap of perivesical fat overlying the bladder dome is rotated and positioned over the defect in a tension-free manner, then anchored. Described applications include salvage prostatectomy after HIFU, RUF, and colovesical fistula. The three illustrated patients underwent salvage prostatectomy without a fistula, recurrent vesicovaginal fistula repair, or recurrent colovesical fistula repair; no complications were reported over follow-up of 1 month to 3 years.[26]
Buccal Mucosa Graft
Buccal mucosa graft is used to reconstruct large urethral defects that cannot be primarily closed, particularly after debridement in radiation-induced RUF and RVF with cavitation.[13][16] In reported radiotherapy-associated RUF reconstructions, buccal mucosa was used to repair the urethral defect; gracilis muscle interposition was used in selected repairs.[13][16]
Outcomes by Etiology
Post-Surgical (Non-Radiated) — Excellent Prognosis
[1][16][19]- Fistula closure: 98% (48/49 non-radiated RUF) with one procedure at median full-cohort follow-up of 14.5 months[16]
- Approach: transperineal in 80% in the Beddy non-radiated cohort (all Kaufman repairs were transperineal)[19][16]
- GI continuity restored: 94% (45/48 non-radiated RUF patients assessed for this outcome)[16]
- Permanent fecal diversion: 0%; permanent urinary diversion: 19% in Beddy's nonradiated RUF cohort[19]
Post-Radiation — Complex, Uncertain
[1][13][16][19]- In a selected radiation- or ablation-associated RUF repair subgroup, 42/49 (86%) had closure after one procedure; median follow-up was 14.5 months for the full 98-patient series[16]
- Approach: transabdominal in 90.6% of Beddy's radiated RUF cohort[19]
- GI continuity restored: 65% (30/46 radiation- or ablation-associated RUF patients assessed for this outcome)[16]
- Permanent colostomy: 83% in Beddy's radiated RUF cohort[19]
- Permanent urostomy: 100% in Beddy's radiated RUF cohort[19]
- 90-day complications: 24% in radiated or ablated versus 2% in non-radiated Kaufman RUF repairs[16]
- Salvage prostatectomy performed in 8/17 post-radiation patients in the Mundy series (40 patients overall), with all fistulas cured[1]
Benign vs Malignancy-Related[2]
| Outcome | Benign | Malignancy-related |
|---|---|---|
| Resolution after initial surgery | 44% | 21% |
| Resolution after reoperation | 100% | 88% |
| Mean surgeries per patient | 1.8 | 2.1 |
| Permanent diversion avoided | 56% | 25% |
Complications
Short- and Medium-Term[16]
| Time point | Non-radiated | Radiated |
|---|---|---|
| 30-day complications | 29% | 29% |
| 90-day complications | 2% | 24% |
Delayed complications requiring surgery: urethral diverticula, urinary incontinence requiring artificial urinary sphincter, urethral stricture, bowel dysfunction.[16]
Functional Outcomes
- Urinary: Significant incontinence was reported by 11/18 questionnaire respondents (61%) after transperineal RUF repair with gracilis interposition.[9] In a separate open urorectal-repair series, the median six-item LUTS score was 4/24 among 17/29 patient-reported-outcome respondents.[8] Eight of 40 patients in the Mundy repair series required an artificial urinary sphincter.[1]
- Bowel: mild fecal incontinence: median Wexner 3 among 17/29 open-repair respondents and mean St Mark's 5/24 among 18/21 gracilis-repair respondents; continence largely preserved.[8][9]
- Quality of life: mean patient satisfaction 9/10 among 18/21 gracilis-repair questionnaire respondents; median Decision Regret Scale 0 among 17/29 open-repair respondents.[8][9]
Long-Term Recurrence[8]
In an open-repair series of 29 patients, 23 entered the survival analysis (median follow-up 50 months for recurrence and 58 months for re-intervention):[8]
- 5-year recurrence-free survival: 96%
- 5-year re-intervention-free survival: 75%
Predictors of Severe Complications[27]
In 69 men undergoing urinary diversion after prostate radiotherapy (single-institution, retrospective), those with prostatic fistula (tract extending outside the urinary tract) had, compared with localized radiation injury:
- Longer operative time (516 versus 414 min, P=0.017)
- Higher Clavien-Dindo ≥3 complications (44.8% versus 20%, P=0.027)[27]
- Higher re-operation for pelvic abscess (37.9% versus 5%)[27]
Related Entity — Pubovesical Fistula
A distinct but overlapping entity in post-prostate-cancer-treatment patients: the pubovesical fistula, a communication between the bladder and the pubic bone, often with associated osteitis pubis or pubic osteomyelitis.[5]
Classic setting: radiation for prostate cancer, followed by bladder-neck contracture, endoscopic incision or dilation, and then pubovesical fistula.
Key data (Matsushita et al.):[5]
- All patients had prior radiation therapy and a BNC requiring endoscopic treatment
- Median interval from BNC treatment to pubovesical fistula: 35.9 months (range 0.6–97)
- 10 of 12 patients required cystectomy with urinary diversion
- Presenting feature most suggestive of pubovesical (versus simple RVF): suprapubic or groin pain with imaging evidence of pubic-bone involvement
Prevention: exercise restraint with endoscopic BNC intervention in radiated patients; counsel before any endoscopic manipulation in this population; and consider pubovesical fistula in the differential for any radiated prostate-cancer survivor with BNC and pubic pain.
See also: Urethropubic Fistula, the urethra-side cousin.
Clinical Recommendations
Diagnostic Workup
- Establish the diagnosis: cystoscopy, urethroscopy and DRE under anesthesia[11]
- Classify by etiology and complexity: post-surgical versus post-radiation; Mundy-Andrich simple versus complex[1]
- Confirm the anatomic level: proximal or distal to the bladder neck (RVF versus RUF)[2][10]
- Screen for malignancy when the history or imaging suggests it; biopsy as indicated
Initial Management
- Early fecal and urinary diversion: especially for complex or post-radiation cases[6][11]
- In a two-patient post-prostatectomy report, Boushey and colleagues proposed 3–6 months of fecal and urinary diversion before posterior repair if the fistula remained open.[31]
Approach Selection
| Scenario | Preferred Approach | Interposition |
|---|---|---|
| Post-surgical (non-radiated), simple | Transperineal when the tract is accessible | Selective interposition; a flap is not obligatory in viable tissue[1] |
| Post-surgical fistula at the vesicourethral anastomosis | Perineal or transabdominal according to tract and outlet reconstruction needs; robotic repair is a reported option[1][15] | Interposition is selective; omentum has been used with abdominal access[1][12] |
| Post-radiation | Perineal, abdominal or combined approach according to defect and extirpative needs | Vascularized tissue usually favored; BMG if needed for urethral reconstruction |
| Simple fistula in previously operated field | TEM (selected cases) | None (with limitations) |
| Complex with cavitation or BNC | Perineal, abdominal, or combined according to tract access and whether outlet reconstruction is required | Vascularized interposition for cavitation or irradiated tissue; select the flap according to access and tissue quality[1][16] |
Patient Counseling
Post-surgical fistulas: selected series report high closure and frequent stoma reversal; residual urinary incontinence and further procedures remain possible.
Post-radiation fistulas: outcomes vary substantially with tissue destruction and selection for repair versus extirpation.
Surveillance
- Clinic visits at 1, 3, and 6 months postoperatively: symptom and physical exam
- Use cystoscopy or imaging for suspected persistent/recurrent fistula or associated pathology.
- Long-term follow-up recommended: delayed complications (urethral stricture, diverticulum, incontinence) may arise and require additional surgery[8][16]
See Also
- Male Fistula Repair database
- Principles of Fistula Repair
- Transabdominal RUF / RVF Repair
- Salvage Prostatectomy for USF
- Fecal Diversion
References
1. Mundy AR, Andrich DE. Urorectal Fistulae Following the Treatment of Prostate Cancer. BJU International. 2011;107(8):1298–1303. doi:10.1111/j.1464-410X.2010.09686.x
2. Muñoz M, Nelson H, Harrington J, et al. Management of Acquired Rectourinary Fistulas: Outcome According to Cause. Diseases of the Colon and Rectum. 1998;41(10):1230–1238. doi:10.1007/BF02258219
3. Leong N, Pai HH, Morris WJ, et al. Rectal Ulcers and Rectoprostatic Fistulas After 125-I Low-Dose-Rate Prostate Brachytherapy. Journal of Urology. 2016;195(6):1811–1816. doi:10.1016/j.juro.2015.12.095
4. Sadighian M, Hakam N, Amend G, et al. Radiation-Induced Fistulas in Patients With Prior Pelvic Radiotherapy for Prostate Cancer: A Systematic Review and Meta-Analysis. Urology. 2023;176:121–126. doi:10.1016/j.urology.2023.03.015
5. Matsushita K, Ginsburg L, Mian BM, et al. Pubovesical Fistula: A Rare Complication After Treatment of Prostate Cancer. Urology. 2012;80(2):446–451. doi:10.1016/j.urology.2012.04.036
6. Kucera WB, Jezior JR, Duncan JE. Management of Post-Traumatic Rectovesical / Rectourethral Fistulas: Case Series of Complicated Injuries in Wounded Warriors and Review of the Literature. Military Medicine. 2017;182(3):e1835–e1839. doi:10.7205/MILMED-D-16-00148
7. Kanehira E, Tanida T, Kamei A, et al. Transanal Endoscopic Microsurgery for Surgical Repair of Rectovesical Fistula Following Radical Prostatectomy. Surgical Endoscopy. 2015;29(4):851–855. doi:10.1007/s00464-014-3737-x
8. Wagner MC, Klemm J, Roessler N, et al. Long-Term Patient-Reported Outcomes of Open Urorectal Fistula Repair After Prostate Cancer Treatment. BJU International. 2026. doi:10.1111/bju.70233
9. Sbizzera M, Morel-Journel N, Ruffion A, et al. Rectourethral Fistula Induced by Localised Prostate Cancer Treatment: Surgical and Functional Outcomes of Transperineal Repair With Gracilis Muscle Flap Interposition. European Urology. 2022;81(3):305–312. doi:10.1016/j.eururo.2021.09.017
10. Sotelo R, Garcia A, Yaime H, et al. Laparoscopic Rectovesical Fistula Repair. Journal of Endourology. 2005;19(6):603–607. doi:10.1089/end.2005.19.603
11. al-Ali M, Kashmoula D, Saoud IJ. Experience With 30 Posttraumatic Rectourethral Fistulas: Presentation of Posterior Transsphincteric Anterior Rectal Wall Advancement. Journal of Urology. 1997;158(2):421–424. doi:10.1016/s0022-5347(01)64493-8
12. Sotelo R, de Andrade R, Carmona O, et al. Robotic Repair of Rectovesical Fistula Resulting From Open Radical Prostatectomy. Urology. 2008;72(6):1344–1346. doi:10.1016/j.urology.2008.06.017
13. Lane BR, Stein DE, Remzi FH, et al. Management of Radiotherapy-Induced Rectourethral Fistula. Journal of Urology. 2006;175(4):1382–1387. doi:10.1016/S0022-5347(05)00687-7
14. Venkatesan K, Zacharakis E, Andrich DE, Mundy AR. Conservative Management of Urorectal Fistulae. Urology. 2013;81(6):1352–1356. doi:10.1016/j.urology.2012.10.040
15. Medina LG, Riva A, Perez LC, et al. Minimally Invasive Management of Post-Treatment Rectovesical Fistulae. Journal of Endourology. 2023;37(2):185–190. doi:10.1089/end.2022.0266
16. Kaufman DA, Zinman LN, Buckley JC, et al. Short- and Long-Term Complications and Outcomes of Radiation and Surgically Induced Rectourethral Fistula Repair With Buccal Mucosa Graft and Muscle Interposition Flap. Urology. 2016;98:170–175. doi:10.1016/j.urology.2016.06.065
17. Lo Re M, Pezzoli M, Garcia Rojo E, et al. A Systematic Review on the Surgical Management of Acquired Rectourethral Fistula. International Journal of Impotence Research. 2026;38(3):214–225. doi:10.1038/s41443-025-01100-y
18. Wexner SD, Ruiz DE, Genua J, et al. Gracilis Muscle Interposition for the Treatment of Rectourethral, Rectovaginal, and Pouch-Vaginal Fistulas: Results in 53 Patients. Annals of Surgery. 2008;248(1):39–43. doi:10.1097/SLA.0b013e31817d077d
19. Beddy D, Poskus T, Umbreit E, et al. Impact of Radiotherapy on Surgical Repair and Outcome in Patients With Rectourethral Fistula. Colorectal Disease. 2013;15(12):1515–1520. doi:10.1111/codi.12350
20. Falavolti C, Sergi F, Shehu E, Buscarini M. York Mason Procedure to Repair Iatrogenic Rectourinary Fistula: Our Experience. World Journal of Surgery. 2013;37(12):2950–2955. doi:10.1007/s00268-013-2199-y
21. Gözen AS, Malkoc E, Al-Sudani I, Rassweiler J. Laparoscopic Urorectal Fistula Repair: Value of the Salvage Prostatectomy and Review of Current Approaches. Journal of Endourology. 2012;26(9):1171–1176. doi:10.1089/end.2012.0024
22. Oner M, Tsay AT, Abbas MA. The Use of the Gracilis Flap in Colorectal Surgery: Surgical Technique, Results, and Review of the Literature. International Journal of Colorectal Disease. 2025;40(1):133. doi:10.1007/s00384-025-04928-4
23. O'Leary DP. Use of the Greater Omentum in Colorectal Surgery. Diseases of the Colon and Rectum. 1999;42(4):533–539. doi:10.1007/BF02234183
24. Menon A, Clark MA, Shatari T, Keh C, Keighley MR. Pedicled Flaps in the Treatment of Nonhealing Perineal Wounds. Colorectal Disease. 2005;7(5):441–444. doi:10.1111/j.1463-1318.2005.00838.x
25. Paprottka FJ, Krezdorn N, Lohmeyer JA, et al. Plastic Reconstructive Surgery Techniques Using VRAM or Gracilis Flaps in Order to Successfully Treat Complex Urogenital Fistulas. Journal of Plastic, Reconstructive & Aesthetic Surgery. 2016;69(1):128–137. doi:10.1016/j.bjps.2015.08.026
26. Hwang A, Watson M, Talluri S, Okafor H, Singh A. A Novel Perivesical Fat Rotational Flap as an Alternative to Omental Interposition in Challenging Urological Reconstruction. Urology. 2023;182:e262–e263. doi:10.1016/j.urology.2023.08.023
27. Myers JB, Hernandez BS, McCormick B, et al. Comparison of Urinary Diversion in Patients With Prostatic Fistula to Those With Localized Radiation Injury After Radiotherapy for the Treatment of Prostate Cancer. Urology. 2024;183:256–263. doi:10.1016/j.urology.2023.11.006
28. Emile SH, Horesh N, Strassmann V, et al. Outcomes of gracilis muscle interposition for rectourethral fistulas caused by treatment of prostate cancer. Tech Coloproctol. 2023;27(10):937-944. doi:10.1007/s10151-023-02759-5
29. Rajan YRD, Priyanka C. A Case of Rectovesical Fistula Following Blunt Trauma in a Child. Cureus. 2021;13(10):e18931. doi:10.7759/cureus.18931
30. Boushey RP, McLeod RS, Cohen Z. "Surgical management of acquired rectourethral fistula, emphasizing the posterior approach." Can J Surg. 1998;41(3):241–244. PMID:9627552
31. Boushey RP, McLeod RS, Cohen Z. "Surgical management of acquired rectourethral fistula, emphasizing the posterior approach." Can J Surg. 1998;41(3):241–244. PMID:9627552
32. de Angelis M, Scilipoti P, Leni R, et al. Clinical and surgical management of recto-urinary fistula after radical prostatectomy: a systematic review on current evidence. Prostate Cancer Prostatic Dis. Published online May 2, 2026. doi:10.1038/s41391-026-01114-7
33. Andreyev J, Adams R, Bornschein J, et al. "British Society of Gastroenterology practice guidance on the management of acute and chronic gastrointestinal symptoms and complications as a result of treatment for cancer." Gut. 2025;74(7):1040–1067. doi:10.1136/gutjnl-2024-333812
34. Long Depaquit T, Michel F, Madec FX, et al. "Comparison of rectourethral fistula repairs: york mason vs. transperineal repair with gracilis flap interposition." World J Urol. 2026;44(1):198. doi:10.1007/s00345-026-06316-1