Urethroperineal Fistula
A urethroperineal fistula (UPF) is an epithelialized communication between the urethra and the perineal skin. It exists in two operationally distinct forms: a rare congenital posterior urethroperineal fistula (CUPF), an epithelialized tract from the posterior urethra to the perineum, described in small case series[41]; and acquired UPF that follows Fournier's gangrene, pelvic-fracture urethral injury, periurethral abscess, urethral stricture surgery, lichen sclerosus, or chronic catheterization.[1][2][3][4][5] After confirming an adequate orthotopic urethra, CUPF can often be treated by accessory-tract excision; acquired UPF requires assessment of infection, obstruction and tissue loss before selecting closure, urethroplasty, interposition or diversion. Perineal urethrostomy is an option for selected anterior urethral disease, provided the proximal outlet and bladder support it.
For the male-shaft equivalent and the broader interposition-flap framework, see Urethrocutaneous Fistula. For the operative principles of perineal-tissue reconstruction, see The Perineum and Fournier's Gangrene. For operative selection across all repair routes, see the Male Fistula Repair database.
Congenital Posterior Urethroperineal Fistula (CUPF)
Definition
An epithelialized tract between the posterior urethra and the perineum in a male, a rare urogenital anomaly. Reported specimens show transitional lining proximally and squamous lining distally; one excised specimen was squamous throughout.[41]
Embryology
Two competing models:[2][3][7]
- Variant of Effmann Type IIA2 Y-duplication but with an inversion: the dorsal (orthotopic) urethra is the functional channel and the ventral perineal tract is hypoplastic. Bello proposed designating CUPF as "Type IIA2, Y-hypoplastic ventral urethra."[3]
- A distinct entity from urethral duplication, since the dorsal urethra is anatomically and functionally normal and the ventral channel is an accessory tract; excision has been successful after functional anatomy is confirmed, in contrast to hypospadiac urethral duplication where ventral excision can be catastrophic.[2]
Clinical presentation
- Perineal urinary leakage during or after voiding
- Normal voiding through the penile meatus: the dorsal urethra is functionally intact[2]
- Visible perineal opening between the scrotum and anus
- Recurrent UTI[6]
Diagnostic discriminators — CUPF vs urethral duplication vs H-type RUF
The distinction is which channel carries useful urinary flow. In reported CUPF, the orthotopic urethra is normal; in some Y-type duplications the ventral channel is essential. Rectourethral fistula requires demonstration of bowel communication.[1][2] Establish the complete anatomy with imaging and endoscopy before sacrificing a channel.[1][2]
Workup
- VCUG: may show the functional dorsal urethra and accessory tract.[2][6][41]
- MRI pelvis: confirms the fluid-filled tract, increases in size during micturition[6]
- Cystourethroscopy assesses the functional urethra and internal opening; dye through the cannulated perineal opening can help localize an occult connection.[2][41]
- Fistulography: through the perineal opening[8]
- Renal ultrasound: assess for associated renal anomalies such as hypoplasia.[41]
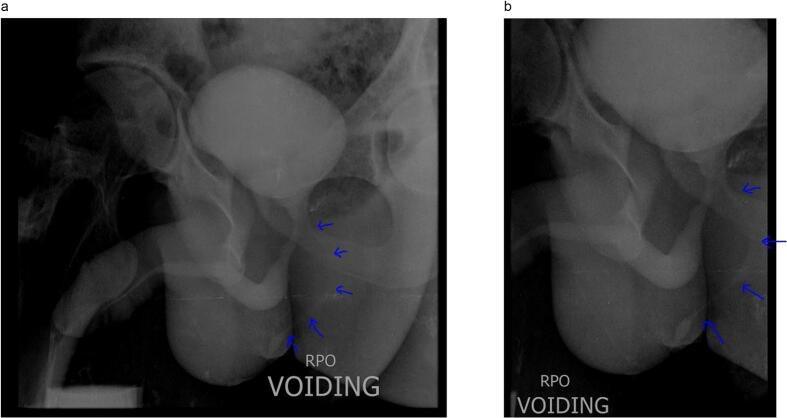
Congenital urethroperineal fistula in an adolescent: (a, b) voiding phase of a cystourethrogram showing the fistula tract (blue arrows). From Shiferaw SF, et al. Int J Surg Case Rep. 2025;128:111043, Fig. 2 (CC BY 4.0).[38]
Treatment and outcomes
- Accessory-tract excision through a perineal incision is the main reported treatment.[2][3][8] Near-total excision with ligation and fulguration of a short proximal stump has been described when further dissection threatens the sphincter complex.[41]
- Endoscopic fulguration has been reported in two CUPF cases, with one recurrence at seven weeks and one without recurrence at three months.[3][41]
- High reported cure in small case reports or series; no population-level guarantee[2][3]
- The single most important point: misdiagnosis as urethral duplication or rectourethral fistula leads to inappropriate and potentially catastrophic surgery; recognize CUPF before operating[1]
Acquired Urethroperineal Fistula
Acquired fistulas vary from an isolated skin tract to extensive infected tissue loss or combined bowel and urinary injury.
Etiology
| Setting | Notes |
|---|---|
| Fournier's gangrene | Necrotizing perineal infection may involve the urethra or periurethral tissues; debride nonviable tissue and use suprapubic drainage when urethral injury, periurethral abscess or extensive perineal debridement warrants it. Reconstruct after infection and necrosis resolve.[9][10][11][21][22] |
| Pelvic fracture urethral injury (PFUI) | Pelvic ring disruption may cause posterior urethral distraction[24][29]; selected repair series describe concurrent urethrorectal fistula.[12][20][28] Map any perineal skin tract and rectal communication before repair.[37] |
| Periurethral abscess | Stricture- or instrumentation-related abscess eroding through urethra and perineal skin; a stricture distal to the leak keeps the tract open, so treat the obstruction as part of the repair |
| Urethral stricture / post-urethroplasty | Fistula formation is one of several possible complications. Verla reported fistula as a high-grade complication in 4/85 (4.7%) adults undergoing repair of failed-hypospadias-related strictures[17][18][19] |
| Lichen sclerosus (BXO) | Progressive panurethral stricture with tissue destruction; can present as a perineal/scrotal mass with a draining fistula; biopsy suspicious induration, ulceration or a mass to assess for SCC[13][14][15][25] |
| Urethral calculi | Chronic stone impaction eroding to the perineum; usually with stricture or long-term catheterization[4] |
| Neurogenic bladder | Decubitus ulcers (33%), wound infection (24%), condom-catheter complications (19%), traumatic catheterization (19%) — 17/21 required permanent surgical or suprapubic-tube diversion in a selected urinary-cutaneous-fistula cohort[16] |
| Trauma | Penetrating injury or blunt perineal injury; characterize the actual urethral and soft-tissue defect |
Pathophysiology
A common final pathway: urethral wall compromise (ischemia, necrosis, infection, inflammation, trauma), then loss of supporting spongiosal and fascial layers, then cutaneous communication, then epithelialization of a persistent tract. The likelihood of healing depends on drainage, obstruction, infection and tissue viability.
- In Fournier's gangrene, debridement of necrotic tissue can expose or sacrifice the urethra.[10][21] WSES-AAST lists urethral involvement among indications for suprapubic diversion but recommends tailoring the drainage route to the patient.[9]
- In PFUI, pelvic ring disruption can separate the membranous and bulbar urethra; define the distraction defect and any associated cutaneous or rectal tract before repair.[24][29][37]
- In lichen sclerosus, progressive inflammatory destruction produces dense fibrosis, panurethral stricture, and eventual fistulization through the perineum[13][14][15]
Clinical presentation
- Urinary leakage from a perineal opening; with suspected rectal communication, ask about urine per rectum, pneumaturia and fecaluria, symptoms reported in a 29-man urorectal-fistula series after prostate cancer treatment.[42]
- Perineal wetness, skin maceration, recurrent local infection
- Obstructive voiding symptoms if a concurrent stricture is present; assess emptying even when symptoms are limited
- Recurrent UTI
- A perineal mass or induration in lichen sclerosus
Workup
- Physical exam: opening(s), skin quality, scarring, available tissue for reconstruction
- RUG with VCUG when needed: map the fistula and associated stricture; VCUG adds proximal information when the outlet is nearly or completely obstructed (EAU 2026 strongly recommends combining RUG with VCUG in nearly obliterative strictures, stenoses and pelvic fracture urethral injury, §5.2.1)[37]
- Cystourethroscopy: assess the internal opening, urethral mucosa and obstruction. In complex PFUI, consider combined retrograde and antegrade cystoscopy through a suprapubic tract when imaging leaves the proximal urethra, bladder neck or associated fistulas uncertain .[37]
- MRI pelvis: adjunct for complex posterior anatomy (EAU 2026 strong recommendation to consider MRI urethrography as an ancillary test in posterior urethral stenosis), collections or unclear associated disease[6][37]
- Fistulography: through the perineal opening
- Biopsy: essential when malignancy is suspected; preoperative LS biopsy may be performed when it alters management (EAU 2026 §5.2)[37]
Management
General principles (any acquired UPF)
- Control sepsis and establish safe drainage promptly; time definitive repair after tissue inflammation and necrosis resolve, often over several months
- Identify and address distal obstruction before or with repair; tissue quality and infection also affect healing
- Manage the tract and diseased tissue according to its anatomy and the planned closure
- Watertight, tension-free urethral closure
- Consider vascularized coverage to separate suture lines, particularly with poor local tissue
- Drainage and catheter removal: choose a route suited to the repair; after urethroplasty, perform validated urethrography before catheter removal , and continue drainage with repeat imaging after one week for a significant persistent leak.[43]
- The first repair offers the best chance of success: consider referral to a high-volume reconstructive center[26]
Conservative management
A drainage trial may be considered for selected early leaks while treating infection and obstruction.[26] In a broad urogenital fistula review, spontaneous closure with catheter drainage occurred in up to 15% of cases.[26]
Etiology-specific management
A. Post-Fournier's-gangrene UPF
The most challenging soft-tissue scenario.[9][10][11][21][22]
- Acute phase: start broad-spectrum antibiotics on presentation and begin repeated surgical debridement within 24 hours .[39] Use suprapubic drainage when urethral involvement or extensive perineal debridement warrants it. WSES-AAST describes negative-pressure therapy for wound management.[9] EAU 2026 found no evidence of benefit for it in Fournier's gangrene and weakly recommends against adjunctive treatments outside trials.[39]
- Reconstructive phase (delayed):
- Split-thickness skin grafts for wound coverage[22]
- Gracilis or VRAM flap may cover complex tissue defects; the cited 12-patient mixed urogenital-fistula series is not a Fournier-specific cure estimate[27]
- Perineal urethrostomy may be suitable for extensive anterior urethral disease with a usable proximal urethra and bladder[21]
- Permanent urinary diversion (suprapubic tube, ileal conduit) in the most severe cases
B. PFUI-associated UPF (assess for urethrorectal fistula)
- PFUI with a concurrent urethrorectal fistula: transperineal urethroplasty with rectal closure and selected tissue interposition has been described; complex defects may need additional access. In a 40-man retrospective cohort, all underwent fecal diversion before reconstruction.[12][20][24][28]
- In a 32-man PFUI-associated urethrorectal-fistula series, transperineal urethroplasty with gracilis interposition had overall treatment success in 29/32 men (91%) at mean 33-month follow-up (range 6–64 months): 22/22 without prior repair and 7/10 after failed repair.[20]
- Posterior excision and primary anastomosis for PFUI (n = 70; median follow-up 130 months): freedom from symptomatic recurrent narrowing requiring intervention was 85.4% at 1 year and 83.8% at 10 years. Recurrence occurred at a median 3 months; postoperative complications and persistent extravasation were associated with recurrence.[29]
- Length-gaining maneuvers: bulbar mobilization, corporal separation, inferior pubectomy, urethral rerouting[24][29]
- Severe PFUI/urethrorectal-fistula cohorts report substantial erectile dysfunction. Separate pre-existing trauma effects from de novo dysfunction after repair[12][29]
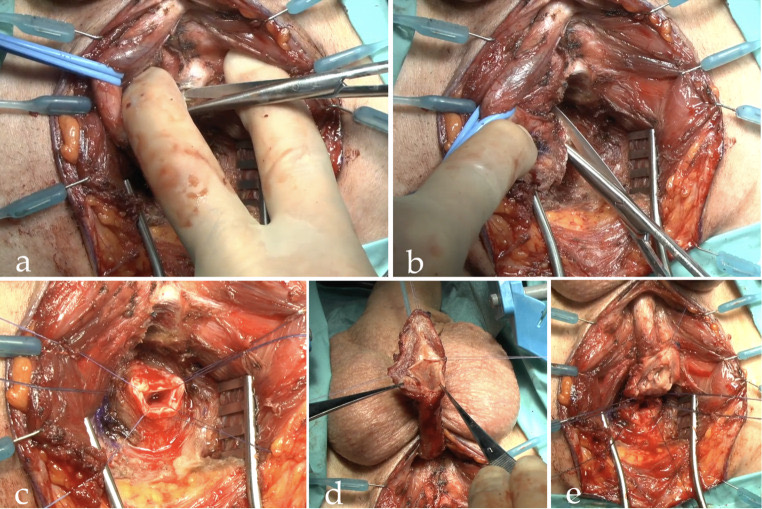
Transecting excision and primary anastomosis for pelvic fracture urethral injury, the repair on which PFUI-associated fistula closure is built. (a) Splitting of the corpora cavernosa to gain length; (b) urethral transection; (c) spatulation of the proximal urethral end; (d) spatulation of the distal urethral end; (e) dorsal urethral plate anastomosis. From Plamadeala N, et al. World J Urol. 2025;43(1):469, Fig. 2 (CC BY 4.0).[29]
C. Post-urethroplasty / stricture-associated UPF
- Small fistulas: local-tissue repair has been described for mature single penile-urethral fistulas.[5]
- Complex with concurrent stricture: select anastomotic or substitution urethroplasty, sometimes staged; address the fistula as part of the reconstruction[18][19]
- Recurrent or refractory anterior stricture with UPF: perineal urethrostomy (see below) is a long-term option the AUA Urethral Stricture Disease Guideline says surgeons should offer to patients at high risk of urethral reconstructive failure[23]
D. Lichen-sclerosus-associated UPF
- Genital skin: do not use it for augmentation penile urethroplasty in LS-related strictures because recurrence in skin grafts or flaps is high .[13][15][40]
- Buccal mucosa is the graft of choice[13][14]
- Oral-mucosa urethroplasty may be single-stage in suitable tissue or staged in complex disease[14]
- Definitive perineal urethrostomy can be considered for selected LS-related anterior strictures, particularly extensive disease.[13] In a retrospective multicenter LS cohort, 47 men underwent perineal urethrostomy; 72% required no postoperative instrumentation and had no diagnosed recurrence (mean follow-up 56 months for the full 215-man cohort).[14] EAU 2026 reports poorer perineal-urethrostomy patency in LS-, trauma- and infection-related strictures.[40]
- Long-term follow-up and biopsy of suspicious lesions; diagnostic biopsy when it changes management[37]
E. UPF in neurogenic bladder
- In one selected cohort of 21 urinary-cutaneous fistulas, 17 required permanent surgical or suprapubic-tube diversion. Discuss options using the patient’s pressure, emptying, tissue and functional assessment.[16]
Tissue interposition options
| Flap | Source | Best fit | Notes |
|---|---|---|---|
| Gracilis muscle flap | Medial thigh | Complex, irradiated, Fournier's defects | Reliable medial-circumflex pedicle; long reach; workhorse[20][27] |
| VRAM flap | Rectus abdominis | Large pelvic / perineal defects | Excellent bulk and vascularity[27] |
| Dartos pedicled flap | Perineal subcutaneous tissue | Selected urethrorectal fistulas | Described between urethral and rectal repairs in 12 men.[30] |
| Bulbospongiosus muscle flap | Perineal bulbospongiosus | PFUI-associated, urethrorectal septum | Local, anatomically natural[28] |
| Rectus fascia graft | Lower abdominal wall | Recurrent urethrocutaneous fistula after metoidioplasty | Interposition between urethral and skin closures was described in three patients (median follow-up seven months).[31] |
| Perivesical fat flap | Bladder dome | Selected pelvic reconstructions | — |
Perineal urethrostomy as definitive management
For selected complex anterior urethral strictures, including LS or failed hypospadias reconstruction, perineal urethrostomy is a possible definitive endpoint. Neurogenic bladder alone is not an indication: storage pressure, emptying and functional proximal anatomy remain central.[23][32][33][34][35][36]
- The EAU 2026 guideline strongly recommends offering PU as an option for complex anterior stricture disease and weakly recommends it for men unfit or unwilling to undergo formal reconstruction.[40]
- The AUA guideline states that surgeons may offer perineal urethrostomy as a long-term alternative to urethroplasty and should offer it in populations at high risk of reconstructive failure [23]
- In a 76-man referral-center PU series, retreatment-free survival was 84% at median 55-month follow-up; questionnaire respondents had a median ICIQ-S outcome score of 21/24.[33] In the PU cohort summarized by EAU 2026, postmicturition dribble was reported by 4/18 (22.2%) Johanson and 4/13 (30.8%) Blandy questionnaire respondents.[40][44]
- A six-cohort meta-analysis of 880 men with complex strictures (624 urethroplasty, 256 PU) found a pooled success RR of 0.93 (95% CI 0.84–1.03; I² = 69%) across nonrandomized comparisons.[34]
- In one tertiary center, use rose from 4.3% of complex anterior reconstructions in 2008 to 38.7% in 2017, with 94.8% success versus 78.5% for BMG and 78.2% for skin flaps, with success defined as no need for further operative management (unadjusted; the urethrostomy patients were older, with longer strictures and more lichen sclerosus)[36]
- In a single-center comparison, 34 men receiving definitive PU were older and had more cardiovascular comorbidity, panurethral disease and longer strictures than 63 men entering planned multistage urethroplasty; 28/63 did not complete the final stage. The authors recommend offering definitive PU early, especially to older patients.[35]
Outcomes
| Etiology | Approach | Success |
|---|---|---|
| Congenital (CUPF) | Near-total accessory-tract excision or selected endoscopic fulguration | Confirm functional urethral anatomy before treatment. Excision usually resolved reported cases; of two historical fulgurations, one recurred at seven weeks and one had no recurrence reported at three months.[1][2][3][41] |
| PFUI with rectal fistula | Transperineal urethroplasty + gracilis | Guo: 29/32 overall, 22/22 without prior repair and 7/10 after prior failure[20] |
| Post-urethroplasty | Repair with any needed urethral reconstruction | — |
| Lichen sclerosus | Oral-mucosa urethroplasty or selected perineal urethrostomy | Stricture-series outcomes[13][14] |
| Fournier's gangrene | Gracilis/VRAM flap or perineal urethrostomy | Variable; permanent diversion in severe cases[22][27] |
| Neurogenic bladder | Individualize repair or diversion | 17/21 diverted in one selected urinary-cutaneous cohort[16] |
Operative Principles
- Recognize CUPF before operating: the dorsal urethra is normal; accessory-tract excision may be curative after functional anatomy is confirmed; misdiagnosis as urethral duplication or rectourethral fistula leads to inappropriate surgery[1][2]
- Assess for concurrent stricture in acquired UPF: correct obstruction before or with repair[5][28][13]
- Vascularized tissue interposition (gracilis, VRAM, dartos) is selected by defect and tissue quality; RUF/mixed-fistula series provide limited UPF-specific data[20][27][30]
- Perineal urethrostomy is an option for selected anterior urethral disease with a functional proximal outlet; counsel separately about bladder dysfunction and other diversion options[23][33][35][36]
- Biopsy suspicious lesions or obtain LS histology when it changes management[37]
- First repair is the best repair: refer to an experienced reconstructive center[26]
See Also
References
1. Cheng JW, Ahn JJ, Cain MP, et al. "Misdiagnosis of congenital posterior urethroperineal fistula and comparison with urethral duplications and rectourethral fistula." Urology. 2021;158:193–196. doi:10.1016/j.urology.2021.09.013
2. Bates DG, Lebowitz RL. "Congenital urethroperineal fistula." Radiology. 1995;194(2):501–504. doi:10.1148/radiology.194.2.7824732
3. Bello JO. "Congenital posterior urethroperineal fistula: a review and report of the 25th case in literature." Urology. 2014;84(6):1492–1495. doi:10.1016/j.urology.2014.09.002
4. Zeng M, Zeng F, Wang Z, et al. "Urethral calculi with a urethral fistula: a case report and review of the literature." BMC Res Notes. 2017;10(1):444. doi:10.1186/s13104-017-2798-z
5. Horton CE, Devine CJ, Graham JK. "Fistulas of the penile urethra." Plast Reconstr Surg. 1980;66(3):407–418. doi:10.1097/00006534-198009000-00017
6. Ghadimi-Mahani M, Dillman JR, Pai D, Park J, DiPietro M. "MRI of congenital urethroperineal fistula." Pediatr Radiol. 2010;40(Suppl 1):S1–S5. doi:10.1007/s00247-010-1852-y
7. Wagner JR, Carr MC, Bauer SB, et al. "Congenital posterior urethral perineal fistulae: a unique form of urethral duplication." Urology. 1996;48(2):277–280. doi:10.1016/s0090-4295(96)00171-9
8. Brown WC, Dillon PW, Hensle TW. "Congenital urethral-perineal fistula: diagnosis and new surgical management." Urology. 1990;36(2):157–159. doi:10.1016/0090-4295(90)80216-a
9. Tarasconi A, Perrone G, Davies J, et al. "Anorectal emergencies: WSES-AAST guidelines." World J Emerg Surg. 2021;16(1):48. doi:10.1186/s13017-021-00384-x
10. Kuzaka B, Wróblewska MM, Borkowski T, et al. "Fournier's gangrene: clinical presentation of 13 cases." Med Sci Monit. 2018;24:548–555. doi:10.12659/msm.905836
11. Hejase MJ, Simonin JE, Bihrle R, Coogan CL. "Genital Fournier's gangrene: experience with 38 patients." Urology. 1996;47(5):734–739. doi:10.1016/s0090-4295(96)80017-3
12. Wang L, Song W, Lv R, et al. "Precise treatment of pelvic fracture urethral injury associated with urethrorectal fistula." BJU Int. 2024;134(4):589–595. doi:10.1111/bju.16401
13. Stewart L, McCammon K, Metro M, Virasoro R. "SIU/ICUD consultation on urethral strictures: anterior urethra — lichen sclerosus." Urology. 2014;83(3 Suppl):S27–S30. doi:10.1016/j.urology.2013.09.013
14. Kulkarni S, Barbagli G, Kirpekar D, Mirri F, Lazzeri M. "Lichen sclerosus of the male genitalia and urethra: surgical options and results in a multicenter international experience with 215 patients." Eur Urol. 2009;55(4):945–954. doi:10.1016/j.eururo.2008.07.046
15. Chung ASJ, Suarez OA. "Current treatment of lichen sclerosus and stricture." World J Urol. 2020;38(12):3061–3067. doi:10.1007/s00345-019-03030-z
16. Raup VT, Eswara JR, Weese JR, Potretzke AM, Brandes SB. "Urinary-cutaneous fistulae in patients with neurogenic bladder." Urology. 2015;86(6):1222–1226. doi:10.1016/j.urology.2015.07.057
17. Granieri MA, Webster GD, Peterson AC. "Critical analysis of patient-reported complaints and complications after urethroplasty for bulbar urethral stricture disease." Urology. 2015;85(6):1489–1493. doi:10.1016/j.urology.2015.03.002
18. Joseph JV, Andrich DE, Leach CJ, Mundy AR. "Urethroplasty for refractory anterior urethral stricture." J Urol. 2002;167(1):127–129. doi:10.1016/s0022-5347(05)65396-7
19. Verla W, Van Nieuwenhuyse F, Hoebeke P, et al. "Urethroplasty for failed hypospadias repair related strictures in adults: a retrospective analysis with long-term follow-up." Urology. 2020;143:248–254. doi:10.1016/j.urology.2020.05.070
20. Guo H, Sa Y, Fu Q, Jin C, Wang L. "Experience with 32 pelvic fracture urethral defects associated with urethrorectal fistulas: transperineal urethroplasty with gracilis muscle interposition." J Urol. 2017;198(1):141–147. doi:10.1016/j.juro.2017.01.071
21. Erickson BA, Flynn KJ. "Management of necrotizing soft tissue infections (Fournier's gangrene) and surgical reconstruction of debridement wound defects." Urol Clin North Am. 2022;49(3):467–478. doi:10.1016/j.ucl.2022.04.008
22. Susini P, Marcaccini G, Efica J, et al. "Fournier's gangrene surgical reconstruction: a systematic review." J Clin Med. 2024;13(14):4085. doi:10.3390/jcm13144085
23. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. "Urethral stricture disease guideline amendment (2023)." J Urol. 2023;210(1):64–71. doi:10.1097/JU.0000000000003482
24. Horiguchi A. "Management of male pelvic fracture urethral injuries: review and current topics." Int J Urol. 2019;26(6):596–607. doi:10.1111/iju.13947
25. Kumar S, Nagappa B, Ganesamoniv R. "Extensive balanitis xerotica obliterans of urethrocutaneous fistula presenting as mass in scrotum." Urology. 2010;76(2):332–333. doi:10.1016/j.urology.2009.09.005
26. Hillary CJ, Osman NI, Hilton P, Chapple CR. "The aetiology, treatment, and outcome of urogenital fistulae managed in well- and low-resourced countries: a systematic review." Eur Urol. 2016;70(3):478–492. doi:10.1016/j.eururo.2016.02.015
27. Paprottka FJ, Krezdorn N, Lohmeyer JA, et al. "Plastic reconstructive surgery techniques using VRAM or gracilis flaps in order to successfully treat complex urogenital fistulas." J Plast Reconstr Aesthet Surg. 2016;69(1):128–137. doi:10.1016/j.bjps.2015.08.026
28. Xu YM, Sa YL, Fu Q, Zhang J, Jin SB. "Surgical treatment of 31 complex traumatic posterior urethral strictures associated with urethrorectal fistulas." Eur Urol. 2010;57(3):514–520. doi:10.1016/j.eururo.2009.02.035
29. Plamadeala N, Waterloos M, Waterschoot M, Lumen N. "Posterior urethroplasty for pelvic fracture urethral injuries: risk factors for recurrence and complications." World J Urol. 2025;43(1):469. doi:10.1007/s00345-025-05839-3
30. Youssef AH, Fath-Alla M, El-Kassaby AW. "Perineal subcutaneous dartos pedicled flap as a new technique for repairing urethrorectal fistula." J Urol. 1999;161(5):1498–1500. doi:10.1016/s0022-5347(05)68937-9
31. Johnsen NV, Voelzke BB. "Autologous rectus fascia graft interposition repair of urethrocutaneous fistulae in female-to-male metoidioplasty patients." Urology. 2018;116:208–212. doi:10.1016/j.urology.2018.03.013
32. Murphy GP, Fergus KB, Gaither TW, et al. "Urinary and sexual function after perineal urethrostomy for urethral stricture disease: an analysis from the TURNS." J Urol. 2019;201(5):956–961. doi:10.1097/JU.0000000000000027
33. Klemm J, Dahlem R, Schulz RJ, et al. "Perineal urethrostomy for complex urethral strictures: long-term patient-reported outcomes from a reconstructive referral center and a scoping literature review." J Urol. 2024;212(5):738–748. doi:10.1097/JU.0000000000004169
34. Zhao X, Li X, Song Y, Guo Q, Wang J. "Comparison of success rates between urethroplasty and perineal urethrostomy in the treatment of complex urethral strictures: a meta-analysis." World J Urol. 2025;43(1):327. doi:10.1007/s00345-025-05679-1
35. Verla W, Oosterlinck W, Waterloos M, Spinoit AF, Lumen N. "Perineal urethrostomy for complicated anterior urethral strictures: indications and patient's choice — an analysis at a single institution." Urology. 2020;138:160–165. doi:10.1016/j.urology.2019.11.064
36. Fuchs JS, Shakir N, McKibben MJ, et al. "Changing trends in reconstruction of complex anterior urethral strictures: from skin flap to perineal urethrostomy." Urology. 2018;122:169–173. doi:10.1016/j.urology.2018.08.009
37. European Association of Urology. Urethral Strictures: Diagnostic Evaluation (sections 5.2 and 5.2.1). 2026. Guideline chapter.
38. Shiferaw SF, Molla MG, Feye YA. "A case report on the management of congenital urethroperineal fistula in an adolescent, a rare congenital anomaly." Int J Surg Case Rep. 2025;128:111043. doi:10.1016/j.ijscr.2025.111043
39. European Association of Urology. EAU Guidelines on Urological Infections: The Guideline (sections 3.13.3–3.13.5). 2026. Guideline chapter.
40. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Males (section 6.3.4.c.4). 2026. Guideline chapter.
41. Alemu CT, Bekele FS, Asnakew SL, Tegegne CY, Gebreamlak AL. "Congenital posterior urethroperineal fistula, a rare congenital anomaly presented in an adult male patient: a case report." BMC Urol. 2025;25:75. doi:10.1186/s12894-025-01759-x
42. Wagner MC, Klemm J, Roessler N, et al. "Long-term patient-reported outcomes of open urorectal fistula repair after prostate cancer treatment." BJU Int. 2026;137(6):1067–1075. doi:10.1111/bju.70233
43. European Association of Urology. EAU Guidelines on Urethral Strictures: Perioperative Care of Urethral Surgery. 2026. Guideline chapter.
44. Lumen N, Beysens M, Van Praet C, et al. "Perineal urethrostomy: surgical and functional evaluation of two techniques." Biomed Res Int. 2015;2015:365715. doi:10.1155/2015/365715