Urethropubic Fistula
Urethropubic fistula, also termed urinary-pubic symphysis fistula (UPF), urosymphyseal fistula, pubosymphyseal fistula, or (when the bladder side dominates) pubovesical fistula, is an abnormal communication between the urinary tract and the pubic symphysis / pubic bone, frequently accompanied by pubic bone osteomyelitis. It is a rare but severely debilitating late complication of pelvic radiation therapy for prostate cancer, frequently following endoscopic intervention in an irradiated field, most commonly treatment of a radiation-induced bladder-neck contracture or posterior urethral stenosis.[1][2][5]
The literature uses several near-synonymous terms for what is fundamentally a spectrum disorder. "Urethropubic" emphasizes the urethra-to-pubis communication; "pubovesical" emphasizes the bladder-to-pubis communication; "urinary-pubic symphysis fistula (UPF)" is the contemporary umbrella term that captures both. The diagnostic principles overlap, but the urinary origin, extent of infected bone, prior treatment and remaining bladder or outlet function change the reconstructive options.[1][4]
Conservative management frequently fails in published post-radiation series. Definitive treatment commonly combines pubic-bone debridement, fistula excision and urinary reconstruction or diversion, often vascularized interposition, and culture-directed infection treatment. Cystectomy with diversion is common, but bladder- or organ-sparing repair is possible in selected patients, including after radiation.[1][2][13][14]
For operative selection across all repair routes, see the Male Fistula Repair database.
See also: Rectovesical Fistula — Pubovesical Fistula section, PFUI, Bony Pelvic Anatomy, The Retropubic Space, Radiation Tissue Effects, Fistulas landing page.
Epidemiology & Etiology
Pelvic radiation therapy for prostate cancer is the predominant risk factor, present in 93% of cases in contemporary systematic review.[1] In Bugeja’s 16-patient series, all patients had received radiotherapy either as primary treatment or after prostatectomy.[2] Presentation can occur years after treatment; cohort estimates differ in whether they measure time from radiation, other cancer treatment or subsequent instrumentation. In Leuven's 26-patient series, median time from radiotherapy to diagnosis was 102 months; 84.6% had at least one urethral manipulation before diagnosis, with a median of 4 months from the last manipulation.[3][4][9][17]
The Endoscopic-Trigger Pathway
A dominant mechanism threads through most contemporary cases:[2][5]
- Prostate cancer treatment (radical prostatectomy ± radiation; primary radiation alone; brachytherapy)
- Bladder-neck contracture (BNC) or posterior urethral stenosis develops in the irradiated, ischemic field
- Endoscopic intervention (bladder-neck incision, urethral dilation, TURP, holmium laser procedures) attempts to relieve obstruction
- Urinary extravasation through the manipulated, radiation-damaged tissue enters the retropubic space
- Chronic infection establishes in the pubic bone (osteomyelitis)
- Fistula matures between bladder / urethra and pubic symphysis
In the systematic review, 83% of post-radiation cases had prior endoscopic outlet surgery. Bugeja reported bladder-neck contracture in 13/16 patients; these are related but different measures.[2][1] Even apparently minor endoscopic maneuvers (single dilation, brief BNC incision) in previously irradiated tissue can precipitate the cascade.[5]
Other Etiologies
- Other pelvic injury or instrumentation: investigate the urinary and bone anatomy
- Radical gynecologic surgery or pelvic exenteration: pubic osteomyelitis can follow these procedures; confirm a urinary fistula separately before classifying it as UPF.[6]
- Female incontinence surgery: a recognized context for pubic symphysis infection; Ross’s 100-case septic-arthritis review was not a USF-only cohort[7]
- Pelvic malignancy: exclude active disease when clinically indicated; pubic infection and a urinary fistula need separate confirmation[7]
- Cryotherapy or HIFU for prostate cancer: reported in small numbers among pubic osteomyelitis cohorts, alongside radiation and surgery[2][4][10]
Clinical Presentation
The classic triad is chronic suprapubic / groin / pelvic pain, gait disturbance, and recurrent UTI in a patient with prior pelvic radiation and recent endoscopic manipulation:[2][3][4][7][8]
- Chronic, debilitating pubic / pelvic / groin pain
- Difficulty with ambulation or waddling gait
- Pain exacerbated by walking
- Recurrent UTIs
- Urinary obstruction and urosepsis in advanced cases
The Misdiagnosis Problem
UPF is commonly misdiagnosed as osteitis pubis, a sterile inflammatory condition, and managed with NSAIDs, activity modification, and empirical antibiotics for months to years before the true diagnosis is made.[2][4] The clinical mimics include septic arthritis of the pubic symphysis, pubic-bone osteonecrosis, and adductor tendinitis. The distinguishing historical features are prior pelvic radiation and recent endoscopic BOO intervention in a patient with compatible symptoms; obtain prompt imaging when a fistula or bone infection is suspected.
Diagnosis
MRI — the Gold Standard
Pelvic MRI is preferred to delineate fistula, bone involvement and soft-tissue infection. A systematic review reported MRI confirmation in 95% of included cases.[1][10] Reported findings in Sexton’s selected 16-patient series:[10]
- High signal on T2-weighted sequences in the pubic symphysis and involved pubic rami
- Low signal on T1-weighted sequences
- Regional inflammatory myositis in the majority of patients
- Diastasis of the pubic symphysis
- Cortical bone erosion
- Fluid collections: 75% of patients
- Fistulous tract visualization on dedicated sequences
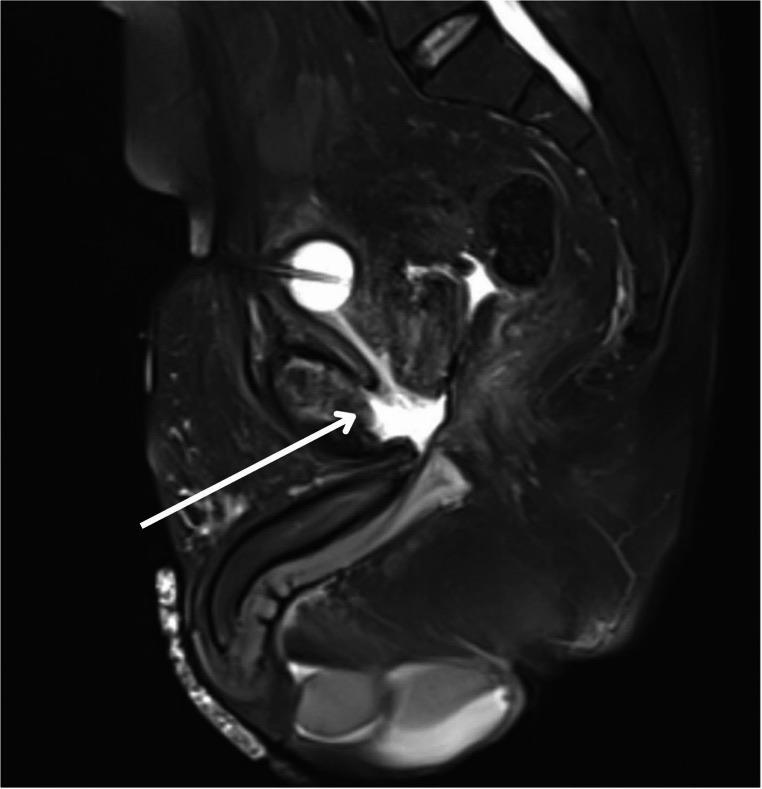
Sagittal pelvic MRI demonstrating a fistulous tract between the urethra and the pubic symphysis (arrow). From Haas C, et al. Curr Urol Rep. 2025;26(1):62, Fig. 3 (CC BY).[16]
Combined MRI + Cystoscopy
The combination of MRI and cystoscopy enables precise characterization of the fistula defect relative to the urinary sphincter complex and the rectum, both necessary for operative planning.[1] In Brändstedt's 24-man post-radiation USF cohort, five had a concomitant rectourethral fistula, and all five underwent sigmoidoscopy during the preoperative workup.[19] Findings at cystoscopy suggestive of UPF include bladder-neck sloughing, mucosal necrosis, dystrophic calcification, and cavitation.
Adjunctive Studies
- Plain radiography is insensitive: no radiographic evidence of osteomyelitis in 63% of Sexton's 16 patients.[10]
- CT demonstrates bone destruction, abscess, soft-tissue mass, adherent bowel loops and the fistulous tract (described in seven patients with post-radiotherapy symphyseal osteomyelitis, mostly bladder or cervical cancer). MRI is preferred for marrow and soft-tissue extent; CT is a reasonable alternative when MRI is not possible.[9][10]
- Retrograde urethrography can visualize the fistula and assess for concurrent stricture.
- Bone sampling: the role of preoperative CT-guided biopsy is uncertain; bone or deep-tissue cultures obtained at debridement are preferred to guide antibiotic therapy.[16][17]
- Urine culture should be obtained, but does not replace bone or tissue cultures: in one selected series, 63% of patients with positive urine cultures had a matching bone organism.[12]
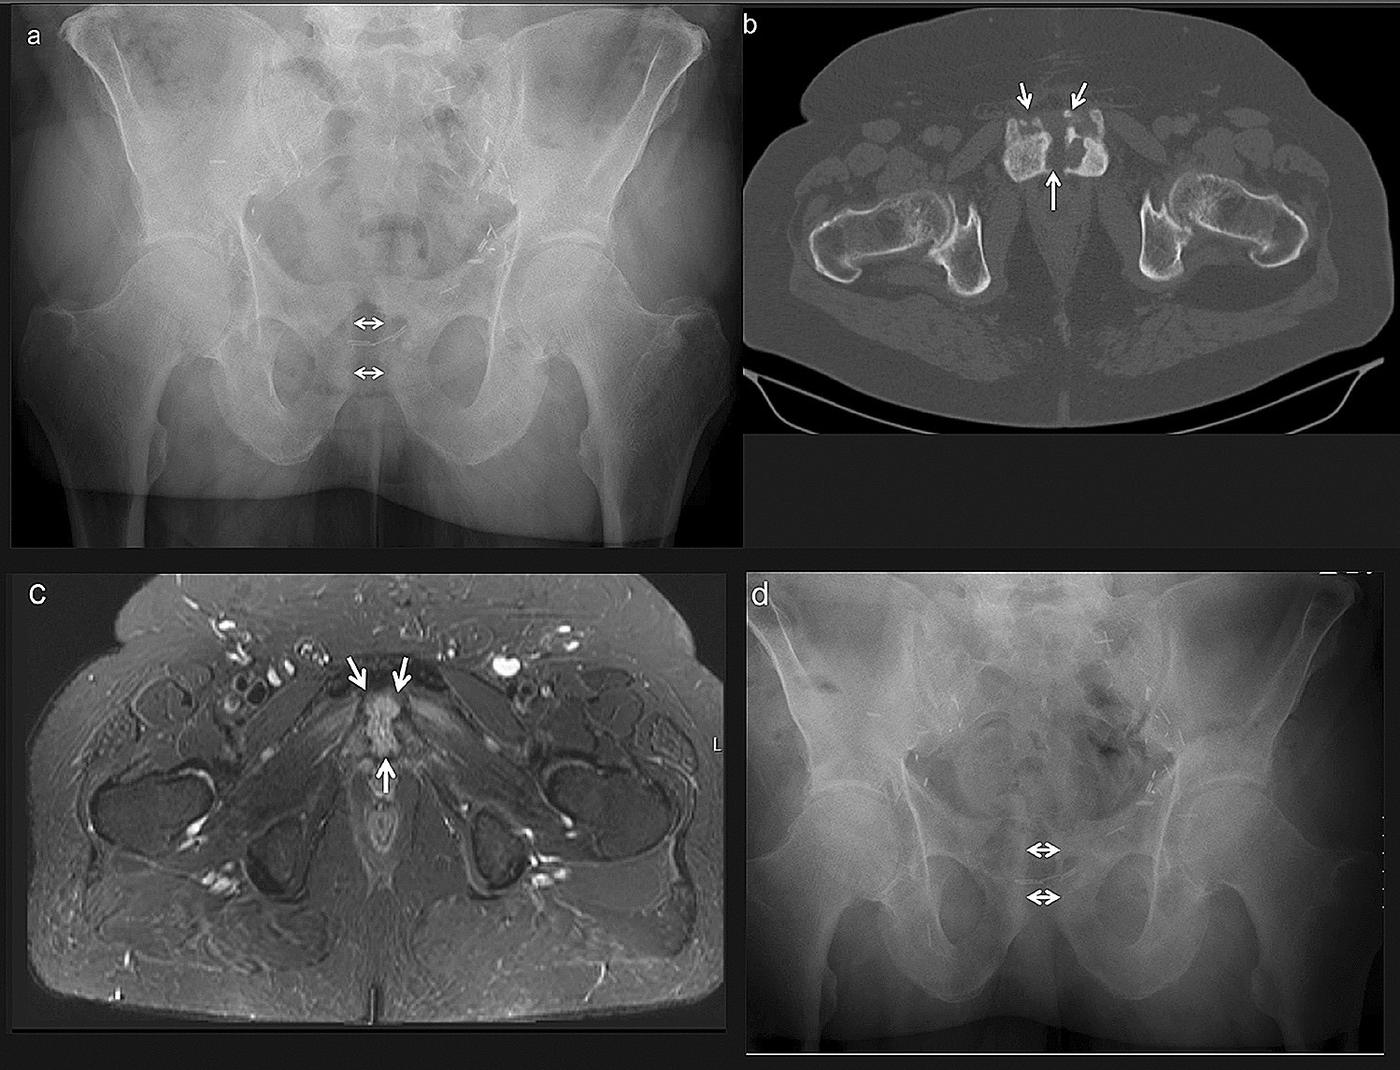
Infected pubic symphysitis in a 69-year-old man after prostatectomy. (a) Preoperative anteroposterior pelvic radiograph showing slight widening of the pubic symphysis (arrows), with surgical clips from the prostatectomy on both sides. (b) CT of the anterior pelvis showing irregular bony surfaces and necrotic bone fragments in the symphyseal joint space (arrows). (c) T2-weighted axial MRI showing a fluid collection in and behind the joint space (arrows). (d) Postoperative radiograph with similar symphyseal widening (arrows). From Devlieger B, et al. Arch Orthop Trauma Surg. 2021;141(11):1835–1843, Fig. 1 (CC BY).[15]
Pathophysiology — UPF as Osteomyelitis
Pubic-bone osteomyelitis commonly accompanies UPF, with a fistulous tract maintaining urinary contamination of the involved bone. The pathology series below are selected surgical populations.[11][12]
Histopathology of Resected Pubic Bone[11]
In Kahokehr’s selected 36-patient extirpative cohort:
- Osteomyelitis: 32/36 (88.9%)
- Chronic osteomyelitis: 41.7%
- Combined acute and chronic osteomyelitis: 44.4%
- Osteonecrosis: 11/36 specimens
Bone Cultures[12]
In Nosé’s 36-patient extirpative cohort, 33/36 (91.7%) had positive bone cultures. Reported organisms included:
- Candida: 11/50 bone-culture isolates (22%)[12]
- Enterococcus: 9/50 bone-culture isolates (18%)[12]
- Pseudomonas: 5/50 bone-culture isolates (10%)[12]
- Staphylococcus aureus: common in athletic / non-radiation populations[7]
In Nosé’s series, urine and bone cultures grew the same organism in 17 cases (reported as 63% after mixed-flora results were excluded).[12] Discordance remains substantial: in Leuven’s series bone cultures were positive in 19/20 sampled patients (95%), and paired urine and bone cultures were strictly discordant in 14/17 (82.4%).[17] Use intraoperative bone or tissue specimens and infectious-disease input to refine treatment.[17]
For persistent fistula with infected or necrotic bone, definitive treatment usually requires debridement of involved pubic bone plus urinary source control. Extent of resection and nonsurgical alternatives depend on disease burden, tissue viability and operative fitness.[11]
Management
Conservative Management — Limited Role
A systematic review of heterogeneous published cases reported conservative-management failure in 96% after radiation and 72% without radiation.[1] One of 16 patients in Bugeja’s series responded to conservative care.[2] Conservative success in Leuven's series was limited to non-irradiated patients, and in a Swedish series three of five patients managed only with catheter or suprapubic tube plus long-term antibiotics (chosen because of comorbidity) died of USF-related infection.[17][19]
Conservative care can be appropriate for selected low-burden disease, patients who decline major surgery, or those whose comorbidity or goals favor palliation. Gupta described two patients managed conservatively because of low disease burden. Individualize drainage, antimicrobial treatment, pain control and monitoring; persistent urinary contamination and bone infection often require surgery for durable control.[4]
Definitive Surgical Management — The Four-Element Operation
Preoperative urinary drainage can limit urine exposure of infected pubic bone; a urethral catheter, suprapubic tube or nephrostomy tubes are selected according to anatomy.[16] Definitive reconstruction commonly combines the following elements, individualized to anatomy and source-control needs:[1][2][4]
- Fistulous tract excision
- Pubic symphyseal debridement / partial pubectomy: guided by infected or nonviable tissue
- Vascularized tissue interposition when indicated: omental flap, rectus muscle or VRAM, or gracilis muscle
- Urinary-tract reconstruction or diversion
Urinary Management — Reconstruction vs Diversion
The division between reconstruction and permanent diversion is driven primarily by bladder quality, radiation history, and the extent of fistula involvement at the bladder neck / trigone.
Cystectomy with ileal-conduit diversion is the most common approach:[1][2]
- In Bugeja's series, 8 of 15 operated patients had cystectomy with ileal conduit and 7 of 15 had reconstruction (salvage prostatectomy with substitution or augmentation cystoplasty); in Patel’s review, 184 cystectomies with diversion versus 30 bladder-sparing operations were reported after radiation (86% versus 14% of those 214 operations)
- Combines bladder removal with fistula excision and debridement of involved pubic bone for source control.[2]
- Removes a poorly functioning reservoir when preservation is unlikely to provide useful function; major morbidity and recurrence remain possible
Bladder-sparing reconstruction: selected by anatomy, function and preferences:[1][2]
- Salvage radical prostatectomy (if prostate still in situ)
- Substitution or augmentation cystoplasty when bladder capacity is inadequate
- Assess usable bladder capacity and compliance, outlet function, infection control and the patient’s ability to manage any augmentation or catheterization
Organ-sparing fistula repair with rectus abdominis muscle flap interposition has been demonstrated in selected irradiated patients:[13]
- Kaufman (n=4): all four patients had prior pelvic radiation and pubic osteomyelitis; all achieved closure after one repair at median 27 months without prostatectomy or diversion
- Requires careful patient selection
Robot-Assisted Holmium Laser Pubic Debridement
Robot-assisted holmium laser debridement of the pubic symphysis has been described with cystectomy and diversion or with urinary reconstruction in small selected series.[8][14] Hebert's four-patient robotic series (holmium debridement, with reconstruction or diversion as judged) reported no fistula recurrence at 7–16 months and suggested the approach for mild osteomyelitis or when prior sacral insufficiency fractures make partial pubectomy risky:[8][14]
Outcomes (Navaratnam series):[14]
- 11 of 12 patients (91.7%) had complete fistula resolution at median 29-month follow-up; 11 had prior prostate radiation[14]
- Median operative time 270 min
- Median length of stay 5 days
- Allows precise, contained debridement of necrotic bone through laparoscopic access
Antibiotic Therapy
- Pathogen-directed treatment based on bone or tissue cultures; urine findings may inform initial coverage but cannot substitute for infected-site cultures[12]
- Individualize duration and route with infectious disease according to organisms, debridement and response; recent reviews describe prolonged culture-directed courses after debridement, without society guidance on regimen or duration;[16] Ross’s historical six-week recommendation came from a heterogeneous pubic septic-arthritis cohort[7][16]
- Suppressive antibiotics may be used in selected conservative plans[4]
- Infectious-disease co-management helps select initial coverage and tailor the often prolonged antibiotic course to operative bone or tissue cultures and surgical source control.[16]
Outcomes
Symptom Resolution
In Bugeja’s 16-patient series, all experienced symptom resolution, including almost immediate pain relief.[2] In 16 prostate cancer survivors with pubic bone osteomyelitis and a urinary tract to pubic symphysis fistula (median age 72; 6 on chronic narcotics before surgery), median pain on an 11-point numeric scale was unchanged by conservative measures (5.5 versus 5.5) but fell to 0 after pubic bone resection and remained 0 at a median follow-up of 9.4 months (p = 0.0005).[21] In a mixed-cause orthopedic series of eight patients with infected pubic symphysitis, only five completed pain follow-up; their mean score fell from 7.2 to 0.4 at a mean 13 months after debridement.[15]
Durability
Small selected series report good closure after bone debridement and urinary source control.[8][14] Persistent leakage, infection, tissue injury and outlet dysfunction can complicate recovery.
Morbidity, Mortality and Recovery
The operation carries high morbidity and prolonged recovery:[2] Bugeja describes a high risk of morbidity and mortality; in Shapiro's five patients treated with pubic debridement, simple cystectomy and diversion, one died postoperatively.[2][5] Among Leuven's 23 surgically treated patients, 13 (56.5%) underwent reintervention after the main operation and 13 (56.5%) had grade III or higher complications by 90 days.[17] All 26 patients were eventually free of fistula and osteomyelitis after up to four treatment attempts.[17]
- Prolonged hospital length of stay
- Significant blood loss in open cases
- Wound and stoma complications
- Prolonged convalescence; in a retrospective series of 57 patients operated for USF, 26 (46%) required a major intervention at least 90 days after surgery (median 11 months), including 14 (25%) who underwent additional major surgery. Pelvic pain resolution was documented in 40 (70%) during follow-up of at least 90 days.[22]
- Postoperative requirement for urinary stoma care (when cystectomy performed)
Timing and Pelvic Ring Stability
In a retrospective Mayo series (27 repairs within 100 days, 31 later; mean follow-up about 25–33 months across groups), earlier repair was associated with less recurrent pain (11.1% versus 46.7%), osteomyelitis (0% versus 20%) and fistula recurrence (3.7% versus 23.3%), with similar 90-day complications. Selection and disease severity may confound these comparisons.[18]
Small series report preserved pelvic stability after limited debridement,[4] but sacral insufficiency fractures are common: 37% of 54 patients developed them (many before surgery), and pubectomy may add risk. Look for sacral fractures on imaging and involve orthopedics when planning resection.[20]
Prevention
Given the dominant etiologic pathway (radiation, then BNC, then endoscopic BOO treatment, then UPF), prevention focuses on the third step:[5]
- Exercise restraint with endoscopic intervention in radiated patients; accept higher thresholds for proceeding to BNC incision, dilation, or TURP.
- Individualize outlet treatment according to stenosis and tissue quality. The EAU 2026 guideline strongly recommends avoiding deep six- and 12-o’clock DVIU incisions for vesicourethral anastomotic or radiation-induced bulbomembranous stenosis because of risks of rectal injury and urosymphyseal fistulation, respectively.[23]
- Inform patients of the UPF risk before any endoscopic manipulation in a radiated pelvis.
- Early imaging (MRI) when any radiated patient with prior BOO treatment develops new pubic or groin pain; do not dismiss as osteitis pubis.
Clinical Pearls
- High index of suspicion in irradiated patients presenting with pubic pain, gait disturbance, and recurrent UTI, especially after any endoscopic BOO procedure.[1][2]
- MRI pelvis should be obtained promptly when UPF is suspected; plain films are insensitive.[10]
- Multidisciplinary team: reconstructive urology, infectious disease, and orthopedic or plastic surgery (for flap).[4][12]
- Plan adequate bone debridement and urinary source control when osteomyelitis is present; tailor resection to involved tissue and clinical circumstances.[11]
- Discuss diversion and feasible reconstructive alternatives using remaining bladder/outlet function, disease extent, operative risk and patient goals.[1][2]
- Even minimally traumatic endoscopic procedures in previously irradiated tissue can precipitate UPF.[5]
- Symptom relief can be substantial after successful surgery; this reframes the operation for patients weighing high morbidity against debilitating chronic pain.[2][15]
See Also
- Male Fistula Repair database
- Principles of Fistula Repair
- Organ-Sparing USF Repair with Interposition Flap
- USF / PPF Bladder-Sparing Approaches
- Primary Repair (No Flap) for USF
- Salvage Prostatectomy for USF
References
1. Patel N, Mehawed G, Dunglison N, et al. Uro-Symphyseal Fistula: A Systematic Review to Inform a Contemporary, Evidence-Based Management Framework. Urology. 2023;178:1–8. doi:10.1016/j.urology.2023.05.002
2. Bugeja S, Andrich DE, Mundy AR. Fistulation Into the Pubic Symphysis After Treatment of Prostate Cancer: An Important and Surgically Correctable Complication. Journal of Urology. 2016;195(2):391–398. doi:10.1016/j.juro.2015.08.074
3. Walach MT, Tavakoli AA, Thater G, et al. Pubic Bone Osteomyelitis and Fistulas After Radiation Therapy of the Pelvic Region: Patient-Reported Outcomes and Urological Management of a Rare but Serious Complication. World Journal of Urology. 2024;42(1):461. doi:10.1007/s00345-024-05155-2
4. Gupta S, Zura RD, Hendershot EF, Peterson AC. Pubic Symphysis Osteomyelitis in the Prostate Cancer Survivor: Clinical Presentation, Evaluation, and Management. Urology. 2015;85(3):684–690. doi:10.1016/j.urology.2014.11.020
5. Shapiro DD, Goodspeed DC, Bushman W. Urosymphyseal Fistulas Resulting From Endoscopic Treatment of Radiation-Induced Posterior Urethral Strictures. Urology. 2018;114:207–211. doi:10.1016/j.urology.2017.12.020
6. Hoyme UB, Tamimi HK, Eschenbach DA, Ramsey PG, Figge DC. Osteomyelitis Pubis After Radical Gynecologic Operations. Obstetrics and Gynecology. 1984;63(3 Suppl):47S–53S. PMID 6700882
7. Ross JJ, Hu LT. Septic Arthritis of the Pubic Symphysis: Review of 100 Cases. Medicine. 2003;82(5):340–345. doi:10.1097/01.md.0000091180.93122.1c
8. Hebert KJ, Boswell TC, Bearrick E, et al. Robotic Puboprostatic Fistula Repair With Holmium Laser Pubic Debridement. Urology. 2022;160:228. doi:10.1016/j.urology.2021.10.019
9. Wignall TA, Carrington BM, Logue JP. Post-Radiotherapy Osteomyelitis of the Symphysis Pubis: Computed Tomographic Features. Clinical Radiology. 1998;53(2):126–130. doi:10.1016/s0009-9260(98)80059-7
10. Sexton SJ, Lavien G, Said N, et al. Magnetic Resonance Imaging Features of Pubic Symphysis Urinary Fistula With Pubic Bone Osteomyelitis in the Treated Prostate Cancer Patient. Abdominal Radiology. 2019;44(4):1453–1460. doi:10.1007/s00261-018-1827-2
11. Kahokehr AA, Boysen WR, Schild MH, et al. Urinary Pubic Symphysis Fistula Leads to Histopathologic Osteomyelitis in Prostate Cancer Survivors. Urology. 2021;148:297–301. doi:10.1016/j.urology.2020.07.038
12. Nosé BD, Boysen WR, Kahokehr AA, et al. Extirpative Cultures Reveal Infectious Pubic Bone Osteomyelitis in Prostate Cancer Survivors With Urinary-Pubic Symphysis Fistulae (UPF). Urology. 2020;142:221–225. doi:10.1016/j.urology.2020.04.095
13. Kaufman DA, Browne BM, Zinman LN, Vanni AJ. Management of Radiation Anterior Prostato-Symphyseal Fistulas With Interposition Rectus Abdominis Muscle Flap. Urology. 2016;92:122–126. doi:10.1016/j.urology.2016.01.029
14. Navaratnam A, Faraj K, Rose K, et al. Robot Assisted Cystectomy With Holmium Laser Debridement for Osteomyelitis of the Pubic Symphysis With Urinary Fistula. Urology. 2019;134:124–134. doi:10.1016/j.urology.2019.08.049
15. Devlieger B, Wagner D, Hopf J, Rommens PM. Surgical Debridement of Infected Pubic Symphysitis Supports Optimal Outcome. Archives of Orthopaedic and Trauma Surgery. 2021;141(11):1835–1843. doi:10.1007/s00402-020-03563-8
16. Haas C, Feinberg A, Koch GE, Patel HV. The Diagnosis and Management of Urosymphyseal Fistula with Pubic Osteomyelitis. Curr Urol Rep. 2025;26:62. doi:10.1007/s11934-025-01293-1
17. Smeyers L, Borremans J, Van der Aa F, Herteleer M, Joniau S. The Complex Challenge of Urosymphyseal Fistula and Pubic Osteomyelitis in Prostate Cancer Survivors. Eur Urol Open Sci. 2024;70:43-51. doi:10.1016/j.euros.2024.09.008
18. Escandón JM, Kreutz-Rodrigues L, Fadel AE, et al. Timing for Repair of Urosymphyseal Fistula After Diagnosis Determines the Incidence Postoperative Outcomes. J Surg Oncol. 2026;133(2):217-225. doi:10.1002/jso.70133
19. Brändstedt J, Abrahamsson J, Baseckas G, et al. Urosymphyseal fistula after pelvic radiotherapy in a tertial referral centre - a rare entity with significant comorbidity requiring multidisciplinary management. Scand J Urol. 2023;58:4-10. doi:10.2340/sju.v58.5765
20. Broida SE, Kemble JP, Wahlig BD, et al. Sacral insufficiency fractures are a frequent and painful consequence of pubic symphysis osteomyelitis. Eur J Orthop Surg Traumatol. 2024;34(1):647-652. doi:10.1007/s00590-023-03707-7
21. Lavien G, Chery G, Zaid UB, Peterson AC. Pubic bone resection provides objective pain control in the prostate cancer survivor with pubic bone osteomyelitis with an associated urinary tract to pubic symphysis fistula. Urology. 2017;100:234-239. doi:10.1016/j.urology.2016.08.035
22. Pinkhasov A, Kemble J, Fadel A, et al. "Delayed Morbidity Associated With Surgical Management of Urosymphyseal Fistula." Urology. 2025;197:180–184. doi:10.1016/j.urology.2024.11.062
23. Lumen N, Campos-Juanatey F, Dimitropoulos K, et al. "EAU Guidelines on Urethral Strictures." EAU Guidelines Office, Arnhem, the Netherlands; 2026. ISBN 978-94-92761-32-5. Disease Management in Males