Buried Penis
Buried penis (BP) is concealment of the penile shaft beneath surrounding skin, prepubic fat, or cicatricial scar, which may impair voiding, hygiene, and sexual activity. It has a congenital (pediatric) form with long inner prepuce in one 61-child series and variable dartos or ligament findings, and an adult acquired form (AABP) associated with morbid obesity, cicatricial circumcision scarring, lichen sclerosus, and scrotal lymphedema.[1][2][3][8][9] Adult acquired buried penis repair is tailored to anatomy; escutcheonectomy, diseased-skin excision, STSG, panniculectomy and scrotoplasty are used when indicated.[37][40] Retrospective series report different endpoints: Pariser found 58/64 (91%) unburied without repeat unburying surgery at median 209 days, Chestnut found 17/76 (22%) recurrent concealment for which repeat repair was offered at mean 436 days, and Plamadeala estimated 83.7% recurrence-free survival at 24 months in 204 men; a 12-patient combined-repair series reported all unburied at mean 8 months.[3][18][23][40] Retrospective cohorts report complications in 27–50%, mainly low-grade wound problems, and small cohorts report improvements in urinary, sexual and psychological measures; a 2023 systematic review judged its included studies at high risk of bias.[4][16][19][29][36][40]
Buried penis describes concealment, whereas micropenis is defined by abnormally short stretched penile length. Adult acquired burial usually conceals normal intrinsic length, but congenital buried penis can include a short shaft; assess stretched penile length when micropenis is a concern.[8][35] Treatment of these is entirely different.[2][6]
For operative technique, see Buried Penis Repair and its component procedures: Escutcheonectomy, Panniculectomy, and Penile Skin Grafting.
Terminology
- Buried penis. Penile shaft concealed by prepubic fat, scrotal tissue, or cicatricial skin; 47/61 children in one congenital series also had a short shaft.[8]
- Concealed or hidden penis. Used interchangeably with buried penis
- Trapped penis. The iatrogenic variant in which a circumcision scar contracts and traps the shaft beneath the skin
- Webbed penis. Penoscrotal webbing obscures the ventral shaft
- Micropenis. True reduction in corporeal length (> 2.5 SD below mean stretched length); a distinct entity that must be excluded
Epidemiology
- Congenital BP. Rare; presents in childhood; exact prevalence unknown[8][9]
- AABP. Described as increasingly common with rising obesity rates; no population incidence estimates exist, and published series are from referral centers[7][36]
- Demographics in surgical referral cohorts: selected series reported mean or median age 44–56 years and mean or median BMI 43–49 kg/m²; a separate 204-patient multicenter cohort reported median age 54 years and BMI 30 kg/m².[3][4][10][11][40]
Etiology and Pathophysiology
Congenital (pediatric) BP
The pediatric form reflects abnormal dartos and fascial mechanics:[6][8][9]
- Abnormal dartos tissue. In Spinoit's prospective operative-specimen study, 14/18 children with buried penis (78%) had hypotrophic or randomly distributed dartos smooth-muscle fibers rather than the normal parallel pattern; 66/94 hypospadias specimens (70%) also had abnormal patterns.[9]
- Abnormal fundiform or suspensory ligaments. Fail to anchor the penis[8]
- Long inner prepuce (LIP). A feature of the cited congenital BP series; may produce ballooning during voiding (congenital megaprepuce is a Grade I variant)[8]
- Hypermobility of ventral skin and dartos. Corporeal bodies telescope proximally into the scrotum and pubis[6]
- Excess suprapubic fat. Contributes in higher grades
Hadidi classification of congenital BP (operative framework from one series):[8]
| Grade | Features | Frequency |
|---|---|---|
| I | Long inner prepuce only | 48% |
| II | LIP + indrawn penis requiring fundiform/suspensory ligament division | 33% |
| III | Grade II + excess suprapubic fat | 20% |
Adult acquired buried penis (AABP)
| Driver | Mechanism |
|---|---|
| Morbid obesity | Massive prepubic fat pad engulfs the shaft; pannus covers the genitalia[1][2][3] |
| Massive weight loss (post-bariatric) | Redundant skin apron covers a normal-position penis ("pseudo-BP"); Mirastschijski describes apronectomy with prepubic lift and tissue fixation.[1] |
| Prior circumcision with cicatricial scarring | Circumcision scar contracts over the shaft → "trapped penis"; circumcision often worsens unrecognized BP[1][2] |
| Lichen sclerosus (BXO) | Chronic inflammatory scarring can cause phimosis and skin contracture.[15] In Daly’s 180-patient buried-penis repair-or-penectomy cohort, LS was found on final pathology in 23%; stricture intervention was required in 54.8% with LS versus 23.8% without.[14] |
| Scrotal lymphedema | Massive scrotal edema engulfs the shaft[3][10] |
| Hidradenitis suppurativa, diabetes | Chronic perineal inflammation; tissue-quality and infection risk; hidradenitis and scrotal lymphedema were common in a small plastic-surgery series[2][10] |
Urine trapping and skin disease. In obesity-related AABP, retracted shaft skin can remain moist and develop maceration or dermatitis. Occluded urine exposure has been proposed as a contributor to male genital LS: in Doiron and Bunker's series of 19 previously circumcised obese men with LS, 16 reported urinary microincontinence. LS-related scarring can further conceal the penis.[13][14][15]
Weight loss may improve fat-related concealment and operative risk, but does not reliably reverse established scarring or redundant skin. In a mixed-methods interview study (n = 20), 4 patients reported that weight loss made their condition worse, and the mons pannus and skin changes (LS, scarring) are often irreversible.[16][17] In a survey of men after bariatric surgery, those with AABP (11 of 64) reported improved voiding, anatomy and sexual function, but the study was small and cross-sectional.[38]
Classification of AABP
Several systems are in use, each oriented to a different decision. Maizels (1986) proposed an early classification of penile concealment in children that guided choice of procedure.[39]
Mirastschijski (2018) — surgical phenotype[1]
| Type | Phenotype | Operation |
|---|---|---|
| 1 — Pseudo-BP | Normal-position penis under lax skin (post-bariatric) | Apronectomy + prepubic lift with tissue fixation |
| 2 — Intermediate | Partial penile invagination | Prepubic apronectomy + anchoring sutures |
| 3 — Classical | Complete retraction into prepubic fat ± cicatricial circumcision scarring | Scar excision + prepubic fat reduction + shaft extraction + anchoring + skin reconstruction |
Hesse (2019) — preoperative anatomy[11]
I (skin deficiency or iatrogenic scarring), II (excess abdominal skin and fat), III (combined; 16/27 [59%] in Hesse’s series), IV (III plus severe scrotal edema). [11]
Pariser–Santucci (2018) — surgical complexity[18]
I (local flap), II (skin graft), III (scrotal surgery), IV (escutcheonectomy), V (panniculectomy). Categories III–V are complex repairs (approximately 69% of that series); they had higher BMI and higher rates of high-grade complications. Success was defined as an unburied penis without additional unburying surgery (91%; all failures were complex repairs).[18]
Flynn–Erickson (2022)[7]
Classifies by status of four anatomic components (abdominal pannus, escutcheon, penile skin, scrotal skin) with their respective fascial attachments, using standardized photographs. The resulting penis-abdomen-scrotum (PAS) system had interrater reliability of κ = 0.95 in a 101-patient, 10-center cohort, and its subtypes tracked with the operation performed; outcome correlation has not yet been shown.[37]
Clinical Presentation
AABP affects multiple functional domains.[14][16][19]
- Urinary dysfunction. A urinary-problem theme was coded in 19 of 20 patient interviews (95%); reported problems include inability to direct stream, sitting to void, urine pooling in skin folds, chronic wetness and maceration.[16]
- Sexual dysfunction was a theme in 19 of 20 patient interviews (95%).[16] In a separate 11-patient surgical series, 10 reported significant preoperative ED.[19]
- Recurrent infection. Balanitis, cellulitis, candidal dermatitis from the warm, moist environment
- Lichen sclerosus. Found on final pathology in 23% of Daly’s 180 patients undergoing buried penis repair or penectomy [14]
- Concurrent urethral stricture. Common in referral cohorts; in the 180-patient Daly cohort, 54.8% with LS versus 23.8% without LS required stricture intervention [14]
- Psychological distress. Mental-health difficulties were discussed by 11 of 20 interviewees (55%), including depression and/or anxiety; relationship avoidance and social isolation were also described [16]
- Care barriers. 14 of 20 interviewees (70%) reported difficulty obtaining treatment [16]
Penile Cancer Association
AABP combines multiple risk factors for penile SCC (chronic inflammation, phimosis, LS, poor hygiene, HPV exposure):[14][20][21][22]
- Penile SCC was found in 7% of 150 men with AABP in a single-center referral cohort (Pekala 2019).[20]
- Premalignant lesions: 35% in that cohort (including condyloma, LS and carcinoma in situ)[20]
- Penile cancer was present in 5% of a later 180-patient cohort undergoing buried penis repair or penectomy from the same institution (Daly 2025).[14] This is prevalence on final pathology in a surgical cohort; LS was the study's primary finding (23%)[14]
- Penis that cannot be exposed preoperatively: in 203 repairs, penile cancer was found in 6.5% of men whose penis could not be exposed versus 2.5% of those who could be examined (OR 2.71, 95% CI 0.56–13.12; not significant). LS was more common when the penis could not be exposed (28.4% vs 13.8%; OR 2.89). Keep these figures separate from the 7% and 5% estimates; the cohorts and denominators differ[44]
- Implication: thorough penile examination (which often requires surgical unburying), biopsy of suspicious penile tissue ,[43] pathologic exam of all excised specimens, and ongoing surveillance in patients with adverse skin changes
Diagnostic Evaluation
- History. Duration, weight history, prior circumcision, voiding and sexual function, infections, care-access barriers
- Physical exam. Measure stretched penile length to assess corporeal length and identify a coexisting short shaft or micropenis; assess skin quality, LS changes, escutcheon size, pannus, and scrotal pathology.[8][35]
- Standardized preoperative photographs for classification and surgical planning[7]
- Urethral evaluation. Given the association with stricture, consider cystoscopy or RUG, particularly with obstructive symptoms or LS[14][18]
- Skin biopsy. Classic LS is usually diagnosed clinically; biopsy if the diagnosis is uncertain, first-line treatment fails, or neoplasia is suspected.[47]
- Preoperative optimization assessment. BMI, glycemic control, smoking, nutrition, frailty index[4][23]
Management
Conservative measures
EAU 2026 recommends lifestyle change and risk-factor modification, particularly weight loss, to reduce surgical complications and improve outcomes , extensive counseling on the benefits and complications of AABP surgery , and surgery for AABP to be considered and performed in high-volume centers . It also recommends considering detailed genital examination in all men presenting with a short-penis complaint, particularly those with BMI above 30 kg/m², lichen sclerosus or penile cancer history and urinary or sexual difficulty or poor cosmesis ; using a classification system for AABP presentation and planning is weak.[35] It notes postoperative complications are frequent, up to 3.5% Clavien-Dindo grade V in the evidence it cites (level 3), with low recurrence and satisfactory function.[35]
- Weight management is part of treatment; residual redundant skin or fixed scarring may still require reconstruction[16][17]
- Potent topical corticosteroids are first-line treatment for penile LS and may improve LS-related phimosis; fixed concealment from excess tissue or established scarring may still require reconstruction.[15][17]
- Hygiene optimization to reduce infection
- Preoperative weight optimization is encouraged where feasible.[23]
Surgical management — AABP
The modern operation is multi-component reconstruction.[3][4][24][25]
Operative components selected by anatomy and tissue quality:
- Penile degloving and unburying. Release of all cicatricial attachments; excision of diseased shaft skin
- Escutcheonectomy. En bloc excision of the suprapubic fat pad (escutcheon) to prevent re-burying
- Panniculectomy when indicated. Remove a contributory abdominal pannus. Panniculectomy was used in 28% of one 103-patient high-complexity cohort[4] and in 7 of 101 patients in a separate multicenter cohort[37]. In the NSQIP analysis, patients undergoing combined repair had higher BMI and more wound complications before adjustment; the adjusted 30-day complication difference was not statistically significant.[4][26][37]
- Scrotoplasty when indicated: reduction of redundant or lymphedematous scrotal tissue[3][10]
- Penile skin reconstruction with split-thickness skin graft (STSG) to the denuded shaft[3][25][27]
- Anchoring sutures. Fixation of penopubic and penoscrotal skin to deep fascia (Buck's, rectus) to prevent retraction[1][6]
- Urethral surgery when indicated. Coordinate meatotomy, urethroplasty, or perineal urethrostomy with skin reconstruction; selected long anterior strictures may be repaired before buried-penis reconstruction.[14][18][46]
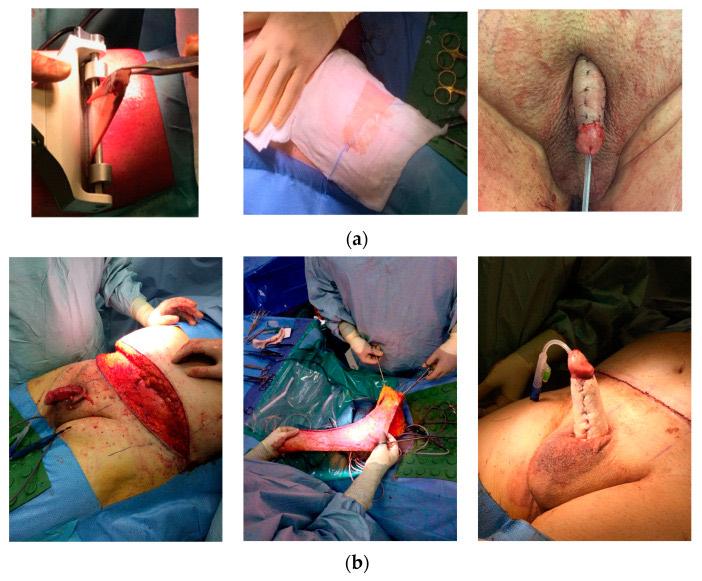
Skin graft harvest and use in adult acquired buried penis reconstruction: (a) split-thickness skin graft (STSG) harvested from the anterior thigh with an air dermatome at 0.3 mm thickness, with the donor site prepared with Vaseline; (b) full-thickness skin graft (FTSG) taken from the removed escutcheon or abdominal tissue. From Falcone M, et al. Life (Basel). 2024;14(10):1321, Figure 2 (CC BY 4.0).[45]
Specific technique variants
| Approach | Notes |
|---|---|
| Escutcheonectomy + STSG (Tang/Santucci, Fuller/Rusilko)[3][24] | En-bloc escutcheon excision; STSG harvested from thigh; Strother separately described graft harvest from the excised escutcheon specimen to avoid a separate donor wound[25]; Figler described a 5–7-day bolster[27]; graft take was 80–100% at 2 months in Tang's five men and 80–100% (mean 91.7%) in Fuller's 12 patients |
| Outpatient panniculectomy + STSG (Figler)[27] | Modified trapezoid pannus mobilization; STSG harvested from pannus; discharge on postoperative day 0 or 1 in 19 patients (median age 70), graft take ≥ 95% in all, cellulitis 26%, minor dehiscence 16% |
| Limited panniculectomy + STSG (Hampson/Voelzke)[28] | 42 underwent repair; 27 of 39 surviving patients completed long-term follow-up (mean 39 months). Among respondents, 85% reported lasting success, 85% would repeat surgery, and 74% reported a positive life change. |
| Penile degloving + ventral anchoring sutures (Alter–Ehrlich)[6] | For patients with adequate shaft skin (no STSG needed); ventral tacking of penoscrotal subdermis to tunica albuginea prevents proximal telescoping |
Surgical management — congenital (pediatric) BP
For asymptomatic preschool boys whose concealment is mainly from suprapubic adiposity, a 2025 review describes observation with reassessment at school age.[48] Inspect the glans and meatus for hypospadias or epispadias before planning isolated buried-penis repair.[48] Congenital buried-penis repairs use techniques tailored to pediatric anatomy, with varying methods and follow-up across published series.[6][8][30][31][32][33][34] Hadidi reported further surgery in 5/61 children (9%) during mean three-year follow-up, while Delgado-Miguel reported no reoperations among 19 children during median 96-month follow-up.[8][32]
Principles:
- Penile degloving
- Excision of abnormal dartos / fibrous tethering
- Release of tethering where needed; the Hadidi series describes ligament division in Grades II–III
- Anchoring. Penile-base skin to Buck's fascia or tunica albuginea
- Skin coverage. Circumcision with redistribution, Z-plasty, scrotal advancement flap, or dorsal dartos flap
- Individualized management of suprapubic adiposity. The Grade III approach describes lipectomy in selected children.
Selected pediatric outcomes:
| Technique | Reported outcome | Follow-up |
|---|---|---|
| Dorsal dartos flap[32] | No reoperations among 19 children; 95% parental cosmetic satisfaction | Median 96 mo |
| External phallopexy ("3 stitches")[30] | No symptomatic recurrence in 28 selected children | Mean 11 mo |
| Modified penoplasty[33] | 95% without postoperative retraction (10/201 had retraction) | 6 mo |
| Midline incision rotation flaps[31] | 89% good, 11% satisfactory | Median 56 mo |
| Simplified Frenkl technique[34] | 23/26 (88.5%) in the circumcision-at-repair group avoided repeat buried-penis repair; 7/49 (14.3%) in the revision-of-circumcision group had mild recurrence without further treatment | Mean 4.4 yr |
Outcomes — AABP
The following estimates come from heterogeneous surgical referral series with different definitions and follow-up.
| Outcome | Result |
|---|---|
| Unburying and recurrence outcomes | Pariser: 58/64 (91%) unburied without further surgery at median 209 d; Falcone: 88.7% 1-year recurrence-free survival; Plamadeala: Kaplan–Meier recurrence-free survival of 91.5% at 12 months and 83.7% at 24 months (204 men; median follow-up 18 months, IQR 7–46); Chestnut: 17/76 (22%) recurrent concealment for which repeat repair was offered at mean 436 d (59/76, 78%, without that event). A selected 12-patient series reported all unburied (100%) at mean 8 months.[3][18][23][29][40] |
| Recurrence (re-burying) | 5–22% across series, depending on definition and follow-up (22% at mean 436 d in Chestnut)[23][36][40] |
| Overall complication rate | 27–50% (30% Chestnut, 32% Falcone, 33% Hampson, 27% Plamadeala, 50% Staniorski)[4][23][28][29][40] |
| Wound dehiscence | 16–31%[4][27] |
| Wound infection / cellulitis | 6.4% (13/204) in Plamadeala’s multicenter cohort, 30% in Staniorski’s high-complexity 103-patient cohort, and 26% (5/19) in Figler’s selected outpatient series; a systematic review reported 4.7–33% across heterogeneous studies and definitions[4][27][36][40] |
| High-grade complications (Clavien ≥ 3) | 7% overall (Falcone); 23% in Pariser high-complexity repairs[18][29] |
| STSG take rate | 80–100%; partial or total graft loss 1.5–21% across a systematic review[3][27][36] |
| Urinary function improvement | 82–91% among postoperative participants (9/11 in Amend, 14/16 in Theisen, 91% among 11 in Rybak, and 91% among 12 questionnaire completers in Voznesensky)[5][12][16][19] |
| Sexual function improvement | 41–87.5% among postoperative respondents (12–16 for the range endpoints; Amend additionally reported 8/11, 73%)[5][12][16] |
| Would undergo surgery again | 85% of 27 long-term respondents in Hampson and 92% of 12 postoperative questionnaire completers in Voznesensky[12][28] |
| Positive life change | 74% of 27 long-term respondents in Hampson and 83% of 12 postoperative questionnaire completers in Voznesensky[12][28] |
| Depression (CES-D) | 7 of 11 preoperatively → 2 of 11 postoperatively[19] |
Risk factors for complications and recurrence
| Factor | Effect |
|---|---|
| BMI > 40 | 12.7-fold higher odds of recurrence (76 patients, wide uncertainty)[23] |
| BMI > 38 | 6.7-fold higher odds of any complication[23] |
| Each 1-point BMI increase | 12% higher adjusted odds of recurrence; 11% higher adjusted odds of complication[23] |
| Frailty (MFI ≥ 2) | Complication 71% vs 41%; adjusted OR 6.4 (95% CI 1.8–23)[4]; mFI-5 also predicted complications in a separate 55-patient series (adjusted OR 5.3)[41] |
| Complex repair (Pariser III–V) | Pariser's 64-patient cohort reported high-grade complications in 23% versus 0% (p = 0.02); in Plamadeala's 204-man retrospective cohort, high-complexity repair was associated with more complications (32.6% versus 13.3%; adjusted OR 2.89, 95% CI 1.25–6.68) and lower recurrence hazard (adjusted HR 0.35, 95% CI 0.1–0.8).[18][40] |
Concurrent Urethral Stricture
Urethral assessment is important, particularly with obstructive symptoms or LS. In Daly’s 180-patient surgical cohort, 23% had LS on pathology and stricture intervention was required in 54.8% with LS versus 23.8% without LS.[14] Concurrent meatotomy, urethroplasty, or perineal urethrostomy may be performed at the time of BP repair.[14][18]
For the broader operative framework, see Lichen Sclerosus and Urethrocutaneous Fistula.
Special Considerations
Circumcision and BP
Circumcision performed on a child or adult with an unrecognized buried penis is a well-known cause of trapped penis: the scar contracts over the retracted shaft, worsens concealment, and creates cicatricial phimosis. Circumcision should be avoided or performed only as part of a proper buried-penis repair.[1][2][8]
For a neonate who presents with trapped penis shortly after circumcision, topical 0.05% betamethasone three times daily for 3 weeks combined with manual retraction was described in a retrospective series of 14 neonates with a dense cicatrix of the residual foreskin distal to the glans: 11 (79%) had cicatrix softening, including two with easy glans exposure and two with a mild residual cicatrix amenable to vertical relaxation incision; three (21%) required formal operative repair at 5 to 8 months of age.[42]
Multidisciplinary planning
Complex AABP repair often benefits from collaboration between urology and plastic surgery for panniculectomy, complex closure, and skin grafting; dermatology input is valuable for LS management.[2][7][25]
Perioperative optimization
- Weight loss before surgery is encouraged (without indefinite delay; the condition causes ongoing harm)[23]
- Glycemic control. Wound healing and infection risk
- Smoking cessation. Graft survival
- Frailty assessment. In a 103-patient retrospective high-complexity cohort, frailty was associated with postoperative complications (71% versus 41%); use this finding for counseling and preoperative planning.[4]
- VTE prophylaxis. Combined repair can be prolonged (mean 312 ± 59 minutes in a 12-patient escutcheonectomy, scrotoplasty and STSG series), and high-complexity case mix includes higher-BMI patients.[3][18] In Hampson’s 42-patient limited panniculectomy and STSG series, the postoperative protocol used subcutaneous heparin during five days of bed rest; one patient developed pulmonary embolism.[28]
Key Principles
- Distinguish concealment from micropenis. Adult acquired burial usually conceals normal intrinsic length, whereas congenital buried penis can include a short measured shaft; assess stretched penile length when micropenis is a concern.[2][6][8][35]
- Weight management improves risk factors; reconstruction may be needed for persistent functional concealment with scarring or redundant skin[16][17]
- AABP reconstruction may combine escutcheonectomy, diseased-skin excision and STSG with panniculectomy or scrotoplasty when indicated. Reported endpoints differ: Pariser found 58/64 (91%) unburied without additional surgery at median 209 days; Chestnut found 17/76 (22%) recurrent concealment for which repeat repair was offered at mean 436 days (59/76, 78%, without that event), with higher BMI associated with recurrence; Plamadeala estimated 83.7% recurrence-free survival at 24 months in 204 men.[18][23][40]
- In Staniorski’s 103 high-complexity repairs, 50% had any complication, with Clavien I–II events in 41% of the cohort; in Voznesensky’s 12 postoperative questionnaire completers, 9/12 (75%) had wound complications, all Clavien I[4][12]
- BMI informs risk counseling. Chestnut's 76-patient retrospective cohort associated higher BMI with recurrence and complications. In Plamadeala's 204-patient cohort, BMI was associated with recurrence by logistic regression, but the BMI ≥30 category did not retain statistical significance in adjusted Cox recurrence analysis, and BMI was not significant in the multivariable complication model.[23][40]
- Screen for penile cancer. Selected cohorts contain occult SCC and other skin disease.[14][20] Biopsy suspicious penile lesions before reconstruction .[43]
- Screen for urethral stricture. Evaluate according to symptoms, examination and LS; concurrent management may be needed[14][18]
- Lichen sclerosus was present on pathology in 23% of the Daly surgical cohort and was associated with more stricture intervention (54.8% vs 23.8%)[14]
- The psychological burden is substantial and improved after surgery in small series[16][19]
- Congenital BP has variable dartos and fascial findings; selected pediatric repairs use anchoring, with 5/61 children requiring further surgery at mean three-year follow-up in one series and no reoperations among 19 dorsal-dartos-flap recipients at median 96 months in another.[8][9][32]
See Also
- Buried Penis Repair
- Escutcheonectomy
- Panniculectomy
- Penile Skin Grafting
- Penile Skin Reconstruction
- Scrotal Reconstruction
- Lichen Sclerosus
Podcasts
Videos
References
1. Mirastschijski U. "Classification and treatment of the adult buried penis." Ann Plast Surg. 2018;80(6):653–659. doi:10.1097/SAP.0000000000001410
2. Pestana IA, Greenfield JM, Walsh M, Donatucci CF, Erdmann D. "Management of 'buried' penis in adulthood: an overview." Plast Reconstr Surg. 2009;124(4):1186–1195. doi:10.1097/PRS.0b013e3181b5a37f
3. Fuller TW, Theisen K, Rusilko P. "Surgical management of adult acquired buried penis: escutcheonectomy, scrotectomy, and penile split-thickness skin graft." Urology. 2017;108:237–238. doi:10.1016/j.urology.2017.05.053
4. Staniorski CJ, Myrga JM, Vasan RV, Klein RD, Rusilko PJ. "Surgical outcomes and prediction of complications following high-complexity buried penis reconstruction." J Urol. 2023;210(5):782–790. doi:10.1097/JU.0000000000003669
5. Theisen KM, Fuller TW, Rusilko P. "Surgical management of adult-acquired buried penis: impact on urinary and sexual quality of life outcomes." Urology. 2018;116:180–184. doi:10.1016/j.urology.2018.03.031
6. Alter GJ, Ehrlich RM. "A new technique for correction of the hidden penis in children and adults." J Urol. 1999;161(2):455–459. doi:10.1016/s0022-5347(01)61922-0
7. Flynn KJ, Vanni AJ, Breyer BN, Erickson BA. "Adult-acquired buried penis classification and surgical management." Urol Clin North Am. 2022;49(3):479–493. doi:10.1016/j.ucl.2022.04.009
8. Hadidi AT. "Buried penis: classification surgical approach." J Pediatr Surg. 2014;49(2):374–379. doi:10.1016/j.jpedsurg.2013.09.066
9. Spinoit AF, Van Praet C, Groen LA, et al. "Congenital penile pathology is associated with abnormal development of the dartos muscle: a prospective study of primary penile surgery at a tertiary referral center." J Urol. 2015;193(5):1620–1624. doi:10.1016/j.juro.2014.10.090
10. Corder B, Googe B, Velazquez A, Sullivan J, Arnold P. "Surgical management of acquired buried penis and scrotal lymphedema: a retrospective review." J Plast Reconstr Aesthet Surg. 2023;85:18–23. doi:10.1016/j.bjps.2023.06.021
11. Hesse MA, Israel JS, Shulzhenko NO, et al. "The surgical treatment of adult acquired buried penis syndrome: a new classification system." Aesthet Surg J. 2019;39(9):979–988. doi:10.1093/asj/sjy325
12. Voznesensky MA, Lawrence WT, Keith JN, Erickson BA. "Patient-reported social, psychological, and urologic outcomes after adult buried penis repair." Urology. 2017;103:240–244. doi:10.1016/j.urology.2016.12.043
13. Doiron PR, Bunker CB. "Obesity-related male genital lichen sclerosus." J Eur Acad Dermatol Venereol. 2017;31(5):876–879. doi:10.1111/jdv.14035
14. Daly WC, Klein RD, Myrga JM, Quiroga-Garza G, Rusilko PJ. "Lichen sclerosus in patients undergoing adult-acquired buried penis repair: a large cohort review." Urology. 2025;205:260–264. doi:10.1016/j.urology.2025.07.061
15. Kwok R, Shah TT, Minhas S. "Recent advances in understanding and managing lichen sclerosus." F1000Res. 2020;9:F1000 Faculty Rev-369. doi:10.12688/f1000research.21529.1
16. Amend GM, Holler JT, Sadighian MJ, et al. "The lived experience of patients with adult acquired buried penis." J Urol. 2022;208(2):396–405. doi:10.1097/JU.0000000000002667
17. Figler BD, Chery L, Friedrich JB, Wessells H, Voelzke BB. "Limited panniculectomy for adult buried penis repair." Plast Reconstr Surg. 2015;136(5):1090–1092. doi:10.1097/PRS.0000000000001722
18. Pariser JJ, Soto-Aviles OE, Miller B, Husainat M, Santucci RA. "A simplified adult acquired buried penis repair classification system with an analysis of perioperative complications and urethral stricture disease." Urology. 2018;120:248–252. doi:10.1016/j.urology.2018.05.029
19. Rybak J, Larsen S, Yu M, Levine LA. "Single center outcomes after reconstructive surgical correction of adult acquired buried penis: measurements of erectile function, depression, and quality of life." J Sex Med. 2014;11(4):1086–1091. doi:10.1111/jsm.12417
20. Pekala KR, Pelzman D, Theisen KM, et al. "The prevalence of penile cancer in patients with adult acquired buried penis." Urology. 2019;133:229–233. doi:10.1016/j.urology.2019.07.019
21. Staniorski C, Grajales V, Pekala KR, et al. "Buried penis reconstruction in the management of localized penile cancer." Urology. 2022;170:221–225. doi:10.1016/j.urology.2022.09.012
22. Brouwer OR, Albersen M, Parnham A, et al. "European Association of Urology — American Society of Clinical Oncology collaborative guideline on penile cancer: 2023 update." Eur Urol. 2023;83(6):548–560. doi:10.1016/j.eururo.2023.02.027
23. Chestnut C, Koch G, Stewart A, et al. "Increased body mass index is associated with recurrence and complications following repair for adult acquired buried penis." J Sex Med. 2025;qdaf149. doi:10.1093/jsxmed/qdaf149
24. Tang SH, Kamat D, Santucci RA. "Modern management of adult-acquired buried penis." Urology. 2008;72(1):124–127. doi:10.1016/j.urology.2008.01.059
25. Strother MC, Skokan AJ, Sterling ME, Butler PD, Kovell RC. "Adult buried penis repair with escutcheonectomy and split-thickness skin grafting." J Sex Med. 2018;15(8):1198–1204. doi:10.1016/j.jsxm.2018.05.009
26. Barrow B, Laspro M, Brydges HT, et al. "Technical considerations and outcomes for panniculectomy in the setting of buried penis patients: a systematic review and database analysis." Ann Plast Surg. 2024;93(3):355–360. doi:10.1097/SAP.0000000000004025
27. Figler BD, Gan ZS, Mohan CS, Zhang Y, Filippou P. "Outpatient panniculectomy and skin graft for adult buried penis." Urology. 2020;143:255–256. doi:10.1016/j.urology.2020.04.129
28. Hampson LA, Muncey W, Chung PH, et al. "Surgical and functional outcomes following buried penis repair with limited panniculectomy and split-thickness skin graft." Urology. 2017;110:234–238. doi:10.1016/j.urology.2017.07.021
29. Falcone M, Preto M, Timpano M, et al. "The outcomes of surgical management options for adult acquired buried penis." Int J Impot Res. 2023;35(8):712–719. doi:10.1038/s41443-022-00642-9
30. Radwan AB, GadAllah MA, Soliman MH, AbouZeid AA. "External phallopexy: a revisited technique and algorithm for simple management of buried penis." J Pediatr Surg. 2023;58(3):580–586. doi:10.1016/j.jpedsurg.2022.07.028
31. Manasherova D, Kozyrev G, Gazimiev M. "Buried penis surgical correction: midline incision rotation flaps." Urology. 2020;138:174–178. doi:10.1016/j.urology.2020.01.021
32. Delgado-Miguel C, Mejía R, Amesty V, et al. "Dorsal dartos flap for buried penis treatment: surgical technique and long-term outcomes." Pediatr Surg Int. 2025;41(1):274. doi:10.1007/s00383-025-06181-w
33. Yang T, Zhang L, Su C, Li Z, Wen Y. "Modified penoplasty for concealed penis in children." Urology. 2013;82(3):697–700. doi:10.1016/j.urology.2013.03.046
34. Frenkl TL, Agarwal S, Caldamone AA. "Results of a simplified technique for buried penis repair." J Urol. 2004;171(2 Pt 1):826–828. doi:10.1097/01.ju.0000107824.72182.95
35. European Association of Urology. EAU Guidelines on Sexual and Reproductive Health, Limited Update March 2026, sections 9.1.3.a, 9.1.4 and 9.3.2.a (adult acquired buried penis). Guideline.
36. Falcone M, Sokolakis I, Capogrosso P, et al. "What are the benefits and harms of surgical management options for adult-acquired buried penis? A systematic review." BJU Int. 2023;131(1):8–19. doi:10.1111/bju.15696
37. Schlaepfer CH, Flynn KJ, Alsikafi NF, et al. "Clinical validation of an adult-acquired buried penis classification system based on standardized evaluation of the penis, abdomen, and scrotum." Urology. 2023;180:249–256. doi:10.1016/j.urology.2023.04.048
38. Dick B, Lopez A, Grant R, et al. "Adult acquired buried penis and bariatric surgery: a mighty motivator." Transl Androl Urol. 2026;15(2):36. doi:10.21037/tau-2025-692
39. Maizels M, Zaontz M, Donovan J, Bushnick PN, Firlit CF. "Surgical correction of the buried penis: description of a classification system and a technique to correct the disorder." J Urol. 1986;136(1 Pt 2):268–271. doi:10.1016/s0022-5347(17)44837-3
40. Plamadeala N, Lee WGD, Ruffo A, et al. "Outcomes of adult acquired buried penis (AABP) reconstruction: a multicentre cohort study." Int J Impot Res. 2026;38(4):354–362. doi:10.1038/s41443-026-01269-w
41. Moura SP, Shaffrey EC, Lam CS, et al. "Modified Frailty Index predicts postoperative complications following adult-acquired buried penis surgery: a retrospective cohort study." J Plast Reconstr Aesthet Surg. 2024;88:493–499. doi:10.1016/j.bjps.2023.11.034
42. Palmer JS, Elder JS, Palmer LS. "The use of betamethasone to manage the trapped penis following neonatal circumcision." J Urol. 2005;174(4 Pt 2):1577–1578. doi:10.1097/00005392-200510020-00015
43. National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Penile Cancer. Version 2.2026. June 5, 2026.
44. Quinn A, Holum P, Daly W, Klein R, Rusilko P. "Pathologic differences in adult acquired buried penis patients by exhumable status." Urology. 2026;215:137–140. doi:10.1016/j.urology.2026.05.007
45. Falcone M, Plamadeala N, Cirigliano L, et al. "The outcomes of adult acquired buried penis surgical reconstruction." Life (Basel). 2024;14(10):1321. doi:10.3390/life14101321
46. Fuller TW, Pekala K, Theisen KM, Tapper A, Burks F, Rusilko PJ. "Prevalence and surgical management of concurrent adult acquired buried penis and urethral stricture disease." World J Urol. 2019;37(7):1409–1413. doi:10.1007/s00345-018-2514-1
47. De Luca DA, Papara C, Vorobyev A, et al. "Lichen sclerosus: The 2023 update." Front Med (Lausanne). 2023;10:1106318. doi:10.3389/fmed.2023.1106318
48. Xiang B, Peng J, Shang X, Zu X, Li D. "Concealed penis: A review of multilevel classification and surgical reconstruction techniques." BJUI Compass. 2025;6(1):e470. doi:10.1002/bco2.470