Hidradenitis Suppurativa — Genitourinary Disease
Hidradenitis suppurativa (HS) is a chronic, inflammatory, recurrent disease of the hair follicle with prevalence estimates that vary by ascertainment (European self-report 1.0%–2.1%; European diagnosis codes 0.09%–0.51%; initial U.S. diagnosis-code estimates approximately 0.1%), presenting with painful nodules, abscesses, draining sinus tracts, and disfiguring scarring in apocrine-bearing intertriginous areas.[1][2] In a prospective Italian dermatology clinic cohort of 53 women with HS, 18 (34%) had anogenital involvement at first assessment; genital disease can bring patients to urologists and gynecologists.[37][5][7] Advanced genitoperineal HS can produce draining sinus tracts, urethrocutaneous fistulae, scrotal or vulvar architectural destruction, secondary lymphedema, and, in long-standing disease, squamous cell carcinoma arising within chronic sinuses.
Epidemiology and Pathogenesis
Women are affected at a 3:1 ratio compared to men; onset typically occurs between ages 18–39.[4][5] The average diagnostic delay is approximately 10 years, during which patients consult dermatologists, gynecologists, surgeons, and primary care physicians and receive multiple misdiagnoses.[2]
Pathogenesis begins with follicular plugging and rupture, triggering an inflammatory cascade driven by TNF-α, IL-1β, and IL-17, leading to immune cell infiltration, tissue destruction, and fibrosis.[1][6] Risk factors include genetic predisposition, obesity, smoking, and hormonal influences.[6]
Hurley Staging
| Stage | Description |
|---|---|
| I | Abscess formation, single or multiple, without sinus tracts or cicatrization |
| II | Recurrent abscesses with tract formation and scarring, single or multiple widely separated lesions |
| III | Diffuse or near-diffuse involvement, or multiple interconnected tracts and abscesses across the entire area |
Genital and Perineal Anatomy of Involvement
Anatomic sites of urologic or urogynecologic relevance:
- Mons pubis, inguinal folds, and vulva and labia in women
- Scrotum, penile shaft, and perineum in men
- Perianal and gluteal regions across sexes
Genital HS is particularly challenging due to functional and reconstructive concerns unique to these anatomic zones. The JAMA Surgery multidisciplinary review by Hamad et al. emphasizes that genital HS requires coordinated care among dermatology, surgery, and urology or urogynecology.[5]
Urologic Complications
| Complication | Notes |
|---|---|
| Urethrocutaneous fistula | Chronic perineal HS can erode into the urethra; documented in case series including fistula with concurrent phimosis[8] |
| Urethral involvement | Urethrocutaneous fistula with phimosis has been reported in HS.[8] Severe genitoperineal disease may require reconstruction.[9] In HS-associated buried penis, obstructive symptoms or meatal narrowing warrant assessment for coexisting urethral stricture before reconstruction.[38] |
| Phimosis | Scarring from penile/preputial HS produces acquired phimosis[8] |
| Scrotal/genital lymphedema | Lymphatic obstruction from fibrosis and scarring; see Genital Lymphedema[10] |
| Hospitalized genitourinary infections | In a retrospective claims cohort of adalimumab initiators, GU infection hospitalizations were more frequent in patients with HS (n = 1,650) than in patients with psoriasis (n = 8,699; IRR 2.22, 95% CI 1.22–3.86).[11] |
| Urethral and perirectal fistulae (case reports) | Individual reports document urethral fistula and perirectal sinus tracks or fistulae, without establishing incidence or a routine screening indication.[30][31] For perianal tunnels or gastrointestinal symptoms, assess for coexisting Crohn disease; pelvic MRI may help distinguish perianal HS tunnels from Crohn fistulae by evaluating sphincteric tracts and rectal inflammation.[2][39] |
For urethrocutaneous fistula and urethral stricture technique, see Urethrocutaneous Fistula and Scrotal Reconstruction.
Urogynecologic Considerations
HS disproportionately affects women of childbearing age; obstetrician-gynecologists are uniquely positioned for early diagnosis during routine well-woman examinations.[12][13]
Vulvoperineal HS: Involvement of the vulva, labia, mons pubis, and perineum causes severe scarring, contractures, and tissue destruction impairing urinary and sexual function. Vulvar HS is frequently misdiagnosed as Bartholin cyst, folliculitis, sexually transmitted infection, or Crohn disease.[7]
Sexual dysfunction. In a 13-country European dermatology outpatient survey, 66.7% of a small HS subgroup reported at least some skin-related sexual difficulty during the preceding week on DLQI item 9.[40] Pain, malodorous discharge, genital scarring, and psychological distress can contribute; the North American guideline includes impaired sexual health among comorbidities to screen for (strength of recommendation A; evidence levels I–II), and validated instruments such as FSFI or IIEF can be used.[3][14][2]
PCOS association. A U.S. cross-sectional study found PCOS prevalence of 9.0% among women with HS versus 2.9% among women without HS (reported odds ratio 2.14, 95% CI 2.04–2.24); shared hormonal and metabolic pathways remain possible.[3][36]
Menstrual flares: Many women report perimenstrual HS flares, indicating hormonal modulation of disease activity.[5]
Pregnancy and breastfeeding: HS management during pregnancy and breastfeeding requires careful medication selection, as many systemic therapies have limited safety data in these populations.[13] For patients planning pregnancy with HS controlled on a biologic, the 2025 North American guideline recommends continuing that treatment through pregnancy (strong; very low certainty) and pediatric consultation about timing of live vaccines after in-utero biologic exposure (strong; very low certainty); it recommends adalimumab when a biologic is needed during pregnancy or breastfeeding (strong; moderate certainty).[32] It recommends avoiding oral doxycycline in pregnancy (strong; low certainty) and suggests avoiding topical resorcinol because pregnancy safety evidence is lacking (conditional; very low certainty).[32]
Malignant Transformation
Squamous cell carcinoma (SCC) arising within chronic HS lesions is rare but serious; among 122 published SCCs in 95 patients (78% men), sites were gluteal (47.5%), perianal (18.9%), and genital (13.9%).[15]
| Feature | Data |
|---|---|
| Mean latency from HS onset to SCC | ~25 years[15] |
| Population predominantly affected | Caucasian men, smokers, severe disease[16] |
| Metastasis rate | ~54% (34/63 with reported outcomes)[15] |
| Mortality | ~59% (44/75 with reported outcomes)[15] |
| Malignant degeneration rate | Up to 4.6% in groin/perianal/perineal severe disease[17] |
| Vulvar/perianal/perineal cancers | Tend to present at advanced stage[18] |
SCC surveillance. North American guidelines recommend periodic skin examination of chronic perineal and buttock lesions.[3] Suspicious new or rapidly growing lesions warrant biopsy; an atypical non-healing lesion may need repeat deep biopsy before reconstruction.[41][19] HPV vaccination has been proposed as a potential preventive strategy.[20]
Surgical Management
Surgical treatment of genitoperineal HS requires a multidisciplinary team (dermatology, reconstructive urology or urogynecology, wound care, rheumatology or immunology).[9]
Principles:
- Match surgery to lesion extent. Deroofing can spare surrounding tissue for localized recurrent tunnels; Hurley III genital disease with extensive irreversible tunnels or scarring may require excision tailored to involved tissue and vital structures, without a universal 1 cm margin.[3][2][29] Preoperative high-frequency ultrasound can map tunnels and lesional margins when available.[42] Reserve incision and drainage for relief of acute abscess pain, not definitive disease control.[3]
- Perianal, vulvar, and inferior breast locations carry higher recurrence rates after surgery[3]
- Coordinate perioperative biologic treatment. SHARPS supported continuing adalimumab through axillary or inguinal wide excision with secondary-intention healing; it observed no increase in postoperative infection or hemorrhage.[25] In a pragmatic RCT (31 per arm), adalimumab plus surgery improved 12-month IHS4 change (−19.1 versus −7.8) and DLQI change (−8.2 versus −4.0) compared with adalimumab alone; follow-up was too short to assess surgical recurrence.[35]
Two-stage reconstruction. In a five-patient, single-centre series of men with Hurley III genital, perineal, anorectal or gluteal disease after biologic treatment failure, radical excision, negative-pressure wound therapy and delayed meshed split-thickness skin grafting yielded >90% graft take in each patient on postoperative day 5; no recurrence was observed within surgically treated areas over a median 19.2 months.[21] For flap and graft options by defect location, see Scrotal Reconstruction and Buried Penis Repair.
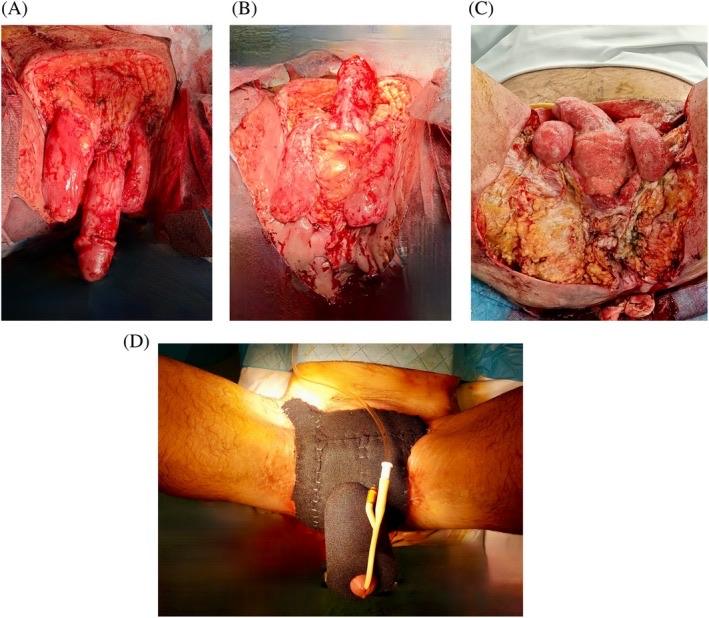
Stage one: resection of all diseased anogenital tissue with negative-pressure closure. (A, B) Excision avoiding injury to the glans, corpora cavernosa and corpus spongiosum and preserving the tunica vaginalis layers of the spermatic cords and testes. (C) Excision avoiding harm to the anal sphincter. (D) Wound closure with negative-pressure wound therapy with instillation and dwell time (system only partly shown). From Fuchs N, et al. Int Wound J. 2026;23(4):e70874, Figure 2 (CC BY-NC).[21]
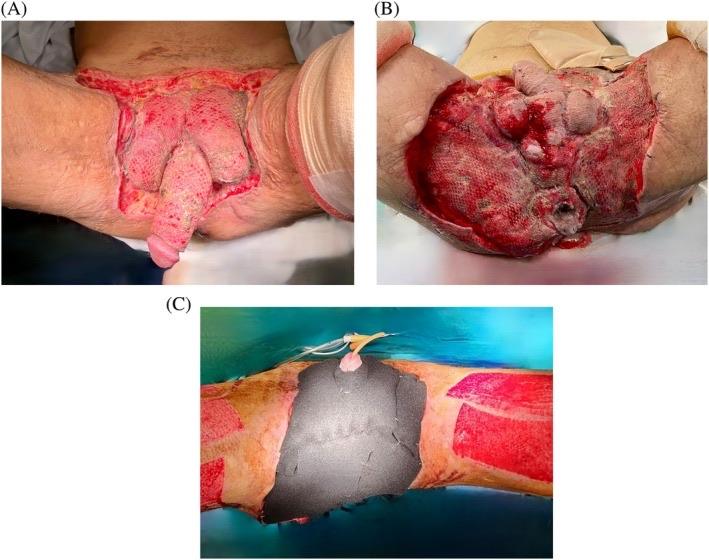
Stage two: wound reconstruction with split-thickness skin graft and negative-pressure wound therapy, with marginal areas left to heal by secondary intention. (A, B) Meshed graft used to replace penile skin. (A, C) Graft donor sites. (C) Negative-pressure system in place (only partly shown). From Fuchs N, et al. Int Wound J. 2026;23(4):e70874, Figure 4 (CC BY-NC).[21]
Medical Management
Select systemic therapy with dermatology, including infection and TB screening and review of agent-specific contraindications and warnings. For bimekizumab, test liver enzymes, alkaline phosphatase, and bilirubin at baseline and periodically during treatment; avoid use in acute liver disease or cirrhosis.[24] Review any history of severe depression or suicidal ideation and weigh risks and benefits; avoid use in active inflammatory bowel disease.[24]
| Agent | Class | FDA Status | Notes |
|---|---|---|---|
| Adalimumab (Humira) | Anti-TNF | Approved 2015 | Adult label: 160 mg on day 1 (or split over two days), 80 mg on day 15, then 40 mg weekly or 80 mg every other week from day 29; pediatric dosing (age 12 and older, at least 30 kg) is weight-based.[23] Infliximab is used off-label in refractory disease. |
| Secukinumab (Cosentyx) | Anti-IL-17A | Adults approved 2023; ages 12 and older approved 2026 | Adults: 300 mg at weeks 0–4, then every 4 weeks; consider every 2 weeks if response is inadequate. Ages 12 and older weighing 30 to <90 kg: 150 mg at weeks 0–4, then every 4 weeks; at least 90 kg: 300 mg on the same schedule.[27] In adults with moderate-to-severe HS, SUNSHINE/SUNRISE used week-16 HiSCR50 as the primary endpoint.[1] Exercise caution in patients with inflammatory bowel disease and monitor for symptoms.[27] |
| Bimekizumab (Bimzelx) | Anti-IL-17A/F | HS indication approved 2024 | Label: 320 mg at weeks 0, 2, 4, 6, 8, 10, 12, 14 and 16, then every 4 weeks.[24] BE HEARD I/II week-16 HiSCR50 was 48% vs 29% and 52% vs 32% for the every-2-week arms versus placebo.[26] |
| Tetracyclines; clindamycin plus rifampicin | Antibiotics | Off-label | Tetracyclines are used for mild-to-severe inflammatory HS; clindamycin plus rifampicin may be considered for selected moderate-to-severe disease for 10–12 weeks.[29] Rifampicin can reduce combined hormonal contraceptive effectiveness; review contraception before prescribing.[33] |
| Hormonal therapy | OCPs, spironolactone | Off-label | Perimenstrual flare suppression |
| Resorcinol 15% cream | Topical | Off-label | Compounded topical option for localized, non-fistulous lesions in mild-to-moderate HS; pregnancy safety data are insufficient.[29] |
Agents under investigation include JAK inhibitors, apremilast, fostamatinib, and others targeting the IL-17 and JAK/STAT pathways.[22] In adults with moderate-to-severe HS after inadequate response, intolerance, or contraindication to systemic therapy, investigational oral povorcitinib 45 mg daily achieved week-12 HiSCR50 in 82/204 (40%) versus 60/202 (30%) with placebo in STOP-HS1 and 88/208 (42%) versus 58/203 (29%) in STOP-HS2.[43] Upadacitinib 30 mg daily reached HiSCR50 in 38.3% (18/47 treated patients) at week 12 in a 68-patient phase 2 trial, significant against a prespecified historical placebo rate of 25.0% but not against the 21-patient in-trial placebo group; it is not approved for HS.[28] The 2025 European S2k guideline gives a current treatment algorithm alongside the North American guidance.[29]
Key Takeaways for the Reconstructive Urologist
- Differential diagnosis. Recurrent boils, abscesses, or draining tunnels in the groin, perineum, or genitalia warrant consideration of HS.[3][5] The 2026 European guideline specifies at least two painful or suppurating episodes within six months as a diagnostic history criterion.[34]
- Multidisciplinary care. Urologists or urogynecologists play a central role in managing complications (fistulae, strictures, lymphedema) and reconstruction after wide excision.[9]
- SCC surveillance. The North American guideline recommends periodic skin examination of chronic perineal and buttock HS (C/II).[3] Promptly biopsy suspicious or treatment-refractory lesions.[15][19]
- Sexual dysfunction screening should be routine given the high prevalence.[14][2]
- Early dermatology referral allows assessment for biologic therapy and coordinated surgical planning.[13][2]
See Also
References
1. Kimball AB, Jemec GBE, Alavi A, et al. "Secukinumab in Moderate-to-Severe Hidradenitis Suppurativa (SUNSHINE and SUNRISE): Week 16 and Week 52 Results of Two Identical, Multicentre, Randomised, Placebo-Controlled, Double-Blind Phase 3 Trials." Lancet. 2023;401(10378):747–761. doi:10.1016/S0140-6736(23)00022-3
2. Sabat R, Alavi A, Wolk K, et al. "Hidradenitis Suppurativa." Lancet. 2025;405(10476):420–438. doi:10.1016/S0140-6736(24)02475-9
3. Alikhan A, Sayed C, Alavi A, et al. "North American Clinical Management Guidelines for Hidradenitis Suppurativa: A Publication From the United States and Canadian Hidradenitis Suppurativa Foundations: Part I: Diagnosis, Evaluation, and the Use of Complementary and Procedural Management." J Am Acad Dermatol. 2019;81(1):76–90. doi:10.1016/j.jaad.2019.02.067
4. Wipperman J, Bragg DA, Litzner B. "Hidradenitis Suppurativa: Rapid Evidence Review." Am Fam Physician. 2019;100(9):562–569. PMID 31674740
5. Hamad J, McCormick BJ, Sayed CJ, et al. "Multidisciplinary Update on Genital Hidradenitis Suppurativa: A Review." JAMA Surg. 2020;155(10):970–977. doi:10.1001/jamasurg.2020.2611
6. van Straalen KR, Prens EP, Gudjonsson JE. "Insights Into Hidradenitis Suppurativa." J Allergy Clin Immunol. 2022;149(4):1150–1161. doi:10.1016/j.jaci.2022.02.003
7. Ogunleye AA, Ndem IE, Bui H, Sayed CJ. "Vulvoperineal Hidradenitis Suppurativa: Diagnosis, Treatment, and Management of Deformities." Obstet Gynecol Surv. 2021;76(10):644–653. doi:10.1097/OGX.0000000000000944
8. Chaikin DC, Volz LR, Broderick G. "An Unusual Presentation of Hidradenitis Suppurativa: Case Report and Review of the Literature." Urology. 1994;44(4):606–8. doi:10.1016/s0090-4295(94)80072-3
9. Michel C, DiBianco JM, Sabarwal V, Stein DM. "The Treatment of Genitoperineal Hidradenitis Suppurativa: A Review of the Literature." Urology. 2019;124:1–5. doi:10.1016/j.urology.2018.10.013
10. Yuan JT, Naik HB. "Complications of Hidradenitis Suppurativa." Semin Cutan Med Surg. 2017;36(2):79–85. doi:10.12788/j.sder.2017.022
11. Wafae BGO, Charrow AP, Stein D, Barbieri JS, Noe MH. "Risk of Serious Infection With Adalimumab in Hidradenitis Suppurativa Compared With Psoriasis." JAMA Dermatol. 2025;161(11):1116–1122. doi:10.1001/jamadermatol.2025.2881
12. Collier EK, Parvataneni RK, Lowes MA, et al. "Diagnosis and Management of Hidradenitis Suppurativa in Women." Am J Obstet Gynecol. 2021;224(1):54–61. doi:10.1016/j.ajog.2020.09.036
13. Sayed CJ, Hsiao JL, Okun MM. "Clinical Epidemiology and Management of Hidradenitis Suppurativa." Obstet Gynecol. 2021;137(4):731–746. doi:10.1097/AOG.0000000000004321
14. Matusiak Ł. "Profound Consequences of Hidradenitis Suppurativa: A Review." Br J Dermatol. 2020;183(6):e171–e177. doi:10.1111/bjd.16603
15. Sachdeva M, Mufti A, Zaaroura H, et al. "Squamous Cell Carcinoma Arising Within Hidradenitis Suppurativa: A Literature Review." Int J Dermatol. 2021;60(11):e459–e465. doi:10.1111/ijd.15677
16. Cohen PR, Cohen-Kurzrock RA, Riahi RR. "Cancer and Hidradenitis Suppurativa." Clin Dermatol. 2024;42(6):585–601. doi:10.1016/j.clindermatol.2024.09.014
17. Abu Rached N, Rüth J, Gambichler T, Ocker L, Bechara FG. "A State-of-the-Art Systematic Review of Cancer in Hidradenitis Suppurativa." Ann Med. 2024;56(1):2382372. doi:10.1080/07853890.2024.2382372
18. Makris GM, Poulakaki N, Papanota AM, et al. "Vulvar, Perianal and Perineal Cancer After Hidradenitis Suppurativa: A Systematic Review and Pooled Analysis." Dermatol Surg. 2017;43(1):107–115. doi:10.1097/DSS.0000000000000944
19. Agdogan Ö. "Gluteal-Anogenital-Perineal Reconstruction in Patients With Chronic Hidradenitis Suppurativa and Related Squamous Cell Carcinoma." J Wound Care. 2026;35(1):76–83. doi:10.12968/jowc.2024.0123
20. Abu Rached N, Käpynen R, Doerler M, et al. "HPV-16-Induced Squamous Cell Carcinoma in Hidradenitis Suppurativa: HPV Vaccination May Be Useful." Cancers. 2025;17(4):702. doi:10.3390/cancers17040702
21. Fuchs N, Pavljak L, Hauptman D, Mance M. "Two-Stage Surgical Management of Anogenital Hidradenitis Suppurativa in Patients on Biologic Therapy: A Retrospective Case Series." Int Wound J. 2026;23(4):e70874. doi:10.1111/iwj.70874
22. Jaguan D, Nguyen KT, Goldfarb N. "Selective Small Molecule Inhibitors for Hidradenitis Suppurativa: Today and Tomorrow." J Am Acad Dermatol. 2024;91(6S):S31–S36. doi:10.1016/j.jaad.2024.09.014
23. AbbVie. HUMIRA prescribing information. Label.
24. US Food and Drug Administration. BIMZELX prescribing information, HS indication. 2024. Label.
25. Bechara FG, Podda M, Prens EP, et al. "Efficacy and Safety of Adalimumab in Conjunction With Surgery in Moderate to Severe Hidradenitis Suppurativa: The SHARPS Randomized Clinical Trial." JAMA Surg. 2021;156(11):1001–1009. doi:10.1001/jamasurg.2021.3655
26. Kimball AB, Jemec GBE, Sayed CJ, et al. "Efficacy and Safety of Bimekizumab in Patients With Moderate-to-Severe Hidradenitis Suppurativa (BE HEARD I and BE HEARD II): Two 48-Week, Randomised, Double-Blind, Placebo-Controlled, Multicentre Phase 3 Trials." Lancet. 2024;403(10443):2504–2519. doi:10.1016/S0140-6736(24)00101-6
27. Novartis. COSENTYX prescribing information (hidradenitis suppurativa dosing, section 2.10). DailyMed.
28. Ackerman LS, Schlosser BJ, Zhan T, et al. "Improvements in Moderate-to-Severe Hidradenitis Suppurativa With Upadacitinib: Results From a Phase 2, Randomized, Placebo-Controlled Study." J Am Acad Dermatol. 2025;92(6):1252–1260. doi:10.1016/j.jaad.2024.12.046
29. Zouboulis CC, Bechara FG, Benhadou F, et al. "European S2k Guidelines for Hidradenitis Suppurativa/Acne Inversa Part 2: Treatment." J Eur Acad Dermatol Venereol. 2025;39(5):899–941. doi:10.1111/jdv.20472
30. Gronau E, Pannek J. "Urethral fistula caused by acne inversa (hidradenitis suppurativa): a case report." Int Urol Nephrol. 2002;34(3):377–378. doi:10.1023/a:1024419200996
31. Nadgir R, Rubesin SE, Levine MS. "Perirectal sinus tracks and fistulas caused by hidradenitis suppurativa." AJR Am J Roentgenol. 2001;177(2):476–477. doi:10.2214/ajr.177.2.1770476
32. Alhusayen R, Dienes S, Lam M, et al. "North American Clinical Practice Guidelines for the Medical Management of Hidradenitis Suppurativa in Special Patient Populations." J Am Acad Dermatol. 2025;92(4):825–852. doi:10.1016/j.jaad.2024.11.071
33. Nguyen AT, Curtis KM, Tepper NK, et al. "U.S. Medical Eligibility Criteria for Contraceptive Use, 2024." MMWR Recomm Rep. 2024;73(4):1–126. doi:10.15585/mmwr.rr7304a1
34. Jemec GBE, Villumsen B, van Straalen KR, et al. "European S2k Guidelines for Hidradenitis Suppurativa/Acne Inversa Part 1: Epidemiology, Diagnosis and Clinical Assessment." J Eur Acad Dermatol Venereol. Published online August 18, 2026. doi:10.1111/jdv.70638
35. Aarts P, van Huijstee JC, van der Zee HH, van Doorn MBA, van Straalen KR, Prens EP. "Adalimumab in Conjunction with Surgery Compared with Adalimumab Monotherapy for Hidradenitis Suppurativa: A Randomized Controlled Trial in a Real-World Setting." J Am Acad Dermatol. 2023;89(4):677–684. doi:10.1016/j.jaad.2023.04.034
36. Garg A, Neuren E, Strunk A. "Hidradenitis Suppurativa Is Associated with Polycystic Ovary Syndrome: A Population-Based Analysis in the United States." J Invest Dermatol. 2018;138(6):1288–1292. doi:10.1016/j.jid.2018.01.009
37. Di Cesare A, Rosi E, Amerio P, Prignano F. "Clinical and Ultrasonographic Characterization of Hidradenitis Suppurativa in Female Patients: Impact of Early Recognition of the Disease." Life (Basel). 2023;13(8):1630. doi:10.3390/life13081630
38. Ho TS, Gelman J. "Evaluation and management of adult acquired buried penis." Transl Androl Urol. 2018;7(4):618–627. doi:10.21037/tau.2018.05.06
39. Yamanaka-Takaichi M, Yalon M, Loftus EV, et al. "Magnetic Resonance Imaging for Distinguishing Perianal Hidradenitis Suppurativa from Fistulizing Crohn Disease." Dermatology. 2025;241(5–6):437–446. doi:10.1159/000547570
40. Sampogna F, Abeni D, Gieler U, et al. "Impairment of Sexual Life in 3,485 Dermatological Outpatients From a Multicentre Study in 13 European Countries." Acta Derm Venereol. 2017;97(4):478–482. doi:10.2340/00015555-2561
41. Jourabchi N, Fischer AH, Cimino-Mathews A, Waters KM, Okoye GA. "Squamous cell carcinoma complicating a chronic lesion of hidradenitis suppurativa: a case report and review of the literature." Int Wound J. 2017;14(2):435–438. doi:10.1111/iwj.12671
42. Wortsman X, Alfageme F, Dini V, et al. "International Consensus Statement on the Use of Ultrasound in Hidradenitis Suppurativa." J Eur Acad Dermatol Venereol. 2026;40(4):626–636. doi:10.1111/jdv.20600
43. Porter ML, Martorell A, Sayed CJ, et al. "Povorcitinib for hidradenitis suppurativa: the randomized, double-blind, placebo-controlled STOP-HS1 and STOP-HS2 phase 3 trials." Nat Med. 2026;32(8):3071–3081. doi:10.1038/s41591-026-04534-z