Lichen Sclerosus
Lichen sclerosus (LS) is a chronic inflammatory mucocutaneous dermatosis that preferentially affects the anogenital skin. It produces ivory-white, atrophic, sclerotic plaques with itching, soreness, fissuring, scarring, sexual dysfunction, urinary morbidity, and increased risk of squamous cell carcinoma.[1][2][3]
For operative details of LS-related urethral stricture repair, see Kulkarni One-Stage Urethroplasty, Asopa Dorsal Inlay, Johanson Two-Stage Urethroplasty, and Blandy Perineal Urethrostomy. For vulvar scarring and adhesions, see Local Skin Flaps for LS Sequelae.
Definition and Terminology
| Term | Meaning |
|---|---|
| Lichen sclerosus (LS) | Current preferred term |
| Lichen sclerosus et atrophicus (LSA) | Historical term; "et atrophicus" is usually dropped |
| Balanitis xerotica obliterans (BXO) | Historical male genital term, especially for glans/prepuce disease |
| Kraurosis vulvae | Obsolete term for vulvar LS |
LS is usually anogenital, but extragenital disease occurs. Vaginal mucosa is classically spared; vulvar, perineal, perianal, penile, preputial, glanular, and meatal skin are the reconstructively important territories.[1][4][5]
Epidemiology
LS is underdiagnosed. Population estimates vary by specialty, biopsy practice, and registry capture.[1][5][6]
Patterns:
- Female predominance varies by ascertainment: a 2023 review cites female-to-male ratios of 3:1 to 10:1, while a Swedish nationwide specialist-care register found 114.4 female versus 47.2 male diagnoses per 100,000 person-years (about 2.4:1).[1][6]
- Bimodal female age pattern: prepubertal girls and postmenopausal women.
- Male disease commonly presents as phimosis, glans or preputial plaques, meatal stenosis, or urethral stricture. It is strongly associated with an intact foreskin: uncircumcised men were far more likely to have LS than circumcised men (age-adjusted OR 53.6, 95% CI 7.2-395.9), and LS involves the urethra in about 20% of men (EAU 2026).[56]
- Children may present with vulvar symptoms, constipation from painful fissures, or phimosis or BXO in boys.[1][7][8]
Recent registry studies suggest LS incidence is rising, likely reflecting both true recognition and improved diagnostic coding. A Swedish nationwide register study reported incidence in both females and males, while Danish biopsy-verified vulvar LS data showed a roughly 7-fold rise in incidence from 1997 to 2022 (5.0 to 35.7 per 100,000 person-years) and increased vulvar precancer or cancer risk.[6][9]
Etiology and Pathophysiology
The cause is incompletely understood. LS likely represents an immune-mediated disease in genetically susceptible skin, modified by trauma, hormonal milieu, local inflammation, and oxidative stress.[1][10][11]
Immune and Genetic Factors
- Autoimmune disease is common, especially thyroid disease, alopecia areata, vitiligo, and pernicious anemia.
- Circulating autoantibodies and reactivity against extracellular matrix protein 1 (ECM1) have been reported.
- T-cell mediated inflammation, Th1/IFN-gamma pathways, tissue-remodeling genes, and microRNA changes are implicated.
- Familial clustering and HLA associations support genetic susceptibility.[1][10]
Hormonal and Local Factors
Prepubertal and postmenopausal peaks suggest a role for hypoestrogenic tissue vulnerability. Premenopausal women and adult men can develop active disease.[1][2]
Koebner Phenomenon
LS can appear in areas of trauma, chronic irritation, surgical scars, urine exposure, and friction.[1][5][11] Trauma can unmask or reactivate disease in susceptible tissue.[1][5][11]
Infection
Infectious triggers such as Borrelia burgdorferi have been proposed but remain unproven. LS should not be treated as an infectious disease.[5][11]
Clinical Presentation
Symptoms
Common symptoms include:
- Pruritus
- Burning, soreness, fissuring, or pain
- Dyspareunia
- Dysuria or urine stinging over fissures
- Painful defecation or constipation in children with perianal disease
- Painful erections, phimosis, spraying, weak stream, or obstructive voiding in male genital or meatal disease
- Asymptomatic white plaques discovered on exam[1][5][12]
Classic Signs
| Site | Findings |
|---|---|
| Vulva / perineum / perianal skin | Porcelain-white plaques, "cigarette paper" atrophy, fissures, purpura/ecchymoses, figure-eight/hourglass distribution |
| Female architecture | Labia minora resorption, labial fusion, clitoral phimosis, introital narrowing, posterior fourchette fissures |
| Penis / foreskin / glans | White sclerotic plaques, phimotic ring, adhesions, glans atrophy, coronal sulcus obliteration, meatal stenosis |
| Urethra | Meatal stenosis, fossa navicularis disease, penile urethral stricture, panurethral extension in severe cases |
| Extragenital skin | Ivory-white plaques on trunk, breasts, thighs, or other sites; often less symptomatic |
In pediatric girls, vulvar bruising, fissuring, and bleeding can be mistaken for sexual abuse. LS does not exclude abuse when the history or injury pattern is concerning, but recognizing the characteristic pattern prevents unnecessary harm.[1][60] When concern remains, arrange joint evaluation with a clinician trained in child abuse.[60]
Histopathology
Classic histology includes:
- Epidermal atrophy with flattening or loss of rete ridges
- Hyperkeratosis, sometimes with follicular plugging
- Vacuolar interface dermatitis with basal layer injury
- Homogenized, hyalinized superficial dermal collagen
- Band-like lymphocytic infiltrate beneath the sclerotic zone
- Loss of elastic fibers in the papillary dermis[14][15][16]
Early or hypertrophic LS may be histologically subtle. Minimal useful clues are a vacuolar interface reaction plus any thickness of dermal sclerosis separating inflammation from epithelium.[15][16]
Diagnosis
Diagnosis is usually clinical when classic anogenital plaques, fissuring, and scarring are present. Biopsy is indicated when the diagnosis is uncertain, disease is atypical, there is treatment failure, or malignancy is a concern; for diagnostic confirmation, sample an untreated typical white lesion and tell the pathologist about prior topical treatment if a treatment pause is impractical.[5][17]
Biopsy suspicious areas:
- New pigmentation
- Induration or fixation to underlying tissue
- Hyperkeratotic, verrucous, bleeding, ulcerated, or nonhealing lesion
- Rapid change
- Persistent erosion despite adequate steroid therapy
- Immunocompromised patient
- Any lesion where SCC, differentiated VIN, penile intraepithelial neoplasia, or vulvar intraepithelial neoplasia is plausible[17][18]
Differential Diagnosis
| Diagnosis | Distinguishing features |
|---|---|
| Lichen planus | Erosive vestibular/vaginal involvement, Wickham striae, oral disease |
| Lichen simplex chronicus | Thickened lichenified skin from itch-scratch cycle |
| Vitiligo | Depigmentation without sclerosis, fissuring, or scarring |
| Morphea | Extragenital/localized scleroderma pattern; less mucosal/genital predilection |
| Psoriasis / dermatitis | Erythematous plaques, scale, irritant/contact history |
| Genitourinary syndrome of menopause | Atrophy and dyspareunia without classic white sclerotic plaques |
| VIN / penile intraepithelial neoplasia / SCC | Focal hyperkeratosis, ulcer, induration, pigmentation, bleeding, mass |
Treatment
First-Line: High-Potency Topical Corticosteroids
High-potency topical corticosteroids are first-line therapy for genital LS. Clobetasol propionate 0.05% ointment is the most common induction agent.[5][17][19][20]
Use the linked pharmacology hub for the induction schedule and application guidance; frequency, taper and maintenance should be individualized to disease control. The German S3 guideline (2025; journal publication 2026) continues potent or ultrapotent topical corticosteroids plus emollients as standard treatment and calcineurin inhibitors as second-line therapy.[5] The same guideline strongly recommends against topical estrogen as LS treatment in women; vaginal estrogen may help coexisting genitourinary syndrome of menopause.[5]
Ointment is preferred to cream because it stings less and supports barrier function. Treatment aims to relieve symptoms and limit further scarring.[5][19][21] Observational vulvar LS cohorts associate sustained topical corticosteroid adherence or exposure with lower neoplasia risk.[33][53]
Supervised topical corticosteroid maintenance is generally well tolerated. Explain where and how much to apply, monitor for adverse effects, and address steroid concerns that could lead to uncontrolled inflammation.[5][21]
Topical Calcineurin Inhibitors
Tacrolimus or pimecrolimus can be considered when corticosteroids fail, are not tolerated, or are contraindicated. They may reduce symptoms, but clobetasol is generally superior for clinical remission and improvement in clinical signs.[20][22][23] Use is off-label for LS, and both agents carry an FDA boxed warning that long-term safety is unestablished and that rare malignancies have been reported. The S3 guideline notes that case-control studies, meta-analyses and post-marketing registries do not support this theoretical concern; there is no consensus calcineurin-inhibitor regimen, so individualize duration and reassess ongoing continuous use. Biopsy new hyperkeratotic lesions or newly arising erosions or ulcerations suspicious for neoplasia before treating them as LS.[5] See Topical Calcineurin Inhibitors.[5]
Refractory Disease
Refractory LS should trigger reassessment before escalating:
- Is the diagnosis correct?
- Is medication being applied to the right location and in the right quantity?
- Is there contact dermatitis, candidiasis, GSM, lichen planus, psoriasis, or neuropathic pain?
- Is there hidden dVIN or SCC?
- Is scarring rather than active inflammation driving symptoms?
Specialist options include changing the topical corticosteroid or using an off-label calcineurin inhibitor. Intralesional corticosteroid is an S3 open option for resistant hyperkeratotic plaques in adults, but is strongly recommended against in girls; in boys it is an open option only during foreskin-preserving surgery.[5] Exclude neoplasia by biopsy before injecting a resistant hyperkeratotic plaque. Systemic treatments are reserved for selected refractory disease.[1][5][24]
Laser and PRP: symptoms are not the same as disease control
Potent or ultrapotent topical corticosteroids remain standard care. The German S3 guideline gives adult genital laser and PRP an open recommendation (no recommendation for or against), reflecting uncertainty; it recommends against laser in children and against PRP in girls.[5]
| Evidence | Main finding | Clinical limit |
|---|---|---|
| Mitchell 2021: sham-controlled CO₂ laser RCT | 40 women randomized; 37 with post-treatment biopsies analyzed. No between-group improvement in histological inflammation (p = 0.76) or patient symptom score (p = 0.60) | Subjective improvement occurred in both groups[51] |
| Hecken 2026: low-density fractional microablative CO₂ laser vs clobetasol RCT | 245 women; open-label comparison. At 3 months, median BIP symptom-score change was −8 with laser vs −5 with clobetasol; adjusted difference −2.90 (95% CI −4.64 to −1.15) | Short-term symptom benefit; later patient-chosen crossover[52] |
| Goldstein 2019: PRP vs saline RCT | 30 randomized; 29 treated/completed. No between-group advantage in histological inflammation (p = 0.542) or patient symptom score (p = 0.654) | Protocols and long-term effects remain uncertain[50] |
The trials used different laser regimens, comparators and endpoints.Earlier systematic review also found substantial heterogeneity and weak long-term evidence. Symptom relief alone does not justify stopping anti-inflammatory care or cancer surveillance.[5][51][52][55]
Surgery
Surgery can treat LS-related complications; complete circumcision may clear disease confined to the foreskin.[5][49]
| Setting | Operation |
|---|---|
| Male phimosis from LS | After guideline-conform topical treatment fails, circumcise with complete foreskin removal; send the foreskin for histopathology to confirm LS and exclude precancer, and use topical corticosteroid ointment before and after surgery.[5] |
| Isolated LS-related frenular shortening | In men and boys with isolated frenular shortening after guideline-conform treatment fails, consider frenuloplasty with local triamcinolone injection or follow-up topical corticosteroids (S3 weak, consensus-based suggestion).[5] |
| Male meatal stenosis | After topical treatment fails, the S3 guideline suggests meatoplasty with continuing LS care and suggests against dilation except for palliation .[5] Meatotomy has also been described for LS-related meatal stenosis.[1] |
| LS urethral stricture | Oral mucosal graft urethroplasty (S3 strong, consensus-based recommendation when the stricture causes voiding or sexual problems), staged repair, perineal urethrostomy, or diversion based on extent and patient goals[5] |
| Clitoral phimosis | In adults with symptomatic LS-related phimosis, clitoral hood release / unhooding for trapped keratin, pain, or sexual dysfunction has been described in an eight-woman series.[63] In girls, consider surgery only for selected functional impairment (S3 weak, consensus-based recommendation against routine surgery).[5] See Clitoral Phimosis & Adhesions. |
| Introital stenosis or labial fusion | For persistent introital stenosis impairing voiding or intercourse despite guideline-conform topical corticosteroids, consider adhesiolysis, scar release, perineoplasty, anatomic vulvoplasty or other introital reconstruction (S3 weak, consensus-based suggestion). Before surgery, confirm agreement to topical corticosteroid treatment before and after surgery and provide interdisciplinary counselling with advice from specialized pelvic-floor physiotherapists and sex therapists (S3 strong recommendations). Use postoperative dilation when appropriate.[5] |
| Cancer | Oncologic excision, staging, and multidisciplinary care |
Circumcision can be curative for isolated foreskin disease but not for meatal or urethral involvement.[7][25][26]
Urological and Reconstructive Complications
Male Genital LS
Male LS can involve the foreskin, glans, meatus, fossa navicularis, and anterior urethra. Urologic consequences include:
- Pathologic phimosis
- Glans or preputial adhesions
- Meatal stenosis
- Penile urethral stricture
- Panurethral stricture
- Painful erections
- Spraying, weak stream, retention, recurrent UTI
- Penile SCC risk[7][11][25][27]
LS Urethral Stricture
LS-related strictures are often distal, penile, long, and recurrent. In Calvo 2024’s mixed-etiology urethroplasty cohort (733 patients; median follow-up 12.3 years), increasing stricture length and LS, radiation, and infectious etiologies independently predicted recurrence.[37][29]
Surgical Principles (AUA 2023)
- Avoid genital skin flaps and grafts for LS-related urethral reconstruction. LS may recur in transplanted genital skin; reported recurrence after skin graft/flap augmentation is 50–100% (AUA 2023 strong recommendation for LS-proven urethral stricture[28]; EAU 2026 strong recommendation against genital skin in augmentation penile urethroplasty in males with LS-related strictures[56]). EAU 2026 also weakly suggests single-stage oral mucosa graft urethroplasty when local tissue conditions are favorable.[28][38][56]
- Oral mucosa (buccal or lingual) is preferred. Choose according to availability, donor-site effects and anatomy.[28][29]
- Biopsy any suspicious lesion before reconstruction to exclude squamous cell carcinoma (2–8.6% of male LS patients).[28]
- Penile strictures have high recurrence after endoscopic treatment. Offer urethroplasty at diagnosis ; EAU 2026 strongly recommends against DVIU for penile strictures.[28][56] In a retrospective LS urethral-stricture cohort managed with endoscopy and/or intermittent catheterization, with or without intraurethral steroids, 29/111 (26.1%) required reconstruction or a chronic catheter at median 68.5 months of follow-up.[61]
- For meatal or fossa-navicularis strictures, extended meatotomy with high-dose topical steroids may reduce recurrence.[28]
One-Stage BMG Urethroplasty in LS — Pooled Outcomes
Kurtzman 2021 meta-analysis (n = 625 LS patients undergoing one-stage BMG urethroplasty):[39]
- Overall pooled stricture recurrence 10% (95% CI 6–14%).[39]
- In studies with ≥24 months of follow-up, pooled stricture recurrence was 18%.[39]
- Across all studies there was no significant LS versus non-LS difference (p = 0.36); the long-term subset had higher LS recurrence (OR 1.83, p = 0.05).[39]
- Among patients with penile urethral involvement, studies using penile invagination had lower pooled recurrence than those using a penile skin incision (p = 0.004), a between-study association[39]
Esperto 2022 SR (all included studies at high risk of bias): single-stage OMGU stricture-free rate 88% versus 60% staged OMGU at mean 66.5 mo in the one available comparative study (p = 0.05); single-arm studies reported 65-100%.[40]
Kulkarni vs Asopa in LS
Wan 2023 was a retrospective comparison (42 Asopa, 35 Kulkarni); treatment selection and confounding limit claims of superiority:[41]
- No difference in stricture recurrence (p = 0.724)
- Asopa had significantly lower postoperative meatal stenosis (p = 0.020)
- The composite of urethral restricture or meatal stenosis favored Asopa on the unadjusted recurrence-free curve (p = 0.016); procedure type was not an independent predictor in multivariable analysis.[41]
- In this retrospective comparison, diabetes (p = 0.003), smoking (p = 0.019), antiplatelet or anticoagulant therapy (p = 0.020), coronary disease (p < 0.001), and stricture length (p = 0.028) were associated with complications.[41]
Two-Stage BMG — When One Stage Isn't Enough
- Patel 2016 (n = 79 LS). One-stage BMG success 75%; among 37 patients planned for two-stage, 24% had recurrence or recurrent LS in the first-stage graft before tubularization.[42]
- Palminteri 2022 (35 multistage BMG patients; 25 with follow-up). Among those followed, 20/25 (80%) needed no further treatment for stricture recurrence at median 134 months; a treatment course shorter than 12 months was associated with failure in this small cohort.[43]
- Levine 2007. One-stage 50% versus two-stage 80% in LS (p = 0.28, small sample).[44]
- Figler 2018 and Verla 2019. Staged BMG urethroplasty (first-stage marsupialization and grafting, followed by tubularization) has been described for complex LS and failed hypospadias repair when single-stage reconstruction is unsuitable.[38][45] EAU 2026 weakly recommends an interval of at least four to six months before the second stage when the first-stage result is satisfactory, and weakly recommends warning that more than two stages may be needed.[56]
Perineal Urethrostomy — Durable Option in Complex LS
- Patel 2016. PU success 93% (14 patients) versus 75% one-stage BMG (20 patients) in a retrospective single-center LS series.[42]
- Fuchs 2018. In complex anterior strictures of all etiologies (LS in 22% of PU patients), PU use rose from 4.3% to 38.7% over a decade; 94.8% needed no further operative management versus 78.5% after BMG and 78.2% after skin flap (p = 0.003), despite older PU patients with longer strictures and more LS.[46]
- Klemm 2024. In 76 patients with complex strictures (not LS-specific; 55% iatrogenic), PU retreatment-free survival was 84% at median 55 mo, with high satisfaction (median ICIQ-satisfaction score 21 of 24).[47]
- Zhao 2025 meta-analysis. PU versus urethroplasty in complex strictures: no significant difference in success rates (RR 0.93, 95% CI 0.84–1.03, p = 0.15).[48]
AUA 2023 states that surgeons may offer PU as a long-term alternative to urethroplasty and should offer it to patients at high risk of reconstruction failure , and lists extensive LS, numerous failed urethroplasties and medical comorbidities among reasons for PU; the SIU/ICUD consultation advises considering PU when LS involves the full length of the urethra.[28][49]
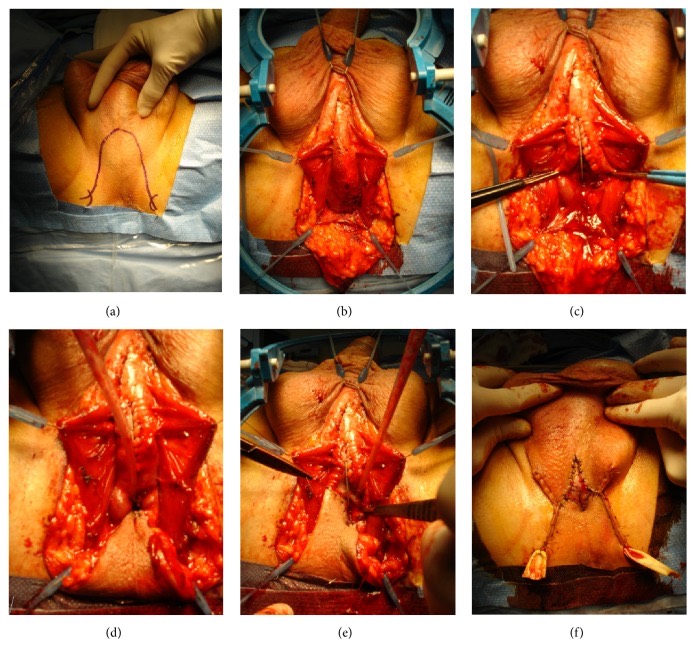
Blandy perineal urethrostomy. (a) Inverted-U perineal incision to raise the Blandy flap. (b) The mobilized flap with the bulbar urethra exposed. (c) The strictured urethra opened until patent proximal urethra is reached. (d) The flap tip sutured to the deepest point of the opened urethra. (e) The flap edges sutured to the urethral edges. (f) The completed perineostomy. From Verla W, et al. Biomed Res Int. 2019;2019:9046430, Figure 13 (CC BY 4.0).[38]
LS Decision Framework
A nine-center retrospective cohort of 231 selected men with LS-related penile strictures found five-year stricture-free estimates of 82% after one-stage oral-mucosa repair (127 men), 76% after staged repair (44 men), and 75% after perineal urethrostomy (60 men; p = 0.6); median follow-up among recurrence-free men was 53 months, and BMI ≥35 was associated with recurrence on Cox regression (HR 2.31, 95% CI 1.28–4.17).[62] It excluded meatal strictures <2 cm, bulbar involvement, and panurethral strictures >10 cm.[62]
| Approach | Best candidates | Success | Key caveat |
|---|---|---|---|
| One-stage BMG (Kulkarni invagination) | Penile / panurethral LS with a usable urethral plate and favorable local tissue | The meta-analysis did not estimate Kulkarni-specific success: pooled recurrence across one-stage BMG methods was 10% overall and 18% in studies with ≥24 months of follow-up.[39] | The invagination association was between studies, without randomization; adverse tissue may favor staging |
| One-stage BMG (Asopa dorsal inlay) | Penile LS | Urethral restricture occurred in 4/42 Asopa and 5/35 Kulkarni patients (p = 0.724) at median 18 months.[41] | Lower meatal stenosis in one retrospective comparison; individualize selection |
| Two-stage BMG | Complex LS, adverse local tissue, circumferential disease, failed prior repair | Reported staged oral-mucosa graft success 60–79% across studies.[56] | In one LS cohort, 9/37 (24%) planned for two-stage BMG had stricture recurrence or recurrent LS in the first-stage graft; stage timing depends on healing and tissue stability.[42] |
| Perineal urethrostomy | Panurethral LS, elderly / comorbid, multiple prior failures | 93% success in one 14-man LS series; in mixed-etiology cohorts, 94.8% needed no further operative management and 84% were retreatment-free at median 55 mo.[42][46][47] | EAU groups LS with trauma and infection among etiologies with poorer PU outcomes (36.7–67% patency failure at median 62 months in cited series).[56] Discuss PU as an alternative, including stomal failure or revision, according to anatomy, prior repair and patient goals. |
Repair extent can also be tailored to the functional segment rather than the full radiographic narrowing: when the distal urethra is the principal tight segment and the remaining urethra appears LS-free and calibrates adequately, only the distal segment may be repaired; when extensive narrowing persists but the proximal bulb and membranous urethra remain open and LS-free, perineal urethrostomy may be favored over panurethral reconstruction.[57]
For full anatomic technique detail of the named procedures, see Kulkarni One-Stage Urethroplasty, Asopa Dorsal Inlay, Johanson Two-Stage Urethroplasty, and Blandy Perineal Urethrostomy. For the staging framework that maps LS into the surgical-decision tree, see the LSE staging system.
Female Urologic Complications
Female LS can contribute to dysuria, urine stinging, introital stenosis, dyspareunia, clitoral phimosis, recurrent fissuring, and rarely urethral narrowing.[28] When female voiding symptoms coexist with LS, assess for urethral stricture, pelvic floor dysfunction, GSM, recurrent UTI, and pain syndromes.[28]
Malignancy Risk
LS increases risk of anogenital squamous cell carcinoma. In women, the main pathway is HPV-independent vulvar carcinogenesis through differentiated VIN and p53-abnormal lesions. In men, LS is associated with increased penile SCC risk.[9][18][30][31]
Practical risk framing:
- Absolute SCC risk in women with LS ranged from 0.21% to 3.88% across studies in a systematic review (0-0.91% in men).[18] A Dutch registry cohort reported 20-year cumulative vulvar SCC incidence of 6.7%; 10-year incidence was 2.8% without concurrent VIN versus 18.8% with concurrent VIN and increased with age at LS diagnosis (1.8% under 50, 3% at 50–70, 5.9% at 70 or older).[30] The S3 guideline puts actual anogenital carcinoma risk below 5%.[5][18][30]
- Danish data show increased risk of vulvar high-grade squamous precancer (SIR 8.5) and SCC (SIR 16.2) in biopsy-verified vulvar LS.[9]
- Swedish registry data show increased odds of vulvar cancer (OR 8.3) and penile cancer (OR 8.9) among patients with LS.[6]
- Male absolute penile cancer risk is low, but relative risk is increased: among 10,592 Danish men with histologically verified penile LS and no previous or concurrent cancer, cumulative penile SCC incidence was 0.4% at 10 years, 1.1% at 20 years, and 1.3% at 30 years; the overall SIR was 15.5, with higher point estimates after longer follow-up and diagnosis before age 40.[32] The AUA guideline cites male SCC rates of 2–8.6% in reported series, higher than the 0–0.91% range across male studies in the systematic review; these estimates come from different study populations.[28][18][32] NCCN cites a 2–9% risk of penile carcinoma in patients with LS.[59]
- Persistent inflammation, undertreatment, older age, long disease duration, and coexistent dVIN raise concern.[18][30][33]
Long-term topical corticosteroid adherence may reduce malignant transformation risk by suppressing inflammation. In Lee 2015 (507 women, mean 4.7 years), none of the 357 adherent women developed VIN or SCC versus 7 (4.7%) of 150 partially adherent women, an observational, single-center comparison.[5][33] Adams 2026, a large propensity-matched electronic-record cohort, found an association between clobetasol exposure and lower vulvar malignancy risk versus matched corticosteroid-naïve controls at 2 years (RR 0.62, 95% CI 0.42–0.94).[53] Calcineurin-inhibitor exposure was not associated with increased malignancy in that study.[53]
Pediatric LS
Girls
Symptoms include vulvar itching, soreness, dysuria, constipation from painful fissures, bleeding, and perianal discomfort. Findings can mimic trauma or sexual abuse, especially bruising, fissures, and bleeding.[1][13][34]
Treatment is still topical corticosteroid based. Pediatric series support ultrapotent topical corticosteroids with good symptom response and low serious adverse-event rates when properly supervised.[34][35][36]
Boys
Male pediatric LS commonly presents as BXO with pathologic phimosis, foreskin whitening, fissuring, ballooning, glans involvement, or meatal stenosis. Topical steroids may help early disease, but circumcision is often definitive for foreskin-limited LS and should remove diseased preputial tissue completely.[7][25]
After circumcision for LS, plan postoperative meatal surveillance: in a retrospective review of 250 boys with histologically confirmed LS, 49 (19.6%) required a later meatal procedure (dilation in 25, meatotomy in 24), and only 4 of the 49 boys needing later intervention had undergone a meatal procedure at circumcision.[58] Preoperative topical steroids were associated with a lower rate of later meatal pathology (2 of 49 who needed later surgery vs. 49 of 151 who did not, p<0.05).[58]
Children require follow-up by specialists experienced in pediatric LS because relapse can occur and scarring may not reverse once established.[5]
Surveillance and Long-Term Management
LS is chronic. Management goals are:
- Control itch, pain, fissures, and inflammation
- Preserve vulvar or penile architecture
- Prevent phimosis, meatal stenosis, urethral stricture, and introital stenosis
- Maintain sexual and urinary function
- Detect dVIN, penile or vulvar intraepithelial neoplasia, and SCC early
Follow-up is typically every 3-6 months during induction or unstable disease, then at least annually when stable; many vulvar specialists maintain 6- to 12-month surveillance indefinitely. Biopsy any changing, thickened, ulcerated, bleeding, pigmented, or treatment-resistant lesion.[5][17][19] After LS-related urethroplasty, separately monitor for stricture recurrence: EAU 2026 strongly recommends at least one year of follow-up and weakly recommends cystoscopy at three months plus a risk-adjusted plan using symptoms and flowmetry; consider longer follow-up after penile or substitution repairs.[56]
Patients should be taught lifelong self-examination and shown exactly where to apply medication.
Trial to watch: PEARLS. The 2026 protocol compares twice-weekly proactive topical corticosteroids with treatment as needed for flares in women and girls aged ≥5 with controlled vulvar LS. Target enrollment is 400; flare frequency is assessed over 12 months, with scarring and other outcomes followed to 24 months. The authors report reaching recruitment target in April 2026. Prior VIN or vulvar SCC is excluded.[54]
See Also
- Kulkarni One-Stage Urethroplasty
- Asopa Dorsal Inlay
- Johanson Two-Stage Urethroplasty
- Blandy Perineal Urethrostomy
- Local Skin Flaps for LS Sequelae
- Male Urethral Stricture
- Female Urethral Stricture
- Buried Penis
- Male Urogenital Exam
- High-Potency Topical Corticosteroids
- Buccal Mucosa
- History of Urethral Surgery: Lichen Sclerosus and Urethral Stricture
References
1. De Luca DA, Papara C, Vorobyev A, et al. "Lichen sclerosus: the 2023 update." Frontiers in Medicine. 2023;10:1106318. doi:10.3389/fmed.2023.1106318
2. Powell JJ, Wojnarowska F. "Lichen sclerosus." Lancet. 1999;353(9166):1777-1783. doi:10.1016/S0140-6736(98)08228-2
3. Kirtschig G. "Lichen sclerosus-presentation, diagnosis and management." Deutsches Arzteblatt International. 2016;113(19):337-343. doi:10.3238/arztebl.2016.0337
4. Ringel NE, Iglesia C. "Common benign chronic vulvar disorders." American Family Physician. 2020;102(9):550-557. PMID 33118795
5. Kirtschig G, Woelber L, Günthert A, et al. "Evidence- and consensus-based guideline on lichen sclerosus." Journal der Deutschen Dermatologischen Gesellschaft. 2026;24(4):566-584. doi:10.1111/ddg.70000
6. Jerkovic Gulin S, Lundin F, Eriksson O, Seifert O. "Lichen sclerosus-incidence and comorbidity: a nationwide Swedish register study." Journal of Clinical Medicine. 2024;13(10):2761. doi:10.3390/jcm13102761
7. Nguyen ATM, Holland AJA. "Balanitis xerotica obliterans: an update for clinicians." European Journal of Pediatrics. 2020;179(1):9-16. doi:10.1007/s00431-019-03516-3
8. Conte S, Mohamed SD, Cohen Y, et al. "Clinical presentations and complications of lichen sclerosus: a systematic review." Journal der Deutschen Dermatologischen Gesellschaft. 2025;23(2):143-149. doi:10.1111/ddg.15606
9. Baandrup L, Hannibal CG, Hertzum-Larsen R, Kjaer SK. "Biopsy-verified vulvar lichen sclerosus: incidence trends 1997-2022 and increased risk of vulvar squamous precancer and squamous cell carcinoma." International Journal of Cancer. 2024;155(3):501-507. doi:10.1002/ijc.34927
10. Tran DA, Tan X, Macri CJ, Goldstein AT, Fu SW. "Lichen sclerosus: an autoimmunopathogenic and genomic enigma with emerging genetic and immune targets." International Journal of Biological Sciences. 2019;15(7):1429-1439. doi:10.7150/ijbs.34613
11. Fergus KB, Lee AW, Baradaran N, et al. "Pathophysiology, clinical manifestations, and treatment of lichen sclerosus: a systematic review." Urology. 2020;135:11-19. doi:10.1016/j.urology.2019.09.034
12. Pérez-López FR, Vieira-Baptista P. "Lichen sclerosus in women: a review." Climacteric. 2017;20(4):339-347. doi:10.1080/13697137.2017.1343295
13. Morrel B, Ewing-Graham PC, van der Avoort IAM, Pasmans SGMA, Damman J. "Structured analysis of histopathological characteristics of vulvar lichen sclerosus in a juvenile population." Human Pathology. 2020;106:23-31. doi:10.1016/j.humpath.2020.09.003
14. Leoni E, Kempf W, Cerroni L. "Lichen sclerosus et atrophicus with histopathologic features mimicking mycosis fungoides: a large series of cases comparing genital with extragenital lichen sclerosus." The American Journal of Surgical Pathology. 2022;46(1):83-88. doi:10.1097/PAS.0000000000001738
15. Yadav D, Agarwal S, Thakur S, Ramam M. "Lymphocyte-peppered sclerotic collagen: an additional histological clue in lichen sclerosus, morphea, and systemic sclerosis." The American Journal of Dermatopathology. 2021;43(12):935-938. doi:10.1097/DAD.0000000000002071
16. Carlson JA, Lamb P, Malfetano J, Ambros RA, Mihm MC. "Clinicopathologic comparison of vulvar and extragenital lichen sclerosus: histologic variants, evolving lesions, and etiology of 141 cases." Modern Pathology. 1998;11(9):844-854. PMID 9758364
17. American College of Obstetricians and Gynecologists. "Diagnosis and management of vulvar skin disorders: ACOG Practice Bulletin Summary, Number 224." Obstetrics & Gynecology. 2020;136(1):222-225. doi:10.1097/AOG.0000000000003945
18. Spekreijse JJ, Streng BMM, Vermeulen RFM, et al. "The risk of developing squamous cell carcinoma in patients with anogenital lichen sclerosis: a systematic review." Gynecologic Oncology. 2020;157(3):671-677. doi:10.1016/j.ygyno.2020.02.020
19. Chi CC, Kirtschig G, Baldo M, et al. "Topical interventions for genital lichen sclerosus." Cochrane Database of Systematic Reviews. 2011;(12):CD008240. doi:10.1002/14651858.CD008240.pub2
20. Funaro D, Lovett A, Leroux N, Powell J. "A double-blind, randomized prospective study evaluating topical clobetasol propionate 0.05% versus topical tacrolimus 0.1% in patients with vulvar lichen sclerosus." Journal of the American Academy of Dermatology. 2014;71(1):84-91. doi:10.1016/j.jaad.2014.02.019
21. Casey GA, Cooper SM, Powell JJ. "Treatment of vulvar lichen sclerosus with topical corticosteroids in children: a study of 72 children." Clinical and Experimental Dermatology. 2015;40(3):289-292. doi:10.1111/ced.12519
22. Pergialiotis V, Bellos I, Biliou EC, et al. "An arm-based network meta-analysis on treatments for vulvar lichen sclerosus and a call for development of core outcome sets." American Journal of Obstetrics and Gynecology. 2020;222(6):542-550.e6. doi:10.1016/j.ajog.2019.10.095
23. Chi CC, Kirtschig G, Baldo M, et al. "Systematic review and meta-analysis of randomized controlled trials on topical interventions for genital lichen sclerosus." Journal of the American Academy of Dermatology. 2012;67(2):305-312. doi:10.1016/j.jaad.2012.02.044
24. Borghi A, Corazza M. "Novel therapeutic approaches and targets for treatment of vulvar lichen sclerosus." Current Pharmaceutical Biotechnology. 2021;22(1):99-114. doi:10.2174/1389201021666200516154310
25. Kravvas G, Shim TN, Doiron PR, et al. "The diagnosis and management of male genital lichen sclerosus: a retrospective review of 301 patients." Journal of the European Academy of Dermatology and Venereology. 2018;32(1):91-95. doi:10.1111/jdv.14488
26. Shieh C, Hakam N, Pearce RJ, et al. "Conservative management of penile and urethral lichen sclerosus: a systematic review." The Journal of Urology. 2024;211(3):354-363. doi:10.1097/JU.0000000000003804
27. Kantere D, Alvergren G, Gillstedt M, Pujol-Calderon F, Tunbäck P. "Clinical features, complications and autoimmunity in male lichen sclerosus." Acta Dermato-Venereologica. 2017;97(3):365-369. doi:10.2340/00015555-2537
28. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. "Urethral stricture disease guideline amendment (2023)." The Journal of Urology. 2023;210(1):64-71. doi:10.1097/JU.0000000000003482
29. Chung ASJ, Suarez OA. "Current treatment of lichen sclerosus and stricture." World Journal of Urology. 2020;38(12):3061-3067. doi:10.1007/s00345-019-03030-z
30. Bleeker MC, Visser PJ, Overbeek LI, van Beurden M, Berkhof J. "Lichen sclerosus: incidence and risk of vulvar squamous cell carcinoma." Cancer Epidemiology, Biomarkers & Prevention. 2016;25(8):1224-1230. doi:10.1158/1055-9965.EPI-16-0019
31. Steinkasserer L, Hachenberg J, Hillemanns P, Jentschke M. "Characterization of patients with vulvar lichen sclerosus and association to vulvar carcinoma: a retrospective single center analysis." Archives of Gynecology and Obstetrics. 2023;307(6):1921-1928. doi:10.1007/s00404-022-06848-y
32. Staerk MG, Kaderly Rasmussen EL, Hannibal CG, et al. "Histologically verified penile lichen sclerosus-incidence in Denmark over 26 years and long-term risk of penile and non-penile cancer." International Journal of Cancer. 2025. doi:10.1002/ijc.35454
33. Lee A, Bradford J, Fischer G. "Long-term management of adult vulvar lichen sclerosus: a prospective cohort study of 507 women." JAMA Dermatology. 2015;151(10):1061-1067. doi:10.1001/jamadermatol.2015.0643
34. Nerantzoulis I, Grigoriadis T, Michala L. "Genital lichen sclerosus in childhood and adolescence-a retrospective case series of 15 patients: early diagnosis is crucial to avoid long-term sequelae." European Journal of Pediatrics. 2017;176(10):1429-1432. doi:10.1007/s00431-017-3004-y
35. Boero V, Caia C, Mastrangelo M, et al. "Pediatric vulvar lichen sclerosus: is a one-size-fits-all prolonged induction therapeutic regimen effective? A referral center experience." Journal of Pediatric and Adolescent Gynecology. 2026;39(2):178-183. doi:10.1016/j.jpag.2025.12.005
36. Smith SD, Fischer G. "Childhood onset vulvar lichen sclerosus does not resolve at puberty: a prospective case series." Pediatric Dermatology. 2009;26(6):725-729. doi:10.1111/j.1525-1470.2009.01022.x
37. Calvo CI, Fender K, Hoy N, Rourke K. Affirming long-term outcomes after contemporary urethroplasty: the adverse impact of increasing stricture length, lichen sclerosus, radiation, and infectious strictures. J Urol. 2024;211(3):455-464. doi:10.1097/JU.0000000000003826
38. Verla W, Oosterlinck W, Spinoit AF, Waterloos M. A comprehensive review emphasizing anatomy, etiology, diagnosis, and treatment of male urethral stricture disease. Biomed Res Int. 2019;2019:9046430. doi:10.1155/2019/9046430
39. Kurtzman JT, Blum R, Brandes SB. One-stage buccal mucosal graft urethroplasty for lichen sclerosus-related urethral stricture disease: a systematic review and pooled proportional meta-analysis. J Urol. 2021;206(4):840-853. doi:10.1097/JU.0000000000001870
40. Esperto F, Verla W, Ploumidis A, et al. What is the role of single-stage oral mucosa graft urethroplasty in the surgical management of lichen sclerosus-related stricture disease in men? A systematic review. World J Urol. 2022;40(2):393-408. doi:10.1007/s00345-021-03803-5
41. Wan X, Yao HJ, Xie MK, et al. A comparative study of two single-stage oral mucosal substitution urethroplasty (Kulkarni and Asopa) in the surgical treatments of lichen sclerosus urethral strictures. Asian J Androl. 2023;25(6):719-724. doi:10.4103/aja20236
42. Patel CK, Buckley JC, Zinman LN, Vanni AJ. Outcomes for management of lichen sclerosus urethral strictures by 3 different techniques. Urology. 2016;91:215-21. doi:10.1016/j.urology.2015.11.057
43. Palminteri E, Gobbo A, Preto M, et al. The role of multi-staged urethroplasty in lichen sclerosus penile urethral strictures. J Clin Med. 2022;11(23):6961. doi:10.3390/jcm11236961
44. Levine LA, Strom KH, Lux MM. Buccal mucosa graft urethroplasty for anterior urethral stricture repair: evaluation of the impact of stricture location and lichen sclerosus on surgical outcome. J Urol. 2007;178(5):2011-5. doi:10.1016/j.juro.2007.07.034
45. Figler BD, Gomella A, Hubbard L. Staged urethroplasty for penile urethral strictures from lichen sclerosus and failed hypospadias repair. Urology. 2018;112:222-224. doi:10.1016/j.urology.2017.10.020
46. Fuchs JS, Shakir N, McKibben MJ, et al. Changing trends in reconstruction of complex anterior urethral strictures: from skin flap to perineal urethrostomy. Urology. 2018;122:169-173. doi:10.1016/j.urology.2018.08.009
47. Klemm J, Dahlem R, Schulz RJ, et al. Perineal urethrostomy for complex urethral strictures: long-term patient-reported outcomes from a reconstructive referral center and a scoping literature review. J Urol. 2024;212(5):738-748. doi:10.1097/JU.0000000000004169
48. Zhao X, Li X, Song Y, Guo Q, Wang J. Comparison of success rates between urethroplasty and perineal urethrostomy in the treatment of complex urethral strictures: a meta-analysis. World J Urol. 2025;43(1):327. doi:10.1007/s00345-025-05679-1
49. Stewart L, McCammon K, Metro M, Virasoro R. SIU/ICUD consultation on urethral strictures: anterior urethra — lichen sclerosus. Urology. 2014;83(3 Suppl):S27-30. doi:10.1016/j.urology.2013.09.013
50. Goldstein AT, Mitchell L, Govind V, Heller D. "A randomized double-blind placebo-controlled trial of autologous platelet-rich plasma intradermal injections for the treatment of vulvar lichen sclerosus." J Am Acad Dermatol. 2019;80(6):1788–1789. doi:10.1016/j.jaad.2018.12.060.
51. Mitchell L, Goldstein AT, Heller D, et al. "Fractionated carbon dioxide laser for the treatment of vulvar lichen sclerosus: a randomized controlled trial." Obstet Gynecol. 2021;137(6):979–987. doi:10.1097/AOG.0000000000004409.
52. Hecken JM, Shoham I, Tempfer CB, Rezniczek GA. "Laser treatment compared with topical clobetasol for lichen sclerosus: a randomized controlled trial." Obstet Gynecol. 2026;148(4):451–461. doi:10.1097/AOG.0000000000006326.
53. Adams PE, Vikram EP, Curman P, Kraus CN, Amber KT. "Topical therapy and vulvar malignancy risk in lichen sclerosus: a large propensity-matched study." Am J Obstet Gynecol. 2026;234(5):1402–1415. doi:10.1016/j.ajog.2025.12.043.
54. Simpson RC, Griffin T, Sach T, et al. "Proactive against reactive therapy for the prevention of lichen sclerosus exacerbation and progression of disease – a pragmatic, parallel group randomised controlled trial with embedded economic evaluation and process evaluation." NIHR Open Research. 2026;6:51. Study protocol. doi:10.3310/nihropenres.14222.1.
55. Tasker F, Kirby L, Grindlay DJC, et al. "Laser therapy for genital lichen sclerosus: a systematic review of the current evidence base." Skin Health Dis. 2021;1(3):e52. doi:10.1002/ski2.52.
56. European Association of Urology. "EAU Guidelines on Urethral Strictures: Limited Update 2026." sections 3.3.1.b and 6.3.1.e. uroweb.org/guidelines/urethral-strictures.
57. Virasoro R, Jordan GH. Lichen sclerosus. In: Brandes SB, Morey AF, eds. Advanced Male Urethral and Genital Reconstructive Surgery. 2nd ed. Humana Press; 2014:37-49 (editorial comment by Steven B. Brandes, pp. 45-47). doi:10.1007/978-1-4614-7708-2_4
58. Homer L, Buchanan KJ, Nasr B, Losty PD, Corbett HJ. "Meatal stenosis in boys following circumcision for lichen sclerosus (balanitis xerotica obliterans)." J Urol. 2014;192(6):1784–1788. doi:10.1016/j.juro.2014.06.077
59. National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Penile Cancer. Version 2.2026. June 5, 2026.
60. Simms-Cendan J, Hoover K, Marathe K, Tyler K. "NASPAG Clinical Opinion: Diagnosis and Management of Lichen Sclerosis in Pediatric and Adolescent Patients." J Pediatr Adolesc Gynecol. 2022;35(2):112-120. doi:10.1016/j.jpag.2021.09.008
61. Saltman AJ, Callegari M, Rizvi TZ, Vanni AJ. "Long-term Outcomes of Conservative Management for Lichen Sclerosus Urethral Stricture Disease." Urology. 2025;202:110-116. doi:10.1016/j.urology.2025.05.004
62. Hengel R, Vanni A, Erickson B, et al. "Multi-Institutional Analysis of Surgery for Lichen Sclerosus-Induced Penile Urethral Stricture: Establishing Single-Stage Urethroplasty as a Primary Treatment Option." J Urol. 2025;213(5):628-637. doi:10.1097/JU.0000000000004434
63. Goldstein AT, Burrows LJ. "Surgical treatment of clitoral phimosis caused by lichen sclerosus." Am J Obstet Gynecol. 2007;196(2):126.e1-126.e4. doi:10.1016/j.ajog.2006.08.023