Müllerian Anomalies & Vaginal Agenesis
Müllerian anomalies encompass congenital defects of the female reproductive tract arising from abnormal formation, fusion, or resorption of the paramesonephric (Müllerian) ducts. In a pooled review of congenital uterine anomalies, a subset of Müllerian anomalies, prevalence was 5.5% in unselected women, 8% in infertile women, 13.3% in women with a history of miscarriage, and 24.5% in women with both miscarriage and infertility.[1][38] Vaginal agenesis, most commonly seen in Mayer-Rokitansky-Küster-Hauser (MRKH) syndrome, is managed first-line with nonsurgical vaginal dilation (90–96% anatomic and functional success in well-counseled, emotionally prepared patients), with surgical neovagina creation (McIndoe, Davydov, Vecchietti, bowel vaginoplasty) considered when dilation is unsuccessful or declined after informed counseling.[2]
This article covers congenital neovagina creation alongside Feminizing Genital Reconstruction; both contexts may use skin, peritoneal or bowel lining, with different starting anatomy and follow-up needs. Related gender-affirming atlas pages are Skin Graft Vaginoplasty, Peritoneal Pull-Through Vaginoplasty, and Intestinal Vaginoplasty. For the geometry of vaginal-septum repair, see Z-plasty; for sigmoid-segment selection in bowel vaginoplasty, see Bowel Anatomy.
Embryology of Müllerian Duct Developmen
The Müllerian ducts form the fallopian tubes, uterus and cervix and contribute the uterovaginal canal to vaginal development; urogenital-sinus cells later replace the fetal vaginal epithelium.[57] Normal development involves three sequential phases:[3][4]
- Organogenesis (approximately 6 weeks). Müllerian ducts form as invaginations of the coelomic epithelium lateral to the Wolffian (mesonephric) ducts, regulated by BMP/Pax2 and FGF/Lim1 signaling cascades.[5]
- Fusion (approximately 8–12 weeks). The paired ducts migrate medially and fuse in the midline to form the uterovaginal canal.
- Septal resorption. The fused midline septum undergoes apoptosis, creating a single uterine cavity.
Disruption at any stage produces the spectrum of Müllerian anomalies. Genes implicated include WNT4, PAX2, LHX1, HNF1B, and HOXA gene clusters.[3][6][7] In males, anti-Müllerian hormone (AMH) from Sertoli cells causes Müllerian duct regression; mutations in AMH or AMHR2 cause persistent Müllerian duct syndrome.[8] See also the broader GU Embryology reference.[9]
Classification of Müllerian Anomalies
The ASRM Müllerian Anomalies Classification 2021 (MAC2021) updated the 1988 AFS system, using descriptive terminology rather than numbered categories and incorporating vaginal and cervical anomalies. It added three groups to the AFS categories (longitudinal vaginal septum, transverse vaginal septum and complex anomalies), and some anomalies appear in more than one category, especially the vaginal ones.[10]
| Category | Description | Key Features |
|---|---|---|
| Müllerian agenesis | Absent uterus and cervix with variable hypoplasia of the upper vagina | MRKH syndrome; atrophic uterine remnants may be present, with or without functional endometrium |
| Cervical agenesis | Absent or severely underdeveloped cervix | May cause outflow obstruction despite a functional uterine body |
| Unicornuate uterus | One Müllerian duct fails to develop | ± rudimentary horn (communicating or non-communicating) |
| Uterus didelphys | Complete non-fusion | Two separate uteri, two cervices; ± longitudinal vaginal septum |
| Bicornuate uterus | Partial non-fusion | Two uterine horns; external fundal indentation > 1 cm; cervical anatomy varies |
| Septate uterus | Failed septal resorption | Most common anomaly in high-risk (infertility / pregnancy-loss) groups; arcuate is commonest in unselected women;[38] MAC2021 defines an endometrial septum > 1 cm from the bicornual line with a leading angle < 90°;[10] assess the external contour. MAC2021 allows any imaging technique for the measurement and treats an arcuate uterus as clinically insignificant |
| Longitudinal vaginal septum | Failure of vaginal fusion / resorption | May be obstructing or non-obstructing |
| Transverse vaginal septum | Failure of canalization | Obstructing → hematocolpos at menarche |
| Complex anomalies | Combined elements | Cross-referenced between categories |
Other classification systems include the ESHRE/ESGE system (uterine classes U0–U6: normal, dysmorphic, septate, bicorporeal, hemi-uterus, aplastic, unclassified; cervical and vaginal anomalies classified separately)[39] and the VCUAM system (Vagina, Cervix, Uterus, Adnexa, associated Malformations).[10]
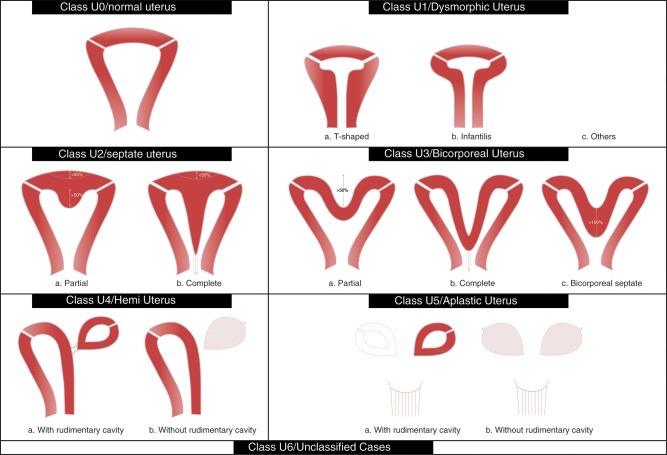
ESHRE/ESGE classification of uterine anomalies. U0 normal uterus; U1 dysmorphic uterus (a, T-shaped; b, infantilis; c, others); U2 septate uterus (a, partial; b, complete), defined by an internal indentation more than 50% of the uterine wall thickness with a straight external contour or an external indentation under 50%; U3 bicorporeal uterus (a, partial; b, complete; c, bicorporeal septate), defined by an external indentation more than 50% of the wall thickness; U4 hemi-uterus (a, with and b, without rudimentary cavity); U5 aplastic uterus (a, with and b, without rudimentary cavity); U6 unclassified cases. From Grimbizis GF, et al. Hum Reprod. 2013;28(8):2032–2044, Figure 2 (CC BY).[39]
For uterine-shape assessment, the 2024 ASRM guideline recommends three-dimensional transvaginal ultrasound, with or without saline infusion, as first-line noninvasive imaging .[51] It recommends offering hysteroscopic septum incision after recurrent miscarriage through shared decision-making (Moderate, B); for infertility without recurrent pregnancy loss, ASRM permits offering incision despite uncertain live-birth benefit, while the 2025 WHO guideline conditionally suggests against resection on low-certainty evidence.[51][54] The 2025 Cochrane review found low-certainty evidence of little or no live-birth difference versus expectant management in one randomized trial of 79 women (OR 0.83, 95% CI 0.32–2.11).[11]
Mayer-Rokitansky-Küster-Hauser (MRKH) Syndrome
Epidemiology and Presentation
MRKH syndrome is the most common cause of vaginal agenesis, with a prevalence of 1 in 4,500–5,000 live female births and the second most common cause of primary amenorrhea (10–15% of cases).[2][12][13][14] Patients have a 46,XX karyotype, normally functioning ovaries, and normal secondary sexual characteristics. The diagnosis is typically made during adolescence when menstruation fails to begin.[2][13]
Classification[13][14]
- Type I (isolated). Uterovaginal aplasia without extragenital anomalies; 78.9% in one South Indian tertiary-center cohort, with proportions varying across cohorts.[12][14]
- Type II (associated). Extragenital anomalies present, including:
- Renal anomalies (15–31% among all MRKH patients across cited cohorts).[12][14] Unilateral renal agenesis, ectopic or pelvic kidney, horseshoe kidney.[12][14][15]
- Skeletal anomalies. One MRKH cohort found abnormalities in 59/184 patients who underwent skeletal imaging (32%); reported defects include Klippel-Feil anomaly and scoliosis.[14]
- MURCS association. Müllerian duct aplasia, renal agenesis, and cervicothoracic somite dysplasia; reported in 16.5% of one South Indian tertiary-center cohort.[12]
- Hearing loss, cardiac defects.[13]
Diagnostic Workup[2]
- Laboratory. Initial evaluation may include serum testosterone, FSH and karyotype; testosterone in the typical male range with a 46,XY karyotype supports complete androgen insensitivity, while FSH helps evaluate delayed pubertal development.[2]
- Imaging. Transabdominal or translabial ultrasound initially; MRI is the gold standard for characterizing Müllerian remnants, endometrial activity, and associated anomalies.[14] Rudimentary Müllerian structures are found in 90% of patients on MRI.[2]
- Evaluation for associated anomalies is necessary; renal imaging is routine (MAC2021 strongly recommends it, and reports a renal anomaly incidence that may approach 40% with Müllerian agenesis, from low-quality case-series literature)[10], and up to 53% have concomitant congenital malformations.[2]
- Laparoscopy is not required for diagnosis but may be useful for pelvic pain evaluation or excision of obstructed uterine horns with active endometrium.
Genetics
The etiology remains largely elusive, though familial clustering suggests genetic causes with autosomal-dominant inheritance, reduced penetrance, and variable expressivity.[6][16] Candidate genes include HNF1B (17q12 deletion), LHX1, WNT4, and PAX2. Loss of HNF1B function in Müllerian duct epithelium has been shown to reproduce the MRKH type II phenotype (uterine hypoplasia and renal anomalies) in mouse models.[3][6]
Obstructive Müllerian Anomalies
Obstruction determines when a patient presents and how urgently she needs surgery. Imperforate hymen, transverse vaginal septum, distal vaginal atresia, cervical atresia, and a non-communicating uterine horn or hemivagina present after menarche with amenorrhea, cyclic or progressive pelvic pain, hematocolpos or hematometra, or a pelvic mass.[40]
- Examination first. Inspection distinguishes imperforate hymen (bulging bluish membrane) from labial adhesions, urogenital sinus, transverse septum and distal vaginal atresia. Pelvic ultrasound is the initial study; MRI defines septal thickness, cervical presence and associated anomalies. Prepubertal imaging can mislead because the uterus is small and unstimulated, so an experienced radiologist helps.[40]
- Timing. ACOG states these anomalies are generally not surgical emergencies, but urinary retention, severe pain, and ascending infection are indications to expedite surgery.[40] Planned surgery after full evaluation gives the best long-term result; ACOG recommends prophylactic antibiotics because obstruction increases infection risk.[40] Transverse septum, distal vaginal atresia and cervical atresia carry a high risk of stenosis and complications, so referral to an experienced center is advised.[40] A scoping review of 41 studies (152 transverse-septum cases) found the published literature sparse and heterogeneous, but concluded that delaying resection until the patient is old enough to participate in postoperative dilation, when pain is otherwise controlled, improves outcomes; of 21 reported cases of postoperative stenosis, 11 occurred without postoperative dilation.[49] Imperforate hymen is the simple end of the spectrum: hymenotomy or hymenectomy.
- Imperforate hymen incision. In a symptomatic newborn with confirmed imperforate hymen and obstructing hydrocolpos, definitive hymenal opening may be needed; a transverse incision has been described to avoid anterior urethral or posterior rectal injury. For an asymptomatic prepubertal patient, confirm the anatomy and defer surgery until pubertal estrogenization; aspiration alone does not provide definitive drainage.[40][50][52] In a pubertal patient, excision of the redundant hymenal tissue under general anesthesia is the usual approach.[50]
- Transverse vaginal septum. A retrospective series of 46 patients found that septa resected vaginally or laparoscopically had low complication rates and good long-term outcomes, while complex septa needed more extensive surgery with a higher complication risk; a thin, perforate septum (< 1 cm) was typically resected vaginally, a mid or high septum < 2 cm with an adequately distended proximal vagina and no other complex pelvic anomaly could be resected laparoscopically, and a septum > 2 cm or an imperforate septum more often needed an abdomino-perineal approach, occasionally with a bridging segment. A temporary vaginal mould after thick-septum excision may help limit scarring, and dilation is recommended after laparoscopic or abdomino-perineal repair, especially when skin flaps are used, though evidence for dilation itself is limited.[45] For a confirmed high septum causing pain, ultrasound-guided decompression of the hematocolpos with a large-bore (12–14-gauge) needle before definitive repair has been described as a selected temporizing measure, not a routine step; viscous blood may need repeated saline irrigation, and the maneuver may increase the risk of upper-genital-tract infection.[43] For a thick septum, ultrasound-guided access with a 14-gauge angiocatheter, a guidewire and a balloon dilator to create an aperture before excision has been described; this technique was reported by a single center.[50]
- Distal vaginal atresia. With a patent upper vagina, a transverse incision at the hymenal ring and dissection through the atretic segment to the upper-vaginal mucosa has been described; a distended upper vagina holding retained menstrual blood can itself provide tissue expansion, and the mobilized vagina is then brought down to the introitus, with perineal skin flaps if needed to bridge the gap. A combined abdominoperineal approach is used when exposure requires it.[50]
- OHVIRA (Herlyn-Werner-Wunderlich). Uterus didelphys with an obstructed hemivagina and ipsilateral renal agenesis or anomaly. In a 2025 meta-analysis of 526 patients, symptom onset averaged 14.5 years and diagnosis 16.4 years (diagnostic delay). Abdominal pain (67%) and dysmenorrhea (64%) were the commonest symptoms, and pelvic endometriosis occurred in 20%.[41] Vaginal septum resection is the standard treatment (83% of reported surgeries), with a hysteroscopic route reported in a smaller group; the pooled studies are case series.[41] Any girl with unilateral renal agenesis should have her Müllerian anatomy considered; apparent agenesis may conceal a dysplastic kidney with an ectopic ureter. In a three-case OHVIRA series, all three patients had persistent vaginal drainage after septum resection despite the kidney not being visualized on imaging.[53] MAC2021 reports ipsilateral renal agenesis or anomaly in up to 95% of obstructed hemivagina, and states that renal imaging is strongly recommended with Müllerian agenesis and with unilateral obstructed vaginal or uterine anomalies.[10] For longitudinal septum excision, leaving a small anterior remnant to protect the bladder has been described, since full excision of the upper septum is often unnecessary; in OHVIRA, removing the entire inferior margin of the septum avoids a residual pocket that retains menstrual blood or cervical secretions and causes intermenstrual bleeding or discharge.[43]
- Cervical agenesis or atresia with a functioning uterus may be considered for uterovaginal continuity reconstruction (including utero-colo-neovaginoplasty below), with less predictable results than septum excision; counseling should cover high risks of stenosis, reoperation and ascending infection, including reported sepsis deaths, and hysterectomy with later vaginal dilation when reconstruction is unsuitable.[40] Laparoscopic uterovaginal anastomosis with a silicone stent to maintain patency has been described; in a 14-patient series in which some patients also underwent McIndoe vaginoplasty (mean follow-up 3.8 years), 92.8% resumed regular menses, one patient required hysterectomy for genital infection and restenosis, and 3 of 5 sexually active patients achieved pregnancy.[46] Longer-term reproductive outcomes need further study.[46]
Management of Vaginal Agenesis
First-Line: Nonsurgical Vaginal Dilation
ACOG recommends primary vaginal dilation as first-line therapy, with reported anatomic and functional success of 90–96% in well-counseled, emotionally prepared patients. ACOG defines functional success by comfortable sexual activity as reported by the patient, with no required vaginal length.[2] Two approaches exist:
- Frank method. Progressive self-dilation using graduated dilators applied to the vaginal dimple for 20–30 minutes daily. In the Danish nationwide cohort, mean vaginal depth at last follow-up was 7.3 cm among 52 patients with follow-up; 21/60 treated with self-dilation (35%) had recorded problems, including low adherence in 15 and urethral dilation in 5 (8%).[17][18] ACOG advises mirror-guided teaching of the vaginal dimple's location and dilator angle.[2] The 90–96% figure is ACOG's estimate for well-counseled, emotionally prepared patients; population-level results vary with counseling and adherence.[2]
- Coital dilation. In a historical, nonrandomized Danish cohort, 20 patients using coital dilation had a mean vaginal depth of 8.7 cm and one recorded complication (5%).[17] It is an option when the patient desires comfortable, consensual penetrative intercourse, never an obligation.[2]
A small comparative study found no significant difference in vaginal length or FSFI.[18]
Second-Line: Surgical Neovagina Creation
Surgery is reserved for patients who fail dilation or prefer surgery after thorough informed consent. ACOG emphasizes that surgery does not eliminate the need for postoperative dilation, and failure to comply with post-surgical dilation can have deleterious effects. Referral to experienced centers is necessary, as the initial procedure is more likely to succeed than revision surgery.[2]
Beyond the McIndoe, Davydov, Vecchietti and bowel techniques detailed below, older and investigational alternatives exist. Williams' vulvovaginoplasty creates a canal from medial labia-majora skin without dissecting the rectovaginal space; the resulting axis is altered, depth is limited, and an elevated perineum can deflect the urinary stream or cause postvoid dribbling. The Creatsas modification lowers the perineal flap to avoid this voiding problem and has been reported in a single-center series of 200 patients with favorable results.[47] A small pilot study implanted autologous tissue-engineered vaginal organs, biodegradable scaffolds seeded with each patient's own epithelial and muscle cells, in four patients with MRKH-related vaginal aplasia; over up to 8 years of follow-up, yearly biopsies showed a trilayered epithelium-muscle structure with no long-term surgical complications, and Female Sexual Function Index scores were in the normal range.[48] The cohort was noncomparative.[48]
McIndoe Vaginoplasty (Modified Abbé-McIndoe)
Technique[2][19]
The historically most common surgical approach:
- Perineal dissection. A space is created between the bladder anteriorly and rectum posteriorly using electrocautery, sharp dissection, and blunt finger dissection to the level of the peritoneal reflection. When the perineum is flat, starting through a 3–4 cm posterior-fourchette incision anterior to the anal sphincter, with a rectal finger guiding the dissection plane, has been described.[43]
- Graft harvest. A split-thickness skin graft (typically 10 × 20 cm) is harvested from the buttock or thigh.
- Mold placement. The graft is secured over a condom-covered rubber-sponge mold, which is inserted into the dissected space and held in place with labial stay sutures.
- Second stage (approximately 14 days). The mold is removed, graft take is assessed, and distal edges are secured. A polyethylene mold replaces the sponge mold for continued healing.
- Postoperative dilation. Lifelong intermittent dilation or regular intercourse is required to maintain vaginal patency.
Modifications
- Micromucosa graft technique. In a seven-patient MRKH series, minced vulvar mucosa provided reported epithelial coverage about 20 times the harvested area with minimal visible scarring; four sexually active patients reported spontaneous lubrication at 6–24 months of follow-up. Buccal mucosa was described as an adjunct when vulvar tissue was insufficient.[20]
- Oxidized cellulose has been used instead of skin graft in a modified Abbé-McIndoe operation. In a 20-patient nonrandomized study, the oxidized-cellulose surgery group (n = 11) and Frank-dilation group (n = 9) did not differ significantly in vaginal length or FSFI at 3–6 months; this did not compare cellulose with a skin graft.[18]
Outcomes[2][17][18]
The historical Danish cohort treated 54 patients with McIndoe vaginoplasty; vaginal depth was measured in 33 with follow-up (median 5.6 years), whereas complications and resurgery were counted among all 54:[17]
- Mean vaginal depth: 7.4 cm (95% CI 6.8–8.1).[17]
- Overall complication rate: 65%.[17]
- Resurgery rate: 33%.[17]
- Complications include graft necrosis, hair-bearing vaginal skin, stenosis, bladder / rectal perforation, and fistulae.
Davydov Vaginoplasty
Technique[2][21]
Originally a three-stage open procedure, now predominantly performed laparoscopically in 8 steps:
- Perineal dissection. The rectovesical space is dissected from below.
- Laparoscopic peritoneal mobilization. The pelvic peritoneum is incised and mobilized as flaps.
- Peritoneal-vaginal anastomosis. The peritoneal flaps are pulled down through the dissected space and sutured to the vaginal introitus.
- Vault reconstruction. The peritoneal dome is closed laparoscopically to create the neovaginal apex.
- Mold placement. An intravaginal dilator is left in place; leaving a soft vaginal stent for approximately 1 week, then removing it and asking the patient to dilate or attempt intercourse to maintain patency, has been described.[44]
The main advantage is the use of autologous pelvic peritoneum as the lining tissue, avoiding the need for skin grafts, bowel segments, or specialized equipment.[21]
Outcomes[15][22][23]
- Mean neovaginal length at 12 months: 8.3 cm (95% CI 8.1–8.6).[22]
- Functional vaginal depth (long-term, 40-year series): 7.8 cm (range 1–13 cm).[15]
- Mean FSFI score: 28.9 (95% CI 26.8–31.1); the mean can mask individual sexual dysfunction.[22]
- Mean operative time: 126 minutes (laparoscopic).[22][23]
- Main reported problems after Davydov peritoneal-graft surgery: granulation tissue (23%) and a tendency toward neovaginal obliteration (12%).[15]
- Neovaginal surface epithelialization after Davydov surgery: 80% at 6 months and complete (100%) at 12 months.[23]
Vecchietti Procedure
A traction-based technique in which an acrylic olive is placed at the vaginal dimple and connected via sutures passed through the rectovesical space to an external traction device on the abdominal wall. Continuous traction (approximately 1 cm/day for 7–10 days) progressively invaginates the vaginal dimple to create a neovagina. Now performed laparoscopically or via single-port robotic approach.[22][28][29][30] Concurrent cystoscopy and a rectal finger during needle passage, with equal tension kept on the two traction sutures, have been described to help keep the sutures out of the bladder and bowel.[43]
- Operative time: 30 minutes in the cited single-port case report[29]; pooled mean 40 minutes (95% CI 35–45) for laparoscopic Vecchietti versus 126 minutes (95% CI 109–143) for laparoscopic Davydov in a 2024 meta-analysis.[22]
- Neovaginal length: 8.7 cm at 12 months.[22]
- Requires postoperative dilation and close follow-up.[30]
Bowel (Intestinal) Vaginoplasty
Uses a pedicled segment of sigmoid colon (most common), ileum, or right colon to line the neovaginal canal.[26][31][32] Advantages include self-lubricating mucosa, reported mean neovaginal length of 11.5 cm in a seven-patient MRKH sigmoid-colpoplasty series and mean vaginal depth of 12.5 cm in a mixed-indication rectosigmoid series, and potentially less intensive dilation requirements.[26][31][32] However, it carries the risks of major abdominal surgery:[25][31]
- Vaginal stenosis (11%; 68/621 across reporting gender-affirming studies).[25]
- Mucorrhea or excessive discharge (approximately 7%).[25]
- Vaginal prolapse (approximately 2.5%; 14/565 across reporting gender-affirming studies).[25]
- Diversion colitis (rare but potentially serious).
- In published gender-affirming intestinal-vaginoplasty series, anastomotic leak, intestinal flap necrosis, bowel obstruction, and intra-abdominal abscess have been reported; some intra-abdominal complications present years later and require prompt assessment.[24][25]
- Overall complication rate: 33% (215 reported complications across 654 gender-affirming intestinal vaginoplasties); return to the operating room approximately 18% (108/608).[25] The preceding 654-vaginoplasty review addresses gender-affirming cases; separately, a 2014 review of 21 retrospective intestinal-vaginoplasty studies (894 patients) imposed no restriction on indication and reported low complication rates, with introital stenosis requiring surgical correction in 4.1% of sigmoid-derived and 1.2% of ileum-derived vaginoplasties.[25][31]
In a 16-patient retrospective series of cervicovaginal or distal vaginal agenesis with functional endometrium, utero-colo-neovaginoplasty restored painless menstrual flow in all 16 at a mean nine years of follow-up. Four developed long-term complications, three needed another operation, and none of the five sexually active patients conceived.[33]
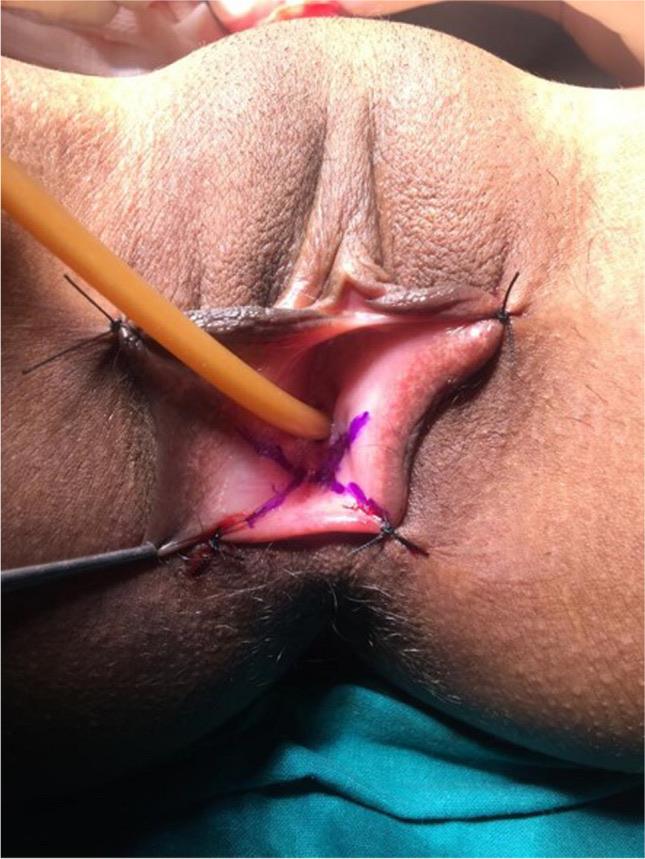
Utero-colo-neovaginoplasty: cruciate incision in the vestibule to develop vaginal mucosal flaps. From Kumar V, et al. Int Urogynecol J. 2024;35(9):1807–1816, Fig. 2 (CC BY).[33]
A 2026 retrospective 12-patient series in transgender women reported a mean neovaginal length of 14.6 cm and postoperative complications in 5/12 patients (41.7%), including anastomotic leak and colon-flap necrosis, after robot-assisted sigmoid vaginoplasty.[24]
Comparison of Surgical Techniques
Outcome ranges are drawn from different cohorts and eras, not randomized head-to-head comparisons. The McIndoe complication / reoperation values are specifically from the 54-patient historical Danish cohort.
| Feature | McIndoe | Davydov (laparoscopic) | Vecchietti (laparoscopic) | Sigmoid Colpoplasty |
|---|---|---|---|---|
| Lining material | Split-thickness skin graft | Pelvic peritoneum | None (traction-based) | Sigmoid colon segment |
| Mean vaginal depth | 7.4 cm[17] | 8.3 cm[22] | 8.7 cm[22] | 11.5 cm (MRKH, n = 7); 12.5 cm (mixed indications, n = 36)[26][32] |
| Operative time | Variable | ~126 min | ~30–40 min | Hours (open or robotic) |
| Complication data | ~65%[17] | Not pooled; granulation tissue 23%, obliteration 12% (single long-term series)[15] | Not pooled; comparable to Davydov in the meta-analysis[22] | 215 reported complication events across 654 gender-affirming intestinal vaginoplasties[25] |
| Resurgery rate | ~33%[17] | Not pooled | Not pooled | ~18% (gender-affirming series)[25] |
| Mean FSFI (MRKH cohorts) | — | 28.9 (95% CI 26.8–31.1)[22] | 27.5 (95% CI 25.0–30.1)[22] | — |
| Key advantage | Well-established, widely known | No graft harvest; minimally invasive | Shorter operative time than Davydov in pooled studies | Self-lubricating; potentially less intensive dilation, with ongoing follow-up |
| Key disadvantage | Donor site morbidity; hair growth; high complication rate | Granulation tissue; obliteration risk | Requires traction device; postop pain | Major abdominal surgery; mucorrhea; prolapse risk |
| References | [2][17][18][19][20] | [15][21][22][23] | [22][29][30] | [25][26][31][32] |
In separate MRKH cohorts pooled in a 2024 meta-analysis, mean neovaginal lengths at 12 months were 8.3 cm after laparoscopic Davydov and 8.7 cm after laparoscopic Vecchietti; pooled mean FSFI scores were 28.9 and 27.5, and pooled mean operative times were 126 and 40 minutes, respectively.[22] Major complications were uncommon in these cohorts.[22] A randomized comparison of 40 patients with congenital vaginal agenesis found shorter operative time and less blood loss after laparoscopic peritoneal vaginoplasty (n = 26) than sigmoid vaginoplasty (n = 14), while neovaginal length, sexual satisfaction, and FSFI did not differ significantly; the sigmoid group reported more abdominal discomfort, vaginal odor, and vaginal contraction during intercourse.[56] A 2025 single-center retrospective comparison (peritoneal n = 20; sigmoid n = 30) reported shorter operative time, earlier return of bowel function, shorter mold use, and higher sexual satisfaction after peritoneal vaginoplasty.[27] Postoperative complications occurred in 3/20 (15%) and 8/30 (26.7%), respectively, without a statistically significant between-group difference.[27]
Complications of Vaginoplasty (All Techniques)
After vaginal dilation or neovagina creation in MRKH, discharge, bleeding, pelvic pain, dyspareunia, or suspected stenosis prompts examination; an abnormal lesion warrants biopsy. For patients without a cervix, ACOG does not recommend routine vaginal cytology, while STI counseling and screening remain appropriate.[2]
ACOG highlights that compared with primary dilation, vaginoplasty complications are much more common and include:[2]
- Bladder or rectal perforation.
- Graft necrosis.
- Hair-bearing vaginal skin (McIndoe).
- Fistulae (vesicovaginal, rectovaginal).
- Neovaginal stenosis / contracture.
- Diversion colitis (bowel vaginoplasty).
- Inflammatory bowel disease (rare).
- Neovaginal malignancy. Published cases after reconstruction for Müllerian anomalies include 18 squamous carcinomas across several methods and 17 adenocarcinomas, 15 after intestinal vaginoplasty.[58]
Reproductive Options
MRKH syndrome involves absolute uterine factor infertility (AUFI). Options include:[2][14]
- Gestational surrogacy. IVF with the patient's own oocytes and a gestational carrier. A systematic review (140 MRKH patients; 125 undergoing 369 IVF cycles) reported 71 newborns; the data are mostly case reports and small series.[34]
- Uterus transplantation (UTx). The first live birth occurred in 2014 (Gothenburg, Sweden). Counseling should cover IVF, donor procurement and recipient surgery, immunosuppression with rejection surveillance, cesarean delivery, and planned graft removal after childbearing.[35][37] In a prospective four-center U.S. cohort of 60 uterus transplants, complications required reoperation in 17/60 recipients (28.3%) and 6/42 living donors (14.3%).[55] The 2026 ISUTx report of activity through 2024 describes 91 transplants entered in the international registry (67 live donors, 24 deceased donors), with 12-month graft survival of 74.7% and 44 singleton live births (live-birth rate 30.3% per embryo transfer after truncating transfer counts at 15).[37] MRKH accounts for 88% of recipients.[37] Preeclampsia occurred in 23% of live-birth pregnancies.[37] Mean gestational age at delivery was 34.5 weeks.[35][36][37]
- Adoption.[2]
The choice of neovagina creation method may impact suitability for subsequent UTx. Vecchietti-based approaches may provide favorable anatomy (sufficient length, natural axis, no prior major abdominal surgery), while bowel vaginoplasty may complicate future UTx.[28]
Pregnancy in Women With Other Müllerian Anomalies
Women with a uterus need obstetric counseling matched to the anomaly. Compared with normal uterine anatomy, a 2026 review of 30 studies found congenital uterine anomalies associated with miscarriage (OR 1.45; 3 studies), preterm birth before 37 weeks (OR 3.74; 5 studies), fetal malpresentation (OR 19.3; 95% CI 6.27–59.24; 2 studies with differing definitions), and cesarean delivery (OR 3.52; 5 studies).[42] Septate uterus tracks with early loss, whereas unicornuate and didelphys uteri carry more preterm birth and malpresentation. The authors advise treating these pregnancies as high risk with tailored surveillance; mode of delivery follows obstetric indications such as malpresentation.[42] Routine septum resection to improve live birth is not supported by randomized evidence.[11]
Psychosocial Considerations
ACOG recommends:[2]
- All patients should be offered counseling and encouraged to connect with peer support groups.
- Future fertility options should be discussed early to help patients cope with the diagnosis.
- Nonsurgical dilation or surgery begins when the patient expresses a desire to proceed and is emotionally ready; surgery also requires readiness for postoperative dilation.[2]
- Care includes gynecologic management, psychosocial counseling, and discussion of reproductive options according to the patient’s needs.
Key Takeaways
- Müllerian anomalies are a continuum of developmental defects classified by the ASRM MAC2021 system into descriptive categories.[10]
- MRKH syndrome (1:5,000 females) is the most common cause of vaginal agenesis; up to 53% have associated congenital anomalies requiring systematic evaluation.[2]
- Nonsurgical dilation remains first-line (90–96% anatomic and functional success reported in well-counseled, emotionally prepared patients); surgery is an option after failure or informed preference.[2]
- Among surgical options, no single technique has demonstrated clear superiority; the choice depends on surgeon expertise, patient anatomy, and patient preference.[2][22]
- Uterus transplantation has emerged as a viable fertility treatment, with 44 live births in the ISUTx registry report through 2024; the registry is self-reported and does not include every center.[37]
- For the obstructive transverse vaginal septum, repair depends on septal level, thickness and available tissue; double-opposing Z-plasty is one reconstructive option; see Z-plasty.
See Also
- Skin Graft Vaginoplasty: operative analogue of the McIndoe neovagina
- Peritoneal Pull-Through Vaginoplasty: operative analogue of the Davydov technique
- Intestinal Vaginoplasty: operative analogue of sigmoid colpoplasty
- Mañero Vaginal Mucosal Graft
- Vulvar Reconstruction (atlas / database)
- Feminizing Genital Reconstruction
- Z-plasty
References
1. Bortoletto P, Romanski PA, Pfeifer SM. "Müllerian Anomalies: Presentation, Diagnosis, and Counseling." Obstet Gynecol. 2024;143(3):369–377. doi:10.1097/AOG.0000000000005469
2. American College of Obstetricians and Gynecologists. "Müllerian Agenesis: Diagnosis, Management, and Treatment." Committee Opinion No. 728. 2018. Guideline.
3. MacLaughlin DT, Donahoe PK. "Sex Determination and Differentiation." N Engl J Med. 2004;350(4):367–378. doi:10.1056/NEJMra022784
4. Robbins JB, Broadwell C, Chow LC, Parry JP, Sadowski EA. "Müllerian Duct Anomalies: Embryological Development, Classification, and MRI Assessment." J Magn Reson Imaging. 2015;41(1):1–12. doi:10.1002/jmri.24771
5. Atsuta Y, Takahashi Y. "Early Formation of the Müllerian Duct Is Regulated by Sequential Actions of BMP/Pax2 and FGF/Lim1 Signaling." Development. 2016;143(19):3549–3559. doi:10.1242/dev.137067
6. Thomson E, Tran M, Robevska G, et al. "Functional Genomics Analysis Identifies Loss of HNF1B Function as a Cause of Mayer-Rokitansky-Küster-Hauser Syndrome." Hum Mol Genet. 2023;32(6):1032–1047. doi:10.1093/hmg/ddac262
7. Venkata VD, Jamaluddin MFB, Goad J, et al. "Development and Characterization of Human Fetal Female Reproductive Tract Organoids to Understand Müllerian Duct Anomalies." Proc Natl Acad Sci U S A. 2022;119(30):e2118054119. doi:10.1073/pnas.2118054119
8. National Library of Medicine. "Persistent Müllerian Duct Syndrome." MedlinePlus Genetics.
9. Johnston A, Eylert MF, Amer T, et al. "Embryology for the Urologist." Chapter 3.
10. Pfeifer SM, Attaran M, Goldstein J, et al. "ASRM Müllerian Anomalies Classification 2021." Fertil Steril. 2021;116(5):1238–1252. doi:10.1016/j.fertnstert.2021.09.025
11. Joosse MI, Kostova EB, Rikken JF, et al. "Septum Resection for Women of Reproductive Age With a Septate Uterus." Cochrane Database Syst Rev. 2025;11:CD008576. doi:10.1002/14651858.CD008576.pub5
12. Vency B, Kumari M, Ebenezer ED, Varghese L, Kumari P. "Prevalence, Clinical Profile, and Associated Anomalies With Women With Mayer-Rokitansky-Küster-Hauser Syndrome in a Tertiary Care Center: A Cross-Sectional Study." Int J Gynaecol Obstet. 2026. doi:10.1002/ijgo.70825
13. National Library of Medicine. "Mayer-Rokitansky-Küster-Hauser Syndrome." MedlinePlus Genetics.
14. Herlin MK, Petersen MB, Brännström M. "Mayer-Rokitansky-Küster-Hauser (MRKH) Syndrome: A Comprehensive Update." Orphanet J Rare Dis. 2020;15(1):214. doi:10.1186/s13023-020-01491-9
15. Willemsen WN, Kluivers KB. "Long-Term Results of Vaginal Construction With the Use of Frank Dilation and a Peritoneal Graft (Davydov Procedure) in Patients With Mayer-Rokitansky-Küster Syndrome." Fertil Steril. 2015;103(1):220–227.e1. doi:10.1016/j.fertnstert.2014.10.014
16. Santana González L, Artibani M, Ahmed AA. "Studying Müllerian Duct Anomalies — From Cataloguing Phenotypes to Discovering Causation." Dis Model Mech. 2021;14(6):dmm047977. doi:10.1242/dmm.047977
17. Herlin M, Bay Bjørn AM, Jørgensen LK, Trolle B, Petersen MB. "Treatment of Vaginal Agenesis in Mayer-Rokitansky-Küster-Hauser Syndrome in Denmark: A Nationwide Comparative Study of Anatomical Outcome and Complications." Fertil Steril. 2018;110(4):746–753. doi:10.1016/j.fertnstert.2018.05.015
18. Apfel VR, Takano CC, Marquini GV, et al. "Treatment for Vaginal Agenesis: A Prospective and Comparative Study Between Vaginal Dilation and Surgical Neovaginoplasty." Int J Gynaecol Obstet. 2022;157(3):574–581. doi:10.1002/ijgo.13931
19. Linder BJ, Gebhart JB. "McIndoe Neovagina Creation for the Management of Vaginal Agenesis." Int Urogynecol J. 2021;32(2):453–455. doi:10.1007/s00192-020-04425-y
20. Teng Y, Zhu L, Chong Y, et al. "The Modified McIndoe Technique: A Scar-Free Surgical Approach for Vaginoplasty With an Autologous Micromucosa Graft." Urology. 2019;131:240–244. doi:10.1016/j.urology.2019.05.020
21. Vermel M, Wehr M, Schwaab T, et al. "Surgical Video Tutorial: Treatment of Congenital Vaginal Agenesis: Laparoscopic Modified Davydov in 8 Steps." J Minim Invasive Gynecol. 2021;28(9):1564. doi:10.1016/j.jmig.2021.02.003
22. Martens L, Tannenbaum L, Van Kuijk SMJ, Notten KJB, Kluivers KB. "Laparoscopic Davydov vs Laparoscopic Vecchietti Neovaginoplasty in Women With Mayer-Rokitansky-Küster-Hauser Syndrome: A Systematic Review and Meta-Analysis." Fertil Steril. 2024;121(4):679–692. doi:10.1016/j.fertnstert.2023.12.015
23. Bianchi S, Frontino G, Ciappina N, Restelli E, Fedele L. "Creation of a Neovagina in Rokitansky Syndrome: Comparison Between Two Laparoscopic Techniques." Fertil Steril. 2011;95(3):1098–1100.e1–3. doi:10.1016/j.fertnstert.2010.11.032
24. Kim KH, Kim KH, Hwang NH, et al. "Gender-Affirming Robot-Assisted Sigmoid Vaginoplasty: Outcomes and Complications From a Retrospective Review of 12 Cases." Medicine. 2026;105(9):e47849. doi:10.1097/MD.0000000000047849
25. Robinson IS, Cripps CN, Bluebond-Langner R, Zhao LC. "Operative Management of Complications Following Intestinal Vaginoplasty: A Case Series and Systematic Review." Urology. 2023;180:105–112. doi:10.1016/j.urology.2023.07.005
26. Darai E, Toullalan O, Besse O, Potiron L, Delga P. "Anatomic and Functional Results of Laparoscopic-Perineal Neovagina Construction by Sigmoid Colpoplasty in Women With Rokitansky's Syndrome." Hum Reprod. 2003;18(11):2454–2459. doi:10.1093/humrep/deg443
27. Yinuo L, Zihan L, Xiaorui L, et al. "Comparative Study of Laparoscopic Peritoneal Vaginoplasty Versus Sigmoid Colon Vaginoplasty in the Treatment of Congenital Absence of Vagina." Surg Endosc. 2025. doi:10.1007/s00464-025-11868-1
28. Kölle A, Taran FA, Rall K, et al. "Neovagina Creation Methods and Their Potential Impact on Subsequent Uterus Transplantation: A Review." BJOG. 2019;126(11):1328–1335. doi:10.1111/1471-0528.15888
29. Yang X, Liang J, Li W, et al. "Modified Vecchietti Vaginoplasty Using Self-Made Single-Port Laparoscopy in Mayer-Rokitansky-Küster-Hauser Syndrome." Fertil Steril. 2021;116(1):266–268. doi:10.1016/j.fertnstert.2020.10.001
30. Clay J, Ferrando C, Gallant T, King CR. "Laparoscopic Vecchietti Procedure: Pearls for Success." Fertil Steril. 2024;122(6):1154–1156. doi:10.1016/j.fertnstert.2024.08.349
31. Bouman MB, van Zeijl MC, Buncamper ME, et al. "Intestinal Vaginoplasty Revisited: A Review of Surgical Techniques, Complications, and Sexual Function." J Sex Med. 2014;11(7):1835–1847. doi:10.1111/jsm.12538
32. Kwun Kim S, Hoon Park J, Cheol Lee K, et al. "Long-Term Results in Patients After Rectosigmoid Vaginoplasty." Plast Reconstr Surg. 2003;112(1):143–151. doi:10.1097/01.PRS.0000066169.78208.D4
33. Kumar V, Thotan SP, Prabhu SP, et al. "Long-Term Outcomes of the Restoration of Uterovaginal Continuity and Vaginoplasty — Utero-Colo-Neovaginoplasty — in Cervicovaginal Agenesis Using the Sigmoid Colon." Int Urogynecol J. 2024;35(9):1807–1816. doi:10.1007/s00192-024-05878-1
34. Friedler S, Grin L, Liberti G, et al. "The Reproductive Potential of Patients With Mayer-Rokitansky-Küster-Hauser Syndrome Using Gestational Surrogacy: A Systematic Review." Reprod Biomed Online. 2016;32(1):54–61. doi:10.1016/j.rbmo.2015.09.006
35. American Society for Reproductive Medicine. "Position Statement on Uterus Transplantation: A Committee Opinion." Fertil Steril. 2018;110(4):605–610. doi:10.1016/j.fertnstert.2018.06.017
36. Brännström M, Dahm Kähler P, Greite R, et al. "Uterus Transplantation: A Rapidly Expanding Field." Transplantation. 2018;102(4):569–577. doi:10.1097/TP.0000000000002035
37. Brännström M, Racowsky C, Wiik J, et al. "Second Report of Registry of the International Society of Uterus Transplantation (ISUTx): International Activities 2000–2024." Hum Reprod. 2026;41(4):541–551. doi:10.1093/humrep/deag017
38. Chan YY, Jayaprakasan K, Zamora J, Thornton JG, Raine-Fenning N, Coomarasamy A. "The Prevalence of Congenital Uterine Anomalies in Unselected and High-Risk Populations: A Systematic Review." Hum Reprod Update. 2011;17(6):761–771. doi:10.1093/humupd/dmr028
39. Grimbizis GF, Gordts S, Di Spiezio Sardo A, et al. "The ESHRE/ESGE Consensus on the Classification of Female Genital Tract Congenital Anomalies." Hum Reprod. 2013;28(8):2032–2044. doi:10.1093/humrep/det098
40. American College of Obstetricians and Gynecologists. "Management of Acute Obstructive Uterovaginal Anomalies." Committee Opinion No. 779. Obstet Gynecol. 2019;133(6):e363–e371. doi:10.1097/AOG.0000000000003281
41. Bonetti E, Anderson G, Duranti S, et al. "Clinical Features and Surgical Options of Obstructed Hemivagina and Ipsilateral Renal Agenesis (OHVIRA) Syndrome: A Systematic Review and a Meta-Analysis of Prevalence." Int J Gynaecol Obstet. 2025;171(1):152–164. doi:10.1002/ijgo.70164
42. Fahmo I, Hakizimana T, Kasujja M, et al. "Maternal and Fetal Outcomes in Women With Uterine Congenital Abnormalities: A Systematic Review and Meta-Analysis." Matern Health Neonatol Perinatol. 2026;12(1):35. doi:10.1186/s40748-026-00283-6
43. Gebhart JB, Breech LL, Hurst BS, Eskew AM. "Congenital Vaginal Abnormalities." In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:793–812.
44. Davies MC, Creighton SM. "Neovaginas for Agenesis." In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:558–561.
45. Williams CE, Nakhal RS, Hall-Craggs MA, et al. "Transverse Vaginal Septae: Management and Long-Term Outcomes." BJOG. 2014;121(13):1653–1658. doi:10.1111/1471-0528.12899
46. Kriplani A, Kachhawa G, Awasthi D, Kulshrestha V. "Laparoscopic-Assisted Uterovaginal Anastomosis in Congenital Atresia of Uterine Cervix: Follow-Up Study." J Minim Invasive Gynecol. 2012;19(4):477–484. doi:10.1016/j.jmig.2012.03.017
47. Creatsas G, Deligeoroglou E. "Creatsas Modification of Williams Vaginoplasty for Reconstruction of the Vaginal Aplasia in Mayer-Rokitansky-Küster-Hauser Syndrome Cases." Womens Health (Lond). 2010;6(3):367–375. doi:10.2217/whe.10.13
48. Raya-Rivera AM, Esquiliano D, Fierro-Pastrana R, et al. "Tissue-Engineered Autologous Vaginal Organs in Patients: A Pilot Cohort Study." Lancet. 2014;384(9940):329–336. doi:10.1016/S0140-6736(14)60542-0
49. Brander EPA, Vincent S, McQuillan SK. "Transverse Vaginal Septum Resection: Technique, Timing, and the Utility of Dilation. A Scoping Review of the Literature." J Pediatr Adolesc Gynecol. 2022;35(1):65–72. doi:10.1016/j.jpag.2021.09.002
50. Kaefer M. Management of Abnormalities of the Genitalia in Girls. In: Partin AW, Dmochowski RR, Kavoussi LR, Peters CA, eds. Campbell-Walsh-Wein Urology. 13th ed. Elsevier; 2025:1211-1229.
51. Practice Committee of the American Society for Reproductive Medicine. "Evidence-based diagnosis and treatment for uterine septum: a guideline." Fertil Steril. 2024;122(2):251–265. doi:10.1016/j.fertnstert.2024.02.033
52. American College of Obstetricians and Gynecologists. "Diagnosis and Management of Hymenal Variants: ACOG Committee Opinion, Number 780." Obstet Gynecol. 2019;133(6):e372–e376. doi:10.1097/AOG.0000000000003283
53. Schlomer B, Rodriguez E, Baskin L. "Obstructed hemivagina and ipsilateral renal agenesis (OHVIRA) syndrome should be redefined as ipsilateral renal anomalies: cases of symptomatic atrophic and dysplastic kidney with ectopic ureter to obstructed hemivagina." J Pediatr Urol. 2015;11(2):77.e1–77.e6. doi:10.1016/j.jpurol.2014.12.004
54. World Health Organisation Guideline Development Group for Infertility, Mburu G, Santesso N, et al. "Recommendations from the WHO guideline for the prevention, diagnosis, and treatment of infertility." Hum Reprod. 2026;41(1):25–38. doi:10.1093/humrep/deaf212
55. O'Neill KE, Humphries LA, Rush M, et al. "Surgical, Reproductive, and Child Developmental Outcomes After 10 Years of Uterus Transplantation in the United States." Obstet Gynecol. 2026. doi:10.1097/AOG.0000000000006440
56. Cao L, Wang Y, Li Y, Xu H. "Prospective randomized comparison of laparoscopic peritoneal vaginoplasty with laparoscopic sigmoid vaginoplasty for treating congenital vaginal agenesis." Int Urogynecol J. 2013;24(7):1173–1179. doi:10.1007/s00192-012-1991-9
57. Hülsman CJM, Köhler SE, Morosan-Puopolo G, Hikspoors JPJM, Lamers WH. "The development of the human female reproductive tract: part 2-vagina." Clin Anat. 2026;39(1):112–131. doi:10.1002/ca.70015
58. Fedele F, Bulfoni A, Parazzini F, Busnelli A. "Neovagina creation methods in Müllerian anomalies and risk of malignancy: insights from a systematic review." Arch Gynecol Obstet. 2024;309(3):801–812. doi:10.1007/s00404-023-07086-6