Myofascial Pelvic Pain
Myofascial pelvic pain (MFPP) is a chronic regional pain condition characterized by hyperirritable trigger points within taut bands of lower abdominal wall or pelvic-floor musculature, including the levator ani (puborectalis, pubococcygeus and iliococcygeus), adjacent coccygeus, and obturator internus.[1][3] Across heterogeneous chronic pelvic pain cohorts, myofascial involvement of the lower abdominal wall, pelvic-floor muscles, or both has been reported in 22–94% of cases, depending on case mix and examination methods; pelvic-floor involvement may be missed without a structured pelvic-floor myofascial exam.[1][2][3] In men, EAU 2026 cites muscle tenderness in 51% of men with prostatitis versus 7% of controls, and pelvic floor dysfunction in 92.2% of men attending a tertiary pain center.[45]
For the broader chronic pelvic pain framework (etiology by organ system, UPOINT phenotyping, pelvic congestion, pudendal neuralgia), see Chronic Pelvic Pain. For the bladder-specific phenotype, see IC/PBS. For high-tone pelvic-floor dysfunction, first-line management centers on Pelvic Floor Physical Therapy (down-training, not strengthening).[40]
Pathophysiology and Presentation
Palpation of tender pelvic-floor muscles and myofascial trigger points (MTrPs) may reproduce localized or referred pain in MFPP.[45] It may exist independently or co-occur with endometriosis, IC/BPS, vulvodynia, IBS, dyspareunia or vaginismus, and CP/CPPS in men, with viscero-somatic convergence amplifying both the pelvic-floor and visceral symptom burden.[1][2][4]
Myofascial urinary frequency syndrome describes patients with pelvic-floor myofascial dysfunction and urinary frequency, a persistent need to void regardless of bladder volume, a sensation of incomplete emptying, and pelvic or bladder pressure; the persistent urge differs from the sudden urgency typical of overactive bladder.[5][61]
Typical clinical features:
- Pelvic, perineal, vulvar, or suprapubic pain
- Dyspareunia, post-coital pain, sexual dysfunction
- Urinary frequency, urgency, hesitancy, or incomplete emptying
- Pain with prolonged sitting
- Referred pain to low back, thighs, abdomen, and rectum
Diagnosis
Diagnosis is clinical and exam-based. There is no validated imaging, biomarker, or laboratory test.[6]
Pelvic-floor myofascial examination
AUA 2025 recommends digital transrectal palpation of pelvic-floor muscles in men to identify tenderness suggesting pelvic-floor myalgia .[50]
- Single-digit transvaginal (or transrectal) palpation. Explain the examination's purpose and possible pain exacerbation, obtain consent, and discuss a chaperone; then sweep the levator-ani complex and obturator internus on each side.[45][6]
- Assess for taut bands, trigger points, hypertonicity, and reproduction of the patient's typical pain with focal pressure.
- Clock-face topography. One published vaginal screening protocol palpates the right obturator internus from 9 to 12 o'clock and the left from 12 to 3 o'clock, confirming each by resisted ipsilateral thigh abduction; it then palpates each levator ani belly and along its fibers while recording pain on a 0–10 scale.[52] The ischial spine marks the sacrospinous-ligament attachment, but the pudendal nerve's course varies; do not treat a fixed clock position or distance as its location.[46]
- A myofascial trigger point has been described by four clinical features: a palpable taut band, a highly tender nodule within that band, reproduction of the patient's pain on palpation of the nodule, and pain-limited stretch or restricted range of motion.[47]
- The ACOG Practice Bulletin 218 explicitly directs particular attention to the abdominal and pelvic neuromusculoskeletal exam.[7]
- Grading muscle tone. Pelvic-floor muscle firmness has been described by comparison with the resting compressibility of the examiner's own thenar eminence, with moderate and severe increased firmness compared to the firmness at the thumb-opposition point with the first and fifth digits, respectively.[48] This is not a validated scale or diagnostic cutoff, and no accepted standard defines myofascial trigger points.[48]
Persistency Index
The Persistency Index (Ackerman 2023) is a screening tool to help identify patients who warrant examination for myofascial dysfunction, incorporating the persistent nature of incomplete-emptying sensation, dyspareunia, and age.[5] A score ≥ 7 discriminated myofascial urinary frequency syndrome from other LUTS in a 719-patient validation cohort (AUC 0.74; sensitivity 80%, specificity 61%).[5]
Stepwise Management
ACOG supports multimodal management and the AUA IC/BPS guideline supports manual PT for IC/BPS with pelvic-floor tenderness.[7][8][2] In men with pelvic-floor or abdominopelvic myalgia, AUA 2025 permits individualized internal and external manual physical therapy and EMG biofeedback when pelvic-floor tone is increased .[49] The 2024 high-tone pelvic-floor algorithm is expert Delphi consensus; PFPT is first line in that consensus, and subsequent options require reassessment.[40]
EAU 2026 weakly recommends myofascial treatment as first-line therapy for pelvic floor dysfunction (level 1b, biofeedback as an adjunct level 1a), and strongly recommends biofeedback with muscle exercises for anal pain from an overactive pelvic floor. It weakly recommends actively looking for trigger points in chronic primary pelvic pain, while noting that no accepted standard defines them. EAU also finds it neither supported nor refuted that needling beats placebo, and finds no evidence that manual trigger point techniques beat no treatment. It recommends that physical therapy be delivered by therapists trained in the musculoskeletal, psychological and central nervous system aspects of chronic pain.[45]
| Step | Intervention | Trigger to escalate |
|---|---|---|
| 1 | PFPT, relaxation and a home program | First-line for high-tone pelvic-floor dysfunction; address access barriers with guided home or virtual care[40] |
| 2 | Local-anesthetic TPIs, cognitive behavioral therapy, selected muscle-relaxant trials | Persistent symptoms or inability to tolerate manual therapy; medication evidence is limited |
| 3 | Off-label onabotulinumtoxinA | Selected refractory patients; discuss negative larger RCTs and phenotype-specific uncertainty |
| 4 | Specialist reassessment | Reconsider diagnosis and comorbid pain mechanisms; the consensus reserves SNM mainly for coexisting urgency/frequency |
Avoid unsupervised Kegel strengthening during symptomatic hypertonicity. PFPT initially emphasizes relaxation and down-training; later exercise is individualized to examination findings.[9][7] Opioids are not recommended.[7][2]
I. Pelvic Floor Physical Therapy
PFPT is central to management; a 2024 expert Delphi panel placed it first line for high-tone pelvic-floor dysfunction.[40] A 2025 systematic review of women with chronic pelvic pain without a defined underlying pathology or disease found lower pain intensity with multimodal physical therapy than inert or nonconservative treatment immediately after treatment (7 RCTs, n = 476; SMD −1.69, 95% CI −2.54 to −0.85; high certainty) and at 12–36 weeks after treatment (5 RCTs, n = 381; SMD −1.82, 95% CI −3.13 to −0.52; moderate certainty).[59] Evidence for isolated modalities and other patient phenotypes remains limited.[7][2][9][59]
| Modality | Technique | Goal |
|---|---|---|
| Internal myofascial release | Single-digit transvaginal/transrectal palpation of levator ani and obturator internus with sustained pressure to taut bands and MTrPs; one component of PFPT, for which expert consensus suggests 1–2 sessions per week for 8–12 weeks[40] | Release fascial restrictions, reduce trigger-point irritability |
| Biofeedback (down-training) | Surface or intracavitary EMG with real-time feedback | Train pelvic-floor relaxation, not strength |
| Electrical stimulation | Low-frequency TENS or interferential current, external or intravaginal | Pain modulation, muscle relaxation |
| Pelvic-floor stretching / home program | Reverse Kegels, child's pose, deep squat, diaphragmatic breathing | Sustain in-clinic gains |
Randomized evidence for manual myofascial PT comes from the urologic pelvic pain literature. In the multicenter IC/PBS trial (81 women with pelvic-floor tenderness and symptoms for no more than 3 years; 10 sessions), the global response rate was 59% with myofascial physical therapy versus 26% with global therapeutic massage (p = 0.0012); pain, urgency and frequency and symptom-index scores improved in both arms without a significant between-group difference.[43] The earlier feasibility trial (47 men and women with CP/CPPS or IC/PBS) reported responders of 57% versus 21% (p = 0.03).[44] In the male subgroup, response rates were 64% with myofascial therapy versus 40% with massage (p = 0.39); urinary subscores favored myofascial therapy (p = 0.007).[49] AUA judged the evidence very low certainty because the trial was open-label, small and imbalanced at baseline.[49] The 2022 AUA IC/BPS guideline (Statement 12; Standard, Evidence Strength Grade A) states that appropriate manual physical therapy should be offered to patients with pelvic-floor tenderness when appropriately trained clinicians are available, and that pelvic-floor strengthening such as Kegel exercises should be avoided.[8]
In a 165-woman RCT limited to postpartum pelvic-floor hypertonia, adding myofascial manipulation to lifestyle advice, electrical stimulation, and biofeedback yielded a reported 'total effective rate' of 94.3%, versus 87.0% without manipulation and 37.7% with lifestyle advice alone.[10]
Men with CP/CPPS. Therapist expertise matters: among 82 men with pelvic-floor spasm in one registry, 79.2% treated at a specialized center improved by at least 6 CPSI points, versus 42% treated elsewhere and 11% who declined therapy (specialized center OR 4.23).[62] In an uncontrolled case series, a 6-day intensive program of trigger-point release, self-treatment training and paradoxical relaxation was followed by a 30% lower CPSI in the 116 of 200 men with refractory symptoms who were followed for a median of 6 months; 60% improved by 6 points or more.[63] In a randomized trial of 103 men unresponsive to conventional treatment (76 completed the program), 18 weeks of aerobic exercise improved total CPSI, pain and quality-of-life scores more than a stretching and motion program.[64]
II. Trigger Point Injections (TPIs)
ACOG Practice Bulletin 218 recommends TPIs (Level B) to improve pain and functional ability in myofascial CPP, alone or with other modalities.[7] For female CPP, SOGC Guideline No. 445 considers targeted therapies such as trigger-point injections and nerve blocks in specific clinical circumstances after nonresponse to modalities with stronger evidence (good practice point; low-quality evidence).[58] In Langford's prospective 18-woman series, 13/18 (72%) met the study's composite success definition after the first levator ani trigger-point injection: at least 50% VAS pain reduction plus satisfaction and cure scores of at least 60%.[12] Six of 18 (33%) were pain-free at a mean 3-month follow-up.[12][45] Small heterogeneous studies cannot determine equivalence among injectants.[7][11]
Injectant options
| Injectant | Notes | Evidence |
|---|---|---|
| Local anesthetic (lidocaine, bupivacaine, levobupivacaine, mepivacaine) | Most commonly used; well-studied | Multiple cohorts and RCTs[12][13][14] |
| Local anesthetic + corticosteroid (triamcinolone, betamethasone) | Common in postpartum and refractory MFPP | An underenrolled 2025 postpartum RCT (57/arm; 124/arm planned) found similar VAS scores at six months postpartum (about four months after injection) with levobupivacaine alone and levobupivacaine plus betamethasone; formal noninferiority remains uncertain[13]; ASRA/AAPM guidance favors considering anesthetic alone because routine steroid addition offers little established benefit[15] |
| Magnesium-based formulation | Novel approach | Small underpowered RCT (44 participants; magnesium, lidocaine and waitlist arms) did not establish superiority over lidocaine[11] |
| Normal saline | Mechanical / needling effect | May produce a needling/contextual response[7] |
| OnabotulinumtoxinA | For refractory / repeated-TPI patients | See Section III |
Office-based transvaginal TPI — published protocols
| Protocol | Injectant | Volume per TrP | Delivery |
|---|---|---|---|
| Langford 2007 | 0.25% bupivacaine 10 mL + 2% lidocaine 10 mL + triamcinolone 40 mg / 1 mL | 5 mL per trigger point | 5.5" Iowa-trumpet pudendal needle guide; all but one injection in the office without sedation[12] |
| Leitch 2022 (RCT) | Lidocaine-only or magnesium-containing lidocaine formulation | Per trigger point | Transvaginal, office; 8 sessions over 12 weeks[11] |
| Solano Calvo 2025 (RCT) | Levobupivacaine 5 mg/mL ± betamethasone 3 mg/mL | 2 mL per trigger point | Transvaginal, 5 mm needle depth; hemostasis checked[13] |
| Moya Esteban 2019 | Mepivacaine 2% (8 mL) + betamethasone acetate (2 mL) | 10 mL prepared mixture; do not assume 10 mL per point | Transvaginal injections in 27 postpartum women[14] |
Calculate the total dose across every injection site and any accompanying block, accounting for additive local-anesthetic toxicity, body size and comorbidity. Keep a LAST rescue kit with 20% lipid emulsion accessible, and use the ASRA checklist if systemic toxicity is suspected.[60] Steroid is not routinely required.[15]
Step-by-step technique
- Position: dorsal lithotomy; sedation usually not required.
- Exam: single-digit transvaginal palpation of pubococcygeus, iliococcygeus, coccygeus, and obturator internus bilaterally; identify trigger points by reproduction of the patient's pain.[12][6]
- Needle guidance: Langford used a 5.5" Iowa-trumpet pudendal needle guide, held transvaginally with the index finger directing the needle tip onto the trigger point; a separate botulinum-toxin protocol used a pudendal-block kit with ≈ 1 cm depth of penetration.[12][17]
- Injection: advance into the trigger point under digital guidance; aspirate and inject incrementally with monitoring. Negative aspiration does not exclude intravascular placement. Choose aliquots and the number of sites within the calculated total-dose limit.
- Post-procedure: brief observation; teach pelvic-floor stretching for home use; resume PFPT.[12]
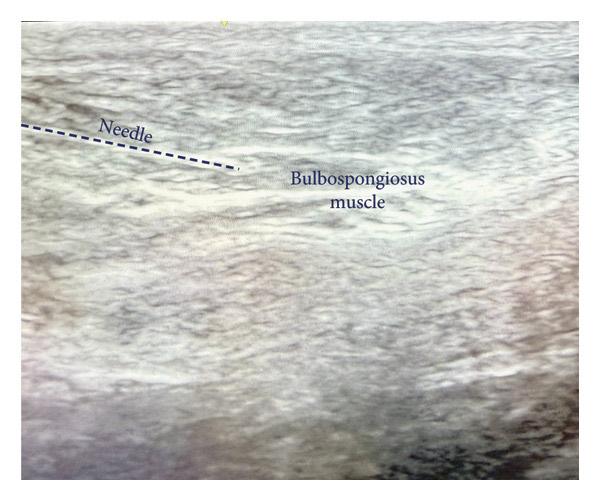
Ultrasound-guided external trigger point injection of the bulbospongiosus muscle in a female patient with myofascial pelvic pain; the dashed line marks the needle. From Smith SE, Patel A. Case Rep Anesthesiol. 2025;2025:7853542, Figure 1 (CC BY 4.0).[51]
Frequency and pairing with PFPT
- Frequency is individualized; the Leitch RCT used 8 sessions over 12 weeks.[11]
- In a retrospective cohort of 87 women assessed 2 weeks after treatment, TPI followed immediately by myofascial-release PFPT was associated with a median VAS reduction of 4 points versus 2 points with TPI alone (p = 0.042); 77% in the combined group improved by ≥ 3 points, versus 45% in the TPI-only group by >3 points (p = 0.008).[16]
III. OnabotulinumtoxinA (Botox)
OnabotulinumtoxinA (BTA) may be discussed for selected refractory patients after PFPT.[17][18] A 2024 meta-analysis of five earlier RCTs in women (n = 329; mean follow-up six months) found no between-group difference in pain, dyspareunia, sexual function, or vaginal manometry.[57] A 2026 expert Delphi panel favored third-line use, typically 100–200 U total (20–50 U per muscle group per side in divided 1–2 mL injection sites), and opposed local-anesthetic test injections as predictors of response; these are technique preferences amid mixed trial results.[53] This is an off-label use; pelvic-floor MFPP is not on the FDA label.[17][54] OnabotulinumtoxinA units are not interchangeable with those of other botulinum toxin products, and the label limits the cumulative adult dose for one or more indications to 400 U in a 3-month interval.[54] Before injection, screen for prior hypersensitivity to any botulinum toxin preparation or formulation component and infection at the proposed sites (labeled contraindications); review neuromuscular disease, aminoglycosides, and muscle relaxants because of possible systemic weakness. Counsel about distant toxin spread, including swallowing or breathing difficulty.[54] For men, AUA 2025 finds the evidence too weak to recommend botulinum toxin for CP/CPPS and notes that pelvic-floor injection is off-label.[49]
Dosing
| Dose | Dilution | Approach | Anesthesia | Note |
|---|---|---|---|---|
| 200 U (published protocol) | 200 U in 20 mL normal saline (10 U/mL) | Transvaginal | Conscious sedation or general | Whitmore 2025 protocol[17]; Dessie RCT[19] |
| 80 U | 80 U in 4 mL (20 U/mL) | Transvaginal | Conscious sedation | Abbott 2006 RCT[20] |
| 50–200 U in Jha's retrospective series | Variable | Transvaginal | Variable | Of 48 treated women, 46 were followed at 3–6 months; no outcome difference by dose was apparent, and optimal dosing remains unestablished[21][22] |
Step-by-step technique (Whitmore 2025)
- Awake exam. Palpate pubococcygeus, iliococcygeus, and obturator internus bilaterally; mark hypertonic or tender targets.[17]
- Sedation. Conscious sedation or general anesthesia; some centers use local-only office protocols.
- Reconstitution. 200 U onabotulinumtoxinA in 20 mL normal saline (10 U/mL).[17]
- Needle. Pudendal-block kit, about 1 cm depth of penetration.
- Injection. Sequentially deliver 1–2 mL (10–20 U) at multiple sites along each affected muscle, distributed across pubococcygeus, iliococcygeus, and obturator internus bilaterally.[17]
- Image-guided alternative. 4D transperineal ultrasound can confirm intramuscular needle placement and visualize fluid tracking along muscle fibers.[23]
Fixed ten-point botulinum toxin type A method (Yang 2026)
In a retrospective comparison of 91 women with pelvic pain and pelvic-floor spasm (64 propensity matched), Yang et al. used a fixed ten-site 100 U pattern at approximately 3–4 cm needle depth and a trigger-point protocol using 100–300 U. Mean Facial Pain Scale–Revised scores at 90 days were 2.53 and 2.38, respectively (p = 0.706).[24]
Concurrent pudendal nerve block — limited benefit
- A 12-year, 182-patient retrospective cohort found no difference in 30-day clinic, ER or message contacts, or in time to repeat injection, between BTA alone and BTA and pudendal block.[18]
- A 96-event subgroup analysis found no difference in PACU pain (VAS 1.7 versus 1.9), PACU time, or opioid requirements.[25]
Onset, duration, retreatment
- Assess response at 2–4 weeks, as suggested by the expert consensus; studies also assess outcomes at 6–12 weeks.[17][26][40]
- Follow-up and retreatment: effects lasting up to 3–6 months have been described; in the Lewis retrospective cohort, the median interval to a second injection was 6 months among those retreated.[17][18]
- Mean number of total injections per patient: 1.6–1.7 in a large cohort; many require retreatment.[18]
Efficacy — mixed
| Study | Design / N | Result |
|---|---|---|
| Spruijt 2025 RCT | n = 94; 100 U vs placebo, then four PFPT sessions | ≥33% pain reduction: 33% vs 20% (p=0.19); global improvement 17% in both groups. Resting activity improved, but pain benefit was not demonstrated.[41] |
| Karp 2026 phase 2 RCT | n = 29 with endometriosis-associated pain and pelvic-floor spasm despite treatment; 100 U vs saline | At one month, self-reported benefit 11/15 (73%) vs 4/14 (29%), p=0.027. Small, selected phenotype; subsequent open injections prevent interpreting one-year outcomes as a sustained randomized comparison.[42] |
| Dessie 2019 RCT | n = 59; 200 U BTA vs saline (all received PFPT from week 4) | Not superior to saline for pain on palpation at 2/4/12 weeks; BTA more likely to report PGI-I global improvement at 4 weeks (p = 0.03)[19] |
| Abbott 2006 RCT | n = 60; 80 U BTA vs saline | Resting pelvic-floor pressure fell 49 → 32 cmH₂O with BTA vs 44 → 39 with placebo; within-arm non-menstrual pelvic pain improved significantly only with BTA, while dyspareunia improved in both arms (VAS 66 → 12 vs 64 → 27); between-arm pain differences were not statistically significant[20] |
| Jha 2021 observational | 48 treated; 46 followed at 3–6 months | 34/46 (74%) reported at least slight global improvement; no dose association was detected across 50–200 U in this nonrandomized series[21] |
| Mooney 2021 pilot | n = 21 | Improvement in dyspareunia, sexual function, QoL; 4 previously apareunic patients regained penetrative intercourse[26] |
| Lewis 2023 retrospective cohort (2010–2022) | n = 182; 63 re-intervention events | Among those receiving a second injection, median interval was 6 months; reported complications included worsening pelvic pain (11.5%) and urinary retention (3.8%).[18] |
Adverse events
| AE | Incidence | Notes |
|---|---|---|
| Constipation | 6.6% in the 182-patient BTA cohort; 4/30 BTA and 2/29 saline in the Dessie RCT at 2 weeks | Most common at 2 weeks in both RCT arms.[17][18][19] |
| Urinary incontinence | Four BTA recipients versus one saline recipient reported incontinence at 2 weeks in the Dessie RCT (30 and 29 randomized, respectively); the abstract's 22% does not state its denominator | Higher doses may increase urinary adverse effects[17][22][19] |
| Urinary retention | 3.8% | [18] |
| Urinary tract infection | 2.7% in the BTA cohort; 9% in the Dessie saline arm[18][19] | — |
| Fecal incontinence | 2.7% in a 182-patient retrospective cohort[18] | A separate review reported transient fecal incontinence or constipation more frequently with higher doses[22] |
| Worsening pelvic pain | 11.5% | [18] |
IV. Compounded Intravaginal Pharmacotherapy
These are off-label compounded vaginal formulations. Compounded drugs are not FDA-approved, and FDA does not review their safety, effectiveness, or quality before marketing.[27][56] They are adjuncts within a multimodal plan (not stand-alone therapies) and the evidence base is dominated by small studies, case reports, and expert opinion.[2][27][9]
Intravaginal diazepam — most studied
- Expert-consensus starting dose: 5–10 mg compounded suppositories.[40]
- Pharmacokinetics (eight healthy volunteers): after one 10-mg vaginal suppository, mean diazepam Cmax was 31 ng/mL at 3.1 hours, bioavailability was 70.5%, and mean terminal half-life was 82 hours; active nordiazepam peaked at 132 hours. The authors reported a lower peak and bioavailability than standard oral use. Repeated vaginal dosing and steady state were not measured; the authors projected accumulation with daily dosing and no steady state for up to one week, and proposed intermittent use before PT or intercourse.[28]
- Evidence is mixed:
- In one retrospective series of 26 women receiving vaginal diazepam alongside PFPT and trigger-point injections, 25/26 reported subjective improvement, but the sexual-pain VAS change was not statistically significant (p = 0.14); perineometry measures of tone improved.[29]
- A triple-blinded RCT (10 mg nightly × 28 days) (21 women) found no improvement in resting EMG, FSFI, or VAS versus placebo as monotherapy.[30]
- In women with vestibulodynia receiving TENS, vaginal diazepam improved dyspareunia and relaxation outcomes, but not the between-group VAS pain outcome.[31]
- A systematic review found two small placebo-controlled trials without significant pain benefit and the limited TENS findings above. The available studies are insufficient to determine benefit from vaginal diazepam as a PFPT adjunct.[32]
- Safety: meaningful systemic absorption and accumulation remain possible; fatigue occurred in 3/8 volunteers. Apply benzodiazepine precautions for sedation, dependence and concurrent opioids or other sedatives.[28]
Intravaginal / topical baclofen
- GABA-B receptor agonist with antispastic and analgesic effects.[33]
- Formulations: topical creams have been reported with palmitoylethanolamide (PEA) or amitriptyline; no established evidence-based vaginal dose exists.
- Evidence. A case report described one 33-year-old woman with vulvodynia and proctodynia whose symptoms decreased by more than 50% and who resumed pain-free intercourse after 3 months of topical baclofen 5% plus oral PEA 400 mg three times daily; the later mechanistic review discusses that same case.[34][35] Amitriptyline-baclofen creams have shown pre-to-post improvement in non-RCT vulvodynia studies.[36] No RCTs of intravaginal baclofen alone for pelvic-floor MFPP.
- Mechanism: acts at peripheral GABA-B receptors on nociceptor terminals and modulates nociceptor or immunocompetent or epithelial cross-talk in vulvar or vaginal mucosa; centrally reduces spasticity.[33][35]
- Safety: formal vaginal-baclofen pharmacokinetic data are lacking, so reduced systemic risk cannot be assumed. Oral baclofen causes sedation and dizziness and can cause withdrawal after abrupt cessation.[33]
Intravaginal / topical ketamine
- NMDA-receptor antagonist; rationale is modulation of peripheral sensitization at nociceptor afferents.[37]
- Formulation: compounded topical combinations are described, but neither an effective vaginal dose nor equivalence between cream concentrations and suppository doses is established.
- Evidence is weak:
- A 2025 Cochrane review found very-low-certainty evidence insufficient to determine whether topical ketamine reduces immediate-term chronic pain versus placebo (MD 1.90 on a 0–100 scale, 95% CI −18.73 to 22.53; one study, 47 participants).[38]
- Small studies of topical ketamine alone show no statistically significant benefit for neuropathic pain.
- Retrospective analyses of topical ketamine combinations (including amitriptyline or lidocaine) for predominantly nonpelvic neuropathic pain reported 40–75% responses, with additional case reports; vaginal MFPP benefit and optimal dosing and combinations remain unclear.[55]
- No RCTs of intravaginal ketamine for MFPP or vulvodynia.
- Safety: psychomimetic effects, unclear long-term cognitive impact, addiction risk. Chronic systemic ketamine causes ketamine cystitis (bladder inflammation or fibrosis), a urologic concern; no cases have been reported with vaginal formulations, but their long-term safety is unknown.[37]
Summary of compounded intravaginal agents
| Agent | Dose evidence | Mechanism | Evidence | Clinical implication |
|---|---|---|---|---|
| Diazepam | 5–10 mg expert starting range; 10 mg tested in trials | GABA-A modulator | Small RCTs and observational studies | Routine benefit unproven; systemic absorption and accumulation[28][30][31][32][40] |
| Baclofen | No established vaginal dose | GABA-B agonist | Case reports / series | Vaginal efficacy and pharmacokinetics uncertain[34][35] |
| Ketamine | No established vaginal dose | NMDA antagonist | Very low certainty | Topical effect uncertain; no basis for routine vaginal combinations[38] |
V. Practical Treatment Ladder
- Start with individualized PFPT, relaxation and a home program. Select oral treatments for a defined comorbid pain phenotype; routine gabapentin for unexplained female CPP is not supported by the GaPP2 trial (see the CPP hub).[7][2][9]
- Persistent focal tenderness or inability to tolerate manual therapy: consider local-anesthetic TPIs. Immediate PFPT may be feasible, but its added benefit rests on retrospective evidence; steroid addition is not routine.[12][15][16]
- Refractory symptoms: reassess diagnosis, comorbidities and goals before considering off-label Botox. Explain the negative larger trial and the positive small endometriosis-specific trial.[40][41][42]
- Compounded vaginal drugs: consider only through shared decisions about uncertain benefit, formulation variability and systemic adverse effects; avoid treating them as a mandatory stage.[28][32][35][38]
- Multidisciplinary reassessment is appropriate for persistent disability.[7] An uncontrolled 186-woman series of nerve blocks, TPIs and PFPT reported improvement.[39]
Key Principles
- Include a structured pelvic-floor examination when evaluating pelvic pain; prevalence varies widely by case mix.[1][2][6]
- Start with relaxation-focused PFPT; avoid unsupervised strengthening during symptomatic hypertonicity.[9][40]
- TPIs can be considered for focal refractory tenderness.[7][11][16]
- Botox is off-label, with mixed randomized evidence and no established optimal dose.[18][22][25][41][42]
- Compounded vaginal diazepam, baclofen and ketamine have uncertain benefit and require attention to systemic exposure and formulation safety.[28][30][32][38]
- Routine opioids are not recommended for MFPP.[7][2]
See Also
- Pelvic Floor Physical Therapy: first-line down-training and manual therapy for hypertonic pelvic floor[40]
- Chronic Pelvic Pain
- IC/PBS
Videos
References
1. Ross V, Detterman C, Hallisey A. Myofascial pelvic pain: an overlooked and treatable cause of chronic pelvic pain. J Midwifery Womens Health. 2021;66(2):148-160. doi:10.1111/jmwh.13224.
2. Namazi G, Chauhan N, Handler S. Myofascial pelvic pain: the forgotten player in chronic pelvic pain. Curr Opin Obstet Gynecol. 2024;36(4):273-281. doi:10.1097/GCO.0000000000000966.
3. Steen JP, Jaiswal KS, Kumbhare D. Myofascial pain syndrome: an update on clinical characteristics, etiopathogenesis, diagnosis, and treatment. Muscle Nerve. 2025;71(5):889-910. doi:10.1002/mus.28377.
4. Lamvu G, Carrillo J, Ouyang C, Rapkin A. Chronic pelvic pain in women: a review. JAMA. 2021;325(23):2381-2391. doi:10.1001/jama.2021.2631.
5. Ackerman AL, Torosis M, Jackson NJ, et al. The Persistency Index: a novel screening tool for identifying myofascial pelvic floor dysfunction in patients seeking care for lower urinary tract symptoms. Am J Obstet Gynecol. 2023;229(6):667.e1-667.e11. doi:10.1016/j.ajog.2023.08.017.
6. Meister MR, Shivakumar N, Sutcliffe S, Spitznagle T, Lowder JL. Physical examination techniques for the assessment of pelvic floor myofascial pain: a systematic review. Am J Obstet Gynecol. 2018;219(5):497.e1-497.e13. doi:10.1016/j.ajog.2018.06.014.
7. Committee on Practice Bulletins—Gynecology. Chronic pelvic pain: ACOG Practice Bulletin, Number 218. Obstet Gynecol. 2020;135(3):e98-e109. doi:10.1097/AOG.0000000000003716.
8. Clemens JQ, Erickson DR, Varela NP, Lai HH. Diagnosis and treatment of interstitial cystitis/bladder pain syndrome. J Urol. 2022;208(1):34-42. doi:10.1097/JU.0000000000002756.
9. Wallace SL, Miller LD, Mishra K. Pelvic floor physical therapy in the treatment of pelvic floor dysfunction in women. Curr Opin Obstet Gynecol. 2019;31(6):485-493. doi:10.1097/GCO.0000000000000584.
10. Xu Y, Li C, Li J. Comparison of the efficacy of three intervention schemes for postpartum pelvic floor muscle hypertonia. Int Urogynecol J. 2025;36(7):1465-1471. doi:10.1007/s00192-025-06128-8.
11. Leitch J, Webb A, Pudwell J, et al. Magnesium-based trigger point infiltrations versus local anaesthetic infiltrations in chronic pelvic myofascial pain: a randomized, double-blind, controlled study. J Obstet Gynaecol Can. 2022;44(8):877-885. doi:10.1016/j.jogc.2022.02.129.
12. Langford CF, Udvari Nagy S, Ghoniem GM. Levator ani trigger point injections: an underutilized treatment for chronic pelvic pain. Neurourol Urodyn. 2007;26(1):59-62. doi:10.1002/nau.20393.
13. Solano Calvo JA, Barreiro García JM, González Hinojosa J, et al. Treatment of postpartum myofascial perineal pain and dyspareunia through local anaesthetic infiltrations compared to anaesthetic and corticosteroids: a randomised double-blind clinical trial. J Clin Med. 2025;14(9):3228. doi:10.3390/jcm14093228.
14. Moya Esteban BM, Solano Calvo JA, Torres Morcillo C, et al. Retrospective case review of combined local mepivacaine and steroid injections into vaginal trigger points for the management of moderate-to-severe perineal pain after childbirth. Arch Gynecol Obstet. 2019;299(2):501-505. doi:10.1007/s00404-018-5000-5.
15. Benzon HT, Elmofty D, Shankar H, et al. Use of corticosteroids for adult chronic pain interventions: sympathetic and peripheral nerve blocks, trigger point injections — guidelines from the ASRA, AAPM, ASIPP, and IPSIS. Reg Anesth Pain Med. 2025. doi:10.1136/rapm-2024-105593.
16. Lewis GK, Chen AH, Craver EC, Crook JE, Carrubba AR. Trigger point injections followed by immediate myofascial release in the treatment of pelvic floor tension myalgia. Arch Gynecol Obstet. 2023;307(4):1027-1035. doi:10.1007/s00404-022-06880-y.
17. Whitmore GT, Tam J, Orlando M. Onabotulinumtoxin A injections for patients with pelvic floor dysfunction. J Minim Invasive Gynecol. 2026;33(3):257. doi:10.1016/j.jmig.2025.07.005.
18. Lewis GK, Carrubba AR, Stanton AP, et al. OnabotulinumtoxinA injections for the treatment of myofascial pelvic pain: 12-year experience at a tertiary care academic center. Gynecol Obstet Invest. 2023;88(1):37-46. doi:10.1159/000528177.
19. Dessie SG, Von Bargen E, Hacker MR, Haviland MJ, Elkadry E. A randomized, double-blind, placebo-controlled trial of onabotulinumtoxin A trigger point injections for myofascial pelvic pain. Am J Obstet Gynecol. 2019;221(5):517.e1-517.e9. doi:10.1016/j.ajog.2019.06.044.
20. Abbott JA, Jarvis SK, Lyons SD, Thomson A, Vancaille TG. Botulinum toxin type A for chronic pain and pelvic floor spasm in women: a randomized controlled trial. Obstet Gynecol. 2006;108(4):915-23. doi:10.1097/01.AOG.0000237100.29870.cc.
21. Jha S, Toozs-Hobson P, Roper JC, et al. Botulinum injections for myofascial pelvic pain. Int Urogynecol J. 2021;32(5):1151-1156. doi:10.1007/s00192-020-04435-w.
22. Karp BI, Tandon H, Vigil D, Stratton P. Methodological approaches to botulinum toxin for the treatment of chronic pelvic pain, vaginismus, and vulvar pain disorders. Int Urogynecol J. 2019;30(7):1071-1081. doi:10.1007/s00192-018-3831-z.
23. Nesbitt-Hawes EM, Dietz HP, Abbott JA. Four-dimensional ultrasound guidance for pelvic floor botulinum toxin-A injection in chronic pelvic pain: a novel technique. Ultrasound Obstet Gynecol. 2018;51(3):396-400. doi:10.1002/uog.17537.
24. Yang J, Ma X, Luo C, et al. The significance of type A botulinum toxin ten-point injection therapy in the treatment of chronic pelvic pain caused by muscle spasms in women. Int Urogynecol J. 2026;37(4):963-972. doi:10.1007/s00192-025-06346-0.
25. Coombs P, Lewis G, Chen AH, Ma Y, Carrubba AR. Does pudendal nerve block improve perioperative pain following onabotulinumtoxinA injection for myofascial pelvic pain? Eur J Obstet Gynecol Reprod Biol. 2025;306:64-68. doi:10.1016/j.ejogrb.2024.12.055.
26. Mooney SS, Readman E, Hiscock RJ, et al. Botulinum toxin A (Botox) injection into muscles of pelvic floor as a treatment for persistent pelvic pain secondary to pelvic floor muscular spasm: a pilot study. Aust N Z J Obstet Gynaecol. 2021;61(5):777-784. doi:10.1111/ajo.13396.
27. Flatow V, Uy-Kroh J, Carey ET, Ascher-Walsh C, Khalil S. Skeletal muscle relaxants for the treatment of myofascial pelvic pain and high tone pelvic floor disorders. Curr Opin Obstet Gynecol. 2023;35(4):311-315. doi:10.1097/GCO.0000000000000894.
28. Larish AM, Dickson RR, Kudgus RA, et al. Vaginal diazepam for nonrelaxing pelvic floor dysfunction: the pharmacokinetic profile. J Sex Med. 2019;16(6):763-766. doi:10.1016/j.jsxm.2019.03.003.
29. Rogalski MJ, Kellogg-Spadt S, Hoffmann AR, Fariello JY, Whitmore KE. Retrospective chart review of vaginal diazepam suppository use in high-tone pelvic floor dysfunction. Int Urogynecol J. 2010;21(7):895-9. doi:10.1007/s00192-009-1075-7.
30. Crisp CC, Vaccaro CM, Estanol MV, et al. Intra-vaginal diazepam for high-tone pelvic floor dysfunction: a randomized placebo-controlled trial. Int Urogynecol J. 2013;24(11):1915-23. doi:10.1007/s00192-013-2108-9.
31. Murina F, Felice R, Di Francesco S, Oneda S. Vaginal diazepam plus transcutaneous electrical nerve stimulation to treat vestibulodynia: a randomized controlled trial. Eur J Obstet Gynecol Reprod Biol. 2018;228:148-153. doi:10.1016/j.ejogrb.2018.06.026.
32. Stone RH, Abousaud M, Abousaud A, Kobak W. A systematic review of intravaginal diazepam for the treatment of pelvic floor hypertonic disorder. J Clin Pharmacol. 2020;60 Suppl 2:S110-S120. doi:10.1002/jcph.1775.
33. Fromm GH. Baclofen as an adjuvant analgesic. J Pain Symptom Manage. 1994;9(8):500-9. doi:10.1016/0885-3924(94)90111-2.
34. Keppel Hesselink JM, Kopsky DJ, Sajben NL. Vulvodynia and proctodynia treated with topical baclofen 5% and palmitoylethanolamide. Arch Gynecol Obstet. 2014;290(2):389-93. doi:10.1007/s00404-014-3218-4.
35. Keppel Hesselink JM, Kopsky DJ, Sajben N. New topical treatment of vulvodynia based on the pathogenetic role of cross talk between nociceptors, immunocompetent cells, and epithelial cells. J Pain Res. 2016;9:757-762. doi:10.2147/JPR.S115407.
36. Schlaeger JM, Glayzer JE, Villegas-Downs M, et al. Evaluation and treatment of vulvodynia: state of the science. J Midwifery Womens Health. 2023;68(1):9-34. doi:10.1111/jmwh.13456.
37. Pickering G, Morel V, Voute M. Managing chronic pain: the ketamine option. CNS Drugs. 2025. doi:10.1007/s40263-025-01234-z.
38. Ferraro MC, Cashin AG, Visser EJ, et al. Ketamine and other NMDA receptor antagonists for chronic pain. Cochrane Database Syst Rev. 2025;8:CD015373. doi:10.1002/14651858.CD015373.pub2.
39. Patil S, Daniel G, Vyas R, et al. Neuromuscular treatment approach for women with chronic pelvic pain syndrome improving pelvic pain and functionality. Neurourol Urodyn. 2022;41(1):220-228. doi:10.1002/nau.24799.
40. Torosis M, Carey E, Christensen K, et al. A treatment algorithm for high-tone pelvic floor dysfunction. Obstet Gynecol. 2024;143(4):595–602. doi:10.1097/AOG.0000000000005536.
41. Spruijt MA, Klerkx WM, Notten K, et al. The efficacy of botulinum toxin A injection in pelvic floor muscles in chronic pelvic pain patients: a double-blinded randomised controlled trial. BJOG. 2025;132(3):297-305. doi:10.1111/1471-0528.17991.
43. FitzGerald MP, Payne CK, Lukacz ES, et al. Randomized multicenter clinical trial of myofascial physical therapy in women with interstitial cystitis/painful bladder syndrome and pelvic floor tenderness. J Urol. 2012;187(6):2113-8. doi:10.1016/j.juro.2012.01.123.
44. Fitzgerald MP, Anderson RU, Potts J, et al. Randomized multicenter feasibility trial of myofascial physical therapy for the treatment of urological chronic pelvic pain syndromes. J Urol. 2013;189(1 Suppl):S75-85. doi:10.1016/j.juro.2012.11.018.
42. Karp BI, Tandon HK, Sinaii N, et al. Botulinum toxin for endometriosis-associated chronic pelvic pain: a randomised, double-masked, parallel, phase 2 trial. EClinicalMedicine. 2026;91:103740. doi:10.1016/j.eclinm.2025.103740.
45. Engeler D, Baranowski AP, Berghmans B, et al. EAU Guidelines on Chronic Pelvic Pain. European Association of Urology; limited update March 2026. Guideline
46. Maldonado PA, Chin K, Garcia AA, Corton MM. Anatomic variations of pudendal nerve within pelvis and pudendal canal: clinical applications. Am J Obstet Gynecol. 2015;213(5):727.e1-6. doi:10.1016/j.ajog.2015.06.009.
47. Pastore EA, Katzman WB. Recognizing myofascial pelvic pain in the female patient with chronic pelvic pain. J Obstet Gynecol Neonatal Nurs. 2012;41(5):680-691. doi:10.1111/j.1552-6909.2012.01404.x.
48. Frawley H, Shelly B, Morin M, et al. An International Continence Society (ICS) report on the terminology for pelvic floor muscle assessment. Neurourol Urodyn. 2021;40(5):1217-1260. doi:10.1002/nau.24658.
49. Lai HH, Pontari MA, Argoff CE, et al. Male Chronic Pelvic Pain: AUA Guideline: Part II Treatment of Chronic Prostatitis/Chronic Pelvic Pain Syndrome. J Urol. 2025;214(2):127-137. doi:10.1097/JU.0000000000004565 Full 2025 guideline
50. Lai HH, Pontari MA, Argoff CE, et al. Male Chronic Pelvic Pain: AUA Guideline: Part I Evaluation and Management Approach. J Urol. 2025;214(2):116-126. doi:10.1097/JU.0000000000004564
51. Smith SE, Patel A. Ultrasound-Guided External Trigger Point Injections for Female Patients With Myofascial Pelvic Pain: A Report of Two Cases. Case Rep Anesthesiol. 2025;2025:7853542. doi:10.1155/cria/7853542
52. Meister MR, Sutcliffe S, Ghetti C, et al. "Development of a standardized, reproducible screening examination for assessment of pelvic floor myofascial pain." Am J Obstet Gynecol. 2019;220(3):255.e1-255.e9. doi:10.1016/j.ajog.2018.11.1106
53. Hufnagel DH, Torosis M, Ackerman AL. "Modified Delphi consensus guidelines for pelvic floor botulinum toxin injection." Urogynecology (Phila). 2026;32(4):312-320. doi:10.1097/SPV.0000000000001841
54. Allergan, Inc. "BOTOX (onabotulinumtoxinA) for injection: US prescribing information." DailyMed. Revised November 2023. Label
55. Sawynok J. "Topical and peripheral ketamine as an analgesic." Anesth Analg. 2014;119(1):170-178. doi:10.1213/ANE.0000000000000246
56. U.S. Food and Drug Administration. "Human Drug Compounding." FDA.
57. Knapman BL, Li FG, Deans R, Nesbitt-Hawes E, Maheux-Lacroix S, Abbott J. "Botulinum Toxin for the Management of Pelvic Floor Tension Myalgia and Persistent Pelvic Pain: A Systematic Review and Meta-analysis." Obstet Gynecol. 2024;143(1):e7-e17. doi:10.1097/AOG.0000000000005388
58. Allaire C, Yong PJ, Bajzak K, et al. "Guideline No. 445: Management of Chronic Pelvic Pain." J Obstet Gynaecol Can. 2024;46(1):102283. doi:10.1016/j.jogc.2023.102283
59. Starzec-Proserpio M, Frawley H, Bø K, Morin M. "Effectiveness of nonpharmacological conservative therapies for chronic pelvic pain in women: a systematic review and meta-analysis." Am J Obstet Gynecol. 2025;232(1):42-71. doi:10.1016/j.ajog.2024.08.006
60. Neal JM, Neal EJ, Weinberg GL. "American Society of Regional Anesthesia and Pain Medicine Local Anesthetic Systemic Toxicity checklist: 2020 version." Reg Anesth Pain Med. 2021;46(1):81-82. doi:10.1136/rapm-2020-101986
61. Ackerman AL, Jackson NJ, Caron AT, Kaufman MR, Routh JC, Lowder JL. "Myofascial urinary frequency syndrome is a novel syndrome of bothersome lower urinary tract symptoms associated with myofascial pelvic floor dysfunction." Sci Rep. 2023;13(1):18412. doi:10.1038/s41598-023-44862-5
62. Polackwich AS, Li J, Shoskes DA. Patients with Pelvic Floor Muscle Spasm Have a Superior Response to Pelvic Floor Physical Therapy at Specialized Centers. J Urol. 2015;194(4):1002-6. doi:10.1016/j.juro.2015.03.130
63. Anderson RU, Wise D, Sawyer T, et al. 6-day intensive treatment protocol for refractory chronic prostatitis/chronic pelvic pain syndrome using myofascial release and paradoxical relaxation training. J Urol. 2011;185(4):1294-9. doi:10.1016/j.juro.2010.11.076
64. Giubilei G, Mondaini N, Minervini A, et al. Physical activity of men with chronic prostatitis/chronic pelvic pain syndrome not satisfied with conventional treatments--could it represent a valid option? The physical activity and male pelvic pain trial: a double-blind, randomized study. J Urol. 2007;177(1):159-65. doi:10.1016/j.juro.2006.08.107