Fecal Incontinence
Fecal incontinence (FI) is involuntary loss of solid or liquid stool; anal incontinence is the broader term that also includes involuntary flatus loss.[1][2]
ACOG recommends nonsurgical treatment as initial management for women with FI except in cases of fistulae or rectal prolapse (Level B); after conservative failure, it lists sacral neuromodulation for women with or without anal sphincter disruption and sphincteroplasty for women with anal sphincter disruption (Level B).[3]
Classification
Classify FI by symptom pattern before ordering tests:[1][2]
| Pattern | Clinical meaning | Common mechanism |
|---|---|---|
| Urgency FI | Leakage preceded by a compelling need to defecate | Loose stool, rectal hypersensitivity, reduced squeeze reserve, external anal sphincter weakness |
| Passive FI | Leakage without awareness | Internal anal sphincter weakness, impaired sensation, neuropathy, overflow |
| Mixed FI | Both urgency and passive leakage | Multifactorial; common in older patients and after OASIS |
| Post-defecatory seepage | Small-volume leakage after an apparently complete bowel movement | Incomplete evacuation, hemorrhoids, rectocele, stool trapping, impaired hygiene mechanics |
Severity depends on frequency, stool consistency, volume, pad use, urgency, and quality-of-life impact. Use a structured scale when tracking response: Wexner / Cleveland Clinic Florida FI score, St Mark's score, or Fecal Incontinence Severity Index. The Pelvic Floor Consortium of the ASCRS, ICS, AUGS, and SUFU recommends combining the St Mark's and Wexner scores as a consensus-based baseline and follow-up assessment, rather than using either alone.[43]
Epidemiology and Impact
Worldwide prevalence in community-dwelling adults is about 7% or less, and ACOG cites 7-15% of community-dwelling women; estimates vary with definition, age, and minimum frequency threshold, and prevalence rises with age and institutionalization.[1][3] Underreporting is the rule. Patients often do not volunteer FI unless asked directly, especially when symptoms are intermittent or limited to staining and seepage.[1][5]
Clinical patterns:
- FI is often multifactorial; sphincter defects, loose stool, urgency, impaired sensation, incomplete evacuation, cognitive impairment, and mobility limitations commonly coexist.
- Women have slightly higher reported prevalence than men, but the sex difference is smaller than clinicians often assume.[1]
- Up to half of nursing-home residents have FI, where immobility, cognition, stool consistency, toileting access, and medications often dominate management.[1]
- FI can be more socially disabling than urinary incontinence and is a driver of isolation, sexual avoidance, skin breakdown, caregiver burden, and institutionalization.[1][3]
Pathophysiology
Continence depends on five interacting systems:[1][2][6]
| System | Continence role | Failure pattern |
|---|---|---|
| Internal anal sphincter (IAS) | Resting tone; passive continence | Passive leakage, seepage, soiling |
| External anal sphincter (EAS) + puborectalis | Voluntary squeeze and anorectal angle control | Urgency leakage, inability to defer defecation |
| Rectal reservoir | Capacity and compliance | Urgency with low rectal volume, radiation/proctitis-related FI |
| Stool consistency / transit | Formed stool is easier to retain than liquid stool | Diarrhea, bile-acid diarrhea, overflow around impaction |
| Neurologic and cognitive control | Sensation, reflexes, mobility, toileting behavior | Passive FI, functional FI, neurogenic bowel |
In prospective physiologic series, most patients have more than one abnormality.
The puborectalis helps maintain an anorectal angle of approximately 90 degrees at rest; its independent contribution to continence remains uncertain.[6]
Etiology and Risk Factors
Bowel disturbance
Loose stool and urgency are often the most powerful modifiable drivers. Diarrhea, rectal urgency, frequent stools, fecal impaction with overflow, irritable bowel syndrome, inflammatory bowel disease, celiac disease, bile-acid diarrhea, metformin, magnesium, antibiotics, and laxative overuse should be addressed before procedural treatment.[1][2][7]
Obstetric and pelvic-floor injury
OASIS is the signature urogynecologic risk factor. ASCRS reports obstetric sphincter injury clinically recognized in about 4–10% of vaginal deliveries, with occult sphincter damage in up to 21–35% of women after vaginal delivery.[4] On anal endosonography six weeks after delivery, 28 of 79 primiparous women (35%) had a sphincter defect, which persisted in all 22 restudied at six months.[55] FI may present decades after delivery, as aging, menopause, neuropathy, prolapse, obesity, and stool changes overwhelm a previously compensated sphincter complex.
Among 2,800 respondents (53%) in a population-based survey of women, rectal urgency was the main FI risk factor (OR 8.3); age was associated with FI (OR 1.3 per decade), while obstetric risk factors for anorectal trauma were not associated with FI.[7]
Among women with obstetric sphincter injury, clinically relevant FI is more common in multiparous women and after instrument-assisted deliveries.[4]
Surgical, anatomic, and neurologic causes
- Anorectal surgery. Fistulotomy, lateral internal sphincterotomy, hemorrhoidectomy, low anterior resection
- Pelvic radiation. Proctitis, poor rectal compliance, urgency, bleeding, fistula risk
- Rectal prolapse, intussusception and rectocele. Impaired evacuation and seepage
- Rectovaginal fistula. Stool or flatus through the vagina, not true sphincteric FI
- Diabetes. In an Australian survey of 8,657 respondents, fecal incontinence at least sometimes was reported by 54/423 people with diabetes (12.8%) versus 3.8% without diabetes; after age and sex adjustment, all 16 surveyed gastrointestinal symptoms were more frequent with diabetes.[26] In a separate physiologic study of 11 patients with diabetes and FI and 20 healthy controls, basal and squeeze pressures were lower in the FI group, and rectal-sensation perception was delayed in 9/11 patients.[52]
- Other neurologic disease. Stroke, dementia, spinal cord injury, multiple sclerosis, pudendal neuropathy
- Functional impairment. Mobility limitation, delayed toileting assistance, cognition, sedatives
Diagnosis and Evaluation
Initial office evaluation
ACOG and ASCRS both emphasize history, symptom characterization, and focused examination before routine ancillary testing.[3][4]
Ask directly:
- Leakage type: solid, liquid, gas, seepage, mucus
- Pattern: urgency versus passive versus post-defecatory seepage
- Frequency, volume, pad use, skin breakdown, sexual impact, activity restriction
- Stool form using the Bristol stool scale
- Constipation, incomplete evacuation, manual splinting, diarrhea, urgency, rectal bleeding
- Obstetric history: OASIS, forceps, episiotomy, large infant, delayed postpartum symptoms
- Prior anorectal, vaginal, prolapse, mesh, fistula, or radiation history
- Medications: metformin, magnesium, antibiotics, laxatives, stool softeners, cholinesterase inhibitors, caffeine, alcohol
- Neurologic disease, cognition, mobility, toileting access, caregiver availability
Examination:
- Inspection. Perianal skin, soiling, hemorrhoids, scars, patulous anus, prolapse, fistula opening, perineal body deficiency
- Digital rectal exam. Resting tone, squeeze tone, puborectalis lift, rectal mass, fecal impaction, tenderness, stool consistency
- Pelvic exam in women. Posterior compartment prolapse, rectocele, perineorrhaphy deficiency, vaginal stool or flatus, atrophy or GSM, fistula suspicion
- Neurologic screen. Perineal sensation, anal wink, bulbocavernosus reflex when relevant, lower-extremity deficits.[27] The reflex is not always reproducible: in one small validation study of women with detrusor overactivity, it was clinically absent in 21% (7 of 33), although a corresponding electrodiagnostic response was present in all but one of those.[27]
No routine laboratory panel is required. Use stool studies when infectious diarrhea is plausible. Colonoscopy is appropriate when FI accompanies change in bowel habits, rectal bleeding, melena, anemia, unexplained weight loss, abdominal pain, or age-based or risk-based colorectal cancer screening indications.[3][4]
When to order specialized testing
Testing should answer a management question: Is there a sphincter defect? Is evacuation impaired? Is sensation abnormal? Is prolapse or fistula driving symptoms? Is surgery being considered?[4][8][9]
| Test | Use |
|---|---|
| Anorectal manometry | Quantifies resting/squeeze pressures, rectal sensation, cough reflex, and coordination; consider when results could clarify dysfunction or guide rehabilitation; not a mandatory prerequisite for SNM |
| Endoanal ultrasound | Useful for IAS/EAS structural assessment when sphincter repair is being considered |
| Pelvic MRI | Better for EAS atrophy, complex scarring, fistula mapping, levator injury, or when ultrasound is unavailable/equivocal |
| Balloon expulsion / defecography | Suspected obstructed defecation, rectocele, intussusception, rectal prolapse, or seepage from incomplete evacuation |
| Pudendal nerve terminal motor latency / EMG | Pudendal latency testing is not routinely recommended [4]; selected specialist neurophysiology may answer a specific question |
Interpret imaging cautiously. Asymptomatic postpartum women can have sphincter defects, and symptomatic patients can have no visible defect. The test must be tied to a treatment decision.
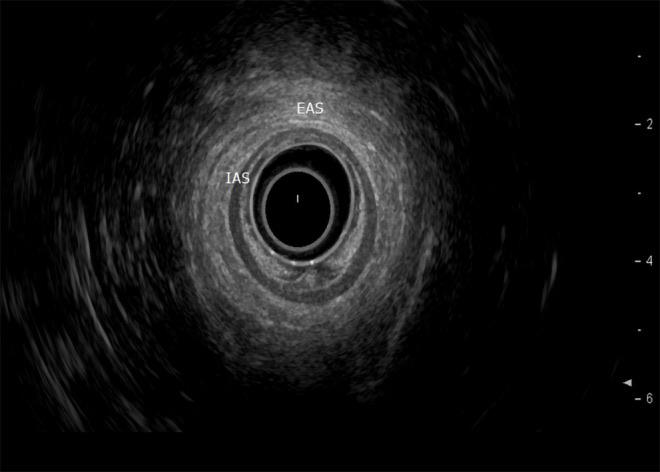
Endoanal ultrasound showing a normal internal anal sphincter (IAS) and external anal sphincter (EAS). From Sbeit W, et al. World J Gastroenterol. 2021;27(15):1553-1562, Figure 3 (CC BY-NC).[8]
Management
First-line: conservative management
Start with stool consistency and toileting mechanics. Conservative measures are first-line treatment, except for fistula or rectal prolapse.[3][4][5] In a five-center cohort of 260 adults with moderate-to-severe FI receiving individualized diet, medication, and pelvic-floor exercises, 39 (15%) sustained a ≥75% reduction in FI frequency at 3 months.[53]
| Intervention | Best use | Practical details |
|---|---|---|
| Bowel diary | Baseline and response tracking | Record stool form, urgency, leakage, meals, medications, and toileting schedule |
| Dietary trigger control | Diarrhea- or urgency-predominant FI | Identify caffeine, alcohol, artificial sweeteners, lactose, high-fat meals, spicy foods |
| Fiber supplementation | Loose stool, seepage, variable stool form | Psyllium is often preferred; titrate slowly to avoid bloating. In the FIRM crossover trial (n=80), psyllium and loperamide each reduced FI episodes with no difference between them[17] |
| Loperamide | Urgency FI with loose stool | Improves stool consistency, urgency threshold, and resting tone. Use for FI is off-label. The 2 mg capsule label covers acute nonspecific diarrhea and chronic diarrhea associated with inflammatory bowel disease; adult dosing begins with 4 mg, then 2 mg after each unformed stool (maximum 16 mg/day). It warns of torsades, cardiac arrest, and death above recommended doses; syncope and ventricular tachycardia have also been reported at recommended doses. Avoid use with QT-prolonging drugs or other QT risk factors and in acute dysentery, acute ulcerative colitis, invasive bacterial enterocolitis, or pseudomembranous colitis.[18] In FIRM, constipation occurred in 29% on loperamide versus 10% on psyllium[17]; in practice, a low dose (2 mg once to three times daily, or before meals or outings) is titrated to stool form |
| Laxative adjustment | Overflow or constipation-associated FI | Treat impaction and incomplete evacuation before labeling as sphincter failure |
| Other antidiarrheal agents | Loperamide-intolerant or -refractory urgency/diarrhea-predominant FI | Diphenoxylate-atropine is an opioid-agonist antidiarrheal; its adult diarrhea label starts at two oral tablets (2.5 mg diphenoxylate hydrochloride/0.025 mg atropine sulfate each) four times daily (maximum 20 mg/day diphenoxylate), with dose reduction after initial control. Use for FI is off-label.[50] In a small matched comparison (21 patients per group), the group receiving cholestyramine plus biofeedback had fewer stools and incontinence episodes and a lower Bristol stool-form score than at baseline at 3 months and 1 year; the mean cholestyramine dose was 3.6 g (titrated). The comparison group received biofeedback alone[30]. Topical phenylephrine raised resting pressure in a 10-patient physiologic study; in a separate randomized crossover trial of 36 patients with structurally intact sphincters, 10% phenylephrine did not significantly improve FI score or resting pressure versus placebo.[31][54] |
| Scheduled toileting | Older adults, mobility impairment, predictable postprandial urgency | Use gastrocolic reflex after meals; coordinate caregiver access |
| Skin care / pads | Any ongoing leakage | Barrier creams, breathable pads, prompt cleansing; treat dermatitis early |
| Anal plugs / inserts and vaginal inserts | Selected patients wanting a device | ASCRS 2023 does not routinely recommend anal or vaginal inserts ; ACOG 2019 says tolerability and availability limit use and that more long-term data are needed before recommending newer devices[3][4]. Named devices: the Eclipse vaginal bowel-control system (an intravaginal pump that inflates a balloon to occlude the distal rectum and deflates for defecation; FDA-cleared 2015, now marketed by Laborie) was successfully fit in 61/110 women (55.5%). Among the 61 who entered treatment, 48/61 (78.7%) had ≥50% fewer episodes at 1 month; 38/44 (86.4%) of those assessed after the optional 3-month extension met that endpoint[28]; the RENEW anal insert (a single-use silicone plug) achieved ≥50% reduction in incontinence frequency in 62% of intention-to-treat subjects, with a 32% mean improvement in severity score at 12 weeks in an uncontrolled study[29]; a 2026 randomized trial of a different single-use anal insert found no significant difference from usual care in its prespecified St Mark's score response at 8 weeks (9/35 versus 7/37), although post hoc episode counts favored the insert and 20/35 users reported device-related events[48] |
| Transanal (rectal) irrigation | Incomplete evacuation with seepage, neurogenic bowel, low anterior resection syndrome | Emptying the rectum on a schedule prevents later leakage; a 2025 systematic review of 16 studies (1,567 adults) with constipation and/or FI, excluding studies limited to neurogenic bowel or low anterior resection syndrome, found mostly observational symptom improvement and 3–57% discontinuation across studies[19] |
A large 2×2 factorial trial (the CAPABLe trial) randomized 300 women with normal stool consistency to oral placebo plus an education pamphlet (42), placebo plus anorectal manometry-assisted biofeedback (84), loperamide plus education (88), or loperamide plus biofeedback (86); 296 were eligible for the efficacy analyses. It found no significant difference in change in St Mark's incontinence score at 24 weeks between loperamide and placebo, biofeedback and education alone, or the combined intervention versus either component alone. Constipation occurred in 33/88 (38%) and 44/86 (51%) of the loperamide groups versus 5/42 (12%) and 19/84 (23%) of the placebo groups.[32]
Pelvic-floor physical therapy and biofeedback
Pelvic-floor muscle training can strengthen the EAS and levator complex, improve coordination, and teach urge suppression. Biofeedback adds visual or auditory feedback from EMG or pressure sensors to isolate EAS contraction without abdominal substitution and to retrain rectal sensation.[3][5][10] ASCRS 2023 says biofeedback may be considered ; it notes that no randomized trial compares biofeedback with sham therapy.[4] The Cochrane review found the trial evidence too limited to define the best protocol.[4][20]
In a 108-patient trial (83 women), manometric biofeedback plus pelvic floor exercises produced adequate relief in 76% at 3 months versus 41% with exercises alone (P<.001). In the 12-month analysis, adequate relief was counted in 24/45 (53%) versus 22/63 (35%; P=.056), while the reduction in Fecal Incontinence Severity Index scores remained greater with biofeedback (P=.03); only 3-month responders were invited to follow-up, with other observations carried forward.[33] In a 98-patient Danish trial, supervised pelvic-floor muscle training with biofeedback was more likely than attention-control massage to produce patient-reported improvement (odds ratio 5.16, 95% CI 2.18-12.19) and produced a larger reduction in the Vaizey score.[34] In a 30-patient trial (20 home, 10 office), the authors reported that voice-guided home biofeedback was noninferior to office biofeedback for change in weekly FI episodes at 6 weeks. Sphincter pressures improved in both groups without a between-group difference; quality-of-life improvement was reported in the home arm.[35]
Best candidates:
- Urgency FI with weak squeeze but preserved cognition and motivation
- Passive or mixed FI with mild-to-moderate sphincter weakness
- Postpartum or post-OASIS patients before considering delayed sphincter repair
- Patients with dyssynergic defecation and seepage from incomplete evacuation
Less favorable candidates include severe dementia, severe rectal hyposensitivity, complete spinal cord injury, profound immobility, and patients who cannot practice between sessions.
Bulking agents
ASCRS 2023 does not routinely recommend injectable anal bulking agents because benefit over placebo and durability are limited.[4] ACOG 2019 says bulking agents may decrease FI episodes for up to 6 months and can be considered as a short-term option for women who have failed conservative treatment (Level B); long-term data are lacking.[3] In the sham-controlled NASHA Dx (Solesta) trial (n=206, 2:1), 52% of treated patients versus 31% of sham had at least a 50% reduction in FI episodes at 6 months (OR 2.36); NASHA Dx is FDA-approved for adults with FI after failed conservative therapy, but Solesta is contraindicated with active inflammatory bowel disease, immunodeficiency or immunosuppression, prior pelvic radiation, significant mucosal or full-thickness rectal prolapse, rectocele, active anorectal abscess, fissure, sepsis, bleeding, proctitis or other infection, anorectal atresia, tumor or malformation, allergy to hyaluronic-acid products, rectal varices, or an existing non-Solesta anorectal implant.[21][45] A separate randomized trial in mild-to-moderate anal incontinence compared a polyacrylate-polyalcohol copolymer bulking agent against endoanal electrical stimulation with biofeedback: at 12 months, the bulking agent produced a significantly greater decline in the Cleveland Clinic Florida Fecal Incontinence Score (mean decline 4.2 versus 0.8 points; between-group difference 3.4 points, 95% CI 1.2-5.5), though quality-of-life measures did not differ between arms.[36] Durability is limited, repeat treatment is common.
Sacral neuromodulation
Sacral neuromodulation (SNM) is an established surgical option for refractory FI and is FDA-approved for FI in the United States.[3][4] It uses an S3 tined lead and implantable pulse generator after a successful test phase, typically defined as at least 50% reduction in FI episodes.[4]
Evidence and counseling:
- In the multicenter InterStim FI cohort (120 implanted after a successful test phase), 89% of the 72 patients with 5-year data had at least a 50% reduction in weekly FI episodes and 36% had complete continence; only 76 of 120 reached 5 years, and 35.5% of those needed revision, replacement, or explant.[22] A pooled analysis restricted to sphincter-defect patients reported continence improvement in 66.7%, a complication rate of 18.5%, and device removal in 9.1%.[12] In a single-center retrospective cohort, 374 patients were screened and 325 received permanent SNM; the authors reported maintained long-term efficacy in 52.7% of all screened patients at a mean 7.1-year follow-up.[38] The device was removed for unsatisfactory results in 81/325 implanted patients (24.9%); quality-of-life scores did not differ from the general population during follow-up.[38] The Cochrane review considers the randomized evidence limited (mostly small crossover trials).[11]
- SNM can work in patients with sphincter defects or pudendal neuropathy; ASCRS 2023 lists it as a conditional, low-quality-evidence first-line surgical option with or without a sphincter defect.[4][12] Prior sphincteroplasty, an EAS defect over 120 degrees, and low resting anal pressure were associated with less improvement.[12] The test-stimulation response determines who is implanted.[22]
- High-grade internal rectal prolapse was associated with lower SNM response in one cohort. Among 106 candidates, temporary test stimulation succeeded in 25/36 (69%) with high-grade intussusception and 60/70 (86%) without it.[37] Among those implanted in that cohort, 1-year success (at least a 50% reduction in FISI score) occurred in 4/25 (16%) with high-grade intussusception versus 31/60 (52%) without it; ASCRS 2023 described the finding as not reproduced.[37][4] A separate retrospective cohort of 169 implanted patients, including 46 with Oxford grade III–IV intussusception, found similar 1-year Wexner-score improvement with and without intussusception (−6.7 versus −5.7; P = .40).[51] Defecography may clarify suspected obstructed evacuation or internal prolapse; anorectal physiology does not reliably predict SNM response.[4][37]
- Adverse events include pain, infection, lead migration, hematoma, loss of efficacy, battery replacement, pocket revision, and explant.[3][11]
SUBSoNIC (2025): the blinded crossover trial compared subsensory active SNM with the implanted device switched off. COVID-19 disrupted recruitment: 39 participants enrolled, and only 16 had complete primary data. The weekly-episode difference was −0.795 (95% CI −1.5 to 0.0; p=0.06). This inconclusive result tempers certainty from uncontrolled implant cohorts.[15]
Percutaneous tibial nerve stimulation
PTNS did not meet the prespecified primary endpoint in two large sham-controlled FI trials: in CONFIDeNT (n=227 randomized), 39/103 patients with complete diaries on PTNS (38%) versus 32/102 on sham (31%) had at least 50% fewer episodes after 12 treatments (p=0.40), although a secondary episode-count analysis favored PTNS; in NOTABLE (n=166 randomized women), the primary St Mark score change did not differ at 12 weeks, and weekly FI episodes fell by 2.1 versus 1.9 (secondary outcome).[23][24]
Intrarectal botulinum toxin — emerging option for urgency-predominant FI
In FI-Toxin, 191 adults with refractory urgency or FI received intrarectal submucosal botulinum toxin type A (200 units; n=96) or saline (n=95).[46] At 3 months, the baseline-adjusted difference in the combined number of FI and urgency episodes was −0.51 per day (95% CI −0.80 to −0.21).[46] Across trial follow-up, constipation was reported in 68/169 patients who received toxin at any point and 38/95 placebo recipients (40% in each group); no serious treatment-related adverse events were reported.[46] A retrospective follow-up found that 52/147 patients met treatment-failure criteria between months 6 and 54; 114 patients received treatment during that interval, including 165 reinjections.[47] Comparative placement and repeat-treatment strategy remain uncertain.[47]
Noninvasive translumbosacral neuromodulation — emerging evidence
A 2026 multicenter sham-controlled trial randomized 109 patients to six weekly sessions of 2400 or 3600 magnetic pulses, or sham. At least 50% fewer weekly FI episodes occurred in 25/38 (65.8%), 30/37 (81.1%), and 11/34 (32.4%), respectively. Quality-of-life changes were not significantly different between groups. No treatment-related serious adverse events were reported.[16]
Sphincteroplasty
Overlapping sphincteroplasty may be considered for FI with a discrete EAS defect after failed conservative therapy, with careful counseling in delayed OASIS presentations.[3][4] ASCRS 2023 makes this a conditional recommendation supported by low-quality evidence.[4] The limiting reality after sphincteroplasty for obstetric injury is durability: short-term improvement is common, but results often deteriorate over time, and as few as 10% to 14% of patients have sustained improvement at 5 years.[4] Wexner score gains in single-center series typically return to baseline by 3 years.[4] Repeat sphincter reconstruction after a failed overlapping sphincteroplasty should generally be avoided ; in one retrospective series of 56 patients, only 28.6% reported a good result after 74 months.[4]
Counseling points:
- Delayed postpartum FI is frequently multifactorial, even with a visible EAS defect.
- SNM is often chosen for refractory FI even when a sphincter defect exists, particularly when neuropathy or urgency physiology dominates. Comparative data are thin: a matched retrospective series of 26 women found a CCF-FIS reduction with SNM but not sphincteroplasty, without a significant between-group difference (P=0.06), and the 2026 meta-analysis judged the data insufficient for firm conclusions.[12][13]
Regenerative and cell-based therapy — investigational
Sphincteric injection of autologous muscle-derived cells is an investigational approach distinct from bulking agents, aiming to regenerate rather than augment sphincter tissue. In a phase 2 randomized, double-blind, placebo-controlled trial of intrasphincteric autologous myoblast injection (24 patients), the Cleveland Clinic Incontinence score improved similarly in both arms at 6 months (a transient placebo effect), but only the treatment arm sustained improvement at 12 months, with at least a 30% reduction in Cleveland Clinic Incontinence score at 12 months in 7/12 treated patients versus 1/12 placebo patients (P = .03).[39] A separate, non-randomized phase 1/2 study of a distinct autologous muscle-derived cell product (iltamiocel) treated 48 participants and reported no serious product-related adverse events; among participants assessed for efficacy at 12 months, 53.7% had at least a 50% reduction in FI episodes and 24.4% had complete restoration of continence, with phase 3 trials ongoing.[40]
Salvage and last-resort options
The artificial bowel sphincter is a salvage option after less invasive treatments fail; end colostomy can be considered when other therapies have failed or are not desired.[4][25] Surgical evidence for FI is generally low quality; the artificial bowel sphincter carried the highest complication rates (22% to 100% across series) and often required reoperation.[25] ASCRS 2023 lists colostomy as an option for patients who have failed or do not wish to pursue other therapies .[4] The same guideline says antegrade colonic enemas can be considered in highly motivated patients seeking an alternative to a stoma (conditional, very low), and recommends against temperature-controlled radiofrequency energy to the sphincter complex (conditional, very low).[4] The magnetic anal sphincter (LINX, FENIX) is not an established option for FI in the United States. A transobturator posterior anal sling (TOPAS), a self-fixating polypropylene mesh placed under the mid-anal canal, was studied in a 152-woman prospective multicenter study: 69.1% met the ≥50% reduction success criterion at 12 months and 19% reported complete continence, with pelvic pain and infection as the main adverse events.[41] Its manufacturers discontinued the device in 2017, so it is not currently commercially available.[41] A rod-shaped prosthesis (Sphinkeeper) placed vertically around the anal canal through a dedicated introducer has been reported for patients whose main symptom is passive leakage. In a single-arm prospective study of 42 patients (14 with a sphincter defect, mean follow-up 15.9 months), implantation improved quality of life.[44] A systematic review pooling GateKeeper and SphinKeeper found eight uncontrolled prospective studies (166 patients); device-related events, including dislodgement and removal or extrusion, occurred in 48/166.[49] SphinKeeper remains a limited-evidence option.[49]
Correct the surgically correctable lesion
FI from rectovaginal fistula, rectal prolapse, large symptomatic rectocele with stool trapping, or severe posterior-compartment or perineal body disruption should be managed as anatomy plus continence, not FI alone. These patients need pelvic-surgery expertise and, often, colorectal collaboration.
Special Populations
Postpartum and delayed OASIS
Ask about remote obstetric trauma even when delivery occurred decades earlier. A thin perineal body, gaping introitus, keyhole deformity, or poor squeeze should prompt consideration of endoanal ultrasound or MRI before posterior repair. FI counseling belongs in the same conversation as posterior colporrhaphy, perineorrhaphy, and rectovaginal fistula repair. Structured follow-up after a recognized OASI (EAUS, manometry and mode-of-delivery counseling) is covered under Postpartum Perineal Clinic.
Older adults
Treatment success often depends less on sphincter pressure and more on stool form, mobility, cognition, medication simplification, toileting access, skin care, and caregiver support.[14] Avoid creating constipation or impaction with aggressive loperamide.
Men
Men underreport FI and should be asked directly. Common settings include post-anorectal surgery, diabetes neuropathy, pelvic radiation, neurologic disease, diarrhea, and rectal prolapse. The evaluation is similar, with emphasis on DRE, stool consistency, anorectal surgical history, radiation history, and neurologic risk.
Neurologic disease
FI in spinal cord injury, multiple sclerosis, dementia, stroke, or diabetic neuropathy may require a bowel program rather than isolated sphincter treatment (see Neurogenic Bowel for SCI, MS, and spina bifida bowel-program escalation). Biofeedback requires cognition and practice capacity; SNM candidacy depends on neurologic diagnosis, intact peripheral pathways, MRI needs, and test response.
Follow-Up and Failure Patterns
Track:
- FI episodes per week
- Stool consistency and urgency
- Pad use and skin breakdown
- Wexner / St Mark's score
- Bowel diary response to fiber, loperamide, laxative changes, and scheduled toileting
- Patient-prioritized goal: no solid stool leakage, less urgency, fewer pads, social confidence, sexual comfort, caregiver ease
The trial-standard "≥50% reduction in FI episodes" is a research convention. In a survey of 186 people with FI, most required at least a 75% reduction in frequency to call a treatment successful, though a ≥50% reduction was an acceptable endpoint for 58% overall (only 26% of those 65 or older).[42]
If treatment fails, reassess the mechanism:
- Persistent loose stool or medication-driven diarrhea
- Overflow from constipation or impaction
- Rectal prolapse, intussusception, or rectocele with trapping
- Rectovaginal fistula rather than sphincteric FI
- Unrecognized EAS or IAS defect or atrophy
- Neurologic disease, cognition, or toileting access
- Radiation proctitis or inflammatory bowel disease
See Also
- The Anal Canal
- The Perineum
- Chronic Constipation
- Rectovaginal Fistula
- Pelvic Organ Prolapse
- Sacral Neuromodulation
- Obstetric Perineal & Vaginal Lacerations
Podcasts
References
1. Bharucha AE, Knowles CH, Mack I, et al. "Faecal Incontinence in Adults." Nat Rev Dis Primers. 2022;8(1):53. doi:10.1038/s41572-022-00381-7
2. Haylen BT, de Ridder D, Freeman RM, et al. "An International Urogynecological Association (IUGA) / International Continence Society (ICS) Joint Report on the Terminology for Female Pelvic Floor Dysfunction." Neurourol Urodyn. 2010;29(1):4-20. doi:10.1002/nau.20798
3. ACOG Practice Bulletin No. 210: "Fecal Incontinence." Obstet Gynecol. 2019;133(4):e260-e273. doi:10.1097/AOG.0000000000003187
4. Bordeianou LG, Thorsen AJ, Keller DS, et al. "The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Management of Fecal Incontinence." Dis Colon Rectum. 2023;66(5):647-661. doi:10.1097/DCR.0000000000002776
5. Wald A, Bharucha AE, Limketkai B, et al. "ACG Clinical Guidelines: Management of Benign Anorectal Disorders." Am J Gastroenterol. 2021;116(10):1987-2008. doi:10.14309/ajg.0000000000001507
6. Rao SSC. "Pathophysiology of Adult Fecal Incontinence." Gastroenterology. 2004;126(1 Suppl 1):S14-S22. doi:10.1053/j.gastro.2003.10.013
7. Bharucha AE, Zinsmeister AR, Locke GR, et al. "Risk Factors for Fecal Incontinence: A Population-Based Study in Women." Am J Gastroenterol. 2006;101(6):1305-1312. doi:10.1111/j.1572-0241.2006.00553.x
8. Sbeit W, Khoury T, Mari A. "Diagnostic Approach to Faecal Incontinence: What Test and When to Perform?" World J Gastroenterol. 2021;27(15):1553-1562. doi:10.3748/wjg.v27.i15.1553
9. Rao SSC, Bharucha AE, Carrington EV, et al. "Anorectal Disorders." Gastroenterology. 2026;170:1318–1346. doi:10.1053/j.gastro.2026.01.037
10. Mazur-Bialy AI, Kolomanska-Bogucka D, Oplawski M, Tim S. "Physiotherapy for Prevention and Treatment of Fecal Incontinence in Women-Systematic Review of Methods." J Clin Med. 2020;9(10):3255. doi:10.3390/jcm9103255
11. Thaha MA, Abukar AA, Thin NN, Ramsanahie A, Knowles CH. "Sacral Nerve Stimulation for Faecal Incontinence and Constipation in Adults." Cochrane Database Syst Rev. 2015;(8):CD004464. doi:10.1002/14651858.CD004464.pub3
12. Emile SH, Wignakumar A, Horesh N, et al. "Efficacy of Sacral Neuromodulation in Treatment of Fecal Incontinence Associated With Anal Sphincter Defects: A Systematic Review and Meta-Analysis." World J Surg. 2026;50(1):48-57. doi:10.1002/wjs.70152
13. Rodrigues FG, Chadi SA, Cracco AJ, et al. "Faecal Incontinence in Patients With a Sphincter Defect: Comparison of Sphincteroplasty and Sacral Nerve Stimulation." Colorectal Dis. 2017;19(5):456-461. doi:10.1111/codi.13510
14. Wang XJ, Nguyen LAB. "'Functional' GI Conditions in the Older Adult: DGBIs and Beyond." Am J Gastroenterol. 2025;120(Suppl 10):S45-S55. doi:10.14309/ajg.0000000000003641.06
15. Vollebregt PF, Goh YL, Bagul A, et al. Clinical efficacy of subsensory sacral neuromodulation in adults with faecal incontinence: the SUBSoNIC crossover randomised controlled trial and cohort follow-up study. Colorectal Dis. 2025;27(11):e70308. doi:10.1111/codi.70308.
16. Rao SSC, Yan Y, Hamdy S, et al. Randomized sham-controlled trial of translumbosacral neuromodulation therapy for fecal incontinence. Gastroenterology. 2026;171(4):656-666. doi:10.1053/j.gastro.2026.04.027.
17. Markland AD, Burgio KL, Whitehead WE, et al. "Loperamide Versus Psyllium Fiber for Treatment of Fecal Incontinence: The Fecal Incontinence Prescription (Rx) Management (FIRM) Randomized Clinical Trial." Dis Colon Rectum. 2015;58(10):983-93. doi:10.1097/DCR.0000000000000442
18. Loperamide hydrochloride capsules 2 mg, prescribing information (Mylan Institutional). DailyMed, National Library of Medicine. setid ad71d4ab-d293-47a2-8f3f-2c9f42d76e40. dailymed.nlm.nih.gov
19. Vollebregt PF, Baeten CIM, Drewes AM, et al. "Transanal Irrigation: Bridging the Gap in Treatment for Chronic Constipation and/or Faecal Incontinence-A Systematic Review and Management Guidance." Colorectal Dis. 2025;27(11):e70274. doi:10.1111/codi.70274
20. Norton C, Cody JD. "Biofeedback and/or Sphincter Exercises for the Treatment of Faecal Incontinence in Adults." Cochrane Database Syst Rev. 2012;2012(7):CD002111. doi:10.1002/14651858.CD002111.pub3
21. Graf W, Mellgren A, Matzel KE, et al. "Efficacy of Dextranomer in Stabilised Hyaluronic Acid for Treatment of Faecal Incontinence: A Randomised, Sham-Controlled Trial." Lancet. 2011;377(9770):997-1003. doi:10.1016/S0140-6736(10)62297-0
22. Hull T, Giese C, Wexner SD, et al. "Long-Term Durability of Sacral Nerve Stimulation Therapy for Chronic Fecal Incontinence." Dis Colon Rectum. 2013;56(2):234-45. doi:10.1097/DCR.0b013e318276b24c
23. Knowles CH, Horrocks EJ, Bremner SA, et al. "Percutaneous Tibial Nerve Stimulation Versus Sham Electrical Stimulation for the Treatment of Faecal Incontinence in Adults (CONFIDeNT): A Double-Blind, Multicentre, Pragmatic, Parallel-Group, Randomised Controlled Trial." Lancet. 2015;386(10004):1640-8. doi:10.1016/S0140-6736(15)60314-2
24. Zyczynski HM, Richter HE, Sung VW, et al. "Percutaneous Tibial Nerve Stimulation vs Sham Stimulation for Fecal Incontinence in Women: NeurOmodulaTion for Accidental Bowel Leakage Randomized Clinical Trial." Am J Gastroenterol. 2022;117(4):654-667. doi:10.14309/ajg.0000000000001605
25. Forte ML, Andrade KE, Lowry AC, et al. "Systematic Review of Surgical Treatments for Fecal Incontinence." Dis Colon Rectum. 2016;59(5):443-69. doi:10.1097/DCR.0000000000000594
26. Bytzer P, Talley NJ, Leemon M, et al. "Prevalence of Gastrointestinal Symptoms Associated With Diabetes Mellitus: A Population-Based Survey of 15,000 Adults." Arch Intern Med. 2001;161(16):1989-96. doi:10.1001/archinte.161.16.1989
27. Wester C, FitzGerald MP, Brubaker L, Welgoss J, Benson JT. "Validation of the Clinical Bulbocavernosus Reflex." Neurourol Urodyn. 2003;22(6):589-91. doi:10.1002/nau.10140
28. Richter HE, Matthews CA, Muir T, et al. "A Vaginal Bowel-Control System for the Treatment of Fecal Incontinence." Obstet Gynecol. 2015;125(3):540-547. doi:10.1097/AOG.0000000000000639
29. Lukacz ES, Segall MM, Wexner SD. "Evaluation of an Anal Insert Device for the Conservative Management of Fecal Incontinence." Dis Colon Rectum. 2015;58(9):892-8. doi:10.1097/DCR.0000000000000427
30. Remes-Troche JM, Ozturk R, Philips C, Stessman M, Rao SS. "Cholestyramine--a Useful Adjunct for the Treatment of Patients With Fecal Incontinence." Int J Colorectal Dis. 2008;23(2):189-94. doi:10.1007/s00384-007-0391-y
31. Cheetham MJ, Kamm MA, Phillips RK. "Topical Phenylephrine Increases Anal Canal Resting Pressure in Patients With Faecal Incontinence." Gut. 2001;48(3):356-9. doi:10.1136/gut.48.3.356
32. Jelovsek JE, Markland AD, Whitehead WE, et al. "Controlling Faecal Incontinence in Women by Performing Anal Exercises With Biofeedback or Loperamide: A Randomised Clinical Trial." Lancet Gastroenterol Hepatol. 2019;4(9):698-710. doi:10.1016/S2468-1253(19)30193-1
33. Heymen S, Scarlett Y, Jones K, Ringel Y, Drossman D, Whitehead WE. "Randomized Controlled Trial Shows Biofeedback to Be Superior to Pelvic Floor Exercises for Fecal Incontinence." Dis Colon Rectum. 2009;52(10):1730-7. doi:10.1007/DCR.0b013e3181b55455
34. Ussing A, Dahn I, Due U, Sørensen M, Petersen J, Bandholm T. "Efficacy of Supervised Pelvic Floor Muscle Training and Biofeedback vs Attention-Control Treatment in Adults With Fecal Incontinence." Clin Gastroenterol Hepatol. 2019;17(11):2253-2261.e4. doi:10.1016/j.cgh.2018.12.015
35. Xiang X, Sharma A, Patcharatrakul T, et al. "Randomized Controlled Trial of Home Biofeedback Therapy Versus Office Biofeedback Therapy for Fecal Incontinence." Neurogastroenterol Motil. 2021;33(11):e14168. doi:10.1111/nmo.14168
36. Corrêa Neto IJF, Pinto RA, Brandão DG, et al. "Administration of an Anal Bulking Agent With Polyacrylate-Polyalcohol Copolymer Particles Versus Endoanal Electrical Stimulation With Biofeedback for the Management of Mild and Moderate Anal Incontinence: A Randomized Prospective Study." Dis Colon Rectum. 2022;65(7):917-927. doi:10.1097/DCR.0000000000002458
37. Prapasrivorakul S, Gosselink MP, Gorissen KJ, et al. "Sacral Neuromodulation for Faecal Incontinence: Is the Outcome Compromised in Patients With High-Grade Internal Rectal Prolapse?" Int J Colorectal Dis. 2015;30(2):229-34. doi:10.1007/s00384-014-2078-5
38. Janssen PT, Kuiper SZ, Stassen LP, Bouvy ND, Breukink SO, Melenhorst J. "Fecal Incontinence Treated by Sacral Neuromodulation: Long-Term Follow-Up of 325 Patients." Surgery. 2017;161(4):1040-1048. doi:10.1016/j.surg.2016.10.038
39. Boyer O, Bridoux V, Giverne C, et al. "Autologous Myoblasts for the Treatment of Fecal Incontinence: Results of a Phase 2 Randomized Placebo-Controlled Study (MIAS)." Ann Surg. 2018;267(3):443-450. doi:10.1097/SLA.0000000000002268
40. Knowles CH, Canestrari E, Jankowski RJ, Cardello K, Raval MJ. "Safety and Efficacy of Iltamiocel Cellular Therapy for the Treatment of Fecal Incontinence. Results of a Phase 1/2 Study." Ann Surg. 2023;278(6):937-944. doi:10.1097/SLA.0000000000005894
41. Mellgren A, Zutshi M, Lucente VR, Culligan P, Fenner DE. "A Posterior Anal Sling for Fecal Incontinence: Results of a 152-Patient Prospective Multicenter Study." Am J Obstet Gynecol. 2016;214(3):349.e1-8. doi:10.1016/j.ajog.2015.10.013
42. Heymen S, Palsson O, Simren M, Whitehead WE. "Patient Preferences for Endpoints in Fecal Incontinence Treatment Studies." Neurogastroenterol Motil. 2017;29(5). doi:10.1111/nmo.13032
43. Bordeianou LG, Anger J, Boutros M, et al. "Measuring Pelvic Floor Disorder Symptoms Using Patient-Reported Instruments: Proceedings of the Consensus Meeting of the Pelvic Floor Consortium of the American Society of Colon and Rectal Surgeons, the International Continence Society, the American Urogynecologic Society, and the Society of Urodynamics, Female Pelvic Medicine and Urogenital Reconstruction." Tech Coloproctol. 2020;24(1):5-22. doi:10.1007/s10151-019-02125-4
44. Litta F, Parello A, De Simone V, et al. "Efficacy of Sphinkeeper™ Implant in Treating Faecal Incontinence." Br J Surg. 2020;107(5):484-488. doi:10.1002/bjs.11558
45. U.S. Food and Drug Administration. "Solesta: Summary of Safety and Effectiveness Data (PMA P100014)." 2011. FDA PDF
46. Leroi AM, Queralto M, Zerbib F, et al. "Intrarectal injections of botulinum toxin versus placebo for the treatment of urge faecal incontinence in adults (FI-Toxin): a double-blind, multicentre, randomised, controlled phase 3 study." Lancet Gastroenterol Hepatol. 2024;9(2):147-158. doi:10.1016/S2468-1253(23)00332-1
47. Desprez C, Brochard C, Vitton V, et al. "Intrarectal Injections of Botulinum Toxin for the Treatment of Urge Fecal Incontinence: Long-Term Results of an FI-Toxin Cohort Study." Neurogastroenterol Motil. 2025;37(7):e70025. doi:10.1111/nmo.70025
48. Assmann SL, Winkens B, Bours A, et al. "Controlling Fecal Incontinence With a Novel Anal Device: A Randomized Clinical Trial." JAMA Netw Open. 2026;9(4):e269208. doi:10.1001/jamanetworkopen.2026.9208
49. Gassner L, Wild C, Walter M. "Clinical effectiveness and safety of self-expandable implantable bulking agents for faecal incontinence: a systematic review." BMC Gastroenterol. 2022;22(1):389. doi:10.1186/s12876-022-02441-4
50. Unichem Pharmaceuticals (USA), Inc. "Diphenoxylate Hydrochloride and Atropine Sulfate Tablets: Prescribing Information." DailyMed. Revised October 2025. Current label.
51. Dawes AJ, Mariscal JO, White PJ, et al. "Does Rectoanal Intussusception Limit Improvements in Clinical Outcome and Quality of Life After Sacral Nerve Stimulation for Fecal Incontinence?" Dis Colon Rectum. 2023;66(6):831-839. doi:10.1097/DCR.0000000000002685
52. Sun WM, Katsinelos P, Horowitz M, Read NW. "Disturbances in anorectal function in patients with diabetes mellitus and faecal incontinence." Eur J Gastroenterol Hepatol. 1996;8(10):1007-1012. doi:10.1097/00042737-199610000-00014
53. Rehman MA, Heymen S, Rao SSC, et al. "Effectiveness of Medical-Behavioral Therapy in Patients with Fecal Incontinence." Clin Gastroenterol Hepatol. Published online September 25, 2026. doi:10.1016/j.cgh.2026.09.024
54. Carapeti EA, Kamm MA, Phillips RKS. "Randomized controlled trial of topical phenylephrine in the treatment of faecal incontinence." Br J Surg. 2000;87(1):38-42. doi:10.1046/j.1365-2168.2000.01306.x
55. Sultan AH, Kamm MA, Hudson CN, Thomas JM, Bartram CI. "Anal-sphincter disruption during vaginal delivery." N Engl J Med. 1993;329(26):1905-1911. doi:10.1056/NEJM199312233292601