CT Urogram & CT-Based Imaging in Reconstructive Urology
CT urography (CTU) maps the urinary tract from the renal parenchyma to the ureteral orifices in three dimensions. It is a principal study for the soft-tissue envelope around the tract, intrinsic urothelial lesions and the spatial relationships of the retroperitoneum and pelvis, where fluoroscopic and nuclear studies are limited. It cannot quantify split renal function or drainage kinetics, which need diuretic renography.
CTU answers an anatomic question. Phases are chosen around the suspected lesion and the decision the result will change. A full CTU is not required for every stone, stricture, episode of microscopic hematuria or postoperative follow-up.[1][2]
Choosing the Study
| Clinical question | Useful study | Limitation |
|---|---|---|
| High-risk microhematuria | Cystoscopy plus axial upper-tract imaging; usually CTU if suitable[1] | — |
| Intermediate-risk microhematuria | Cystoscopy and renal/bladder ultrasound; in appropriately counseled patients who wish to avoid cystoscopy, cytology or a validated urine marker may guide that decision | Ultrasound is still performed if cystoscopy is deferred.[1] |
| Suspected stone | Ultrasound or noncontrast CT according to presentation | Contrast/excretory phases are added for a separate anatomic question.[7] |
| Suspected ureteral injury or urinary leak | Contrast CT with delayed images; AUA recommends this for stable trauma patients with suspected ureteral injury (Statement 9a; Recommendation, Grade C) | Poor excretion can limit localization; further delayed or direct studies may be needed.[5] |
| Suspected bladder rupture | Retrograde CT or conventional cystography | Excreted IV contrast passively filling the bladder is insufficient to exclude rupture.[5][6] |
| Differential renal function / drainage | Diuretic renography, usually MAG3 | Interpret function, drainage, hydration and bladder emptying together.[8] |
1. Indications and Alternatives
Hematuria and urothelial lesions
Apply the AUA/SUFU 2025 risk assessment. Pre-urethroplasty CTU is indication-specific. In a patient with a urethral or ureteral stricture and gross or persistent microscopic hematuria, the hematuria evaluation still applies, because upper-tract urothelial carcinoma can coexist with stricture disease and a missed lesion delays oncologic care. Low/negligible-risk microhematuria calls for repeat urinalysis within six months . For intermediate-risk patients, AUA/SUFU recommends cystoscopy and renal ultrasound ; urine cytology or validated urine markers may inform cystoscopy in appropriately counseled patients who wish to avoid it, with ultrasound still performed . High-risk patients receive cystoscopy and axial upper-tract imaging , with multiphasic CT urography when suitable . When CTU is unsuitable, MR urography is an alternative ; when both are unsuitable, retrograde pyelography with noncontrast axial imaging or renal ultrasound may be used . The guideline recommends upper-tract imaging in any risk category when there is a family history of renal cell carcinoma, a known genetic renal tumor syndrome, or a personal or family history of Lynch syndrome , and allows additional imaging for persistent or recurrent microhematuria after renal ultrasound . Gross hematuria requires a separate complete clinical evaluation.[1]
CTU may demonstrate filling defects, urothelial thickening, papillary lesions or obstruction with hydroureteronephrosis above a discrete lesion. AUA/SUO 2023 recommends cystoscopy and contrast cross-sectional upper-tract imaging with delayed collecting-system and ureter images for suspected UTUC . Its discussion favors multiphasic CT urography when suitable, MR urography when contrast-enhanced CT is contraindicated, and retrograde pyelography with noncontrast axial imaging when both CT and MR urography are contraindicated.[23]
EAU 2026 describes CT urography as the most accurate imaging test for UTUC (pooled sensitivity 92% and specificity 95% in a meta-analysis of 13 studies, 1,233 patients); AUA/SUO cites the same pooled sensitivity and specificity.[10][23] EAU notes that flat epithelial lesions without mass effect or urothelial thickening are generally not visible on CT and strongly recommends CT with urography, or MRI when CT is contraindicated, for the diagnosis and staging of all upper-tract tumors (evidence summary LE 2a for CT urography with ureteroscopy).[10] MR urography is less sensitive than CT urography (75% for contrast-enhanced MR urography in tumors under 2 cm).[10] EAU strongly recommends diagnostic ureteroscopy when imaging and voided cytology do not establish the diagnosis or risk category.[10] AUA/SUO recommends diagnostic ureteroscopy, biopsy of identified lesions and selective upper-tract cytologic washing for suspected UTUC . Its discussion permits rare exceptions when other evidence clearly establishes UTUC or endoscopy would not affect management.[23]
Stone disease with stricture
Unenhanced CT is the standard test for urolithiasis. EAU 2026 strongly recommends noncontrast CT to confirm the diagnosis in acute flank pain after initial ultrasound (LE 1a, superior to intravenous urography), and suggests a contrast study when stone removal is planned and the collecting-system anatomy needs delineation (LE 3).[7] When a stone coexists with a ureteral stricture, and stone passage may itself have caused the stricture, one CTU can identify the stones by size and location, localize the transition point, show hydronephrosis and perinephric stranding or abscess, and give the operative map for ureteroscopy with dilation or formal ureteroplasty.
Ureteral reconstruction and congenital anatomy
Specify the operative question: narrowing location, opacified length, collecting-system duplication, relationship to a mass, or vascular anatomy. Thin sections with multiplanar and maximum-intensity reconstructions localize the transition point of a ureteral stricture and the periureteral tissue around it. Stricture length can be measured when both the dilated proximal segment and the collapsed distal segment are seen. Poorly excreting or completely obstructed segments may remain unopacified, so a retrograde or antegrade study can supply additional luminal information.[2][5]
Reconstructive selection also uses symptoms, serial anatomy and functional assessment. Neither a cortical-thickness measurement nor a delayed nephrogram is a substitute for a measured differential renal function.[8] An arterial or corticomedullary acquisition with thin sections and 3D reconstruction shows a lower-pole vessel crossing anterior to the UPJ, and dedicated CT or MR angiography can be requested for complex cases such as a redundant pelvis, secondary vessels or horseshoe kidney.
Periureteral stranding, thickening and enhancement indicate inflammation. Dense soft tissue encasing the ureter suggests retroperitoneal fibrosis (see below), and diffuse thickening within a radiation field suggests radiation fibrosis. Before radical cystectomy with diversion, CTU documents ureteral caliber, position and any existing stricture, hydronephrosis, ureteral length and course for the planned anastomosis, and the presence of an upper-tract lesion.
Beyond a crossing vessel, descriptive ancillary signs reported for UPJ obstruction include an abnormal renal axis (hilum rotated anteriorly, upper pole pointing laterally), absent perinephric stranding (favoring a chronic process over an acutely obstructing stone), asymmetric corticomedullary and pelvicalyceal opacification between the two sides, cortical thinning, and hydronephrosis disproportionately greater in the extrarenal than the intrarenal collecting system.[15]
Congenital anatomy. Before pyeloplasty in a horseshoe kidney, CTU with 3D reconstruction maps the isthmus relative to the aorta and mesenteric vessels, aberrant renal arteries and the ureteral course, which usually passes anterior to the isthmus. In a pelvic kidney it shows the anomalous vascular supply and the relationship of the ureter to pelvic structures. In a duplex system it shows the ureteral insertions (the upper-moiety ureter usually inserts ectopically, below and medial to the lower-moiety orifice, the Weigert-Meyer rule), any ureterocele and coexisting lower-moiety UPJ obstruction.
Fistula, collection and postoperative complication
Request an excretory phase when the question is a urinary leak and a retrograde cystogram when bladder integrity is the question. Communicate prior surgery, diversion anatomy, stents, drains, renal function and the suspected communication. Delayed contrast in a collection supports a urinary source; absent opacification does not reliably exclude a small leak in a poorly functioning unit.[5][6]
Complex pelvic fistulae may also need MRI, endoscopy or direct contrast studies. See MRI and the fistula repair atlas.
For a vesicovaginal fistula, excretory CT or CT cystography can show vaginal contrast, a visible tract, associated ureteral dilation and pelvic changes; cystoscopy maps the fistula in relation to the ureteral orifices.[26] For rectourethral fistula, CTU with a CT cystogram can show the communication, surrounding radiation fibrosis, associated ureteral or bladder involvement and pelvic abscess. In the irradiated pelvis, CT can map bladder wall thickening, ureteral dilation, pelvic masses and adjacent bowel for operative planning.[26]
Oral contrast can help show a communication between bowel and the urinary tract (for example an enterovesical fistula), and rectal contrast is used for a suspected colovesical fistula, most often from sigmoid diverticular disease, when CT cystography alone has not confirmed the tract.[17]
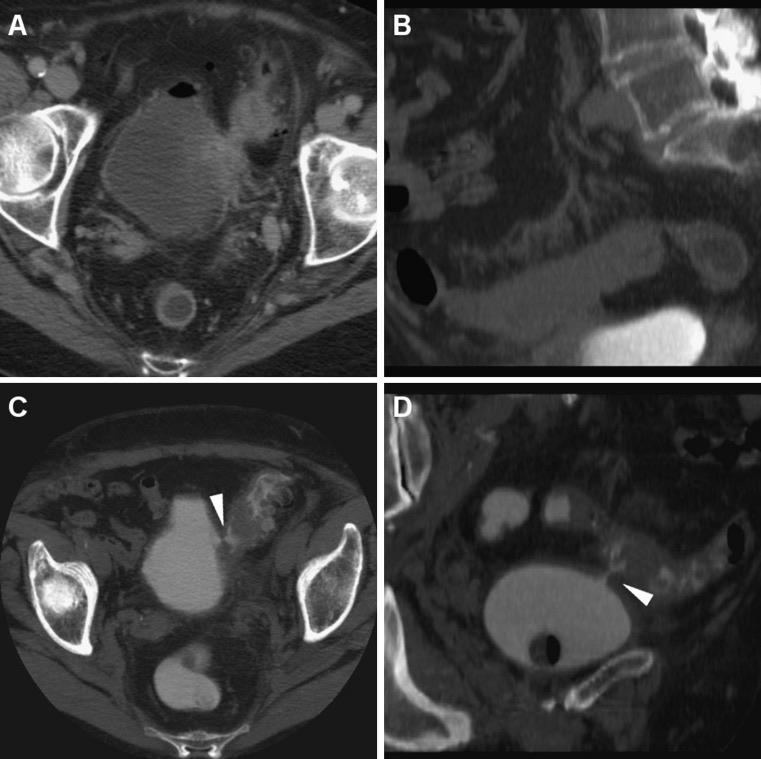
Colovesical fistula from sigmoid diverticular disease in a patient with fecaluria and a negative cystoscopy. (A) Axial CT: sigmoid diverticulosis with perivisceral inflammation, focally adherent to the thickened left bladder wall, and air in the bladder without prior catheterization. (B) Focused sagittal MIP of the excretory phase: the fistula is not visualized. (C, D) MDCT cystography, axial and oblique-coronal reformats: leakage of dilute contrast into the sigmoid colon through a short fistula (arrowheads). From Tonolini M, Bianco R. Insights Imaging. 2012;3(2):181–187, Fig. 1 (CC BY).[17]
2. CTU Protocol — Match the Acquisition to the Question
The ESUR technical consensus describes selecting one, two or three phases according to indication and patient characteristics.[2]
| Acquisition | Main contribution | Planning point |
|---|---|---|
| Unenhanced | Stones, renal and ureteral wall calcification, phleboliths, baseline lesion attenuation | Include when that information is needed. Split-bolus protocols can also include an unenhanced scan.[2] |
| Nephrographic | Renal parenchyma, renal masses, ureteral wall enhancement, retroperitoneal soft tissue | A corticomedullary (arterial) acquisition is added for vascular detail such as a UPJ crossing vessel. Coordinate lesion-specific phases with radiology.[2] |
| Excretory | Contrast-filled collecting systems and ureters: filling defects, stricture transition point, duplication, ureterocele, dilation, bladder wall and diverticula | Timing depends on excretion and the clinical question.[2][3] |
| Split-bolus combined phase | Nephrographic and excretory information in fewer acquisitions | May reduce exposure, but additional delayed images can offset savings.[3] |
In the split-bolus technique a first contrast bolus is followed by a wait to allow excretion into the collecting system and then a second bolus, and a single acquisition captures excretory and nephrographic information together. This removes one acquisition. It suits urothelial and collecting-system questions without a dedicated stone or mass question. A separate unenhanced series, the corticomedullary phase for vascular mapping and a full three-phase protocol are chosen when stone detection, mass enhancement or pre-pyeloplasty vascular mapping is the main question.
Low-dose IV furosemide given with the contrast has been used to distend the ureter and improve mid-ureteral opacification, a common technical failure that can be mistaken for obstruction. Furosemide is omitted when the aim is to preserve obstructed anatomy; the ESUR consensus advises against its use in acute obstruction or acute renal insufficiency and calls for caution with dehydration or hypotension.[2] Oral contrast is not routinely used because it can obscure ureteral filling. Water as negative oral contrast improves bowel delineation. Prone imaging during unenhanced CT can distinguish a stone impacted at the ureterovesical junction from one that has passed into the bladder; studies of excretory-phase opacification have shown mixed results.[2]
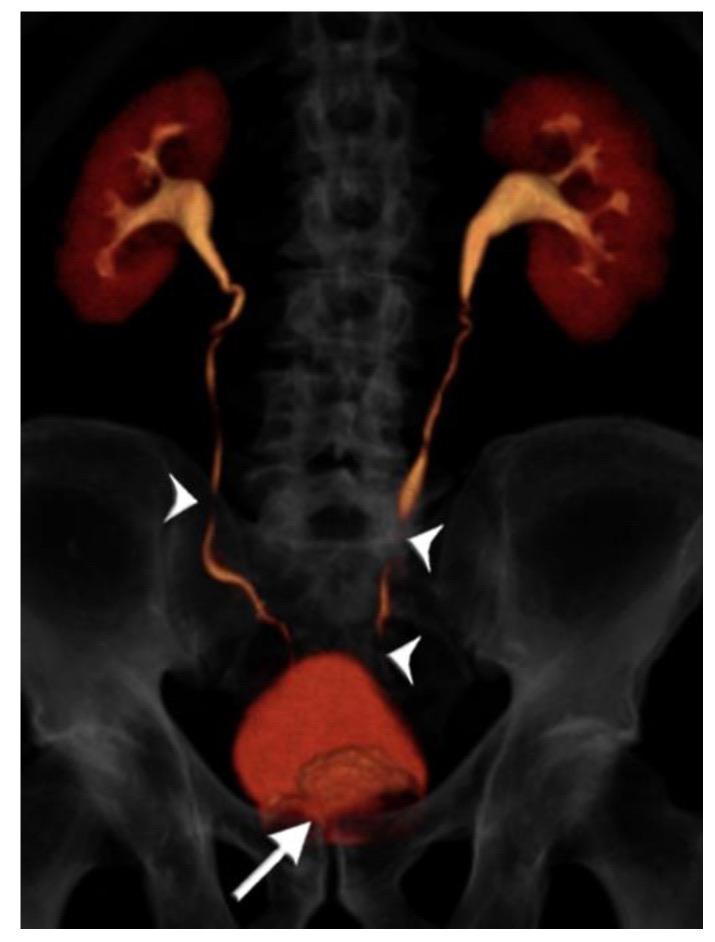
Volume-rendered excretory phase of a single-bolus CT urogram in a patient with gross hematuria. The ureters are almost completely opacified apart from very short unopacified segments (arrowheads), with no upstream hydroureteronephrosis, and image quality was judged adequate. An enlarged prostate indents the bladder base (arrow). Total table time was 11 min and the dose-length product 870 mGy·cm. From Morrison N, Bryden S, Costa AF. Tomography. 2021;7(2):210–218, Figure 4 (CC BY).[3]
Dose is protocol-dependent. Scan length, patient size, scanner settings and repeat phases change exposure materially. The ESUR consensus proposes lower-dose acquisitions for benign indications and standard dose when malignancy is possible.[2] In a retrospective single-center comparison of 241 CTU examinations (240 assessed for scan time and repeat excretory phases), the single-bolus group aged 50 or older needed a repeat excretory phase less often (32/112, 28.6%) than the split-bolus groups aged under 50 (25/48, 52.1%) and 50 or older (37/80, 46.3%); mean scan times were 678 s, 1,046 s, and 978 s, respectively.[3] Mean dose-length product was higher in the single-bolus group (1,422 vs 1,041 and 1,137 mGy·cm); first-excretory-phase opacification category was not significantly associated with protocol group (p = 0.13).[3] Record the protocol and dose in the report for longitudinal tracking, especially in young patients and those needing serial imaging.
Provide prior studies to avoid duplicating acquisitions. Use the lowest exposure that still answers the diagnostic question. Ultrasound, MR urography or MAG3 renography may be preferable for repeated assessment in an appropriate patient.[2][7]
3. Iodinated Contrast
Renal risk and hydration
Distinguish contrast-associated AKI (temporal association) from contrast-induced AKI (causal attribution). The ACR–NKF consensus does not treat an eGFR below 30 as an absolute prohibition on a clinically necessary contrast CT.[4]
| Situation | Practical interpretation |
|---|---|
| Stable eGFR ≥30 mL/min/1.73 m² | Routine IV saline prophylaxis is not indicated for every patient. |
| eGFR 30–44 with recent AKI or other high-risk circumstances | Consider prophylaxis individually. |
| AKI or eGFR <30, not on maintenance dialysis | Discuss diagnostic benefit and alternatives; isotonic saline prophylaxis is indicated when not contraindicated by volume risk. |
| Maintenance dialysis | Do not initiate or reschedule dialysis solely to clear IV iodinated contrast; consider residual renal function and fluid burden. |
Contrast is not reduced below a diagnostic dose to create a nominally safer but nondiagnostic study.[4] Low-osmolality or iso-osmolality nonionic agents are standard. N-acetylcysteine has no supported role in prevention. In the PRESERVE randomized trial of 4,993 analyzed high-risk patients undergoing angiography, sodium bicarbonate versus saline and acetylcysteine versus placebo did not reduce the 90-day composite of death, dialysis or persistent kidney impairment, or contrast-associated AKI.[13]
Metformin and prior reactions
ACR 2026 does not require withholding metformin for IV contrast when there is no AKI and eGFR is ≥30. With AKI or severe CKD below 30, hold it at or before exposure and for 48 hours, then reassess renal function before restarting; specified arterial catheter procedures have additional considerations. FDA labeling or local policy may be more restrictive.[9]
Document the actual prior contrast reaction and agent. Shellfish or povidone-iodine allergy alone is not an iodinated-contrast allergy. For a prior immediate allergic-like reaction to IV iodinated contrast, identify the culprit agent and coordinate a different iodinated agent with radiology when feasible. The 2025 ACR–AAAAI consensus recommends against premedication after a mild reaction, allows consideration after a moderate reaction, and recommends premedication after a severe reaction when no acceptable alternative study exists; in the severe-reaction setting, perform the study in a hospital with a rapid-response team available.[27] When premedication is indicated, ACR elective regimens begin oral corticosteroids 12–13 hours before contrast, and diphenhydramine is optional; accelerated IV regimens generally require 4–5 hours, with timing coordinated with radiology and local protocol.[9] Premedication does not eliminate breakthrough reactions and should not delay an urgent diagnosis without weighing the harm of the delay. After a prior severe reaction, consider whether contrast is necessary or whether MR urography, retrograde pyelography or noncontrast CT with nuclear imaging answers the question.[9]
Acute reactions occur within an hour of injection and range from mild (injection-site pain, nausea, rash) to severe (bronchospasm, laryngeal edema, hypotension). Direct-injection reactions during a retrograde study (RUG, VCUG, retrograde pyelography) are also reported but are rare. For intravascular iodinated contrast, a prior allergic-like or unknown-type reaction to the same class raises future allergic-like reaction risk approximately fivefold; unrelated allergies raise risk twofold to threefold, and asthma also increases risk without warranting premedication on its own.[9] Observe self-limited mild reactions; offer an antiemetic for nausea or an antihistamine for symptomatic urticaria. Assess vital signs if hypotension occurs; a vasovagal reaction requiring treatment may need IV fluids and, if severe bradycardia persists, atropine. IV corticosteroids do not treat an acute contrast reaction. A severe reaction is managed as an airway–breathing–circulation emergency, and epinephrine is the treatment of choice regardless of whether the reaction is judged anaphylactic or anaphylactoid.[9][18][19]
Delayed reactions occur from one hour to about one week after injection; a pruritic rash or urticaria is the most frequent finding, though nausea, vomiting, diarrhea and hypotension can also occur. Severe delayed cutaneous reactions resembling Stevens–Johnson syndrome, toxic epidermal necrolysis or vasculitis have been reported; progressive or widespread manifestations may merit allergy or dermatology consultation.[9] In one prospective single-center comparison, a delayed reaction occurred in 14.3% of patients receiving a low-osmolar nonionic agent versus 2.5% of a non-contrast control group.[20] In a randomized, double-blind cardiac-catheterization trial of 2,001 patients, reactions before 24 hours occurred in 22.2% receiving ioxaglate, 7.6% iodixanol and 8.8% iopamidol; skin reactions after 24 hours through day 7 occurred in 4.3%, 12.2% and 4.2%, respectively.[21] A prior iodinated-contrast reaction is associated with greater delayed-reaction risk.[18] Delayed-reaction rates differed between contrast-enhanced and unenhanced CT groups and among cardiac-catheterization agents; a retrospective series of 4,875 patients recorded 52 late skin reactions that clustered seasonally and often involved sun-exposed areas.[20][21][22]
Pregnancy
Iodinated contrast crosses the placenta. After maternal intravascular administration of water-soluble iodinated contrast, ACR 2026 reports no documented neonatal hypothyroidism and advises no extra thyroid testing beyond routine newborn screening.[9]
Sequencing with MAG3
The SNMMI/EANM procedure standard does not set a universal wait after iodinated contrast or a mandatory CTU-first sequence. Supply recent imaging, kidney-function changes and medication history to nuclear medicine, and schedule according to the diagnostic question and the department's protocol. Acute renal deterioration after any event may affect interpretation.[8]
4. Trauma: CT, Cystography and Urethrography Have Different Roles
Resuscitation takes priority. CT is appropriate when the trauma patient's condition allows it; hemodynamic instability is not an instruction to delay definitive hemorrhage management for a CT scan.[5]
Pelvic fracture, hematoma or superior bladder displacement can raise concern for urethral injury. Blood at the meatus after pelvic trauma is an indication for RUG . Repeated blind catheter attempts are avoided; urinary drainage and any realignment decision depend on the injury and the treating trauma or urology team.[5]
What CT shows in pelvic fracture urethral injury
CT is obtained for the fracture and hemorrhage, and it adds information relevant to later reconstruction.[5][14]
- Ring pattern. Fractures that disrupt the posterior pelvic ring, and displaced or vertically unstable patterns (for example Tile C or Young-Burgess APC-III and vertical shear), are associated with posterior urethral injury more often than isolated anterior arch fractures.
- Bladder and hematoma. In pelvic fracture, cranial bladder displacement by a large hematoma (the “pie-in-the-sky” appearance) can accompany an intact or injured urethra and prompts RUG when urethral injury is suspected. For confirmed complete urethral injury in polytrauma, establish prompt suprapubic drainage; avoid blind transurethral catheterization.[5][14]
- Hematoma. Volume, distribution and active extravasation (a contrast blush on the arterial phase) direct hemorrhage control. A large posterior hematoma may indicate denser scar at later perineal surgery.
- Bone fragments. Retropubic fragments can injure the bladder neck or urethra, can be incorporated into the obliterative scar, and can obscure urethrographic anatomy.
- Associated injuries. Bladder laceration (intraperitoneal or extraperitoneal, shown by retrograde CT cystography) and rectal injury (wall defect, perirectal stranding, free air) change the operative plan. Unrecognized rectal injury complicates urethroplasty and diversion decisions.
- Findings by Goldman type. In a series correlating CT with urethrography-proven injury, elevation of the prostatic apex was specific for type I, extravasation above the urogenital diaphragm for type II, and extravasation below the urogenital diaphragm for type III; extraperitoneal bladder rupture with periurethral extravasation raised concern for type IV/IVA. Five additional soft-tissue signs were more common with an associated urethral injury than with an uncomplicated pelvic fracture: distortion or obscuration of the urogenital diaphragm fat plane, ischiocavernosus muscle hematoma, distortion or obscuration of the prostatic contour, distortion or obscuration of the bulbocavernosus muscle, and obturator internus muscle hematoma.[16]
Planning delayed urethroplasty. For a posterior urethral distraction defect, coronal and sagittal reconstructions show the position of the fractured pubic arch and prostate, the thickness of the inferior pubic arch, retropubic fibrosis, and the integrity of the ischiopubic rami and levator ani. Marked posterior displacement of the arch may lead to inferior pubectomy, and very long defects may need an abdominoperineal approach.
In renal trauma, EAU 2026 strongly recommends multiphase CT for visible hematuria, nonvisible hematuria with hypotension, rapid deceleration or significant associated injuries, penetrating trauma and clinical signs of renal injury. It also strongly recommends repeat imaging after high-grade or penetrating injury or with fever, worsening flank pain or a falling hematocrit.[6] The arterial phase assesses vascular injury and active extravasation, the nephrographic phase parenchymal injury, and a five-minute delayed phase the collecting system and ureter. The delayed phase can be unreliable in hypovolemic patients and is often omitted in whole-body protocols; EAU recommends adding it when injury is not fully evaluated. When ureteral injury is suspected, EAU calls CT urography the examination of choice: delayed contrast extravasation is the hallmark, but hydronephrosis, ascites or urinoma may be the only signs, and retrograde or antegrade urography confirms unclear cases. One-shot IVP is unreliable (negative in up to 60%). For a male urethral injury, EAU names RUG the standard early test (20 to 30 mL of contrast with the meatus occluded, 30-degree oblique).[6]
For suspected bladder injury, actively fill retrograde by gravity with dilute water-soluble contrast using an appropriate cystography protocol. EAU strongly recommends cystography for visible hematuria with pelvic fracture and active retrograde filling with 300–350 mL of dilute contrast (LE 3) for adult trauma evaluation when tolerated; fresh repairs, small bladders and children need an individualized volume.[6] Passive excretion from IV contrast cannot provide an adequate negative study. Conventional and CT cystography have comparable diagnostic performance when properly performed; CT also shows surrounding injuries.[6][5]
CT retrograde urethrography
CT-RUG combines retrograde urethral contrast injection with CT acquisition during or immediately after injection, giving cross-sectional and 3D views of the urethra and periurethral tissue. The urologist manages injection and urethral filling in the CT suite while radiology controls acquisition timing, so the two teams agree on technique, contrast dilution and reconstructions beforehand.
It has been described for problems that fluoroscopic RUG and VCUG leave unresolved:
- spongiofibrosis extent and periurethral tissue characterization
- false passages, distinguishing the true lumen from a periurethral tract
- complex rectourethral or urethrocutaneous fistula anatomy and the tissue between the structures
- recurrent stricture after prior urethroplasty with distorted anatomy
- posterior urethral distraction defects in which prostate position and defect length are unclear
- urethral duplication or complex congenital anomalies
The technique is not standardized for acquisition, contrast concentration or reporting, the evidence is limited, and it exposes the patient to more radiation than fluoroscopic RUG. It is a problem-solving study. MRI can add information in selected posterior stenoses and complex periurethral disease.[11]
Comparison With Other Modalities
| Feature | CTU | MAG3 renography | MR urography | Retrograde pyelography |
|---|---|---|---|---|
| Anatomic detail | Excellent, 3D | Functional map only | Excellent, best soft-tissue contrast | Collecting system only |
| Function and drainage | None | Split function and drainage kinetics | Limited | None |
| Radiation | Yes | Yes, low relative to CT | None | Yes, fluoroscopy |
| Urothelial lesions | Filling defects and wall thickening | Cannot detect | Wall thickening and mass | Filling defects; ureteroscopy allows biopsy |
| Stones | Excellent on unenhanced CT | Poor | Poor | Radiolucent stones may appear as filling defects.[24] |
| UPJ crossing vessel | Good with arterial phase | Cannot detect | Good with MR angiography | Cannot detect |
| Retroperitoneal fibrosis | Good | Cannot characterize | Very good | Suggests medial deviation |
| Effect of poor renal function | Contrast decision; poor excretion limits opacification | Curve quality falls | Gadolinium considerations | Unaffected |
Qualitative ratings summarize the general roles described above. Local availability and expertise decide the choice.
5. Retroperitoneal Fibrosis
Retroperitoneal fibrosis is a fibro-inflammatory process that forms a soft-tissue mantle around the infrarenal aorta and IVC and encases the ureters, and CT or MRI shows it. The typical CT appearance is homogeneous soft tissue around the aorta, most often in the lower lumbar segments, with ureteral encasement, hydronephrosis and medial deviation of the mid-ureters. In a retrospective CT comparison, medial ureteral bowing occurred in 15/19 RPF cases and 1/23 retroperitoneal lymphoma cases.[30] Enhancement varies with activity: active inflammatory disease enhances, and chronic fibrotic tissue enhances little.
Imaging distribution, clinical history and, when indicated, biopsy help distinguish idiopathic or IgG4-related disease from malignant and other secondary causes. FDG-PET/CT shows metabolic activity of the mantle; in a retrospective 50-patient RPF cohort, PET measures decreased between baseline and first follow-up, and 36 patients underwent second follow-up imaging. The investigators reported eight progression cases at second follow-up, with PET measures differing by progression status.[25] Medical therapy, drainage and ureterolysis are complementary options selected according to the cause and renal threat.[12]
Before ureterolysis, CT maps the level and length of encasement, laterality and the collecting system after stenting; ureteral tissue perfusion and whether a mobile omental flap reaches the ureter are assessed during surgery.[28][29]
See ureterolysis and ureteral stricture for treatment.
6. Follow-up and Reporting
No universal schedule applies for CTU after urethroplasty or a fixed wait for a suspected leak. New fever, pain, renal deterioration or concerning drain output calls for timely clinical assessment and the study best suited to the suspected complication. Stable postoperative surveillance is procedure- and risk-specific.[5][8]
After ureteral reconstruction, pyeloplasty or diversion, CTU with an excretory phase can show extravasation along the ureter or around the renal pelvis, a perinephric urinoma that accumulates contrast over time, its size and communication with the collecting system, and the position of drains and stents. Comparing density before and after contrast helps separate urinoma from hematoma or lymphocele. Recurrent hydronephrosis after reconstruction is evaluated for an anastomotic stricture: an abrupt caliber change at the anastomosis, stricture length, periureteral scar and upstream dilation. Early postoperative studies can show edema, stent-related change and dilation from manipulation that overstate obstruction, so anatomic assessment of an anastomosis is usually more reliable after the stent is out and edema has settled.
Hydronephrosis that predated urethroplasty because of outlet obstruction is expected to improve after successful reconstruction, and the time course varies with severity and duration. Persistent mild dilatation with a normal MAG3 drainage curve represents residual dilation, not ongoing obstruction. CTU is preferred when the question is anatomic, for example persistent hydronephrosis after a technically successful urethroplasty that suggests an independent ureteral or UPJ process. MAG3 is preferred for functional questions and for serial surveillance, because it avoids repeated CT exposure.[8]
A useful report identifies the indication, acquisitions and contrast, limitations of opacification, lesion or transition-point location, upstream findings, leaks or collections, stent or drain position and comparison with prior studies. Separate observed anatomy from inference about function or causation. If uncertainty will affect reconstruction, state which additional study could resolve it.[2][8]
References
1. AUA/SUFU. Microhematuria guideline, amended 2025. Guideline. 2025 amendment. Accessed September 11, 2026.
2. Van Der Molen AJ, Cowan NC, Mueller-Lisse UG, et al. CT urography: definition, indications and techniques. A guideline for clinical practice. Eur Radiol. 2008;18:4–17. doi:10.1007/s00330-007-0792-x. Expert technical consensus; PubMed.
3. Morrison N, Bryden S, Costa AF. Split vs. single bolus CT urography: comparison of scan time, image quality and radiation dose. Tomography. 2021;7:210–218. doi:10.3390/tomography7020019. Full study.
4. Davenport MS, Perazella MA, Yee J, et al. Use of intravenous iodinated contrast media in patients with kidney disease: ACR–NKF consensus statements. Radiology. 2020;294:660–668. doi:10.1148/radiol.2019192094. Society PDF.
5. Morey AF, Broghammer JA, Hollowell CMP, et al. Urotrauma Guideline 2020: AUA Guideline. J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408. Full guideline, published 2014; amended April 2017 and August 2020.
6. Waterloos M, Campos-Juanatey F, Hallscheidt P, et al. EAU Guidelines on Urological Trauma. Limited update, March 2026. Sections 4.1.2.b (renal imaging), 4.2.2.b (ureteral imaging), 4.3.3.c (bladder imaging) and 4.4.2.b (urethrography). Guideline. Accessed September 11, 2026.
7. EAU. Urolithiasis: diagnostic imaging. 2026 (limited update, March 2026), section 3.3.1.a. Guideline. Accessed September 11, 2026.
8. Taylor AT, Brandon DC, de Palma D, et al. SNMMI/EANM procedure standard for diuretic renal scintigraphy in adults with suspected upper urinary tract obstruction. Semin Nucl Med. 2018;48:377–390. doi:10.1053/j.semnuclmed.2018.02.010. Full guideline.
9. ACR. Manual on Contrast Media. 2026. Chapters on metformin and patient selection. Manual and updates. Accessed September 11, 2026.
10. EAU. Upper Urinary Tract Urothelial Cell Carcinoma: diagnosis. 2026 (limited text update, March 2026), sections 5.2 and 5.7. Guideline. Accessed September 11, 2026.
11. EAU. Urethral Strictures: diagnostic evaluation. 2026. Guideline. Accessed September 11, 2026.
12. Kermani TA, Crowson CS, Achenbach SJ, Luthra HS. Idiopathic retroperitoneal fibrosis: a retrospective review of clinical presentation, treatment, and outcomes. Mayo Clin Proc. 2011;86:297–303. Primary cohort. doi:10.4065/mcp.2010.0663
13. Weisbord SD, Gallagher M, Jneid H, et al. Outcomes after angiography with sodium bicarbonate and acetylcysteine. N Engl J Med. 2018;378:603–614. doi:10.1056/NEJMoa1710933. PubMed.
14. Mundy AR, Andrich DE. Urethral trauma. Part I: introduction, history, anatomy, pathology, assessment and emergency management. BJU Int. 2011;108(3):310–327. doi:10.1111/j.1464-410X.2011.10339.x. PubMed.
15. Houat AP, Guimarães CTS, Takahashi MS, et al. Congenital anomalies of the upper urinary tract: a comprehensive review. Radiographics. 2021;41(2):462–486. doi:10.1148/rg.2021200078
16. Ali M, Safriel Y, Sclafani SJ, Schulze R. CT signs of urethral injury. Radiographics. 2003;23(4):951–963. doi:10.1148/rg.234025097
17. Tonolini M, Bianco R. Multidetector CT cystography for imaging colovesical fistulas and iatrogenic bladder leaks. Insights Imaging. 2012;3(2):181–187. doi:10.1007/s13244-011-0145-9
18. Pasternak JJ, Williamson EE. Clinical pharmacology, uses, and adverse reactions of iodinated contrast agents: a primer for the non-radiologist. Mayo Clin Proc. 2012;87(4):390–402. doi:10.1016/j.mayocp.2012.01.012
19. Kemp SF, Lockey RF, Simons FE; World Allergy Organization ad hoc Committee on Epinephrine in Anaphylaxis. Epinephrine: the drug of choice for anaphylaxis. A statement of the World Allergy Organization. Allergy. 2008;63(8):1061–1070. doi:10.1111/j.1398-9995.2008.01733.x
20. Loh S, Bagheri S, Katzberg RW, Fung MA, Li CS. Delayed adverse reaction to contrast-enhanced CT: a prospective single-center study comparison to control group without enhancement. Radiology. 2010;255(3):764–771. doi:10.1148/radiol.10091848
21. Sutton AG, Finn P, Grech ED, et al. Early and late reactions after the use of iopamidol 340, ioxaglate 320, and iodixanol 320 in cardiac catheterization. Am Heart J. 2001;141(4):677–683. doi:10.1067/mhj.2001.113570
22. Mikkonen R, Vehmas T, Granlund H, Kivisaari L. Seasonal variation in the occurrence of late adverse skin reactions to iodine-based contrast media. Acta Radiol. 2000;41(4):390–393. doi:10.1080/028418500127345532
23. Coleman JA, Clark PE, Bixler BR, et al. Diagnosis and Management of Non-Metastatic Upper Tract Urothelial Carcinoma: AUA/SUO Guideline. J Urol. 2023;209(6):1071-1081. doi:10.1097/JU.0000000000003480
24. Adhoni MZU, Nagle A, Ali Z. "Radiolucent matrix stones in a transplanted kidney: a case report." Cureus. 2023;15(4):e38280. doi:10.7759/cureus.38280
25. Bayerl C, Kaufmann J, Metzger G, et al. "[18F]FDG PET/CT for treatment monitoring and prediction of progression in retroperitoneal fibrosis." Eur J Nucl Med Mol Imaging. 2026;53:1258–1269. doi:10.1007/s00259-025-07479-6
26. El-Azab AS, Abolella HA, Farouk M. "Update on vesicovaginal fistula: A systematic review." Arab J Urol. 2019;17(1):61–68. doi:10.1080/2090598X.2019.1590033
27. Wang CL, Ramsey A, Lang D, et al. "Management and Prevention of Hypersensitivity Reactions to Radiocontrast Media: A Consensus Statement from the American College of Radiology and the American Academy of Allergy, Asthma & Immunology." Radiology. 2025;315(2):e240100. doi:10.1148/radiol.240100
28. Hebert KJ, Bearrick E, Anderson KT, Viers BR. "High Rates of Discordant Ureteral Perfusion During Open Ureteral Reconstruction With Indocyanine Green: Does Near-Infrared Fluorescence Imaging Change Management or Stricture Outcomes?" Urology. 2024;190:117–122. doi:10.1016/j.urology.2024.04.055
29. Carletti F, Turcan A, Tamborino F, et al. "Single-port robot-assisted ureterolysis for retroperitoneal fibrosis: A less invasive path to functional recovery." BJUI Compass. 2026;7(5):e70218. doi:10.1002/bco2.70218
30. Zhang S, Chen M, Li CM, Song GD, Liu Y. "Differentiation of lymphoma presenting as retroperitoneal mass and retroperitoneal fibrosis: Evaluation with multidetector-row computed tomography." Chin Med J (Engl). 2017;130(6):691–697. doi:10.4103/0366-6999.201606