Cystography
Retrograde cystography evaluates bladder integrity; voiding cystourethrography (VCUG) adds urethral and reflux assessment. CT and conventional cystography are both suitable for suspected bladder rupture when the bladder is adequately filled. EAU summarizes their diagnostic performance as comparable: sensitivity approximately 90–95%, specificity 100%.[23]
See also: RUG & VCUG for urethral imaging and CT Urogram for upper-tract assessment.
Choosing the study
| Study | Main question | Practical distinction |
|---|---|---|
| CT cystography | Is the bladder leaking, and where does contrast travel? | Convenient during trauma CT; provides cross-sectional detail of the pelvis and associated injuries and better identifies bladder-neck injury, intravesical bone fragments, and concomitant abdominal injuries than conventional cystography.[23] |
| Conventional cystography | Is the bladder leaking during retrograde filling or after drainage? | Useful for initial assessment or follow-up; allows real-time observation and targeted projections |
| Fluoroscopic VCUG | Is there reflux, a bladder/urethral abnormality, or an abnormal voiding outlet? | Requires filling and voiding images; remains a reference examination for reflux grading and urethral anatomy |
| Radionuclide cystography | Does known reflux persist? | Sensitive surveillance option with limited anatomic detail; radiation depends on the protocol and comparator |
| Contrast-enhanced voiding urosonography (ceVUS) | Is there vesicoureteral reflux? | Radiation-free ultrasound alternative where expertise is available; select the study according to whether detailed urethral evaluation is also needed |
A low-dose conventional examination may answer a follow-up leak question without repeating a pelvic CT. Neither a routine contrast-enhanced abdominal CT nor its excretory phase substitutes for a properly performed retrograde cystogram.[2][4] For suspected bladder injury after pelvic surgery, EAU strongly recommends postoperative cystography; direct inspection or cystoscopy evaluates a suspected injury during the operation.[23]
VCUG images the bladder during filling and emptying, the urethra during voiding, and refluxing upper tracts when present. Reflux grade is only one factor in management; age, febrile infections, renal findings and bladder and bowel dysfunction also matter.[7][8]
ceVUS is an established option. Lumason has a US intravesical indication for evaluating suspected or known VUR in children. It still requires catheterization, label-specified contrast preparation, an experienced operator and the local pediatric imaging protocol. Lumason is contraindicated with hypersensitivity to sulfur hexafluoride lipid microspheres or components including polyethylene glycol; trained personnel and resuscitation equipment must be readily available.[25]
Contrast and filling technique
Contrast agents
Use a water-soluble agent and dilution appropriate to the examination. Examples of products labeled for retrograde cystography include:
- Cystografin contains diatrizoate meglumine 30%; a separate Cystografin Dilute 18% product is available.[9][10] These are retrograde preparations, not intravenous products. Cystografin is contraindicated with hypersensitivity to diatrizoate salts, and its label calls for caution during active urinary infection.[9][10]
- Cysto-Conray II: iothalamate meglumine 17.2%, with administration volume adapted to age and bladder capacity. This retrograde preparation must not be administered intravascularly or intrathecally.[11]
Product concentration, instilled volume and CT dilution are different quantities. Follow the radiology protocol rather than applying a manufacturer's maximum volume to every patient. Use sterile catheterization and avoid excessive instillation pressure.[9][11]
Adult trauma examination
- Establish safe bladder access; investigate suspected urethral injury before instrumentation when indicated.
- Instill dilute contrast retrograde by gravity. EAU specifies retrograde filling with 300–350 mL of dilute contrast.[23] The ACS 2025 guideline likewise sets a minimum of 300 mL, or until the patient reaches discomfort or contrast stops flowing, and specifies dilute contrast of about 2–5 g iodine/100 mL for CT cystography (for example, 50 mL iohexol in 500 mL saline) against about 8–25 g iodine/100 mL for conventional cystography.[1] AUA describes gravity filling to at least 300 mL or patient tolerance (Statement 14a discussion).[13] Record the actual volume and any limitation; an underfilled examination may miss a tear.[23][1][13]
- CT cystography obtains pelvic images with the bladder distended. Additional intravenous contrast is unnecessary for the cystographic component, although other trauma questions may require it.
- Conventional cystography includes adequately filled anteroposterior and bilateral oblique views and a post-drainage image, with a lateral view when concern persists without a visible leak.[1] Drainage can reveal leakage obscured by the contrast-filled bladder. Routine post-drainage CT is generally unnecessary.[5]
An adult trauma volume is not forced into a child, a painful low-capacity bladder, a fresh repair or an augmented reservoir. Agree on a tailored filling endpoint with the treating team. Clamping a catheter to collect renally excreted contrast does not provide a reliable trauma cystogram.[4][5][13]
Children
Use a pediatric protocol with low-dose pulsed fluoroscopy or an appropriate ultrasound technique. Age formulas such as (age + 2) × 30 mL are estimates, not targets that must be reached.[29] Bael and colleagues' analysis of 386 children with grade III–IV VUR found a nonlinear age-capacity relationship and wide reference ranges.[12] Cyclic filling can improve reflux detection in selected infants; avoid overdistension.[6]
Trauma indications and interpretation
In a stable patient, visible hematuria with pelvic fracture requires retrograde cystography .[13] Under EAU guidance, microscopic hematuria with pelvic-circle displacement >1 cm, pubic-symphysis diastasis >1 cm, or posterior urethral injury is an absolute indication for bladder imaging.[23] Penetrating pelvic injury and other clinical indicators may also warrant evaluation.[23]
In stable patients, AUA also recommends retrograde cystography for gross hematuria with a concerning mechanism or pelvic-ring fracture with clinical indicators of rupture (Statement 14b; Recommendation, Grade C).[13] Concerning findings include inability to void, suprapubic pain, abdominal distension, unexplained low urine output, urinary ascites or otherwise unexplained pelvic fluid.[13] A cystogram does not evaluate renal or ureteral injury adequately; choose upper-tract imaging separately.[4]
If pelvic bleeding is amenable to angioembolization and bladder injury is suspected, postpone cystography until the angiographic procedure is complete because extravasated cystographic contrast can impair interpretation (WSES-AAST, GoR 2A). Hemorrhage control takes priority.[4]
| Pattern | Typical contrast appearance | Management implication in blunt trauma |
|---|---|---|
| Extraperitoneal | Perivesical leakage tracking through pelvic tissue planes | Uncomplicated injuries usually receive catheter drainage; bladder-neck involvement, bone fragments in the bladder wall, rectal/vaginal injury or bladder-wall entrapment require surgical repair |
| Intraperitoneal | Contrast around bowel loops or freely within the peritoneal cavity | Surgical exploration and repair |
| Combined | Both patterns | Surgical repair |
| Contusion | No full-thickness leak demonstrated | — |
In a retrospective registry of 140 blunt bladder ruptures, 82 (58.6%) were extraperitoneal, 49 (35.0%) intraperitoneal and 9 (6.4%) combined.[21]
ACS describes two-layer repair as standard practice; EAU notes that superiority over a watertight single-layer closure has not been demonstrated. Selected small uncomplicated endoscopic intraperitoneal perforations have a different management pathway from blunt traumatic rupture.[1][23]
Technical pitfalls
| Pitfall | Consequence | Response |
|---|---|---|
| Passive filling from IV contrast with the catheter clamped | Insufficient intravesical distension; false-negative study | Fill retrograde through the catheter |
| Underfilling | A small perforation is missed | Fill to tolerated distension and record the volume |
| No post-drainage image on conventional cystography | Leakage hidden by the contrast-filled bladder | Obtain a post-drainage film |
| Posterior-wall injury on an AP view | Missed leak; a lateral view is rarely feasible with pelvic fracture | CT cystography, or oblique projections on fluoroscopy |
| Cystography before pelvic angioembolization in suspected bladder injury | Extravasated contrast may impair angiographic interpretation | Postpone cystography until angiography is complete; hemorrhage control takes priority.[4] |
| Forceful syringe instillation | Iatrogenic rupture or extension of an existing injury | Fill by gravity and stop at discomfort or reflux |
Pediatric reflux: when to image
The AAP 2025 perinatal UTD report supports risk-based lower-tract imaging:[6]
| Postnatal category | Lower-tract imaging approach |
|---|---|
| UTD P1 | No routine VCUG/ceVUS or prophylactic antibiotics; repeat ultrasound in 3–6 months |
| UTD P2 | Individualize VCUG/ceVUS and prophylaxis; repeat ultrasound in 1–3 months |
| UTD P3 | Recommend VCUG/ceVUS, prophylaxis and functional assessment; repeat ultrasound at 1 month |
For ureteral dilation ≥7 mm, the AAP report recommends VCUG or ceVUS and antibiotic prophylaxis. Febrile UTI in a child with known UTD also prompts reflux evaluation. Suspected neonatal bladder outlet obstruction requires prompt specialist consultation, bladder decompression, appropriate imaging and antibiotic prophylaxis, ideally within 48 hours of life. For P3 without suspected outlet obstruction, lower-tract imaging can occur during the birth admission or at the repeat ultrasound. When renal scintigraphy is indicated, AAP advises deferring it until 6–12 weeks of age when clinically feasible because earlier MAG3 measurements may misstate function.[6]
Outside the UTD-specific pathway, the 2026 AAP guideline conditionally suggests against routine VCUG after a first febrile UTI with normal renal-bladder ultrasound in medically noncomplex children younger than five years.[30] It conditionally suggests offering VCUG after a clinically relevant ultrasound abnormality, a second febrile UTI before age two, or a second febrile UTI at age two or older without another explanatory risk factor.[30] NICE NG224 uses age, atypical infection and ultrasound and clinical findings: infants under 6 months with atypical or recurrent UTI receive MCUG; in children 6 months to under 3 years it is not routine but may be considered with dilation, poor flow, non-E. coli infection or a family history of VUR.[24] Older children do not routinely receive MCUG solely because of recurrent UTI.[24]
For established VUR, follow-up combines ultrasound and selective repeat reflux imaging. For children older than one year with VUR, the current AUA guideline recommends ultrasonography and voiding cystography (radionuclide or low-dose fluoroscopy) every 12–24 months, with longer intervals for grades III–V, bladder and bowel dysfunction, and older age.[8] Cystography becomes optional if the child is managed by observation, and for grades I–II after one year of age. DMSA is recommended when ultrasound is abnormal, when scarring is a concern (breakthrough UTI, grades III–V) or when creatinine is elevated. After endoscopic injection the guideline recommends voiding cystography, and after any reflux surgery it sets renal ultrasound as a standard to look for obstruction.[8] Beyond these intervals, the modality depends on grade, age, bladder and bowel dysfunction, infections and whether the result would change management.
Fistulas and reconstructed bladders
Suspected fistula
Select imaging for the suspected communication and its cause. CT abdomen/pelvis helps evaluate bowel disease, abscess and malignancy in suspected colovesical fistula; cystography may provide additional tract or leak information.[16]
Melchior's 49-patient surgical series detected CVF with cystography in 5/30, CT in 25/41, and the poppy-seed test in 35/37 tested patients.[14] It does not define the tract or exclude cancer.[14] Najjar's 12-patient series likewise favored CT followed by evaluation for colonic malignancy.[15]
For suspected vesicovaginal fistula, EAU strongly recommends focused examination with direct visualization and weakly recommends cystoscopy with retrograde colored-fluid filling.[32] When diagnosis remains difficult or ureterovaginal fistula is suspected, EAU weakly recommends delayed-excretory contrast CT and/or MRI.[32] Routine VCUG is not indicated for uncomplicated recurrent UTI in women. In suspected structural disease, choose targeted imaging for the actual question rather than ordering VCUG for recurrent infection or prolapse alone.[3]
Intraoperative assessment
Direct inspection of the bladder is part of emergency laparotomy when bladder injury is suspected. Retrograde instillation of dilute dye (for example, methylene blue) through the catheter helps identify small perforations. If the defect is near the trigone, inspect the ureteric orifices for involvement.[23]
Suspected augmented-bladder perforation
New abdominal symptoms or unexplained systemic illness after augmentation require urgent urologic assessment, and a negative cystogram does not exclude perforation. Sensory impairment may blunt abdominal findings. Braverman's historical series found leakage on 12/13 cystograms, whereas Glass and Rushton's four-patient series demonstrated an abnormal cystogram in only one case despite confirmed rupture; ultrasound detected free fluid in all four.[17][19]
CT or ultrasound may reveal fluid or other complications when contrast leakage is absent. In a retrospective pediatric series, CT cystography showed extravasation in 14/19 augmented-bladder perforations; two had only unexplained pneumoperitoneum and three only moderate or large ascites.[31] Unexplained pneumoperitoneum or moderate to large ascites on CT or ultrasound warrants continued evaluation despite absent contrast leakage.[31] Persistent clinical concern, peritonitis or instability requires immediate surgical decision-making; additional imaging must not delay needed treatment. Tailor filling to reservoir anatomy and the clinical situation. A historical recommendation for maximal reservoir filling is not a mandate to pressurize a suspected perforation.[1][18][20]
Follow-up after bladder injury or repair
Guidelines differ on routine imaging after a simple repair. EAST's 2019 systematic guideline makes the following recommendations, all based on very-low-certainty evidence:[2]
| Clinical group | EAST recommendation |
|---|---|
| Simple IP or EP injury surgically repaired, without concerning symptoms | Conditionally omit routine follow-up cystography |
| Complex IP injury surgically repaired | Obtain follow-up cystography; strong recommendation |
| Simple EP injury treated with catheter drainage | Obtain follow-up cystography; strong recommendation |
The underlying cohorts had 0/175, 2/22, and 34/200 leaks, respectively.[2]
Johnsen's retrospective 140-patient series found one leak among 49 imaged patients after cystorrhaphy; 10/56 patients managed with catheter drainage had persistent extravasation, and seven of those ten required operations for related complications. Johnsen's series supports selective postoperative imaging and closer assessment after drainage-only treatment.[21]
Timing and local protocol. ACS 2025 recommends cystography for most operative repairs, beginning at least 7 days after repair and potentially 3–4 weeks for complex injury. AUA describes 2–3 weeks of drainage with cystographic confirmation of healing for uncomplicated EP injury; it advises cystography after complex repair while allowing omission after selected simple repairs (Statements 15–17 discussion).[13] EAU 2026 allows catheter removal five to ten days after simple repair in a healthy patient without cystography, plans cystography at approximately ten days for conservatively treated injuries, and advises cystography after complex repair or with impaired-healing risks.[23] Use the injury, repair, healing risks and clinical course to agree on catheter removal; document which pathway is being followed.[1][13] For persistent leakage, EAU advises cystoscopy to exclude intravesical bone fragments and repeat cystography one week later.[23]
After colovesical fistula repair, a postoperative cystogram may be reserved for a large defect or complex repair; the supporting 2025 Pau study was retrospective, with only 18 postoperative cystograms.[22] After vesicovaginal fistula repair, a cystogram before catheter removal can theoretically miss a persistent fistula without a voiding phase or when the fistula lies at the bladder neck.[33] After augmentation or neobladder construction, the operating team's reconstruction-specific pathway determines whether and when cystography or pouchography is needed.
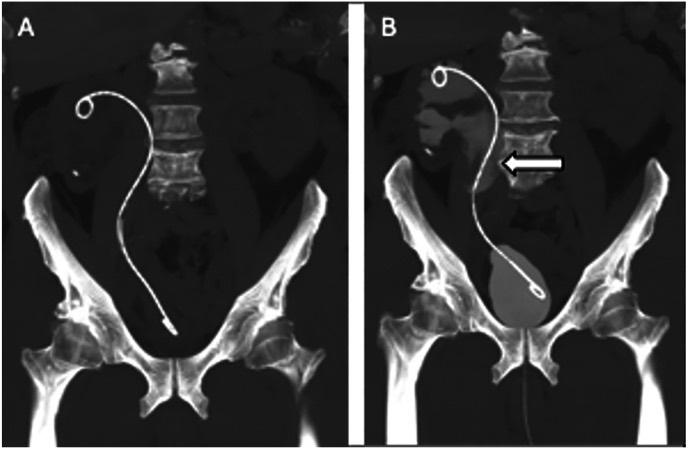
CT cystography for a postoperative leak check after ureteral reimplantation, using dilute gadolinium-based contrast in a patient with a prior severe iodinated contrast reaction. A, coronal unenhanced CT MIP before intravesical contrast; B, coronal CT cystogram MIP after intravesical dilute gadolinium-based contrast via a Foley catheter, with contrast opacifying the anastomosis (arrow) and no leak. From Holmes B, et al. Urol Case Rep. 2024;57:102856, Fig. 1 (CC BY-NC 4.0).[28]
Bladder-neck position after prostatectomy
After radical prostatectomy, cystography before catheter removal can identify a substantial vesicourethral-anastomotic leak. Men with LUTS, large prostates, prior TURP, bladder-neck reconstruction or intraoperative leakage may benefit most, but EAU states that heterogeneous data preclude a recommendation on routine use.[34] Static images can also be read for bladder-neck position. The bladder-neck-to-pubic-symphysis (BNPS) ratio — the distance from the superior pubic-symphysis border to the bladder neck, divided by total pubic-symphysis height — is lower in continent men and rises with worse post-prostatectomy incontinence. In a retrospective series of 611 consecutive RARP patients, 215 had a postoperative cystogram: mean BNPS at 3 months was 0.39 in continent men versus 0.49 in incontinent men; at 12 months it was 0.40 versus 0.60 (12-month incontinence 2.8% in the lowest BNPS tertile versus 19.4% in the highest).[26] A separate 203-patient laparoscopic/robotic cohort found a BNPS ratio above 0.59 was the only factor significantly associated with persistent incontinence at every follow-up interval to 12 months.[27]
See also
References
1. Johnsen N, Wessells H, Archer-Arroyo K, et al. Best Practices Guidelines: Management of Genitourinary Injuries. American College of Surgeons; 2025.
2. Yeung LL, McDonald AA, Como JJ, et al. "Management of blunt force bladder injuries: a practice management guideline from the Eastern Association for the Surgery of Trauma." J Trauma Acute Care Surg. 2019;86(2):326–336. doi:10.1097/TA.0000000000002132
3. Venkatesan AM, Oto A, Allen BC, et al. "ACR Appropriateness Criteria® recurrent lower urinary tract infections in females." J Am Coll Radiol. 2020;17(11S):S487–S496. doi:10.1016/j.jacr.2020.09.003
4. Coccolini F, Moore EE, Kluger Y, et al. "Kidney and uro-trauma: WSES-AAST guidelines." World J Emerg Surg. 2019;14:54. doi:10.1186/s13017-019-0274-x
5. Tominaga GT, Bernstein M, Aquino MR, et al. Best Practices Guidelines in Imaging. American College of Surgeons; 2018.
6. Herndon CDA, Otero HJ, Hains D, Sweeney RM, Lockwood GM. "Perinatal urinary tract dilation: recommendations on pre- / postnatal imaging, prophylactic antibiotics, and follow-up — clinical report." Pediatrics. 2025;156(1):e2025071814. doi:10.1542/peds.2025-071814
7. Arlen AM, Cooper CS. "New trends in voiding cystourethrography and vesicoureteral reflux: who, when, and how?" Int J Urol. 2019;26(4):440–445. doi:10.1111/iju.13915
8. Peters CA, Skoog SJ, Arant BS Jr, et al. Management and Screening of Primary Vesicoureteral Reflux in Children. American Urological Association; published 2010, amended 2017.
9. DailyMed. Cystografin: prescribing information. Label record updated November 23, 2025.
10. DailyMed. Cystografin Dilute: prescribing information. Revised June 2024; 18% diatrizoate meglumine, retrograde use.
11. DailyMed. Cysto-Conray II: prescribing information. Iothalamate meglumine 17.2%.
12. Bael AM, Lax H, Hirche H, et al. "Reference ranges for cystographic bladder capacity in children — with special attention to vesicoureteral reflux." J Urol. 2006;176(4 Pt 1):1596–1600. doi:10.1016/j.juro.2006.06.037
13. Morey AF, Broghammer JA, Hollowell CMP, et al. Urotrauma Guideline 2020: AUA Guideline. J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408. Full guideline, published 2014; amended April 2017 and August 2020.
14. Melchior S, Cudovic D, Jones J, et al. "Diagnosis and surgical management of colovesical fistulas due to sigmoid diverticulitis." J Urol. 2009;182(3):978–982. doi:10.1016/j.juro.2009.05.022
15. Najjar SF, Jamal MK, Savas JF, Miller TA. "The spectrum of colovesical fistula and diagnostic paradigm." Am J Surg. 2004;188(5):617–621. doi:10.1016/j.amjsurg.2004.08.016
16. Weinstein S, Kim DH, Fowler KJ, et al. "ACR Appropriateness Criteria® left lower quadrant pain: 2023 update." J Am Coll Radiol. 2023;20(11S):S471–S480. doi:10.1016/j.jacr.2023.08.013
17. Braverman RM, Lebowitz RL. "Perforation of the augmented urinary bladder in nine children and adolescents: importance of cystography." AJR Am J Roentgenol. 1991;157(5):1059–1063. doi:10.2214/ajr.157.5.1927793
18. Breen M, Phelps A, Estrada C, Chow JS. "The role of imaging in pediatric bladder augmentation." Pediatr Radiol. 2015;45(10):1440–1447. doi:10.1007/s00247-015-3349-1
19. Glass RB, Rushton HG. "Delayed spontaneous rupture of augmented bladder in children: diagnosis with sonography and CT." AJR Am J Roentgenol. 1992;158(4):833–835. doi:10.2214/ajr.158.4.1546602
20. Pagani JJ, Barbaric ZL, Cochran ST. "Augmentation enterocystoplasty." Radiology. 1979;131(2):321–326. doi:10.1148/131.2.321
21. Johnsen NV, Dmochowski RR, Guillamondegui OD. "Clinical utility of routine follow-up cystography in the management of traumatic bladder ruptures." Urology. 2018;113:230–234. doi:10.1016/j.urology.2017.11.011
22. Pau S, Patel A, Yap S, Eglinton T, Fischer J. "Colovesical fistula management and the role of cystoscopy: a single-institution experience." ANZ J Surg. 2025. doi:10.1111/ans.70273
23. Waterloos M, Campos-Juanatey F, Hallscheidt P, et al. EAU Guidelines on Urological Trauma. Limited update, March 2026. Section 4.3 (bladder trauma).
24. National Institute for Health and Care Excellence. Urinary tract infection in under 16s: diagnosis and management. NG224, recommendations 1.3 and tables 4–6.
25. DailyMed. Lumason: prescribing information. Revised July 2025; sections 1.3, 2.3 and 14.3.
26. Olgin G, Alsyouf M, Han D, et al. "Postoperative cystogram findings predict incontinence following robot-assisted radical prostatectomy." J Endourol. 2014;28(12):1460-3. doi:10.1089/end.2014.0236
27. Kageyama S, Yoshida T, Nagasawa M, et al. "The location of the bladder neck in postoperative cystography predicts continence convalescence after radical prostatectomy." BMC Urol. 2018;18(1):52. doi:10.1186/s12894-018-0370-3
28. Holmes B, Sanampudi S, Ananthakrishnan L. "Diagnostic CT cystography with diluted gadolinium-based contrast: a viable alternative to an iodinated contrast-based cystogram." Urol Case Rep. 2024;57:102856. doi:10.1016/j.eucr.2024.102856
29. Berger RM, Maizels M, Moran GC, Conway JJ, Firlit CF. "Bladder capacity (ounces) equals age (years) plus 2 predicts normal bladder capacity and aids in diagnosis of abnormal voiding patterns." J Urol. 1983;129(2):347–349. doi:10.1016/S0022-5347(17)52091-1
30. Alverson BK, Hains DS, Downs SM, et al. "Clinical practice guideline for the diagnosis and treatment of urinary tract infection in children from 8 days to 5 years of age." Pediatrics. 2026;158(4):e2026078565. doi:10.1542/peds.2026-078565
31. Karmazyn B, Gurram S, Marine MB, et al. "Is CT cystography an accurate study in the evaluation of spontaneous perforation of augmented bladder in children and adolescents?" J Pediatr Urol. 2015;11(5):267.e1–267.e6. doi:10.1016/j.jpurol.2015.04.024
32. European Association of Urology. EAU Guidelines on Non-neurogenic Female LUTS. Limited update, March 2026. Section 4.8.3 (urinary fistula).
33. European Association of Urology. EAU Guidelines on Non-neurogenic Female LUTS. Limited update, March 2026. Section 4.8.4.a.2 (postoperative management).
34. European Association of Urology. EAU Guidelines on Prostate Cancer. 2026. Section 6.2.2.e (postoperative considerations).