MRI in Reconstructive Urology
MRI shows the tissue around the urethra and pelvic floor, which contrast studies of the lumen do not. It can clarify periurethral and pelvic soft-tissue anatomy when examination, endoscopy, or lumen-based imaging leaves a specific reconstructive question unanswered.[1][2] The study is ordered around that question and the relevant prior operation.
MRI is used selectively for complex posterior urethral disease, female urethral diverticulum, difficult fistulas, or selected pelvic-floor and postoperative problems. The implant and contrast plan is established before scanning. Findings are interpreted alongside examination, symptoms, endoscopy, and prior imaging.[1][2][3][4]
1. Overview: What MRI Adds
| Clinical question | Useful MRI contribution | Companion evaluation |
|---|---|---|
| Posterior urethral stenosis or complex PFUI | Periurethral anatomy and associated fistula or other pathology | RUG/VCUG; selected antegrade/retrograde endoscopy |
| Female urethral diverticulum | Extent, configuration, and relationship to urethra and sphincter | Examination and urethroscopy; histology when tissue is removed |
| Selected prolapse or defecatory dysfunction | Dynamic compartment relationships | Symptoms, POP-Q examination, and bowel assessment |
| Difficult postoperative pelvic problem | Deep tissue, collection, tract, or inflammatory change | Operation/device details and targeted endoscopy or ultrasound |
MRI has four practical advantages in reconstruction. It shows soft tissue (periurethral scar, levator muscle, a diverticular sac, a fistula tract) rather than only the contrast-filled lumen. It uses no ionizing radiation. It is acquired in true multiple planes, so the urethral axis or a diverticulum can be imaged along its own orientation. Dynamic, diffusion-weighted and contrast-enhanced sequences add functional information.
2. Pelvic Fracture Urethral Injury (PFUI)
When MRI helps
Combined RUG and VCUG remain central for a nearly obliterated or obliterated posterior urethra. The 2026 EAU guideline gives a Strong recommendation to consider MRI urethrography as an ancillary test in posterior stenosis; associated pathology or complex spatial anatomy may make it useful.[1]
A prospective study of 25 men with complete posterior stenosis found MRI measurements correlated more closely with operative length than conventional urethrography. Of the 25 men, 22 also underwent RUG with VCUG; mean measurement error against operative length was 0.4 ± 0.4 cm with MR urethrography and 1.4 ± 1.1 cm with RUG and VCUG (p < 0.001). The prospective study supports adjunctive MRI for posterior stenosis length.[7]
In that series the MR urethrogram was acquired after aseptic lubricant was infused through the meatus to dilate the distal urethra up to the stricture, with axial and sagittal T2 turbo spin-echo, sagittal T1 and contrast-enhanced sagittal T1 images.[7] A scar bridge between the urethral ends can appear as a low-signal band on T2, and diffusion or post-contrast sequences are sometimes added to separate fibrosis from residual lumen.
Request and reporting checklist
Request a dedicated urethral or pelvic protocol and provide the trauma, prior repair, catheter, and endoscopy history. Thin-section T2 images in sagittal, axial and coronal planes aligned to the relevant anatomy are useful; contrast and additional sequences depend on the question. A phased-array pelvic surface coil is the usual choice. The bladder is moderately filled, and a clamped suprapubic catheter can help outline the bladder neck. Document the following:
- the visible ends of the urethra, the estimated intervening distance and the plane of measurement;
- prostatic position, including superior or posterior displacement;
- the angle between the urethral remnants and the bladder neck axis;
- any low-signal band that could represent a scar bridge;
- the pubic symphysis (diastasis, marrow edema or osteitis on fluid-sensitive images);
- the bladder neck appearance, and associated abnormalities. If the proximal lumen or bladder neck is inadequately assessed, the report says so.[1][7]
Operative limit. Gap length and stump geometry inform planning; neither a 3-cm gap nor a 30-degree angle alone mandates pubectomy or an abdominal approach.
| Feature | RUG with VCUG | MRI |
|---|---|---|
| Luminal detail and dynamic filling | Yes | Limited |
| Gap length | Underestimated in some series; depends on filling | Closer to operative length in a small series[7] |
| Prostatic position, bladder neck, symphysis | Limited | Shown directly |
| Fibrosis and associated pathology | Not shown | Shown |
| Radiation | Yes | No |
| Availability and cost | More widely available; lower cost[1] | Center-dependent; higher |
3. Dynamic (Defecation) MRI for Pelvic Organ Prolapse
Select the clinical question
Do not routinely obtain imaging simply to document prolapse already demonstrated on examination. When imaging is needed for complex compartment symptoms, defecatory dysfunction, or unresolved postoperative findings, MR defecography is one option; fluoroscopic and ultrasound examinations answer overlapping questions.[5][6]
Acquisition and reporting
The ESUR/ESGAR consensus recommends static images plus coached squeeze, strain, and evacuation sequences, obtained on 1.5 T or 3 T systems with a surface coil centered low on the pelvis. The patient is trained in the maneuvers beforehand. Inadequate effort or incomplete evacuation is recorded because either can conceal findings.[8]
| Element | Consensus recommendation |
|---|---|
| Bladder | Moderately filled; the patient voids about 2 hours before |
| Rectum | Ultrasound gel distension, 120–250 mL depending on the patient (larger volumes help evacuation) |
| Vagina | Gel opacification (about 20 mL) helps but did not reach consensus |
| Bowel preparation | Cleansing enema helps but did not reach consensus |
| Contrast | No oral or intravenous contrast is necessary |
| Phases | Rest, squeeze, strain and evacuation, in the sagittal plane; dynamic sequences are single-slice, fast T2 |
| Position | Supine with the knees flexed; the patient wears a pad for comfort during evacuation |
The pubococcygeal line (PCL) runs from the inferior pubic symphysis to the last coccygeal joint. Organ descent is measured perpendicular to it at rest and at maximum strain. The report states the reference line, organ landmark, phase, and displacement. A 2026 multidisciplinary expert consensus also proposes compartment-based reporting with hymenal-plane and anal-canal landmarks aligned with clinical prolapse assessment.[21] The ESUR/ESGAR grading below differs by compartment:[8]
| Finding | Grading |
|---|---|
| Bladder base or cervix/vaginal vault ("rule of three") | Graded from 1 cm below the PCL: mild 1–3 cm, moderate 3–6 cm, severe more than 6 cm. The bladder base may descend up to 1 cm below the PCL on straining in continent women, which is not reported as a cystocele. |
| Rectocele ("rule of two") | Grade I under 2 cm, grade II 2–4 cm, grade III over 4 cm. It is reported as pathological from grade II, because grade I is common in parous women. |
| Anorectal junction descent | Grade I 3–5 cm below the PCL, grade II 5 cm or more |
| Enterocele | The contents of the peritoneal sac are reported (fat, small bowel or sigmoid) |
| Intussusception | Small rectal wall intussusception is a common normal finding during defecation |
Levator defects are described with the method used.
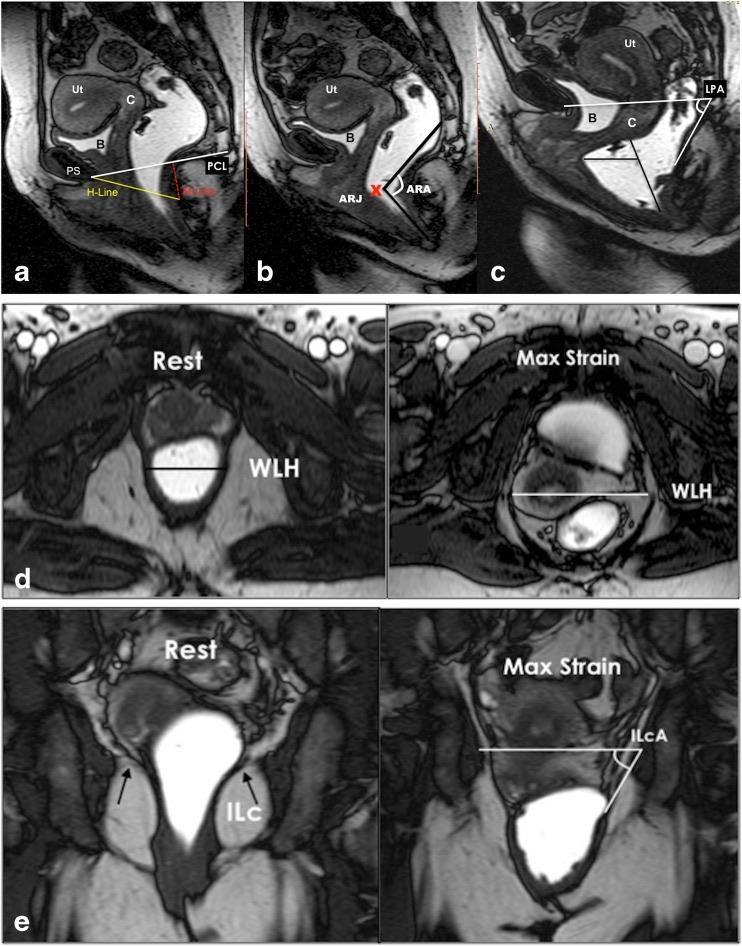
Pelvic floor relaxation and posterior compartment measurements on dynamic balanced fast field echo MRI. (a–c) Midsagittal images at rest (a), mild strain (b) and maximum strain (c). (a) The H-line runs from the inferior pubic symphysis to the anorectal junction; the M-line is dropped perpendicular from the pubococcygeal line (PCL) to the posterior end of the H-line. (b) The anorectal angle (ARA) at the anorectal junction (ARJ), between the posterior rectal border and the anal canal axis. (c) Rectocele measurement: a line along the anterior wall of the anal canal is extended upward, and an anterior rectal bulge of more than 2 cm beyond it is a rectocele; the levator plate angle (LPA) lies between the levator plate and the PCL. (d) Axial images at rest and maximum strain: width of the levator hiatus (WLH) between the puborectalis slings. (e) Coronal images at rest and maximum strain: iliococcygeus angle (ILcA) between the iliococcygeus muscle (ILc) and the transverse pelvic plane. B, bladder; PS, pubic symphysis; Ut, uterus. From El Sayed RF, et al. Eur Radiol. 2017;27(5):2067–2085, Fig. 4 (CC BY).[8]
Use the report to reconcile symptoms and examination, then return to the POP clinical pathway.
4. Urethral Diverticulum
Role and limits
MRI is a preferred study for characterizing female urethral diverticulum and planning surgery. Ask for location, dimensions, simple versus multiloculated or circumferential configuration, visible communication with the urethra, and relationship to the sphincter. Fluid-sensitive images can show a small lesion; the ostium is not always demonstrable. Record prior bulking injections because they can mimic pathology.[2][9]
In a single-institution study of 60 women referred for suspected diverticulum, MRI had a sensitivity and specificity of 100% for diverticula (20 patients). Of 27 diverticula in 20 women, 12 were locally round, 25 had sharp margins, 19 had high T2 signal and 16 had homogeneous T2 signal; the ostium was seen in 23 of 27 (85%). Among 60 symptomatic women, 28 had an alternative diagnosis; MRI visualized 13 of those 28 (46%). An endoluminal vaginal coil gave the best image quality in that study.[9] Thin-section T2 images in axial, sagittal and coronal planes show the sac, and post-contrast T1 and diffusion sequences are added when a solid component is suspected. A horseshoe or circumferential sac wrapping the urethra on axial images has been described as a characteristic configuration.
In Chung and colleagues' selected retrospective operated series, 10 of 41 patients who had preoperative MRI had a diagnostic or anatomical discrepancy; cancer within the diverticulum was missed in two.[10]
Complexity and surgical planning
Simple fluid is T2 bright without enhancement. Proteinaceous debris or a calculus changes the signal pattern, and a solid component that enhances on post-contrast images raises the possibility of carcinoma, which in diverticula is most often adenocarcinoma in published series. Wall thickening, debris, or an enhancing component requires clinical interpretation. Persistent clinical concern needs specialist assessment and appropriate tissue diagnosis. Do not assign a continence procedure or a biopsy route from a neck-width cutoff alone.[2][10]
Items worth reporting for surgical planning are the clock-position and level of the neck along the urethra, the relationship of the neck to the sphincter, unilateral versus horseshoe or circumferential extent, any tract to the vaginal wall, and any solid enhancing component.[2][9] A proximal neck and a neck close to the sphincter are generally regarded as raising the continence risk of excision.
5. Vesicovaginal Fistula (VVF)
Examination, bladder dye testing, and cystoscopy are often the starting point. The 2026 EAU guideline gives a Weak recommendation to perform late-excretory CT and/or MRI when the diagnosis of urinary fistula is challenging or a ureterovaginal fistula is suspected.[2] For MRI, specify whether the unanswered question concerns a tract, collection, radiation change, or adjacent organ involvement. These may require a different protocol from uncomplicated prolapse imaging.[6]
Common protocol elements are T2-weighted sagittal, axial and coronal images (the tract is T2 bright and linear), with post-contrast T1 images when inflammation or radiation change is a concern. Coronal images can show the fistula tract in relation to the bladder dome. Radiation-related fistulas may show diffuse wall thickening and fibrosis with a larger, irregular tract, which indicates poorer tissue quality. The MRI report should describe visible tract anatomy and uncertainty; cystoscopy assesses the fistula’s size and location relative to the ureteric orifices.[23] It should not assign a vaginal versus abdominal repair, interposition flap, or ureteral stent on the basis of a fixed millimeter distance alone. Examination, exposure, ureteral involvement, tissue quality, and prior treatment remain part of the VVF assessment.[2]
6. MRI Urethrogram
MRI may add information about periurethral tissues, fistulation, or complex posterior anatomy. Routine anterior strictures usually begin with conventional urethral assessment; MRI is not required simply because urethroplasty is planned.[1]
On T2 images the corpus spongiosum is bright, and fibrosis replaces that signal with lower signal. Compared with RUG, MRI can show periurethral fibrosis, the surrounding muscle and the posterior urethra, and it can be used to look for an associated mass. Sonourethrography shows spongiofibrosis in part, and RUG shows only the lumen.[1] After radical prostatectomy the anastomotic scar appears as a low-signal band, and contrast enhancement alone does not separate scar from recurrent tumor. Describe narrowing and surrounding signal abnormalities without equating MRI signal with histological fibrosis depth. There is no validated universal MRI grade in the cited guidance that independently selects endoscopic treatment, anastomotic repair, onlay, or staged reconstruction. For anterior disease, sonourethrography can be a useful adjunct, with its own limitations.[1]
In women, MRI is particularly useful when another periurethral lesion is suspected.
7. Peyronie's Disease
MRI is not a routine investigation for Peyronie's disease in current EAU guidance. History, examination, objective erection and curvature assessment, and selected ultrasound or duplex studies guide evaluation. MRI signal should not be used to label an oral treatment effective or to assign grafting from plaque length alone.[11] Where it is used, MRI has been described as showing plaque location and thickness, calcification (signal void on T1 and gradient-echo images), an hourglass waist and, on post-contrast images, enhancement that some authors associate with active disease. Scans are usually flaccid, on a small surface coil, with thin axial and sagittal T2 images and fat-suppressed T1 images. Erect curvature is documented separately by history, photographs or a supervised erection.
Use the Peyronie's treatment atlas and penile Doppler page for the relevant clinical workflow.
8. VI-RADS for Bladder Cancer
VI-RADS is a five-point MRI assessment of the likelihood of muscle invasion, using T2-weighted, diffusion-weighted, and dynamic contrast-enhanced findings in its original multiparametric protocol. The score runs from 1 (muscle invasion very unlikely) to 5 (very likely), with 3 equivocal. Bladder filling is moderate, because overdistension thins the wall and underfilling obscures wall layers.[12] A prospective 231-patient validation using a cutoff of VI-RADS ≥3 for muscle-invasive disease found 91.9% sensitivity and 91.1% specificity for discriminating non-muscle-invasive from muscle-invasive disease at initial resection (AUC 0.94); among 114 high-risk non-muscle-invasive patients, sensitivity was 85% and specificity 93.6% for identifying muscle-invasive disease at repeat resection (AUC 0.93).[15]
For reconstructive practice, its relevance is coordination with the oncology team when a known or suspected bladder lesion affects planning. Examples are an irradiated or contracted bladder before augmentation, a neurogenic bladder with hematuria, and a lesion at the bladder neck before outlet reconstruction. A low VI-RADS score is not clearance for augmentation, diversion, or treatment of an unexplained bladder abnormality.[12]
9. Upper Tract / MR Urography (MRU)
Choose the technique for the question
| Technique | What it provides | Important limit |
|---|---|---|
| Static-fluid MRU | Heavily T2-weighted depiction of urinary fluid; no injected contrast required | — |
| Excretory/functional MRU | Contrast excretion, anatomy, and protocol-dependent functional information | Depends on excretion, acquisition, processing, and local expertise |
Hydronephrosis workup depends on symptoms, prior imaging, pregnancy, renal function, and the likely cause. CT urography, MRU, and MAG3 are alternative or complementary investigations; no single study is automatically preferred for every dilated system.[13][14]
MRU avoids ionizing radiation and can be useful for complex congenital anatomy (duplicated systems, ectopic ureters, ureteroceles), for children who would otherwise accumulate radiation from repeated studies, and for planning before ureteral reconstruction. For pediatric split renal function, Tc-99m MAG3 is the most widely used clinical method, and dynamic contrast-enhanced MRU can also estimate it. In a 23-patient pediatric series, the paired methods had a small mean difference but 95% limits of agreement of −16.7 to +17.5 percentage points, limiting interchangeability near decision thresholds.[20] In one adult excretory MRU protocol, furosemide was given shortly before gadolinium to promote diuresis. Specify MRU diuretic timing relative to gadolinium and acquisition; nuclear-renography F+15 or F−15 labels require an MRU-specific definition.[19] See MAG3 renal scintigraphy for the dedicated functional evaluation.
9.5. Mesh and Sling Complications
Obtain the operative report and device information. MRI can assess deep postoperative pelvic problems; ultrasound can show many slings and accessible mesh segments. Modality selection depends on the suspected complication and local expertise. ACR rates contrast-enhanced MRI as usually appropriate for selected subacute or chronic complications after pelvic-floor repair, a different question from uncomplicated recurrent prolapse.[6]
MRI can assess deep pelvic regions beyond ultrasound: the retropubic space, obturator foramen and ischiorectal fossa, sacrocolpopexy mesh, deep abscess or osteomyelitis, and peripheral nerve involvement (MR neurography). Acute postoperative bleeding, such as a presacral hematoma, is generally evaluated with CT after sacrocolpopexy.[24] Ultrasound is often preferred for suburethral and vaginal-wall mesh, because polypropylene is echogenic and can be hard to separate from scar on MRI, and it allows real-time assessment during Valsalva. Useful MRI sequences are T2 in three planes, fat-suppressed post-contrast T1 for inflammation, and diffusion imaging for abscess. See mesh complications and removal and ultrasound.
Suspected urinary tract exposure still needs appropriate endoscopic evaluation, and vaginal exposure is assessed clinically.[5]
10. MRI Sequence Quick Reference Table
| Sequence family | Typical contribution | Interpretation boundary |
|---|---|---|
| T2-weighted anatomical imaging | Urethral, periurethral, and pelvic-floor structure | — |
| Dynamic cine/defecography | Movement during coached maneuvers | Depends on effort and the phase captured |
| DWI with ADC maps | Additional lesion characterization | — |
| Contrast-enhanced T1 imaging | Selected masses, inflammation, or postoperative complications | Use only when it adds information relevant to the question |
| Heavily T2-weighted MRU | Fluid-filled collecting system anatomy | — |
Protocols are selected with radiology for the clinical indication.[7][8][12][14]
11. Practical Protocol Tips
Implants and MRI safety
For a sacral neuromodulator or another active implanted system, identify the exact generator, leads, and any retained or abandoned components. Apply the current device-specific MR conditions, including field strength, permitted scan region, programming, and other restrictions. “MR Conditional” does not mean safe under every protocol. Unknown or unmet conditions require the radiology service's formal MR risk assessment; a prior uneventful scan is not substitute clearance.[3]
Gadolinium, renal impairment, and pregnancy
The ACR contrast manual distinguishes agents by NSF risk. When gadolinium is necessary in a patient at risk, Group II agents are preferred; renal impairment is not a blanket contraindication to every gadolinium agent. Use the lowest dose that provides a diagnostic examination under the agent's labeling and institutional protocol, rather than an automatic half-dose rule. ACR does not recommend initiating or altering dialysis solely because Group II contrast was administered.[4]
Group I gadolinium agents are contraindicated in patients on chronic dialysis or with CKD stage IV/V (eGFR <30 mL/min/1.73m²), and ACR advises avoiding them in known or suspected acute kidney injury.[4] Most reported NSF cases occurred in patients already on dialysis.[4] In an at-risk patient, use a Group II agent at the lowest dose that yields diagnostic images. For a patient already receiving hemodialysis, schedule elective enhanced MRI as close as possible before a regular session to improve clearance; do not initiate or intensify dialysis solely for Group II contrast. The ACR considers NSF risk with standard or lower doses of Group II agents very low regardless of renal function or dialysis status.[16][4][17]
During pregnancy, consider a noncontrast examination or another adequate test first. Gadolinium requires a documented judgment that the expected clinical benefit justifies the uncertain fetal risk.[4]
Separate from NSF, the FDA requires a class-wide warning and patient medication guide for gadolinium-based agents because gadolinium is retained in tissue, including the brain, for months to years after IV administration in patients with normal renal function; the long-term clinical significance is unknown. Macrocyclic agents — the class generally preferred in this population — show lower CNS deposition than linear agents.[18]
Field strength, coil and antispasmodic
A 3 T system gives higher signal-to-noise and resolution but more susceptibility artifact, so 1.5 T is often adequate for dynamic pelvic studies. A phased-array pelvic surface coil is the default. An endorectal coil deforms anatomy and is used for prostate imaging, not for PFUI or prolapse. An endoluminal vaginal coil has been reported to improve urethral and periurethral detail.[9] An antispasmodic (hyoscine butylbromide or glucagon) is sometimes given to reduce bowel motion. The AS Kalceks injectable hyoscine butylbromide label lists narrow-angle glaucoma, tachycardia, and prostate hypertrophy with urinary retention as contraindications; other cardiac disease, including arrhythmia, requires caution.[22] Select the antispasmodic with the radiology service.
Patient tolerance of the scanner
Claustrophobia in the closed bore is common and can sometimes be managed with an oral sedative; an open MRI is an alternative when sedation is not wanted or not effective, at some cost to image quality. Acoustic noise from rapid gradient switching can be considerable, particularly at 1.5 T and above, and the patient and any accompanying personnel should wear ear protection.
Request quality
Include the clinical question, symptom pattern, prior operations, device details, pregnancy status when relevant, and contrast-risk history. Let the MR service tailor bladder filling, coil, field strength, motion reduction, and rectal preparation.[3][4][8][14]
12. References
1. European Association of Urology. Urethral Strictures Guidelines: Diagnostic Evaluation. 2026. Official guideline.
2. European Association of Urology. Non-neurogenic Female LUTS Guidelines: Disease Management (urinary fistula and urethral diverticulum sections). 2026. Official guideline.
3. American College of Radiology. Manual on MR Safety. Current downloadable manual inspected September 11, 2026, including 2026 revisions; see implant identification and risk assessment. Official manual.
4. American College of Radiology. Manual on Contrast Media. 2026. NSF and pregnancy chapters. Official manual.
5. NICE. Urinary Incontinence and Pelvic Organ Prolapse in Women: Management (NG123), recommendations on imaging and mesh complications. Official recommendations. Accessed September 11, 2026.
6. American College of Radiology. ACR Appropriateness Criteria: Pelvic Floor Dysfunction in Females. Revised 2021. Official narrative and scenario-specific ratings.
7. Oh MM, Jin MH, Sung DJ, et al. Magnetic resonance urethrography to assess obliterative posterior urethral stricture: comparison to conventional retrograde urethrography with voiding cystourethrography. J Urol. 2010;183:603–607. doi:10.1016/j.juro.2009.10.016.
8. El Sayed RF, Alt CD, Maccioni F, et al. Magnetic resonance imaging of pelvic floor dysfunction—joint recommendations of the ESUR and ESGAR Pelvic Floor Working Group. Eur Radiol. 2017;27:2067–2085. doi:10.1007/s00330-016-4471-7.
9. Dwarkasing RS, Dinkelaar W, Hop WC, et al. MRI evaluation of urethral diverticula and differential diagnosis in symptomatic women. AJR Am J Roentgenol. 2011;197:676–682. doi:10.2214/AJR.10.6144.
10. Chung DE, Purohit RS, Girshman J, Blaivas JG. Urethral diverticula in women: discrepancies between magnetic resonance imaging and surgical findings. J Urol. 2010;183:2265–2269. doi:10.1016/j.juro.2010.02.016.
11. European Association of Urology. Guidelines on Sexual and Reproductive Health, Limited Update March 2026, section 8.2.2 (Peyronie's disease: diagnostic evaluation). Official guideline.
12. Panebianco V, Narumi Y, Altun E, et al. Multiparametric magnetic resonance imaging for bladder cancer: development of VI-RADS. Eur Urol. 2018;74:294–306. doi:10.1016/j.eururo.2018.04.029.
13. Expert Panel on Urological Imaging. ACR Appropriateness Criteria: Hydronephrosis on Prior Imaging—Unknown Cause. J Am Coll Radiol. 2024;21:S144–S167. doi:10.1016/j.jacr.2024.02.020.
14. Leyendecker JR, Barnes CE, Zagoria RJ. MR urography: techniques and clinical applications. Radiographics. 2008;28:23–46. doi:10.1148/rg.281075077.
15. Del Giudice F, Barchetti G, De Berardinis E, et al. Prospective assessment of Vesical Imaging Reporting and Data System (VI-RADS) and its clinical impact on the management of high-risk non-muscle-invasive bladder cancer patients candidate for repeated transurethral resection. Eur Urol. 2020;77(1):101–109. doi:10.1016/j.eururo.2019.09.029.
16. Perazella MA. Current status of gadolinium toxicity in patients with kidney disease. Clin J Am Soc Nephrol. 2009;4(2):461–469. doi:10.2215/CJN.06011108.
17. Rudnick MR, Wahba IM, Leonberg-Yoo AK. Use of gadolinium-based contrast agents in patients with severe renal impairment: absence of risk versus caution — a nephrologist's perspective. Kidney360. 2020;1(6):433–435. doi:10.34067/KID.0003022020.
18. Choi JW, Moon WJ. Gadolinium deposition in the brain: current updates. Korean J Radiol. 2019;20(1):134–147. doi:10.3348/kjr.2018.0356.
19. Sudah M, Masarwah A, Kainulainen S, et al. "Comprehensive MR Urography Protocol: Equally Good Diagnostic Performance and Enhanced Visibility of the Upper Urinary Tract Compared to Triple-Phase CT Urography." PLoS One. 2016;11(7):e0158673. doi:10.1371/journal.pone.0158673
20. Ariyurek C, Timms L, Cao X, et al. "Comparison of Dynamic Contrast-Enhanced MRI versus MAG-3 Scintigraphy for Differential Renal Function Assessment in Pediatric Patients." Pediatr Radiol. 2026. doi:10.1007/s00247-026-06624-z
21. Poncelet E, Bazot M, Mestdagh P, Chauveau B, Rousset P, Florin M. "Dynamic Pelvic Floor MRI in Pelvic Organ Prolapse: Practical Recommendations for Acquisition and Reporting." Int Urogynecol J. 2026. doi:10.1007/s00192-026-06792-4
22. AS Kalceks. "Hyoscine butylbromide 20 mg/ml solution for injection: Summary of Product Characteristics." 2025. Official product information.
23. El-Azab AS, Abolella HA, Farouk M. "Update on vesicovaginal fistula: A systematic review." Arab J Urol. 2019;17(1):61–68. doi:10.1080/2090598X.2019.1590033
24. Haouari MA, Boulay-Coletta I, Khatri G, et al. "Complications of Mesh Sacrocolpopexy and Rectopexy: Imaging Review." Radiographics. 2023;43(2):e220137. doi:10.1148/rg.220137