Penile Doppler Ultrasound & Cavernosometry
Penile Doppler ultrasound (PDUS) is the primary minimally invasive imaging modality for evaluating penile hemodynamics, used to differentiate arteriogenic, venogenic, and mixed vasculogenic erectile dysfunction (ED), as well as to assess Peyronie disease plaques, penile fracture, and priapism.[1][2] Dynamic infusion cavernosometry and cavernosography (DICC) is a specialist invasive assessment with important false-positive and interpretation limitations.[3][4]
For the broader ultrasound primer (sonourethrogram, renal US, pelvic floor US), see Ultrasound in Reconstructive Urology. For the clinical conditions evaluated by these tests, see Erectile Dysfunction and the PDE5 inhibitor, intracavernosal injection agent, and priapism management hubs.
Physiology of Erection — Basis for Hemodynamic Testing
Normal erection involves three hemodynamic phases that produce characteristic Doppler waveform changes:[5]
- Arterial inflow phase. Cavernosal artery dilation leads to increased peak systolic velocity (PSV) and high diastolic flow.
- Tumescence phase. Expanding sinusoids compress subtunical venules, leading to a progressive decrease in end-diastolic velocity (EDV).
- Full erection or rigid phase. Complete veno-occlusion leads to EDV approaching zero or becoming negative (reversed diastolic flow), and the resistive index (RI) approaches 1.0.
Waveforms must be interpreted with the erection phase, rigidity and technical quality.[5][6]
Penile Doppler Ultrasound (PDUS)
Indications
- Selected ED with suspected vascular disease or an unclear mechanism when the result would change counseling or treatment.[1][7]
- Pre-surgical evaluation for Peyronie disease (plaque characterization, calcification, vascular integrity).[8][9]
- Penile fracture with equivocal clinical findings.[10]
- Priapism. Differentiation of ischemic and non-ischemic subtypes; localization of arteriovenous fistulae.[11][12]
- Post-revascularization follow-up.[2]
- Young men with post-traumatic ED being considered for penile revascularization.[13]
Equipment and Setup
- High-frequency linear transducer (7.5–15 MHz).[2][6]
- Patient supine or in lithotomy position.
- Gray-scale, color Doppler, and spectral (pulsed-wave) Doppler modes.
- Private, comfortable environment to minimize anxiety-related sympathetic tone, which impairs smooth muscle relaxation and produces false-positive results.[1]
Vasoactive Agents and Dosing Protocols
For elective vascular ED testing, adequate cavernosal smooth-muscle relaxation is necessary. Do not administer an erectogenic drug to evaluate an already prolonged erection or an acute suspected fracture. Those examinations answer different questions.[1][2]
| Agent | Diagnostic context |
|---|---|
| Alprostadil | Caverject has a US diagnostic-adjunct indication. For diagnostic Doppler testing, its label calls for a single individualized dose producing a rigid erection using the vasculogenic/psychogenic/mixed ED titration regimen, which starts at 2.5 µg; the 1.25 µg start applies to treatment titration for purely neurogenic ED. A fixed 10–20 µg diagnostic starting dose is not the label regimen. The label contraindicates it in men prone to priapism (sickle cell disease or trait, multiple myeloma, leukemia), with penile implants, and for ED treatment with penile fibrosis or Peyronie's disease. It also advises avoiding Caverject in known cavernosal venous leakage because systemic alprostadil exposure may cause hypotension.[14] |
| Compounded combinations, such as Trimix | Used in specialist protocols; concentrations and administered doses vary. These combinations are not FDA-approved formulations[44] |
| Papaverine, with or without phentolamine | Historical/off-label intracavernosal protocols; account for prolonged erection and fibrosis risks |
Published protocols differ. Bassiem's 100-patient study began alprostadil at 5 µg, escalating to 10 and 20 µg when needed.[16] Flores describes a rigidity-based institutional protocol with redosing. Record dose, timing, stimulation and erection hardness.[1]
Use the intracavernosal-agent hub for drug preparation, contraindications and treatment dosing. Diagnostic redosing requires a trained team and a detumescence or rescue plan.
Technique — Step by Step
- Baseline scan. Gray-scale assessment of penile anatomy (cavernosal artery diameter, normal approximately 0.3–0.5 mm flaccid and typically greater than 0.7 mm in the normal erect state; tunica albuginea, septum, plaques, structural abnormalities).[2][6]
- Intracavernosal injection (ICI). For Caverject, inject into one corpus cavernosum at the right or left lateral proximal third of the penis using a 29–30-gauge half-inch needle perpendicular to the long dorsolateral penile axis. Avoid visible veins and compress the site for 5 minutes. Follow the administration instructions for other preparations.[14]
- Serial Doppler measurements. Time-based protocols commonly sample at intervals after injection; Flores uses a rigidity-based assessment. Record timing and hardness, and measure bilaterally at a standardized location.[1][6]
- Doppler parameters recorded:
- Peak systolic velocity (PSV) at peak systole.
- End-diastolic velocity (EDV) at end-diastole.
- Resistive index (RI) is (PSV − EDV) / PSV.
- Acceleration time. Time from onset of systole to peak systole.
- Cavernosal artery diameter change (pre- and post-injection).
- Angle correction. Doppler angle should be ≤ 60° for accurate velocity measurements.[6]
- Post-procedure monitoring. Confirm detumescence before discharge. A persistent penetration-rigid erection may need intracavernosal phenylephrine under the supervised rescue protocol, with blood pressure and heart-rate monitoring; refractory cases may require aspiration. Distinguish early post-injection prolonged erection from established ischemic priapism, which requires urgent treatment. See the priapism management hub.[1][11]
Sampling Location — A Critical Variable
The anatomic sampling site can materially change the result. Pagano and Stahl studied 52 men (104 cavernosal arteries): mean PSV was 52.9 cm/s at the crus, 29.5 proximally and 21.6 at mid-artery.[20] EDV differences were not significant in that cohort; another 210-patient study did find location-related EDV differences.[19][20]
The site, Doppler angle and erection phase are standardized and documented. Reference values must match the technique.
Interpretation — Normal Values and Diagnostic Criteria
EAU describes PSV >30 cm/s, EDV <3 cm/s and RI >0.8 as commonly normal. Other specialist protocols use EDV <5 cm/s and different RI thresholds.[40][1]
| Parameter | Interpretation |
|---|---|
| PSV | Low values suggest impaired arterial inflow when stimulation and technique are adequate; borderline values and incomplete relaxation require caution |
| EDV | Persistent positive flow, commonly >5 cm/s in published protocols, may suggest impaired veno-occlusion when arterial inflow and relaxation are adequate |
| RI | Derived from PSV and EDV |
| Acceleration / artery diameter | Supplementary measurements; neither an isolated timing cutoff nor post-injection diameter establishes arterial disease |
A low PSV plus positive EDV during a suboptimal erection does not reliably prove “mixed arterial and venous disease.”[4][6][22][23]
Kaufman's 743-patient DICC series reported 58.9% combined abnormalities in a detailed 124-patient single-center subgroup.[13] Pathak's 259 men were selected from 2,043 referrals for sustained rigidity and normal Doppler parameters; their age-related PSV association does not define normality for all men.[18]
Diagnostic Accuracy of PDUS for Venous Leak
Chen and colleagues compared three composite Doppler criteria with cavernosography in 54 selected men with ED, 36 of whom were cavernosography-positive. Continuous deep dorsal vein flow with peak velocity >3 cm/s plus PSV >30 and EDV >5 cm/s had reported sensitivity 91.7%, specificity 70.6% and accuracy 84.9%. Adding RI <0.89 or <0.80 increased specificity but reduced sensitivity and overall accuracy; the study did not evaluate an RI <0.75 add-on.[21] These estimates are study-specific and depend on an imperfect invasive reference standard.
Venous-compression Doppler remains investigational. Gutwein's proof-of-concept study included 40 men, but only 17 underwent compression and only 10 had CT comparison. The reported 90% versus 20% accuracy therefore comes from a small selected comparison. A nonsignificant P value of 0.096 does not establish equivalence to CT cavernosography.[24]
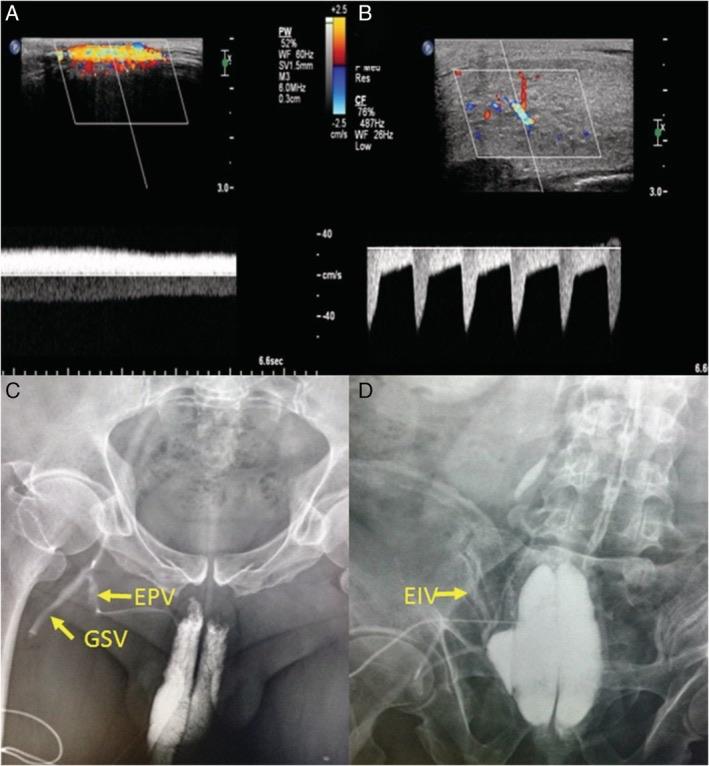
Superficial dorsal venous leak in a patient with prior segmental ligation of the deep dorsal vein. (A, B) Duplex ultrasound: continuous flow signal in the superficial dorsal vein and no signal in the deep dorsal vein; the cavernous artery spectrum showed normal PSV, EDV >7 cm/s and RI <0.80. (C, D) Cavernosography: contrast opacifies the right external pudendal vein (EPV), great saphenous vein (GSV) and external iliac vein (EIV). From Chen L, et al. J Ultrasound Med. 2019;38(10):2739–2748, Figure 7 (CC BY).[21]
PDUS in Peyronie Disease
The AUA Peyronie Disease Guideline recommends an in-office ICI test with or without duplex Doppler ultrasound prior to invasive intervention such as intralesional therapy, prosthesis placement or surgery .[8] When duplex is added, plaque size and density, calcified versus non-calcified plaque and penile vascular integrity can also be assessed.[8] PDUS provides:[9][25][26]
- Plaque characterization. Document plaque location, number, calcification and approximate size; ultrasound plaque-size measurement is inaccurate and operator-dependent, and calcification extent can affect the feasibility of the intended therapy.[46][9]
- Vascular assessment. In Masterson’s 108-man cohort, 48/87 (55%) with questionnaire-defined ED and 20/33 (61%) with severe questionnaire scores had normal Doppler parameters. Masterson's data show discordance without assigning a psychological or mechanical cause.[27]
- Fibrosis. Intracavernosal fibrosis was associated with difficulty maintaining erection in the cited cohort.[26]
- Surgical planning. PDUS helps determine whether plication, grafting, or penile prosthesis is most appropriate.[25]
PDUS in Priapism
The AUA/SMSNA permits penile duplex Doppler when ischemic versus non-ischemic priapism remains indeterminate , whereas EAU 2026 strongly recommends penile and perineal color duplex before corporal aspiration; Doppler findings include:[11][12][28][47]
- Ischemic priapism. Absent or severely diminished cavernosal artery flow; diastolic flow may be absent or reversed.[11]
- Non-ischemic priapism. Normal to high cavernosal artery velocities; turbulent flow at the site of arteriovenous fistula; color aliasing.[41] A single case report described cavernosal artery peak systolic velocity above 50 cm/sec with elevated end-diastolic velocity, arterialized draining-vein waveforms and a high-velocity, turbulent focus at the fistula itself.[41]
- Fistula localization. PDUS identifies the location and size of arterio-lacunar fistulae, guiding selective embolization planning.[11] One described acquisition scans the perineum in color-flow mode with the patient frog-legged, beginning at the proximal corpora cavernosa and moving distally, together with examination of the entire penis.[42][11]
The AUA/SMSNA Priapism Guideline states that, in diagnosed non-ischemic priapism, the clinician should consider penile duplex ultrasound to assess fistula location and size .[11] Doppler ultrasound may be used when the ischemic versus non-ischemic diagnosis is indeterminate ; it is not a routine prerequisite to urgent ischemic-priapism treatment.[48]
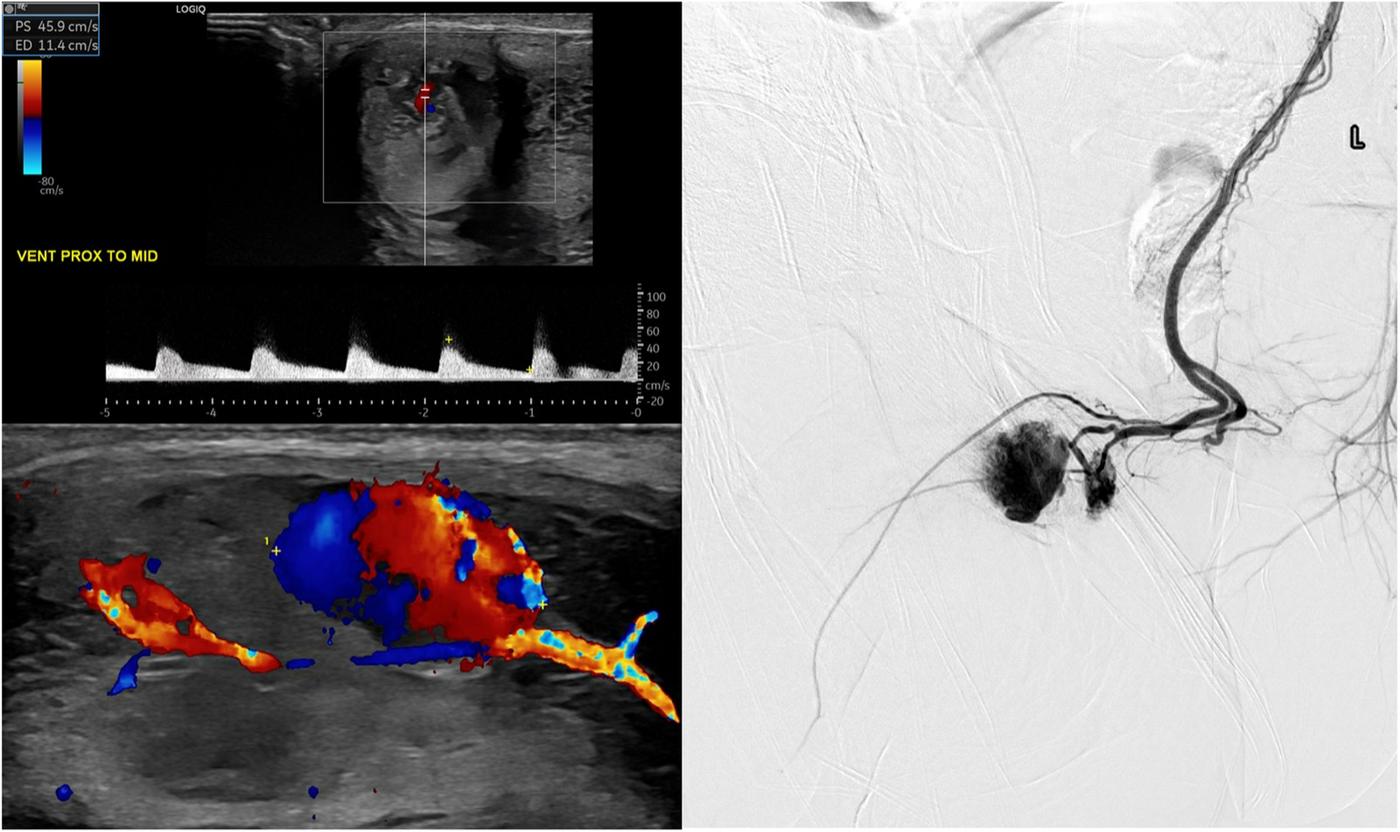
Cavernosal artery pseudoaneurysm and fistula. Top left: right cavernosal artery spectral Doppler with a low-resistance waveform (PSV 45.9 cm/s, EDV 11.4 cm/s). Bottom left: large bilobed pseudoaneurysm arising from the proximal right cavernosal artery, with the red and blue "yin-yang" color pattern. Right: selective catheter angiogram of a right accessory pudendal artery (variant anatomy) supplying the penis, with a contrast blush at the large bilobed fistula. From von Stempel C, Walkden M, Kirkham A. Int J Impot Res. 2026;38(7):541–546, Fig. 1 (CC BY).[12]
After shunting, persistent rigidity can reflect reactive hyperemia or conversion to non-ischemic priapism. For persistent erection after shunting for acute ischemic priapism, AUA/SMSNA advises corporal blood gas testing or color duplex Doppler before repeat surgery to assess cavernous oxygenation or arterial inflow ; examination alone is insufficient.[11]
The STIFF protocol (Sonography to Identify Forward Flow) was described in a single case report using glans compression during Doppler. It has not been validated to predict response or justify withholding phenylephrine; it should not delay established ischemic-priapism treatment.[29][11]
PDUS in Penile Fracture
The 2020 AUA Urotrauma Guideline permits ultrasound when penile-fracture findings are equivocal (Statement 28; Recommendation, Evidence Strength: Grade C).[10] Ultrasound can:[10][30]
- Identify tunica albuginea disruption (discontinuity of the hyperechoic tunica).
- Differentiate intracavernosal from extracavernosal hematomas.
Routine ultrasound is unnecessary when penile fracture is clinically clear; MRI is an alternative when ultrasound is equivocal or unavailable, and surgical exploration should follow if imaging is equivocal or the diagnosis remains in doubt.[10] In penile fracture with blood at the meatus, gross hematuria or inability to void, AUA Statement 29 requires evaluation for urethral injury (Standard, Grade B) by urethroscopy or retrograde urethrography.[45]
Dynamic Infusion Cavernosometry and Cavernosography (DICC)
Overview
DICC measures pressure and flow relationships and can map venous drainage. Its positive predictive value and false-positive rate in potent men remain uncertain; the 2013 SOP explicitly recognizes these limitations.[3][4] However, its use has declined substantially as venous ligation surgery has demonstrated poor long-term outcomes.[4][31]
Technique and reported parameters
Specialist protocols use separate corporal access for pressure measurement and infusion after pharmacologic relaxation. They record equilibrium pressure, flow-to-maintain (FTM), pressure decay after stopping infusion, and sometimes contrast drainage pathways. Document the infusion pressure, drug regimen, units and image timing.[4][13][17]
The historical Kaufman protocol assessed pressure decay from 150 mmHg over 30 seconds and performed cavernosography at 90 mmHg. Other studies used different target pressures. FTM values obtained at different pressures are not interchangeable. Likewise, mL/second and mL/minute differ sixtyfold.[13][31]
Gao's 147-patient observational protocol used flow expressed in mL/second and pressure-decay criteria. Its treatment-linked severity categories are not a consensus grading system. Do not use these study-specific categories as automatic indications for embolization or prosthesis placement.[3] The small controlled Lowe study found substantial overlap in flow and resistance between potent and impotent men, reinforcing the need to interpret the entire study.[32]
Limitations of DICC[4][31]
- Invasive. Requires corporal puncture, contrast injection, and fluoroscopy.
- False positives. Incomplete smooth muscle relaxation is the most common cause of false-positive results.[4][33]
- Cavernosography adds limited value. 46% of men with abnormal FTM values had a normal cavernosogram, undermining the utility of the radiographic component, particularly in low-grade venous leak.[31]
- Declining clinical relevance. As venous ligation surgery has fallen out of favor due to poor long-term outcomes, the anatomic information from cavernosography is less actionable.[31][34]
Gravity Cavernosometry
A 1991 comparison in 96 men found comparable diagnostic value for gravity and pump techniques, with practical advantages for gravity infusion. Incomplete relaxation limited both.[33]
Pudendal Arteriography
Selective internal pudendal arteriography defines arterial anatomy in selected patients being considered for penile revascularization surgery, often young men with post-traumatic ED.[13][22][40] In the multi-institutional DICC study, 169 patients underwent arteriography, and 105 proceeded to arterial bypass surgery.[13]
Advanced Imaging Modalities
| Modality | Role | Advantages | Limitations |
|---|---|---|---|
| CT cavernosography | Venous leak mapping; validation of PDUS findings | 3D anatomic detail; identifies venous drainage patterns | Radiation; contrast; invasive |
| CT angiography | Pudendal artery anatomy for embolization planning (NIP) | Vascular roadmap | Radiation; contrast |
| MRI | Penile fracture (equivocal US); tumor staging; cavernosal necrosis in ischemic priapism | Superior soft-tissue contrast; no radiation | Cost; availability; limited hemodynamic data |
| Time-resolved MRA | Arteriovenous shunting; venous leak localization | Temporal + spatial resolution; 85.2% concordance with Doppler for shunt/AVM in a selected 26-man study[35] | Requires contrast + ICI; limited availability |
| Penile angiography | Pre-revascularization arterial mapping; therapeutic embolization (NIP) | Detailed arterial mapping[22][40]; therapeutic capability | Invasive; radiation; contrast |
Sources: [12][13][24][35][36][37][11]
MRI assessment of corporal viability is a selected later question; it must not delay initial treatment of acute ischemic priapism.[11]
Doppler is the usual hemodynamic examination; MRI can answer selected structural or oncologic questions.[36]
PDUS as a Cardiovascular Risk Marker
ED is increasingly recognized as an early manifestation of systemic vascular disease. A 2026 retrospective study of 275 men used PSV <35 cm/s and found an association with estimated QRISK3 risk. It was not independent after adjustment for age and diabetes, discrimination was modest (AUC 0.60), and adding PSV barely changed the clinical model.[38]
Practical Pearls and Pitfalls
- Incomplete smooth muscle relaxation can produce false-positive results on both PDUS and DICC. Consider stimulation and supervised redosing when appropriate; respect drug-specific limits and document an indeterminate response.[1][4][33]
- Anxiety-mediated sympathetic tone can produce falsely low PSV and falsely elevated EDV. A private, comfortable environment is necessary.[1]
- Asymmetric cavernosal artery flow (significant PSV difference between right and left) suggests unilateral arterial disease.[23]
- Direct venous visualization is not the same as functional assessment. The cited 1990 study of 13 men could not visualize cavernosal venous leaks.[39]
- Peyronie patients. Questionnaire severity can reflect curvature-related intercourse difficulty as well as erectile function. Interpret discordant Doppler findings individually.[27]
Summary of Diagnostic Algorithm
- Begin with history, examination, symptom assessment and appropriate metabolic or hormonal evaluation. For predominantly vasculogenic ED, assess cardiovascular risk independently of the Doppler result; Princeton IV recommends estimating 10-year ASCVD risk.[43]
- Add PDUS when a vascular question would change management, including selected post-traumatic ED or Peyronie planning.
- Reserve DICC or cavernosography for a specific specialist question. Venous ligation is not recommended as routine ED treatment.
- Use pudendal arteriography for selected revascularization candidates.
References
1. Flores JM, West M, Mulhall JP. "Efficient Use of Penile Doppler Ultrasound for Investigating Men With Erectile Dysfunction." J Sex Med. 2024;21(8):734–739. doi:10.1093/jsxmed/qdae070
2. Kho YY, Lee SHE, Chin K, et al. "US of the Penis: Beyond Erectile Dysfunction." Radiographics. 2024;44(6):e230157. doi:10.1148/rg.230157
3. Gao QQ, Chen JH, Chen Y, Song T, Dai YT. "Dynamic Infusion Cavernosometry and Cavernosography for Classifying Venous Erectile Dysfunction and Its Significance for Individual Treatment." Chin Med J. 2019;132(4):405–410. doi:10.1097/CM9.0000000000000099
4. Glina S, Ghanem H. "SOP: Corpus Cavernosum Assessment (Cavernosography / Cavernosometry)." J Sex Med. 2013;10(1):111–114. doi:10.1111/j.1743-6109.2012.02795.x
5. Meuleman EJ, Bemelmans BL, van Asten WN, et al. "Assessment of Penile Blood Flow by Duplex Ultrasonography in 44 Men With Normal Erectile Potency in Different Phases of Erection." J Urol. 1992;147(1):51–56. doi:10.1016/s0022-5347(17)37131-8
6. Varela CG, Yeguas LAM, Rodríguez IC, Vila MDD. "Penile Doppler Ultrasound for Erectile Dysfunction: Technique and Interpretation." AJR Am J Roentgenol. 2020;214(5):1112–1121. doi:10.2214/AJR.19.22141
7. Burnett AL, Nehra A, Breau RH, et al. "Erectile Dysfunction: AUA Guideline." J Urol. 2018;200(3):633–641. doi:10.1016/j.juro.2018.05.004
8. Nehra A, Alterowitz R, Culkin DJ, et al. "Peyronie's Disease: AUA Guideline." J Urol. 2015;194(3):745–753. doi:10.1016/j.juro.2015.05.098
9. McCauley JF, Dean RC. "Diagnostic Utility of Penile Ultrasound in Peyronie's Disease." World J Urol. 2020;38(2):263–268. doi:10.1007/s00345-019-02928-y
10. Morey AF, Broghammer JA, Hollowell CMP, McKibben MJ, Souter L. "Urotrauma Guideline 2020: AUA Guideline." J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408
11. Bivalacqua TJ, Allen BK, Brock GB, et al. "The Diagnosis and Management of Recurrent Ischemic Priapism, Priapism in Sickle Cell Patients, and Non-Ischemic Priapism: An AUA/SMSNA Guideline." J Urol. 2022;208(1):43–52. doi:10.1097/JU.0000000000002767. The Diagnosis and Management of Priapism: an AUA/SMSNA Guideline (2022), unified full guideline.
12. von Stempel C, Walkden M, Kirkham A. "Review of the Role of Imaging in the Diagnosis of Priapism." Int J Impot Res. 2026;38(7):541-546. doi:10.1038/s41443-024-00928-0
13. Kaufman JM, Borges FD, Fitch WP, et al. "Evaluation of Erectile Dysfunction by Dynamic Infusion Cavernosometry and Cavernosography (DICC). Multi-Institutional Study." Urology. 1993;41(5):445–451. doi:10.1016/0090-4295(93)90505-5
14. Pfizer. Caverject (alprostadil) prescribing information. Sections 1.2, 2.2 and 5.
15. Meuleman EJ, Bemelmans BL, Doesburg WH, et al. "Penile Pharmacological Duplex Ultrasonography: A Dose-Effect Study Comparing Papaverine, Papaverine/Phentolamine and Prostaglandin E1." J Urol. 1992;148(1):63–66. doi:10.1016/s0022-5347(17)36511-4
16. Bassiem MA, Ismail IY, Salem TA, El-Sakka AI. "Effect of Intracavernosal Injection of Prostaglandin E1 on Duration and Rigidity of Erection in Patients With Vasculogenic Erectile Dysfunction: Is It Dose Dependent?" Urology. 2021;148:173–178. doi:10.1016/j.urology.2020.09.030
17. Bookstein JJ, Valji K, Parsons L, Kessler W. "Penile Pharmacocavernosography and Cavernosometry in the Evaluation of Impotence." J Urol. 1987;137(4):772–776. doi:10.1016/s0022-5347(17)44208-x
18. Pathak RA, Broderick GA. "Color Doppler Duplex Ultrasound Parameters in Men Without Organic Erectile Dysfunction." Urology. 2020;135:66–70. doi:10.1016/j.urology.2019.09.002
19. Pezzoni F, Scroppo FI, Cavallini G. "Differences in Cavernosal Artery Parameters According to Different Anatomic Sampling Locations During the Diagnosis of Vascular Erectile Dysfunction Using Duplex Ultrasound." Urology. 2017;105:33–41. doi:10.1016/j.urology.2017.01.057
20. Pagano MJ, Stahl PJ. "Variation in Penile Hemodynamics by Anatomic Location of Cavernosal Artery Imaging in Penile Duplex Doppler Ultrasound." J Sex Med. 2015;12(9):1911–1919. doi:10.1111/jsm.12958
21. Chen L, Xu L, Wang J, et al. "Diagnostic Accuracy of Different Criteria of Pharmaco-Penile Duplex Sonography for Venous Erectile Dysfunction." J Ultrasound Med. 2019;38(10):2739–2748. doi:10.1002/jum.14982
22. Valji K, Bookstein JJ. "Diagnosis of Arteriogenic Impotence: Efficacy of Duplex Sonography as a Screening Tool." AJR Am J Roentgenol. 1993;160(1):65–69. doi:10.2214/ajr.160.1.8416650
23. Benson CB, Vickers MA. "Sexual Impotence Caused by Vascular Disease: Diagnosis With Duplex Sonography." AJR Am J Roentgenol. 1989;153(6):1149–1153. doi:10.2214/ajr.153.6.1149
24. Gutwein A, Braun AJ, Thalhammer C, et al. "Evaluating the Feasibility of a New Non-Invasive Technique for Improved Diagnostics in Vascular Erectile Dysfunction Using an Ultra-High-Resolution Ultrasound Probe and Venous Compression: A Proof of Concept Study." J Sex Med. 2025;22(6):1024–1034. doi:10.1093/jsxmed/qdaf073
25. Pradeep A, Alexander LF, Padilla-Maldonado GW, et al. "Imaging Techniques for Diagnosing and Managing Peyronie Disease." Abdom Radiol. 2025;50(1):349–359. doi:10.1007/s00261-024-04521-3
26. Chung E, Yan H, De Young L, Brock GB. "Penile Doppler Sonographic and Clinical Characteristics in Peyronie's Disease and/or Erectile Dysfunction: An Analysis of 1500 Men With Male Sexual Dysfunction." BJU Int. 2012;110(8):1201–1205. doi:10.1111/j.1464-410X.2011.10851.x
27. Masterson TA, Efimenko IV, Nackeeran S, Parmar M, Ramasamy R. "Discordant Erectile Function Assessment Between Validated Questionnaire Scores and Penile Doppler Ultrasound in Peyronie's Disease." Int J Impot Res. 2022;34(5):452–455. doi:10.1038/s41443-021-00416-9
28. Pang KH, Alnajjar HM, Lal A, Muneer A. "An Update on Mechanisms and Treatment Options for Priapism." Nat Rev Urol. 2025. doi:10.1038/s41585-025-01069-9
29. Leamon A, Montoya K, Shokoohi H. "A Novel Approach to Priapism Doppler Assessment: Sonography to Identify Forward Flow (STIFF Protocol)." J Emerg Med. 2025;78:33–36. doi:10.1016/j.jemermed.2025.07.051
30. Bertelli E, D'Amico G, Bertolotto M, Miele V. "Penile Ultrasound: An Essential Tool in an Emergency Setting (Traumatic and Non-Traumatic Diseases)." Ultraschall Med. 2022;43(3):232–251. doi:10.1055/a-1748-3995
31. Mulhall JP, Anderson M, Parker M. "Congruence Between Veno-Occlusive Parameters During Dynamic Infusion Cavernosometry: Assessing the Need for Cavernosography." Int J Impot Res. 2004;16(2):146–149. doi:10.1038/sj.ijir.3901177
32. Lowe MA, Schwartz AN, Berger RE. "Controlled Trial of Infusion Cavernosometry in Impotent and Potent Men." J Urol. 1991;146(3):783–785. doi:10.1016/s0022-5347(17)37920-x
33. Meuleman EJ, Wijkstra H, Doesburg WH, Debruyne FM. "Comparison of the Diagnostic Value of Pump and Gravity Cavernosometry in the Evaluation of the Cavernous Veno-Occlusive Mechanism." J Urol. 1991;146(5):1266–1270. doi:10.1016/s0022-5347(17)38065-5
34. Bertolotto M, Campo I, Sachs C, et al. "Sonography of the Penis / Erectile Dysfunction." Abdom Radiol. 2020;45(7):1973–1989. doi:10.1007/s00261-020-02529-z
35. Roudenko A, Wilcox Vanden Berg RN, Song C, et al. "Utility of Dynamic MRA in the Evaluation of Male Erectile Dysfunction." Abdom Radiol. 2020;45(7):1990–2000. doi:10.1007/s00261-019-02339-y
36. Shenoy-Bhangle A, Perez-Johnston R, Singh A. "Penile Imaging." Radiol Clin North Am. 2012;50(6):1167–1181. doi:10.1016/j.rcl.2012.08.009
37. Parker RA, Menias CO, Quazi R, et al. "MR Imaging of the Penis and Scrotum." Radiographics. 2015;35(4):1033–1050. doi:10.1148/rg.2015140161
38. Graziani A, Delbarba A, Nardin M, et al. "Association Between Parameters of Penile Doppler Ultrasound and Cardiovascular Risk in Patients With Erectile Dysfunction: A Single-Center Retrospective Study." J Clin Med. 2026;15(7):2722. doi:10.3390/jcm15072722
39. Vickers MA, Benson CB, Richie JP. "High Resolution Ultrasonography and Pulsed Wave Doppler for Detection of Corporovenous Incompetence in Erectile Dysfunction." J Urol. 1990;143(6):1125–1127. doi:10.1016/s0022-5347(17)40202-3
40. European Association of Urology. Management of erectile dysfunction. Guidelines on Sexual and Reproductive Health, Limited Update March 2026, section 5.5 (advanced diagnostic work-up; section 5.5.3, dynamic duplex ultrasound).
41. Qureshi JM, Wood H, Feldman M. "High Flow Priapism on Color Doppler Ultrasound." J Urol. 2013;189(6):2312–2313. doi:10.1016/j.juro.2013.03.007
42. Mulhall JP, Jenkins LC. Penile Duplex Doppler Ultrasonography. In: Mulhall JP, Jenkins LC, eds. Atlas of Office Based Andrology Procedures. Springer; 2017:31–46. doi:10.1007/978-3-319-42178-0_6
43. Kloner RA, Burnett AL, Miner M, et al. "Princeton IV consensus guidelines: PDE5 inhibitors and cardiac health." J Sex Med. 2024;21(2):90–116. doi:10.1093/jsxmed/qdad163
44. US Food and Drug Administration. Compounding and the FDA: Questions and Answers. FDA guidance. Accessed October 5, 2026.
45. Morey AF, Brandes S, Dugi DD III, et al. "Urotrauma: AUA Guideline." J Urol. 2014;192(2):327–335. doi:10.1016/j.juro.2014.05.004
46. European Association of Urology. Penile Curvature. Guidelines on Sexual and Reproductive Health. 2026, section 8.2.2.
47. European Association of Urology. Priapism. Guidelines on Sexual and Reproductive Health. 2026, section 10.1.2.e.
48. Bivalacqua TJ, Allen BK, Brock G, et al. "Acute Ischemic Priapism: An AUA/SMSNA Guideline." J Urol. 2021;206(5):1114–1121. doi:10.1097/JU.0000000000002236