The Cervix
The cervix is the inferior fibromuscular cylinder of the uterus that projects into the vaginal vault and contains the endocervical canal linking the uterine cavity to the vagina.
See also The Vagina for the surrounding fornices; The Ureters for the "water under the bridge" geometry; and Pelvic Neuroanatomy for the pelvic plexus.
Gross Anatomy
The cervix is a cylinder; one cited review describes it as approximately 2 cm long. It divides anatomically into two portions:[1][2]
- Supravaginal portion. Above the vaginal attachment, surrounded by the cardinal-ligament complex and paracervical tissues.
- Vaginal portion (portio vaginalis). Protrudes into the vaginal vault, visible at speculum examination; demarcated from the vault by the anterior, posterior, and lateral fornices.
The canal extends from the internal os (communication with the uterine cavity) to the external os (communication with the vaginal vault). The external os is slit-like in parous women and round in nulliparas, a difference seen at pessary fitting and at colposcopy.
Three mucosal regions
| Region | Epithelium | Surface landmarks |
|---|---|---|
| Ectocervix (portio) | Non-keratinized stratified squamous, continuous with vaginal epithelium | Smooth, pink at speculum |
| Endocervix | Simple columnar mucus-secreting; surface thrown into plicae palmatae that increase surface area | Red, granular at speculum; lined by glands |
| Transformation zone (TZ) | Zone of ongoing squamous metaplasia between the original and current squamocolumnar junctions (SCJ) | A major site of HPV-associated cervical precancer and cancer; visibility varies by age and individual anatomy[3][4][5] |
The TZ commonly becomes more visible on the ectocervix around puberty and may recede into the canal after menopause. Cervical screening follows current age- and risk-based guidance. At colposcopy after an abnormal result, the ASCCP 2023 guideline recommends endocervical curettage when the squamocolumnar junction is not fully visible and for several higher-risk findings (high-grade cytology, HPV 16/18, positive p16/Ki-67 dual stain, prior treatment for cervical precancer). It prefers endocervical curettage for patients aged 40 years and older undergoing colposcopy (BIII), with stated exceptions, and calls it unacceptable in pregnancy (EIII).[20]
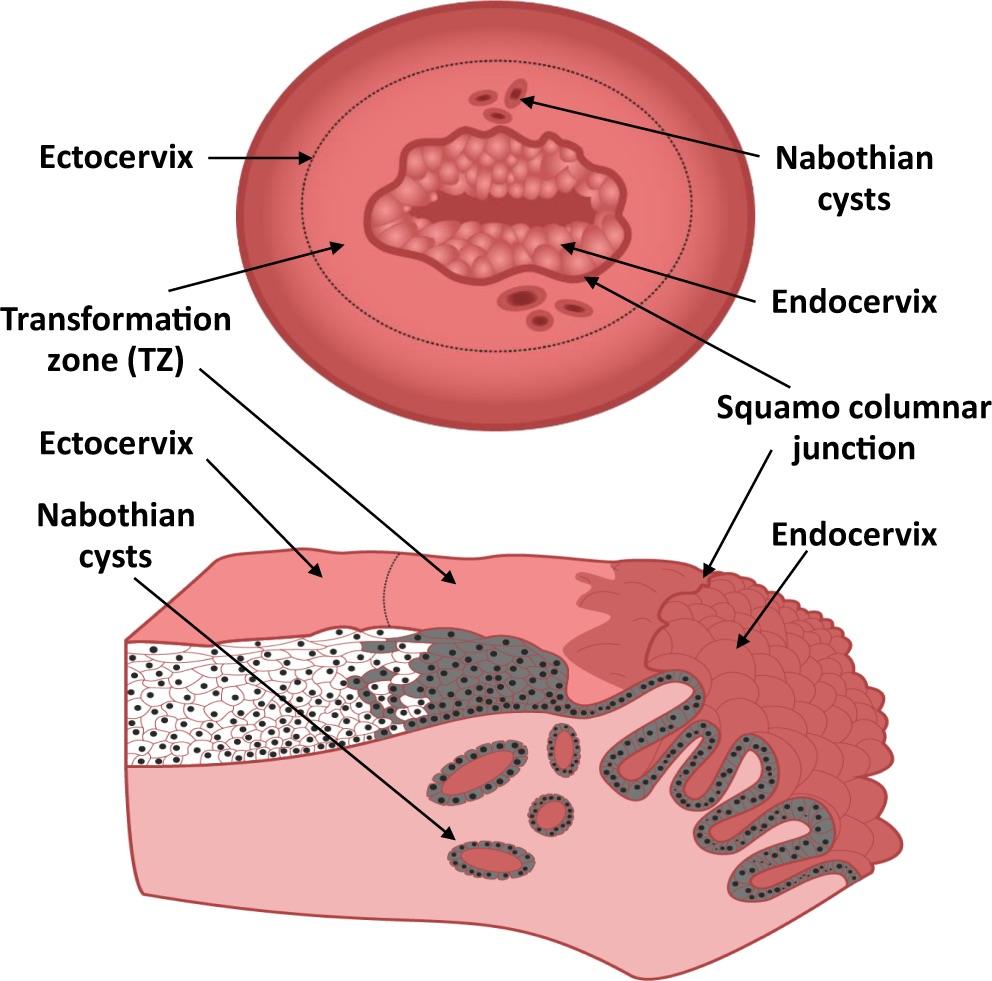
Schematic of the cervical transformation zone. Top: the cervix as seen through a speculum, showing the ectocervix, the transformation zone with Nabothian cysts, the squamocolumnar junction and the endocervix. Bottom: cross section showing columnar epithelium of the endocervix and stratified squamous epithelium of the transformation zone and ectocervix; Nabothian cysts form when endocervical mucous ducts are occluded by overgrowth of squamous epithelium from the newly formed transformation zone. Shaded cells are those derived from endocervical reserve cells. From Deng H, et al. Sci Rep. 2018;8(1):15402, Figure 1 (CC BY).[5]
Structural Supports — The Apex of Pelvic-Floor Reconstruction
The cervix is the anchoring point of Level-I pelvic support in DeLancey's model. Two ligamentous / connective-tissue complexes suspend it:[11]
| Complex | Origin | Insertion | Contents |
|---|---|---|---|
| Cardinal ligament (Mackenrodt) | Pelvic sidewall at the obturator internus fascia | Lateral cervix and upper vagina | Uterine artery and vein, the ureter (crossing beneath the uterine artery), pelvic plexus autonomic fibers, lymphatics |
| Uterosacral ligament (USL) | Presacral fascia at the level of S2–S4 | Posterior cervix and upper vagina | Sympathetic fibers from the pelvic plexus; lymphatic channels |
The cardinal and uterosacral supports are mesentery-like visceral ligaments containing connective and adipose tissue, vessels, autonomic nerves and some smooth muscle; the cardinal ligament is chiefly vascular, while the deep uterosacral ligament is rich in autonomic fibers.[33] Clinically:
- Apical prolapse (uterine / vault) represents failure of the cardinal-uterosacral (CUL) complex.
- USLS, Manchester (Fothergill), and vaginal hysterectomy with McCall culdoplasty reinforce native apical support. Sacrocolpopexy suspends the vaginal apex to the sacral anterior longitudinal ligament with mesh.[34]
- Cervical elongation is disproportionate cervical lengthening that may coexist with uterine descent; when the uterine body remains supported, an elongated cervix can mimic apical prolapse. Assess cervical length and apical descent separately when choosing cervical reduction, Manchester repair or apical suspension.[28][29]
Anatomical Relations — Why the Ureter Lives Under the Uterine Artery
| Aspect | Relation | Operative note |
|---|---|---|
| Anterior | Bladder base and trigone, separated by the vesicocervical/vesicouterine space | The plane of anterior dissection in hysterectomy, cervical cancer surgery, and vesicovaginal fistula repair |
| Posterior | Rectum and the rectouterine pouch (Douglas') | Approached via the posterior colpotomy; enterocele sits in this peritoneal pocket |
| Lateral | Broad ligament, cardinal ligament, uterine vessels, and ureter near the lateral cervix (distance varies) | Site of potential iatrogenic ureteric injury |
Water under the bridge (the ureteric injury pattern). The uterine artery crosses anterior (over) the ureter near the cervix, but the often-quoted distance of approximately 1.5–2 cm varies with anatomy and pathology. This is a recognized danger zone in hysterectomy and deep paracervical dissection. Identify the ureter and adapt the dissection to the actual anatomy.
A CT study of 499 women found the right ureter closer to the cervix than the left overall (2.0 ± 0.8 vs 2.2 ± 1.0 cm; p < .05), while among the subset with isolated cervical pathology the right ureter was farther away than the left (2.0 ± 0.6 vs 1.7 ± 0.6 cm; p < .05); age was not associated with distance. At least one ureter was within 5 mm of the cervix in 3.6% of normal scans and 10.3% of scans with cervical pathology.[27]
Vascular Supply
The uterine artery (usually a branch of the anterior division of the internal iliac) is a principal cervical arterial supply; its horizontal parametrial segment gives one or two cervicovaginal branches near the cervix.[7][8][9][35] Additional contributions come from the vaginal artery and, in limited fashion, the middle rectal artery.
In a corrosion-cast study of 20 autopsy cervices (two near-complete casts), the endocervical mucosa showed dense, near-parallel capillaries with few interconnections; the authors suggested that this pattern may aid vascular adaptation during parturition.[7] Even superficial biopsies and LEEP excisions of the non-pregnant cervix bleed.
Venous drainage parallels the arteries to the uterine and vaginal plexuses and thence the internal iliac vein.
Lymphatic drainage of the cervix runs to parametrial, obturator, internal iliac, external iliac, and common iliac nodes, with variable posterior pathways; presacral nodes may receive cervical drainage, but a fixed posterior-lip-to-presacral pathway is not established.[43][44] These pathways guide nodal mapping and indicated lymph-node dissection in cervical-cancer surgery. Wertheim and Okabayashi are named radical-hysterectomy approaches, whereas Querleu–Morrow classes describe parametrial resection extent and consider lymph-node dissection separately.[21][45]
Innervation — Nerve-Sparing and Cervical Cancer Surgery
The cervix has sympathetic, parasympathetic and sensory innervation and is reported to be more densely innervated than the uterine corpus and fundus.[10][11][12] This innervation is the anatomic substrate of nerve-sparing radical hysterectomy.
| Source | Pathway | Function |
|---|---|---|
| Parasympathetic | S2–S4 pelvic nerve → inferior hypogastric plexus → cardinal ligament (lateral and inferior) | Smooth muscle tone and vasodilation; afferent pain fibers |
| Sympathetic | T10–L2 hypogastric nerve → inferior hypogastric plexus → uterosacral ligament (posterior) | Contraction, vasoconstriction; afferent pain fibers |
The inferior hypogastric plexus and its branches to the bladder, rectum and vagina are at risk during paracervical resection. In the 2017 Querleu–Morrow classification, type C1 is nerve-preserving: the hypogastric nerve, inferior hypogastric plexus and bladder branches are identified and preserved while uterine branches are divided. Type C2 does not preserve the autonomic nerves. C1 and C2 are distinct surgical extents. Functional and oncologic outcomes depend on tumor selection and operative execution.[10][11][21]
Cervical Mucus — Compressed to What's Clinically Useful
Endocervical columnar cells produce a hydrated mucin gel that changes cyclically under estrogen and progesterone control:[13][14][15][16]
- Periovulatory (estrogen-dominant). Thin, copious, low-viscosity, high-spinnbarkeit mucus with a "ferning" pattern when dried; permissive to sperm transit and partially protective to vaginal flora.
- Luteal and pregnant (progesterone-dominant). Luteal mucus is relatively thick, scant and less penetrable to sperm. During pregnancy, accumulated cervical mucus forms a compact physical and immune barrier that impedes, but does not completely block, ascending microbes.[36][37]
- Postmenopausal (hypoestrogenic). Atrophic, thin, reduced mucus, higher vaginal pH (as with vaginal atrophy; see The Vagina).
First, NICE NG123 advises considering vaginal estrogen for genitourinary symptoms and signs of menopause in a patient with prolapse.[25] Second, cervical mucus penetrability testing (the historical post-coital test) has limited modern clinical utility. Third, cervical ectopy (visible columnar epithelium on the ectocervix) is commonly physiological in younger women, oral-contraceptive users and pregnancy.
Cervical Remodeling in Pregnancy (in broad strokes)
The non-pregnant cervix is a stiff collagen-dominant organ; pregnancy transforms it into a compliant, extensible one through four overlapping phases:[6][17][18][19][22]
- Softening. Collagen reorganization increases compliance early in pregnancy while the cervix remains closed and mechanically competent; marked hydration, increased hydrophilic glycosaminoglycans and tensile-strength loss characterize later ripening.[22]
- Ripening. Increased compliance and distensibility and reduced tissue stiffness and tensile strength, with greater hydration and collagen-matrix remodeling.[22]
- Dilation. Active labor opens the cervix under uterine contraction.
- Postpartum repair. Rapid return toward baseline structure.
Cervical insufficiency describes a clinical pattern of painless cervical dilation and pregnancy loss or very early birth in the absence of labor. Cerclage is considered for selected patients according to obstetric history, examination and current guidance, and a prior LEEP, cone or cervical trauma alone does not indicate it.
Clinical Correlations for the Reconstructive Surgeon
- Hysterectomy and ureteric injury. The ureter passes close to the cervix and beneath the uterine artery. Identify and protect it during dissection in this region, especially when anatomy is distorted. Cystoscopy can help evaluate suspected urinary-tract injury, but its use and interpretation depend on the operation and clinical circumstances.[24]
- Nerve-sparing radical hysterectomy. Querleu–Morrow type C1 (but not C2) aims to preserve the hypogastric nerve, inferior hypogastric plexus and bladder branches. The extent of parametrial resection and the cancer-treatment context determine whether nerve preservation is appropriate.[21] In the SHAPE randomized trial of 700 patients with cervical tumors 2 cm or smaller and limited stromal invasion, simple hysterectomy with nodal assessment was noninferior to radical hysterectomy for pelvic recurrence at three years (2.52% versus 2.17%) and had less urinary retention beyond four weeks (0.6% versus 9.9%).[30]
- Apical prolapse and the cervix. Uterine prolapse involves failure of the cardinal–uterosacral Level-I support complex. During USLS, sutures can compromise the nearby ureter; AUGS recommends intraoperative cystoscopy with confirmation of ureteral efflux during apical prolapse repair.[31][32] Options: vaginal hysterectomy with apical suspension (USL suspension or McCall culdoplasty), sacrospinous hysteropexy, sacrohysteropexy (mesh), and the Manchester (Fothergill) procedure (cervical shortening or amputation with uterosacral plication, often with cardinal plication; anterior colporrhaphy is added for a concomitant anterior defect) for selected uterine descent, including cervical elongation.[38] In a Dutch trial of first uterus-preserving surgery with POP-Q point D at or proximal to −1 cm, two-year composite success was 172/197 (87.3%) after Manchester versus 151/196 (77.0%) after sacrospinous hysteropexy; the composite required absence of prolapse beyond the hymen, absence of bothersome bulge symptoms and no retreatment.[39]
- Cervical elongation. Disproportionate cervical overgrowth mimics apical prolapse; at examination the uterine body may remain within the pelvis despite a cervix below the hymen. Treatment is trachelectomy or the Manchester procedure, with or without apical suspension.
- Conization and LEEP. Outpatient excisional procedures for CIN 2/3. Clinically relevant to obstetric outcomes (excision depth is associated with preterm delivery risk) and to the later reconstructive surgeon (cervical stenosis can cause hematometra or dysmenorrhea; cervical shortening affects fertility-preserving cerclage planning).[1]
- Trachelectomy. Fertility-sparing cervical surgery may include conization, simple or radical trachelectomy after specialist staging and multidisciplinary selection. The ESGO/ESHRE/ESGE fertility-sparing guideline distinguishes favorable tumors around ≤2 cm from selected 2–4-cm cases and requires assessment of histology, nodal status, margins and internal-os involvement.[23]
- Supracervical (subtotal) hysterectomy and the retained cervix. The cervical stump stays in situ, and the patient continues cervical cancer screening. Complications include persistent cyclical bleeding, stump infection, and, rarely, stump carcinoma, each of which can present to a reconstructive surgeon years later.
- Sequelae of pelvic radiation. Radiation can cause vesicovaginal or rectovaginal fistula, cystitis, vaginal stenosis, ureteric stricture and bladder dysfunction. Repair planning depends on tissue quality, fistula location, prior treatment and patient goals. EAU reports lower repair success for irradiated than nonirradiated fistulae and weakly recommends an interposition graft when repair is undertaken. If diversion is required, it weakly recommends avoiding irradiated bowel.[24]
- Vesicocervical space and vesicovaginal fistula. A post-hysterectomy VVF may involve the vaginal cuff and adjacent bladder dissection plane. Repair may use transvaginal or abdominal access, layered closure and, for selected complex or radiated defects, vascularized tissue interposition; an abdominal route is indicated for a high, fixed vault fistula inaccessible vaginally, but no one plane, flap or approach is required for every fistula.[24] See The Vagina.
- Cervical cancer and the reconstructive burden. Prior radical surgery or chemoradiation can complicate fistula repair, urinary diversion, vaginal reconstruction and bladder-function care. Evaluation is tailored to the presenting problem and may include direct examination, cystoscopy and upper-tract imaging when anatomy or ureteric involvement is uncertain.[24]
- Cerclage. McDonald (transvaginal, simpler to place) and Shirodkar (transvaginal, submucosal) are vaginal approaches. SMFM recommends offering transabdominal cerclage after a history- or ultrasound-indicated vaginal cerclage followed by spontaneous singleton delivery before 28 weeks (GRADE 1B).[40] Its checklist also lists patients with a history-based indication and too little cervix for a vaginal stitch after trachelectomy or extensive excision as potential candidates.[41] The 2023 ESGO cervical-cancer guideline separately recommends permanent cerclage during simple or radical trachelectomy (IV, B).[42] SMFM suggests both laparoscopic and open transabdominal placement (GRADE 2B) and recommends maternal-fetal medicine consultation (Best Practice).[40] Prior bladder or urethral surgery may complicate access and involve the reconstructive surgeon.
- Postmenopausal tissue and pessary care. Vaginal estrogen may be considered when prolapse coexists with genitourinary symptoms and signs of menopause; it is not established as a way to improve pessary retention. In a 2025 placebo-controlled trial of 420 postmenopausal women in China already fitted with ring pessaries, 12-month continuation with patient-reported improvement was 181/208 (87.0%) with estrogen versus 176/203 (86.7%) with placebo (risk difference 0.3%, 95% CI −6.2 to 6.9).[26] The estrogen group had fewer reports of excessive discharge (34/208 [16.3%] versus 52/203 [25.6%]), vaginal erosion or ulcer (4/208 [1.9%] versus 14/203 [6.9%]), and vaginal bleeding (3/208 [1.4%] versus 13/203 [6.4%]).[26]
References
1. Kyrgiou M, Athanasiou A, Arbyn M, et al. "Terminology for Cone Dimensions After Local Conservative Treatment for Cervical Intraepithelial Neoplasia and Early Invasive Cervical Cancer: 2022 Consensus Recommendations From ESGO, EFC, IFCPC, and ESP." Lancet Oncol. 2022;23(8):e385–e392. doi:10.1016/S1470-2045(22)00191-7
2. Barrios De Tomasi J, Opata MM, Mowa CN. "Immunity in the Cervix: Interphase Between Immune and Cervical Epithelial Cells." J Immunol Res. 2019;2019:7693183. doi:10.1155/2019/7693183
3. Aiyenuro A, Griffin H, Schichl K, et al. "Role of Reserve Cells in Metaplasia and the Development of Human Papillomavirus-Associated High-Grade Squamous Intraepithelial Lesions at the Cervical Transformation Zone." Lab Invest. 2025;105(7):104166. doi:10.1016/j.labinv.2025.104166
4. Regauer S, Reich O. "The Origin of Human Papillomavirus (HPV)-Induced Cervical Squamous Cancer." Curr Opin Virol. 2021;51:111–118. doi:10.1016/j.coviro.2021.09.012
5. Deng H, Hillpot E, Mondal S, Khurana KK, Woodworth CD. "HPV16-Immortalized Cells From Human Transformation Zone and Endocervix Are More Dysplastic Than Ectocervical Cells in Organotypic Culture." Sci Rep. 2018;8(1):15402. doi:10.1038/s41598-018-33865-2
6. Tantengco OAG, Menon R. "Contractile Function of the Cervix Plays a Role in Normal and Pathological Pregnancy and Parturition." Med Hypotheses. 2020;145:110336. doi:10.1016/j.mehy.2020.110336
7. Walocha JA, Litwin JA, Bereza T, Klimek-Piotrowska W, Miodoński AJ. "Vascular Architecture of Human Uterine Cervix Visualized by Corrosion Casting and Scanning Electron Microscopy." Hum Reprod. 2012;27(3):727–732. doi:10.1093/humrep/der458
8. Bereza T, Tomaszewski KA, Bałajewicz-Nowak M, et al. "The Vascular Architecture of the Supravaginal and Vaginal Parts of the Human Uterine Cervix: A Study Using Corrosion Casting and Scanning Electron Microscopy." J Anat. 2012;221(4):352–357. doi:10.1111/j.1469-7580.2012.01550.x
9. Höckel M, Horn LC, Fritsch H. "Association Between the Mesenchymal Compartment of Uterovaginal Organogenesis and Local Tumour Spread in Stage IB-IIB Cervical Carcinoma: A Prospective Study." Lancet Oncol. 2005;6(10):751–756. doi:10.1016/S1470-2045(05)70324-7
10. Giovannetti O, Tomalty D, Velikonja L, Jurkus C, Adams MA. "The Human Cervix: Comprehensive Review of Innervation and Clinical Significance." Clin Anat. 2023;36(1):118–127. doi:10.1002/ca.23960
11. Zhang J, Feng L, Lu Y, et al. "Distribution of Lymphatic Tissues and Autonomic Nerves in Supporting Ligaments Around the Cervix Uteri." Mol Med Rep. 2013;7(5):1458–1464. doi:10.3892/mmr.2013.1360
12. Di Tommaso S, Cavallotti C, Malvasi A, et al. "A Qualitative and Quantitative Study of the Innervation of the Human Non Pregnant Uterus." Curr Protein Pept Sci. 2017;18(2):140–148. doi:10.2174/1389203717666160330105341
13. Argüeso P, Spurr-Michaud S, Tisdale A, Gipson IK. "Variation in the Amount of T Antigen and N-Acetyllactosamine Oligosaccharides in Human Cervical Mucus Secretions With the Menstrual Cycle." J Clin Endocrinol Metab. 2002;87(12):5641–5648. doi:10.1210/jc.2002-020766
14. Gipson IK, Moccia R, Spurr-Michaud S, et al. "The Amount of MUC5B Mucin in Cervical Mucus Peaks at Midcycle." J Clin Endocrinol Metab. 2001;86(2):594–600. doi:10.1210/jcem.86.2.7174
15. Gipson IK. "Mucins of the Human Endocervix." Front Biosci. 2001;6:D1245–D1255. doi:10.2741/gipson
16. Brunelli R, Papi M, Arcovito G, et al. "Globular Structure of Human Ovulatory Cervical Mucus." FASEB J. 2007;21(14):3872–3876. doi:10.1096/fj.07-8189com
17. Iams JD. "Prevention of Preterm Parturition." N Engl J Med. 2014;370(3):254–261. doi:10.1056/NEJMcp1103640
18. Shi L, Hu L, Lee N, Fang S, Myers K. "Three-Dimensional Anisotropic Hyperelastic Constitutive Model Describing the Mechanical Response of Human and Mouse Cervix." Acta Biomater. 2022;150:277–294. doi:10.1016/j.actbio.2022.07.062
19. Nallasamy S, Palacios HH, Setlem R, et al. "Transcriptome and Proteome Dynamics of Cervical Remodeling in the Mouse During Pregnancy." Biol Reprod. 2021;105(5):1257–1271. doi:10.1093/biolre/ioab144
20. Massad LS, et al. "Colposcopy Standards: Guidelines for Endocervical Curettage at Colposcopy." J Low Genit Tract Dis. 2023;27(1):97–101. doi:10.1097/LGT.0000000000000710
21. Querleu D, Cibula D, Abu-Rustum NR. "2017 Update on the Querleu–Morrow Classification of Radical Hysterectomy." Ann Surg Oncol. 2017;24(11):3406–3412. doi:10.1245/s10434-017-6031-z
22. Timmons B, Akins M, Mahendroo M. "Cervical Remodeling during Pregnancy and Parturition." Trends Endocrinol Metab. 2010;21(6):353–361. doi:10.1016/j.tem.2010.01.011
23. ESGO/ESHRE/ESGE. Fertility-Sparing Treatment: Cervical Cancer, Ovarian Cancer, Borderline Ovarian Tumours. Pocket guidelines based on Morice P, Scambia G, et al., Lancet Oncol. 2024;25:e602–e610. Official pocket guideline.
24. European Association of Urology. "Disease Management," §4.8, EAU Guidelines on Non-neurogenic Female LUTS. Current online guideline (accessed September 20, 2026).
25. National Institute for Health and Care Excellence. Urinary Incontinence and Pelvic Organ Prolapse in Women: Management. NG123, recommendations 1.7.3–1.7.8. NICE guidance (accessed September 20, 2026).
26. Zhou Y, et al. "Effects of Intravaginal Conjugated Oestrogen on Pessary Continuation for Pelvic Organ Prolapse: Multicentre, Randomised, Double Blind, Placebo Controlled Trial." BMJ. 2025;389:e084418. doi:10.1136/bmj-2025-084418
27. Gemer O, Simonovsky A, Huerta M, Kapustian V, Anteby E, Linov L. "A Radiological Study on the Anatomical Proximity of the Ureters and the Cervix." Int Urogynecol J Pelvic Floor Dysfunct. 2007;18(9):991–995. doi:10.1007/s00192-006-0269-5
28. Berger MB, Ramanah R, Guire KE, DeLancey JOL. "Is cervical elongation associated with pelvic organ prolapse?" Int Urogynecol J. 2012;23(8):1095–1103. doi:10.1007/s00192-012-1747-6
29. Güler Çekiç S, Aktoz F, Urman B, Aydin S. "A systematic review of uterine cervical elongation and meta-analysis of Manchester repair." Eur J Obstet Gynecol Reprod Biol. 2024;300:315–326. doi:10.1016/j.ejogrb.2024.07.029
30. Plante M, Kwon JS, Ferguson S, et al. "Simple versus Radical Hysterectomy in Women with Low-Risk Cervical Cancer." N Engl J Med. 2024;390(9):819–829. doi:10.1056/NEJMoa2308900
31. Wieslander CK, Roshanravan SM, Wai CY, Schaffer JI, Corton MM. "Uterosacral ligament suspension sutures: anatomic relationships in unembalmed female cadavers." Am J Obstet Gynecol. 2007;197(6):672.e1–672.e6. doi:10.1016/j.ajog.2007.08.065
32. Cohen SA, Carberry CL, Smilen SW. "American Urogynecologic Society Consensus Statement: Cystoscopy at the Time of Prolapse Repair." Female Pelvic Med Reconstr Surg. 2018;24(4):258–259. doi:10.1097/SPV.0000000000000529
33. Ramanah R, Berger MB, Parratte BM, DeLancey JOL. "Anatomy and histology of apical support: a literature review concerning cardinal and uterosacral ligaments." Int Urogynecol J. 2012;23(11):1483–1494. doi:10.1007/s00192-012-1819-7
34. Culligan PJ, Saiz CM, Rosenblatt PL. "Contemporary Use and Techniques of Laparoscopic Sacrocolpopexy With or Without Robotic Assistance for Pelvic Organ Prolapse." Obstet Gynecol. 2022;139(5):922–932. doi:10.1097/AOG.0000000000004761
35. Kristek J, Kachlik D, Sticova E, Fronek J. "Contralateral and Ipsilateral Arterial Vasculature of the Human Uterus: The Pilot Results of an Anatomical Study." Physiol Res. 2022;71(Suppl 1):S89–S97. doi:10.33549/physiolres.934972
36. Hansen LK, Becher N, Bastholm S, et al. "The cervical mucus plug inhibits, but does not block, the passage of ascending bacteria from the vagina during pregnancy." Acta Obstet Gynecol Scand. 2014;93(1):102–108. doi:10.1111/aogs.12296
37. Vornhagen J, Quach P, Santana-Ufret V, et al. "Human Cervical Mucus Plugs Exhibit Insufficiencies in Antimicrobial Activity Towards Group B Streptococcus." J Infect Dis. 2018;217(10):1626–1636. doi:10.1093/infdis/jiy076
38. Elissaoui S, El Issaoui M, Klarskov N, Husby K. "The Manchester procedure: A systematic review of recurrence, perioperative measures, and financial cost, and a scoping review of sexual dysfunction, gynecologic cancer, and obstetric outcomes." Acta Obstet Gynecol Scand. 2026;105(7):1371–1383. doi:10.1111/aogs.70209
39. Enklaar RA, Schulten SFM, van Eijndhoven HWF, et al. "Manchester Procedure vs Sacrospinous Hysteropexy for Treatment of Uterine Descent: A Randomized Clinical Trial." JAMA. 2023;330(7):626–635. doi:10.1001/jama.2023.13140
40. Society for Maternal-Fetal Medicine (SMFM), Temming L, Mikhail E, et al. "Society for Maternal-Fetal Medicine Consult Series #65: Transabdominal cerclage." Am J Obstet Gynecol. 2023;228(6):B2–B10. doi:10.1016/j.ajog.2023.02.018
41. Society for Maternal-Fetal Medicine (SMFM), Mateus Nino J, Combs CA, et al. "Society for Maternal-Fetal Medicine Special Statement: Checklists for transabdominal cerclage." Am J Obstet Gynecol. 2023;229(4):B2–B6. doi:10.1016/j.ajog.2023.07.015
42. Cibula D, Raspollini MR, Planchamp F, et al. "ESGO/ESTRO/ESP Guidelines for the management of patients with cervical cancer: Update 2023." Int J Gynecol Cancer. 2023;33(5):649–666. doi:10.1136/ijgc-2023-004429
43. Weyl A, Sanson C, Roumiguié M, et al. "The lymphatic system of the uterine cervix: towards a more precise definition of the drainage routes." Surg Radiol Anat. 2023;45(5):653–659. doi:10.1007/s00276-023-03129-4
44. Sahli L, Siegenthaler F, Büchi CA, et al. "Role of pre-sacral sentinel lymph nodes in endometrium and cervical cancer: experience with minimally invasive indocyanine green sentinel lymph node mapping." Int J Gynecol Cancer. 2025;35(1):100032. doi:10.1016/j.ijgc.2024.100032
45. Querleu D, Morrow CP. "Classification of radical hysterectomy." Lancet Oncol. 2008;9(3):297–303. doi:10.1016/S1470-2045(08)70074-3