The Vagina
The vagina is a fibromuscular tubular organ running from the vulvar vestibule to the uterine cervix.
See also The Vulva for the introital and vestibular anatomy; Female Urethra for the anterior-wall urethral structures; and Perineum for the perineal body and posterior-compartment anchors.
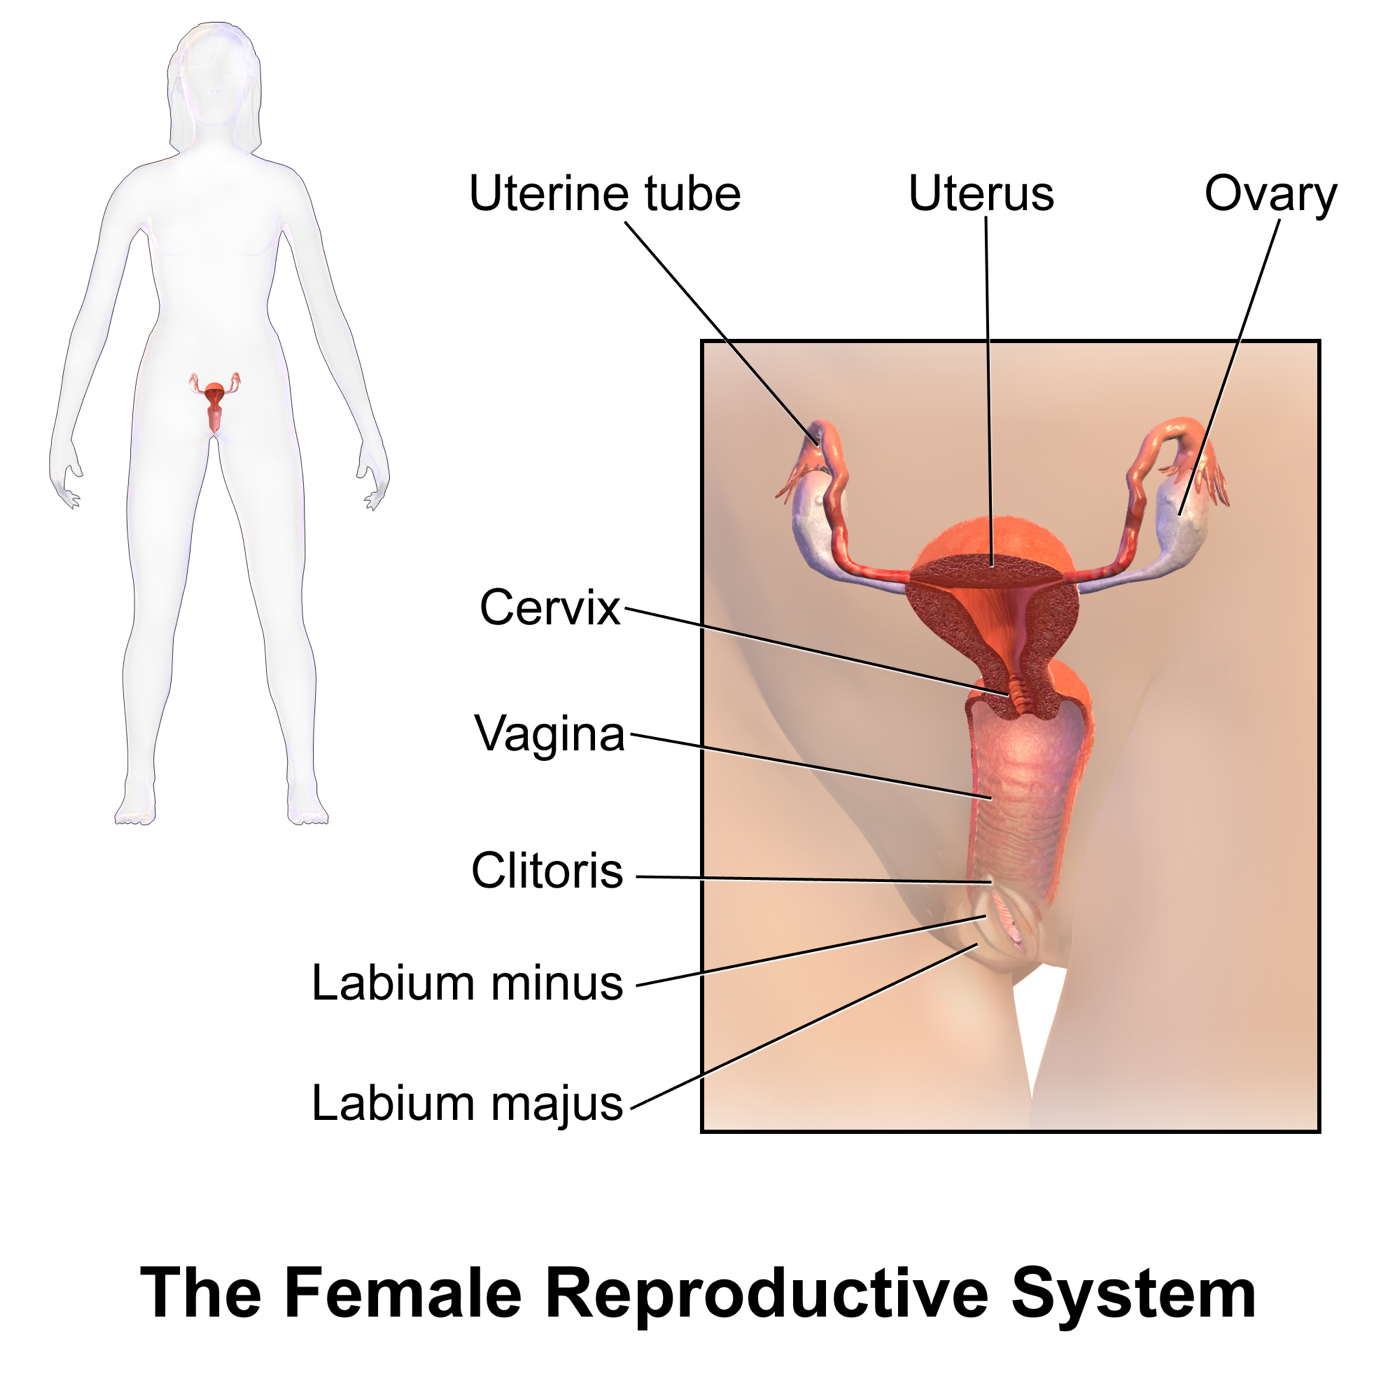
Blausen Medical — Female reproductive system, frontal schematic. (CC BY 3.0)
Dimensions and Shape
Vaginal dimensions vary with the person, measurement method and degree of distension. In one MRI study of undistended volunteers, mean cervix-to-introitus length was 62.7 mm; a separate cast study reported a substantially wider range in a different cohort.[1][2] In the MRI cohort, mean width was 32.5 mm proximally, 27.8 mm at the pelvic diaphragm and 26.2 mm at the introitus.[1] Surface area is likewise method-dependent.[3]
The vagina is not a straight tube. In the supine pelvis the axis bends predictably:[3]
- Approximately 90° relative to the horizontal in the lower vagina (nearly vertical)
- Approximately 72° in the mid-vagina
- Approximately 41° at the apex, directed toward the hollow of the sacrum
Contrast-distended MRI shows three vaginal zones that correspond broadly to DeLancey's support levels:[5]
| Zone | Location | Key features |
|---|---|---|
| Superficial sphincteric (distal) | Surrounded by pelvic-floor muscles and perineal membrane | Perineal body anchor; bulbospongiosus and superficial transverse perinei |
| Central transition (mid) | Between levator plate and pelvic sidewall | Lateral attachments to ATFP; the paravaginal territory |
| Deep forniceal (proximal) | Expanded around the cervix; anterior, posterior, lateral fornices | Apical support from the cardinal–uterosacral ligament (CUL) complex |
Anatomical relations
| Aspect | Relation |
|---|---|
| Anterior | Urethra (distal), bladder base and trigone (mid), cervix/vesicocervical space (proximal) |
| Posterior | Perineal body (distal), rectum (mid), rectouterine pouch of Douglas (proximal, peritoneum) |
| Lateral | Levator ani (pubovisceral), pelvic plexus, cardinal ligament, vaginal artery, ureter near the cervix as it passes beneath the uterine artery; distance varies |
| Apex | Cervix with anterior, posterior, and lateral fornices |
The ureter at the vaginal apex. The ureter passes beneath the uterine artery near the cervix; the often-quoted 1.5–2-cm separation is an approximate teaching landmark, not a fixed safe distance. It is at risk during hysterectomy and some apical or paracervical dissections, with risk depending on the actual course and any distortion of anatomy. See The Ureters.
Wall Structure
| Layer | Composition | Operative relevance |
|---|---|---|
| Mucosa | Non-keratinised stratified squamous epithelium, hormone-responsive, glycogen-rich with rugae; ~26–28 cell layers in reproductive years[8] | Relevant to colporrhaphy and fistula repair; estrogen can improve atrophy symptoms and the tissue appearance judged by surgeons[6][26] |
| Muscularis (fibromuscular layer) | Inner circular and outer longitudinal smooth muscle in a collagen/elastin matrix; the lamina propria belongs to the mucosa | In anterior colporrhaphy, dissection splits vaginal muscularis and repair plicates muscularis and adventitia. Pubocervical and rectovaginal “fascia” are operative terms, not discrete vaginal histologic layers.[4] |
| Adventitia | Loose connective tissue carrying vessels, lymphatics, and nerves | Dissection between the vaginal wall and bladder or proximal rectum can follow local areolar planes in fistula, prolapse and hysterectomy surgery. Behind the distal vagina, connective tissue is fused to adjacent perineal and rectal tissues, so a continuous avascular plane cannot be assumed.[4][35] |
Unlike the columnar endocervix, the superficial epithelium of both the vagina and ectocervix lacks classical tight junctions. The cited experiment demonstrated IgG penetration through apical ectocervical layers; vaginal junctions were assessed by staining.[10]
Hormone responsiveness. Estrogen thickens the epithelium and increases glycogen, which can support lactobacillus-dominant communities and an acidic vaginal pH in reproductive years.[9] Postmenopausal hypoestrogenism may thin the epithelium and raise pH, contributing to genitourinary symptoms.[6][26]
DeLancey's Three-Level Support — the Prolapse Framework
The mechanical support of the vagina is best understood through DeLancey's three-level model.[19][21][22]
| Level | Structures | Clinical failure |
|---|---|---|
| Level I — apical | Cardinal ligament + uterosacral ligament complex (CUL); suspends the vaginal apex and cervix from the sacrum and pelvic sidewall | Apical prolapse: uterine descent, vaginal vault prolapse, enterocele |
| Level II — mid-vaginal / lateral | Paravaginal attachments to the arcus tendineus fasciae pelvis (ATFP) ("white line") and superior fascia of levator ani | Anterior (cystocele) and posterior (rectocele) compartment descent |
| Level III — distal | Perineal membrane, perineal body, and levator–bulbospongiosus complex | Distal anterior wall descent, perineal deficiency, gaping introitus |
Two operative rules follow:
- Apical support matters to compartment descent. Biomechanical modeling links levator impairment, hiatus size and apical support with anterior-wall prolapse severity.[21] An apical defect should be assessed when planning compartment repair.
- Paravaginal (Level II) and distal (Level III) defects may coexist with apical descent and require individual assessment.
Vascular Supply and Drainage
Arterial supply is polysegmental, with four paired contributions:[7][12]
| Artery | Origin | Territory |
|---|---|---|
| Vaginal artery | Internal iliac (anterior division) | Dominant middle / lower vagina |
| Descending vaginal branch of uterine artery | Uterine artery (at the point where it crosses the ureter) | Upper vagina and cervix |
| Internal pudendal artery (perineal branches) | Internal iliac | Lower vagina and introitus |
| Middle rectal artery | Variable origin; often from the internal pudendal or inferior gluteal artery[38] | Posterior vaginal wall |
In anterior-wall biopsies from 32 women, microvessel density was greater in the distal third than in the proximal third in both the lamina propria and muscle layer.[13]
Venous drainage parallels the arteries to the vaginal venous plexus and into the internal iliac veins.
Lymphatic drainage split:
- Upper vagina. Drains to the internal iliac and external iliac (obturator) nodes.
- Middle vagina. Drains to the internal and external iliac nodes.
- Lower vagina and introitus. Drains to the superficial inguinal nodes.
For surgically treated stage I primary vaginal squamous carcinoma, the 2023 ESTRO/ESGO/SIOPe guideline recommends pelvic lymph-node assessment for tumors involving the upper two-thirds of the vagina and surgical inguinal lymph-node assessment for lower-third involvement (both [IV, A]).[36]
Innervation
Two distinct territories:[13][14][15][16]
| Region | Dominant supply | Functional notes |
|---|---|---|
| Upper vagina (above pelvic diaphragm) | Autonomic fibers from the inferior hypogastric (pelvic) plexus — sympathetic T10–L2 and parasympathetic S2–S4 | Sparse sensory supply; dilation and distension are the main perceived sensations; visceral afferents travel with the pelvic nerve |
| Lower vagina (below pelvic diaphragm) | Pudendal nerve (S2–S4) — perineal branches to introitus and distal vaginal mucosa | Dense somatic sensation; the introital territory shares its sensory map with the vestibule |
In anterior-wall biopsies from 32 women, small-nerve-fiber density was greater in the distal third than the proximal third.[13] The authors proposed that distal anterior repair could disrupt this neurovascular tissue and affect sexual function, but they did not measure sensation or postoperative outcomes.[13]
Autonomic input drives transudation-based lubrication during arousal, smooth-muscle tone, and vascular engorgement.
Secretion, pH, and the Microbiome (operative level)
The vagina has no glands. Luminal fluid comes from:
- Transudate across the permeable superficial epithelium
- Cervical mucus descending from the endocervix
- Bartholin and Skene-gland secretions
- Desquamated epithelial cells
In many reproductive-age patients, vaginal pH is approximately 3.8–4.5. Estrogen supports epithelial glycogen accumulation; its breakdown products can be metabolized by lactobacilli to lactic acid. Lactobacillus-dominant communities include L. crispatus, L. iners, L. gasseri and L. jensenii.[9][17][40][41] Practical consequences:
- Postmenopausal atrophy can raise vaginal pH, reduce lactobacilli, and present with atrophic vaginitis. Bacterial vaginosis and candidiasis can also occur after menopause.[34] Elevated pH alone does not establish either diagnosis; Candida vaginitis is usually associated with pH <4.5.[32][33]
- Vaginal estrogen may be considered for bothersome menopause-associated genitourinary symptoms. For GSM-related vulvovaginal discomfort or irritation, dryness or dyspareunia, the 2025 AUA/SUFU/AUGS guideline gives a Strong Recommendation (Grade C) to offer local low-dose vaginal estrogen.[42] In the IMPROVE trial, surgeons rated estrogen-treated tissue more favorably at surgery.[6]
Biomechanics — What Fails in Prolapse
The vagina is fibromuscular, and murine testing demonstrates biaxial mechanical responses and pressure-dependent creep.[11][18] In a 2025 human biaxial study, directional stiffness differences appeared in some premenopausal groups but not in postmenopausal or stage III prolapse groups.[39] A finite-element model simulated pelvic-support loading.[20]
Prolapse may involve several interacting supports:
- Levator ani (pubovisceral) impairment leads to opening of the genital hiatus
- Apical (Level I) support failure leads to proximal descent
- Paravaginal (Level II) and distal (Level III) failure leads to a compartment-specific bulge
Operative planning assesses apical, compartment and levator findings together. Apical suspension and compartment repair are selected for the patient's actual defects.
Developmental Origin
Human fetal immunostaining and histologic reconstructions support replacement of Müllerian by urogenital-sinus epithelium during vaginal development; an earlier immunostaining series interpreted fornix epithelium as Müllerian in origin.[23][24][25] Müllerian epithelium is progressively replaced by UGS epithelium in a caudal-to-cranial direction, beginning around weeks 10–13 and reaching the uterovaginal junction around weeks 15–19 in the series reviewed by Hülsman et al.[23]
Clinical consequences:
- Müllerian anomalies (vaginal agenesis, transverse septum, duplicated vagina) reflect disordered Müllerian-duct fusion and descent but not UGS development.
- In-utero DES exposure is associated with a small risk of clear-cell adenocarcinoma of the vagina or cervix, estimated at approximately 1 in 1,000 exposed women through age 34.[37]
- Vaginal elongation or neovaginal reconstruction in Müllerian agenesis (MRKH) usually begins with primary dilation when the patient is ready; surgery may use a skin graft (McIndoe), peritoneum (Davydov), buccal mucosa, or a bowel segment (sigmoid or ileum). A short distal vagina or vaginal dimple may be present.[30] Tissue-engineered scaffolds have been described in a four-patient pilot series.[31]
Clinical Correlations for the Reconstructive Surgeon
- Apical prolapse reconstruction. Sacrocolpopexy (mesh to sacral promontory), uterosacral ligament suspension (USLS) and sacrospinous ligament fixation (SSLF) are established apical options with different routes and trade-offs. Add anterior, posterior or paravaginal repair when the patient's compartment findings warrant it; none is universally required with every apical suspension.
- Paravaginal defect repair. Loss of lateral anterior-wall support at the ATFP can contribute to cystocele, but physical examination does not consistently identify a paravaginal defect or distinguish it from levator-related descent.[46] Paravaginal repair reattaches the pubocervical fascia to the ATFP via retropubic or vaginal approach.
- Anterior colporrhaphy. Addresses a central (distension) Level-II defect; apical support is assessed at the same operation. Mesh-augmented anterior repair has been curtailed by the FDA-mandated transvaginal-mesh limitations.
- Posterior colporrhaphy and rectocele repair. Plicates the rectovaginal fascia; the perineal body is reconstructed at the distal (Level-III) terminus. A perineal-body deficiency can account for some "recurrent rectoceles" after posterior colporrhaphy.
- Vaginal hysterectomy. Uses the vaginal fornices as the access route; the apex is anchored to the uterosacral-cardinal complex at closure to prevent subsequent vault prolapse.
- Vesicovaginal fistula (VVF). Pelvic surgery is an important cause of non-obstetric VVF, but location and mechanism vary. Latzko partial colpocleisis and transvaginal layered closure, sometimes with tissue interposition, are useful options; an abdominal route may be appropriate for a high fixed vault fistula or other anatomy inaccessible vaginally. The approach and flap choice are tailored to size, tissue quality, prior radiation and ureteric involvement.[27] For radiation-associated fistula repair, the EAU weakly recommends a tissue interposition graft.[27]
- Rectovaginal fistula (RVF). Obstetric (OASIS-related), inflammatory (Crohn's), or post-radiation. Repair depends on etiology, location, and sphincter status: transvaginal advancement flap, transperineal rectovaginal septum repair, gracilis interposition, or definitive diversion.
- Urethrovaginal fistula (UVF). Most commonly iatrogenic (anti-incontinence surgery, diverticulectomy). Layered vaginal-flap repair with catheter drainage; an interposition flap (Martius, peritoneal, or gracilis) may be used when tissue quality or defect complexity warrants it.[27] Urethrovaginal fistula repair may be complicated by stress urinary incontinence, urethral stricture or shortening, which may require long-term follow-up.[27]
- Vaginal stenosis and reconstruction. Post-radiation, post-LS, post-FGM, post-radical cystectomy, or congenital (MRKH). Options: dilator therapy, vaginal-wall flaps, buccal-graft neovagina, sigmoid / ileal neovagina, peritoneal (Davydov) neovagina.
- Vaginoplasty.
- Primary neovagina (MRKH, DSD, gender-affirming): McIndoe (split-thickness graft on stent), Davydov (peritoneum), Vecchietti (traction-dilation), sigmoid (ample length, self-lubricating but colitis risk, rare adenocarcinoma), ileum (adequate length, less mucus output).
- Gender-affirming vaginoplasty. Penile skin inversion, scrotal graft, or pedicled bowel is used as the neovaginal lining; in penile-inversion vaginoplasty, the canal is dissected posterior to the prostate and urethra and anterior to the rectum, ending at the peritoneal reflection when the peritoneum is not used.[47] Peritoneal-flap techniques use peritoneum to construct the vaginal apex.[48]
- Vaginal cuff dehiscence. A complication of hysterectomy (particularly total laparoscopic hysterectomy); presents as postcoital bleeding, evisceration or acute abdomen with bowel through the cuff. Emergent repair may be transvaginal or abdominal, with tissue-preserving closure. Smoking is an identified risk factor after minimally invasive hysterectomy.[43]
- Clear-cell adenocarcinoma of the vagina. A DES-exposure sequela arising from residual Müllerian vaginal epithelium; historically seen in the upper anterior vagina of women exposed in utero.
- Vaginal SCC. Rare, usually upper vagina, HPV-associated. Treatment depends on stage: radiation for most, surgery for small, superficial, or distal tumors (partial or radical vaginectomy with LND dictated by site).
- Pessary fitting. Vaginal dimensions and support, genital-hiatus size, patient comfort and the chosen device all matter; more than one fitting may be needed.[28][29] Consider vaginal estrogen for concomitant menopause-associated genitourinary symptoms.[28] A 2025 placebo-controlled ring-pessary trial did not improve its 12-month continuation-plus-improvement primary outcome.[29] In secondary outcomes, erosion or ulcer (4/208 versus 14/203) and bleeding (3/208 versus 13/203) were less frequent with estrogen; these findings need cautious interpretation.[29]
- Perioperative vaginal estrogen. In the Rahn 2023 IMPROVE trial, estrogen-treated tissue appeared more estrogenized and was rated more robust by surgeons, and some participants with bothersome atrophy symptoms improved. However, 12-month composite surgical failure was not lower with estrogen (model-estimated 19% versus 9% with placebo; adjusted HR 1.97, 95% CI 0.92–4.22)[6]; a 36-month follow-up likewise found no significant surgical-success benefit.[26] In a separate 2026 trial of postmenopausal women having primary native-tissue prolapse repair (311 randomized; 293 had surgery and started treatment; 57 dropped out), 92% in the perioperative estriol group versus 80% in the placebo group reported their prolapse symptoms were “much” or “very much” improved on the PGI-I at 12 months; anatomic and composite surgical success did not differ.[49]
- Vaginal packing. Packs may be used selectively for hemostasis, flap support or graft splinting. Routine packing after vaginal hysterectomy showed no clear reduction in bleeding, hematoma or cuff infection across four trials (337 participants), and a systematic review advised against routine use.[44] If a pack is used, 24-hour dwell is not obligatory: a trial found no benefit to retaining both pack and catheter for 24 rather than 3 hours after vaginal surgery.[45]
References
1. Barnhart KT, Izquierdo A, Pretorius ES, et al. "Baseline Dimensions of the Human Vagina." Hum Reprod. 2006;21(6):1618–1622. doi:10.1093/humrep/del022
2. Pendergrass PB, Reeves CA, Belovicz MW, Molter DJ, White JH. "The Shape and Dimensions of the Human Vagina as Seen in Three-Dimensional Vinyl Polysiloxane Casts." Gynecol Obstet Invest. 1996;42(3):178–182. doi:10.1159/000291946
3. Luo J, Betschart C, Ashton-Miller JA, DeLancey JO. "Quantitative Analyses of Variability in Normal Vaginal Shape and Dimension on MR Images." Int Urogynecol J. 2016;27(7):1087–1095. doi:10.1007/s00192-016-2949-0
4. Haylen BT, Vu D, Wong A, Livingstone S. "Surgical Anatomy of the Mid-Vagina." Neurourol Urodyn. 2022;41(6):1293–1304. doi:10.1002/nau.24994
5. Appelbaum AH, Zuber JK, Levi-D'Ancona R, Cohen HL. "Vaginal Anatomy on MRI: New Information Obtained Using Distention." South Med J. 2018;111(11):691–697. doi:10.14423/SMJ.0000000000000889
6. Rahn DD, Richter HE, Sung VW, Pruszynski JE, Hynan LS. "Perioperative Vaginal Estrogen as Adjunct to Native Tissue Vaginal Apical Prolapse Repair: A Randomized Clinical Trial." JAMA. 2023;330(7):615–625. doi:10.1001/jama.2023.12317
7. Zulfiqar M, Shetty A, Yano M, et al. "Imaging of the Vagina: Spectrum of Disease With Emphasis on MRI Appearance." Radiographics. 2021;41(5):1549–1568. doi:10.1148/rg.2021210018
8. Patton DL, Thwin SS, Meier A, et al. "Epithelial Cell Layer Thickness and Immune Cell Populations in the Normal Human Vagina at Different Stages of the Menstrual Cycle." Am J Obstet Gynecol. 2000;183(4):967–973. doi:10.1067/mob.2000.108857
9. American College of Obstetricians and Gynecologists. "Vaginitis in Nonpregnant Patients: ACOG Practice Bulletin, Number 215." Obstet Gynecol. 2020;135(1):e1–e17. doi:10.1097/AOG.0000000000003604
10. Blaskewicz CD, Pudney J, Anderson DJ. "Structure and Function of Intercellular Junctions in Human Cervical and Vaginal Mucosal Epithelia." Biol Reprod. 2011;85(1):97–104. doi:10.1095/biolreprod.110.090423
11. White SE, Conway CK, Clark GL, et al. "Biaxial Basal Tone and Passive Testing of the Murine Reproductive System Using a Pressure Myograph." J Vis Exp. 2019;(150). doi:10.3791/60125
12. Höckel M, Horn LC, Fritsch H. "Association Between the Mesenchymal Compartment of Uterovaginal Organogenesis and Local Tumour Spread in Stage IB-IIB Cervical Carcinoma." Lancet Oncol. 2005;6(10):751–756. doi:10.1016/S1470-2045(05)70324-7
13. Li T, Liao Q, Zhang H, et al. "Anatomic Distribution of Nerves and Microvascular Density in the Human Anterior Vaginal Wall: Prospective Study." PLoS One. 2014;9(11):e110239. doi:10.1371/journal.pone.0110239
14. Barry CM, Ji E, Sharma H, et al. "Morphological and Neurochemical Differences in Peptidergic Nerve Fibers of the Mouse Vagina." J Comp Neurol. 2017;525(10):2394–2410. doi:10.1002/cne.24214
15. Wecht JM, Krassioukov AV, Alexander M, et al. "International Standards to Document Autonomic Function Following SCI (ISAFSCI): Second Edition." Top Spinal Cord Inj Rehabil. 2021;27(2):23–49. doi:10.46292/sci2702-23
16. Hoyle CH, Stones RW, Robson T, Whitley K, Burnstock G. "Innervation of Vasculature and Microvasculature of the Human Vagina by NOS and Neuropeptide-Containing Nerves." J Anat. 1996;188(Pt 3):633–644. PMID 8763480
17. Paavonen J, Brunham RC. "Bacterial Vaginosis and Desquamative Inflammatory Vaginitis." N Engl J Med. 2018;379(23):2246–2254. doi:10.1056/NEJMra1808418
18. Clark-Patterson GL, McGuire JA, Desrosiers L, et al. "Investigation of Murine Vaginal Creep Response to Altered Mechanical Loads." J Biomech Eng. 2021;143(12):121008. doi:10.1115/1.4052365
19. Kieserman-Shmokler C, Swenson CW, Chen L, et al. "From Molecular to Macro: The Key Role of the Apical Ligaments in Uterovaginal Support." Am J Obstet Gynecol. 2020;222(5):427–436. doi:10.1016/j.ajog.2019.10.006
20. Xu Z, Chen N, Wang B, et al. "Creation of the Biomechanical Finite Element Model of Female Pelvic Floor Supporting Structure Based on Thin-Sectional High-Resolution Anatomical Images." J Biomech. 2023;146:111399. doi:10.1016/j.jbiomech.2022.111399
21. Chen L, Ashton-Miller JA, Hsu Y, DeLancey JO. "Interaction Among Apical Support, Levator Ani Impairment, and Anterior Vaginal Wall Prolapse." Obstet Gynecol. 2006;108(2):324–332. doi:10.1097/01.AOG.0000227786.69257.a8
22. Lamblin G, Delorme E, Cosson M, Rubod C. "Cystocele and Functional Anatomy of the Pelvic Floor: Review and Update of the Various Theories." Int Urogynecol J. 2016;27(9):1297–1305. doi:10.1007/s00192-015-2832-4
23. Hülsman CJM, Köhler SE, Morosan-Puopolo G, Hikspoors JPJM, Lamers WH. "The Development of the Human Female Reproductive Tract: Part 2 — Vagina." Clin Anat. 2026;39(1):112–131. doi:10.1002/ca.70015
24. Robboy SJ, Kurita T, Baskin L, Cunha GR. "New Insights Into Human Female Reproductive Tract Development." Differentiation. 2017;97:9–22. doi:10.1016/j.diff.2017.08.002
25. Fritsch H, Hoermann R, Bitsche M, Pechriggl E, Reich O. "Development of Epithelial and Mesenchymal Regionalization of the Human Fetal Utero-Vaginal Anlagen." J Anat. 2013;222(4):462–472. doi:10.1111/joa.12029
26. Rahn DD, Richter HE, Sung VW, Pruszynski JE. "Three-Year Outcomes of a Randomized Clinical Trial of Perioperative Vaginal Estrogen as Adjunct to Native Tissue Vaginal Apical Prolapse Repair." Am J Obstet Gynecol. 2024;231(2):263.e1–263.e10. doi:10.1016/j.ajog.2024.04.042
27. European Association of Urology. "Disease Management," §4.8, EAU Guidelines on Non-neurogenic Female LUTS. Current online guideline (accessed September 20, 2026).
28. National Institute for Health and Care Excellence. Urinary Incontinence and Pelvic Organ Prolapse in Women: Management. NG123, recommendations 1.7.3–1.7.8. NICE guidance (accessed September 20, 2026).
29. Zhou Y, et al. "Effects of Intravaginal Conjugated Oestrogen on Pessary Continuation for Pelvic Organ Prolapse: Multicentre, Randomised, Double Blind, Placebo Controlled Trial." BMJ. 2025;389:e084418. doi:10.1136/bmj-2025-084418
30. American College of Obstetricians and Gynecologists. "Müllerian Agenesis: Diagnosis, Management, and Treatment." Obstet Gynecol. 2018;131(1):e35–e42. doi:10.1097/AOG.0000000000002458
31. Raya-Rivera AM, Esquiliano D, Fierro-Pastrana R, et al. "Tissue-engineered autologous vaginal organs in patients: a pilot cohort study." Lancet. 2014;384(9940):329–336. doi:10.1016/S0140-6736(14)60542-0
32. Centers for Disease Control and Prevention. "Bacterial Vaginosis." STI Treatment Guidelines. Guideline chapter (accessed October 4, 2026).
33. Centers for Disease Control and Prevention. "Vulvovaginal Candidiasis." STI Treatment Guidelines. Guideline chapter (accessed October 4, 2026).
34. Nyirjesy P. "Postmenopausal vaginitis." Curr Infect Dis Rep. 2007;9(6):480–484. doi:10.1007/s11908-007-0073-5
35. Kleeman SD, Westermann C, Karram MM. "Rectoceles and the anatomy of the posterior vaginal wall: revisited." Am J Obstet Gynecol. 2005;193(6):2050–2055. doi:10.1016/j.ajog.2005.07.096
36. Nout RA, Calaminus G, Planchamp F, et al. "ESTRO/ESGO/SIOPe Guidelines for the management of patients with vaginal cancer." Int J Gynecol Cancer. 2023;33(8):1185–1202. doi:10.1136/ijgc-2023-004695
37. Melnick S, Cole P, Anderson D, Herbst A. "Rates and risks of diethylstilbestrol-related clear-cell adenocarcinoma of the vagina and cervix. An update." N Engl J Med. 1987;316(9):514–516. doi:10.1056/NEJM198702263160905
38. Kim H, Youn KH, Kim YS. "Anatomical classification of middle rectal arteries regarding detailed vasculature patterns." Anat Cell Biol. 2022;55(2):118–123. doi:10.5115/acb.22.010
39. Zhou Q, Li G, Kiley JX, et al. "Vaginal biomechanical function in premenopausal and postmenopausal women with and without pelvic organ prolapse." Sci Rep. 2025;15(1):27039. doi:10.1038/s41598-025-11094-8
40. Ravel J, Gajer P, Abdo Z, et al. "Vaginal microbiome of reproductive-age women." Proc Natl Acad Sci U S A. 2011;108 Suppl 1:4680–4687. doi:10.1073/pnas.1002611107
41. Spear GT, McKenna M, Landay AL, et al. "Effect of pH on cleavage of glycogen by vaginal enzymes." PLoS One. 2015;10(7):e0132646. doi:10.1371/journal.pone.0132646
42. American Urological Association, Society of Urodynamics, Female Pelvic Medicine & Urogenital Reconstruction, American Urogynecologic Society. Genitourinary Syndrome of Menopause: AUA/SUFU/AUGS Guideline. 2025. Full guideline
43. Zorzato PC, Vizza R, Garzon S, et al. "Incidence and Prevention of Vaginal Cuff Dehiscence After Laparoscopic and Robotic Hysterectomy in Benign Conditions: An Updated Systematic Review and Meta-Analysis." Medicina (Kaunas). 2025;61(4):647. doi:10.3390/medicina61040647
44. Porta-Roda O, Cornet-Cortada A, Font-Vilamitjana A, Huguet-Galofré E, Lleberia-Juanós J, Solà-Arnau I. "Vaginal packing after vaginal hysterectomy: systematic review and recommendations." Int Urogynecol J. 2023;34(4):789–796. doi:10.1007/s00192-022-05331-1
45. Rajan P, Soundara Raghavan S, Sharma D. "Study comparing 3 hour and 24 hour post-operative removal of bladder catheter and vaginal pack following vaginal surgery: a randomised controlled trial." BMC Womens Health. 2017;17(1):78. doi:10.1186/s12905-017-0431-x
46. Arenholt LTS, Pedersen BG, Glavind K, Glavind-Kristensen M, DeLancey JOL. "Paravaginal defect: anatomy, clinical findings, and imaging." Int Urogynecol J. 2017;28(5):661–673. doi:10.1007/s00192-016-3096-3
47. Pariser JJ, Kim N. "Transgender vaginoplasty: techniques and outcomes." Transl Androl Urol. 2019;8(3):241–247. doi:10.21037/tau.2019.06.03
48. Coon D, Morrison SD, Morris MP, et al. "Gender-Affirming Vaginoplasty: A Comparison of Algorithms, Surgical Techniques and Management Practices across 17 High-volume Centers in North America and Europe." Plast Reconstr Surg Glob Open. 2023;11(5):e5033. doi:10.1097/GOX.0000000000005033
49. Vodegel EV, van Rest K, Speksnijder L, et al. "Vaginal Oestrogen Therapy for Postmenopausal Women Undergoing Prolapse Surgery: A Multicentre Double-Blind Randomised Placebo-Controlled Clinical Trial." BJOG. Published online August 28, 2026. doi:10.1111/1471-0528.70311