The Anal Canal
The anal canal is the terminal segment of the GI tract, extending from the anorectal junction to the anal verge.[1] The cited ASCRS guideline describes this surgical segment as approximately 4–5 cm long.[2]
See also The Perineum for the surrounding fascial pouches and neurovascular supply; The Bladder for the neurogenic-bladder patterns that coexist with anorectal dysfunction in SCI; and Bowel Anatomy for the rectum and sigmoid.
Anatomical Boundaries and the Dentate Line
The anal canal lies between the anorectal junction and the anal verge, where anoderm transitions to hair-bearing perianal skin. The peritoneal reflection is a separate, more proximal landmark.
The dentate (pectinate) line is a principal anatomic landmark in anorectal surgery. Jacobs places it about 3–4 cm above the anal verge.[6] In an MRI study of 70 patients with anal fistula, the mucosal-landmark estimate averaged 2.0 ± 0.53 cm in the 35 patients assessed by that method.[33] It marks a quadruple transition:[2][3]
| Domain | Above the dentate line | Below the dentate line |
|---|---|---|
| Epithelium | Columnar (rectal mucosa) → transitional zone immediately above the line | Non-keratinized squamous (anoderm) → keratinized perianal skin at the verge |
| Innervation | Predominantly visceral sensory pathways | Somatic (pudendal) — sensitive anoderm |
| Venous drainage | Superior rectal vein → inferior mesenteric → portal system | Inferior rectal vein → internal pudendal → systemic (caval) system |
| Lymphatic drainage | Perirectal and paravertebral → inferior mesenteric nodes; also internal iliac nodes[30] | Inguinal and femoral nodes |
The anal transitional zone (ATZ) lies near the junction of rectal columnar mucosa and squamous anoderm. Epithelial transitions are more complex than a sharp line; this region is relevant to HPV-related neoplasia.[2][25]
The columns of Morgagni, vertical mucosal folds above the dentate line, contain the terminal branches of the superior rectal artery and vein. The anal crypts between the columns communicate with anal glands that penetrate into the intersphincteric space, the anatomic origin of cryptoglandular abscess and fistula-in-ano.
Sphincter Complex
Internal anal sphincter (IAS)
A 0.3–0.5 cm thick expansion of the circular smooth muscle of the rectum.[1][7]
- Autonomic and intrinsic control. Resting smooth-muscle tone and relaxation are influenced by extrinsic and enteric mechanisms.
- Provides much of the resting anal pressure through tonic smooth-muscle contraction.[1][8]
- Relaxes reflexively on rectal distension (RAIR) to allow "sampling" of rectal contents by the sensory-rich upper anal canal.
- Injury pattern. IAS injury can contribute to passive stool or mucus leakage.[26]
External anal sphincter (EAS)
A 0.6–1.0 cm thick striated muscle ring under voluntary (pudendal S2–S4) control.[1][7][10]
The traditional description separates three subdivisions, with anatomical overlap and variable nerve branching. Nerve branching is variable, so a rigid one-nerve-per-layer map is unreliable for operative dissection.[4][10][12] The deep (proximal) EAS does not always close into a complete anterior ring: an endosonographic study of 93 nulliparous women and 21 men found the deep EAS annular in 72% of females and 76% of males, and found it shorter anteriorly in women than in men.[29] This normal anatomic variant can be misread as a sphincter defect on endoanal ultrasound, particularly anteriorly, the direction of classic obstetric injury.[29]
| Subdivision | Anatomical relationship |
|---|---|
| Subcutaneous | Most distal and superficial portion around the anal orifice |
| Superficial | Related to the perineal body and posterior attachments |
| Deep | Closely related to puborectalis superiorly |
- Predominantly slow-twitch, fatigue-resistant fibers. These can sustain contraction for prolonged periods.
- Contributes to resting pressure and produces voluntary squeeze pressure.[1][8] Pressure measurements depend on the method and patient.[1][8]
- Injury pattern. EAS injury can contribute to urgency-associated leakage.[26]
The EAS overlaps the distal IAS by approximately 1–2 cm; the entire sphincter complex extends approximately 4 cm up the anal canal.[4]
Puborectalis
A U-shaped sling of the levator ani that wraps around the anorectal junction and maintains the anorectal angle:[1][12]
- Approximately 90° at rest, approximately 70° with squeeze, approximately 110–130° during defecation.[1]
- Contributes to closure by maintaining anorectal angulation and acting with the sphincters.[12]
- Paradoxical contraction (failure to relax on attempted defecation) is the anatomic substrate of dyssynergic defecation or anismus.
Longitudinal muscle (conjoint longitudinal coat)
Lies in the intersphincteric space between IAS and EAS; continuous with the longitudinal muscle of the rectum and with extensions to the coccyx, perineal body, and endopelvic fascia. It forms a "suspensory diaphragm" for the anorectal junction and may assist straightening of the anorectal angle during defecation.[12]
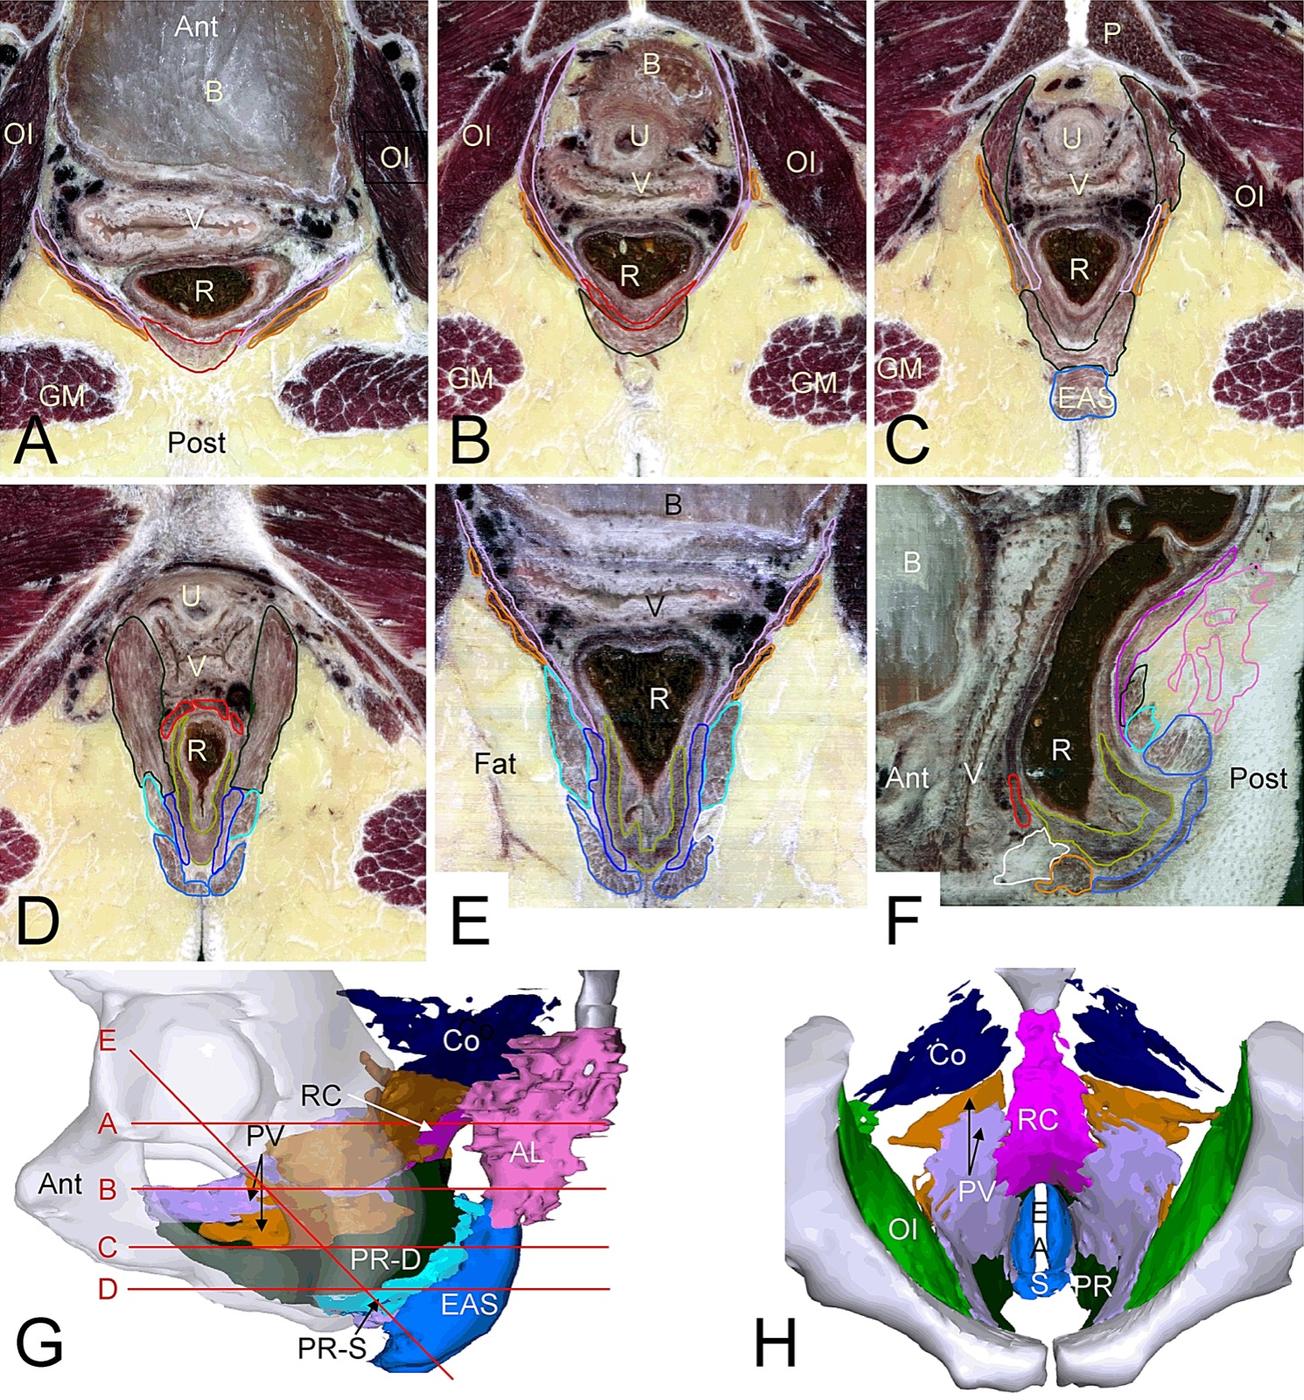
Architecture of the levator ani and anal-sphincter complex from undeformed serial anatomical sections. Transverse sections (A-D) and an oblique section (E), with their positions marked on the reconstruction in G, show the bilayered pubovisceral muscle (A-C) and its attachment to the rectococcygeal muscle (A, B), the extension of the pubovisceral and deep puborectal muscles to the pubic bone (B, C), the external anal sphincter, the superficial puborectal muscle and the conjoint longitudinal muscle of the rectum (C-E), and the rectoperineal muscle (D). E shows the successive layers of the sphincter complex; F, a calculated midsagittal section, shows the muscles surrounding the anal canal. G and H are reconstructions seen from the left and anterosuperiorly. AL, anococcygeal ligament; B, bladder; Co, coccygeal muscle; EAS, external anal sphincter; GM, gluteus maximus; OI, obturator internus; PR-D and PR-S, deep and superficial puborectal muscle; PV, pubovisceral muscle; R, rectum; RC, rectococcygeal muscle; U, urethra; V, vagina. From Wu Y, et al. PLoS One. 2015;10(8):e0132226, Fig 1 (CC BY).[12]
Mucosal Anatomy and the Anal Cushions
Three epithelial zones line the canal (see dentate-line table above). The anoderm (below the dentate) is a modified squamous epithelium without hair follicles or sweat glands; it is thin, pale, and exquisitely sensitive.
Anal cushions (hemorrhoidal tissue)
Submucosal fibrovascular arteriovenous sinusoids that are normal anatomy, not pathology:[5][6][14]
- Three classical positions: left lateral, right anterolateral, right posterolateral.
- Covered by anal mucosa above the dentate (internal hemorrhoids) or squamous epithelium below (external hemorrhoids).
- Help form the mucosal seal; they complement muscular closure.[5]
- Functions: sensing fullness and anal contents, supporting sphincter closure, protecting the sphincter during defecation.
- Become symptomatic (hemorrhoidal disease) when they enlarge, bleed, or prolapse due to loss of the anchoring mucosal suspensory ligament (Treitz's ligament of the anal canal) or to chronic straining. Internal hemorrhoids are graded I–IV by prolapse; this grading does not apply to external hemorrhoids.[14][24]
Vascular Supply
Arterial — triple supply with rich anastomosis
| Artery | Origin | Territory |
|---|---|---|
| Superior rectal | Terminal branch of the inferior mesenteric artery | Mucosa above the dentate line; dominant supply to the anal cushions |
| Middle rectal | Internal iliac artery (variable) | Muscular wall of the lower rectum and upper canal; assess the whole remaining blood supply during reconstruction[10] |
| Inferior rectal | Internal pudendal artery (Alcock's canal) | Anal canal below the dentate line; crosses the ischiorectal fossa |
Venous — portal/systemic watershed
The dentate line divides two drainage territories:[6]
- Internal rectal venous plexus (above) drains via the superior rectal vein to the portal system. Engorgement produces internal hemorrhoids.
- External rectal venous plexus (below) drains via the inferior rectal veins to the systemic circulation (internal pudendal, then internal iliac). Thrombosis produces painful external hemorrhoids.
This watershed explains why portal hypertension can produce anorectal varices (distinct from hemorrhoids) and why anal-canal carcinoma above the dentate can, rarely, produce hepatic metastases via the portal route.
Lymphatic drainage — governs cancer workup
- Above the dentate. Lymph drains to perirectal and inferior mesenteric nodes and also to internal iliac nodes.[30]
- Below the dentate. Drains to inguinal and femoral nodes.
Anal-cancer evaluation includes inguinal examination; an anal squamous carcinoma above the dentate line should not automatically be evaluated as rectal adenocarcinoma. Use the tumor's site, histology and current oncology pathway.[25]
Recent ICG-fluorescence studies describe widespread anorectal lymphatic networks spreading across the levator ani surface and hiatal ligament; the networks are broader than classical descriptions suggest.[15][16]
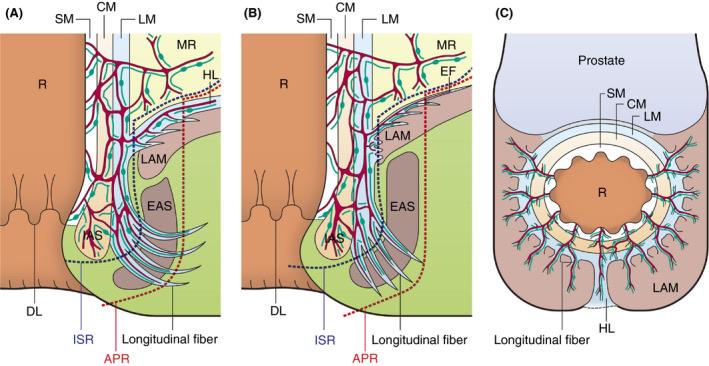
Lymphovascular flow around the anal canal. (A) Sagittal section of the posterior wall. (B) Frontal section of the lateral and anterolateral wall. (C) Male axial section around the anal canal and levator ani. Blood vessels (red) and initial lymphatics (green, with round dots) communicate from the longitudinal muscle to the hiatal ligament, endopelvic fascia and longitudinal fibers. Resection lines of intersphincteric resection (blue dotted line) and standard abdominoperineal resection (red dotted line) are shown in A and B. CM, circular muscle; DL, dentate line; EAS, external anal sphincter; EF, endopelvic fascia; HL, hiatal ligament; IAS, internal anal sphincter; LAM, levator ani muscle; LM, longitudinal muscle; MR, mesorectum; R, rectum; SM, submucosa. From Sato K, et al. Colorectal Dis. 2021;23(6):1334-1345, Figure 7 (CC BY).[15]
Innervation
Five sources converge on the anal canal, a complexity that explains why anorectal functional outcomes are sensitive to pelvic surgery, radiation, and SCI:[1][9][17]
| Source | Origin | Target | Function |
|---|---|---|---|
| Sympathetic | T10–L2 → superior hypogastric plexus → hypogastric nerves | IAS | Maintains IAS tone; inhibits motility |
| Parasympathetic | S2–S4 → pelvic splanchnic nerves | Anorectal smooth muscle and enteric circuits | Modulates anorectal motor activity |
| Somatic (pudendal) | S2–S4, Onuf's nucleus | EAS, anal mucosa below the dentate, perianal skin | Voluntary EAS contraction; somatic sensation |
| Enteric (intrinsic) | Auerbach's and Meissner's plexuses | Rectal and upper-canal smooth muscle | Coordinates motility; ganglion cells mostly restricted to above the dentate[18][19] |
| Sensory afferents | Visceral pelvic pathways and somatic pudendal pathways | Spinal and supraspinal sensory processing | Rectal distension, urge perception and anal sensation; pain is not confined categorically to one side of the dentate line |
The sampling reflex depends on the IAS relaxing (RAIR) to let rectal contents contact the sensory-rich upper anal canal, where receptors discriminate between gas, liquid, and solid. IAS injury or internal sphincterotomy can reduce resting tone and contribute to passive leakage. Discrimination of gas from stool also depends on anal-canal sensation and coordinated reflexes.[8][26]
Perianal and Perirectal Spaces
Five named spaces surround the anal canal and determine abscess / fistula anatomy:[4][11][19]
| Space | Boundaries | Clinical significance |
|---|---|---|
| Intersphincteric | Between IAS and EAS; contains longitudinal muscle, nerves | Origin of cryptoglandular abscess; intersphincteric and transsphincteric tracts are the most frequently encountered fistula types[27] |
| Ischiorectal (ischioanal) | Lateral to the canal; fat, inferior rectal vessels, pudendal branches | Site of ischiorectal abscess; communicates posteriorly via the deep postanal space → horseshoe abscess |
| Perianal | Surrounds the anal verge subcutaneously | Site of superficial abscess; prompt drainage is usually needed, in an office or operating room according to the examination and infection extent[27][31] |
| Supralevator | Above the levator ani | Rare abscess; can result from upward extension of intersphincteric infection or downward extension of pelvic pathology |
| Deep postanal (Courtney) | Posterior, between levator and anococcygeal ligament | Bridge of horseshoe abscess; must be drained to resolve horseshoe fistula |
Understanding these spaces is the anatomic basis of Goodsall's rule (posterior fistulae curve to a posterior midline internal opening; anterior fistulae track radially) and of the Parks classification of fistula-in-ano (submucosal, intersphincteric, transsphincteric, suprasphincteric, extrasphincteric). ASCRS 2022 notes that Goodsall's rule has generally proven accurate for anterior fistulas and is less accurate for posterior ones.[27]
Continence Physiology — Reconstructive Depth
Fecal continence is a multilayered defense, which is why partial injuries are often tolerated and disruption at multiple levels causes severe incontinence:[1][8][20][21]
First line (colonic mechanisms). Retrograde propagating cyclic motor patterns in the sigmoid and rectum prevent continuous transit of contents into the anal canal.[8]
Second line (mechanical barriers):
- IAS tonic contraction
- EAS tonic, reflex and voluntary contraction
- Puborectalis sling and anorectal angulation
- Anal cushions and the mucosal seal
Third line (reflex integration):
- RAIR. The IAS relaxes on rectal distension, allowing sampling.
- Rectoanal contractile reflex. The EAS contracts reflexively during RAIR, providing second-line defense while sampling occurs.
- Guarding reflex. Sudden increases in intra-abdominal pressure recruit the EAS before sphincter pressure is exceeded.
Fourth line (voluntary control):
- Cortical decision to defer defecation, then sustained EAS and puborectalis contraction, then rectal accommodation (compliance absorbs the volume, urgency fades).
Defecation Physiology — Four Phases
Normal defecation requires intact coordination between colon, anorectum, pelvic floor, and CNS:[13][21][22]
| Phase | What happens |
|---|---|
| 1. Basal | Stool stored in the sigmoid and rectum; IAS and puborectalis maintain closure; retrograde motor patterns prevent continuous filling |
| 2. Pre-expulsive | High-amplitude propagating contractions (HAPCs) can propel stool into the rectum, but smaller antegrade or segmental contractions also contribute to filling → rectal distension activates mechanoreceptors and urge → RAIR permits sampling.[22] |
| 3. Expulsive | Voluntary decision to defecate → puborectalis relaxes (angle opens to ~110–130°) → EAS relaxes → IAS continues RAIR → perineal descent (1–3 cm) → Valsalva + rectal contraction expel stool through the open canal |
| 4. Closure | Sphincters re-contract; anorectal angle restored; anal cushions re-seal the lumen |
Dyssynergic defecation involves impaired coordination during attempted evacuation. Diagnosis combines compatible symptoms with anorectal manometry and balloon-expulsion testing; discordant results may require defecography. Biofeedback is the main treatment.[14]
Clinical Correlations for the Reconstructive Surgeon
- OASIS and later incontinence. Third-degree injury involves the anal sphincter complex; fourth-degree injury also disrupts the anorectal mucosa. Assess IAS and EAS separately. Later incontinence requires reassessment of stool consistency, sphincter anatomy and function. For women with prior OASIS, the 2026 IUGA algorithm considers secondary repair when bothersome fecal incontinence coexists with a substantial residual sphincter defect and sphincter contractility on digital rectal examination; absent contractility prompts referral for pelvic health physiotherapy and/or sacral neuromodulation.[34] Sphincteroplasty is an option for selected EAS defects, but repeat reconstruction after a failed overlapping repair is generally discouraged; sacral neuromodulation may be considered with or without a defect.[26]
- Rectourethral fistula. Perineal repair requires dissection between the urinary tract and anterior rectal wall. Tissue quality, radiation injury and defect extent guide the approach and need for vascularized interposition. Avoid transferring a flap list from rectovaginal repair without considering the actual anatomy.
- Rectovaginal fistula. Define cause, tract level, inflammation and sphincter integrity. Local advancement or perineal repair, interposition and abdominal reconstruction suit different situations. Selected obstetric fistulas initially receive nonoperative care.[27]
- Fistula-in-ano (Parks classification). Describe the tract as intersphincteric, transsphincteric, suprasphincteric or extrasphincteric. Fistulotomy is reserved for appropriately selected simple fistulas with preserved sphincter function. LIFT treats a transsphincteric tract through an intersphincteric approach. Prior injury, anterior fistulas in women, recurrence and baseline continence alter selection.[27]
- Hemorrhoidal disease. Evaluate rectal bleeding before attributing it to hemorrhoids; selected patients need colonoscopy when no anorectal source is evident or bleeding persists after treatment .[24] Begin with dietary and bowel-habit measures .[24] Office treatment suits most symptomatic grade I–II and selected grade III internal disease after conservative treatment, with banding considered the most effective office option (strong, moderate). Excisional hemorrhoidectomy should typically be offered to selected patients with external or combined grade III–IV disease (strong, high-quality evidence). ASCRS does not routinely recommend stapled hemorrhoidopexy as first-line surgery for internal hemorrhoids because of marginal efficacy and a significant risk profile (conditional, moderate); Doppler-guided artery ligation may reduce pain but may increase recurrence compared with excision (conditional, moderate).[24] Rectal artery embolization is an emerging intervention; the Cochrane review of its efficacy is at protocol stage.[23][24]
- Anal fissure. A tear in the anoderm, often posterior and associated with elevated sphincter tone. Sphincter-dividing treatment requires an assessment of existing injury and continence, and the risk of postoperative incontinence varies with technique and patient factors.
- Anal SCC. Definitive chemoradiation is the principal treatment for most anal-canal squamous cancers; selected small anal-margin lesions may be excised, and salvage surgery has a role in persistent or recurrent disease. Include inguinal assessment regardless of a simplified dentate-line map.[25]
- Neurogenic bowel in SCI. Reflexic and areflexic bowel patterns help organize care, but symptoms, examination and functional testing determine the individual program. See anorectal testing and defecatory dysfunction.
- Sacral neuromodulation for fecal incontinence. An operative option after conservative treatment, including in patients with sphincter defects.[26] Selection includes a test phase.[26]
- Posterior sagittal anorectoplasty (PSARP) or pull-through. Definitive repair of anorectal malformations in children; the dissection splits the EAS and puborectalis in the posterior midline and reconstructs the anorectal unit within the sphincter complex. Long-term continence depends on the quality of the native sphincter and puborectalis.
- Abdominoperineal resection (APR) and perineal reconstruction. APR removes the anal canal, sphincter complex, and distal rectum en bloc. The resulting perineal defect is reconstructed with primary closure, biologic mesh, or muscle or myocutaneous flaps (gracilis, VRAM) depending on radiation status and defect size.
- Intersphincteric resection (ISR). These ultra-low rectal-cancer operations enter the intersphincteric plane and remove part or all of the IAS while preserving the EAS. Continence outcomes vary with the extent of IAS excision and other functional factors.[32]
- Levator ani syndrome. Exclude structural causes of anorectal pain. Pelvic-floor relaxation and biofeedback have randomized-trial support, particularly when levator palpation reproduces tenderness.[28]
References
1. Rao SS; American College of Gastroenterology Practice Parameters Committee. "Diagnosis and Management of Fecal Incontinence." Am J Gastroenterol. 2004;99(8):1585–1604. doi:10.1111/j.1572-0241.2004.40105.x
2. Stewart DB, Gaertner WB, Glasgow SC, et al. "The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for Anal Squamous Cell Cancers (Revised 2018)." Dis Colon Rectum. 2018;61(7):755–774. doi:10.1097/DCR.0000000000001114
3. Ryan DP, Compton CC, Mayer RJ. "Carcinoma of the Anal Canal." N Engl J Med. 2000;342(11):792–800. doi:10.1056/NEJM200003163421107
4. Stoker J. "Anorectal and Pelvic Floor Anatomy." Best Pract Res Clin Gastroenterol. 2009;23(4):463–475. doi:10.1016/j.bpg.2009.04.008
5. Ashburn JH. "Hemorrhoidal Disease." JAMA. 2025. doi:10.1001/jama.2025.13083
6. Jacobs D. "Hemorrhoids." N Engl J Med. 2014;371(10):944–951. doi:10.1056/NEJMcp1204188
7. Alshiek J, Murad-Regadas SM, Mellgren A, et al. "Consensus Definitions and Interpretation Templates for Dynamic Ultrasound Imaging of Defecatory Pelvic Floor Disorders." Dis Colon Rectum. 2023;66(2):200–216. doi:10.1097/DCR.0000000000002651
8. Trzpis M, Sun G, Chen JH, Huizinga JD, Broens P. "Novel Insights Into Physiological Mechanisms Underlying Fecal Continence." Am J Physiol Gastrointest Liver Physiol. 2023;324(1):G1–G9. doi:10.1152/ajpgi.00313.2021
9. Wecht JM, Krassioukov AV, Alexander M, et al. "International Standards to Document Autonomic Function Following SCI (ISAFSCI): Second Edition." Top Spinal Cord Inj Rehabil. 2021;27(2):23–49. doi:10.46292/sci2702-23
10. Siddharth P, Ravo B. "Colorectal Neurovasculature and Anal Sphincter." Surg Clin North Am. 1988;68(6):1185–1200. doi:10.1016/s0039-6109(16)44680-3
11. Hussain SM, Stoker J, Laméris JS. "Anal Sphincter Complex: Endoanal MR Imaging of Normal Anatomy." Radiology. 1995;197(3):671–677. doi:10.1148/radiology.197.3.7480737
12. Wu Y, Dabhoiwala NF, Hagoort J, et al. "3D Topography of the Young Adult Anal Sphincter Complex Reconstructed From Undeformed Serial Anatomical Sections." PLoS One. 2015;10(8):e0132226. doi:10.1371/journal.pone.0132226
13. Lembo A, Camilleri M. "Chronic Constipation." N Engl J Med. 2003;349(14):1360–1368. doi:10.1056/NEJMra020995
14. Wald A, Bharucha AE, Limketkai B, et al. "ACG Clinical Guidelines: Management of Benign Anorectal Disorders." Am J Gastroenterol. 2021;116(10):1987–2008. doi:10.14309/ajg.0000000000001507
15. Sato K, Shimoda H, Miura T, et al. "Widespread Anorectal Lymphovascular Networks and Tissue Drainage: Analyses From Submucosal India Ink Injection and Indocyanine Green Fluorescence Imaging." Colorectal Dis. 2021;23(6):1334–1345. doi:10.1111/codi.15582
16. Sato K, Kasajima H, Imaizumi K, et al. "Visualization of Anorectal Lymphatic Flow Using Indocyanine Green Fluorescence Imaging: An Observational Study." Anticancer Res. 2023;43(4):1591–1598. doi:10.21873/anticanres.16309
17. Yan Y, Inal B, Kapavarapu P, Alber K, Rao SSC. "Novel Concepts on the Functional Neuroanatomy of the Anorectum: Implications for Anorectal Neuropathy and Neuromodulation Therapy." Am J Gastroenterol. 2024;120(7):1478–1487. doi:10.14309/ajg.0000000000003221
18. Han MN, Furness JB, Ringuet MT, et al. "Gut-Brain Communication: Nerve Circuits and Chemical Messengers of Colorectal Motility Control Pathways." Am J Physiol Regul Integr Comp Physiol. 2025. doi:10.1152/ajpregu.00212.2025
19. Hieda K, Cho KH, Arakawa T, et al. "Nerves in the Intersphincteric Space of the Human Anal Canal With Special Reference to Their Continuation to the Enteric Nerve Plexus of the Rectum." Clin Anat. 2013;26(7):843–854. doi:10.1002/ca.22227
20. Bajwa A, Emmanuel A. "The Physiology of Continence and Evacuation." Best Pract Res Clin Gastroenterol. 2009;23(4):477–485. doi:10.1016/j.bpg.2009.06.002
21. Heitmann PT, Vollebregt PF, Knowles CH, et al. "Understanding the Physiology of Human Defaecation and Disorders of Continence and Evacuation." Nat Rev Gastroenterol Hepatol. 2021;18(11):751–769. doi:10.1038/s41575-021-00487-5
22. Santucci NR, Velez A. "Physiology of Lower Gastrointestinal Tract." Aliment Pharmacol Ther. 2024;60 Suppl 1:S1–S19. doi:10.1111/apt.17900
23. Khan K, Lakshminarayan R, Yiasemidou M, et al. "Endovascular Rectal Artery Embolisation (RAE) for Symptomatic Haemorrhoids." Review protocol. Cochrane Database Syst Rev. 2024;5:CD014829. doi:10.1002/14651858.CD014829
24. Hawkins AT, Davis BR, Bhama AR, et al. The American Society of Colon and Rectal Surgeons clinical practice guidelines for the management of hemorrhoids. Dis Colon Rectum. 2024;67:614–623. doi:10.1097/DCR.0000000000003276. Full society guideline.
25. National Cancer Institute. Anal cancer treatment (PDQ), health professional version. Initial evaluation and localized-treatment sections accessed September 12, 2026.
26. Bordeianou LG, Thorsen AJ, Keller DS, et al. The American Society of Colon and Rectal Surgeons clinical practice guidelines for the management of fecal incontinence. Dis Colon Rectum. 2023;66:647–661. doi:10.1097/DCR.0000000000002776.
27. Gaertner WB, Burgess PL, Davids JS, et al. The American Society of Colon and Rectal Surgeons clinical practice guidelines for the management of anorectal abscess, fistula-in-ano, and rectovaginal fistula. Dis Colon Rectum. 2022;65:964–985. doi:10.1097/DCR.0000000000002473.
28. Chiarioni G, Nardo A, Vantini I, Romito A, Whitehead WE. Biofeedback is superior to electrogalvanic stimulation and massage for treatment of levator ani syndrome. Gastroenterology. 2010;138:1321–1329. doi:10.1053/j.gastro.2009.12.040.
29. Sultan AH, Kamm MA, Hudson CN, Nicholls JR, Bartram CI. "Endosonography of the Anal Sphincters: Normal Anatomy and Comparison with Manometry." Clin Radiol. 1994;49(6):368–374. doi:10.1016/s0009-9260(05)81819-7
30. Carmichael JC, Mills S. "Anatomy and Embryology of the Colon, Rectum, and Anus." In: Steele SR, Hull TL, Hyman N, et al., eds. The ASCRS Textbook of Colon and Rectal Surgery. 4th ed. Springer; 2022:3–27. doi:10.1007/978-3-030-66049-9_1
31. American Society of Colon and Rectal Surgeons. "Abscess and Fistula." Patient education resource. ASCRS page (accessed October 4, 2026).
32. Denost Q, Rullier E. "Intersphincteric Resection Pushing the Envelope for Sphincter Preservation." Clin Colon Rectal Surg. 2017;30(5):368-376. doi:10.1055/s-0037-1606114
33. Liu X, Wang Z, Ren H, Wang Z, Li J. "Accuracy of magnetic resonance imaging in defining dentate line in anal fistula." BMC Med Imaging. 2022;22(1):201. doi:10.1186/s12880-022-00927-x
34. Sultan AH, Okeahialam NA, De Leeuw J, et al. "IUGA International Guidelines on Obstetric Anal Sphincter Injuries." Int Urogynecol J. 2026;37(8):2223-2280. doi:10.1007/s00192-026-06642-3