GU Embryology
See also The Kidneys, The Ureters, The Bladder; The Prostate & Seminal Vesicles; The Testicles & Scrotum; The Uterus and The Vagina for adult-anatomy articles that reference embryologic origins.
The Three Kidney Systems
Mammalian kidneys develop through three sequential systems in cranio-caudal progression. Only the third becomes the definitive kidney, but the first two leave operative legacies:[1]
| System | Timing | Fate |
|---|---|---|
| Pronephros | Week 3–4 | Rudimentary; regresses fully. Its duct persists and becomes the nephric (Wolffian) duct |
| Mesonephros | Week 4–8 | Interim excretory organ. Regresses in females. In males, selected tubules persist as the efferent ductules of the testis. The mesonephric (Wolffian) duct persists and becomes vas deferens, epididymis, seminal vesicles, and ejaculatory ducts |
| Metanephros | Week 5 onward | The permanent kidney |
Metanephros — reciprocal induction between ureteric bud and mesenchyme
At week 5 the ureteric bud sprouts from the distal Wolffian duct and invades the metanephric mesenchyme. A series of reciprocal inductive interactions (mesenchyme secretes GDNF, and the Wolffian duct expresses RET; epithelium secretes Wnt9b, and the mesenchyme undergoes MET) drives 15–20 generations of ureteric-bud branching and nephron formation.[2][3] Two operative consequences:
- The collecting system (renal pelvis, calyces, collecting ducts) is ureteric-bud–derived; nephrons (glomerulus to distal convoluted tubule) are metanephric-mesenchyme–derived.[1] Separate failures produce different CAKUT phenotypes.
- Nephron induction is completed by approximately 34–36 weeks of gestation. Premature birth truncates nephron endowment, which is a lifelong risk factor for hypertension and CKD.
Ascent of the kidney
The metanephros begins in the pelvis and ascends to its adult lumbar position by week 9, rotating so that the hilum faces medially. Three anomalies stem from this migration:
- Pelvic kidney. Failed ascent. Arterial supply is variable and may arise from the common or external iliac, aorta, mid-sacral or hypogastric vessels rather than the normal renal-artery origin; identify the specific vascular anatomy before pelvic surgery in a patient with a pelvic kidney.[4]
- Horseshoe kidney. Lower-pole fusion is common, but ascent and isthmus position vary; the inferior mesenteric artery does not arrest every horseshoe kidney.[27] The low-lying, malrotated kidneys often have anteriorly facing hila or pelves.[35] Ureteric anomalies, UPJ obstruction, nephrolithiasis, and Wilms tumor in childhood are associated findings.[27]
- Crossed fused renal ectopia. One kidney ascends to the opposite side.
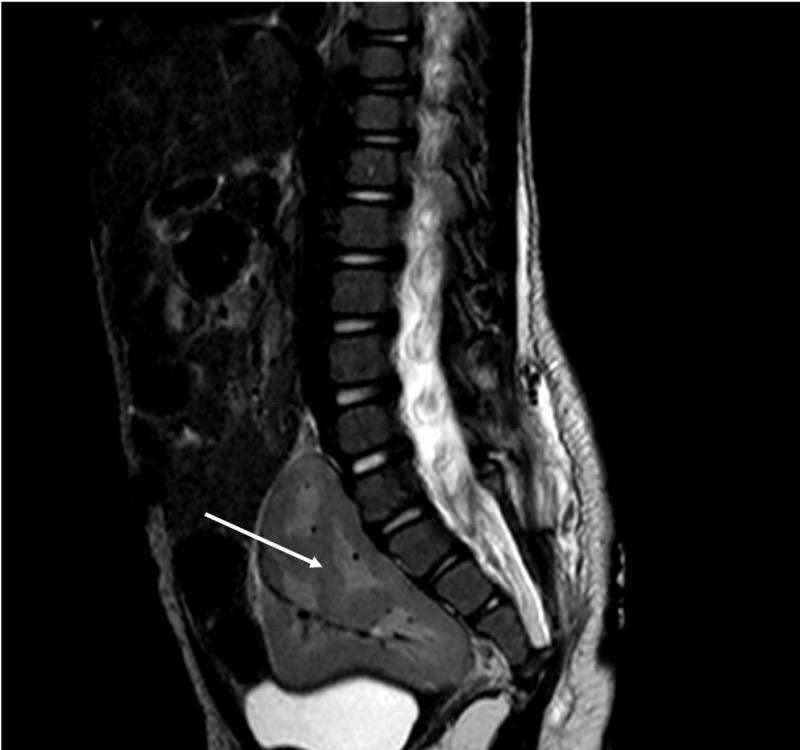
Sagittal T2-weighted MRI of the spine showing an incidental pelvic kidney (arrow), found during evaluation of a midline lumbar cutaneous capillary hemangioma to exclude occult spinal dysraphism; the patient had no pelvic pain or renal dysfunction. From Eid S, et al. Cureus. 2018;10(6):e2775, Figure 1 (CC BY).[4]
Cloaca → Urogenital Sinus → Bladder and Urethra
At week 4 the cloaca is a common hindgut / urogenital chamber closed by the cloacal membrane. During weeks 5–6, the cloaca partitions into:[5]
- Anterior compartment. The urogenital sinus, which forms the bladder, most of the urethra, and (in women) the lower vagina.
- Posterior compartment. The anorectal canal.
Disordered cloacal development can produce persistent cloaca and anorectal malformations, including imperforate anus.[21] Cloacal exstrophy and bladder exstrophy–epispadias complex involve ventral body-wall defects; their embryologic mechanisms remain unresolved.[5]
Bladder and urethra from the urogenital sinus
The urogenital sinus has three zones:
| Zone | Becomes (male) | Becomes (female) |
|---|---|---|
| Vesical (upper) | Bladder | Bladder |
| Pelvic (middle) | Prostatic and membranous urethra | Urethra and sinovaginal bulbs at the junction with the Müllerian-derived uterovaginal canal[5] |
| Phallic (lower) | Penile urethra | Vestibule |
Incorporation of the ureters and the trigone
The ureteric bud arises from the distal Wolffian duct. As the bladder enlarges, a portion of the distal Wolffian duct is absorbed into the developing bladder, carrying the ureter with it. Through remodeling, the ureters migrate to their adult trigonal positions, while the Wolffian duct orifice moves caudally to form the ejaculatory duct (male) or Gartner's duct remnant (female).[5] Failures here produce:
- Vesicoureteral reflux (VUR). Inadequate submucosal tunnel length causes failure of the flap-valve.
- Duplex collecting system. Complete ureteral duplication arises from two ureteric buds; incomplete duplication can arise when one bud divides prematurely.[36]
- Ureterocele. Cystic dilation of the distal ureter, classically of the upper-pole ureter in a duplex system.
- Ectopic ureter. In females, insertion distal to the external sphincter can cause continuous leakage despite normal voiding. In males, insertion proximal to the sphincter can present with recurrent epididymitis.[28]
The Weigert-Meyer rule. In a complete duplex system the upper-pole ureter inserts ectopically, inferomedially (often obstructed, sometimes with ureterocele), and the lower-pole ureter inserts orthotopically or superolaterally (often refluxing due to short tunnel). The relationship helps anticipate insertion and reflux; observation, drainage, partial nephroureterectomy, ureteroureterostomy, or common-sheath reimplantation is selected according to clinical status, moiety function, obstruction, reflux, infection, and bladder-neck involvement.[29]
Urachus
The urachus is the obliterated allantois, remnant of the embryonic connection between the bladder apex and umbilicus. Persistence produces:
- Patent urachus (leakage from the umbilicus in a newborn)
- Urachal cyst (often discovered incidentally or when infected)
- Urachal sinus (external opening at the umbilicus)
- Urachal diverticulum (internal opening to the bladder)
- Urachal adenocarcinoma in adults. A midline dome or anterior-wall bladder tumor; localized disease is commonly managed with partial cystectomy and en-bloc resection of the urachus and umbilicus.[41]
Gonadal Development — The Bipotential Gonad
At week 5 the gonadal ridge forms on the medial aspect of the mesonephros. It begins sexually indifferent. Two tissue streams contribute: the coelomic epithelium (surface / somatic cells) and primordial germ cells that migrate from the yolk sac through the allantois and dorsal mesentery to colonize the ridge.[6]
Transcription factors supporting ridge formation include WT1, SF-1 (NR5A1), Lhx9, Emx2.[7]
Sex determination at week 7
- XY (testis) pathway. SRY on the Y chromosome activates SOX9 in pre-Sertoli cells, with FGF9 feedback. Sertoli cells organize into testis cords, and AMH and testosterone are secreted.[6][8]
- XX (ovary) pathway. Absence of SRY allows activation of RSPO1, WNT4, β-catenin and FOXL2, leading to granulosa-cell commitment; oocytes enter meiotic arrest as primary oocytes.[6][8]
Sex determination is actively bi-directional. Testis- and ovary-promoting pathways oppose each other during embryonic differentiation. In mouse studies, FOXL2 maintains adult granulosa-cell identity, while DMRT1 with SOX9/SOX8 maintains adult Sertoli-cell identity; an adult WNT maintenance role remains uncertain.[38] In mice, adult FOXL2 knockout in granulosa cells can transdifferentiate ovaries to a testis-like fate, which is the basis for certain sex-reversal phenotypes and a conceptual framework for late-onset gonadal dysgenesis.
Testicular development
- Sertoli cells are the first somatic cells to differentiate (week 7); they secrete AMH, which causes Müllerian-duct regression.[8]
- Leydig cells differentiate in the interstitium by week 8; they secrete testosterone, which drives Wolffian-duct development and DHT-dependent external genital masculinization.
- Male germ cells become gonocytes during fetal development; pre-spermatogonia continue development before puberty, while complete spermatogenesis begins at puberty.[39]
Ovarian development
- Granulosa cells (Sertoli-cell homologs) and theca cells (Leydig-cell homologs) differentiate more slowly.
- Germ cells enter meiosis during fetal life and arrest at prophase I as primary oocytes; no new oocytes are generated after birth.
Genital Duct Development — Wolffian and Müllerian
At the indifferent stage both male and female embryos possess:
- Wolffian (mesonephric) ducts. Bilateral
- Müllerian (paramesonephric) ducts. Bilateral, lateral to Wolffian
Male — testosterone drives Wolffian retention; AMH drives Müllerian regression
| Wolffian duct derivative | Adult structure |
|---|---|
| Cranial mesonephric tubules | Efferent ductules of testis |
| Wolffian duct — proximal | Epididymis |
| Wolffian duct — middle | Vas deferens |
| Wolffian duct — caudal | Seminal vesicle (diverticulum) + ejaculatory duct |
| Müllerian duct (regressed) | Appendix testis (cranial tip); prostatic utricle (caudal tip, opens at verumontanum)[8] |
Female — absence of testosterone regresses Wolffian; absence of AMH retains Müllerian
| Müllerian duct derivative | Adult structure |
|---|---|
| Unfused cranial portions | Fallopian tubes |
| Fused caudal portions | Uterus (fundus, body, cervix) and the uterovaginal canal contributing to upper vaginal morphogenesis[25]; urogenital-sinus cells replace the fetal vaginal epithelium by 16–19 weeks.[37] |
| Wolffian remnants | Gartner's duct cysts (paravaginal); epoophoron, paroophoron (ovarian ligament) |
Clinical consequences of duct-development failure
- Persistent Müllerian duct syndrome (PMDS). AMH or AMHR2 mutations; 46,XY with normal testes but retained uterus and fallopian tubes encountered at inguinal orchiopexy or herniorrhaphy.
- Müllerian agenesis (MRKH). Absent or underdeveloped uterus and upper vagina with typical external genitalia and ovaries. When vaginal elongation is desired, supported dilation is first-line for most patients; neovaginoplasty is an option when needed and should reflect the patient's readiness and preference. Uterine transplantation is a separate fertility intervention, not a neovaginoplasty technique. See ACOG Committee Opinion 728.
- Müllerian-fusion anomalies (see ASRM / ESHRE–ESGE classification):
- Uterine septum. Failed resorption of the midline septum after fusion
- Bicornuate. Partial failure of fusion
- Didelphys. Complete failure of fusion produces two uteri, two cervices, often a longitudinal vaginal septum
- Unicornuate. Unilateral Müllerian agenesis produces a single horn with or without a rudimentary horn (an obstructed horn causes cryptomenorrhea)
- Congenital absence of the vas deferens (CAVD). This Wolffian-duct anomaly may be unilateral or bilateral. Bilateral absence (CBAVD) is strongly associated with CFTR variants and obstructive infertility; unilateral absence is more often associated with renal anomalies than bilateral absence, including ipsilateral renal agenesis. CFTR variants also occur with unilateral absence.[22][23]
- Zinner syndrome. Ipsilateral renal agenesis, ipsilateral seminal-vesicle cyst and ipsilateral ejaculatory-duct obstruction; a developmental constellation reflecting a failed Wolffian-duct segment.
External Genitalia Development
Until week 9 the external genitalia are sexually indifferent, arising from four primordia identical across sexes:[9]
| Indifferent structure | Male (DHT-driven) | Female (default) |
|---|---|---|
| Genital tubercle | Phallus / penis; glans | Clitoris; glans clitoris |
| Urethral (urogenital) folds | Fuse ventrally to form the penile urethra | Remain unfused as labia minora |
| Labioscrotal swellings | Fuse to form the scrotum | Remain unfused as labia majora |
| Urogenital sinus (phallic) | Penile urethra | Vestibule |
Male external genitalia — the "zippers"
Two sequential morphogenetic events drive masculinization:
- Opening zipper. Canalization of the solid urethral plate forming the urethral groove on the ventral shaft.
- Closing zipper. Midline fusion of the urethral folds forms the penile-shaft urethra; the glanular urethra forms by direct canalization of the solid urethral plate.[9]
The urethra reaches the glans by week 14.[9] Failure of the closing zipper at any point produces hypospadias:
- Glanular / coronal / subcoronal: distal
- Midshaft
- Penoscrotal, scrotal or perineal. Proximal, often associated with chordee and bifid scrotum
- Associated anomalies more common in proximal forms: cryptorchidism, DSD, disorders of androgen biosynthesis / action[10]
Epispadias is a dorsal urethral defect that may occur alone or with bladder exstrophy; its precise embryologic mechanism remains unresolved.[5][11]
Female external genitalia
In the absence of androgens, the external genitalia develop by default along the female program. Congenital adrenal hyperplasia (21-hydroxylase deficiency) produces excess androgens in a 46,XX fetus and virilizes the external genitalia. It is the commonest 46,XX DSD and the classic newborn "ambiguous genitalia" presentation.
Testosterone vs dihydrotestosterone
- Testosterone drives Wolffian-duct development (internal male ducts).
- DHT (converted from testosterone by 5α-reductase type 2 in genital skin) drives external masculinization (penile urethra, scrotum) and prostate development.
- 5α-reductase deficiency (46,XY, normal testes, normal Wolffian structures, undervirilized external genitalia) produces the striking phenotype of apparent female genitalia at birth with virilization at puberty (as rising testosterone overrides the enzyme deficit).
Prostate Development
Prostatic buds arise from the urogenital sinus epithelium near the verumontanum at approximately week 10 under the influence of androgens.[12] The main features are:
- Endodermal origin (FOXA1-positive); contrasts with the mesonephric-duct origin of the central zone.
- Bud emergence, elongation and branching, canalization, then cytodifferentiation. The adult zonal anatomy (McNeal) reflects two lineages:
- Peripheral and transition zones. Urogenital-sinus origin; the site of most cancers (PZ) and all BPH (TZ).
- Central zone. A Wolffian-duct origin has been proposed from histologic similarity to seminal vesicles and a three-case pathology series.[40] The central zone is relatively cancer-resistant.
- Signaling: androgens (required), FGF10 (can bypass testosterone in vitro), retinoic acid, WNT, epithelial–mesenchymal cross-talk (stromal AR signaling is essential).[12]
See The Prostate & Seminal Vesicles for zonal-origin implications in adult disease.
Testicular Descent
A two-phase process under separate hormonal controls:[13]
| Phase | Timing | Mechanism |
|---|---|---|
| Transabdominal | Weeks 8–15 | Gubernaculum thickens and anchors the testis near the internal ring. Driven by INSL3 from Leydig cells acting on the LGR8/RXFP2 receptor on the gubernaculum. Cranial suspensory ligament regresses under testosterone influence |
| Inguinoscrotal | Weeks 25–35 | Gubernaculum migrates across the pubic region; androgens and the genitofemoral nerve (via CGRP release) drive gubernacular migration. The processus vaginalis elongates, creating the path; the testis follows |
Cryptorchidism
- 1–3% at term; up to 30% in preterm infants; approximately 1% at 1 year of age.[13][14]
- INSL3 / RXFP2 (LGR8) variants are uncommon causes. In one cohort of 600 newborns with cryptorchidism, variants were found in 7 of 600 (1.2%) at birth and in 7 of 303 (2.3%) of boys with persistent cryptorchidism.[26] See Ferlin et al..
- If spontaneous descent has not occurred by 6 months corrected age, the AUA guideline recommends referral and orchiopexy within the following year (by 18 months corrected age; Standard, Grade B); long-term risks of cryptorchidism include:[14]
- Infertility risk (heat-related germ-cell injury rises rapidly after age 1)
- Testicular cancer risk (in a Swedish cohort after orchiopexy, RR 2.23 for surgery before age 13 and 5.40 at age 13 or later, each compared with the general population; earlier surgery was associated with lower risk, but risk remained elevated and orchiopexy enables surveillance)[24]
Patent processus vaginalis
Failure of the processus vaginalis to close produces the spectrum of inguinal hernia ↔ hydrocele ↔ communicating hydrocele depending on the caliber and length of the residual patency.
Adrenal Development
The adrenogonadal primordium, a shared precursor of the adrenal cortex and gonads, forms at week 4. The adrenal cortex derives from intermediate mesoderm and coelomic epithelium; the adrenal medulla is colonized by neural-crest cells (chromaffin cells that produce catecholamines).[15]
Fetal cortex dominates prenatally, producing DHEA and DHEA-S (precursors for placental estrogen synthesis); regresses postnatally. The definitive (adult) cortex matures after birth into the three classical zones (glomerulosa, fasciculata, reticularis).[15]
Relevant anomalies: congenital adrenal hyperplasia (most commonly 21-hydroxylase deficiency), the leading cause of 46,XX DSD with virilization of the external genitalia.
CAKUT — Congenital Anomalies of the Kidney and Urinary Tract
A diverse spectrum with a common embryologic theme: failed reciprocal induction between the ureteric bud and the metanephric mesenchyme, and/or failed incorporation of the Wolffian duct and ureter into the bladder. Prevalence is estimated at 4–60 per 10,000 births depending on the registry. CAKUT comprises developmental kidney and urinary tract anomalies[16] and accounts for almost 50% of chronic kidney disease manifesting within the first three decades of life.[18]
| Anomaly | Embryologic basis | Adult-practice relevance |
|---|---|---|
| Renal agenesis (unilateral > bilateral) | Failed ureteric-bud outgrowth or metanephric-mesenchyme response | Associated with Müllerian anomalies (MRKH) and CBAVD |
| Renal hypodysplasia | Partial induction failure | Risk factor for adult CKD and hypertension |
| Multicystic dysplastic kidney | Grossly disordered development; atretic renal pelvis | Usually non-functional; involution common |
| Horseshoe kidney | Lower-pole fusion before ascent; isthmus caught on IMA | Higher UPJ obstruction, stones, Wilms risk |
| Duplex kidney ± ureterocele / ectopic ureter | Two ureteric buds / abnormal Wolffian absorption | Weigert-Meyer rule; often presents with UTI / incontinence |
| Ureteropelvic junction obstruction | Intrinsic stenosis or crossing vessel | Pyeloplasty territory |
| Megaureter | Distal ureter muscle / valve / obstruction abnormality | Classified obstructive / refluxing / both / neither |
| Vesicoureteral reflux (VUR) | Short submucosal tunnel from abnormal Wolffian-duct incorporation | Grades I–V; manage asymptomatic grades I–III with normal kidneys conservatively; offer reimplantation for persistent grades IV–V or reimplantation/endoscopic correction for frequent breakthrough infections[34] |
| Posterior urethral valves (PUV) | Abnormal remnant of congenital urethral membrane | Most common cause of bladder-outlet obstruction in male infants; lifelong renal and bladder monitoring after ablation because dysfunction is common[42] |
| Prune-belly (Eagle-Barrett) syndrome | Abnormal urinary-tract development + absent abdominal-wall musculature + cryptorchidism | Triad — lifelong reconstructive burden |
| Exstrophy-epispadias complex | Failure of cloacal-membrane reinforcement / ventral body-wall closure | Bladder exstrophy, cloacal exstrophy, epispadias; staged reconstruction |
Monogenic causes account for approximately 12–20% of CAKUT, with approximately 54 disease genes implicated: PAX2, HNF1B, EYA1, SIX1, SALL1, RET, GDNF, BMP4, ROBO2, and others.[17][18]
Syndromic forms include renal coloboma syndrome (PAX2), branchio-oto-renal (EYA1/SIX1), Townes-Brocks (SALL1), 17q12 deletion (HNF1B), and VACTERL association.[17][18]
Disorders of Sex Development (DSD)
DSDs arise from abnormalities in chromosomal, gonadal, or phenotypic sex. Simplified classification (46,XY, 46,XX, sex-chromosome):[19][20]
46,XY DSD — undervirilized
- Gonadal dysgenesis. SRY, SOX9, SF1 (NR5A1), WT1, DHH mutations
- Defects in androgen biosynthesis. 17β-HSD3, 17,20-lyase, StAR mutations
- 5α-reductase type 2 deficiency. Underdeveloped external genitalia at birth; striking virilization at puberty
- Complete / partial androgen insensitivity syndrome (CAIS / PAIS). AR mutations; normal testes, normal AMH-driven Müllerian regression, undervirilized external genitalia
- Persistent Müllerian duct syndrome. AMH or AMHR2 mutations; retained uterus and tubes in an otherwise phenotypically male 46,XY
46,XX DSD — virilized
- Congenital adrenal hyperplasia. Most commonly 21-hydroxylase deficiency; virilization of external genitalia; salt-wasting or simple-virilizing subtypes
- Aromatase deficiency. Failure to convert androgens to estrogens; virilizes fetus and sometimes mother during pregnancy
- Maternal androgen exposure
Sex-chromosome DSD
- Turner syndrome (45,X). Gonadal dysgenesis with streak gonads; short stature; associated renal and cardiac anomalies
- Klinefelter syndrome (47,XXY). Hypergonadotropic hypogonadism; small firm testes; common cause of non-obstructive azoospermia
- Mixed gonadal dysgenesis (45,X/46,XY). Asymmetric gonadal phenotype; risk of gonadoblastoma in the dysgenetic gonad with Y material
Principles of DSD management
Multidisciplinary team (endocrinology, urology, psychology, genetics, neonatology). In a neonate with atypical genitalia, urgently exclude salt-wasting CAH with electrolytes and 17-OHP; the EAU guideline strongly recommends prompt diagnosis and treatment.[33] Further evaluation includes karyotype, testosterone, DHT, AMH, LH/FSH, cortisol, ACTH, pelvic ultrasound, and sometimes genitography. Decision-making about gender assignment and reconstructive surgery is individualized, evidence-guided, and increasingly deferred until the patient can participate where possible.[20]
Clinical Correlations for the Reconstructive Urologist
- Horseshoe kidney and UPJ obstruction. UPJ obstruction is more common in horseshoe kidneys; the ureteral course across the isthmus and variant arteries may impair drainage. Pyeloplasty planning requires imaging of the individual collecting system and arterial supply.[27]
- Duplex systems. Follow the Weigert-Meyer rule. Upper-pole ureteroceles cause obstruction and present with UTI / hydronephrosis; ectopic ureters in females present with continuous incontinence despite normal voiding.
- PUV. Even after valve ablation, bladder dysfunction (thick-walled, poorly compliant, detrusor overactivity or underactivity) is the lifetime reconstructive problem. Hostile bladder in adolescence or young adulthood may require augmentation cystoplasty ± continent diversion.
- Bladder exstrophy–epispadias complex. Modern care is staged functional repair (MSRE) with bladder closure, epispadias repair, and bladder-neck reconstruction, or complete primary repair. Long-term renal and continence outcomes depend on repeat reconstructions.
- Hypospadias repair. Timing: 6–18 months. Technique: TIP (Snodgrass) for distal, two-stage preputial / buccal-graft for severe / proximal hypospadias. Adult revision-hypospadias is a major reconstructive burden after failed childhood repair.
- Cryptorchidism. Orchiopexy is preferred by 12 months and no later than 18 months when descent has not occurred by 6 months corrected age. For high intra-abdominal testes, a staged Fowler-Stephens approach is one option after assessment of testicular position, vessel length and collateral supply. See the current EAU paediatric guideline.
- MRKH / Müllerian agenesis. Patient-directed vaginal dilation is first-line for most patients who desire elongation; specialist neovaginoplasty options include Vecchietti (traction-dilation), McIndoe (split-thickness graft over stent), Davydov (peritoneal), or bowel-segment techniques when appropriate. Uterine transplantation is a distinct, highly specialized fertility option. See ACOG Committee Opinion 728.
- Müllerian anomalies of the uterus. For a septate uterus with recurrent miscarriage, the 2024 ASRM guideline recommends offering hysteroscopic incision through shared decision-making ; for infertility alone, whether resection increases live births is uncertain.[32] Unicornuate uterus with obstructed rudimentary horn: excision. Didelphys with obstructed hemivagina: hemivaginal septum excision.
- Urachal anomalies. A patent urachus in infancy requires assessment; persistent or symptomatic remnants may require excision.[30] Simple asymptomatic adult urachal cysts can be monitored with ultrasound after malignancy is excluded.[31] Adenocarcinoma is managed separately as above.
- Persistent Müllerian duct syndrome (PMDS). Encountered intraoperatively during orchiopexy or inguinal hernia repair as a retained uterus and tubes in a 46,XY child. Management is staged orchidopexy with preservation of the vas deferens and epididymis adjacent to the Müllerian structures.
- Zinner syndrome. Ipsilateral renal agenesis, ipsilateral seminal-vesicle cyst and ejaculatory-duct obstruction. It may present with recurrent epididymitis, perineal pain or hematospermia. Asymptomatic or mildly symptomatic cases may be observed.[43] Persistent symptoms may be treated with transurethral resection of the ejaculatory duct or cyst marsupialization.
- CBAVD and CFTR. Most males with cystic fibrosis have CBAVD, and many men with CBAVD carry a CFTR variant. Sperm retrieval with IVF-ICSI may be considered after genetic evaluation and counseling of both partners. See CFTR/CBAVD review and genetic cohort.
- Cloacal malformations. Managed with posterior sagittal anorectoplasty (PSARP) or anterior sagittal approaches in infancy; adolescent and adult reconstructive urologic sequelae include neobladder / continent diversion, augmentation, neovagina, and complex fistula repair.
- DSD surgical planning. Avoid irreversible early surgery where feasible. In 45,X/46,XY mosaicism, gonadal-tumor risk and a decision about gonadectomy depend on phenotype, gonadal location/histology, Y-chromosome material, age, fertility/hormonal considerations and patient preferences; Y material alone is not an automatic surgical rule. See the risk-stratification review and 45,X/46,XY cohort.
- CAKUT surveillance. Identifying a single CAKUT phenotype (e.g., unilateral renal agenesis) should prompt a broader survey: contralateral vesicoureteral reflux, obstructive megaureter, Müllerian anomaly, and CBAVD or CFTR evaluation when indicated.
- Fetal-diagnosed urinary tract dilation and postnatal workup. Timing of postnatal ultrasound depends on severity and suspected obstruction; when clinically appropriate, imaging after the first 48 hours reduces underestimation from early neonatal physiology. Functional imaging is selective. AUA VUR guidance recommends VCUG for high-grade hydronephrosis, hydroureter, abnormal bladder or later UTI, while allowing observation for low-grade isolated dilation. See AUA VUR screening guidance.
References
1. Dressler GR. "The Cellular Basis of Kidney Development." Annu Rev Cell Dev Biol. 2006;22:509–529. doi:10.1146/annurev.cellbio.22.010305.104340
2. Sanchez-Ferras O, Pacis A, Sotiropoulou M, et al. "A Coordinated Progression of Progenitor Cell States Initiates Urinary Tract Development." Nat Commun. 2021;12(1):2627. doi:10.1038/s41467-021-22931-5
3. Blake J, Rosenblum ND. "Renal Branching Morphogenesis: Morphogenetic and Signaling Mechanisms." Semin Cell Dev Biol. 2014;36:2–12. doi:10.1016/j.semcdb.2014.07.011
4. Eid S, Iwanaga J, Loukas M, Oskouian RJ, Tubbs RS. "Pelvic Kidney: A Review of the Literature." Cureus. 2018;10(6):e2775. doi:10.7759/cureus.2775
5. Liaw A, Cunha GR, Shen J, et al. "Development of the Human Bladder and Ureterovesical Junction." Differentiation. 2018;103:66–73. doi:10.1016/j.diff.2018.08.004
6. Wilhelm D, Palmer S, Koopman P. "Sex Determination and Gonadal Development in Mammals." Physiol Rev. 2007;87(1):1–28. doi:10.1152/physrev.00009.2006
7. Eggers S, Ohnesorg T, Sinclair A. "Genetic Regulation of Mammalian Gonad Development." Nat Rev Endocrinol. 2014;10(11):673–683. doi:10.1038/nrendo.2014.163
8. MacLaughlin DT, Donahoe PK. "Sex Determination and Differentiation." N Engl J Med. 2004;350(4):367–378. doi:10.1056/NEJMra022784
9. Baskin L, Shen J, Sinclair A, et al. "Development of the Human Penis and Clitoris." Differentiation. 2018;103:74–85. doi:10.1016/j.diff.2018.08.001
10. Joodi M, Amerizadeh F, Hassanian SM, et al. "The Genetic Factors Contributing to Hypospadias and Their Clinical Utility in Its Diagnosis." J Cell Physiol. 2019;234(5):5519–5523. doi:10.1002/jcp.27350
11. Suzuki K, Matsumaru D, Matsushita S, et al. "Epispadias and the Associated Embryopathies: Genetic and Developmental Basis." Clin Genet. 2017;91(2):247–253. doi:10.1111/cge.12871
12. Cunha GR, Vezina CM, Isaacson D, et al. "Development of the Human Prostate." Differentiation. 2018;103:24–45. doi:10.1016/j.diff.2018.08.005
13. Hutson JM, Southwell BR, Li R, et al. "The Regulation of Testicular Descent and the Effects of Cryptorchidism." Endocr Rev. 2013;34(5):725–752. doi:10.1210/er.2012-1089
14. Kolon TF, Herndon CD, Baker LA, et al. "Evaluation and Treatment of Cryptorchidism: AUA Guideline." J Urol. 2014;192(2):337–345. doi:10.1016/j.juro.2014.05.005
15. Abou Nader N, Boyer A. "Adrenal Cortex Development and Maintenance." Endocrinology. 2021;162(12):bqab187. doi:10.1210/endocr/bqab187
16. Murugapoopathy V, Gupta IR. "A Primer on Congenital Anomalies of the Kidneys and Urinary Tracts (CAKUT)." Clin J Am Soc Nephrol. 2020;15(5):723–731. doi:10.2215/CJN.12581019
17. van der Ven AT, Vivante A, Hildebrandt F. "Novel Insights Into the Pathogenesis of Monogenic Congenital Anomalies of the Kidney and Urinary Tract." J Am Soc Nephrol. 2018;29(1):36–50. doi:10.1681/ASN.2017050561
18. Kolvenbach CM, Shril S, Hildebrandt F. "The Genetics and Pathogenesis of CAKUT." Nat Rev Nephrol. 2023;19(11):709–720. doi:10.1038/s41581-023-00742-9
19. Federman DD. "Three Facets of Sexual Differentiation." N Engl J Med. 2004;350(4):323–324. doi:10.1056/NEJMp038175
20. León NY, Reyes AP, Harley VR. "A Clinical Algorithm to Diagnose Differences of Sex Development." Lancet Diabetes Endocrinol. 2019;7(7):560–574. doi:10.1016/S2213-8587(18)30339-5
21. Thomas DFM. "The embryology of persistent cloaca and urogenital sinus malformations." Asian J Androl. 2020;22(2):124–128. doi:10.4103/aja.aja_72_19
22. Cai H, Qing X, Niringiyumukiza JD, et al. "CFTR variants and renal abnormalities in males with congenital unilateral absence of the vas deferens (CUAVD): a systematic review and meta-analysis of observational studies." Genet Med. 2019;21(4):826–836. doi:10.1038/s41436-018-0262-7
23. Mo B, Garla V, Wyner LM. "A case of congenital unilateral absence of the vas deferens." Int Med Case Rep J. 2013;6:21–23. doi:10.2147/IMCRJ.S40611
24. Pettersson A, Richiardi L, Nordenskjold A, et al. "Age at Surgery for Undescended Testis and Risk of Testicular Cancer." N Engl J Med. 2007;356(18):1835–1841. doi:10.1056/NEJMoa067588
25. Dixit R, Duggireddy CS, Pradhan GS. "Mullerian anomalies: revisiting imaging and classification." Insights Imaging. 2025;16(1):40. doi:10.1186/s13244-024-01879-2
26. Ferlin A, Zuccarello D, Garolla A, et al. "Mutations in INSL3 and RXFP2 genes in cryptorchid boys." Ann N Y Acad Sci. 2009;1160:213–214. doi:10.1111/j.1749-6632.2008.03784.x
27. Humphries A, Speroni S, Eden K, et al. "Horseshoe kidney: Morphologic features, embryologic and genetic etiologies, and surgical implications." Clin Anat. 2023;36(8):1081–1088. doi:10.1002/ca.24018
28. European Association of Urology. "Ureterocele and Ectopic Ureter." EAU Guidelines on Paediatric Urology. 2026. Online guideline (accessed October 7, 2026).
29. European Association of Urology. "Ureterocele and Ectopic Ureter." EAU Guidelines on Paediatric Urology. 2026. Online guideline (accessed October 7, 2026).
30. Ghattas YS, Gelikman DG, Ibanez KR, Ellsworth P, Seth A. "Current management strategies of urachal anomalies in pediatric patients: A scoping review." Front Urol. 2023;3:1159439. doi:10.3389/fruro.2023.1159439
31. Hassanbhai DH, Ng FC, Koh LT. "Is excision necessary in the management of adult urachal remnants?: a 12-year experience at a single institution." Scand J Urol. 2018;52(5-6):432–436. doi:10.1080/21681805.2018.1534884
32. Practice Committee of the American Society for Reproductive Medicine. "Evidence-based diagnosis and treatment for uterine septum: a guideline." Fertil Steril. 2024;122(2):251–265. doi:10.1016/j.fertnstert.2024.02.033
33. European Association of Urology. "Disorders/Differences of Sex Development." EAU Guidelines on Paediatric Urology. 2026. Online guideline (accessed October 7, 2026).
34. European Association of Urology. "Vesicoureteric Reflux." EAU Guidelines on Paediatric Urology. 2026. Online guideline (accessed October 7, 2026).
35. Jain S, Chen F. "Developmental pathology of congenital kidney and urinary tract anomalies." Clin Kidney J. 2019;12(3):382–399. doi:10.1093/ckj/sfy112
36. Khatib N, Bronshtein M, Bachar G, et al. "Fetal Renal Duplicated Collecting System at 14–16 Weeks of Gestation." J Clin Med. 2023;12(22):7124. doi:10.3390/jcm12227124
37. Hülsman CJM, Köhler SE, Morosan-Puopolo G, Hikspoors JPJM, Lamers WH. "The Development of the Human Female Reproductive Tract: Part 2—Vagina." Clin Anat. 2026;39(1):112–131. doi:10.1002/ca.70015
38. Jiménez R, Burgos M, Barrionuevo FJ. "Sex Maintenance in Mammals." Genes (Basel). 2021;12(7):999. doi:10.3390/genes12070999
39. Sanou I, Lakshmipathi M, Schönhage LK, et al. "Temporal dynamics of Sertoli and germ cell development in human foetal and prepubertal testis." Biol Open. 2026;15(2):bio062319. doi:10.1242/bio.062319
40. Argani P, Walsh PC, Epstein JI. "Analysis of the prostatic central zone in patients with unilateral absence of Wolffian duct structures: further evidence of the mesodermal origin of the prostatic central zone." J Urol. 1998;160(6 Pt 1):2126–2129. doi:10.1097/00005392-199812010-00047
41. Suartz CV, Martinez LM, Silvestre MHL, et al. "Urachal Carcinomas: A Comprehensive Systematic Review and Meta-analysis." Int Braz J Urol. 2025;51(3):e20240665. doi:10.1590/S1677-5538.IBJU.2024.0665
42. European Association of Urology. "Congenital Lower Urinary Tract Obstruction." EAU Guidelines on Paediatric Urology. 2026. Online guideline (accessed October 7, 2026).
43. Liu T, Li X, Huang L, et al. "Zinner syndrome: an updated pooled analysis based on 214 cases from 1999 to 2020: systematic review." Ann Palliat Med. 2021;10(2):2271–2282. doi:10.21037/apm-20-1997