Female Urethra
The female urethra is a short (approximately 3–4 cm) muscular tube running from the bladder neck to the external meatus, embedded within the anterior vaginal wall and supported by a hammock of endopelvic fascia, paravaginal attachments, and pelvic-floor muscles.[1][9] It is the functional center of the anterior compartment. Its continence depends on intrinsic sphincteric bulk, hormonally-responsive mucosal coaptation, vascular engorgement ("seal effect"), and a supporting hammock that transmits abdominal pressure to it.
Segmental Anatomy
DeLancey's paraurethral anatomy study described approximate regions by percent of total length.[4]
| Zone | % of urethral length | What is there |
|---|---|---|
| Intramural | 0–15% | Urethra traverses the bladder wall[4] |
| Midurethra | 20–60% | Striated urethral sphincter (rhabdosphincter); vaginolevator attachments[4] — the target of midurethral slings |
| Perineal membrane region | 54–76% | Compressor urethrae and urethrovaginal sphincter (external striated muscle continuations)[4]; perineal membrane |
| Distal urethra | 79–100% | Passes between vestibular bulbs and bulbocavernosus muscles[4] |
Midurethral slings (TVT, TOT, single-incision slings) are positioned beneath the midurethra, where sphincteric and supportive structures overlap. Incorrect placement or excessive tension can affect continence and voiding; the mechanism is more complex than recruiting one discrete sphincter zone.[4]
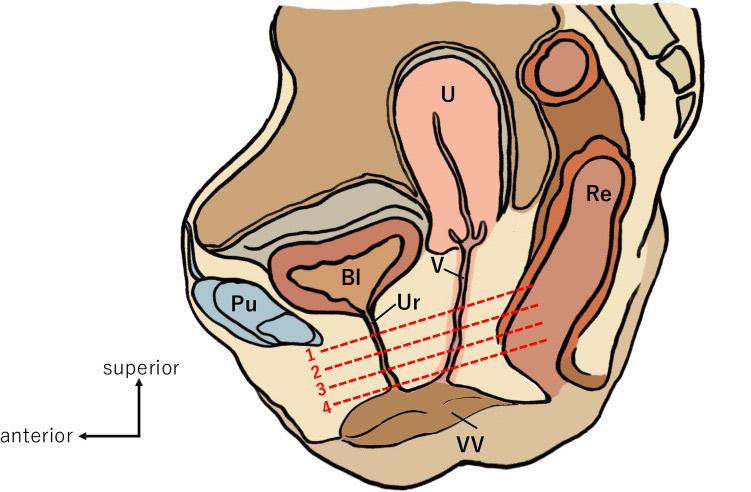
Midsagittal illustration of the female pelvis (right half): the urethra (Ur) runs from the bladder (Bl) behind the pubic bone (Pu), anterior to the vagina (V), to open in the vaginal vestibule (VV); uterus (U) and rectum (Re) lie posteriorly. Dashed lines 1-4 mark the proximal-to-distal levels of the representative serial sections used in the study. From Liu T, et al. Int Urogynecol J. 2025;36(3):647-654, Fig. 1 (CC BY 4.0).[3]
Urethral Wall and Histology
MRI–histology correlation in 13 cadavers identified four concentric urethral signal rings corresponding to mucosa, submucosa, smooth muscle, and striated sphincter.[7] Histologic studies describe more detailed muscle organization, including smooth muscle external to the striated sphincter in a five-cadaver series.[3][8]
| Layer (inside → outside) | Composition | Operative relevance |
|---|---|---|
| Mucosa | Stratified squamous distally; pseudostratified columnar and, occasionally, transitional proximally. A 16-woman histologic study found a shift from squamous to columnar epithelium with advancing age[2] | Mucosal coaptation contributes to closure; EAU strongly recommends offering vaginal estrogen to postmenopausal women with SUI and vulvovaginal atrophy symptoms[26] |
| Submucosa | Loose connective tissue with an extensive vascular plexus; urethral interstitial cells | Vascular engorgement contributes to the urethral "seal"; a five-woman study estimated roughly one-third of closure pressure[5][23][24] |
| Smooth muscle | Inner longitudinal + outer circular; outermost layer extends anteriorly to pelvic attachments[3][8] | The lissosphincter — tonic closure at rest |
| Striated muscle (rhabdosphincter) | Small type I fibers, embedded in the elastic perineal membrane; U-shaped anteriorly, deficient posteriorly where the urethra is continuous with the vagina[6][8] | Active phasic closure on cough/Valsalva; childbirth-related muscle or nerve injury may impair closure.[24] Female AUS cuffs are generally placed around the bladder neck or proximal urethra.[28] |
The rhabdosphincter, compressor urethrae, and urethrovaginal sphincter together constitute the striated urogenital sphincter complex, which extends from midurethra to the perineal membrane.[8][6] Posteriorly, urethral and anterior vaginal tissues are closely continuous; a four-cadaver histologic study found no discrete fascial layer between them.[1] The EAU describes raising a vaginal flap and preserving periurethral fascia for layered closure.[26]
Urethral Support — the Hammock
The anterior vaginal wall, endopelvic fascia, and levator ani form a supportive hammock that helps maintain urethral position and stress continence; intrinsic sphincteric and mucosal closure mechanisms also contribute.[1][9][19][20][21][22][24]
Key support structures
- Pubourethral ligaments (three components: proximal, midurethral, distal) run from the pubic bone to the urethra ventrally.[18] Their existence as discrete histologic ligaments has been debated;[1] clinically they are best understood as thickenings of the endopelvic fascia where it inserts on the urethra.
- Arcus tendineus fasciae pelvis (ATFP). The "white line" running from the posterior aspect of the pubic symphysis to the ischial spine. The anterior vaginal wall inserts on the ATFP laterally; detachment of this insertion produces the paravaginal defect.[1][20]
- Levator ani (pubococcygeus and puborectalis). The active backstop against which the urethra is compressed on a rise in intra-abdominal pressure. In one MRI-derived computational model, simulated weakening of the vaginal walls, puborectalis and pubococcygeus produced the largest individual increases in urethral excursion.[19]
- Perineal membrane. The elastic fiber-rich lamina wrapping the midurethra anteriorly and extending to the perineal body posteriorly.[6]
The hammock mechanism
Because the urethra is not anchored to a rigid structure, it is the posterior hammock (vaginal wall attached to ATFP and levator) that must supply the "firm backstop" against which a rising abdominal pressure compresses the urethra. This is the mechanical essence of normal stress continence and of the Integral / hammock theories of SUI:[9][22]
- Loss of lateral vaginal support can contribute to urethral hypermobility and stress leakage.[24]
- Levator injury or age-related change may weaken active support, but the effects of birth, sphincter pressure and neural injury vary between individuals.[24]
- A midurethral sling adds suburethral support.[4]
Vascular Supply and the "Seal Effect"
Arterial supply comes from internal pudendal and vaginal branches, with additional superior vesical branches to the proximal urethra and bladder neck; venous drainage parallels the arteries into vesical and pudendal plexuses.[5] A fetal-to-infant histologic series found longitudinal submucosal veins rather than a plexiform arrangement.[16] Adult Doppler studies describe regional vascularity.[14][15] In a randomized comparison of three topical estrogens among 41 postmenopausal women with SUI, periurethral vessel counts increased after three months of conjugated estrogen or estriol.[34]
Quantitative Doppler studies show regional variation:
- Highest perfusion intensity in the distal urethra (rich venous vascularization).
- Greatest resistance index in the anterior proximal urethra.
- Midurethral vascularity differs between external and internal sub-layers.[14][15]
The submucosal plexus contributes to mucosal coaptation and closure.[23][24] The familiar approximately one-third contribution to maximal urethral closure pressure (MUCP) is an estimate from a small mechanistic study of five women.[23][24]
Lymphatic drainage follows the vessels:
- Proximal two-thirds. Drain to pelvic nodes (obturator, internal and external iliac).
- Distal third. Drains to superficial inguinal nodes.[17]
Innervation
The urethra has dual somatic and autonomic innervation, with the somatic supply arriving through two distinct routes.[10][11][12][13]
Somatic
- Pudendal nerve (S2–S4). From Onuf's nucleus, supplies the rhabdosphincter, compressor urethrae, and urethrovaginal sphincter.
- Intrapelvic somatic branch. A separate pathway from S2–S4 sacral roots, running beneath the endopelvic fascia in close relation to the inferior vascular pedicle of the bladder and the lateral and anterior vaginal wall.[11] This branch is at risk during radical pelvic surgery (hysterectomy, colpectomy, radical anterior exenteration) and during vaginal dissections carried lateral to the urethra.
Autonomic
- Sympathetic (T10–L2, hypogastric). α₁-adrenergic activity contributes to female urethral smooth-muscle tone, while β-adrenergic activity relaxes the bladder dome.[29] Histochemistry found sparse noradrenergic nerves but numerous cholinergic nerves at the female bladder neck and proximal urethra.[30]
- Parasympathetic (S2–S4, pelvic). Nitrergic and cholinergic; opens the urethra at the start of voiding.
- Dual nitrergic and non-nitrergic innervation. nNOS-positive branches from the vaginal nervous plexus and nNOS-negative fibers from the pudendal nerve enter the sphincter complex at different points.[10]
Sensory
Dense sensory innervation of the urothelium and lamina propria.[5] The precise contribution of urethral afferents to continence remains incompletely understood but likely supports the guarding and voiding reflexes.
Continence Physiology
Resting maximal urethral closure pressure (MUCP) varies widely even among continent women of similar age; a single 60–100 cmH₂O interval should not be used as a universal normal or diagnostic cutoff.[23][24] A small mechanistic study in five women suggested roughly equal contributions from three tissue components:[23][24]
| Component | Contribution to MUCP | Failure mode |
|---|---|---|
| Striated + smooth muscle | Approximate study contribution | Age-related muscle or nerve changes |
| Submucosal vascular plexus ("seal") | Approximate study contribution | Vascular and hormonal changes may alter coaptation |
| Connective tissue / mucosal coaptation | Approximate study contribution | Tissue changes remain incompletely characterized |
Dynamic behavior adds two further mechanisms:
- Reflex closure. The distal urethra participates in active closure, and midurethral support can influence the response.[25]
- Passive pressure transmission. One proposed model holds that passive pressure transmission can occur only in the proximal abdominal third of the urethra and that active reflex closure contributes to distal urethral continence.[25]
Life-course and hormonal effects
- In a cross-sectional cohort of 82 nulliparous women aged 21–70 years, each decade of age was associated with 15 cmH₂O lower MUCP.[33] A 2021 review reported approximately 40% lower MUCP in women with SUI than in controls.[24]
- In one comparison, women with de novo SUI persisting 9–12 months postpartum had approximately 25% lower MUCP than age- and parity-matched controls. Longitudinal studies in the same review found no consistent postbirth change.[24]
- Menopausal tissue changes can affect coaptation.[26] Current EAU guidance recommends vaginal estrogen for postmenopausal women with SUI and vulvovaginal atrophy symptoms , based on short-term symptom evidence.[26]
- Bladder-neck opening does not by itself mean incontinence. A transvaginal-ultrasound study in nulliparous women found an open bladder neck at rest in 21% overall, entirely among women who were otherwise asymptomatic; the few women in that cohort with occasional stress incontinence all had closed bladder necks.[27] Distal urethral sphincter mechanisms have been proposed to compensate for bladder-neck incompetence in some continent women, though this compensation is incompletely characterized, and the finding still identifies patients worth watching if the distal sphincter mechanism is later compromised.
Clinical Correlations for the Reconstructive Surgeon
- Stress urinary incontinence — support and sphincter. Urethral support and closure pressure both contribute and can fail together.[26] Treatment choice depends on symptoms, prior surgery, anatomy, risk and patient preference.[26]
- Midurethral sling placement. Position the sling under the midurethra without undue tension.[4] Retropubic (TVT) slings pass through the retropubic space and risk bladder and vascular injury; transobturator slings (TOT) traverse the obturator foramen and risk groin pain and obturator nerve injury; single-incision slings avoid retropubic or transobturator passage. Selected devices had noninferior patient-reported success through 36 months, but later efficacy remains uncertain; mesh exposure and dyspareunia warrant counseling.[26] EAU strongly recommends counseling that long-term outcomes are better with retropubic than transobturator slings and performing intraoperative cystoscopy to check for bladder perforation when placing a synthetic midurethral sling.[26]
- Burch colposuspension. Anchors paravaginal fascia to Cooper's (pectineal) ligament, supporting the proximal urethra and bladder neck.[26] Open or laparoscopic colposuspension remains an option for women seeking SUI surgery after discussion of alternatives and tradeoffs.[26]
- Urethral diverticulum. Often attributed to periurethral gland obstruction or infection, though etiology is not certain. EAU weakly recommends MRI for diagnosis and characterization of urethral diverticula.[26] Transvaginal diverticulectomy commonly uses a well-vascularized vaginal flap, preserves periurethral fascia for closure, removes the entire diverticular wall and ostium, and closes the urethra watertight with multilayer closure and nonoverlapping suture lines.[26] A Martius flap is selective, for example in recurrent, large or deficient-tissue repairs.[26] EAU strongly recommends counseling about persistent or de novo lower urinary tract symptoms, including incontinence, after repair.[26] EAU strongly recommends assessing coexisting voiding dysfunction and urinary incontinence; for bothersome SUI, it weakly recommends a counseled concomitant non-synthetic sling. It discourages a concomitant synthetic midurethral sling because mesh near a fresh repair may increase erosion, extrusion, and fistula risks.[26]
- Female urethral stricture. Uncommon but often diagnosed late. EAU guidance weakly recommends dilation to 24–41 Fr as initial treatment of female urethral stricture and meatotomy or meatoplasty for meatal stricture; for a second recurrence when intermittent self-dilation is unsuitable or definitive care is desired, it strongly recommends urethroplasty.[31] The 2023 AUA amendment says urethroplasty should be offered because endoscopic efficacy is low; its recommendation that surgeons may use oral mucosal grafts, vaginal flaps, or both is Moderate (Grade C).[35] Dorsal or ventral onlay buccal-graft urethroplasty is one option among oral, vaginal and labial graft or flap repairs; selection depends on tissue quality and operative factors.[31] Stricture patterns differ from the male urethra because of its short length, lack of a corpus spongiosum and vaginal-wall continuity.
- Urethrovaginal fistula. Often iatrogenic in adults (including after anti-incontinence or diverticulum surgery); obstetric and radiation-associated causes also occur. Repair is individualized to site, size, etiology and tissue loss, usually with a vaginal approach, watertight layered closure and drainage. EAU weakly recommends an interposition graft for radiation-associated fistula repair.[26] In other urethrovaginal repairs, tissue interposition is selective when tissue is deficient or the repair is complex; evidence for routine Martius use is limited.[26]
- Radical cystectomy with urethral preservation for orthotopic neobladder. The mid and distal sphincter and intrapelvic somatic nerves are relevant to continence, and tumor clearance governs whether urethral preservation is appropriate.[6][11] Urethral-margin assessment, including the decision to use frozen section, and nerve and vessel preservation depend on cancer location, planned diversion and operative anatomy. For orthotopic diversion after cystectomy for cancer, the AUA/ASCO/SUO guideline (2017; amended 2024) requires verification of a negative urethral margin .[32][36]
- Radical pelvic surgery and pudendal sparing. Pudendal and intrapelvic somatic branches may be vulnerable during extensive lateral vaginal dissection or colpectomy; injury and postoperative denervation are risks.
- Cystocele repair. Prolapse reduction testing can reveal occult SUI, and de novo SUI may appear after repair. Counsel according to symptomatic or occult SUI status and the added adverse-event risk of combined surgery. Current EAU guidance advises against concomitant anti-incontinence surgery at abdominal prolapse repair when neither symptomatic nor occult SUI is present.[26]
Videos
Lecture series by Dr. Divakar Dalela (Dalela Academy of Urology):
References
1. Hamner JJ, Carrick KS, Ramirez DMO, Corton MM. "Gross and Histologic Relationships of the Retropubic Urethra to Lateral Pelvic Sidewall and Anterior Vaginal Wall in Female Cadavers: Clinical Applications to Retropubic Surgery." Am J Obstet Gynecol. 2018;219(6):597.e1–597.e8. doi:10.1016/j.ajog.2018.09.037
2. Carlile A, Davies I, Faragher E, Brocklehurst JC. "The Epithelium in the Female Urethra: A Quantitative Study." J Urol. 1987;138(4):775–777. doi:10.1016/s0022-5347(17)43369-6
3. Liu T, Muro S, Tharnmanularp S, Akita K. "Three-Dimensional Analysis of the Distribution of Smooth and Skeletal Muscle Tissue Around the Female Urethra." Int Urogynecol J. 2025;36(3):647–654. doi:10.1007/s00192-025-06045-w
4. DeLancey JO. "Correlative Study of Paraurethral Anatomy." Obstet Gynecol. 1986;68(1):91–97. PMID 3725263
5. Mueller M, Drumm BT, Hannan JL, Ruetten H. "Advancing Our Understanding of the Urothelium and Lamina Propria, Hormone Receptors, Vascular Supply, and Sensory Aspects of the Female Human Urethra." Neurourol Urodyn. 2025;44(4):935–943. doi:10.1002/nau.70003
6. Hinata N, Murakami G, Abe S, et al. "Detailed Histological Investigation of the Female Urethra: Application to Radical Cystectomy." J Urol. 2012;187(2):451–456. doi:10.1016/j.juro.2011.10.037
7. Strohbehn K, Quint LE, Prince MR, Wojno KJ, DeLancey JO. "Magnetic Resonance Imaging Anatomy of the Female Urethra: A Direct Histologic Comparison." Obstet Gynecol. 1996;88(5):750–756. doi:10.1016/0029-7844(96)00323-7
8. Colleselli K, Stenzl A, Eder R, et al. "The Female Urethral Sphincter: A Morphological and Topographical Study." J Urol. 1998;160(1):49–54. doi:10.1016/s0022-5347(01)63025-8
9. Norton P, Brubaker L. "Urinary Incontinence in Women." Lancet. 2006;367(9504):57–67. doi:10.1016/S0140-6736(06)67925-7
10. Yucel S, De Souza A, Baskin LS. "Neuroanatomy of the Human Female Lower Urogenital Tract." J Urol. 2004;172(1):191–195. doi:10.1097/01.ju.0000128704.51870.87
11. Borirakchanyavat S, Aboseif SR, Carroll PR, Tanagho EA, Lue TF. "Continence Mechanism of the Isolated Female Urethra: An Anatomical Study of the Intrapelvic Somatic Nerves." J Urol. 1997;158(3 Pt 1):822–826. doi:10.1097/00005392-199709000-00035. PMID: 9258091
12. Wecht JM, Krassioukov AV, Alexander M, et al. "International Standards to Document Autonomic Function Following SCI (ISAFSCI): Second Edition." Top Spinal Cord Inj Rehabil. 2021;27(2):23–49. doi:10.46292/sci2702-23
13. Panicker JN, Fowler CJ, Kessler TM. "Lower Urinary Tract Dysfunction in the Neurological Patient: Clinical Assessment and Management." Lancet Neurol. 2015;14(7):720–732. doi:10.1016/S1474-4422(15)00070-8
14. Siracusano S, Bertolotto M, d'Aloia G, Silvestre G, Stener S. "Colour Doppler Ultrasonography of Female Urethral Vascularization in Normal Young Volunteers: A Preliminary Report." BJU Int. 2001;88(4):378–381. doi:10.1046/j.1464-410x.2001.02233.x
15. Wieczorek AP, Woźniak MM, Stankiewicz A, et al. "Quantitative Assessment of Urethral Vascularity in Nulliparous Females Using High-Frequency Endovaginal Ultrasonography." World J Urol. 2011;29(5):625–632. doi:10.1007/s00345-011-0732-x
16. Sery FG, Wolfram-Gabel R, Sick H. "Microvascularization of the Female Urethra in Fetuses, Neonates and Infants." Surg Radiol Anat. 2002;24(5):271–276. doi:10.1007/s00276-002-0062-1
17. Carroll PR, Dixon CM. "Surgical Anatomy of the Male and Female Urethra." Urol Clin North Am. 1992;19(2):339–346. doi:10.1016/s0094-0143(21)00397-9
18. El-Sayed RF, Morsy MM, El-Mashed SM, Abdel-Azim MS. "Anatomy of the Urethral Supporting Ligaments Defined by Dissection, Histology, and MRI of Female Cadavers and MRI of Healthy Nulliparous Women." AJR Am J Roentgenol. 2007;189(5):1145–1157. doi:10.2214/AJR.07.2215
19. Peng Y, Khavari R, Nakib NA, Boone TB, Zhang Y. "Assessment of Urethral Support Using MRI-derived Computational Modeling of the Female Pelvis." Int Urogynecol J. 2016;27(2):205–212. doi:10.1007/s00192-015-2804-8
20. DeLancey JO. "Structural Aspects of the Extrinsic Continence Mechanism." Obstet Gynecol. 1988;72(3 Pt 1):296–301. PMID 3405547
21. Chermansky CJ, Moalli PA. "Role of Pelvic Floor in Lower Urinary Tract Function." Auton Neurosci. 2016;200:43–48. doi:10.1016/j.autneu.2015.06.003
22. Ashton-Miller JA, DeLancey JO. "Functional Anatomy of the Female Pelvic Floor." Ann N Y Acad Sci. 2007;1101:266–296. doi:10.1196/annals.1389.034
23. van Geelen H, Sand PK. "The Female Urethra: Urethral Function Throughout a Woman's Lifetime." Int Urogynecol J. 2023;34(6):1175–1186. doi:10.1007/s00192-023-05469-6
24. Pipitone F, Sadeghi Z, DeLancey JOL. "Urethral Function and Failure: A Review of Current Knowledge of Urethral Closure Mechanisms, How They Vary, and How They Are Affected by Life Events." Neurourol Urodyn. 2021;40(8):1869–1879. doi:10.1002/nau.24760
25. de Vries AM, Venema PL, Heesakkers JPFA. "Midurethral Support Is Also Necessary for Reflex Closure of the Urethra." Neurourol Urodyn. 2018;37(8):2965–2972. doi:10.1002/nau.23807
26. European Association of Urology. EAU Guidelines on Non-neurogenic Female LUTS: Disease Management, §§4.2, 4.7–4.9. Current online edition accessed 2026-09-20.
27. Chapple CR, Helm CW, Blease S, Milroy EJ, Rickards D, Osborne JL. "Asymptomatic Bladder Neck Incompetence in Nulliparous Females." Br J Urol. 1989;64(4):357–359. doi:10.1111/j.1464-410x.1989.tb06042.x
28. British Association of Urological Surgeons. Functional, Continence & Reconstruction. “Artificial Urinary Sphincter (AUS) – Female.” Accessed October 4, 2026.
29. de Groat WC, Griffiths D, Yoshimura N. "Neural control of the lower urinary tract." Compr Physiol. 2015;5(1):327–396. doi:10.1002/cphy.c130056
30. Gosling JA, Dixon JS, Lendon RG. "The autonomic innervation of the human male and female bladder neck and proximal urethra." J Urol. 1977;118(2):302–305. doi:10.1016/S0022-5347(17)57981-1
31. European Association of Urology. EAU Guidelines on Urethral Strictures: Disease Management in Females. Current online edition accessed October 4, 2026.
32. Chang SS, Bochner BH, Chou R, et al. "Treatment of Non-Metastatic Muscle-Invasive Bladder Cancer: AUA/ASCO/ASTRO/SUO Guideline." J Urol. 2017;198(3):552–559. doi:10.1016/j.juro.2017.04.086
33. Trowbridge ER, Wei JT, Fenner DE, Ashton-Miller JA, DeLancey JO. "Effects of aging on lower urinary tract and pelvic floor function in nulliparous women." Obstet Gynecol. 2007;109(3):715–720. doi:10.1097/01.AOG.0000257074.98122.69
34. Kobata SA, Girão MJBC, Baracat EC, et al. "Estrogen therapy influence on periurethral vessels in postmenopausal incontinent women using Dopplervelocimetry analysis." Maturitas. 2008;61(3):243–247. doi:10.1016/j.maturitas.2008.07.015
35. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. "Urethral Stricture Disease Guideline Amendment (2023)." J Urol. 2023;210(1):64–71. doi:10.1097/JU.0000000000003482
36. Holzbeierlein J, Bixler BR, Buckley DI, et al. "Treatment of Non-Metastatic Muscle-Invasive Bladder Cancer: AUA/ASCO/SUO Guideline (2017; Amended 2020, 2024)." J Urol. 2024;212(1):3–10. doi:10.1097/JU.0000000000003981