The Kidneys
The kidneys are paired retroperitoneal organs that together receive roughly 20% of cardiac output at rest.[17] In healthy adults, glomeruli can produce as much as 180 L of ultrafiltrate per day.[3] Average urine output is approximately 1.5 L per day.[18]
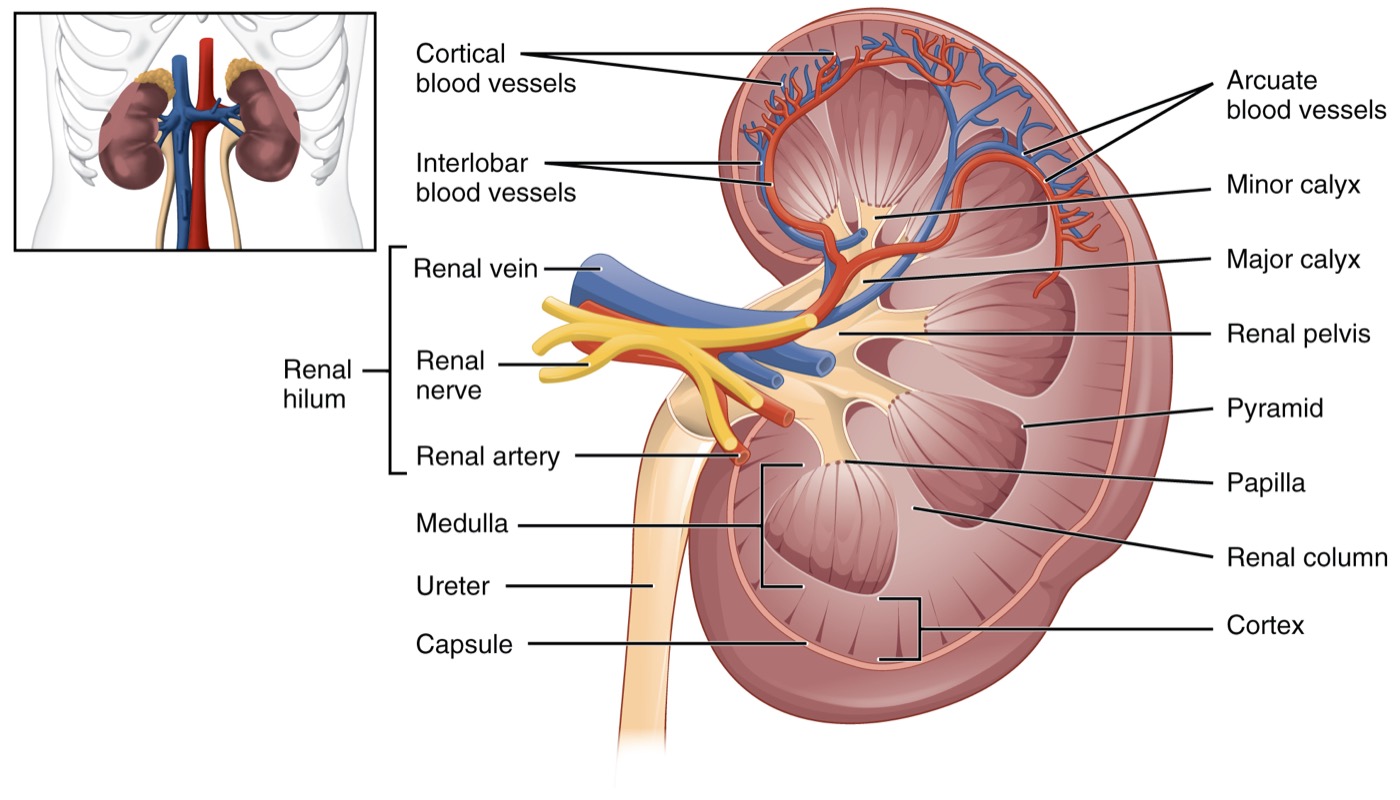
OpenStax Anatomy & Physiology — Internal structure of the kidney. (CC BY 4.0)
Surgical Anatomy
Each adult kidney is approximately 11 × 6 × 3 cm and 125–170 g. The right kidney sits 1–2 cm lower than the left because of the liver. The relations in the operating field are:
| Aspect | Left kidney | Right kidney |
|---|---|---|
| Anterior | Stomach, pancreas (body/tail), spleen, splenic flexure, jejunum | Liver, duodenum (2nd portion), hepatic flexure |
| Posterior | Diaphragm, psoas, quadratus lumborum, transversus abdominis; 11th–12th ribs | Same; usually only 12th rib |
| Superior | Left adrenal | Right adrenal |
Upper pole relations explain the risk of pleural injury with posterior flank access above the 12th rib and splenic / hepatic capsule injury during mobilization. Pancreatic tail injury is a recognized pitfall on the left.
Fascial compartments
The retroperitoneal envelope determines how urinomas track, how abscesses are drained, and which planes are developed during nephrectomy, ureterolysis and auto-transplantation.
- Renal (fibrous) capsule. The capsule is tightly adherent. It is stripped off in decapsulation and during intraparenchymal dissection or partial nephrectomy.
- Perirenal fat. This fat immediately surrounds the kidney and harbors accessory polar vessels.
- Gerota's (renal) fascia. This fascia encloses the kidney, perirenal fat and adrenal. It fuses superolaterally and has limited continuity across the midline; inferiorly, its anterior and posterior leaves merge into a multilaminar fascia in the iliac fossa. Multilaminar caudal renal fascia can restrain perirenal collections, but cadaveric injection studies disagree on communication with the infrarenal and pelvic extraperitoneal spaces; imaging defines the extent of each urinoma or hematoma.[15][27]
- Pararenal fat. This fat lies outside Gerota's fascia, in anterior and posterior compartments.
- Transversalis fascia. This fascia forms the lateral limit of the retroperitoneum.
Collecting system
The papillae drain through approximately 7–14 minor calyces into 2–3 major calyceal groups and then the renal pelvis. Superior and inferior groups are common; an independent interpolar major group is a variant.[28] Calyceal anatomy varies widely and is worth reviewing on preoperative imaging before endopyelotomy, UPJ reconstruction, or percutaneous access planning. The ureteropelvic junction (UPJ) lies on the medial aspect of the pelvis.[5] A lower-pole crossing vessel is a frequent finding in selected adult UPJ-obstruction surgical series.[5]
Innervation and referred pain
Visceral sensory fibers travel with sympathetic roots T10–L1. Pain from ureteral obstruction, pyelonephritis, or parenchymal distension classically refers to the flank and radiates to the ipsilateral groin or testicle or labium majus, reflecting shared innervation with the genitofemoral and ilioinguinal nerves.
Vascular Anatomy
Every renal operation is organized around the vascular pedicle.
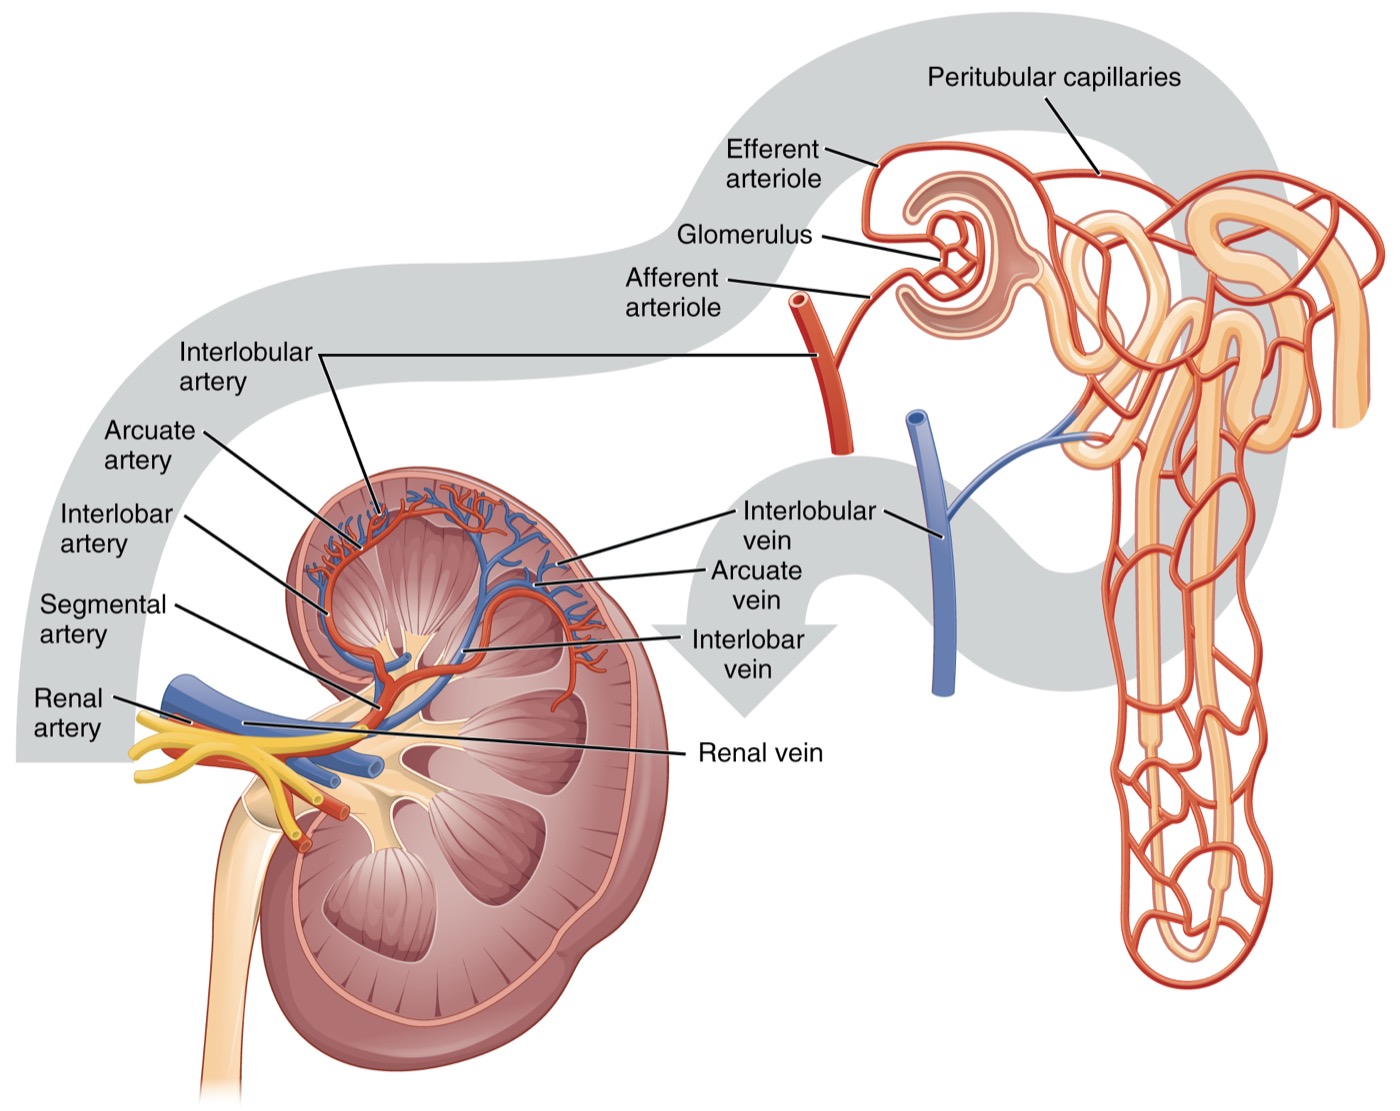
The renal vascular tree. The renal artery divides into segmental → interlobar → arcuate → interlobular (cortical radiate) arteries, which feed the glomerular afferent arterioles; efferent arterioles then form the peritubular capillary network investing the tubules. (CC BY, OpenStax Anatomy & Physiology)
- A single renal artery enters each hilum in most people; a systematic review estimated accessory arteries in about 21%, with variation by population and imaging method.[6] Segmental and polar branches often supply distinct territories, so inadvertent loss can cause segmental ischemia; the extent of infarction and whole-kidney functional effect depend on the artery and territory.[7]
- The main renal artery divides into anterior and posterior branches before or near the hilum, with variable branching.[23] Brödel's plane between these territories is relatively less vascular, varies in extent, and still contains small crossing vessels; it is the classical plane for intersegmental nephrotomy in open surgery.[24] For percutaneous access, a posterior calyceal trajectory helps avoid major vessels but does not eliminate bleeding risk.[25]
- Arterial branching runs from segmental arteries to interlobar, arcuate (at the corticomedullary junction), interlobular (cortical radial) and afferent arterioles. Efferent arterioles emerging from juxtamedullary glomeruli give rise to the vasa recta that supply the medulla. The medulla is essentially supplied by postglomerular blood and is therefore more vulnerable to ischemia than the cortex.
- Venous drainage. Interlobular, arcuate, interlobar and segmental veins drain to the main renal vein. The left renal vein usually receives the left gonadal, adrenal, and lumbar veins and crosses anterior to the aorta beneath the SMA, where compression can produce nutcracker physiology. Retroaortic and circumaortic left renal veins are variants to identify on preoperative vascular imaging.[29] The right renal vein is short, drains directly, and usually has no tributaries. A cadaveric morphometric study of 100 kidney pairs measured the right renal vein at 2.4 ± 0.7 cm and the left at 5.9 ± 1.5 cm, a length difference relevant to vascular control during donor nephrectomy, autotransplantation and IVC/renal-vein exposure.[14]
- Lymphatics. The right kidney drains to right paracaval and interaortocaval nodes and the left kidney to left paraaortic and preaortic nodes. Some cross-drainage occurs between the two sides.
Accessory arteries and reconstruction. Unrecognized variant vessels can complicate renal hilar and UPJ surgery. Review available vascular-phase imaging and, when the operation requires it, map the arteries and veins on both sides, including lower-pole vessels near the UPJ. Preservation or sacrifice of a branch is individualized to its territory, procedure and available reconstruction options; neither CT urogram phase selection nor a brief clamp or Doppler test alone establishes that a segment is dispensable.[6][7]
Nephron Overview (Clinically Relevant Level)
Each kidney contains roughly a million nephrons, with substantial individual variation. After loss of renal mass, single-nephron filtration can rise in the remaining kidney (compensatory hyperfiltration), but the degree of compensation and long-term outcome vary.[8]

The uriniferous tubule (nephron). The glomerular capsule and convoluted tubules sit in the cortical substance; the loop of Henle descends into the medulla, and the collecting tubules drain through the ducts of Bellini at the papilla. (Public domain, Gray's Anatomy)
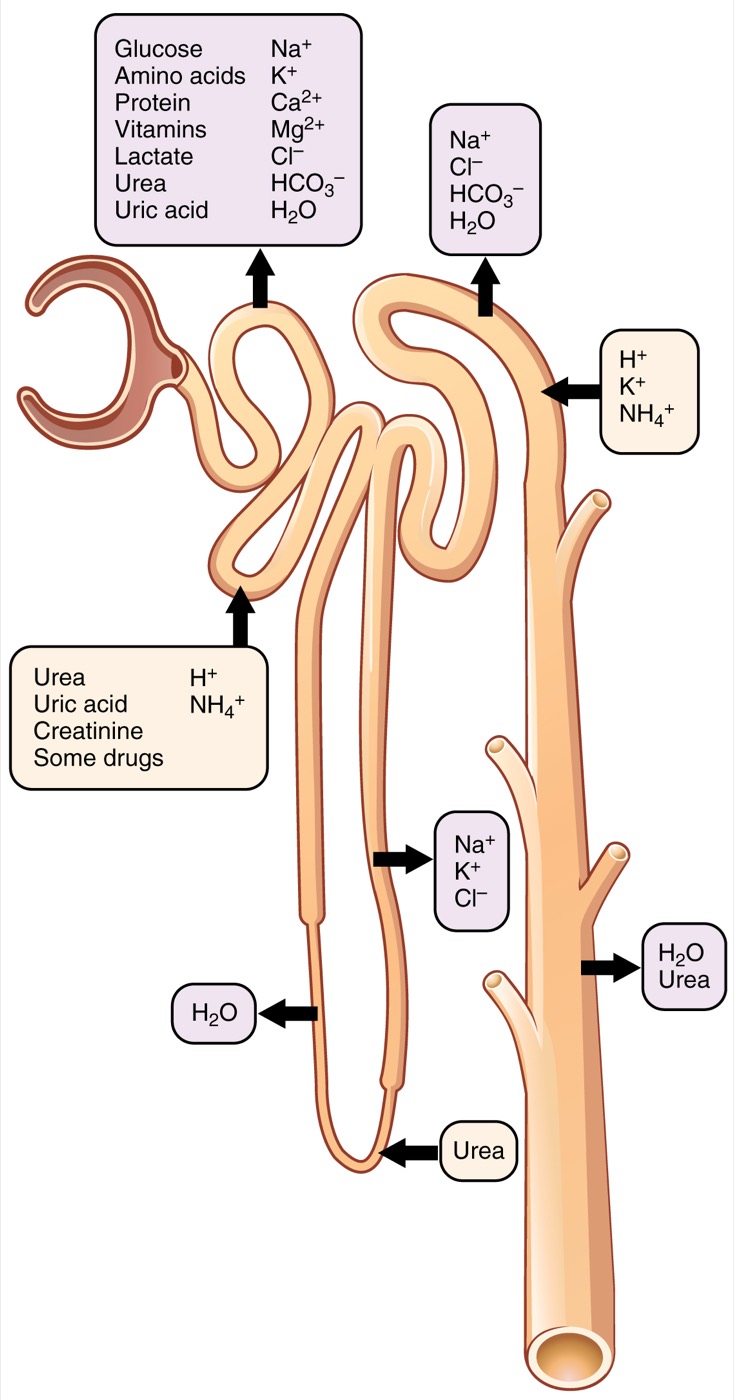
Tubular handling along the nephron — the major solutes and water reabsorbed into the blood and secreted into the filtrate at each segment. This segmental division of labor underlies the kidney's clearance of drugs and metabolites and the electrolyte disturbances seen after bowel-segment urinary reconstruction. (CC BY, OpenStax Anatomy & Physiology)
Glomerular filtration depends on three things:
- The ultrafiltration coefficient (area × hydraulic permeability of the barrier) falls in glomerulosclerosis, diabetic nephropathy, and with nephron loss.
- Ureteral obstruction can raise Bowman's-space pressure and reduce filtration.[16] In rats with partial renal-vein ligation, GFR fell despite an unchanged transglomerular hydrostatic gradient; renal plasma flow and the ultrafiltration coefficient fell while glomerular-capillary and Bowman's-space pressures both rose.[30] Renal tamponade is a proposed contributor to dysfunction in heart failure.[2]
- The oncotic pressure opposing filtration is modestly altered by plasma protein concentration.
Tubular function can be collapsed, for operative purposes, into three jobs:
- Bulk reabsorption (proximal tubule). This segment recovers 60–70% of filtered Na⁺ and water, approximately 80% of filtered bicarbonate, and nearly all filtered glucose, amino acids, and low-molecular-weight proteins.[19][20] Substantial generalized proximal dysfunction can produce low-molecular-weight proteinuria, glucosuria despite euglycemia, aminoaciduria, and phosphaturia (a Fanconi phenotype). These findings are neither consistent nor necessarily early in ischemic or drug-associated acute kidney injury; distinguish injury after contrast from injury caused by contrast.[4][9]
- Concentration (loop of Henle and collecting duct). This segment generates and exploits the medullary osmotic gradient under vasopressin control. Loop-of-Henle or medullary injury can impair urinary concentration, but post-obstructive diuresis after relief of prolonged obstruction also reflects solute excretion, loss of medullary tonicity, aquaporin downregulation and tubular transporter dysfunction; urine output varies.[16]
- Fine tuning (distal nephron). The distal nephron regulates final Na⁺, K⁺, H⁺ and water handling under aldosterone and vasopressin, which is relevant when interpreting postoperative electrolyte and acid-base derangements.
The medulla is a vulnerable zone. Its relatively low oxygen tension reflects countercurrent vascular exchange while the thick ascending limb has high transport-related oxygen demand.[1][9] This makes medullary tissue susceptible to hypoxic stress.[1][9] Ischemic, drug-associated and post-contrast kidney injury have different mechanisms and distributions.[1][9]
Illustrative adult reference values
These approximate values describe healthy adult physiology. GFR, urine volume and concentrating ability vary with age, body size, fluid intake, illness and measurement method.
| Parameter | Typical adult value |
|---|---|
| Renal blood flow | ~1 L/min (20–25% of cardiac output)[21] |
| GFR | ~100–125 mL/min/1.73 m² (age-dependent)[22] |
| Filtration fraction | ~20%[17] |
| Daily ultrafiltrate | ~180 L |
| Daily urine output | ~1.0–2.0 L |
| Minimum urine osmolality | ~50 mOsm/kg (max dilution) |
| Maximum urine osmolality | ~1,200 mOsm/kg (max concentration) |
Endocrine Output
The kidney has three hormonal roles with operative relevance:
- Renin (juxtaglomerular cells). Reduced afferent-arteriolar perfusion pressure, sympathetic input and reduced distal NaCl delivery trigger renin release. Renin release is relevant in renovascular hypertension, post-clamp ischemic hypertension, and the hemodynamic swings after nephrectomy or revascularization.
- Erythropoietin (peritubular cortical fibroblasts). Hypoxia stimulates erythropoietin release. Reduced erythropoietin contributes to anemia in advanced CKD over time; an abrupt postoperative hemoglobin fall should not be attributed to new erythropoietin loss without assessing bleeding, dilution and other causes.[10]
- Active vitamin D (proximal-tubule 1α-hydroxylase). The enzyme converts 25(OH)D to 1,25(OH)₂D. Reduced calcitriol synthesis contributes to secondary hyperparathyroidism and CKD-associated bone disease alongside hypocalcemia and hyperphosphatemia.[31]
Clinical Correlations for the Reconstructive Urologist
- Medullary ischemic injury and warm ischemia time. During partial nephrectomy, minimize ischemic exposure while preserving viable parenchyma and achieving safe tumor removal. Some series associate longer warm ischemia beyond about 25–30 minutes with worse operated-kidney function; an off-clamp approach is not routinely superior to limited on-clamp ischemia in patients with two functioning kidneys .[11][12]
- Segmental arterial supply. Injury to an accessory or polar artery can compromise the supplied territory during partial nephrectomy, donor procurement, transplant, or UPJ reconstruction.[7] The actual infarct and functional consequence depend on branch caliber, territory and collateral or alternative perfusion.[7]
- Obstruction and backpressure nephropathy. Elevated collecting-system pressure can reduce filtration and injure renal parenchyma. An infected obstructed kidney or obstruction with severe renal failure requires urgent decompression. After drainage, urine output >200 mL/h for at least 2 consecutive hours or >3 L/24 h meets a common definition of post-obstructive diuresis and calls for fluid-balance and electrolyte monitoring, particularly after chronic or bilateral obstruction.[16] Recovery depends on duration, severity, infection, and baseline function.[16]
- Venous congestion and compartment pressure. Elevated renal venous or intra-abdominal pressure may reduce renal perfusion and filtration; the contribution of a distinct "renal tamponade" mechanism in heart failure remains a hypothesis.[2]
- Split renal function assessment. MAG3 or DMSA studies can estimate each kidney's contribution when the result would change decisions about a poorly functioning obstructed unit, bilateral disease or salvage versus nephrectomy.
- Hyperfiltration after nephrectomy. The remaining kidney often compensates, so total GFR usually falls by less than half after donation, but the amount varies between people.[8][13] Donor follow-up includes blood pressure, estimated GFR and albuminuria assessment.[13]
- Low-molecular-weight proteinuria as a tubular-injury marker. Cystatin C, β₂-microglobulin, and retinol-binding protein are normally reabsorbed by the proximal tubule. Increased urinary excretion suggests impaired proximal reabsorption, but heavy glomerular proteinuria can saturate uptake without primary tubular injury.[4][26]
- Gerota's fascia, urinoma, and abscess. Urinomas from calyceal tears, pyeloplasty leak, or percutaneous-tract extravasation may be contained within Gerota's fascia; abscesses can cross into the pararenal spaces once Gerota's is violated. Imaging interpretation after any upper-tract reconstruction depends on knowing these compartments.
Videos
References
1. Brezis M, Rosen S. "Hypoxia of the Renal Medulla — Its Implications for Disease." N Engl J Med. 1995;332(10):647–655. doi:10.1056/NEJM199503093321006
2. Boorsma EM, Ter Maaten JM, Voors AA, van Veldhuisen DJ. "Renal Compression in Heart Failure: The Renal Tamponade Hypothesis." JACC Heart Fail. 2022;10(3):175–183. doi:10.1016/j.jchf.2021.12.005
3. Benzing T, Salant D. "Insights into Glomerular Filtration and Albuminuria." N Engl J Med. 2021;384(15):1437–1446. doi:10.1056/NEJMra1808786
4. Hoenig MP, Brooks CR, Hoorn EJ, Hall AM. "Biology of the Proximal Tubule in Body Homeostasis and Kidney Disease." Nephrol Dial Transplant. 2025;40(2):234–243. doi:10.1093/ndt/gfae177
5. O'Sullivan NJ, Anderson S. "Pelviureteric Junction Obstruction in Adults: A Systematic Review of the Literature." Curr Urol. 2023;17(2):86–91. doi:10.1097/CU9.0000000000000154
6. Triantafyllou G, Paschopoulos I, Węgiel A, et al. "The Accessory Renal Arteries: A Systematic Review with Meta-Analysis." Clin Anat. 2025;38(6):660–672. doi:10.1002/ca.24255
7. Karmacharya J, Parmer SS, Antezana JN, et al. "Outcomes of Accessory Renal Artery Occlusion During Endovascular Aneurysm Repair." J Vasc Surg. 2006;43(1):8–13. doi:10.1016/j.jvs.2005.09.008
8. Lenihan CR, Busque S, Derby G, Blouch K, Myers BD, Tan JC. "Longitudinal Study of Living Kidney Donor Glomerular Dynamics After Nephrectomy." J Clin Invest. 2015;125(3):1311–1318. doi:10.1172/JCI78885
9. Davenport MS, Perazella MA, Yee J, et al. "Use of Intravenous Iodinated Contrast Media in Patients With Kidney Disease: Consensus Statements from the American College of Radiology and the National Kidney Foundation." Radiology. 2020;294(3):660–668. doi:10.1148/radiol.2019192094
10. Kidney Disease: Improving Global Outcomes (KDIGO) Anemia Work Group. "KDIGO 2026 Clinical Practice Guideline for the Management of Anemia in Chronic Kidney Disease." Kidney Int. 2026;109(1 Suppl):S1–S99. doi:10.1016/j.kint.2025.06.006
11. Rod X, Peyronnet B, Seisen T, et al. "Impact of Ischaemia Time on Renal Function After Partial Nephrectomy: A Systematic Review." BJU Int. 2016;118(5):692–705. doi:10.1111/bju.13580
12. European Association of Urology. EAU Guidelines on Renal Cell Carcinoma: Disease Management, §7.2.3.b.9. Current online edition, accessed 2026-09-20.
13. Kidney Disease: Improving Global Outcomes (KDIGO) Living Kidney Donor Work Group. Clinical Practice Guideline on the Evaluation and Care of Living Kidney Donors, Chapter 19. Transplantation. 2017;101(8 Suppl 1):S1–S109. doi:10.1097/tp.0000000000001769
14. Satyapal KS, Rambiritch V, Pillai G. "Morphometric Analysis of the Renal Veins." Anat Rec. 1995;241(2):268–272. doi:10.1002/ar.1092410213
15. Raptopoulos V, Lei QF, Touliopoulos P, Vrachliotis TG, Marks SC Jr. "Why perirenal disease does not extend into the pelvis: the importance of closure of the cone of the renal fasciae." AJR Am J Roentgenol. 1995;164(5):1179–1184. doi:10.2214/ajr.164.5.7717228
16. Yaxley J, Yaxley W. "Obstructive uropathy - acute and chronic medical management." World J Nephrol. 2023;12(1):1–9. doi:10.5527/wjn.v12.i1.1
17. Betts JG, Young KA, Wise JA, et al. "25.5 Physiology of Urine Formation." Anatomy and Physiology 2e. OpenStax; 2022. Chapter.
18. Betts JG, Young KA, Wise JA, et al. "26.2 Water Balance." Anatomy and Physiology 2e. OpenStax; 2022. Chapter.
19. Curthoys NP, Moe OW. "Proximal Tubule Function and Response to Acidosis." Clin J Am Soc Nephrol. 2014;9(9):1627–1638. doi:10.2215/CJN.10391012
20. Molitoris BA, Sandoval RM, Yadav SPS, Wagner MC. "Albumin uptake and processing by the proximal tubule: physiological, pathological, and therapeutic implications." Physiol Rev. 2022;102(4):1625–1667. doi:10.1152/physrev.00014.2021
21. Guerci P, Ergin B, Ince C. "The macro- and microcirculation of the kidney." Best Pract Res Clin Anaesthesiol. 2017;31(3):315–329. doi:10.1016/j.bpa.2017.10.002
22. Noronha IL, Santa-Catharina GP, Andrade L, Coelho VA, Jacob-Filho W, Elias RM. "Glomerular filtration in the aging population." Front Med (Lausanne). 2022;9:769329. doi:10.3389/fmed.2022.769329
23. Klatte T, Ficarra V, Gratzke C, et al. "A Literature Review of Renal Surgical Anatomy and Surgical Strategies for Partial Nephrectomy." Eur Urol. 2015;68(6):980–992. doi:10.1016/j.eururo.2015.04.010
24. Macchi V, Picardi E, Inferrera A, et al. "Anatomic and Radiologic Study of Renal Avascular Plane (Brödel's Line) and Its Potential Relevance on Percutaneous and Surgical Approaches to the Kidney." J Endourol. 2018;32(2):154–159. doi:10.1089/end.2017.0689
25. Kim HY, Lee KW, Lee DS. "Critical causes in severe bleeding requiring angioembolization after percutaneous nephrolithotomy." BMC Urol. 2020;20:22. doi:10.1186/s12894-020-00594-6
26. Bökenkamp A. "Proteinuria—take a closer look!" Pediatr Nephrol. 2020;35(4):533–541. doi:10.1007/s00467-019-04454-w
27. Mindell HJ, Mastromatteo JF, Dickey KW, et al. "Anatomic communications between the three retroperitoneal spaces: determination by CT-guided injections of contrast material in cadavers." AJR Am J Roentgenol. 1995;164(5):1173–1178. doi:10.2214/ajr.164.5.7717227
28. Morais ARM, Favorito LA, Sampaio FJB. "Kidney collecting system anatomy applied to endourology - a narrative review." Int Braz J Urol. 2024;50(2):164–177. doi:10.1590/S1677-5538.IBJU.2024.9901
29. Valenzuela Fuenzalida JJ, Vera-Tapia K, Urzúa-Márquez C, et al. "Anatomical Variants of the Renal Veins and Their Relationship with Morphofunctional Alterations of the Kidney: A Systematic Review and Meta-Analysis of Prevalence." J Clin Med. 2024;13(13):3689. doi:10.3390/jcm13133689
30. Dilley JR, Corradi A, Arendshorst WJ. "Glomerular ultrafiltration dynamics during increased renal venous pressure." Am J Physiol. 1983;244(6):F650–F658. doi:10.1152/ajprenal.1983.244.6.F650
31. Kidney Disease: Improving Global Outcomes (KDIGO) CKD-MBD Update Work Group. "KDIGO 2017 Clinical Practice Guideline Update for the Diagnosis, Evaluation, Prevention, and Treatment of Chronic Kidney Disease–Mineral and Bone Disorder (CKD-MBD)." Kidney Int Suppl (2011). 2017;7(1):1–59. doi:10.1016/j.kisu.2017.04.001