The Ureters
The ureters are paired retroperitoneal muscular tubes approximately 25–30 cm long that pump urine from the renal pelvis to the bladder.[1][2] They have a tenuous blood supply that is easily devascularized, a course that is anatomically predictable but iatrogenically vulnerable, and physiologic behaviors (peristalsis, anti-reflux, response to obstruction) that determine how a reconstruction will function.
Segmental Anatomy
The ureter is conventionally divided into three segments based on the iliac vessels and the bony pelvis. This division is practical: it maps to the course on imaging, the expected relations during dissection, and the typical injury mechanisms for each zone.[2]
| Segment | Landmarks | Key relations |
|---|---|---|
| Proximal (upper) | UPJ → crossing of the sacroiliac joint / iliac vessels | On psoas; gonadal vessels cross anterior ~mid-length; aorta/IVC medial; lower pole of kidney / retroperitoneal fat lateral |
| Middle | Over the iliac vessels and bony pelvis | Crosses the iliac vessels near the common iliac bifurcation; the crossing may be over the common or external iliac artery.[23] |
| Distal (pelvic/lower) | From iliac vessels → UVJ | Deep to superior vesical and uterine/vas deferens structures; enters the bladder obliquely |
Course and relations
From superior to inferior:
- Retroperitoneal on psoas. Lies on the psoas major, medial to the genitofemoral nerve, covered by peritoneum. Mobilization requires recognition that the psoas is deep to the ureter.
- Gonadal vessels. The gonadal artery and vein cross anterior to the ureter ("water runs over bridge") at approximately the level of the lower pole of the kidney / mid-ureter. In orchiectomy and ureteral dissection for retrocaval or high ureter, the two structures must be distinguished before ligation.
- Common iliac bifurcation. The ureter crosses anterior to the iliac vessels near the common iliac bifurcation; the crossing may lie over the common or external iliac artery. This region remains a useful landmark during pelvic or vascular surgery, but the ureter’s exact course must be identified.[23]
- Pelvic brim. After crossing the iliac vessels the ureter descends along the lateral pelvic sidewall against the obturator internus, posterior to the ovary in women, medial to the vas deferens in men.
- Cardinal ligament and the uterine artery ("water under the bridge"). In the female pelvis the uterine artery crosses anterior (superior) to the ureter near the cervix within the cardinal ligament; the distance varies with anatomy and pathology. This crossing carries a risk of hysterectomy injury from thermal injury, ligation in hemostatic clamps or inclusion in a cardinal-ligament pedicle. The ureter runs closer to the uterosacral ligament posteriorly and laterally, and palpating a structure believed to be the ureter does not reliably establish its location — direct visual identification is needed.[19] One atlas estimates the interval from the uterine-artery crossing to bladder entry at approximately 2.5 cm.[19]
- Vas deferens. In men the vas crosses anterior to the distal ureter as it runs to the seminal vesicle.
- Ureterovesical junction (UVJ). The ureter enters the bladder obliquely, travels approximately 1.5–2 cm within the detrusor, and opens at the trigonal corner. The oblique intramural course is the structural basis of the passive anti-reflux mechanism (see below).
Operative hotspots for ureteral injury. EAU reports that the lower ureter is usually involved in iatrogenic injury and that gynecologic operations are the most common cause of significant injury, followed by colorectal and vascular surgery.[11] The exact site depends on the procedure and series. Typical sites include:
- The cardinal ligament / uterine artery crossing during hysterectomy
- The IP (infundibulopelvic) ligament during oophorectomy: the gonadal vessels run here alongside the ureter
- The bladder base / trigone during anterior colporrhaphy or anti-incontinence procedures
- Over the common iliac bifurcation during vascular and sigmoid surgery
- At the UPJ during renal or retroperitoneal dissection
Visual identification and careful dissection near the ureter are the basis of prevention. Routine mobilization of the ureter before every adjacent ligation is not required. EAU strongly recommends visual identification of the ureters during complex abdominal and pelvic surgery.[11]
Finding the ureter at laparotomy or laparoscopy. Three direct exposure routes to the pelvic ureter have been described: opening the posterior peritoneum over psoas lateral to the external iliac artery and following the artery cranially to the ureteral crossing; dividing or tenting the round ligament and separating the broad-ligament leaves; or applying gentle adnexal traction, tracing the infundibulopelvic ligament to its retroperitoneal origin, and opening the peritoneum parallel to the ovarian vessels, where the ureter lies posterior and medial to the ovarian pedicle. Distinguishing the ureter from surrounding structures by its paler color and peristaltic activity is a useful cue, but visible peristalsis alone does not confirm ureteral continuity if injury is already suspected (see below).[19]
Blood Supply
The ureter has a segmental blood supply that is longitudinally redundant only because of an adventitial periureteric plexus running along its length. The plexus permits mobilization when the periureteral adventitia and segmental feeders are preserved; stripping the adventitia risks ischemia.[12][11]
| Segment | Typical arterial supply | Approach direction |
|---|---|---|
| Renal pelvis and proximal ureter | Renal artery branches | Medial |
| Abdominal (middle) ureter | Gonadal artery, aorta, common iliac | Medial |
| Pelvic ureter | Internal iliac branches — uterine artery (F), superior/inferior vesical, middle rectal, vaginal (F) | Lateral |
Two practical consequences follow:
- Adventitial preservation. Dissect the ureter with its surrounding adventitial tissue in continuity. The longitudinal anastomotic plexus running in this adventitia is what perfuses the ureter between segmental feeders. Skeletonizing it, even during an otherwise uneventful dissection, can disrupt its adventitial vascular plexus and cause delayed ischemic injury or stricture.[12][11]
- Approach direction matters. Arterial branches generally reach the abdominal ureter medially and the pelvic ureter laterally. Preserve the segmental feeders and periureteral adventitial plexus; choose the dissection plane for the exposure and reconstruction, not by a universal "opposite-side" rule.[12]
Venous and lymphatic drainage
Veins parallel the arteries. Lymphatics follow the course of the ureter: renal and proximal ureteral lymph drains to the para-aortic and interaortocaval basins, middle to common iliac, distal to internal iliac and obturator nodes.
Innervation and Referred Pain
Ureteral innervation is autonomic (sympathetic and parasympathetic), with a dense adventitial and intramural plexus and sensory afferents traveling with the sympathetic roots.[8][9][10]
The operative points are:
- Peristalsis is myogenic, not neurogenic. Complete autonomic denervation does not abolish peristalsis; the ureter continues to contract. Reimplantation, mobilization and even transposition can therefore work despite disruption of the extrinsic nerve supply. The same property is a recognition trap: a fully transected ureter can still show a visible peristaltic wave, so peristalsis by itself does not establish continuity when injury is suspected, and the ureter's course should be directly inspected.[20] If continuity remains uncertain, retrograde or antegrade urography can confirm injury; Ureteral Trauma covers repair by location.[11]
- Referred pain follows the sympathetic roots. The roots are T10–L2. Ureteral pain refers to the flank (upper segment), periumbilical region or groin (middle), and the scrotum, labium majus or anterior thigh (lower or intramural segment), mirroring the migrating stone.
- Nerve density increases distally. In a cadaveric series of 12 ureters from six donors, adventitial nerve density was higher in women throughout the ureter, particularly distally, and smooth-muscle nerve density rose progressively from proximal to distal.[9]
Ureteral Wall, Peristalsis, and What Matters at the Table
The ureter is a three-layer tube: urothelium, smooth muscle arranged in heterogeneously oriented bundles (not discrete circular and longitudinal layers), and adventitia carrying the vessels and nerves.[3][4] Experimental work locates the origin of coordinated pyeloureteric contractions near the pelvis–kidney junction; atypical smooth-muscle cells are proposed pacemakers, with cell distribution varying by species.[6][7]
For operative reasoning the relevant features are:
- Unidirectional pump, not a passive tube. Urine is delivered in discrete boluses, and the oblique UVJ closes between waves. In a postoperative series of 51 ileal ureter replacements in 39 patients, well-functioning intestinal peristalsis was observed in 49; a Boari flap substitutes tubularized bladder wall for native ureter.[24][11]
- Acute and chronic obstruction can behave differently. Acute obstruction can increase contractile activity and produce colic. Chronic obstruction disrupted the coordination of peristalsis in a porcine model.[13]
- Peristalsis depends on L-type calcium channels. Nifedipine blocks action potential, calcium transient, and contraction; clinically, this is relevant only as background to medical expulsive therapy of distal stones.[5]
- Stents alter, but do not invariably abolish, peristalsis. A porcine experiment found an initial increase followed by reduced or absent activity with the tested stents; another reported abnormal waves and flow predominantly around the stent after prolonged placement.[14][15]
The Ureterovesical Junction and Anti-reflux Mechanism
The oblique intramural ureter provides a passive flap valve, and trigonal or ureteric muscle activity may contribute to reflux prevention; there is no discrete ureteral sphincter.[25] Its competence depends on three features, any of which can be disrupted by disease or surgery:[1][2]
- Oblique intramural course. A submucosal tunnel that is compressed as the bladder fills (flap-valve principle). Tunnel length relative to ureteral diameter contributes to anti-reflux competence.[16] The historical 5: 1 ratio is a teaching guide. A finite-element study found that applying it at operative bladder fill may overestimate the needed length.[16]
- Detrusor backing. The ureter lies between mucosa and detrusor so filling pressure closes the tunnel against its muscular floor.
- Trigonal continuity. The ureteral longitudinal fibers continue as the superficial trigone, and Waldeyer's sheath continues as the deep trigone; together these structures anchor the orifice and support tunnel geometry.[21] The distal 3–4 cm of the juxtavesical ureter, including its intramural segment, is surrounded by a fibromuscular sheath (Waldeyer's sheath); its muscular component continues proximally into the ureteral musculature and distally into the deep trigone, while the ureteral longitudinal fibers continue as the superficial trigone and meet the contralateral side at the interureteric ridge, also called Mercier's bar. The superficial and deep trigonal layers can be dissected apart.[21]
Surgical implications:
- Anti-reflux reimplantation (for example, Lich-Gregoir, Cohen cross-trigonal or Politano-Leadbetter) aims for a supported, adequately long tunnel; some adult reimplantations with a psoas hitch or Boari flap intentionally use a refluxing anastomosis, so a submucosal tunnel is not mandatory in every reconstruction. In one retrospective series of 60 adult uretero-neocystostomies (open, laparoscopic and robotic), all anastomoses were refluxing and extravesical, with no significant difference in recurrent stricture between approaches.[18]
- Loss of trigonal continuity (radical cystectomy with neobladder, extensive trigone resection) removes the native mechanism; refluxing ureteral anastomoses to ileal or colonic reservoirs rely on low reservoir pressure rather than a true valve.
Clinical Correlations for the Reconstructive Urologist
- Stone impaction is not confined to three textbook narrowings. The UPJ, iliac crossing and UVJ are useful landmarks, but in a 94-patient CT series of single stones at emergency presentation, only one stone was at the iliac crossing and most were at the UVJ.[17]
- Iatrogenic injury prevention depends on anatomy. Positively identify the ureter and dissect carefully near it while preserving adventitial blood supply. For operations at high risk of ureteral injury, the 2026 EAU guideline gives a Weak recommendation for preoperative prophylactic stents to aid identification or detection; its evidence summary states that they do not prevent injury. Direct visual identification remains necessary.[11]
- Long-segment defects: location, length and vascularity. Reconstruction depends on the site and extent of the defect, viable tissue, bladder capacity and patient factors. Ureteroureterostomy may suit selected shorter defects; psoas hitch or Boari flap can bridge distal defects. Selected complex strictures may also be repaired with oral-mucosa grafts or appendiceal tissue, although the published studies have heterogeneous outcomes and short follow-up.[26] Bowel interposition or renal autotransplantation are selected salvage options. Preserve adventitia at cut edges when feasible.[11]
- Megaureter and post-obstructive dilation. Chronic obstruction may impair contractile coordination; recovery after relief or reconstruction varies with the underlying lesion and degree of damage.[13]
- Vesicoureteral reflux and the 5: 1 rule. Tunnel geometry is one determinant of anti-reflux competence. The historical 5: 1 ratio is a planning heuristic.[16]
- Denervation tolerance. Peristalsis is myogenic, so extensive ureteral mobilization and transposition can be tolerated functionally if the adventitial blood supply is respected.
- Sex-specific relations. In women the uterine-artery crossing is an important pelvic operative hazard; in men the vas deferens crosses the distal ureter.
- Ureteral herniation. The ureter can rarely enter an inguinal hernia beside a peritoneal sac (paraperitoneal) or with retroperitoneal fat and no sac (extraperitoneal), producing unilateral or, if bilateral, potentially bilateral obstruction and hydronephrosis; a looped "fish-hook" appearance may be seen on retrograde pyelography. It has been found incidentally during hernia repair and in the workup of otherwise unexplained hydronephrosis. In an inguinal hernia with unexplained hydronephrosis, renal impairment, or urinary tract infection, consider ureteral involvement and define its course before repair with CT urography or retrograde pyelography when indicated.[22]
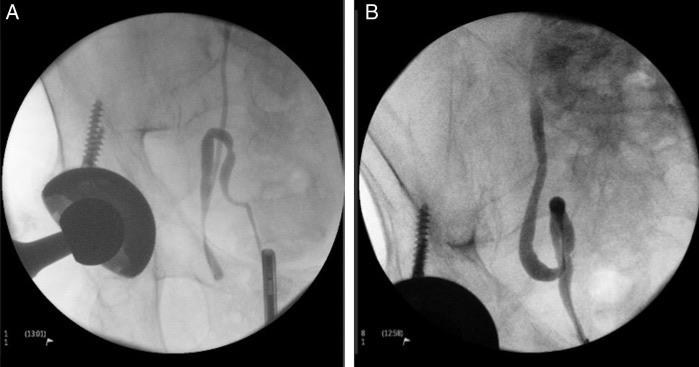
Intraoperative retrograde pyelogram of the right ureter (A) before and (B) after inguinal hernia repair. In A the ureter extends below the right superior pubic ramus; note its position in relation to the prosthesis. From Yahya Z, et al. BMJ Case Rep. 2017;2017:bcr2017219288, Figure 3 (CC BY-NC).[22]
Videos
References
1. Bohnenpoll T, Kispert A. "Ureter Growth and Differentiation." Semin Cell Dev Biol. 2014;36:21–30. doi:10.1016/j.semcdb.2014.07.014
2. Bhargava P, Dighe MK, Lee JH, Wang C. "Multimodality Imaging of Ureteric Disease." Radiol Clin North Am. 2012;50(2):271–299. doi:10.1016/j.rcl.2012.02.008
3. Hanna MK, Jeffs RD, Sturgess JM, Barkin M. "Ureteral Structure and Ultrastructure. Part I. The Normal Human Ureter." J Urol. 1976;116(6):718–724. doi:10.1016/s0022-5347(17)58986-7
4. Bohnenpoll T, Feraric S, Nattkemper M, et al. "Diversification of Cell Lineages in Ureter Development." J Am Soc Nephrol. 2017;28(6):1792–1801. doi:10.1681/ASN.2016080849
5. Burdyga T, Lang RJ. "Excitation-Contraction Coupling in Ureteric Smooth Muscle: Mechanisms Driving Ureteric Peristalsis." Adv Exp Med Biol. 2019;1124:103–119. doi:10.1007/978-981-13-5895-1_4
6. Hurtado R, Bub G, Herzlinger D. "The Pelvis-Kidney Junction Contains HCN3, a Hyperpolarization-Activated Cation Channel That Triggers Ureter Peristalsis." Kidney Int. 2010;77(6):500–508. doi:10.1038/ki.2009.483
7. Lang RJ, Hashitani H. "Pacemaker Mechanisms Driving Pyeloureteric Peristalsis: Modulatory Role of Interstitial Cells." Adv Exp Med Biol. 2019;1124:77–101. doi:10.1007/978-981-13-5895-1_3
8. Zaitouna M, Alsaid B, Lebacle C, et al. "Origin and Nature of Pelvic Ureter Innervation." Neurourol Urodyn. 2017;36(2):271–279. doi:10.1002/nau.22919
9. Vernez SL, Okhunov Z, Wikenheiser J, et al. "Precise Characterization and 3-Dimensional Reconstruction of the Autonomic Nerve Distribution of the Human Ureter." J Urol. 2017;197(3 Pt 1):723–729. doi:10.1016/j.juro.2016.08.118
10. Nemeth L, O'Briain DS, Puri P. "Demonstration of Neuronal Networks in the Human Upper Urinary Tract Using Confocal Laser Scanning Microscopy." J Urol. 2001;166(1):255–258. doi:10.1097/00005392-200107000-00078
11. Waterloos M, Campos-Juanatey F, Hallscheidt P, et al. EAU Guidelines on Urological Trauma. Limited update, March 2026. Sections 4.2.1–4.2.5 (ureteral trauma).
12. Wein AJ, Kavoussi LR, Novick AC, Partin AW, Peters CA, eds. Campbell-Walsh Urology: Surgical anatomy of the ureter. Elsevier electronic text; ureteral blood-supply section.
13. Djurhuus JC, Constantinou CE. Chronic ureteric obstruction and its impact on the coordinating mechanisms of peristalsis. Urol Res. 1982;10:267–270. doi:10.1007/BF00255872
14. Venkatesh R, Landman J, Minor SD, et al. Impact of a double-pigtail stent on ureteral peristalsis in the porcine model. J Endourol. 2005;19:170–176. doi:10.1089/end.2005.19.170
15. Kinn AC, Lykkeskov-Andersen H. Impact on ureteral peristalsis in a stented ureter: an experimental study in the pig. Urol Res. 2002;30(4):213–218. doi:10.1007/s00240-002-0258-1
16. Kalayeh K, Fowlkes JB, Schultz WW, Sack BS. The 5:1 rule overestimates the needed tunnel length during ureteral reimplantation. Neurourol Urodyn. 2021;40:85–94. doi:10.1002/nau.24526
17. Eisner BH, Reese A, Sheth S, Stoller ML. Ureteral stone location at emergency room presentation with colic. J Urol. 2009;182:165–168. doi:10.1016/j.juro.2009.02.131
18. Ramesmayer C, Pallauf M, Gruber R, et al. Uretero-neocystostomy: a retrospective comparison of open, laparoscopic and robotic techniques. BMC Urol. 2023;23:35. doi:10.1186/s12894-023-01200-1
19. Baggish MS. Identifying and Avoiding Ureteral Injury. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:449–462.
20. Baggish MS. Foundations of Laparoscopy. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:219–230.
21. Karram MM. Surgical Anatomy of the Bladder and Pelvic Ureter. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:1057–1062.
22. Yahya Z, Al-habbal Y, Hassen S. "Ureteral Inguinal Hernia: An Uncommon Trap for General Surgeons." BMJ Case Rep. 2017;2017:bcr2017219288. doi:10.1136/bcr-2017-219288
23. Han Y, Liu P, Chen C, et al. "Digital anatomic study of the ureter relative to bifurcation of the common iliac artery in females." Minim Invasive Ther Allied Technol. 2021;30(2):101–105. doi:10.1080/13645706.2019.1692038
24. Chen S, Huang C, Li Z, et al. "The modified Whitaker test in evaluating the surgical effect after ileal ureter replacement." World J Urol. 2024;42(1):533. doi:10.1007/s00345-024-05209-5
25. Noordzij JW, Dabhoiwala NF. "A view on the anatomy of the ureterovesical junction." Scand J Urol Nephrol. 1993;27(3):371–380. doi:10.3109/00365599309180449
26. Ditonno F, Costantino S, Treccani LP, et al. "Autologous Tissue Substitutes for Ureteral Reconstruction: A Systematic Review of Surgical Techniques and Outcomes." Eur Urol Open Sci. 2026;86:30–41. doi:10.1016/j.euros.2026.02.007