Nerve Blocks
Regional blocks can reduce postoperative pain and opioid requirements when their coverage matches the operation. Two groups matter in reconstructive, functional and urogynecologic practice: fascial plane blocks (TAP, quadratus lumborum, erector spinae, rectus sheath) for abdominal-wall analgesia, and targeted peripheral blocks (pudendal, dorsal penile, penile ring, ilioinguinal/iliohypogastric, spermatic cord, periurethral, uterosacral or cervical) for perineal, penile, scrotal and office-based female procedures. Select the technique with the anesthesia team using the incision, anticipated visceral pain, patient anatomy, anticoagulation, existing neurologic deficits and available monitoring. The 2026 ASA guideline strongly recommends fascial plane blocks to reduce pain and/or opioid use during the first 24 hours after adult open abdominal, retroperitoneal or pelvic surgery; it also strongly recommends them for adult minimally invasive cholecystectomy, appendectomy, bariatric surgery, gastrectomy and liver resection during the first 24 hours. It does not rank ESP, QL and TAP against one another.[1]
This is the block-selection and safety workflow. Use Local Anesthetics for formulation-specific doses and Liposomal Bupivacaine for its label and comparative evidence. Analgesia covers systemic treatment and postoperative monitoring; Anesthesia covers the anesthetic plan.
See also: Nausea & Vomiting, ERAS, Pelvic Neuroanatomy.
Local Anesthetic Pharmacology
Plan the total exposure
Before injection, agree on the agent, concentration, total milligrams, sites and timing with everyone administering local anesthetic. Include bilateral blocks, wound infiltration, urethral or mucosal preparations, catheters and any IV lidocaine. Toxicity is additive; changing agents or dividing injections between surgeon and anesthesiologist does not reset the dose allowance.[2][3]
A generic mg/kg ceiling is not a guarantee of safety. The product, route, vascularity of the site, age, body size, hepatic or cardiac function and repeat dosing matter. Choose the lowest effective exposure and follow the actual product label and institutional protocol. Adult block volumes must not be transferred to children.[2][3]
Amide agents used for blocks
| Agent | Usual concentration | Onset | Typical nerve-block duration | Labeled maximum (adult) |
|---|---|---|---|---|
| Lidocaine | 0.5–2% | Fast | 1–2 h | 4.5 mg/kg, not above 300 mg, without epinephrine; 7 mg/kg, not above 500 mg, with epinephrine[4] |
| Bupivacaine | 0.25–0.5% | Slower | 4–8 h | Adult peripheral block: up to 175 mg per dose without epinephrine or 225 mg with epinephrine, individualized by patient and site; repeat no more often than every 3 h and do not exceed 400 mg in 24 h[3] |
| Ropivacaine | 0.2–0.75% | Slower | 4–8 h | Adult major nerve block: 175–250 mg at 0.5% or 75–300 mg at 0.75%; field/minor nerve block: up to 200 mg at 0.5%. The 770 mg/24 h figure describes intraoperative block plus postoperative epidural infusion, not a general peripheral-block limit.[5] |
Onset and duration are typical ranges that vary with site, volume and adjuvants. For infiltration without vasoconstrictor, the Iowa protocol lists weight-based teaching ceilings of about 2–2.5 mg/kg for bupivacaine and 2–3 mg/kg for ropivacaine; the vulvar series cited below used levobupivacaine up to 2 mg/kg.[39][20] Amides are metabolized hepatically and true allergy is rare. Esters (chloroprocaine, tetracaine, procaine) are hydrolyzed by plasma cholinesterase, and allergy is more common.
Four principles govern block behavior:[6]
- Lipid solubility determines intrinsic potency.
- Protein binding determines duration.
- pKa determines onset; a lower pKa gives faster onset.
- Drug mass influences onset, success and duration in studied peripheral blocks, while low volumes can delay or fail blockade and placement changes the volume needed. Large-volume ropivacaine fascial plane blocks can yield high plasma concentrations, so use the lowest effective total milligram dose.
Mixing and adjuvants
Mixing lidocaine with bupivacaine or ropivacaine is common. In a 2025 synthesis of 19 randomized peripheral-block trials (1,060 adults), short/intermediate- plus long-acting mixtures shortened time to surgical block by 8.4 minutes (18 trials, 1,026 patients) and sensory-block duration by 226 minutes (12 trials, 657 patients); evidence certainty was low to very low.[43] In a randomized comparison of femoral and sciatic blocks, the mixture shortened onset (about 16 versus 23–28 minutes for the long-acting agent alone) but shortened block duration, and the investigators could not show a safety benefit because the lower long-acting plasma level was offset by lidocaine exposure.[7] The current bupivacaine label does not recommend mixing or intercurrent use of other local anesthetics because clinical data are insufficient. Any planned combination needs a compatibility and cumulative-dose assessment. Liposomal bupivacaine has additional restrictions below.[3]
Adjuvants are used to extend block duration:
- Epinephrine 1:200,000 causes local vasoconstriction, slows systemic absorption and can act as an early marker of intravascular injection. Avoid it in end-artery fields such as the penis (see the penile ring block).
- Dexamethasone is a well-studied peripheral-block adjuvant. In an 11-trial meta-analysis (914 patients), perineural dosing prolonged analgesia by about 3 hours versus systemic dosing; the mean difference was 4.0 hours with bupivacaine and a nonsignificant 2.0 hours with ropivacaine, and perineural use is off-label.[8] A 2024 model-based synthesis of 118 trials (9,284 adults receiving unilateral peripheral blocks) estimated similar duration effects for 4 mg perineural and 8 mg intravenous dexamethasone after risk-of-bias correction.[41]
- Clonidine and dexmedetomidine are α2 agonists that extend sensory block, with sedation, bradycardia and hypotension as costs. Verify agent, preservative content and route in a pharmacy or anesthesia protocol.
- Bicarbonate buffers lidocaine for infiltration pain (see below); it is not a duration adjuvant.
Single-shot block duration varies by agent, site, dose and adjuvant; use the typical agent-specific ranges in the table above when planning postoperative analgesia.[6] Beyond that, a continuous catheter is the established way to extend analgesia.
For IV lidocaine, follow the separation intervals and monitoring in Analgesia: a block or infiltration must be coordinated with the infusion, including longer restrictions after liposomal bupivacaine.
Injection Best Practices
- Confirm consent, procedure, side, baseline sensory and motor findings, anticoagulants and the rescue plan. Deep blocks require assessment under the applicable regional-anesthesia antithrombotic rules; the current reference is the ASRA fifth edition (2025), which now describes anticoagulant doses as "low" and "high" rather than prophylactic and therapeutic. It recommends applying the neuraxial guidance to deep plexus and deep peripheral blocks (grade IC); for other plexus or peripheral blocks, performance, catheter maintenance and catheter removal depend on site compressibility, vascularity and the consequences of bleeding (grade IIC).[9]
- Use aseptic technique and appropriate anatomical or ultrasound localization. Ultrasound lowers LAST risk but does not eliminate intravascular injection or nerve injury.
- Use the lowest effective dose. Aspirate before incremental injections; negative aspiration is not proof of correct placement. Inject slowly, observe spread when using ultrasound and stop if placement is uncertain, injection is unexpectedly painful or resistance is abnormal. Bolus delivery drives both intravascular toxicity and infiltration pain.
- Use appropriate cardiovascular, respiratory and consciousness monitoring during and after injection. LAST can be delayed; the ASRA advisory recommends at least 30 minutes of close monitoring after potentially toxic doses, with 30–45 minutes specifically discussed for truncal blocks.
- Keep oxygen, resuscitation equipment, 20% lipid emulsion and the ASRA checklist immediately available at every block location.[2] An office block needs the same capacity to recognize and initially manage toxicity as its drug exposure warrants.[2][3]
Reducing injection pain in awake and office cases
These maneuvers apply to office urethral procedures, perineal infiltration and awake penile or scrotal work:
- Buffer lidocaine with sodium bicarbonate. Lidocaine with epinephrine is far more acidic than tissue (pH about 4, versus about 6 for plain lidocaine). Titration data support roughly 1 mL of 8.4% bicarbonate per 10 mL of 1% lidocaine with epinephrine; plain lidocaine needs less. Use a validated pharmacy preparation; bupivacaine and ropivacaine can precipitate at higher pH, so buffer them only under a specific protocol.[10]
- Warm the solution toward body temperature.
- Use small-gauge needles (27–30 G) and a slow infiltration rate.
- After the first puncture, inject through already-anesthetized tissue; the initial needle insertion is the most painful.
- Use vibration or cold skin cooling at the injection site, and a circumferential field block around a lesion rather than injecting into it.
- Explain the sequence and allow anesthetic onset before proceeding.
Warming and buffering follow a preparation protocol; neither replaces accurate placement or dose control.
Local Anesthetic Systemic Toxicity (LAST)
Neurologic symptoms may include circumoral numbness, metallic taste, tinnitus, agitation, altered consciousness or seizures. Cardiovascular toxicity (arrhythmia, hypotension, arrest) can occur without a preceding neurologic warning. Stop local anesthetic, summon help and use the ASRA LAST checklist.[2][11]
The posted 2020 checklist specifies:[11]
- Support the airway; prefer benzodiazepines for seizures. Consider lipid emulsion early.
- 20% lipid, under 70 kg: bolus approximately 1.5 mL/kg over 2–3 minutes, then 0.25 mL/kg/min (consider a pump under 40 kg). Over 70 kg: approximately 100 mL over 2–3 minutes, then approximately 250 mL over 15–20 minutes.[11]
- If unstable, repeat the bolus and double the infusion. Continue infusion for more than 15 minutes after hemodynamic stability; maximum lipid dose 12 mL/kg.[11]
- Resuscitation differs from standard ACLS: use smaller epinephrine doses, starting below 1 microgram/kg; avoid vasopressin, beta-blockers, calcium-channel blockers and local-anesthetic antiarrhythmics. Consider extracorporeal support for refractory collapse; prolonged resuscitation may be needed.
- Observe at least 2 hours after seizure or 4–6 hours after cardiovascular instability, with further care determined after cardiac arrest.
Fascial Plane Blocks for Abdominal and Pelvic Reconstruction
Transversus Abdominis Plane (TAP) Block
The target is the plane between internal oblique and transversus abdominis, which carries the T10–L1 anterior branches. Lateral and subcostal approaches cover different portions of the abdominal wall; select the approach to the actual incision and extraction site. TAP primarily addresses somatic abdominal-wall pain (skin, muscle, parietal peritoneum of the incision) and does not provide reliable visceral analgesia.[1][12]
Reconstructive uses: open ileal conduit or continent reservoir, ureteral reconstruction (ureteroureterostomy, Boari flap, ileal ureter), enterocystoplasty and other lower-abdominal incisions, Pfannenstiel incisions, and combined abdominoperineal urethroplasty. Its effect may fade sooner than surgeon-administered wound infiltration in some studies, and large-volume ropivacaine TAP blocks can produce high plasma concentrations, so count the mass injected.[6]
Quadratus Lumborum (QL) Block
Specify the approach: anterior (transmuscular) QL targets the QL–psoas interface; posterior QL lies behind the muscle; lateral QL is at its lateral fascial border. These are distinct injections. QL spread and effect vary; reliable visceral coverage and categorical superiority to TAP are not established.[1][12] It is chosen when coverage cephalad to a TAP block is wanted: robotic ureteral reimplantation, pyeloplasty, augmentation, and flank or subcostal incisions.
Erector Spinae Plane (ESP) Block
The target is deep to the erector spinae muscles at the transverse process. Select the vertebral level for the surgical territory (T7–T9 in the urologic series below). Paravertebral spread and visceral analgesia are variable; a technically successful ESP block does not replace a rescue plan.[1][12]
Rectus Sheath Block
The target is between rectus abdominis and its posterior sheath where that sheath is present. It is an option for midline somatic incisional pain (augmentation, Mitrofanoff, ileal ureter) and umbilical or periumbilical port sites. Coverage depends on injection level and spread; it does not cover all lateral ports or visceral pain.[1][12]
What the comparative evidence supports
The ASA 2026 guideline's recommendations concern pain and/or opioid reduction in the first 24 hours, with moderate evidence for adult abdominal surgery. The ASA subgroup found modest pain reductions and lower opioid use in minimally invasive nephrectomy/urology, with no block ranking for reconstruction.[1]
Micali et al. (2024) studied 190 patients prospectively: 97 received bilateral ESP (20 mL of 0.375% ropivacaine plus dexmedetomidine 0.5 mcg/kg per side at T7–T9) and 93 received bilateral TAP (20 mL of 0.375% or 0.25% ropivacaine). Allocation reflected clinician choice, and the regimens differed: ESP included dexmedetomidine, whereas TAP included perioperative morphine. Lower pain and rescue use in the ESP group are observational associations. There was no QL group.[13]
A randomized trial of 110 patients after laparoscopic nephrectomy found lower 24-hour opioid consumption with ESP than QL (median 13 versus 25 µg sufentanil equivalents; median difference −8 µg, 95% CI −15 to 0, P = 0.041) and about one point lower pain scores.[14]
Peripheral Blocks Specific to Urology
Pudendal Nerve Block
The pudendal nerve (S2–S4) supplies the perineum, penis or clitoris, urethral sphincter and much of the perineal skin. A pudendal block may be useful for the perineal component of urethroplasty, perineal urethrostomy, AUS placement, rectourethral or other fistula repair and vaginal surgery, with additional anesthesia for deeper pelvic work, abdominal incisions or flap donor sites. It is not a reliable block of all bladder, trigonal or upper-vaginal visceral sensation.
Ischial-spine approaches and Alcock-canal approaches are distinct. Options include a transvaginal or transperineal injection at the ischial spine (through the sacrospinous ligament), nerve-stimulator guidance, ultrasound guidance at the Alcock canal, and fluoroscopic transgluteal injection for chronic pudendal neuralgia. Specify the target and guidance method rather than applying one needle direction or volume to all.[15] Bendtsen's report of the Alcock-canal technique involved only three patients and two cadavers and used a small volume; it established feasibility.[15]
In a single-center randomized trial of 60 men undergoing primary anastomotic posterior urethroplasty, combined bilateral pudendal and spermatic-cord blocks yielded mean time from surgery completion to pain onset of 653.6 versus 540.4 minutes with caudal block; 24-hour rescue-analgesic use did not differ significantly.[42]
Catheter-related bladder discomfort is one supported use. In 175 men having TURP or TURBT under general anesthesia, bilateral nerve-stimulator-guided pudendal block lowered CRBD incidence through 12 hours (52% versus 69% at 12 h), with less moderate-to-severe CRBD (6% versus 16% at 12 h).[16]
Urogynecology: trials disagree
Khalil et al. randomized 57 women aged 20–53 with stage I–II prolapse undergoing anterior or posterior colporrhaphy to nerve-stimulator-guided pudendal block (0.7 mL/kg of the anesthetic mixture at four sites) or general anesthesia. Pain and analgesic consumption were lower with block; return to normal daily activity took 3.6 versus 12.2 days, and satisfaction was 71.4% versus 27.8%.[17] The comparator was general anesthesia alone rather than a general anesthetic with a sham block.[17]
Two later trials add a block to a general anesthetic and are negative or marginal. In a sham-controlled trial of 71 women (mostly prolapse repair; 9 mL of 0.25% bupivacaine plus triamcinolone), pain scores were equivalent in the PACU and on day 4, day-1 pain was lower but below the prespecified 20-mm clinical threshold, and opioid use did not differ significantly.[18] In a 44-patient trial of transvaginal multicompartment repair within an ERAS pathway (20 mL total of 0.5% bupivacaine, 10 mL per side, versus usual care), 24-hour opioid use did not differ between usual care (median 8 MME) and pudendal block (median 6.7 MME), nor did return to activity.[19]
For major vulvar and/or related groin surgery, surgeon-administered ilioinguinal plus pudendal blocks used local anesthetic up to 2 mg/kg divided over up to four sites (0.25% levobupivacaine in 17 women, 0.5% bupivacaine in one); pain scores were 0–3 in 17 of 18 women on days 0–1 and 15 of 18 on days 2–5, in an uncontrolled observational series.[20]
Dorsal Penile Nerve Block
The paired dorsal penile nerves (pudendal branches) run deep to Buck fascia on either side of the dorsal vein and supply dorsal and ventral penile skin. Approaches include the traditional two-puncture subpubic technique, ultrasound guidance at the compartment just deep to Buck fascia, and an ultrasound-guided perineal approach. Avoid the adjacent vessels and corpora, and assess the ventral or frenular territory, which may need supplementary infiltration. Indications include hypospadias repair and revision, circumcision, paraphimosis reduction and penile shaft procedures such as grafting or scar revision.[21]
For priapism procedures, AUA/SMSNA 2022 advises considering a penile block before phenylephrine injections and includes a block before aspiration and irrigation in its sample protocol . It does not specify a preferred penile-block technique.[36]
In 104 children having circumcision, an ultrasound-guided perineal dorsal penile block with 3–5 mL of ropivacaine 0.25% plus lidocaine 0.8% delayed first analgesic request compared with a caudal block and caused less leg numbness.[22] A 33-child hypospadias RCT reported first analgesic requirement at approximately 32 versus 21 hours for ultrasound-guided dorsal penile versus nerve-stimulator-guided pudendal block.[23] In an early-terminated 16-center randomized trial of 210 children aged 2 years or younger undergoing primary distal or midshaft hypospadias repair, 161 had 3-month fistula follow-up: 7/79 after caudal versus 6/82 after penile block; the caudal group received fewer intraoperative and rescue opioids.[44]
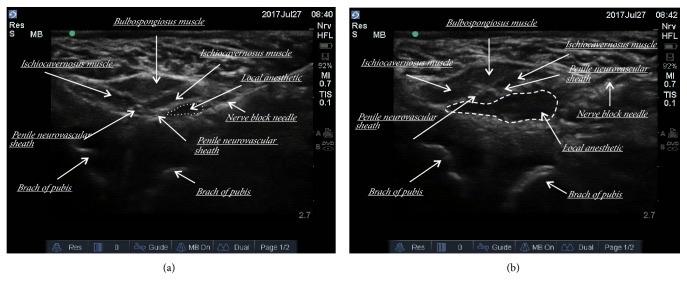
Ultrasound-guided dorsal penile nerve block by the perineal approach. (a) The penile neurovascular sheath before a complete injection. (b) The sheath after a complete block; the injected local anesthetic appears as a hypoechoic area that first fills one side of the neurovascular sheath and then spreads to the opposite side. From Wang X, et al. Biomed Res Int. 2019;2019:6875756, Figure 2 (CC BY).[22]
Penile Ring Block
Circumferential subcutaneous infiltration at the base of the shaft blocks the small cutaneous branches from both the dorsal nerves and the perineal branches of the pudendal. It can supplement or, for simple skin procedures such as circumcision, replace a dorsal block, and is quicker to perform in the awake office setting. Use a small needle, inject slowly with frequent aspiration and avoid a large-volume, high-pressure injection in tissue with uncertain perfusion.
Plain local anesthetic is standard. Do not add epinephrine or another vasoconstrictor without a specific reason: current bupivacaine/epinephrine labeling calls for carefully restricted quantities in the penis and warns of ischemic injury or necrosis. Assess the exact product and tissue perfusion before use.[3]
An alternative urethra-sparing path has been described: with the needle kept above Buck's fascia, advance from the 11 o'clock to the 5 o'clock position while injecting on withdrawal, then repeat from 11 o'clock to 7 o'clock, giving a 270-degree block. This is an attributed technique option; no comparative or outcome data establish that it reduces urethral injury relative to a standard circumferential pass.[34]
Spermatic Cord Block
Cord and surrounding-tissue blockade is widely used for office and operating-room scrotal-content procedures: vasectomy and vasovasostomy, hydrocelectomy, spermatocelectomy, microsurgical varicocelectomy and microTESE (as an adjunct to sedation or general anesthesia), scrotal biopsy and microsurgical cord denervation. The genital branch of the genitofemoral nerve travels with the cord; the ilioinguinal nerve runs nearby in the inguinal canal, outside the cord's internal contents. Skin innervation is broader, so a cord block may need separate cutaneous or ilioinguinal coverage.[24]
Technique: identify the cord at the external ring or over the pubic tubercle, stabilize it between thumb and index finger, identify the vas and vessels, and place anesthetic around the intended neural tissue rather than into those structures. For a cord block near the pubic tubercle, the Canadian Urological Association best practice report describes 10–20 mL of local anesthetic without epinephrine; count the total milligrams with any skin infiltration.[40] Allow several minutes for onset and supplement with skin infiltration at the incision.
An alternative position, high in the spermatic cord within the scrotum, has also been described: stabilize the cord between thumb and index finger, pass a 27-gauge needle across it, aspirate, and inject while withdrawing, adding separate scrotal-skin infiltration when needed. The authors describe no more than 5–10 mL per cord at this site, a separate practice figure from the 10–20 mL convention above.[35]
For isolated unilateral chronic scrotal content pain, AUA 2025 permits diagnostic cord and/or ilioinguinal block as expert opinion.[25]
Ilioinguinal / Iliohypogastric Block
The ilioinguinal (L1) and iliohypogastric (T12–L1) nerves supply parts of the lower abdominal wall and inguinal and genital skin. Ultrasound-guided targeting is usually in the internal oblique–transversus abdominis plane, not between external and internal oblique. It can complement orchiopexy, hydrocelectomy, inguinal or Pfannenstiel incisional analgesia and, with pudendal block, major vulvar surgery; it does not anesthetize the entire testis, scrotum or vulva.[12][20][24]
Periurethral Block (Female)
This is local infiltration, used with topical anesthesia in selected office urethral procedures, particularly bulking, and sometimes for cystoscopy in women who do not tolerate topical anesthesia alone, urethral dilation or calibration, transurethral botulinum toxin injection and small periurethral procedures. For Bulkamid urethral bulking, the manufacturer's procedure guide describes intraurethral anesthetic gel, then 5–10 mL of 0.5–1% lidocaine injected bilaterally beside the urethra at 3 and 9 o'clock, 5–10 minutes before the procedure.[38] Use a small-gauge needle, aspirate before each injection, and allow onset. Choose preparation, placement and monitoring from the actual procedure and device instructions, and count topical and injected anesthetic together.
The bulking material is not a local anesthetic. Bulkamid is polyacrylamide hydrogel and water; analgesia is a separate intervention. The FDA-hosted physician instructions describe separate anesthetic preparation and prohibit mixing the hydrogel with other substances. Routine cystoscopy, intradetrusor Botox and urethral procedures have different pain sources and do not all require a periurethral block.[26]
Uterosacral / Cervical and Paracervical Blocks
Local injection around the cervix or uterosacral region is a separate technique from pudendal blockade. In Barba's 40-woman nonrandomized pilot of vaginal hysterectomy and pelvic floor repair through uterosacral suspension, patients chose whether to receive a pre-emptive block of ropivacaine plus clonidine at 2, 4, 8 and 10 o'clock of the cervix after induction of general or spinal anesthesia. Pain was lower at 1 hour and at 24 hours with cough, but rescue-opioid use and hospital stay did not differ significantly.[27]
Conventional bupivacaine HCl and EXPAREL are contraindicated for obstetrical paracervical block anesthesia because bupivacaine HCl use in that setting has caused fetal bradycardia and death.[3][28]
Liposomal Bupivacaine (Exparel) — the Evidence
The current label distinguishes local infiltration (adults up to 266 mg) from its established adult regional indications: interscalene and popliteal sciatic blocks use 133 mg of EXPAREL, while adductor canal block uses 133 mg of EXPAREL admixed with 50 mg of 0.5% bupivacaine HCl (20 mL total).[28] Pudendal, penile, spermatic-cord and TAP regional use are not established labeled indications. Do not transfer an approved limb-block dose to a bilateral GU block or promise 72 hours of analgesia.[28]
Avoid additional local anesthetic within 96 hours after EXPAREL, while following the label's specific permitted concurrent bupivacaine regimens (bupivacaine HCl not above a 1:2 milligram ratio to EXPAREL when admixed). It must not be admixed with lidocaine or other non-bupivacaine local anesthetics; administration after local lidocaine requires at least 20 minutes. Detailed dosing remains on the pharmacology hub.[28]
Comparative evidence is consistently modest:
- Ilfeld 2021 reviewed all 76 randomized trials available. Of 36 trials of infiltrated liposomal versus unencapsulated bupivacaine or ropivacaine, 4 (11%) reported a clinically relevant, statistically significant improvement in the primary outcome favoring liposomal bupivacaine. Of 12 trials, 11 (92%) suggested a peripheral nerve block with plain bupivacaine outperformed infiltrated liposomal bupivacaine. Trials at high risk of bias reported statistically significant primary-outcome superiority of liposomal bupivacaine in 84% (16 of 19), versus 14% (4 of 28) at low risk.[29]
- Perineural meta-analysis (Hussain 2021): 9 trials, 619 patients. Pooled 24–72 h pain area under the curve improved by 1.0 cm·h (below the 2.0 cm·h minimal important difference), and the difference became nonsignificant (0.7 cm·h, P = 0.100) after excluding one industry-sponsored trial. No difference in opioid use, time to first analgesic request, satisfaction, hospital stay or functional recovery.[30]
- Fascial plane blocks (Hussain 2024): 16 trials, 1,287 patients. The meta-analysis did not detect a statistically significant difference in 24–72-hour resting-pain area under the curve (SMD −0.21, 95% CI −0.43 to 0.01, P = 0.058), including in subgroup analysis by mixing plain bupivacaine; day-2 and day-3 secondary outcomes also did not differ statistically.[31]
- Peripheral nerve and field blocks (Nguyen 2023): 27 trials, 2,122 patients. Rest pain was 0.9 points lower at 24 h and 0.7 points lower at 48–72 h; there was no difference in morphine use at any time. The authors graded the evidence as moderate.[32]
- A positive signal: in an 80-patient supraclavicular block trial, adding liposomal bupivacaine to plain bupivacaine lowered 48-hour rest pain area under the curve (0.6 versus 1.4), but daily pain differences after day 1 were not significant.[33]
In the CLEVELAND randomized trial’s modified intention-to-treat cohort of 261 patients having major abdominal surgery, four-quadrant TAP blocks with liposomal plus plain bupivacaine, plain bupivacaine, or saline yielded similar opioid use at 0–24 and 24–48 hours and similar pain scores.[45]
Practical stance for GU reconstruction: standard bupivacaine or ropivacaine, with or without dexamethasone, is the default for peripheral and fascial plane blocks. A pain-score gain of about 1 point with no opioid-use difference rarely justifies the substantial cost premium, and for analgesia beyond 24 hours a continuous catheter with standard agent is the established alternative.
Practical Block Selection by Reconstructive / Functional Operation
| Surgical territory | Options | Coverage to confirm |
|---|---|---|
| Abdominal reconstruction: augmentation, channel creation, ureteral repair/diversion | Incision-matched TAP, rectus sheath, QL or ESP; selected neuraxial techniques | Midline versus lateral/extraction-site pain, visceral pain, cumulative local anesthetic |
| Pfannenstiel incision (autologous sling, simple prostatectomy, retropubic work) | TAP or ilioinguinal/iliohypogastric | Lateral extent of the incision; visceral pain not covered |
| Perineal urethroplasty, AUS or fistula repair | Pudendal plus local infiltration as appropriate | Deep dissection, abdominal component and gracilis/other donor site |
| Penile surgery, including prosthesis and plaque surgery | Dorsal penile and/or ring block | Ventral/frenular, proximal and deeper operative territories; perfusion |
| Scrotal-content or inguinal surgery | Cord, skin infiltration and/or ilioinguinal/iliohypogastric block | Cutaneous versus cord/testicular pain and expected traction |
| Vaginal or vulvar repair | Procedure-specific pudendal, local or other regional technique; pre-emptive uterosacral/cervical block | Upper vaginal/visceral and anterior vulvar territories; trial evidence for added benefit is mixed |
| Office urethral bulking | Topical anesthesia with procedure-specific local infiltration | Patient comfort and separate device/anesthetic preparation |
Confirm block effect before relying on it, retain rescue analgesia, and give instructions about residual numbness, weakness, delayed toxicity and whom to contact after discharge.
Key Takeaways
- Drug mass influences onset, success and duration in studied peripheral blocks; volume, concentration and deposition also affect block performance, so count every source of local anesthetic toward the total milligram dose.[6]
- Aspirate, inject slowly, monitor, and keep lipid emulsion available at every block location. LAST lipid dosing is 1.5 mL/kg over 2–3 minutes then 0.25 mL/kg/min (under 70 kg).[11]
- Buffer lidocaine (about 1 mL of 8.4% bicarbonate per 10 mL of 1% lidocaine with epinephrine) for awake injections; it is the simplest injection-pain lever.[10]
- Perineural dexamethasone extends bupivacaine blocks by roughly 4 hours in pooled data; the ropivacaine effect is not established and the route is off-label.
- No fascial plane block has been shown to be best for reconstruction. ESP has shown lower opioid use than QL in one nephrectomy RCT and than TAP in an observational urologic series.
- Pudendal block suits perineal urethroplasty, AUS and fistula work as an adjunct; in vaginal prolapse surgery the evidence is mixed, favorable against general anesthesia alone and neutral when added to an ERAS general anesthetic.
- Dorsal penile block (ultrasound-guided where available) and ring block cover penile skin surgery; avoid epinephrine in penile blocks unless there is a specific reason.
- Spermatic cord block covers scrotal-content surgery; a diagnostic cord block is permitted by AUA 2025 for isolated chronic scrotal content pain.
- Periurethral infiltration is the office companion to female bulking and other urethral procedures; the bulking agent is not an anesthetic.
- Liposomal bupivacaine has not shown a reliable clinically important pain advantage over plain local anesthetic for abdominal fascial-plane blocks. A 2026 TAP meta-analysis found 2.4 fewer MME in the first 24 hours, with no detected difference in pain through 48 hours, length of stay or opioid-related adverse effects. Pudendal, penile, cord and TAP blocks are not established labeled regional indications.[28][31][37]
References
1. Joshi GP, Mariano E, Elkassabany NM, et al. "2026 American Society of Anesthesiologists Practice Guideline on Perioperative Pain Management Using Local and Regional Analgesia for Cardiothoracic Surgeries, Mastectomy, and Abdominal Surgeries." Anesthesiology. 2026;144:19–43. doi:10.1097/ALN.0000000000005790.
2. Neal JM, Barrington MJ, Fettiplace MR, et al. "The Third American Society of Regional Anesthesia and Pain Medicine Practice Advisory on Local Anesthetic Systemic Toxicity: Executive Summary 2017." Reg Anesth Pain Med. 2018;43:113–123. doi:10.1097/AAP.0000000000000720.
3. Pfizer. Bupivacaine hydrochloride with/without epinephrine (Marcaine): prescribing information. Current label; DailyMed. Accessed September 25, 2026.
4. Xylocaine (lidocaine hydrochloride and epinephrine) injection: prescribing information, "Maximum recommended dosages." DailyMed. Accessed September 25, 2026.
5. Fresenius Kabi. Naropin (ropivacaine hydrochloride) injection: prescribing information. DailyMed. Accessed September 25, 2026.
6. Eng HC, Ghosh SM, Chin KJ. "Practical use of local anesthetics in regional anesthesia." Curr Opin Anaesthesiol. 2014;27:382–387. doi:10.1097/ACO.0000000000000091.
7. Cuvillon P, Nouvellon E, Ripart J, et al. "A comparison of the pharmacodynamics and pharmacokinetics of bupivacaine, ropivacaine (with epinephrine) and their equal volume mixtures with lidocaine used for femoral and sciatic nerve blocks: a double-blind randomized study." Anesth Analg. 2009;108:641–649. doi:10.1213/ane.0b013e31819237f8.
8. Baeriswyl M, Kirkham KR, Jacot-Guillarmod A, Albrecht E. "Efficacy of perineural vs systemic dexamethasone to prolong analgesia after peripheral nerve block: a systematic review and meta-analysis." Br J Anaesth. 2017;119:183–191. doi:10.1093/bja/aex191.
9. Kopp SL, Vandermeulen E, McBane RD, Perlas A, Leffert L, Horlocker T. "Regional anesthesia in the patient receiving antithrombotic or thrombolytic therapy: American Society of Regional Anesthesia and Pain Medicine Evidence-Based Guidelines (fifth edition)." Reg Anesth Pain Med. Published online January 29, 2025. doi:10.1136/rapm-2024-105766.
10. Frank SG, Lalonde DH. "How acidic is the lidocaine we are injecting, and how much bicarbonate should we add?" Can J Plast Surg. 2012;20:71–73. doi:10.1177/229255031202000207.
11. ASRA Pain Medicine. Local Anesthetic Systemic Toxicity Checklist. Version 2020. Checklist.
12. El-Boghdadly K, Wolmarans M, Stengel AD, et al. "Standardizing nomenclature in regional anesthesia: an ASRA-ESRA Delphi consensus study of abdominal wall, paraspinal, and chest wall blocks." Reg Anesth Pain Med. 2021;46:571–580. doi:10.1136/rapm-2020-102451.
13. Micali M, Cucciolini G, Bertoni G, et al. "Analgesic Strategies for Urologic Videolaparoscopic or Robotic Surgery in the Context of an Enhanced Recovery after Surgery Protocol: A Prospective Study Comparing Erector Spinae Plane Block versus Transversus Abdominis Plane Block." J Clin Med. 2024;13:383. doi:10.3390/jcm13020383.
14. Zhang Z, Kong H, Li Y, et al. "Erector spinae plane block versus quadratus lumborum block for postoperative analgesia after laparoscopic nephrectomy: A randomized controlled trial." J Clin Anesth. 2024;96:111466. doi:10.1016/j.jclinane.2024.111466.
15. Bendtsen TF, Parras T, Moriggl B, et al. "Ultrasound-Guided Pudendal Nerve Block at the Entrance of the Pudendal (Alcock) Canal: Description of Anatomy and Clinical Technique." Reg Anesth Pain Med. 2016;41:140–145. doi:10.1097/AAP.0000000000000355.
16. Xiaoqiang L, Xuerong Z, Juan L, et al. "Efficacy of pudendal nerve block for alleviation of catheter-related bladder discomfort in male patients undergoing lower urinary tract surgeries: A randomized, controlled, double-blind trial." Medicine (Baltimore). 2017;96:e8932. doi:10.1097/MD.0000000000008932.
17. Khalil I, Itani SE, Naja Z, et al. "Nerve stimulator-guided pudendal nerve block vs general anesthesia for postoperative pain management after anterior and posterior vaginal wall repair: a prospective randomized trial." J Clin Anesth. 2016;34:668–675. doi:10.1016/j.jclinane.2016.07.024.
18. Slopnick EA, Sears SB, Chapman GC, et al. "Pudendal Nerve Block Analgesia at the Time of Vaginal Surgery: A Randomized, Double-Blinded, Sham-Controlled Trial." Urogynecology (Phila). 2023;29:827–835. doi:10.1097/SPV.0000000000001351.
19. Torosis M, Fullerton M, Kaefer D, et al. "Pudendal Block at the Time of Transvaginal Prolapse Repair: A Randomized Controlled Trial." Urogynecology (Phila). 2024;30:706–713. doi:10.1097/SPV.0000000000001448.
20. Shahabuddin Y, Gleeson N, Maguire PJ. "Surgeon-administered ilio-inguinal and pudendal nerve blocks for major vulval surgery: An observational study with visual analogue pain scoring." Eur J Obstet Gynecol Reprod Biol. 2022;268:87–91. doi:10.1016/j.ejogrb.2021.11.429.
21. Flores S, Herring AA. "Ultrasound-guided dorsal penile nerve block for ED paraphimosis reduction." Am J Emerg Med. 2015;33:863.e3–5. doi:10.1016/j.ajem.2014.12.041.
22. Wang X, Dong C, Beekoo D, et al. "Dorsal Penile Nerve Block via Perineal Approach, an Alternative to a Caudal Block for Pediatric Circumcision: A Randomized Controlled Trial." Biomed Res Int. 2019;2019:6875756. doi:10.1155/2019/6875756.
23. Aksu C, Akay MA, Şen MC, Gürkan Y. "Ultrasound-guided dorsal penile nerve block vs neurostimulator-guided pudendal nerve block in children undergoing hypospadias surgery: A prospective, randomized, double-blinded trial." Paediatr Anaesth. 2019;29:1046–1052. doi:10.1111/pan.13727.
24. USRA. Inguinal Canal Block. Anatomy and ultrasound chapter. Accessed September 12, 2026.
25. AUA. Diagnosis and Management of Male Chronic Pelvic Pain. 2025; statement 12. Guideline.
26. FDA. Bulkamid Urethral Bulking System. PMA P170023, 2020. Device composition; physician instructions, preparation and mixing precautions.
27. Barba M, Cola A, De Vicari D, et al. "Enhanced recovery after surgery (ERAS) in prolapse repair: A prospective study on pre-emptive uterosacral/cervical block." Int J Gynaecol Obstet. 2024;166:1240–1246. doi:10.1002/ijgo.15483.
28. Pacira. EXPAREL: prescribing information, label effective December 2025. DailyMed. Accessed September 25, 2026.
29. Ilfeld BM, Eisenach JC, Gabriel RA. "Clinical Effectiveness of Liposomal Bupivacaine Administered by Infiltration or Peripheral Nerve Block to Treat Postoperative Pain." Anesthesiology. 2021;134:283–344. doi:10.1097/ALN.0000000000003630.
30. Hussain N, Brull R, Sheehy B, et al. "Perineural Liposomal Bupivacaine Is Not Superior to Nonliposomal Bupivacaine for Peripheral Nerve Block Analgesia." Anesthesiology. 2021;134:147–164. doi:10.1097/ALN.0000000000003651.
31. Hussain N, Speer J, Abdallah FW. "Analgesic Effectiveness of Liposomal Bupivacaine versus Plain Local Anesthetics for Abdominal Fascial Plane Blocks: A Systematic Review and Meta-analysis of Randomized Trials." Anesthesiology. 2024;140:906–919. doi:10.1097/ALN.0000000000004932.
32. Nguyen A, Grape S, Gobbetti M, Albrecht E. "The postoperative analgesic efficacy of liposomal bupivacaine versus long-acting local anaesthetics for peripheral nerve and field blocks: A systematic review and meta-analysis, with trial sequential analysis." Eur J Anaesthesiol. 2023;40:624–635. doi:10.1097/EJA.0000000000001833.
33. Chan TCW, Wong JSH, Wang F, et al. "Addition of Liposomal Bupivacaine to Standard Bupivacaine versus Standard Bupivacaine Alone in the Supraclavicular Brachial Plexus Block: A Randomized Controlled Trial." Anesthesiology. 2024;141:732–744. doi:10.1097/ALN.0000000000005035.
34. Mulhall JP, Jenkins LC. Penile Block. In: Mulhall JP, Jenkins LC, eds. Atlas of Office Based Andrology Procedures. Springer; 2017:19–26. doi:10.1007/978-3-319-42178-0_4
35. Mulhall JP, Jenkins LC. Spermatic Cord Block. In: Mulhall JP, Jenkins LC, eds. Atlas of Office Based Andrology Procedures. Springer; 2017:27–29. doi:10.1007/978-3-319-42178-0_5
36. AUA/SMSNA. The Diagnosis and Management of Priapism: an AUA/SMSNA Guideline (2022), Appendices A–B. Official guideline.
37. Liu S, Zhang C, Zhao J, Sun Q. "Comparison of liposomal bupivacaine and regular bupivacaine in the transversus abdominis plane for postoperative analgesia: an updated systematic review and meta-analysis." BMC Anesthesiol. 2026;26(1):340. doi:10.1186/s12871-026-03852-6
38. Axonics, Inc. Bulkamid Urethral Bulking System: Standard Operating Procedure. 2022; pp. 4, 12–13. PDF.
39. University of Iowa Carver College of Medicine. "Maximum Recommended Doses and Duration of Local Anesthetics." Iowa Head and Neck Protocols. 2017. Protocol.
40. Jarvi KA, Wu C, Nickel JC, Domes T, Grantmyre J, Zini A. "Canadian Urological Association best practice report on chronic scrotal pain." Can Urol Assoc J. 2018;12(6):161–172. doi:10.5489/cuaj.5238.
41. Zufferey PJ, Chaux R, Lachaud PA, Capdevila X, Lanoiselée J, Ollier E. "Dose-response relationships of intravenous and perineural dexamethasone as adjuvants to peripheral nerve blocks: a systematic review and model-based network meta-analysis." Br J Anaesth. 2024;132(5):1122–1132. doi:10.1016/j.bja.2023.12.021
42. Zhou Y, Gong WY, Zhang JY, et al. "The effect of combined pudendal nerve and spermatic cord block or caudal epidural block on postoperative analgesia after posterior urethroplasty: a randomized trial." BMC Anesthesiol. 2024;24:380. doi:10.1186/s12871-024-02744-x
43. Lin C, Guerrero AL, Jesin J, et al. "Comparing block characteristics of mixtures of short/intermediate- and long-acting local anesthetics for peripheral nerve block: a systematic review and meta-analysis." Braz J Anesthesiol. 2025;75(3):844617. doi:10.1016/j.bjane.2025.844617
44. Taenzer A, Mandler TN, Gagliardi A, et al. "Caudal versus penile block and urethrocutaneous fistula formation following hypospadias repair in children <2 years: a multicenter randomized clinical trial." Reg Anesth Pain Med. Published online September 11, 2026. doi:10.1136/rapm-2026-108027
45. Turan A, Ali Sakr Esa W, Brooker J, et al. "Liposomal bupivacaine, plain bupivacaine, and saline for transversus abdominis plane blocks: The CLEVELAND randomized trial." Anesthesiology. 2026;144(3):546–558. doi:10.1097/ALN.0000000000005869