Arista AH — Microporous Polysaccharide Hemospheres
Arista AH is a plant-starch-derived hemostatic powder composed of microporous polysaccharide hemospheres (MPH). The agent works by rapidly absorbing water and small molecules from blood, concentrating platelets, red cells, and clotting factors onto the matrix surface to accelerate natural clot formation.[1] Unlike Surgicel, Arista is typically absorbed in 24–48 hours by amylases (longer in neonates and infants).[1] The label indication is adjunctive hemostasis when pressure, ligature and other conventional measures are ineffective or impractical, in any surgical field except neurological and ophthalmic procedures.[1]
Mechanism
- Hydrophilic polysaccharide spheres exert an osmotic action that dehydrates and gels blood on contact[1]
- Water absorption concentrates platelets, red cells, and clotting factors against the matrix surface
- The concentrated environment accelerates fibrin formation
- Matrix is degraded by amylases, typically within 24–48 hours. BD reports absence on one-day imaging in a preclinical model.[1]
- Never inject or place in a blood vessel; the label warns of embolization and death.[1]
- It swells to maximum volume immediately on contact with blood or fluid (to about 5 times its original volume), so remove excess, particularly near bone foramina, confined bony spaces, the spinal cord, and the optic nerve and chiasm[1]
Like Surgicel, Arista is a passive matrix without thrombin. BD states that clotting begins on contact regardless of coagulation status. In a CryoLife/Artivion-sponsored randomized comparison involving 83 open renal operations, seven-minute hemostasis occurred at 40/40 Arista-treated urologic sites (10 partial-nephrectomy kidney surfaces and 30 radical-nephrectomy retroperitoneal beds) and 39/43 investigational-polysaccharide-treated sites; four Arista-treated urologic sites failed to maintain hemostasis at 12 minutes. Only oozing or slight bleeding after conventional control was eligible, significant coagulopathy and major hemorrhage were excluded, and the urologic subgroup was not powered for comparative efficacy.[5] Treat systemic coagulopathy separately.[1][5]
Distinctive Features vs. Other Matrices
| Feature | Arista AH | Surgicel | Gelfoam |
|---|---|---|---|
| Source | Plant starch (polysaccharide) | Plant cellulose | Porcine gelatin |
| Time to resorption | 24–48 hours | 7–14 days | 4–6 weeks |
| Foreign body granuloma risk | Not established | Reported | Reported |
| Form | Powder | Fabric / fibril / powder | Sponge / flowable |
| Acidic microenvironment | No (neutral) | Yes (low pH) | No (neutral) |
The manufacturer specifically warns against leaving Arista in the renal pelvis or ureters.[1]
GU Applications
- Diffuse renal-bed oozing after partial nephrectomy. Arista is an adjunct for residual oozing after conventional hemostasis. In a randomized trial of topical hemostatic agents as a class during robotic partial nephrectomy, mean postoperative day 1 hemoglobin decline was 1.8 g/dL with an agent (90 analyzed) versus 1.7 g/dL without one (88 analyzed; p = 0.5); the trial did not estimate an Arista-specific effect.[1][6]
- Pelvic sidewall after lymphadenectomy. In a randomized side-controlled RARP study, CT-detected lymphoceles at least 3 cm occurred on 5/88 Arista-treated and 9/88 untreated sides at 3 months (p = 0.248); none was symptomatic. A retrospective RARP comparison found longer operating time after MPH introduction (260 versus 229 minutes; p < 0.001), with similar recorded blood loss and complications.[3][4]
- Flap donor-bed oozing (gracilis, ALT, VRAM). In a randomized head-and-neck ALT donor-site trial after standard hemostasis, 62 patients were randomized and 55 analyzed (29 received 3 g MPH; 26 received no MPH). Drain output, seroma, hematoma, and infection did not differ significantly through at least six months of follow-up; active oozing control was not tested.[2]
- Buccal mucosa donor site. For residual oozing after conventional hemostasis, Arista use is an extrapolation from its general surgical indication; irrigate and aspirate excess powder after hemostasis.[1]
- Fournier debridement wounds are infected or contaminated fields. If Arista is used for residual scrotal or perineal oozing, BD advises caution; infection or abscess at the application site may require reoperation for drainage.[1]
- Urinary tract-adjacent placement. Use cautiously; rapid absorption does not justify leaving material in the collecting system. No comparative GU evidence cited here establishes superiority to Surgicel.
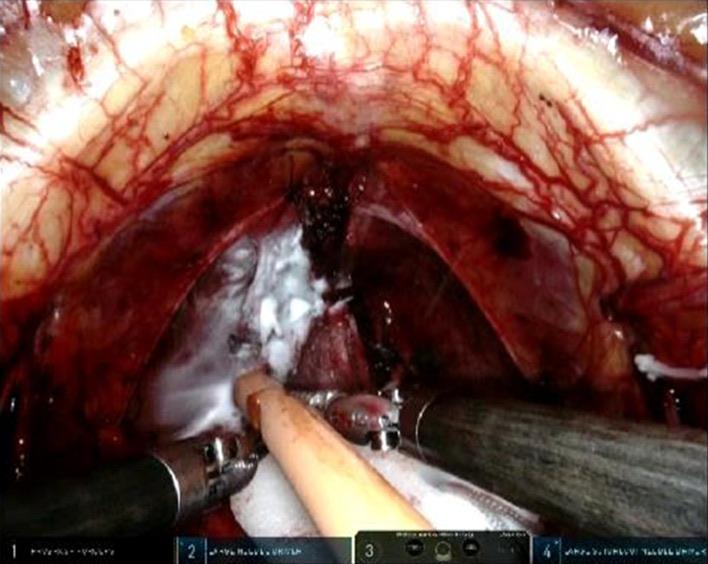
Microporous polysaccharide hemospheres sprayed on the prostatic bed, the dissection surface of the prostate and the transected edge after lymph node dissection during robot-assisted radical prostatectomy, following conventional hemostatic methods. From Nirei T, et al. Urol Res Pract. 2023;49(4):241-245, Figure 1 (CC BY).[3]
Application Technique
- Clear pooled blood. Blot, wipe, or suction the bleeding site, then apply dry Arista directly to active bleeding. Do not prewet the powder or site with saline or antibiotic solution before hemostasis.[1]
- Apply a liberal amount with the applicator tip close to the bleeding source, covering the wound; deep wounds may require deep application. Begin delivery as the applicator enters the wound to reduce tip occlusion. FlexiTip options are 14 cm and 38 cm (flexible XL or rigid XL-R).[1]
- Apply wound-appropriate direct pressure, using a nonadherent interface when needed
- Reassess. If bleeding or oozing continues, remove excess Arista and reapply. Avoid disrupting the formed clot.[1]
- Remove excess by irrigation and aspiration once hemostasis is achieved, while preserving the formed clot. Arista expands markedly on fluid contact; excess can compress nearby structures.[1] Available in 1, 3 and 5 g presentations.[1]
Advantages
- Rapid absorption
- Plant-derived. No animal or human blood-product source; suitable for patients with religious restrictions on animal products
- Plant-derived composition; no blanket guarantee against adverse tissue reactions
- Fast preparation. Powder ready to use, no reconstitution
- Low cost for routine oozing relative to thrombin-based flowable matrices (institution-dependent)
Limitations
- Arterial bleeding. Arista is labeled as an adjunct for capillary, venous, and arteriolar bleeding when conventional measures are ineffective or impractical; use definitive surgical control for a major arterial source.[1]
- Severe coagulopathy or heparinization. The manufacturer claims clotting starts regardless of coagulation status, but there are no independent GU data; correct coagulopathy in parallel
- Infection and special populations. Use with caution in infected or contaminated fields; safety and effectiveness have not been clinically evaluated in children or pregnant women. BD advises against applying more than 50 g in diabetic patients because of glucose load and against use to control postpartum bleeding or menorrhagia.[1]
- Powder can blow around in the surgical field; aim carefully, especially in laparoscopic cases where the pneumoperitoneum can disperse the powder
- Cell salvage. If Arista is used with an autologous blood-salvage circuit, follow the current IFU for cardiotomy-reservoir filtration, cell washing, and transfusion filtration.[1]
- Comparative performance. A 23-patient retrospective open partial-nephrectomy series found no significant difference in mean blood loss between Arista (12 patients; 250 mL) and FloSeal (11 patients; 227 mL; p = 0.68), but was too small to establish equivalence.[7] In a heparinized porcine liver model, FloSeal controlled bleeding more effectively at 5 and 10 minutes; outcomes in anticoagulated GU patients remain uncertain.[7][8]
See Also
References
1. BD. Arista AH indications, warnings and application instructions. Accessed September 24, 2026.
2. David AP, Zebolsky AL, Park AM, et al. Effect of microporous polysaccharide hemospheres on anterolateral thigh free flap donor site complications. Laryngoscope Investig Otolaryngol. 2022;7(2):380-387. doi:10.1002/lio2.770
3. Nirei T, Tatenuma T, Muraoka K, et al. Real-World Data on the Effectiveness of Microporous Polysaccharide Hemospheres for Allowing Even Novice Surgeons to Perform Robot-Assisted Radical Prostatectomy Safely. Urol Res Pract. 2023;49(4):241-245. doi:10.5152/tud.2023.22242
4. Gilbert DR, Angell J, Abaza R. "Evaluation of Absorbable Hemostatic Powder for Prevention of Lymphoceles Following Robotic Prostatectomy With Lymphadenectomy." Urology. 2016;98:75-80. doi:10.1016/j.urology.2016.06.071
5. House MG, Kim R, Tseng EE, et al. "Evaluating the safety and efficacy of a novel polysaccharide hemostatic system during surgery: A multicenter multispecialty prospective randomized controlled trial." Surg Open Sci. 2024;19:205-211. doi:10.1016/j.sopen.2024.04.009
6. Lazarovich A, Tremblay S, Nottingham C, et al. "Randomized, Prospective Evaluation of Hemostatic Agents in Robotic-Assisted Laparoscopic Partial Nephrectomy." J Urol. 2026;215(5):526-534. doi:10.1097/JU.0000000000004889
7. Palacios DA, McDonald M, Miyake M, Rosser CJ. "Pilot study comparing the two hemostatic agents in patients undergoing partial nephrectomy." BMC Res Notes. 2013;6:399. doi:10.1186/1756-0500-6-399
8. Lewis KM, Atlee H, Mannone A, Lin L, Goppelt A. "Efficacy of hemostatic matrix and microporous polysaccharide hemospheres." J Surg Res. 2015;193(2):825-830. doi:10.1016/j.jss.2014.08.026