Botulinum Toxin (Neuromodulation Adjunct)
OnabotulinumtoxinA (Botox) has FDA-labeled uses for adult OAB with urge urinary incontinence, urgency and frequency (100 U), and urinary incontinence due to adult neurogenic detrusor overactivity (NDO; 200 U), after inadequate response to or intolerance of an anticholinergic medication.[1] Pediatric NDO is labeled from age 5 with weight-based dosing (see below). Its off-label applications include IC/BPS, detrusor-sphincter dyssynergia (DSD), primary bladder-neck obstruction, pelvic-floor and pudendal myofascial pain, and chronic prostatitis / CPPS.[1][2] Of these agents, onabotulinumtoxinA has FDA-approved urologic indications; abobotulinumtoxinA and incobotulinumtoxinA have no urologic indications on their US labels, and their potency units are not interchangeable with those of onabotulinumtoxinA.[1][2][68][69]
Botulinum toxin is chemodenervation, not electrical nerve stimulation. This adjunct page explores its broader evidence and off-label uses; the storage/OAB pharmacology hub holds the core drug-class summary, and the intradetrusor injection page holds the procedural workflow.
For related classes, see Anticholinergics, β3-agonists, and Topical compounded agents.
Mechanism — why dual efferent + afferent matters
OnabotulinumtoxinA cleaves SNAP-25, blocking SNARE-complex-mediated vesicle fusion at presynaptic terminals. In the lower urinary tract, efferent blockade is established; afferent and anti-inflammatory effects may also contribute to urgency, frequency, and pain outcomes:[3][4]
| Pathway | Effect |
|---|---|
| Efferent (motor) | Blocks acetylcholine release at the detrusor neuromuscular junction; blocks ATP release from purinergic efferent nerves — reduces involuntary detrusor contraction |
| Afferent (sensory) | Markedly reduces urothelial ATP release and increases NO release; inhibits release of substance P, CGRP, and glutamate from sensory terminals; downregulates TRPV1 and P2X3 on C-fiber afferents; decreases urothelial NGF |
| Anti-inflammatory | Reduces neurogenic inflammation by suppressing neuropeptide release; modulates mast-cell degranulation |
Afferent and anti-inflammatory mechanisms may contribute, but their clinical contributions remain uncertain.[3][4] Investigational non-injection delivery aims to affect sensory pathways while reducing motor effects.[4]
Agents in this class
| Agent | FDA urologic indication | Urologic role |
|---|---|---|
| OnabotulinumtoxinA (Botox) | Adult OAB 100 U; adult NDO 200 U; pediatric NDO ≥5 y: 200 U if ≥34 kg, 6 U/kg if <34 kg | The only US-approved urologic formulation; the main clinical-outcome sections below focus on this agent[1][2] |
| AbobotulinumtoxinA (Dysport) | None | In two phase III trials (485 adults with SCI- or MS-related NDO using regular CIC), 600 U and 800 U each reduced weekly incontinence episodes versus placebo at six weeks.[70] US urologic use is off label, and its potency units are not interchangeable with onabotulinumtoxinA.[68] |
| IncobotulinumtoxinA (Xeomin) | None | In a single-blind idiopathic-OAB trial (59 analyzed), 100 U met the prespecified noninferiority margin versus 100 U onabotulinumtoxinA for UUI episode reduction at 2–6 weeks; daytime voids and patient-impression scores favored onabotulinumtoxinA.[71] US urologic use is off label, and potency units are not interchangeable.[69] |
| RimabotulinumtoxinB (Myobloc) | None | Serotype B; not used in urology |
FDA indication #1 — idiopathic OAB (100 U)
Guideline position
The AUA/SUFU OAB guideline (2024) says clinicians should offer sacral neuromodulation (SNM), percutaneous tibial nerve stimulation (PTNS) and/or intradetrusor onabotulinumtoxinA to patients with an inadequate response to, or intolerable side effects from, pharmacotherapy or behavioral therapy .[5] In shared decision-making, clinicians may offer these minimally invasive therapies without requiring prior behavioral, non-invasive or drug trials , and it is reasonable to go straight to toxin after β3-agonist failure or when a patient declines oral drugs.[5] PVR must be measured before injection ; the pivotal RCTs used PVR exclusion thresholds above 100–200 mL, so the panel advises caution above those thresholds.[5] Reassess about two weeks after the initial injection to assess symptom improvement and rule out retention, and check PVR if symptoms have not improved or have worsened (Statement 27).[5] A patient with an inadequate response to 100 U and minimal side effects may be offered 200 U off label, above the FDA-labeled 100-U OAB dose, with counseling about higher retention and UTI risk.[1][5] Repeat injections are typically needed every 3–12 months, and toxin should be offered cautiously when symptoms are mainly nocturnal.[5]
The EAU non-neurogenic female LUTS guideline (limited update March 2026) recommends bladder-wall injection of onabotulinumtoxinA 100 U for OAB or UUI refractory to conservative or drug treatment . It also recommends warning patients about limited duration, UTI and possible prolonged intermittent catheterization . It finds no difference between suburothelial and intradetrusor injection (level 1a), and it notes that other doses and other toxin brands are not licensed for OAB in Europe.[52]
Pivotal phase 3 — Nitti 2013
The registration trial (n = 557 adults with OAB / urge urinary incontinence refractory to antimuscarinics) remains the anchor data:[6]
- UI reduction: −2.65 episodes/day (onabotA 100 U) versus −0.87 (placebo); p < 0.001[6]
- Positive treatment benefit: 60.8% versus 29.2% (p < 0.001)[6]
- Complete continence: 22.9% versus 6.5%[6]
- All other OAB symptoms improved (p ≤ 0.05), and quality of life improved across multiple measures (p < 0.001)[6]
- Most frequent AE was UTI; dysuria and bacteriuria were also reported, and urinary retention occurred in 5.4% in this trial; retention and initiation of clean intermittent catheterization (CIC) are distinct outcomes[6]
The companion phase 3 trial (Chapple 2013, n = 548; 100 U as 20 injections of 0.5 mL) gave a similar result: −2.95 versus −1.03 incontinence episodes/day at week 12 and a positive treatment benefit in 62.8% versus 26.8%. CIC was started in 6.9% versus 0.7%, and mean PVR at week 2 was 46.9 mL versus 10.1 mL.[54]
Long-term efficacy — 3.5-year extension
The open-label extension (Nitti 2016, up to 6 treatments):[7]
- Consistent mean UI reductions of −3.1 to −3.8 episodes/day across repeat injections[7]
- Durable symptom and QoL improvement
- Median duration of effect 7.6 months
- De novo CIC 4.0% after first treatment, falling to 0.6–1.7% on subsequent treatments[7]
- No new safety signal in the extension cohort
Head-to-head vs combined oral pharmacotherapy (Hsieh 2025, RCT, 74 enrolled / 66 completed)
In women with urodynamically confirmed DO refractory to single pharmacotherapy:[8]
- In the 66 completers, onabotA 100 U and solifenacin 5 mg plus mirabegron 25 mg each had a median of 2.0 urgency episodes / 24 h at 12 weeks (mean difference −0.1 episodes / 24 h; p = 0.925), but the median reduction from baseline in urgency episodes was greater with onabotA (−3.0 versus −1.0 episodes / 24 h; p = 0.029).[8]
- Frequency, nocturia, UUI, and QoL improvements were similar
- Adverse events (dry mouth, constipation, blurred vision) were significantly more common with combination pharmacotherapy (all p < 0.05)
FDA indication #2 — neurogenic detrusor overactivity (200 U)
Guideline position
The AUA/SUFU NLUTD guideline (2021):[9]
- Statement 40 : in NLUTD patients with SCI or MS refractory to oral medications, clinicians should recommend onabotulinumtoxinA to improve storage parameters, decrease incontinence, and improve QoL[9]
- Statement 41 : in NLUTD patients other than SCI or MS who are refractory to oral medications, clinicians may offer onabotulinumtoxinA; evidence is more limited[9]
- Statement 42 : in NLUTD patients who void spontaneously, discuss the specific risk of retention and possible need for intermittent catheterization before choosing toxin[9]
The EAU Neuro-Urology guideline (limited update March 2026) also recommends detrusor injection of botulinum toxin A to reduce NDO when antimuscarinic therapy is ineffective (Strong; level 1a). It reports that repeated injections appear possible without loss of efficacy, up to 10 cycles in some series, and that 100 U may lower the catheterization rate in MS.[53] Post-treatment urodynamic studies may be needed to monitor bladder pressure in patients with NDO.[53]
Pivotal phase 3 — MS and SCI
The registration program (Sanford 2014 review) produced:[10]
- Significant reductions in UI episodes and MCC increases with matching detrusor-pressure reductions
- 200 U versus 300 U: in the two pivotal trials (Cruz 2011, n = 275; Ginsberg 2012, n = 416), both doses beat placebo with no clinically relevant efficacy or duration advantage for 300 U.[55][56] CIC initiation among patients not catheterizing at baseline rose with dose (Ginsberg: 10% placebo, 35% at 200 U, 42% at 300 U), so 200 U is the labeled adult dose.[55][56] The AUA/SUFU guideline likewise finds no efficacy difference between the doses and a dose-dependent increase in retention and CIC; in its pooled MS analysis of the pivotal trials, 31.4% (200 U) and 47.1% (300 U) started CIC versus 4.5% with placebo[9]
- Most common AEs: UTI and urinary retention
- Among noncatheterizing adults in the label’s pooled NDO trials, 30.6% required CIC after 200 U versus 6.7% with placebo; discuss the relevant population and possible prolonged catheterization.[1]
Low-dose 100 U for noncatheterizing MS — Tullman 2018
Placebo-controlled evidence supports symptom benefit from 100 U in noncatheterizing MS patients; 200 U remains the recommended adult NDO label dose:[11]
- UI reduction −3.3 episodes/day versus −1.1 placebo (p < 0.001)
- CIC initiation at any time during the first treatment cycle was 15.2% versus 2.6% with placebo; comparisons with the 200 U studies are indirect[11]
- A specialist may discuss the lower off-label dose with selected patients; it does not remove the need for a catheterization plan
4-year durability — Rovner 2016
Post hoc NDO analysis of 227 patients who completed four years of treatment:[12]
- Consistent UI reduction −3.4 to −3.9 episodes/day across all 4 years
- 86.6–94.1% achieved ≥50% UI reduction annually; 43.6–57.4% achieved 100% UI reduction each year[12]
- I-QOL improvements sustained year-to-year
- Median duration of effect ≥9.0 months (range 3.0–49.2); ≥26% experienced ≥12-month duration[12]
- No accumulating safety signal
Personalization (Wang 2026 narrative review)
Practical levers for NLUTD dosing:[13]
- Baseline voiding status. CIC status changes the practical consequences of retention but does not remove dose-related or systemic adverse effects
- Self-catheterization ability. The go / no-go criterion for most non-CIC patients
- Age. Older patients carry higher retention risk
- Reduced injection-site templates and trigone-inclusive techniques are active areas of investigation
ROSETTA — onabotulinumtoxinA vs sacral neuromodulation
Amundsen 2016 (JAMA, 386 randomized; 381 in the two assigned-treatment groups reported in the abstract; 364 in the primary analysis) compared SNM with 200 U, a dose above the labeled 100 U OAB dose:[14]
- UUI reduction: −3.9 (onabotA 200 U) versus −3.3 (SNM) episodes/day; mean difference 0.63 favoring onabotA (p = 0.01)[14]
- Complete UUI resolution: 20% versus 4% (p < 0.001)[14]
- At six months, UTI was 35% versus 11%; Botox-group CIC use was 8% at one month and 2% at six months.[14] SNM revision or removal occurred in 3%.[14]
Among 298 initial clinical responders in ROSETTA's 24-month extension, 260 had outcome data. With repeat 200-U injections allowed after six months, mean daily UUI episodes decreased by 3.88 with toxin versus 3.50 with SNM over 24 months, without a significant between-group difference; among women without recurrent UTI at baseline, recurrent UTI developed in 40/167 (24%) after toxin versus 16/154 (10.4%) after SNM. Among 189 women who received initial 200-U toxin, 45 (24%) needed CIC at least once over two years; after a second 200-U injection, 6 of 101 (6%) needed CIC. SNM revision and removal occurred in 3% and 9%, respectively.[65]
Longitudinal fluctuation (Hendrickson 2024). Over 6 months, 61% of onabotA versus 51% of SNM patients maintained persistent objective success. OnabotA had lower 30-day transition probability from success to failure (10% versus 14%; ratio 0.75). Roughly 2 in 5 women's symptoms fluctuated regardless of modality.[15]
2025 pooled review (Roman, 12 studies, 2,645 patients). In this meta-analysis, onabotA 100 U reduced UUI more than placebo at 3 months, while predominantly 200-U onabotA cohorts had greater UUI reduction than SNM at 6 months; ≥75% UUI reduction was more likely with onabotA in each separate comparison. Its abstract reports complete UUI resolution favoring SNM (p < 0.00001), opposite the six-month ROSETTA exploratory endpoint above. The pooled endpoint's contributing studies, time points and analysis require figure/table review before interpreting this as a treatment-selection rule. UTI was higher with BoNT-A.[16]
Crossover to SNM after failed BoNT-A (Yang 2020 meta-analysis) showed 58.5% success, no statistically significant difference from prior-BoNT-naive comparators (RR 0.96; 95% CI 0.72–1.26).[17]
Who does worse? ROSETTA secondary analysis (Richter 2017). Older women with multiple comorbidities and lower baseline QoL had lower response and satisfaction with onabotA versus SNM; higher BMI was associated with reduced odds of achieving ≥50% UUI reduction with either treatment (adjusted OR 0.82 per 5 BMI points).[18]
Dose, administration and label safeguards
Use the current US prescribing information for reconstitution and administration. Units cannot be converted between toxin products.[1]
| Population | Labeled bladder dose / dilution |
|---|---|
| Adult OAB | 100 U in 10 mL; 20 detrusor injections of 0.5 mL |
| Adult NDO | 200 U in 30 mL; 30 detrusor injections of 1 mL |
| Pediatric NDO, age ≥5 y | ≥34 kg: 200 U, reconstituted to 20 U/mL (10 mL total); <34 kg: 6 U/kg, first reconstituted to 20 U/mL in the vial, then drawn as a weight-based aliquot with preservative-free saline added to 10 mL final volume per label Table 2. Inject 0.5 mL at each of 20 detrusor sites. |
The cumulative adult limit is 400 U in three months across indications; pediatric cumulative exposure is limited to the lesser of 10 U/kg or 340 U. These are overall ceilings, not a reason to exceed a bladder-indication dose. Reinject when effect wanes, no sooner than 12 weeks; there is no mandatory six-month interval. In the OAB trials, median time until patients qualified for retreatment was about 24 weeks (169 days); in the 200 U NDO trials it was roughly 42–48 weeks.[1] Antibody formation is uncommon with bladder dosing: in the label's OAB program, neutralizing antibodies developed in 0 of 954 patients on 100 U and in 3 of 260 (1.2%) who later received at least one 150 U dose. The label notes that these figures are assay-dependent and not comparable across products.[1]
Inject the detrusor through a flexible or rigid cystoscope, avoiding the trigone as labeled, and fill the bladder enough to see the wall without overdistending it. AUA 2024 notes that trigone-sparing and trigone-including techniques are both effective, but the placebo-controlled pivotal trials used trigone-sparing injection.[1][5]
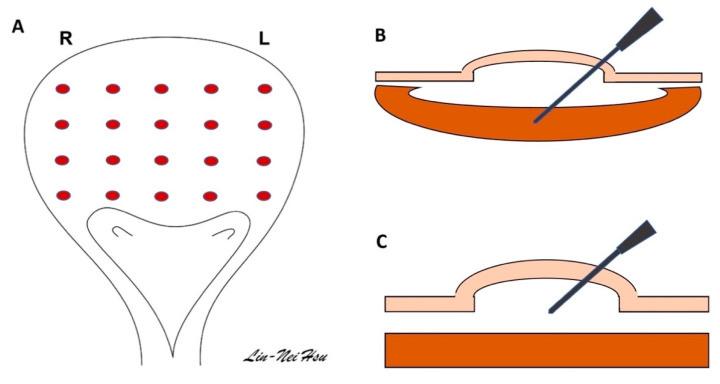
Bladder injection of onabotulinumtoxinA: (A) twenty injection sites mapped over the bladder wall; (B) intradetrusor method, with the needle placed directly into the trabeculation or detrusor muscle; (C) submucosal method, with solution retained in the submucosal layer to raise a bleb. From Hu JC, et al. Toxins (Basel). 2023;15(2):166, Figure 3 (CC BY).[50]
Do not inject with active UTI, relevant hypersensitivity or injection-site infection. For OAB, weigh likely benefit against UTI risk in patients with more than two UTIs in six months, chronic antibiotics for recurrent UTI, or multiple recurrent UTIs during treatment.[1] Intradetrusor use is contraindicated with retention or PVR >200 mL in a patient not routinely catheterizing. For adults, treat only patients willing and able to initiate catheterization if retention occurs. In those not routinely catheterizing, particularly patients with MS or diabetes, assess PVR within two weeks and periodically as appropriate through 12 weeks; depending on symptoms, begin catheterization when PVR exceeds 200 mL and continue until it falls below 200 mL.[1]
The adult bladder label specifies prophylactic antibiotics excluding aminoglycosides for 1–3 days before, on the day, and 1–3 days after treatment. A single preprocedure IV-dose alternative in the label applies to pediatric NDO under general anesthesia or conscious sedation, not to the adult template. A 2024 meta-analysis of studies searched through June 2022 found no direct regimen comparisons and favored antibiotics continued for 2–3 days after injection in idiopathic OAB; pooled UTI rates were 10% at 4 weeks and 15% at 12 weeks.[58] A 2026 randomized trial in 96 women undergoing office bladder toxin injection for uncomplicated OAB found one UTI in each arm after a single oral antibiotic dose or three postprocedure days; noninferiority was not established.[63] Reconcile stewardship pathways with local policy. The label advises stopping antiplatelet therapy at least 3 days before injection and managing anticoagulation appropriately to limit bleeding; coordinate any change with the prescriber.[1]
Eilber’s 2025 expert consensus and Rovner’s 2014 practical review describe variations in office anesthesia and injection distribution. Fewer sites, alternative dilution or trigonal inclusion should be identified as deviations from the labeled template, with their evidence limits.[19][20] A 64-patient retrospective cohort compared ultrasound-guided transabdominal with cystoscopic injection; its cystoscopic arm used Hengli botulinum toxin type A rather than onabotulinumtoxinA.[21] Nonsignificant efficacy comparisons do not establish route equivalence or justify routine substitution for labeled cystoscopic onabotulinumtoxinA delivery.[21][1]
The boxed warning covers distant spread, including generalized weakness, dysphagia and breathing difficulty, potentially hours to weeks after injection. Neuromuscular disease, respiratory compromise and interacting agents (including aminoglycosides or muscle relaxants) require particular attention.[1]
Adverse effects and predictors of response
| Adverse effect | OAB (100 U) | NDO (200 U) | Notes |
|---|---|---|---|
| UTI | 18% vs 6% placebo in the first 12 weeks (label) | 24% vs 17% in the first 12 weeks; 49% at any time before re-injection (200 U label trials) | Most common AE; in the separate ROSETTA 200 U trial, cumulative UTI was 35% vs 11% with sacral neuromodulation through 6 months; pooled RCT relative risk vs placebo across studied doses about 2.5 in idiopathic OAB and 1.5 in NDO.[1][14][57] The pivotal OAB trial counted bacteriuria plus leukocyturia regardless of symptoms.[6] |
| CIC for retention in label trials | 6.5% (36/552) versus 0.4% (2/542) placebo; median CIC duration 63 days among Botox recipients who started | 30.6% (33/108) versus 6.7% (7/104) placebo among patients not using CIC at baseline; median CIC duration 289 days among Botox recipients who started after 200 U[1] | — |
| Urinary retention / elevated PVR | Retention 6% (label AE table); residual volume not requiring catheterization 3% | Retention 17% within 12 weeks (200 U); expected in CIC-dependent patients | Check PVR within 2 weeks, and again as indicated through 12 weeks; pooled RCT relative risk of retention vs placebo across studied doses about 7 in OAB and 6.6 in NDO[1][57] |
| Dysuria, hematuria | Dysuria 9% versus 7% placebo in the first 12 weeks (label); hematuria not a ≥2% excess event | Hematuria 4% versus 3% placebo in the first 12 weeks; dysuria 4% at any time before re-injection (200 U label trials) | Procedure-related and usually transient[1][6] |
| Autonomic dysreflexia | N/A | 1.5% with 200 U versus 0.4% with placebo in adult NDO trials | Monitor during injection; autonomic dysreflexia may require prompt medical therapy.[9][1] In patients with SCI at or above T6, avoid bladder overfilling and monitor blood pressure during cystoscopy; if hypertension or dysreflexia symptoms occur, stop the procedure, decompress the bladder promptly, and sit the patient upright.[13] |
| Systemic weakness / dysphagia | Serious potential risk | Serious potential risk | See boxed warning; no safe-dose threshold eliminates it |
Predictors of poor response / CIC need — Abrar 2020 (n = 74)[22]
- Male sex. The only predictor of poor response (OR 5.45; 95% CI 1.83–16.47; p = 0.002) and also the strongest predictor of CIC need (OR 5.14; p = 0.013)[22]
- Lower Qmax predicted CIC need (OR 0.91 per mL/s; p = 0.023)[22]
- Prior hysterectomy in women predicted CIC (OR 4.55; p = 0.038)[22]
- CIC use predicted UTI (OR 5.26; p = 0.015)[22]
Factors associated with efficacy — Hsiao 2016 (89 treated; 80 assessed at 3 months)[23]
- Overall success 63.8%[23]
- Female sex was the only independent predictor of success (OR 3.75)[23]
- Low baseline OABSS and OAB-wet predicted better efficacy
- Low baseline voiding efficiency was the only predictor of a large PVR at 3 months (cutoff <87%, AUC 0.64, so a weak discriminator)[23]
Biomarker signal — Hanna 2026
Baseline urinary cytokine profiling suggests older women are less likely to respond; the authors propose pre-treatment cytokine panels as a future selection tool.[24]
Off-label urologic applications
Interstitial cystitis / bladder pain syndrome
AUA IC/BPS guideline (2022), Statement 20 (Option; Grade C): intradetrusor onabotulinumtoxinA may be administered after other treatments have failed; patients must accept the possibility of CIC.[25] The 2025 CUA guideline conditionally recommends intradetrusor onabotulinumtoxinA with or without hydrodistension for refractory IC/BPS (very low certainty).[67] Its pooled pain analysis of four RCTs (n = 213) found a mean 0.57-point lower pain score on a 0–10 scale versus control at 30–90 days (95% CI 1.33 lower to 0.20 higher; low certainty); most studies in the guideline combined toxin with hydrodistension.[67]
Intratrigonal injection (Pinto 2018, RCT, n = 19): 10 trigonal injections of 100 U reduced pain versus saline at week 12 (Δ −3.8 versus −1.6; p < 0.05).[26] O'Leary-Sant scores and quality of life also improved, while voiding frequency fell numerically.[26] Injection-site variability across studies (trigonal, lateral, posterior) and the scarcity of placebo-controlled trials remain the principal interpretive limits. In a small head-to-head RCT (Welch 2024, n = 47), intradetrusor onabotulinumtoxinA gave lower O'Leary-Sant scores than bladder instillations at 2 months, but the difference was gone by 6 to 9 months, and 8% of the toxin group needed CIC.[59] See Intravesical IC/BPS agents for the broader armamentarium.
Detrusor-sphincter dyssynergia
Goel 2020 systematic review and meta-analysis (11 studies, n = 353):[27]
- BoNT-A reduces PVR, mean detrusor pressure, DLPP, and urethral pressure in 60–78% of patients at 1 month[27]
- Most need reinjection at 4–9 months
- A 2013 expert evidence review assigned Level B using the AAN classification scale[28]
An early prospective series extended sphincter injection beyond spinal cord injury to 8 men and 13 women aged 34 to 74 with neurogenic DSD (12), pelvic-floor spasticity (8) or an acontractile detrusor in a patient with MS who wished to void by Valsalva (1). Botox 80 to 100 U was injected cystoscopically into the external sphincter at 3, 6, 9 and 12 o'clock. Before injection, 19 of 21 used indwelling or intermittent catheterization; afterward, all but 1 voided without catheterization. PVR fell by 71% and voiding pressure by an average of 38%, 14 (67%) reported significant subjective improvement, and no stress incontinence was reported over 3 to 16 months of follow-up, with up to 3 injections in some patients.[62]
The EAU Neuro-Urology guideline (2026) likewise describes sphincter injection as effective for DSD, but the effect lasts only a few months and needs repeat injections. It warns that reducing outlet resistance can cause urinary incontinence; discuss this tradeoff before injection.[53] For non-neurogenic detrusor underactivity in women, the EAU guideline weakly recommends external-sphincter injection before more invasive options if patients understand the evidence is low quality. Evidence for female bladder outlet obstruction rests on small case series of 100 U intrasphincteric injections, with no comparative trial.[52]
Concomitant detrusor plus external urethral sphincter injection (Huang 2022, open pre/post trial of 20 men with suprasacral SCI, detrusor overactivity and detrusor-sphincter dyssynergia): after 200 U detrusor and 100 U EUS BoNT-A, mean maximal detrusor and urethral pressures were lower and MCC higher at 12 weeks; UDI-6 scores improved at 4 and 12 weeks and IIQ-7 scores at 12 weeks, while PVR ratio and daily CIC frequency did not increase from baseline through 24 weeks.[29]
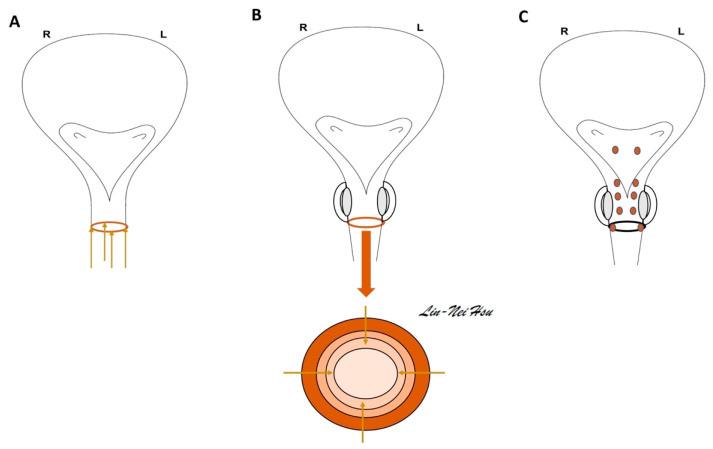
Urethral injection of onabotulinumtoxinA: (A) in female patients, periurethral injection from the meatal side at the 3, 6, 9 and 12 o'clock positions; (B) in male patients, cystoscopic injection of the external sphincter at the 3, 6, 9 and 12 o'clock positions, shown in cross-section below; (C) divided dosing across the trigone, superficial prostatic urethra and external sphincter for patients unresponsive to standard injection. From Hu JC, et al. Toxins (Basel). 2023;15(2):166, Figure 4 (CC BY).[50]
Predictors of sphincter-injection success (Lee 2025, n = 207). Overall success 33.8%; DSD grade 1 had 65.7% success versus grade 2 at 14.3% and grade 3 at 7.1%. Higher Qmax and lower PVR predicted response.[30]
Primary bladder-neck obstruction
Sacco 2014 (n = 30 men). Among 29 of 30 enrolled men who completed follow-up, transurethral 200 U into the bladder neck in medically refractory PBNO dropped IPSS from 21.9 to 7.8 at 2 months (p < 0.001), with partial persistence at 6 months (10.3) and waning by 9 months (16.6); this series had no comparator.[31]
Lee 2025 (n = 41). Bladder-neck BoNT-A for both neurogenic and non-neurogenic BND yielded 65.9% satisfactory outcomes at 6 months (26.8% successful and 39.0% improved); non-neurogenic BND had the highest satisfaction; among patients without detrusor acontractility, higher baseline BOOI was associated with failure in exploratory univariate analysis.[32]
BPH / LUTS — no overall IPSS advantage versus placebo in two phase 2 trials
Two large phase 2 RCTs are decisive:
- Marberger 2013 (380 randomized; 374 received injection): 100, 200, or 300 U intraprostatic onabotA: IPSS, Qmax, and prostate-volume improvements at week 12 were matched by placebo, with a large placebo effect from the injectable procedure itself[33]
- McVary 2014 (n = 315): 200 U versus placebo: IPSS −6.3 versus −5.6 (no difference) despite a sham-injection run-in designed to suppress placebo response[34]
Phase 3 was not pursued. OnabotulinumtoxinA should not be used for BPH / LUTS outside of study.[35][36]
Chronic prostatitis / CPPS and pelvic-floor myofascial pain
- Falahatkar 2015 (pilot RCT, 60 men). In the toxin arm, NIH-CPSI pain-subscale scores fell from baseline by 64.8%, 75.6% and 80.0% at one, three and six months; the saline arm showed no significant improvement.[37]
- Franco 2019 Cochrane. Intraprostatic BoNT-A may decrease prostatitis symptoms (MD −25.80; low-quality evidence, one trial). Pelvic-floor injection showed little to no effect (MD −2.60; low-quality)[38]
- Panunzio 2022 reviewed 18 studies (896 patients); its pooled analysis used 21 toxin-treated cohorts from 14 studies (447 patients) and found lower pain scores at last follow-up than baseline overall and in bladder, prostate and gynecologic subgroups amid varied designs and outcome measures.[39]
- EAU 2026. Botulinum toxin for chronic primary pelvic pain is off-label. EAU cites a systematic review of two RCTs and one non-randomized comparative study of intraprostatic injections (100–200 U) in primary prostate pain syndrome. Two of the three reported a significant pain reduction, but incomplete data and differences in dose and methods prevented a summary estimate. EAU rates a possible modest effect of pelvic-floor or prostate botulinum toxin injection in primary prostate pain syndrome at level 2b.[60] For primary bladder pain syndrome it gives a strong recommendation to consider submucosal bladder wall and trigonal injection plus hydrodistension when instillation therapies have failed (hydrodistension plus onabotulinumtoxinA superior to hydrodistension alone, level 1b)[60]
- AUA 2025. Evidence is too weak to recommend botulinum toxin A for CP/CPPS; pelvic-floor injection in men remains off-label and needs further study. This is an ungraded Future Directions discussion.[61]
Women (pelvic-floor injection for chronic pelvic pain):
-
Knapman 2024 systematic review and meta-analysis (five randomized trials, n = 329 women; mean follow-up six months) found no between-group difference in pain, dyspareunia, sexual function or vaginal manometry. Positive nonrandomized studies were heterogeneous and of low quality.[66]
-
Spruijt 2022 systematic review and meta-analysis (8 studies, n = 289 women). At 24–26 weeks, pooled within-treatment improvement was 15 points for non-menstrual pelvic pain and 13 points for dyspareunia on a 0–100 VAS. Pelvic-floor resting pressure and QoL also improved within the included studies.[40]
-
Dessie 2019 RCT (n = 59): 200 U trigger-point injection was not superior to saline on the primary endpoint (muscle pain on palpation); participants were more likely to report overall improvement at 4 weeks (p = 0.03); de novo constipation 10.1% across both arms, urinary incontinence 22% in the toxin arm[41]
-
Practical technique (Whitmore 2025): 200 U in 20 mL saline; inject pubococcygeus, iliococcygeus, and obturator internus using a pudendal nerve kit (1 cm needle depth); effect 3–6 months; pain reduction onset at about 6 weeks; AEs include constipation, incontinence, UTI, retention[42]
-
Expert consensus (Hufnagel 2026; modified Delphi, 15 first-round respondents): after pelvic-floor physical therapy for high-tone myofascial pain, palpate puborectalis, pubococcygeus, iliococcygeus and obturator internus to target bilateral transvaginal injections, typically 100–200 U total in divided 20–50-U muscle-group doses; reassess pain at 3–4 months.[73]
-
Overall read (Karp 2025). Numerous uncontrolled series are positive; the few RCTs are equivocal.[43]
Spruijt 2025 added a four-center placebo-controlled trial of 94 women, using 100 U plus pelvic-floor muscle therapy. Neither clinical primary outcome differed significantly: ≥33% pain reduction occurred in 33% versus 20% (p=0.19), and 17% in each arm reported marked improvement. Reduced resting muscle activity did not translate into established additional pain relief.[51]
See Chronic Pelvic Pain and IC/PBS.
Novel delivery — injection-free approaches
The dual-compartment mechanism (efferent and afferent) raises the question of whether BoNT-A can be delivered into the urothelium without a cystoscopic needle. Three approaches are in development.
Liposome-encapsulated BoNT-A (lipotoxin)
Liposomes adsorb to and fuse with urothelial cell membranes, delivering toxin across the urothelium without injection; the approach aims for sensory effects with less detrusor weakness.[44][45]
- Chuang 2014 multicenter RCT (n = 62). Intravesical 200 U lipo-BoNT-A reduced micturitions per 3 days (Δ −4.64 versus −0.19; p = 0.025) and urgency severity (p = 0.018) versus placebo at 4 weeks, with no retention signal. UUI effects inconclusive.[46]
- Kuo 2014 pilot RCT (n = 24). Frequency and urgency fell at one month in the 12 treated patients; no increase in PVR or UTI was detected, and SV2A/SNAP-25 protein assays did not differ significantly between responders and nonresponders.[47]
- Mechanism contrast (Liu 2015). In a small retrospective human biopsy comparison (16 injected, 11 given lipotoxin), cleaved SNAP-25 was detected in suburothelial tissue after injection but not after lipotoxin; urothelial P2X3 fell in five lipotoxin responders.[48]
TC-3 thermosensitive hydrogel
A gel that is liquid at room temperature and solid at body temperature prolongs intravesical dwell time. The 39-woman pilot found no significant benefit in conventional comparisons; an exploratory analysis favored gel plus 200 U for high-grade urgency and leakage over 72 hours.[49] A later phase 2 placebo-controlled trial found no efficacy endpoint better than placebo at week 12 with 100–500 U hydrogel admixtures.[64]
Energy-assisted delivery
In a six-patient IC/BPS case series, suprapubic ESW after intravesical BoNT-A was followed by cleaved SNAP-25 staining in bladder biopsies, consistent with passage across the urothelium; pain and symptom scores did not improve significantly at one month.[49]
Status: all three are investigational.
Special populations
Pediatric NDO (≥5 y)
Pediatric NDO is FDA-labeled from age 5 after inadequate response to or intolerance of anticholinergics: 200 U if weight ≥34 kg, 6 U/kg below 34 kg. Use the pediatric dilution and procedural instructions rather than transferring the adult NDO template.[1]
Parkinson's disease and post-stroke
For PD and post-stroke bladder dysfunction, 100 U is a commonly reported intradetrusor dose.[50] In a 23-patient post-stroke series using 100 U, 4 (17.4%) developed acute retention; in a 2025 retrospective cohort of 95 toxin-treated patients with post-stroke UUI, 66% reported >50% symptom improvement.[50][72]
Elderly and men
Older women with comorbidities had lower response and satisfaction with onabotA compared with SNM in ROSETTA secondary analysis.[18][24] One small retrospective series associated male sex with poorer response and CIC; do not use its fivefold odds estimate as the expected risk for all men.[22]
Clinical Positioning
- OAB and NDO have strong efficacy evidence, but doses, trial populations and catheterization risks differ. Use the indication-specific label and a retention plan.
- AUA 2024 allows shared selection of minimally invasive OAB treatment without requiring prior behavioral or drug trials; this recommendation does not rewrite the product’s labeled indication.[5]
- ROSETTA compared SNM with 200 U Botox. ROSETTA’s small UUI difference and higher UTI risk were measured at six months with 200 U Botox.[14]
- IC/BPS, sphincter or bladder-neck injection, and pelvic-floor treatment are off-label. The newer pelvic-floor RCT did not establish additional pain relief.[25][51]
- Intraprostatic Botox has not shown convincing benefit for BPH in large placebo-controlled trials.[33][34]
- Repeat dosing follows clinical response, the ≥12-week interval and cumulative limits; investigational delivery techniques do not remove label safety precautions.
See Also
- Anticholinergics
- β3-agonists
- Topical compounded agents
- Local anesthetics
- Intravesical IC/BPS agents
- IC/PBS
- Chronic Pelvic Pain
References
1. AbbVie. BOTOX (onabotulinumtoxinA): US prescribing information. Manufacturer PDF, revised November 2023. Current Allergan label on DailyMed (SPL published August 2026, same November 2023 revision), checked September 27, 2026; adverse reactions in section 6.1 (Tables 14–18), retention in section 5.13, immunogenicity in section 6.2.
2. Nitti V, Haag-Molkenteller C, Kennelly M, et al. "Treatment of neurogenic detrusor overactivity and overactive bladder with Botox (onabotulinumtoxinA): development, insights, and impact." Medicine. 2023;102(S1):e32377. doi:10.1097/MD.0000000000032377
3. Lin YH, Chiang BJ, Liao CH. "Mechanism of action of botulinum toxin A in treatment of functional urological disorders." Toxins. 2020;12(2):E129. doi:10.3390/toxins12020129
4. Jiang YH, Liao CH, Kuo HC. "Current and potential urological applications of botulinum toxin A." Nat Rev Urol. 2015;12(9):519–533. doi:10.1038/nrurol.2015.193
5. Cameron AP, Chung DE, Dielubanza EJ, et al. "The AUA/SUFU guideline on the diagnosis and treatment of idiopathic overactive bladder." J Urol. 2024;212(1):11–20. doi:10.1097/JU.0000000000003985
6. Nitti VW, Dmochowski R, Herschorn S, et al. "OnabotulinumtoxinA for the treatment of patients with overactive bladder and urinary incontinence: results of a phase 3, randomized, placebo-controlled trial." J Urol. 2013;189(6):2186–2193. doi:10.1016/j.juro.2012.12.022
7. Nitti VW, Ginsberg D, Sievert KD, et al. "Durable efficacy and safety of long-term onabotulinumtoxinA treatment in patients with overactive bladder syndrome: final results of a 3.5-year study." J Urol. 2016;196(3):791–800. doi:10.1016/j.juro.2016.03.146
8. Hsieh MH, Hwang JC, Su TH, Lau HH. "The efficacy and safety between intradetrusor onabotulinumtoxinA injection and combined pharmacotherapy in patients with refractory overactive bladder: a randomized controlled trial." J Urol. 2025. doi:10.1097/JU.0000000000004660
9. Ginsberg DA, Boone TB, Cameron AP, et al. "The AUA/SUFU guideline on adult neurogenic lower urinary tract dysfunction: treatment and follow-up." J Urol. 2021;206(5):1106–1113. doi:10.1097/JU.0000000000002239
10. Sanford M. "OnabotulinumtoxinA (Botox): a review of its use in the treatment of urinary incontinence in patients with multiple sclerosis or subcervical spinal cord injury." Drugs. 2014;74(14):1659–1672. doi:10.1007/s40265-014-0271-z
11. Tullman M, Chartier-Kastler E, Kohan A, et al. "Low-dose onabotulinumtoxinA improves urinary symptoms in noncatheterizing patients with MS." Neurology. 2018;91(7):e657–e665. doi:10.1212/WNL.0000000000005991
12. Rovner E, Kohan A, Chartier-Kastler E, et al. "Long-term efficacy and safety of onabotulinumtoxinA in patients with neurogenic detrusor overactivity who completed 4 years of treatment." J Urol. 2016;196(3):801–808. doi:10.1016/j.juro.2016.04.046
13. Wang SL, Jaffe WI, Smith AL. "How can we personalize the delivery of onabotulinumtoxin-A for patients with neurogenic lower urinary tract dysfunction?" Neurourol Urodyn. 2026. doi:10.1002/nau.70290
14. Amundsen CL, Richter HE, Menefee SA, et al. "OnabotulinumtoxinA vs sacral neuromodulation on refractory urgency urinary incontinence in women: a randomized clinical trial." JAMA. 2016;316(13):1366–1374. doi:10.1001/jama.2016.14617
15. Hendrickson WK, Zhang C, Jelovsek JE, Nygaard IE, Presson AP. "Longitudinal fluctuations in treatment response after onabotulinumtoxinA and sacral neuromodulation for refractory urgency incontinence." J Urol. 2024;211(1):134–143. doi:10.1097/JU.0000000000003746
16. Roman MP, Ciortea R, Doumouchtsis SK, et al. "Comparison of different treatment outcomes for refractory overactive bladder: a systematic review and meta-analysis." Toxins. 2025;17(10):479. doi:10.3390/toxins17100479
17. Yang G, Xu Y, Qu G, Zhang Y. "Refractory overactive bladder patients who chose sacral neuromodulation therapy after failed onabotulinumtoxinA treatment: a systematic review and meta-analysis." PLoS One. 2020;15(3):e0230355. doi:10.1371/journal.pone.0230355
18. Richter HE, Amundsen CL, Erickson SW, et al. "Characteristics associated with treatment response and satisfaction in women undergoing onabotulinumtoxinA and sacral neuromodulation for refractory urgency urinary incontinence." J Urol. 2017;198(4):890–896. doi:10.1016/j.juro.2017.04.103
19. Eilber KS, Brucker BM, Pezzella A, et al. "Expert opinions on best practices for overactive bladder management with onabotulinumtoxinA." Toxins. 2025;17(4):207. doi:10.3390/toxins17040207
20. Rovner E. "Chapter 6: practical aspects of administration of onabotulinumtoxinA." Neurourol Urodyn. 2014;33 Suppl 3:S32–S37. doi:10.1002/nau.22637
21. Li J, Tang C, Pan H, Song C. "Ultrasound-guided transabdominal botulinum toxin injection for refractory overactive bladder treatment." Sci Rep. 2025;15(1):18162. doi:10.1038/s41598-025-03116-2
22. Abrar M, Stroman L, Malde S, Solomon E, Sahai A. "Predictors of poor response and adverse events following botulinum toxin-A for refractory idiopathic overactive bladder." Urology. 2020;135:32–37. doi:10.1016/j.urology.2019.08.054
23. Hsiao SM, Lin HH, Kuo HC. "Factors associated with therapeutic efficacy of intravesical onabotulinumtoxinA injection for overactive bladder syndrome." PLoS One. 2016;11(1):e0147137. doi:10.1371/journal.pone.0147137
24. Hanna MG, Shah AM, Li W, et al. "Urinary cytokines in predicting intradetrusor onabotulinumtoxin-A response." Neurourol Urodyn. 2026;45(4):845–852. doi:10.1002/nau.70261
25. Clemens JQ, Erickson DR, Varela NP, Lai HH. "Diagnosis and treatment of interstitial cystitis/bladder pain syndrome." J Urol. 2022;208(1):34–42. doi:10.1097/JU.0000000000002756
26. Pinto RA, Costa D, Morgado A, et al. "Intratrigonal onabotulinumtoxinA improves bladder symptoms and quality of life in patients with bladder pain syndrome/interstitial cystitis: a pilot, single-center, randomized, double-blind, placebo-controlled trial." J Urol. 2018;199(4):998–1003. doi:10.1016/j.juro.2017.10.018
27. Goel S, Pierce H, Pain K, et al. "Use of botulinum toxin A (BoNT-A) in detrusor external sphincter dyssynergia (DESD): a systematic review and meta-analysis." Urology. 2020;140:7–13. doi:10.1016/j.urology.2020.03.007
28. Chancellor MB, Elovic E, Esquenazi A, et al. "Evidence-based review and assessment of botulinum neurotoxin for the treatment of urologic conditions." Toxicon. 2013;67:129–140. doi:10.1016/j.toxicon.2013.01.020
29. Huang YH, Chen SL. "Concomitant detrusor and external urethral sphincter botulinum toxin-A injections in male spinal cord injury patients with detrusor overactivity and detrusor sphincter dyssynergia." J Rehabil Med. 2022;54:jrm00264. doi:10.2340/jrm.v54.122
30. Lee CL, Kuo HC. "Video urodynamic predictors of outcomes after urethral sphincter botulinum toxin A injection in spinal cord-injured patients with detrusor sphincter dyssynergia." Toxins. 2025;17(8):412. doi:10.3390/toxins17080412
31. Sacco E, Tienforti D, Bientinesi R, et al. "OnabotulinumtoxinA injection therapy in men with LUTS due to primary bladder-neck dysfunction: objective and patient-reported outcomes." Neurourol Urodyn. 2014;33(1):142–146. doi:10.1002/nau.22393
32. Lee YS, Lee YK, Chang TL, et al. "Clinical efficacy of bladder neck injection of botulinum toxin A in treating neurogenic and non-neurogenic voiding dysfunctions due to bladder neck dysfunction." Toxins. 2025;17(6):289. doi:10.3390/toxins17060289
33. Marberger M, Chartier-Kastler E, Egerdie B, et al. "A randomized double-blind placebo-controlled phase 2 dose-ranging study of onabotulinumtoxinA in men with benign prostatic hyperplasia." Eur Urol. 2013;63(3):496–503. doi:10.1016/j.eururo.2012.10.005
34. McVary KT, Roehrborn CG, Chartier-Kastler E, et al. "A multicenter, randomized, double-blind, placebo-controlled study of onabotulinumtoxinA 200 U to treat lower urinary tract symptoms in men with benign prostatic hyperplasia." J Urol. 2014;192(1):150–156. doi:10.1016/j.juro.2014.02.004
35. da Silva CM, Chancellor MB, Smith CP, Cruz F. "Use of botulinum toxin for genitourinary conditions: what is the evidence?" Toxicon. 2015;107(Pt A):141–147. doi:10.1016/j.toxicon.2015.07.333
36. Chermansky CJ, Chancellor MB. "Use of botulinum toxin in urologic diseases." Urology. 2016;91:21–32. doi:10.1016/j.urology.2015.12.049
37. Falahatkar S, Shahab E, Gholamjani Moghaddam K, Kazemnezhad E. "Transurethral intraprostatic injection of botulinum neurotoxin type A for the treatment of chronic prostatitis/chronic pelvic pain syndrome: results of a prospective pilot double-blind and randomized placebo-controlled study." BJU Int. 2015;116(4):641–649. doi:10.1111/bju.12951
38. Franco JV, Turk T, Jung JH, et al. "Pharmacological interventions for treating chronic prostatitis/chronic pelvic pain syndrome." Cochrane Database Syst Rev. 2019;10:CD012552. doi:10.1002/14651858.CD012552.pub2
39. Panunzio A, Tafuri A, Mazzucato G, et al. "Botulinum toxin-A injection in chronic pelvic pain syndrome treatment: a systematic review and pooled meta-analysis." Toxins. 2022;14(1):25. doi:10.3390/toxins14010025
40. Spruijt MA, Klerkx WM, Kelder JC, Kluivers KB, Kerkhof MH. "The efficacy of botulinum toxin A injections in pelvic floor muscles in chronic pelvic pain patients: a systematic review and meta-analysis." Int Urogynecol J. 2022;33(11):2951–2961. doi:10.1007/s00192-022-05115-7
41. Dessie SG, Von Bargen E, Hacker MR, Haviland MJ, Elkadry E. "A randomized, double-blind, placebo-controlled trial of onabotulinumtoxin A trigger point injections for myofascial pelvic pain." Am J Obstet Gynecol. 2019;221(5):517.e1–517.e9. doi:10.1016/j.ajog.2019.06.044
42. Whitmore GT, Tam J, Orlando M. "OnabotulinumtoxinA injections for patients with pelvic floor dysfunction." J Minim Invasive Gynecol. 2025. doi:10.1016/j.jmig.2025.07.005
43. Karp BI, Stratton P. "Chronic pelvic pain and botulinum toxin." Toxicon. 2025;258:108336. doi:10.1016/j.toxicon.2025.108336
44. Hung FC, Kuo HC. "Liposome-encapsulated botulinum toxin A in treatment of functional bladder disorders." Toxins. 2022;14(12):838. doi:10.3390/toxins14120838
45. Tyagi P, Kashyap M, Yoshimura N, Chancellor M, Chermansky CJ. "Past, present and future of chemodenervation with botulinum toxin in the treatment of overactive bladder." J Urol. 2017;197(4):982–990. doi:10.1016/j.juro.2016.11.092
46. Chuang YC, Kaufmann JH, Chancellor DD, Chancellor MB, Kuo HC. "Bladder instillation of liposome-encapsulated onabotulinumtoxinA improves overactive bladder symptoms: a prospective, multicenter, double-blind, randomized trial." J Urol. 2014;192(6):1743–1749. doi:10.1016/j.juro.2014.07.008
47. Kuo HC, Liu HT, Chuang YC, Birder LA, Chancellor MB. "Pilot study of liposome-encapsulated onabotulinumtoxinA for patients with overactive bladder: a single-center study." Eur Urol. 2014;65(6):1117–1124. doi:10.1016/j.eururo.2014.01.036
48. Liu HT, Chen SH, Chancellor MB, Kuo HC. "Presence of cleaved synaptosomal-associated protein-25 and decrease of purinergic receptors P2X3 in the bladder urothelium influence efficacy of botulinum toxin treatment for overactive bladder syndrome." PLoS One. 2015;10(8):e0134803. doi:10.1371/journal.pone.0134803
49. Jhang JF, Kuo HC. "Novel applications of non-invasive intravesical botulinum toxin A delivery in the treatment of functional bladder disorders." Toxins. 2021;13(5):359. doi:10.3390/toxins13050359
50. Hu JC, Hsu LN, Lee WC, Chuang YC, Wang HJ. "Role of urological botulinum toxin-A injection for overactive bladder and voiding dysfunction in patients with Parkinson's disease or post-stroke." Toxins. 2023;15(2):166. doi:10.3390/toxins15020166
51. Spruijt MA, Klerkx WM, Notten K, et al. The efficacy of botulinum toxin A injection in pelvic floor muscles in chronic pelvic pain patients: a double-blinded randomised controlled trial. BJOG. 2025;132:297–305. doi:10.1111/1471-0528.17991.
52. Harding CK, Lapitan MC, Arlandis S, et al. EAU Guidelines on Management of Non-Neurogenic Female Lower Urinary Tract Symptoms (LUTS). Limited update March 2026. European Association of Urology; 2026. Sections 4.1.4.c.1, 4.4.4.c.2 and 4.5.4.b.3.a.
53. Blok B, Hamid R, Hentzen C, et al. EAU Guidelines on Neuro-Urology. Limited update March 2026. European Association of Urology; 2026. Sections 3.4.2.e.6 and 3.4.2.e.7.
54. Chapple C, Sievert KD, MacDiarmid S, et al. "OnabotulinumtoxinA 100 U significantly improves all idiopathic overactive bladder symptoms and quality of life in patients with overactive bladder and urinary incontinence: a randomised, double-blind, placebo-controlled trial." Eur Urol. 2013;64(2):249–256. doi:10.1016/j.eururo.2013.04.001
55. Cruz F, Herschorn S, Aliotta P, et al. "Efficacy and safety of onabotulinumtoxinA in patients with urinary incontinence due to neurogenic detrusor overactivity: a randomised, double-blind, placebo-controlled trial." Eur Urol. 2011;60(4):742–750. doi:10.1016/j.eururo.2011.07.002
56. Ginsberg D, Gousse A, Keppenne V, et al. "Phase 3 efficacy and tolerability study of onabotulinumtoxinA for urinary incontinence from neurogenic detrusor overactivity." J Urol. 2012;187(6):2131–2139. doi:10.1016/j.juro.2012.01.125
57. Yu PH, Wang CC. "Adverse effects of intravesical onabotulinumtoxinA injection in patients with idiopathic overactive bladder or neurogenic detrusor overactivity: a systematic review and meta-analysis of randomized controlled studies." Toxins. 2024;16(8):343. doi:10.3390/toxins16080343
58. Getaneh FW, Simhal R, Sholklapper T, et al. "Antibiotic prophylaxis for onabotulinum toxin A injections: systematic review and meta-analysis." Int Urogynecol J. 2024;35(1):19–29. doi:10.1007/s00192-023-05665-4
59. Welch EK, Dengler KL, DiCarlo-Meacham AM, et al. "Bladder instillations vs onabotulinumtoxinA injection for interstitial cystitis/bladder pain syndrome: a randomized clinical trial." Am J Obstet Gynecol. 2024;231(5):528.e1–528.e11. doi:10.1016/j.ajog.2024.05.027
60. Engeler D, Baranowski AP, Berghmans B, et al. EAU Guidelines on Chronic Pelvic Pain. European Association of Urology; limited update March 2026. Guideline
61. American Urological Association. Diagnosis and Management of Male Chronic Pelvic Pain (Chronic Prostatitis/Chronic Pelvic Pain Syndrome and Chronic Scrotal Content Pain): AUA Guideline (2025). Approved March 2025. Full 2025 guideline Future Directions, p43.
62. Phelan MW, Franks M, Somogyi GT, Yokoyama T, Fraser MO, Lavelle JP, et al. "Botulinum toxin urethral sphincter injection to restore bladder emptying in men and women with voiding dysfunction." J Urol. 2001;165(4):1107-1110. doi:10.1016/s0022-5347(05)66438-5
63. Gleich L, Shenhar C, Booher J, Slopnick E. "Bladder OnabotulinumtoxinA Antibiotic Prophylaxis: A Prospective RCT." Urogynecology (Phila). 2026;32(2):149–154. doi:10.1097/SPV.0000000000001762
64. Chermansky CJ, Richter HE, Jacoby K, et al. "Intravesical instillation of onabotulinumtoxinA in the treatment of refractory overactive bladder in participants with urinary incontinence." J Urol. 2022;208(4):855–862. doi:10.1097/JU.0000000000002800
65. Amundsen CL, Komesu YM, Chermansky C, et al. "Two-year outcomes of sacral neuromodulation versus onabotulinumtoxinA for refractory urgency urinary incontinence: a randomized trial." Eur Urol. 2018;74(1):66–73. doi:10.1016/j.eururo.2018.02.011
66. Knapman BL, Li FG, Deans R, Nesbitt-Hawes E, Maheux-Lacroix S, Abbott J. "Botulinum toxin for the management of pelvic floor tension myalgia and persistent pelvic pain: a systematic review and meta-analysis." Obstet Gynecol. 2024;143(1):e7–e17. doi:10.1097/AOG.0000000000005388
67. Doiron RC, Tadayon B, Violette PD, et al. "2025 Canadian Urological Association guideline: Selected treatment recommendations for interstitial cystitis/bladder pain syndrome." Can Urol Assoc J. 2025;19(4):90–103. doi:10.5489/cuaj.9182
68. Galderma Laboratories, L.P. "DYSPORT (abobotulinumtoxinA) US prescribing information." DailyMed. Revised September 2023. Label.
69. Merz Pharmaceuticals, LLC. "XEOMIN (incobotulinumtoxinA) US prescribing information." DailyMed. Revised June 2026. Label.
70. Denys P, Castaño Botero JC, Vita Nunes RL, et al. "AbobotulinumtoxinA is effective in patients with urinary incontinence due to neurogenic detrusor overactivity regardless of spinal cord injury or multiple sclerosis etiology: Pooled analysis of two phase III randomized studies (CONTENT1 and CONTENT2)." Neurourol Urodyn. 2023;42(1):153–167. doi:10.1002/nau.25062
71. Trikhacheva AS, Hamade SJ, Gisseman JD, Olsen C, Vaccaro CM, Dengler KL. "IncobotulinumtoxinA Versus OnabotulinumtoxinA for Treatment of Overactive Bladder Syndrome: A Randomized Single-blinded Non-inferiority Trial." Urology. 2026;212:8–13. doi:10.1016/j.urology.2026.03.040
72. Trump T, Anis O, Goldman HB, Chow PM. "Outcomes of Sacral Neuromodulation and Intradetrusor Onabotulinum Toxin in the Management of Stroke Associated Urinary Incontinence." Int Neurourol J. 2025;29(1):10–16. doi:10.5213/inj.2448412.206
73. Hufnagel DH, Torosis M, Ackerman AL. "Modified Delphi Consensus Guidelines for Pelvic Floor Botulinum Toxin Injection." Urogynecology (Phila). 2026;32(4):312–320. doi:10.1097/SPV.0000000000001841