Operative Exposure
Choose the position, incision and extent of mobilization for the structure that must be seen and controlled. Good exposure also preserves the blood supply, nerves and tissue needed for reconstruction.
Use Positioning & Nerve Injury for positioning precautions, Incisions & Closure for abdominal entry and closure, and Vascular Damage Control for hemorrhage management.
Vaginal Exposure
Position and retraction
Use dorsal lithotomy with only the hip flexion, abduction and tilt required for access. Assess the patient's comfortable joint range before anesthesia; move and support both legs together. Avoid sustained fibular-head pressure, excessive hip movement and stretch across both the hip and knee. Neither a particular stirrup nor a duration below two hours guarantees freedom from nerve injury. Limit exaggerated lithotomy, which increases hip flexion for combined abdominoperineal work, to the portion of the operation that requires it. A Trendelenburg tilt displaces abdominal viscera cephalad and can improve exposure of the vaginal apex and pelvic floor.[1]
Adjust lighting, vaginal traction and retractor depth before increasing force or extending an incision. A weighted posterior speculum can support the posterior wall; Deaver and Breisky–Navratil retractors are hand-held instruments and are not interchangeable names for a weighted speculum. Right-angle blades and self-retaining rings with elastic stays serve different fields. Confirm that blades and stays retract the intended tissue without trapping the urethra, rectum or vulnerable skin.[2]
Local infiltration is optional and procedure-specific. Plain fluid, local anesthetic and vasoconstrictor-containing solutions have different purposes and risks. See Hydrodissection Agents for agent selection, off-label use and systemic toxicity precautions.
Match the incision to the repair
| Target | Exposure principle | Structures and limits |
|---|---|---|
| Anterior vaginal wall | Tailor the incision and separation of epithelium/fibromuscular tissue to the defect and planned repair | Identify the urethra and bladder; a sling incision and an anterior colporrhaphy are different operations |
| Lateral anterior support | Paravaginal repair requires exposure of the lateral vaginal support and arcus tendineus fasciae pelvis | This is a prolapse repair |
| Posterior vaginal wall | Expose the fibromuscular layer while protecting the adjacent rectum; extend only as required by the defect | Levator plication and perineal repair are separate procedures |
| Vaginal apex | Identify the intended ligament and its relation to adjacent organs before suspension | Sacrospinous and uterosacral suspension require different access and injury checks |
The AUGS–IUGA terminology report describes substantial variation in incision length and dissection depth. A longitudinal posterior incision need not automatically extend from the hymen to the apex, and routine deep puborectalis dissection is not required merely to obtain posterior-wall exposure.[2]
Burch colposuspension uses retropubic access, through an abdominal or minimally invasive approach. See the Burch procedure and prolapse atlas for their distinct operative steps.
Apical landmarks
For sacrospinous fixation, identify the ischial spine and sacrospinous ligament–coccygeus complex. Posterior, anterior and apical vaginal approaches are described; posterior access develops the rectovaginal and pararectal spaces. The chosen suture location and depth must account for nearby nerves and vessels, and palpation of the spine alone is not sufficient. For uterosacral suspension, account for the ureter along the intended suture path and assess ureteral patency with intraoperative cystoscopy. For sacrospinous fixation, the terminology report describes attachment 2–3 cm medial to the ischial spine to avoid neurovascular structures; it gives no fixed 2 cm ureteral exclusion zone for uterosacral suspension.[2]
Perineal Exposure
Position and incision
Select lithotomy, a modified lithotomy position or prone access according to the target and the need for abdominal access. A prone jackknife approach may help selected posterior perineal operations, but requires a coordinated turn, airway access and pressure protection. In a retrospective APR study, prone positioning was associated with fewer wound infections; urethroplasty, fistula repair and other GU reconstructions were not assessed.[1][3]
- Bulbar urethral access: a midline longitudinal perineal incision is common. An inverted-Y or lambda extension is a distinct incision choice. Bulbospongiosus handling and the degree of urethral mobilization depend on the reconstruction.
- Posterior urethral or prostatic-apical access: a curvilinear or extended midline perineal approach may be used. Corporal separation or bony work is selected for the actual length and access problem.
- Perianal or extirpative access: the incision and tissue removed follow the disease and reconstructive plan.
Use the urethral reconstruction atlas for named repairs. Plan incisions with the reconstructive team when local flaps, abdominal flaps or a stoma may be needed; avoid sacrificing a potential donor pedicle during access.[4]
Transpubic and combined approaches
Pubic symphysiotomy is a specialized access option, distinct from inferior pubectomy or other bony resections. Peters and Hendren reported 46 patients aged 1–32 years (exstrophy in 16, epispadias in 11, cloacal exstrophy in 6, and smaller numbers with posterior urethral valves, severe trauma and other complex problems), most with a prior operation. The pubis, or the interpubic ligament in exstrophy, was divided in the midline and the rami were spread with a laminectomy spreader to reach the bladder neck and urethra (down to the bulb in males). No pubic segment was resected, and there was no nonunion or pubic osteitis in that series.[5]
Combined abdominal and perineal work can be synchronous in a suitable modified lithotomy setup or sequential with repositioning. Decide in advance how the teams will share access and when the position can be relaxed. A VRAM flap, harvested through the abdominal incision and transposed through the pelvic floor, is one option for a large pelviperineal defect; incision choice must also accommodate previous scars, stoma sites, flap-pedicle availability and alternative donor tissues.[4]
Abdominal Incision and Route
| Access | Useful exposure | Main limitation to plan for |
|---|---|---|
| Midline | Extensible access to multiple abdominal compartments; commonly used for major reconstruction and emergency exploration | Upper retroperitoneal targets may still require visceral mobilization |
| Low transverse/Pfannenstiel | Selected bladder, retropubic and pelvic operations | Restricted cephalad access and extension compared with a long midline incision |
| Gibson/iliac-fossa | Distal ureter, transplant bed and iliac vessels | Primarily a unilateral field; bilateral or more proximal work may require another route |
| Flank/lumbotomy | Direct ipsilateral upper-tract/retroperitoneal access | Limited cross-abdominal access; muscle, nerve and positioning morbidity |
| Subcostal/chevron with selected extension | Broad upper-abdominal access for complex renal, adrenal or vascular surgery | Greater abdominal-wall exposure; mobilization still depends on the target |
| Thoracoabdominal | Selected lesions requiring access across the diaphragm | Adds thoracic/diaphragmatic morbidity |
The incision atlas covers incision-specific trade-offs. Transplant-derived subcostal approaches can facilitate selected difficult upper-tract operations; safe hepatic-vein, intracardiac-IVC and vascular control require separate planning.[6]
Extraperitoneal versus transperitoneal
An extraperitoneal route may reduce manipulation of intraperitoneal adhesions and bowel. Prior retroperitoneal surgery and fibrosis may make this route difficult.[7] Orikasa's 51-patient series demonstrated feasibility of a midline extraperitoneal approach by mobilizing the peritoneal sac with its supporting fascia.[7]
Sato's retrospective salvage report involved 23 operations in 22 patients, including selected bilateral reconstruction. Transperitoneal access generally provides more room for multi-organ reconstruction and bowel or omental mobilization.[8]
Retroperitoneal Mobilization
Describe the actual plane
The lateral colonic peritoneal reflection, renal fascia and tissue behind the duodenum and pancreas are different landmarks. Terms such as Toldt, Treitz and Gerota are used inconsistently across specialties. A 2026 JSES surgical consensus describes fusion fascia as a multilayered connective-tissue region with selectable operative planes, and not as a single guaranteed bloodless membrane.[9]
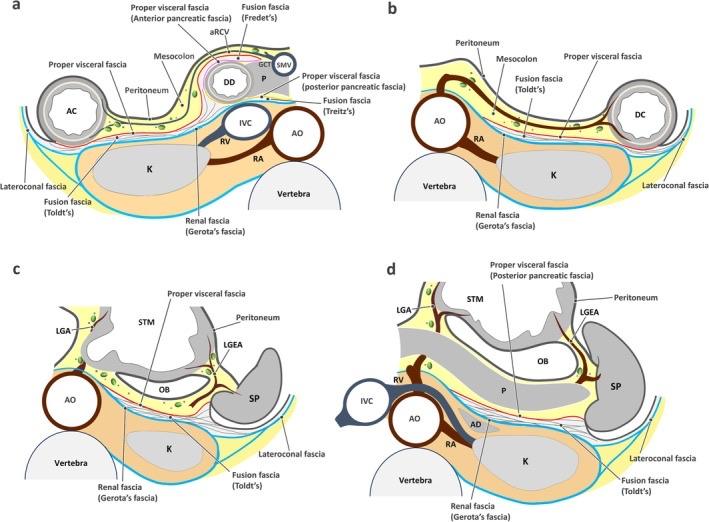
Fusion interface between the viscera and the retroperitoneum in axial section: (a) ascending mesocolon and pancreaticoduodenal region; (b) descending mesocolon; (c) mesogastrium including the spleen; (d) mesogastrium including the distal pancreas and spleen. Renal (Gerota's) fascia and the lateroconal fascia are light blue; the newly proposed proper visceral fascia is red. Fusion fascia is drawn as a multilayered connective-tissue zone that permits selection of a dissection plane, and eponyms in parentheses are supplementary descriptors only. From Watanabe J, et al. Asian J Endosc Surg. 2026;19:e70348, Figure 1 (CC BY).[9]
Kocher maneuver
Kocher mobilization releases the duodenum and pancreatic head medially. Open the lateral duodenal peritoneal attachments and develop the tissue plane posterior to the pancreaticoduodenal unit while preserving the unit and its vascular attachments. This exposes the underlying IVC and adjacent aortic and renal-level structures as the mobilization is extended. A complete Kocher maneuver, with the duodenum mobilized until the posterior head of the pancreas and uncinate process are visible, is described as necessary to expose the juxtarenal and suprarenal IVC; retracting the inferior edge of the right hepatic lobe adds distal control above the renal veins. The left renal vein crosses anterior to the aorta below the superior mesenteric artery origin. Kocher mobilization is not identical to a full right medial visceral rotation, and it does not automatically expose the kidney or the entire right ureter.[10]
The duodenal plane is commonly described in relation to Treitz fascia; the white line of Toldt is a colonic reflection. Do not chase an assumed avascular plane into the mesenteric root or pancreatic vessels merely to meet a fixed “complete Kocher” endpoint.[9][10]
Cattell–Braasch: right medial visceral rotation
- Release the right colonic lateral attachments from the cecal region toward the hepatic flexure.
- Mobilize the right colon and small-bowel mesentery from the retroperitoneum, with controlled Kocher mobilization where needed.
- Reflect the bowel toward the patient's left and cephalad to expose the infrahepatic IVC and right retroperitoneal field.
- Identify the ureter and renal and iliac structures as dissection approaches them; extend the exposure only to the required vessel and control points.
This provides broader access than Kocher mobilization alone.[10][11] Reaching the retrohepatic or suprahepatic IVC requires additional liver-related exposure.[10][11]
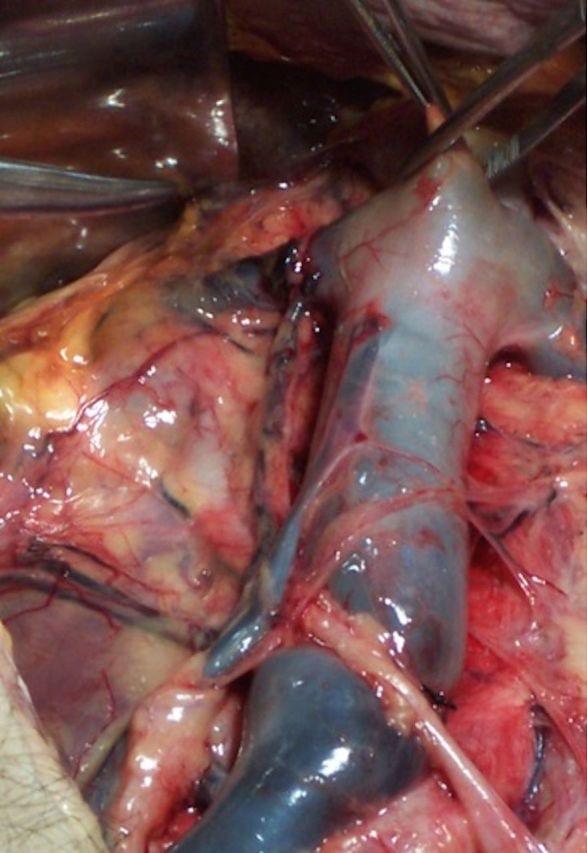
Infrarenal, juxtarenal and suprarenal IVC exposed after right medial visceral rotation. The suprarenal segment is reached by displacing the inferior edge of the right hepatic lobe superiorly after an extended Kocher maneuver. From Kobayashi LM, et al. Trauma Surg Acute Care Open. 2016;1:e000015, Figure 2 (CC BY-NC).[10]
Mattox: left medial visceral rotation
Incise the white line of Toldt along the left paracolic gutter from the splenic flexure to the sigmoid colon. Develop the plane between the left colon and its mesocolon and the anterior surface of Gerota's fascia, then mobilize the spleen, the pancreatic tail and body (and the stomach if needed) with the left colon as one visceral package toward the patient's right, pivoting on the aorta. The renal plane must be stated explicitly:
- Full trauma rotation behind the kidney: includes the left kidney in the mobilized package and provides broad aortic exposure.
- Modified rotation anterior to the kidney: leaves the kidney posteriorly while mobilizing the colon, spleen and pancreas.
The target determines which plane and extent are appropriate. Depending on the extent of rotation, the exposure can include the aorta from the hiatus to the bifurcation, the celiac, superior mesenteric and left renal artery origins, the left renal hilum and left ureter, and the left iliac vessels. Reaching the supraceliac aorta may require additional hiatal and crural dissection.[10][11]
Protect the splenic capsule, pancreatic tail and vascular pedicles from traction. In Reilly's older complex aortic series, 108 operations in 104 patients included 23 splenic injuries (21.3%) and five postoperative pancreatitis events (contributing to death in two patients).[12] Conversely, Ciancio's 70-patient upper-quadrant tumor series used an extended subcostal transabdominal incision with en bloc mobilization of the spleen and pancreas (and the stomach when necessary). Mean blood loss was 973 mL; no pancreatitis, acute renal failure or perioperative deaths were reported, but other morbidity and comparative outcomes remain uncertain.[12][13]
Direct aortic and mesenteric access
Infrarenal aorta: move the small bowel to the patient's right, lift the transverse mesocolon and open the overlying retroperitoneum under direct vision. Identify the left renal vein and variant anatomy before selecting proximal control. This is an inframesocolic retroperitoneal exposure; it does not require indiscriminately cutting through the small-bowel mesentery.[10]
Supraceliac control: selected emergency exposure can be obtained through the gastrohepatic region, with retraction of the stomach and esophagus and deliberate hiatal dissection. Left medial rotation is another route. Approach selection depends on the injury and available exposure; no maneuver is uniformly fastest. Aortic compression, clamping, ischemic consequences and resuscitation belong in the vascular-control workflow.[10][11]
Mesenteric-vessel injuries: a targeted approach through an existing injury or the mesenteric root may be needed. Identify the artery and vein, bowel perfusion and proximal and distal control requirements before extending that opening.[10]
Retroperitoneal Hematoma: Physiology Before a Zone Label
Central, perirenal and pelvic zones remain useful for communicating location.ESVS 2025 notes that hematomas cross zone boundaries and that the older zone rules predate widespread CTA and endovascular treatment.[11]
- Shock with ongoing suspected major abdominal vascular bleeding: proceed to immediate hemorrhage control; imaging must not delay it.
- At trauma laparotomy, an unstable patient or an expanding, pulsatile or actively bleeding retroperitoneal hematoma: ESVS recommends exploration.
- A stable patient and a stable hematoma: ESVS supports leaving it unopened with subsequent CTA to direct management. These are Class I, Level C recommendations.
Plan vascular control and appropriate expertise before deliberately releasing tamponade. Pelvic-fracture hemorrhage may need coordinated stabilization, preperitoneal packing and embolization; a stable retrohepatic hematoma should not be opened merely because it is labeled “portal.” See Vascular Damage Control for vessel- and injury-specific decisions.[10][11]
The ESVS guideline addresses traumatic vascular injury and not iatrogenic injury. Applying its principles to an intraoperative GU injury is an extrapolation. A known vessel injury, organ ischemia or suspected bowel or ureteral injury requires its own assessment even if a hematoma is temporarily contained.
Specialized Exposure and Reconstruction
Marsh and Lange described the liver-transplant incision (bilateral subcostal with a cephalad T extension) combined with a fixed retractor system (Iron Intern and Olivier retractors), used together with liver mobilization and rotation, pancreatic and splenic reflection, control of the intra-abdominal and intracardiac IVC, and veno-venous bypass. Transplant-derived liver mobilization and en-bloc pancreaticosplenic mobilization can expand access for selected renal or adrenal masses and caval thrombi. Plan the resection and reconstruction with teams capable of the required hepatic, vascular or cardiothoracic work.[6][13]
IVC Tumor Thrombus: Level Dictates Exposure
For a renal or adrenal mass with IVC extension, the exposure and vascular-control plan is driven by how far the thrombus extends. In renal cell carcinoma with venous tumor thrombus, preoperative imaging within one to two weeks of surgery can reassess the apex because the thrombus may progress rapidly, as described in the 2026 EAU RCC guideline.[22] The Neves-Zincke level system grades extent as follows: Level 0, thrombus limited to the renal vein; Level 1, extending 2 cm or less above the renal vein; Level 2, more than 2 cm above the renal vein but below the hepatic-vein confluence; Level 3, at or above the hepatic-vein confluence but below the diaphragm; Level 4, extending into the supradiaphragmatic IVC or right atrium. This level, not AJCC T-category alone, determines whether the Kocher, Cattell-Braasch, Mattox or Marsh-Lange mobilizations already described above are sufficient, and whether hepatic, cardiothoracic or vascular surgery involvement is required; in a registry of pT3b-c RCC cases undergoing radical nephrectomy and IVC thrombectomy, higher hospital volume was associated with longer overall survival, without a statistically significant difference in 30- or 90-day mortality.[15][16]
Before incising the IVC for thrombectomy, vascular control is tailored to tumor laterality and the thrombus apex; a described sequence includes the ipsilateral renal artery, the infrarenal IVC below the thrombus, lumbar veins between the suprarenal and infrarenal clamps, contralateral renal outflow, and the suprarenal IVC above the thrombus. Dellaportas et al. describe control of both the right renal artery and vein for left-sided RCC to limit back-bleeding, whereas left renal-vein control with the artery left unclamped may suffice for right-sided RCC; they used intraoperative ultrasonography to locate the apex before proximal clamping.[23] For thrombus at or above the hepatic-vein confluence (level 3 and above), the proximal clamp site and need for hepatic inflow control depend on the thrombus apex and mobility. When suprahepatic IVC clamping is needed, a Pringle maneuver temporarily clamps the hepatic artery and portal vein in the hepatoduodenal ligament; hepatic inflow occlusion is minimized. In one reported mobile level IIIc-to-IV RCC thrombus, the suprahepatic clamp was moved below the hepatic veins after caudal thrombus displacement, permitting early Pringle release.[24] Weight-based pre-clamp heparinization can be considered case by case depending on anticipated clamp time and hypercoagulable state. This intraoperative choice is separate from anticoagulation between RCC diagnosis and surgery: AFU 2024–26 describes preventive dosing as a reasonable expert-opinion compromise while benefit remains uncertain, and a retrospective propensity-matched cohort did not detect a statistically significant difference in thromboembolic events. AFU addresses postoperative VTE prophylaxis separately.[25][26] For level 4 (supradiaphragmatic or intracardiac) thrombus, two alternatives reach the cephalad extent: cardiopulmonary bypass (with or without hypothermic cardiac arrest) or venovenous bypass, versus a transdiaphragmatic approach to the pericardium from the abdomen that allows controlled clamping of the intra-pericardial IVC and can avoid cardiopulmonary bypass and sternotomy; the choice is dictated by local surgical and institutional expertise, with limited comparative data. Transesophageal echocardiography is used intraoperatively to assess superior extent, thrombus fragility and adherence, guide clamp placement and monitor for embolization; intraoperative tumor-thrombus embolization occurred in 5/149 patients (3.4%) with level I–IV thrombus in one retrospective series, and 3/5 events were fatal[19]; discuss this risk preoperatively. For renal cell carcinoma with IVC thrombus, open surgery remains the reference approach for complex or high-level thrombi requiring extensive vascular control.[17][18][19][20] A 2026 systematic review of 66 studies (3,241 patients) found increasing laparoscopic and robotic use in selected patients, mainly with level I-II thrombi at experienced centers, but selection bias prevents a definitive comparison with open surgery.[21]
A left paracolic approach can expose the para-aortic field while preserving a plane anterior to the renal fascia. The original gynecologic lymphadenectomy report incised the peritoneum along the left paracolic gutter to the splenic flexure, elevated the left colon medially into the avascular plane over the prerenal fascia, and exposed the left kidney, renal pedicle, ureter, ovarian vessels and aorta from the bifurcation to 3–4 cm above the left renal pedicle. In 81 patients, median aortic node yield was 29 (range 21–56), with no major intraoperative injuries. Preserve the ureter, gonadal vessels and renal structures according to the intended operation.[14]
Before closure, reassess tissues mobilized or retracted, confirm the planned organ and vascular checks, and communicate any exposure-related concern in the operative handover. The aim is sufficient access for the repair with the least unnecessary tissue disruption.
Matching Exposure to Target
| Target | Usual position | Approach | Maneuver or point to plan |
|---|---|---|---|
| Anterior vaginal wall or urethra | Dorsal lithotomy | Midline anterior vaginal incision | Hydrodissection where chosen; weighted retractors |
| Posterior vaginal wall or rectovaginal space | Dorsal lithotomy | Midline posterior vaginal incision | Protect the rectum; extend only as the defect requires |
| Vaginal apex or sacrospinous ligament | Dorsal lithotomy | Posterior vaginal approach | Pararectal space; ischial spine and ligament identification |
| Bulbar urethra | Lithotomy or modified lithotomy | Midline perineal incision | Bulbospongiosus handling matched to the repair |
| Membranous urethra or prostatic apex | Lithotomy or modified lithotomy | Curvilinear or extended midline perineal incision | Corporal separation only if the length requires it |
| Bladder neck; entire female urethra or male urethra to the bulb | Supine with lithotomy access | Transpubic (symphysiotomy) | Laminectomy spreader for the pubic rami |
| Distal ureter or bladder | Supine | Gibson or Pfannenstiel | Extraperitoneal dissection where suitable |
| Right retroperitoneum or IVC | Supine | Midline or chevron | Kocher, with Cattell–Braasch rotation when broader access is needed |
| Left retroperitoneum or aorta | Supine | Midline or chevron | Left medial visceral rotation (Mattox), modified or full |
| Infrarenal aorta | Supine | Midline | Small bowel to the right, transverse mesocolon up, retroperitoneum opened at the ligament of Treitz |
| Supraceliac aorta (emergency) | Supine | Midline | Gastrohepatic ligament opened, esophagus and stomach retracted, right crus divided at the hiatus |
| Combined pelviperineal | Modified lithotomy | Abdominal and perineal | Synchronous two-team or sequential; VRAM flap availability |
See Also
- Incisions & Closure: the incision atlas and fascial closure technique.
- Bony Pelvic Anatomy: pubic symphysis, ischial spine and coccyx landmarks for perineal exposure.
- Pelvic Vascular Anatomy: the arterial and venous roadmap for retroperitoneal exposure.
- Positioning & Nerve Injury: lithotomy, prone and exaggerated-lithotomy complications.
References
1. American Society of Anesthesiologists Task Force. “Practice Advisory for the Prevention of Perioperative Peripheral Neuropathies 2018.” Anesthesiology. 2018;128:11–26. doi:10.1097/ALN.0000000000001937.
2. American Urogynecologic Society and International Urogynecological Association Joint Writing Group. “Joint Report on Terminology for Surgical Procedures to Treat Pelvic Organ Prolapse.” Female Pelvic Med Reconstr Surg. 2020;26:173–201. doi:10.1097/SPV.0000000000000846. Society document.
3. Showalter SL, Kelz RR, Mahmoud NN. “Effect of technique on postoperative perineal wound infections in abdominoperineal resection.” Am J Surg. 2013;206:80–85. doi:10.1016/j.amjsurg.2012.10.036.
4. Shahzad F, Ray E. “Pelvic and perineal reconstruction.” Plast Reconstr Surg. 2024;154:803e–816e. doi:10.1097/PRS.0000000000011137.
5. Peters CA, Hendren WH. “Splitting the pubis for exposure in difficult reconstructions for incontinence.” J Urol. 1989;142:527–531. doi:10.1016/s0022-5347(17)38805-5.
6. Marsh CL, Lange PH. “Application of liver transplant and organ procurement techniques to difficult upper abdominal urological cases.” J Urol. 1994;151:1652–1656. doi:10.1016/s0022-5347(17)35331-4.
7. Orikasa S, Kanbe K, Shirai S, et al. “Midline extraperitoneal approach to upper urinary tract surgery: anatomical basis of surgical technique.” Int J Urol. 2006;13:1150–1153. doi:10.1111/j.1442-2042.2006.01477.x.
8. Sato M, Kaiho Y, Kawamorita N, et al. “Retroperitoneal laparoscopic approach to ureteral primary and reoperative ureteral reconstructive surgery: a case series.” J Endourol. 2021;35:828–834. doi:10.1089/end.2020.0175.
9. Watanabe J, Shinohara H, Obama K, et al. “Standardizing Upper Abdominal Fascial Terminology: A Transdisciplinary Expert Consensus From the Japanese Society for Endoscopic Surgery.” Asian J Endosc Surg. 2026;19:e70348. doi:10.1111/ases.70348. Full text.
10. Kobayashi LM, Costantini TW, Hamel MG, Dierksheide JE, Coimbra R. “Abdominal vascular trauma.” Trauma Surg Acute Care Open. 2016;1:e000015. doi:10.1136/tsaco-2016-000015. Full text.
11. Wahlgren CM, Aylwin C, Davenport RA, et al. “Editor's Choice — European Society for Vascular Surgery (ESVS) 2025 Clinical Practice Guidelines on the Management of Vascular Trauma.” Eur J Vasc Endovasc Surg. 2025;69:179–237. doi:10.1016/j.ejvs.2024.12.018. Sections 1.6 and 5.1–5.3, recommendations 61–63.
12. Reilly LM, Ramos TK, Murray SP, Cheng SW, Stoney RJ. “Optimal exposure of the proximal abdominal aorta: a critical appraisal of transabdominal medial visceral rotation.” J Vasc Surg. 1994;19:375–389. doi:10.1016/s0741-5214(94)70065-6.
13. Ciancio G, Vaidya A, Shirodkar S, et al. “En bloc mobilization of the pancreas and spleen to facilitate resection of large tumors, primarily renal and adrenal, in the left upper quadrant of the abdomen: techniques derived from multivisceral transplantation.” Eur Urol. 2009;55:1106–1111. doi:10.1016/j.eururo.2008.12.038.
14. Benedetti-Panici P, Maneschi F, Scambia G, Mancuso S. “A new transabdominal approach to the left retroperitoneum for systematic removal of lymph nodes left of the aorta in gynecologic malignancies.” Obstet Gynecol. 1994;83:1060–1064. doi:10.1097/00006250-199406000-00032.
15. Neves RJ, Zincke H. “Surgical treatment of renal cancer with vena cava extension.” Br J Urol. 1987;59:390–395. doi:10.1111/j.1464-410x.1987.tb04832.x.
16. Freifeld Y, Woldu SL, Singla N, et al. “Impact of Hospital Case Volume on Outcomes Following Radical Nephrectomy and Inferior Vena Cava Thrombectomy.” Eur Urol Oncol. 2019;2(6):691–698. doi:10.1016/j.euo.2018.10.005.
17. Shuch B, Crispen PL, Leibovich BC, et al. “Cardiopulmonary bypass and renal cell carcinoma with level IV tumour thrombus: can deep hypothermic circulatory arrest limit perioperative mortality?” BJU Int. 2011;107(5):724–728. doi:10.1111/j.1464-410X.2010.09488.x.
18. Ciancio G, Shirodkar SP, Soloway MS, et al. “Renal carcinoma with supradiaphragmatic tumor thrombus: avoiding sternotomy and cardiopulmonary bypass.” Ann Thorac Surg. 2010;89(2):505–510. doi:10.1016/j.athoracsur.2009.11.025.
19. Shuch B, Larochelle JC, Onyia T, et al. “Intraoperative thrombus embolization during nephrectomy and tumor thrombectomy: critical analysis of the University of California-Los Angeles experience.” J Urol. 2009;181(2):492–498. doi:10.1016/j.juro.2008.10.036.
20. Calderone CE, Tuck BC, Gray SH, et al. “The role of transesophageal echocardiography in the management of renal cell carcinoma with venous tumor thrombus.” Echocardiography. 2018;35(12):2047–2055. doi:10.1111/echo.14187.
21. Amparore D, Pandolfo SD, Bertolo R, et al. "Surgical Management of Nonmetastatic Renal Cell Carcinoma with Inferior Vena Cava Thrombus: A Systematic Review and Network Meta-analysis." Eur Urol Oncol. 2026;9(3):660–672. doi:10.1016/j.euo.2026.01.007
22. European Association of Urology. "EAU Guidelines on Renal Cell Carcinoma." EAU Guidelines. 2026. Disease management.
23. Dellaportas D, Arkadopoulos N, Tzanoglou I, et al. "Technical Intraoperative Maneuvers for the Management of Inferior Vena Cava Thrombus in Renal Cell Carcinoma." Front Surg. 2017;4:48. doi:10.3389/fsurg.2017.00048.
24. Mata M, Tabbara MM, Alvarez A, González J, Ciancio G. "Renal cell carcinoma with an uncoiling tumor thrombus: intraoperative shift from level III to level IV." World J Surg Oncol. 2024;22:76. doi:10.1186/s12957-024-03355-z.
25. Bigot P, Boissier R, Khene ZE, et al. "French AFU Cancer Committee Guidelines - Update 2024-2026: Management of kidney cancer." Fr J Urol. 2024;34(12):102735. doi:10.1016/j.fjurol.2024.102735.
26. Bertail T, Khene ZE, Fleury R, et al. "Is Preoperative Anticoagulation in Nephrectomy with Caval Thrombectomy Necessary? A Multicenter Retrospective Cohort Study." Eur Urol Open Sci. 2025;80:14–20. doi:10.1016/j.euros.2025.08.002.