Bladder Flap Family
Bladder flaps mobilize full-thickness or partial-thickness bladder wall on a vascular pedicle to bridge defects in the ureter, urethra or bladder neck, or to repair fistulae. The family includes the Boari flap, spiral bladder muscle flap and laparoscopic bladder flap for ureteral reconstruction, the rotational bladder flap for complex or recurrent VVF, and bladder wall–based flaps for female urethral and bladder-neck reconstruction. A psoas hitch is a companion mobilization maneuver for ureteral reimplantation and is not itself a tubularized bladder flap.[1][2][3]
This is the foundations-level family page. For the operative deep-dive on Boari flap and psoas hitch as a treatment-atlas technique, see Boari Flap & Psoas Hitch. For ileal substitution when bladder flaps are insufficient, see Ileal Ureter.
Why a Bladder Flap?
The bladder sits in continuity with the urinary tract, has a rich arterial supply (superior, inferior and middle vesical arteries with extensive collateral), and offers stretchable, urothelium-lined tissue that handles urine natively, which makes it a natural source for ureteral and urethral reconstruction. The trade-offs are:
- Potential capacity loss. A substantial flap borrows wall from the reservoir; assess baseline capacity and tissue quality
- New lower urinary tract symptoms (LUTS). These occurred in 8/29 women (27.6%) in one retrospective Boari-flap cohort, many of whom also received a psoas hitch.[4]
- Finite reach. Select a tension-free option according to bladder mobility, capacity, vascularity and defect length; longer defects may require a specialized bladder-flap variant or intestinal substitution
For cross-cutting bladder reconstruction principles see Augmentation Principles and Continent Catheterizable Channels.
Bladder Flap Variants
1. Psoas hitch — the workhorse for distal ureteral defects
The bladder is fully mobilized in the Space of Retzius, and the contralateral superior vesical pedicle may be divided for additional length. The bladder dome is pulled cephalad and sutured to the ipsilateral psoas tendon or muscle, taking care to avoid the nearby genitofemoral nerve; the ureter is reimplanted medially into an immobilized portion of the bladder without tension.[3][5][18]
| Series | n | Reported outcome | Notes |
|---|---|---|---|
| Riedmiller 1984[5] | 181 | 96.7% success | Original large series; indications included distal ureteral defects, congenital anomalies and reflux, and a long submucosal tunnel was used |
| Manassero 2012[6] | 24 | 22/24 (91.6%) normal renal imaging at mean 53 mo | Defects 3–10 cm; no reinterventions |
| ACS Best Practices | — | Up to 97% reported (citing prior series) | Described as a mainstay for lower ureteral injuries[3] |
Contraindications. Neurogenic bladder dysfunction, severely reduced bladder capacity and a frozen pelvis that prevents mobilization.[5]
2. Boari flap — extending reach to the mid-ureter
The bladder is opened on its anterior surface to raise a broad-based, vascularized flap toward the remaining ureter. The ureter is anastomosed to the flap near its apex, and the flap is tubularized into a neoureter over a stent. Andrade's demonstration creates a submucosal anti-reflux tunnel, whereas Li omitted the tunnel for the spiral bladder muscle flap. The remaining bladder defect is closed without tension.[1][12] The Uebelhoer modified Boari flap (UBBF) uses an arcuate incision to create a triangular flap, described to address the reduced vascularization and mobility of the classic rectangular flap in pretreated patients (12-patient series, most with prior oncologic surgery or radiotherapy).[7]
Indications:
- Distal and mid-ureteral strictures (iatrogenic, radiation-induced, oncologic). In previously irradiated patients, assess bladder capacity, lower urinary tract function and tissue vascularity before choosing a Boari flap; a small, dysfunctional or poorly vascularized bladder may favor non-bladder reconstruction or urinary diversion.[22]
- Ureteral injuries distal to the iliac vessels when psoas hitch alone is insufficient
- Ureteral defects of roughly 10–15 cm in commonly quoted operative teaching, depending on bladder mobility and capacity[21]; the ACS guideline gives no reach figure and describes the Boari flap only as an option for mid-to-lower injuries too long for a psoas hitch[3]
Outcomes
| Series | n | Reported outcome | Notes |
|---|---|---|---|
| Corse 2023 (multi-institutional robotic)[8] | 50 | 45/50 (90%) | Median follow-up 15 mo; five observed failures within 2 mo |
| Mauck 2011 (single-surgeon open)[9] | 20 Boari flaps within 29 reconstructions | Not separately reported for the 20 flaps in the abstract | Overall group failure 17% proximal vs 12% distal; 83% proximal was the proportion receiving a Boari flap, not its success rate |
| Dell'Oglio 2021 (robotic)[10] | 37 (81% psoas hitch, 19% Boari flap) | — | Median OR 180 min; EBL 100 mL; 0 conversions; 27% any complication (22% Clavien I–II, 5.4% grade III); median follow-up 24 mo. Results are not reported separately for the Boari subgroup |
| Hardesty 2024 (women)[4] | 29 | — | 8/29 (27.6%) new-onset LUTS managed with anticholinergics; 2/29 (6.9%) ureteral stricture; retrospective single-center cohort |
Repair principles: tension-free anastomosis, adequate flap length to compensate for the ureteral defect, preservation of the contralateral bladder pedicle (or deliberate ligation of the contralateral superior vesical pedicle for additional mobilization) and stented repair.[1][3]
3. Combined Boari flap + psoas hitch
When ureteral defects exceed what either technique alone can bridge, the two are combined for mid-to-upper ureteral injuries within bladder-flap reach. The ACS 2025 Best Practices Guidelines describe the Boari flap as a "highly technical reconstructive procedure generally performed by urologists" that is rarely used in the acute trauma setting, where a damage control approach is recommended for such complex situations.[3]
For full-length defects exceeding 20 cm, the Boari flap and psoas hitch can be combined with ileal ureter replacement to reduce the length of intestinal graft required (Zhong 2017, 3 patients).[11]
4. Spiral bladder muscle flap — full-length ureter without intestine
A specialized technique for full-length ureteral defects (> 20 cm) that avoids intestinal segments. An S-shaped incision is made along the bladder wall following the course of the superior vesical arteries, creating a long vascularized muscle flap (basal width about 2–3 cm, total length 1–2 cm longer than the defective ureter). The flap is tubularized and anastomosed to the renal pelvis proximally; kidney descent and psoas hitch are performed to reduce tension.[12]
Li's spiral flap preserves superior-vesical-artery pedicles and uses bladder tissue without an intestinal segment.[12] Intestinal substitution carries mucus and metabolic risks.[2]
5. Laparoscopic bladder muscle flap
A minimally invasive adaptation of the bladder-flap concept for extensive ureteral avulsion (full-length defects > 20 cm or upper-ureteral avulsion > 10 cm).
Bai 2021. In 10 patients (7 full-length, 3 upper ureteral defects):[13]
- Average operative time 124 min; EBL 92 mL[13]
- At median 18.5-month follow-up (range 3–39 months), stents had been removed in 9/10 patients within six months.[13] The authors report normal voiding and pear-shaped cystography.
- One anastomotic stricture led to ipsilateral nephrectomy after one year; durable renal-unit preservation requires follow-up beyond stent removal
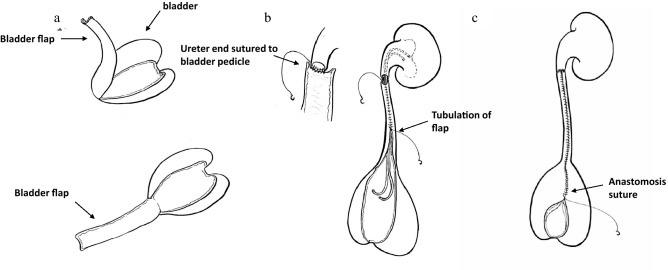
Laparoscopic bladder flap for a full-length ureteral defect: (a) raising the bladder flap; (b) suturing the ureteral end to the bladder pedicle and tubularizing the flap into a neoureter; (c) completed reconstruction from the pelviureteric junction to the ureterovesical junction. From Bai Y, et al. Sci Rep. 2021;11(1):3970, Figure 2 (CC BY).[13]
6. Rotational bladder flap for complex VVF
This distinct application is used for complex, recurrent or giant vesicovaginal fistula. The bladder is bisected sagittally to the fistula, and a full-thickness bladder flap is rotated downward and medially to fill the fistula defect. The vaginal defect is closed separately, and an interposition flap (omentum, peritoneum, gracilis or Martius) is often placed between the bladder and vaginal closures.[14][15] The 2026 EAU guideline weakly recommends interposition for radiation-associated fistula repair and continuous bladder drainage until healing; its 14–21-day range for complex or post-radiation repairs is expert opinion.[24] The 2024 systematic review’s six comparative vaginal-repair studies (n = 924) yielded RR 0.98 (95% CI 0.96–1.01) for fistula closure with versus without interposition.[20]
| Series | n | Indication | Success |
|---|---|---|---|
| Ezzat 2009[15] | 35 | Giant VVF (28 large VVF, 7 with loss of the urethral floor; obstructed labor, iatrogenic, sling erosion, radiation); interposition flap in 23 | 88% (31/35) first-attempt closure |
| Chen 2016[14] | 18 | Iatrogenic VVF (12 recurrent) — rotational bladder flap + peritoneal interposition | 17/18 (94%) without recurrent VVF at mean 20 mo (range 6–36) |
| Sharifiaghdas 2012[16] | 10 | Recurrent mixed trigonal-supratrigonal VVF | 90% (9/10) |
The technique has been reported for fistulae near the trigone (Sharifiaghdas' mixed trigonal-supratrigonal series); ureteral reimplantation was needed in 1 of 18 patients in Chen's series.[14][16]
7. Bladder wall flaps for female urethral / bladder-neck reconstruction
Anterior or posterior bladder wall–based flaps reconstruct complex female urethral defects involving the bladder neck.
Patidar 2021. In 22 patients (16 anterior, 6 posterior bladder flaps), 18/22 (82%) were socially dry: 15 were completely continent and 3 had minimal stress incontinence managed conservatively. Four had postoperative incontinence, and 2 developed voiding difficulty requiring self-calibration.[17]
Comparison of Bladder-Flap Techniques for Ureteral Reconstruction
| Technique | Defect length | Reported outcome | Key advantage | Key limitation |
|---|---|---|---|---|
| Psoas hitch alone | Up to 10 cm in Manassero's series | 22/24 normal imaging (Manassero)[6]; up to 97% reported by ACS[3] | Established bladder mobilization with reimplantation | Limited reach for proximal defects |
| Boari flap | Often ~10–15 cm; individual reach varies | 45/50 success in Corse's robotic series[8] | Bridges longer defects than hitch alone | Potential capacity/LUTS trade-off; specialized technique |
| Boari + psoas hitch | Reach depends on mobilization and bladder capacity | No separate pooled rate established here | Combines bladder advancement and tubularized flap | More bladder wall mobilization; operative complexity |
| Spiral bladder muscle flap | > 20 cm (full-length) | Technical report | Avoids intestinal segment entirely | Technically demanding; limited data |
| Laparoscopic bladder flap | Full-length or upper avulsion in a 10-patient series | 9/10 stents removed within 6 mo[13] | Avoids bowel interposition in selected patients | Small series; one nephrectomy; follow-up 3–39 mo |
| Boari + ileal ureter | > 20 cm (full-length) | 3-patient series | Minimizes ileal-graft length | Combines two complex procedures |
Complications Common to Bladder-Flap Procedures
- Urinary symptoms. Hardesty reported new-onset LUTS in 8/29 women (27.6%), managed with anticholinergics.[4] In a separate cohort of 81 bladder-flap recipients (50 women), 12/81 (15%) began persistent medication for bladder symptoms and 9/81 (11%) reported reflux-related flank pain at median 2.3-year follow-up; 56/81 answered the postoperative symptom survey.[19]
- Reduced bladder capacity. This is more likely with large flaps or combined procedures.
- Urinary extravasation and Boari flap necrosis. Leakage after ureteral reconstruction warrants prompt evaluation and urinary drainage. Boari flap necrosis has been reported after radiation-associated reconstruction and can require diversion; prior surgery or retroperitoneal fibrosis may also compromise flap perfusion.[23]
- Ureteral stricture or obstruction. 2/29 in Hardesty's Boari cohort; five failures (a broader endpoint) among 50 robotic Boari reconstructions in Corse; Mauck reported 17% versus 12% overall failure by proximal versus distal group.[9][4][8]
- UTI and pyelonephritis. Recurrent UTI occurred in 17% of one Boari series.[4]
- Vesicoureteral reflux. An anti-reflux tunnel may be incorporated, but bladder compliance can also affect the consequences of reflux. In Findlay's cohort, one radiated patient with a solitary kidney developed poor bladder compliance and required nephrostomy.[1][19]
- Higher morbidity with proximal strictures. In Mauck's single-surgeon series, proximal reconstruction had longer LOS (8.0 versus 4.4 days) and greater EBL (447 versus 224 mL), with complications in 75% versus 35% (p = 0.060).[9]
Current Guidelines
The American College of Surgeons 2025 Best Practices Guidelines for Genitourinary Injuries state that ureteral reimplantation is the recommended practice for repair of injuries distal to the iliac vessels whenever possible, and that a psoas hitch or Boari flap can be employed to ensure a tension-free repair. They describe the Boari flap as a "highly technical reconstructive procedure generally performed by urologists" that is rarely used in the acute trauma setting, where a damage control approach is recommended for complex situations.[3]
Key Takeaways
Bladder-wall mobilization and flaps are reconstructive options for the lower and mid ureter. A psoas hitch brings the bladder toward the distal ureter, and a Boari flap can extend reconstruction to selected longer or more proximal defects. Outcome definitions and follow-up differ between series: Manassero reported normal imaging in 22/24 hitch patients, while Corse reported success in 45/50 robotic Boari patients.[6][8] For extensive ureteral defects, spiral[12] and laparoscopic bladder muscle flaps[13] are reported alternatives to intestinal interposition in selected small series, and combined Boari flap and ileal-ureter techniques can reduce the intestinal graft length.[11] Small VVF rotational-flap series reported differing first-repair and recurrence outcomes, including 17/18 closures in Chen's iatrogenic cohort.[14][15][16] Patidar reported 18/22 women socially dry after bladder-wall-flap urethral and bladder-neck reconstruction.[17]
Counsel about potential capacity changes, urinary symptoms, obstruction and the uncertainty of small-series outcomes.[4] Hardesty's 27.6% new-LUTS figure applies to its 29-woman Boari cohort.[4]
See Also
- Flaps in GU Reconstruction
- Boari Flap & Psoas Hitch: operative deep-dive
- Ureteral Reimplantation
- Ileal Ureter
- Ureteral Stricture
- Vesicovaginal Fistula
- Augmentation Principles
- Y-V plasty: bladder-wall geometric variant for BNC and VUAS
References
1. Andrade C, Narducci F, Bresson L, Leblanc E. Boari flap ureteroneocystostomy in an oncological patient. Gynecol Oncol. 2016;143(1):193. doi:10.1016/j.ygyno.2016.07.115
2. Xiong S, Zhu W, Li X, et al. Intestinal interposition for complex ureteral reconstruction: a comprehensive review. Int J Urol. 2020;27(5):377–86. doi:10.1111/iju.14222
3. Johnsen N, Wessells H, Archer-Arroyo K, et al. Best Practices Guidelines: Management of Genitourinary Injuries. American College of Surgeons; 2025. facs.org/media/ya5hcu0s/genitourinary_guidelines.pdf
4. Hardesty JK, Burns RT, Soyster ME, Jansen NE, Mellon M. Female bladder dysfunction following Boari bladder flap ureteral reconstruction. Urology. 2024;186:31–5. doi:10.1016/j.urology.2024.01.020
5. Riedmiller H, Becht E, Hertle L, Jacobi G, Hohenfellner R. Psoas-hitch ureteroneocystostomy: experience with 181 cases. Eur Urol. 1984;10(3):145–50. doi:10.1159/000463777
6. Manassero F, Mogorovich A, Fiorini G, et al. Ureteral reimplantation with psoas bladder hitch in adults: a contemporary series with long-term followup. ScientificWorldJournal. 2012;2012:379316. doi:10.1100/2012/379316
7. Radtke JP, Korzeniewski N, Huber J, et al. Ureterocystoneostomy in complex oncological cases with an "Uebelhoer" modified Boari bladder flap. Langenbecks Arch Surg. 2017;402(8):1271–8. doi:10.1007/s00423-017-1554-0
8. Corse TD, Dayan L, Cheng N, et al. A multi-institutional experience utilizing Boari flap in robotic urinary reconstruction. J Endourol. 2023;37(7):775–80. doi:10.1089/end.2022.0618
9. Mauck RJ, Hudak SJ, Terlecki RP, Morey AF. Central role of Boari bladder flap and downward nephropexy in upper ureteral reconstruction. J Urol. 2011;186(4):1345–9. doi:10.1016/j.juro.2011.05.086
10. Dell'Oglio P, Palagonia E, Wisz P, et al. Robot-assisted Boari flap and psoas hitch ureteric reimplantation: technique insight and outcomes of a case series with ≥ 1 year of follow-up. BJU Int. 2021;128(5):625–33. doi:10.1111/bju.15421
11. Zhong W, Du Y, Yang K, et al. Ileal ureter replacement combined with Boari flap-psoas hitch to treat full-length ureteral defects: technique and initial experience. Urology. 2017;108:201–6. doi:10.1016/j.urology.2017.07.014
12. Li Y, Li C, Yang S, et al. Reconstructing full-length ureteral defects using a spiral bladder muscle flap with vascular pedicles. Urology. 2014;83(5):1199–204. doi:10.1016/j.urology.2014.01.027
13. Bai Y, Wei H, Ji A, et al. Reconstruction of full-length ureter defects by laparoscopic bladder flap forming. Sci Rep. 2021;11(1):3970. doi:10.1038/s41598-021-83518-0
14. Chen Y, Yu W, Yang Y, et al. Repair of complex vesicovaginal fistulas by combining a rotational bladder flap and full thick vascular peritoneal interposition. Neurourol Urodyn. 2016;35(8):934–8. doi:10.1002/nau.22828
15. Ezzat M, Ezzat MM, Tran VQ, Aboseif SR. Repair of giant vesicovaginal fistulas. J Urol. 2009;181(3):1184–8. doi:10.1016/j.juro.2008.10.152
16. Sharifiaghdas F, Taheri M. The use of a rotational bladder flap for the repair of recurrent mixed trigonal-supratrigonal vesicovaginal fistulas. Int J Gynaecol Obstet. 2012;119(1):18–20. doi:10.1016/j.ijgo.2012.04.026
17. Patidar V, Dias S, Prakash S, et al. Results of bladder neck reconstruction using bladder flaps in complex female urethral defects. Int Urogynecol J. 2021;32(3):665–71. doi:10.1007/s00192-020-04538-4
18. Pugh J, Farkas A, Su LM. "Robotic distal ureterectomy with psoas hitch and ureteroneocystostomy: Surgical technique and outcomes." Asian J Urol. 2015;2(2):123–127. doi:10.1016/j.ajur.2015.04.017
19. Findlay BL, Fadel A, Miller AJ, et al. "Urinary Quality of Life Outcomes Following Bladder Flap Reconstruction for Ureteral Strictures." Urology. 2026;211:102–106. doi:10.1016/j.urology.2026.02.017
20. Thompson JC, Halder GE, Jeppson PC, et al. "Repair of Vesicovaginal Fistulae: A Systematic Review." Obstet Gynecol. 2024;143(2):229–241. doi:10.1097/AOG.0000000000005468
21. Nakada SY, Hsu THS. "Management of Upper Urinary Tract Obstruction." In: Wein AJ, et al., eds. Campbell-Walsh Urology. 10th ed. Saunders; 2012:1122–1168.e7. doi:10.1016/B978-1-4160-6911-9.00041-4
22. Bourillon A, Peyronnet B, McGuire BB, et al. "Ureteral stricture: current treatment algorithm and key surgical principles in the robotic upper urinary tract reconstruction era." World J Urol. 2026;44(1):102. doi:10.1007/s00345-025-06181-4
23. Rosenfeld J, Boehm D, Raikar A, et al. "A review of complications after ureteral reconstruction." Asian J Urol. 2024;11(3):348–356. doi:10.1016/j.ajur.2024.02.007
24. European Association of Urology. "EAU Guidelines on Non-neurogenic Female LUTS." EAU Guidelines Office; 2026. Disease management, section 4.8