Gracilis Flap
The gracilis provides vascularized medial-thigh tissue for perineal fistula interposition, support of a compromised urethral graft bed, and selected pelvic or genital defects. A proximally pedicled muscle flap usually reaches the perineum without microvascular anastomosis. Whether it supplies enough bulk, skin and reach depends on the defect and the patient's anatomy.[1][2]
See Flaps in GU Reconstruction for flap selection and The Leg & Thigh for regional anatomy.
Anatomy That Determines the Operation
| Structure | Operative relevance |
|---|---|
| Muscle | Superficial medial-thigh adductor, with proximal attachment to the pubic body/inferior pubic ramus and distal insertion on the proximal medial tibia as part of the pes anserinus. Distinguish its distal tendon from sartorius and semitendinosus. |
| Dominant vascular pedicle | A proximal pedicle from the deep femoral/adductor arterial system; descriptions include medial circumflex femoral contributions. A named artery or fixed surface distance does not replace identification of the actual pedicle. |
| Accessory pedicles | Distal branches, commonly from the superficial femoral system. These may need division to mobilize a proximally based flap, after its dominant supply is identified and protected. |
| Venous drainage | Paired venae comitantes; proximal convergence may provide a larger vein when free transfer is planned. |
| Motor nerve | Branch of the obturator nerve, usually from its anterior division, entering near the dominant pedicle and branching longitudinally within the muscle. |
Anatomical studies use different landmarks and methods. The gracilis is a Mathes–Nahai type II muscle, with one dominant pedicle and several minor pedicles.
- Macchi (CT angiography, 40 patients, mean age 63 years). Mean muscle length was 41 ± 2.1 cm. The dominant pedicle entered approximately 10 ± 1 cm from the ischiopubic attachment, with a mean caliber of 2.5 ± 0.5 mm. It arose directly from the deep femoral artery in 45% and from the artery to the adductors in 46%, and it was larger when it arose directly from the deep femoral artery. The mean number of distal accessory pedicles was 1.8 (range 1–4), and the first accessory pedicle had a mean caliber of 2.0 mm.[3]
- Morris (14 cadavers). The musculotendinous unit measured 44 ± 2 cm, including up to 6 ± 2 cm of tendon. The main pedicle entered 10 ± 1 cm from the pubic attachment (diameter 1.5–2.5 mm), and one to three small branches of the superficial femoral artery supplied the distal muscle. The obturator nerve entered with the major pedicle and ran within the muscle in two or three longitudinal branches parallel to the arterial branches; the authors conclude that this consistent anatomy suits segmental functional muscle transfer.[4]
- Magden (30 dissections). The deep femoral artery was the dominant pedicle in 87% and the medial circumflex femoral artery in 13%. Distal pedicles from the superficial femoral artery were present in all specimens (double in 77%) and entered about 266 mm from the pubic tubercle.[5]
- Whetzel (cadaver study). The pedicle was described as the medial femoral circumflex artery, with connections to fasciocutaneous perforators from the superficial femoral artery that supply the overlying skin.[9]
Naming of the dominant pedicle therefore differs between studies.
Match Nerve Handling to the Reconstruction
- Static interposition or coverage: decide whether to preserve or divide the motor branch as part of the selected technique. Denervation can cause atrophy.
- Innervated pedicled transfer: preserve the required motor connection in continuity when contraction is part of the intended function.
- Distant free functional transfer: plan vascular anastomoses and motor-nerve coaptation. This differs from simply rotating a pedicled muscle into the perineum.[4][7][8]
Pedicled Harvest and Transfer Principles
The exact dissection depends on muscle-only versus myocutaneous design, required reach and the recipient repair. The following is an operative planning framework; the dedicated procedure and flap design determine the details.[1][2]
- Assess both donor and recipient sites. Review medial-thigh operations, vascular disease, prior irradiation, tissue loss and available alternatives. Position and prepare the thigh so the tendon and perineum are accessible without excessive abduction or pressure injury. Selective vascular imaging can help when anatomy or previous surgery raises concern; routine CT angiography has not been established for every uncomplicated pedicled transfer.[3][2]
- Identify the muscle and dominant pedicle directly. Use the adductor longus and the medial-thigh anatomy to guide exposure. Preserve the fascia needed for any planned skin paddle and do not strip it indiscriminately.[6][9]
- Mobilize only the tissue needed. Distal tendon release and selective division of accessory vessels permit rotation while the dominant proximal supply remains intact. Tailor further proximal release or extended pedicle dissection to the required reach, with nerve handling matched to the functional plan.[1][2]
- Create a generous transfer tunnel. Avoid twisting, traction, compression or an acute turn of the pedicle. Check reach and perfusion with the leg in its expected postoperative position.[1][2]
- Inset for the recipient problem. For fistulas, independently repair the involved organs and place viable muscle between the closures. For urethral support, provide a vascular bed without constricting the lumen. For pelvic defects, fill the appropriate dead space and obtain skin closure without undue tension.[10][11][2]
- Plan wound and drainage care around the repair. Check donor and recipient wounds for hematoma, infection, ischemia and leakage. Drain removal, catheter duration and activity restrictions depend on output, healing, recipient anatomy and the reconstruction.[12][13][2]
The microsurgeon.org atlas is an additional anatomical resource; its free-flap harvest and recipient-specific postoperative instructions need adaptation to a pedicled GU reconstruction.
Positioning and Marking
- Position the patient supine with the leg prepped to the groin, the thigh abducted and externally rotated and the knee slightly flexed (frog-leg position).
- Palpate the adductor longus with the thigh abducted. The gracilis lies about two to three finger breadths posterior to it, which is the surface guide commonly taught for the incision. Mark the axis from the pubic attachment toward the medial tibial condyle.
- The dominant pedicle enters about 10 cm from the ischiopubic attachment, so the incision must extend distal to this point.[3][4]
- A separate distal incision near the medial tibial condyle can be used to divide the tendon when full muscle length is needed. Identify the gracilis tendon at its insertion and distinguish it from sartorius and semitendinosus.
Standard Open Harvest Sequence
The following is the commonly described sequence. Individual surgeons vary the details.
- Incise skin and subcutaneous tissue to the muscle fascia. For a muscle-only flap, open the fascia to expose the gracilis. For a myofasciocutaneous flap, elevate the skin paddle with underlying fascia in continuity with the deep fascia around the gracilis to preserve the connecting vascular network.[9][58]
- Identify the septum between the gracilis and the adductor longus and enter the fascial cleft. The dominant pedicle lies on the medial aspect of the gracilis in the cleft between the adductor longus and the adductor magnus.[6]
- Trace the pedicle proximally. Dividing the small branches to the adductor muscles and passing the gracilis deep to the adductor longus gives more reach (extended dissection).[1][6]
- Free the muscle from its soft-tissue attachments except the pedicle. Divide the distal accessory pedicles after the dominant supply is identified.
- Divide the distal tendon at its insertion or through a distal counter-incision.
- Preserve or divide the obturator nerve branch according to the reconstruction plan (see nerve handling above).
- Tunnel the muscle to the perineum through a generous subcutaneous tunnel or skin bridge, checking the pedicle for twisting and tension.
- Close the thigh in layers over a closed-suction drain.
Postoperative Care
- Oner et al. describe removing the thigh drain usually between 3 and 5 days in their colorectal gracilis-flap technique.[57]
- Ambulation is encouraged as the recipient site allows. The donor site itself does not usually require restricted weight-bearing, and Ducic's extended-dissection series reported no restriction of ambulation or thigh abduction.[1]
- See Pelvic and Perineal Flap Postoperative Care for shared recipient-site positioning, drain management and flap-monitoring principles across perineal flaps.
Useful Variants
| Variant | Role and limitation |
|---|---|
| Extended pedicle dissection | Ducic's series applied extended dissection to 19 pedicled perineal/groin reconstructions in high-risk patients; all reconstructions were successful, with one late donor-site infection. Passing the muscle beneath adductor longus can improve reach; this requires deliberate protection of the vascular supply. The authors report a greater arc of rotation and no restriction of ambulation or thigh abduction.[1] |
| Bilateral gracilis | Adds tissue when one muscle is insufficient and preserves the abdominal donor site. A 50-patient pelvic-oncology series described an interwoven configuration; complete wound healing was reported in 42/49 surviving patients at follow-up. Donor-site and perineal complication rates were 14% and 22%, and flap integrity was maintained on follow-up imaging.[14] |
| Myofasciocutaneous flap | Includes the associated fascia and skin. Whetzel–Lechtman's anatomical work and 12-patient/18-flap experience support preserving the fascial vascular network. The 18 flaps in previously irradiated patients were up to 8 cm wide and 30 cm long, with no partial or complete flap necrosis and minor complications in 6 of 12 patients (mean follow-up 12.1 months).[9] |
| Bilobed design | Adds an adjacent soft-tissue arm. The original six-reconstruction report establishes a technical option.[15] |
| Robotic harvest | Described for free gracilis transfer.[16] |
Fistula Interposition
Gracilis is an established option for complex or recurrent rectourethral and selected rectovaginal fistulas, especially when the local tissues are scarred or irradiated. The 2022 ASCRS guideline typically recommends gracilis or Martius interposition for recurrent or otherwise complex rectovaginal fistulas .[55] The exposure, diversion strategy and choice of interposition depend on fistula level, associated stenosis, tissue quality, prior repairs and bowel and bladder function.[17][10][18] For post-traumatic posterior urethroplasty with excessive dead space or a concomitant rectourethral fistula, the EAU 2026 guideline gives a Weak recommendation for a local tissue flap; gracilis is one listed option.[60]
What the Outcome Numbers Mean
The 2023 Garoufalia systematic review included 25 studies and 658 patients with mixed complex perineal fistulas. Its pooled 79.4% healing rate included additional procedures, with substantial heterogeneity. In the five studies reporting initial repair separately, pooled success after the index gracilis operation was 62.8%, increasing to 84.5% after further treatment; those additional procedures were often advancement flaps rather than another gracilis transfer. The review rated healing evidence very low certainty.[19]
| Series | Findings and counseling limits |
|---|---|
| Wexner 2008 | Among 36 men with rectourethral fistulas in a 53-patient mixed cohort, initial success was 78% and final clinical healing 97% after additional procedures. The final rate includes further treatment.[17] |
| Vanni 2010 | 74 repairs, 68 using gracilis, with selective buccal onlay. At mean 20-month follow-up, single-stage closure was 100% in 35 nonirradiated cases and 84% in 39 radiation/ablation cases. In the latter group, 31% required permanent fecal diversion. Closure and reversal of diversion are separate outcomes.[18] |
| Sbizzera 2022 | At median 27-month follow-up, fistula closure was 20/21 after prostate-cancer treatment, while digestive stomas were closed in 10/12 diverted patients. Of 18 postoperative questionnaire respondents, 11 reported significant urinary incontinence.[10] |
| Higashino 2021 | 38 colorectal or urinary-tract-related fistulas repaired with vascularized tissue (gracilis in 19, gluteal fold flap in 13). Fistulas were cured in 31/38 (13/17 rectovaginal, 14/16 urorectal, p = 0.656), with a major leak in nine. Mixed flaps and fistula types.[42] |
| Zmora 2006 | Nine patients (five rectovaginal, three rectourethral, one pouch-vaginal), all with fecal diversion. At median follow-up of 14 months since stoma closure, fistulas had healed in 7 of 8 patients who underwent closure; one patient refused closure.[43] |
| Park 2022 | Retrospective comparison: recurrence 8% in 24 gracilis repairs versus 50% in 12 controls.[20] |
For rectovaginal fistulas, Wexner's series reported healing in 75% of non-Crohn's fistulas and 33% of Crohn's-associated fistulas, with 76% of the women having had prior failed repairs.[17] A 2023 rectovaginal-only systematic review pooled fistula closure at 64% (95% CI 53%-74%) across 20 mostly small series (384 patients); sexual-function impairment was commonly reported.[56] A three-center retrospective comparison of 62 patients (55 Martius and 24 gracilis procedures) reported absence of both fistula and stoma in 69% of each group at median 23-month follow-up, versus immediate success of 35% and 31%, respectively; total hospital stay was two days longer with gracilis.[61] Paprottka's retrospective series reported final fistula treatment in all 12 selected patients (five VRAM and eight gracilis flaps, after at least two failed repairs), with mean follow-up of 6.3 years.[44] Continence was restored in all seven gracilis patients assessed, whereas the three VRAM patients had slight incontinence; the series is small and selected.[44]
A 2026 systematic review of post-prostatectomy rectourinary fistulas identified 455 cases across 34 studies, with heterogeneous surgical outcomes. The authors' flowchart proposes an approach to heterogeneous fistulas, without a validated ranking of approaches or flaps.[21] In a four-center retrospective rectourethral-fistula cohort (30 transperineal gracilis repairs and 27 York Mason repairs), first-attempt closure was 77% versus 44%, and 12-month reintervention-free survival was 94.7% versus 68.2%, respectively; median follow-up was 39 months.[59]
Early leakage requires reassessment of the repair and drainage. Chen's small prospective series reported initial healing in 14/19 mixed fistulas and eventual healing in 18/19 after selected irrigation-suction salvage. There was no control group for salvage, and one patient required diversion with persistent fistula.[13]
Urethral Reconstruction
Same-Stage Buccal Graft Support
The muscle can provide vascularized coverage for a ventral buccal mucosa onlay in selected long strictures with compromised local tissue.[11] Rozanski–Vanni's updated retrospective cohort included 30 patients, with patency in 23/30 at mean 32-month follow-up and seven patients requiring an artificial urinary sphincter postoperatively.[11] The earlier 20-patient report and updated 30-patient experience should not be added as independent cohorts; “20-year experience” describes the treatment period, not 20-year follow-up for every patient.[22][11]
Palmer's earlier report from the same institution (20 patients, mean stricture length 8.2 cm; 45% radiation etiology, 45% prior urethroplasty, 15% prior UroLume stent) had success in 16/20 (80%) at mean 40 months, with 5 patients (25%) needing an artificial urinary sphincter.[22] Recurrence was defined as inability to pass a 16 Fr cystoscope in Palmer’s earlier 20-patient cohort, compared with 17 Fr in the updated 30-patient cohort.[22][11] A single 1996 case report described a 12-cm bulbar and penile urethral defect after Fournier's gangrene reconstructed with a proximally pedicled gracilis flap alone; it healed without stricture or leak, and urethral biopsies showed uroepithelial migration across the defect.[45]
See Ventral BMG with Gracilis Support for the urethral operation.
Staged Prelaminated Gracilis–Buccal Composite
This is a distinct salvage technique for a devastated bulbar urethra. In the original case, stage 1 created a dorsal buccal plate on the corporal bed and a temporary perineal outlet, while a second buccal graft was quilted onto distal gracilis. Eight weeks later, the vascularized muscle–mucosa composite was transferred to form the ventral plate.[2]
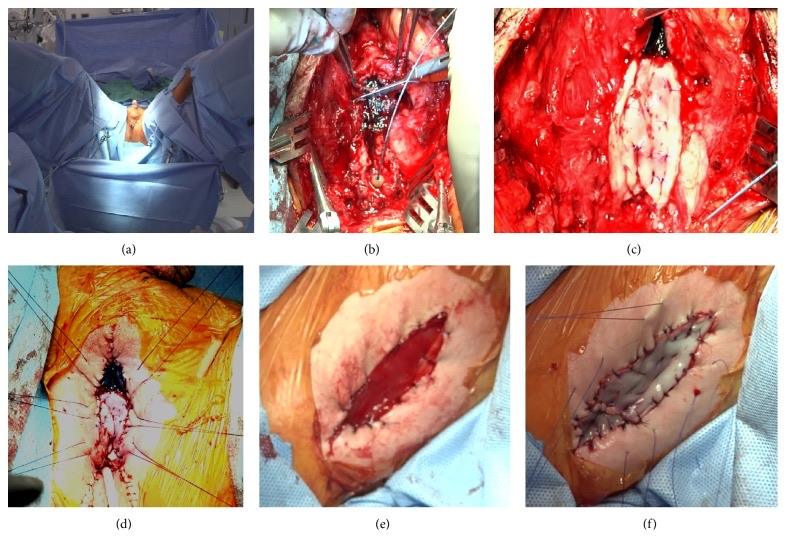
Stage 1: (a) positioning with access to the perineum and left inner thigh; (b) transection of the affected urethral plate; (c) dorsal plate augmented with buccal mucosa; (d) augmented perineal urethrostomy with catheter in place, ready for the tie-over dressing; (e) exposed distal gracilis; (f) buccal mucosa quilted onto the gracilis. From Nikolavsky D. Case Rep Urol. 2015;2015:490518, Figure 2 (CC BY).[2]
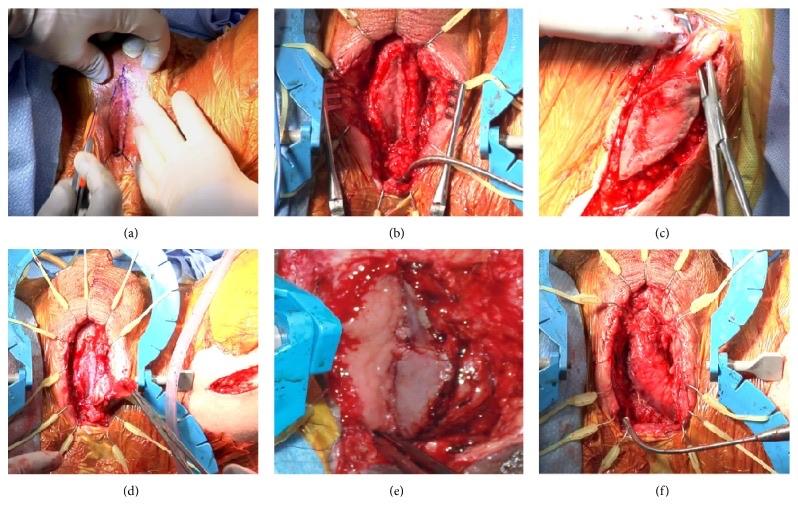
Stage 2: (a) engrafted perineal urethrostomy at 8 weeks; (b) dorsal plate dissected; (c) harvest of the gracilis-buccal mucosa composite; (d) gracilis tunneled into the perineal incision; (e) dorsal (left) and ventral (right) plates anastomosed on the left side; (f) completed anastomosis of the ventral and dorsal hemi-plates. From Nikolavsky D. Case Rep Urol. 2015;2015:490518, Figure 3 (CC BY).[2]
The subsequent two-center series contained five patients, with no reported recurrence at mean 61-month follow-up and a mean 6.2-week interval between stages. Discuss permanent perineal outlet and urinary diversion alongside reconstruction.[23]
See Laminated Gracilis Flap Urethroplasty for the staged concept and follow-up.
Pelvic, Perineal and Genital Coverage
After APR or Pelvic Exenteration
Gracilis may be useful when preserving the abdominal wall matters, abdominal donor sites are unavailable, or the defect can be filled with one or both thigh muscles. VRAM and other regional flaps remain options when greater bulk, skin or reach is required.[24][14][1]
Selected perineal reconstruction series:
| Series | Design | Findings |
|---|---|---|
| Chong 2015 | 16 consecutive APRs (10 with pelvic exenteration), all after neoadjuvant chemoradiation; 6 bilateral flaps | One major perineal wound complication, from a pelvic anastomotic leak, managed with dressing changes. Three patients had skin separation greater than 5 mm. No operative debridement, revision, perineal hernia or gross dehiscence.[41] |
| Singh 2016 | 40 patients, single surgeon, mean follow-up 2 years | Donor-site complications 12.5% (5) and recipient-site complications 40% (16); minor 25%, major 17.5%; no 30-day deaths.[37] |
| Jenkins 2023 | 50 patients, bilateral gracilis reconstruction after extralevator APE | Complete perineal wound healing 86% (42/49); donor-site complications 14%, perineal 22%; 30-day mortality 2%.[14] |
| Rinkinen 2024 | 101 patients, mean follow-up 75 months | Early major complications 7.9%, late major 12.9%, minor 32.7%; 91.1% had no donor-site complication.[12] |
Single-surgeon and single-center series predominate.
The 2022 VRAM–gracilis proportional meta-analysis mainly pooled separate cohorts rather than direct comparisons. Its overall donor-complication analysis included only 56 gracilis and 240 VRAM patients, with inconsistent outcome definitions and important heterogeneity. It reported pooled overall donor-site complication proportions of 16.0% (95% CI 5.8–29.5%) for gracilis and 57.6% (95% CI 38.7–75.4%) for VRAM, with wide intervals and no significant difference in minor or major recipient-site complications or in flap necrosis. Some wound-dehiscence estimates favored VRAM. Defect requirements, donor anatomy, planned stomas and surgical experience guide flap selection.[24]
For persistent perineal wounds after proctectomy in IBD, the 2026 Pelly systematic review found 25 publications, no randomized trials and very low certainty for muscle-flap outcomes. It could not pool healing rates meaningfully. Define the sinus, adjacent bowel involvement and deep infection before selecting local repair, gracilis, a larger flap or combined abdominal and perineal treatment.[25]
Vulvovaginal and Penoscrotal Defects
Myocutaneous gracilis can replace selected vulvar or vaginal tissue, including neovaginal reconstruction after exenteration. Historical experience includes substantial skin necrosis, wound breakdown and prolapse. Goals, required lining, available tissue, hair-bearing skin and alternative flaps guide selection.[26][27][28]
- Copeland 1989 compared 107 women with gracilis neovaginal reconstruction at total pelvic exenteration with 44 without reconstruction. Reconstruction did not increase operating time, blood loss or length of stay. Neovaginal prolapse occurred in 65% before 1980 (25% severe) and fell to 16% (6% severe) after modifications: smaller flaps, anchoring the neovagina to the levator and retropubic fascia, and ligating the neurovascular pedicle when needed for mobilization. Two-thirds of patients were free of wound breakdown or necrosis after the modifications, and severe necrosis fell from 24% to 13%.[28]
- Short gracilis myocutaneous flaps are based on the muscle's pubic origin and have greater mobility than the classic flap. Unlike the usual proximally pedicled harvest, Soper's short-flap modification deliberately sacrifices the dominant pedicle and relies on terminal obturator branches; major loss occurred in 4/24 short-flap versus 3/22 long-flap recipients in a retrospective comparison, without a significant between-group difference.[53][54] An earlier series reported bilateral flap necrosis in one patient after vulvar and groin irradiation with chemotherapy; its authors advised against the short design after extensive groin irradiation.[53][54] Chen's 16 myocutaneous and 1 muscular flaps for vulvoperineal, inguinal, perineal and ischial defects all had surviving muscle, with partial necrosis of the distal third of the skin in six patients and superficial infection in seven.[26] Burke's 18 single flaps in 17 women had skin necrosis in three and minor wound separation or edge necrosis in five, with a mean hospital stay of 18.4 days.[27]
Transverse myocutaneous skin-island design. A proximal transverse skin island, oriented along the inguinal–infragluteal crease, follows septocutaneous and musculocutaneous perforators from the proximal gracilis pedicle that run transversely and extend beyond the muscle's posterior margin.[51] One described design uses an island approximately 25–30 cm wide and 8–12 cm high at its broadest point, with the anterior tip kept medial to the femoral vessels to limit lymphatic injury, the posterior island elevated suprafascially where feasible to preserve posterior femoral cutaneous branches, and posterior fascia included when comorbidity or a superficial defect calls for added skin-paddle support.[52] Actual dimensions depend on available tissue and pinch testing.[52]
After Fournier's gangrene, muscle may fill a residual deep cavity, while skin grafts or local or perforator flaps provide surface coverage as needed. Hsu reported eight patients with Fournier's gangrene (defects 12 × 7 to 30 × 15 cm) treated with a unilateral gracilis myofasciocutaneous advancement flap, with one hematoma and one donor-thigh abscess. Lee reported seven patients (six Fournier's gangrene, one extramammary Paget's disease) treated with gracilis combined with an internal pudendal artery perforator flap, with all flaps surviving.[29][30] These are reconstructive options after adequate debridement and infection control.[29][30] In a retrospective comparison, filling the perianal dead space of Fournier's gangrene with gracilis was associated with a shorter interval from surgery to discharge (5.1 versus 12.7 days, p = 0.022) and a shorter hospital stay (23.5 versus 31 days) than soft-tissue reconstruction alone.[46] The short gracilis flap, based on the muscle origin at the pubis, was described in two Fournier's gangrene patients for scrotal reconstruction, with greater mobility, no bulky pedicle zone and later atrophy.[47]
Graciloplasty for Continence: Historical and Specialized Uses
Urinary or fecal graciloplasty seeks a functional outlet, a different objective from static fistula interposition.
| Application | Evidence boundary |
|---|---|
| Adynamic urinary wrap | Guo's 24-patient series (after prostatectomy, TURP or posterior urethroplasty) reported 18 cures, 4 improved and 2 failures at mean 31.5 months, with higher postoperative maximum urethral pressure, but five of six patients with severe incontinence did not achieve a good result.[31] Chancellor's 1997 pilot of three men after prostatectomy and radiotherapy reported improved continence at 6 to 24 months, with mean Valsalva leak point pressure rising from 26.3 to 83.0 cm H2O.[8] |
| Electrically stimulated urinary wrap | Janknegt's 1995 pilot included seven patients: three continent, one partially continent and three treatment failures. This remains a small historical feasibility experience.[32] |
| Free-flap urinary neosphincter | Anatomical and canine experiments demonstrated feasibility.[33][34] |
| Dynamic fecal graciloplasty | Baeten reported continence in 38/52 patients. In the later multicenter study, 85/128 graciloplasty patients met a study-specific success endpoint, which was not uniformly complete continence; major wound complications were common.[35][36] |
Morbidity and Follow-Up
Track flap viability, wound healing, fistula closure, urethral patency, continence and quality of life separately. Also record whether repeat procedures or ongoing diversion were needed.[10][11][19]
The donor site can develop dehiscence, seroma, hematoma, infection, sensory symptoms or functional complaints. Preserving other thigh adductors often limits disability. In a later 101-patient perineal-reconstruction cohort, eight patients had early major complications, 13 had late major complications and 33 had minor complications; the study extended earlier institutional experience rather than supplying an independent population to add to it.[37][12]
In Singh's 40-patient series, obesity (OR 7.5) and active smoking (OR 9.3) were associated with minor complications (p = 0.01 for each), and neoadjuvant chemoradiation (OR 21.4, p = 0.04) with any complication.[37]
Optimize smoking, nutrition, diabetes and other modifiable risks; factor prior chemoradiation and donor and recipient tissue quality into planning. Follow-up should address both wounds, the reconstructed organ and the patient's functional goals.[37][12][10]
Other Reconstructive Uses
Free gracilis is also used for limb coverage, breast reconstruction and functional reanimation. Transverse upper gracilis provides limited breast volume; functional transfers require a suitable motor source and rehabilitation. Facial-reanimation reviews found heterogeneous reporting and could not establish one optimal donor nerve; spontaneous smiling has been reported after masseteric innervation, but assessment methods and results vary.[38][39][7][40]
Selected non-GU experience for context: a series of 204 free gracilis transfers for lower-limb reconstruction found no significant difference in major complications between defects smaller and larger than 150 cm² (15.72% versus 10.91%, p = 0.506) when the muscle was enlarged by epimysial dissection;[38] the distally pedicled gracilis salvaged the knee in 8 of 9 patients with complex proximal knee wounds;[48] and for breast reconstruction, Schoeller's 111 patients with 154 transverse gracilis flaps had three complete flap losses and a concealed donor scar,[49] and the fleur-de-lis design was used in 17 patients (31 flaps), with 100% flap success and donor-site dehiscence in 6/31 flaps (19.3%); among 26 donor sites treated with negative-pressure dressings, 2/26 (7.7%) had dehiscence in this observational series.[50]
Videos
References
1. Ducic I, Dayan JH, Attinger CE, Curry P. "Complex Perineal and Groin Wound Reconstruction Using the Extended Dissection Technique of the Gracilis Flap." Plast Reconstr Surg. 2008;122(2):472–478. doi:10.1097/PRS.0b013e31817d607d
2. Nikolavsky D. "Prelaminated Gracilis Flap with Buccal Mucosal Graft for Salvage of Devastated Urethra." Case Rep Urol. 2015;2015:490518. doi:10.1155/2015/490518. Full text.
3. Macchi V, Vigato E, Porzionato A, et al. "The Gracilis Muscle and Its Use in Clinical Reconstruction: An Anatomical, Embryological, and Radiological Study." Clin Anat. 2008;21(7):696–704. doi:10.1002/ca.20685
4. Morris SF, Yang D. "Gracilis Muscle: Arterial and Neural Basis for Subdivision." Ann Plast Surg. 1999;42(6):630–3. doi:10.1097/00000637-199906000-00008
5. Magden O, Tayfur V, Edizer M, Atabey A. "Anatomy of Gracilis Muscle Flap." J Craniofac Surg. 2010;21(6):1948–50. doi:10.1097/SCS.0b013e3181f4ed81
6. Hasen KV, Gallegos ML, Dumanian GA. "Extended Approach to the Vascular Pedicle of the Gracilis Muscle Flap: Anatomical and Clinical Study." Plast Reconstr Surg. 2003;111(7):2203–8. doi:10.1097/01.PRS.0000060114.95065.C5
7. Vila PM, Kallogjeri D, Yaeger LH, Chi JJ. "Powering the Gracilis for Facial Reanimation — A Systematic Review and Meta-Analysis of Outcomes Based on Donor Nerve." JAMA Otolaryngol Head Neck Surg. 2020;146(5):429–436. doi:10.1001/jamaoto.2020.0065
8. Chancellor MB, Watanabe T, Rivas DA, et al. "Gracilis Urethral Myoplasty: Preliminary Experience Using an Autologous Urinary Sphincter for Post-Prostatectomy Incontinence." J Urol. 1997;158(4):1372–1375. doi:10.1016/s0022-5347(01)64218-6
9. Whetzel TP, Lechtman AN. "The Gracilis Myofasciocutaneous Flap: Vascular Anatomy and Clinical Application." Plast Reconstr Surg. 1997;99(6):1642–1652; discussion 1653–1655. PubMed. doi:10.1097/00006534-199705010-00026
10. Sbizzera M, Morel-Journel N, Ruffion A, et al. "Rectourethral Fistula Induced by Localised Prostate Cancer Treatment: Surgical and Functional Outcomes of Transperineal Repair With Gracilis Muscle Flap Interposition." Eur Urol. 2022;81(3):305–312. doi:10.1016/j.eururo.2021.09.017
11. Rozanski AT, Vanni AJ. "Ventral Buccal Mucosa Graft Urethroplasty With Gracilis Muscle Flap for High Risk, Long Segment Urethral Strictures: A 20-Year Experience." Urology. 2020;140:178–180. doi:10.1016/j.urology.2020.03.008
12. Rinkinen JR, Fruge S, Welten VM, et al. "Long-Term Outcomes Analysis of Flap-Based Perineal Reconstruction." J Gastrointest Surg. 2024;28(1):57–63. doi:10.1016/j.gassur.2023.11.006
13. Chen XB, Wang YX, Jiang H, et al. "Salvage Irrigation-Suction in Gracilis Muscle Repair of Complex Rectovaginal and Rectourethral Fistulas." World J Gastroenterol. 2013;19(39):6625–6629. doi:10.3748/wjg.v19.i39.6625
14. Jenkins E, Humphrey H, Finan C, et al. "Long-Term Follow-Up of Bilateral Gracilis Reconstruction Following Extra-Levator Abdominoperineal Excision." J Plast Reconstr Aesthet Surg. 2023;76:198–207. doi:10.1016/j.bjps.2022.10.025
15. Weinstein B, King KS, Triggs W, Harrington MA, Pribaz J. "Bilobed Gracilis Flap — A Novel Alternative for Pelvic and Perineal Reconstruction." Plast Reconstr Surg. 2020;145(1):231–234. doi:10.1097/PRS.0000000000006341
16. Sert G, Yıldızdal S, Güdeloğlu A, Selber J. "Robotic Harvest of the Free Gracilis Muscle Flap." J Plast Reconstr Aesthet Surg. 2024;90:323–325. doi:10.1016/j.bjps.2024.02.031
17. Wexner SD, Ruiz DE, Genua J, et al. "Gracilis Muscle Interposition for the Treatment of Rectourethral, Rectovaginal, and Pouch-Vaginal Fistulas: Results in 53 Patients." Ann Surg. 2008;248(1):39–43. doi:10.1097/SLA.0b013e31817d077d
18. Vanni AJ, Buckley JC, Zinman LN. "Management of Surgical and Radiation Induced Rectourethral Fistulas With an Interposition Muscle Flap and Selective Buccal Mucosal Onlay Graft." J Urol. 2010;184(6):2400–2404. doi:10.1016/j.juro.2010.08.004
19. Garoufalia Z, Gefen R, Emile SH, et al. "Gracilis Muscle Interposition for Complex Perineal Fistulas: A Systematic Review and Meta-Analysis of the Literature." Colorectal Dis. 2023;25(4):549–561. doi:10.1111/codi.16427
20. Park KM, Rosli YY, Simms A, et al. "Preventing Rectourethral Fistula Recurrence With Gracilis Flap." Ann Plast Surg. 2022;88(4 Suppl 4):S316–S319. doi:10.1097/SAP.0000000000003085
21. de Angelis M, Scilipoti P, Leni R, et al. "Clinical and surgical management of recto-urinary fistula after radical prostatectomy: a systematic review on current evidence." Prostate Cancer Prostatic Dis. 2026. doi:10.1038/s41391-026-01114-7.
22. Palmer DA, Buckley JC, Zinman LN, Vanni AJ. "Urethroplasty for High Risk, Long Segment Urethral Strictures With Ventral Buccal Mucosa Graft and Gracilis Muscle Flap." J Urol. 2015;193(3):902–905. doi:10.1016/j.juro.2014.09.093
23. Sterling J, Schardein J, Joshi PM, Kulkarni SB, Nikolavsky D. "Long-term outcomes from a multi-institutional experience with prefabricated composite gracilis-buccal mucosal flap for reconstruction of devastated urethras." Int Urol Nephrol. 2022. doi:10.1007/s11255-022-03154-z.
24. Eseme EA, Scampa M, Viscardi JA, et al. "Surgical Outcomes of VRAM vs Gracilis Flaps in Vulvo-Perineal Reconstruction Following Oncologic Resection — A Proportional Meta-Analysis." Cancers. 2022;14(17):4300. doi:10.3390/cancers14174300
25. Pelly T, Anand E, Holubar S, Tozer P, Hart A. "Systematic review: The management of unhealed wounds and persistent perineal sinuses following proctectomy in inflammatory bowel disease." Tech Coloproctol. 2026;30:5 (published online December 2025). doi:10.1007/s10151-025-03242-z. Full text.
26. Chen SH, Hentz VR, Wei FC, Chen YR. "Short Gracilis Myocutaneous Flaps for Vulvoperineal and Inguinal Reconstruction." Plast Reconstr Surg. 1995;95(2):372–7. doi:10.1097/00006534-199502000-00018
27. Burke TW, Morris M, Roh MS, Levenback C, Gershenson DM. "Perineal Reconstruction Using Single Gracilis Myocutaneous Flaps." Gynecol Oncol. 1995;57(2):221–5. doi:10.1006/gyno.1995.1129
28. Copeland LJ, Hancock KC, Gershenson DM, et al. "Gracilis Myocutaneous Vaginal Reconstruction Concurrent With Total Pelvic Exenteration." Am J Obstet Gynecol. 1989;160(5 Pt 1):1095–1101. doi:10.1016/0002-9378(89)90168-3
29. Hsu H, Lin CM, Sun TB, Cheng LF, Chien SH. "Unilateral Gracilis Myofasciocutaneous Advancement Flap for Single Stage Reconstruction of Scrotal and Perineal Defects." J Plast Reconstr Aesthet Surg. 2007;60(9):1055–1059. doi:10.1016/j.bjps.2006.09.005
30. Lee SH, Rah DK, Lee WJ. "Penoscrotal Reconstruction With Gracilis Muscle Flap and Internal Pudendal Artery Perforator Flap Transposition." Urology. 2012;79(6):1390–1394. doi:10.1016/j.urology.2012.01.073
31. Guo H, Sa Y, Xu Y, Wang L, Fei X. "Adynamic Graciloplasty With a Pedicled Gracilis Muscle Flap Wrapped Around Bulbar Urethra for Treatment of Male Acquired Urinary Incontinence." Urology. 2016;91:208–214. doi:10.1016/j.urology.2015.12.073
32. Janknegt RA, Heesakkers JP, Weil EH, Baeten CG. "Electrically Stimulated Gracilis Sphincter (Dynamic Graciloplasty) for Treatment of Intrinsic Sphincter Deficiency: A Pilot Study on Feasibility and Side Effects." J Urol. 1995;154(5):1830–1833. PubMed. doi:10.1016/s0022-5347(01)66794-6
33. van Aalst VC, Werker PM, Stremel RW, et al. "Electrically Stimulated Free-Flap Graciloplasty for Urinary Sphincter Reconstruction: A New Surgical Procedure." Plast Reconstr Surg. 1998;102(1):84–91. doi:10.1097/00006534-199807000-00013
34. Perez-Abadia G, Van Aalst VC, Palacio MM, et al. "Gracilis Muscle Neosphincter for Treating Urinary Incontinence." Microsurgery. 2001;21(6):271–280. doi:10.1002/micr.1051
35. Baeten CG, Geerdes BP, Adang EM, et al. "Anal Dynamic Graciloplasty in the Treatment of Intractable Fecal Incontinence." N Engl J Med. 1995;332(24):1600–1605. doi:10.1056/NEJM199506153322403
36. Madoff RD, Rosen HR, Baeten CG, et al. "Safety and Efficacy of Dynamic Muscle Plasty for Anal Incontinence: Lessons From a Prospective, Multicenter Trial." Gastroenterology. 1999;116(3):549–556. doi:10.1016/s0016-5085(99)70176-9
37. Singh M, Kinsley S, Huang A, et al. "Gracilis Flap Reconstruction of the Perineum: An Outcomes Analysis." J Am Coll Surg. 2016;223(4):602–10. doi:10.1016/j.jamcollsurg.2016.06.383
38. Heidekrueger PI, Ehrl D, Ninkovic M, et al. "The Spreaded Gracilis Flap Revisited — Comparing Outcomes in Lower Limb Reconstruction." Microsurgery. 2017;37(8):873–880. doi:10.1002/micr.30245
39. Blough JT, Saint-Cyr MH. "Modern Approaches to Alternative Flap-Based Breast Reconstruction — Transverse Upper Gracilis Flap." Clin Plast Surg. 2023;50(2):313–323. doi:10.1016/j.cps.2022.11.001
40. Griepp DW, Shah NV, Scollan JP, et al. "Outcomes of Gracilis Free-Flap Muscle Transfers and Non-Free-Flap Procedures for Restoration of Elbow Flexion — A Systematic Review." J Plast Reconstr Aesthet Surg. 2022;75(8):2625–2636. doi:10.1016/j.bjps.2022.04.025
41. Chong TW, Balch GC, Kehoe SM, Margulis V, Saint-Cyr M. "Reconstruction of Large Perineal and Pelvic Wounds Using Gracilis Muscle Flaps." Ann Surg Oncol. 2015;22(11):3738–3744. doi:10.1245/s10434-015-4435-1
42. Higashino T, Sakuraba M, Fukunaga Y, et al. "Surgical Outcome for Colorectal or Urinary Tract-Related Fistula: Usefulness of Vascularized Tissue Transfer — A Retrospective Study." J Plast Reconstr Aesthet Surg. 2021;74(5):1041–1049. doi:10.1016/j.bjps.2020.10.046
43. Zmora O, Tulchinsky H, Gur E, et al. "Gracilis Muscle Transposition for Fistulas Between the Rectum and Urethra or Vagina." Dis Colon Rectum. 2006;49(9):1316–1321. doi:10.1007/s10350-006-0585-3
44. Paprottka FJ, Krezdorn N, Lohmeyer JA, et al. "Plastic Reconstructive Surgery Techniques Using VRAM or Gracilis Flaps in Order to Successfully Treat Complex Urogenital Fistulas." J Plast Reconstr Aesthet Surg. 2016;69(1):128–137. doi:10.1016/j.bjps.2015.08.026
45. Beckenstein M, Smith AA, Dinchman K, Wyatt-Ashmead J, Meland NB. "Muscle Flap Reconstruction Aids in Urethral Regeneration." Ann Plast Surg. 1996;36(6):641–643. doi:10.1097/00000637-199606000-00014
46. Ismayilzade M, Dadaci M, Kendir MS, Ince B. "Gracilis Muscle Interposition to Fill the Perianal Dead Space May Decrease Hospital Length of Stay in Fournier's Gangrene." Ann Plast Surg. 2023;90(4):356–362. doi:10.1097/SAP.0000000000003517
47. Kayikçioğlu A. "A New Technique in Scrotal Reconstruction: Short Gracilis Flap." Urology. 2003;61(6):1254–1256. doi:10.1016/s0090-4295(03)00158-4
48. Mitsala G, Varey AH, O'Neill JK, Chapman TW, Khan U. "The Distally Pedicled Gracilis Flap for Salvage of Complex Knee Wounds." Injury. 2014;45(11):1776–1781. doi:10.1016/j.injury.2014.06.019
49. Schoeller T, Huemer GM, Wechselberger G. "The Transverse Musculocutaneous Gracilis Flap for Breast Reconstruction — Guidelines for Flap and Patient Selection." Plast Reconstr Surg. 2008;122(1):29–38. doi:10.1097/PRS.0b013e318177436c
50. McKane BW, Korn PT. "The Fleur-De-Lis Upper Gracilis Flap for Breast Reconstruction — Flap Design and Outcome." Ann Plast Surg. 2012;69(4):383–386. doi:10.1097/SAP.0b013e31824b25c1
51. Yousif NJ, Matloub HS, Kolachalam R, Grunert BK, Sanger JR. The transverse gracilis musculocutaneous flap. Ann Plast Surg. 1992;29(6):482–490. doi:10.1097/00000637-199212000-00002
52. Kolehmainen M, Suominen S. Gracilis Flap. In: Kosutic D, ed. Perineal Reconstruction: Principles and Practice. Springer; 2023:85–100. doi:10.1007/978-3-030-97691-0_9
53. Soper JT, Rodriguez G, Berchuck A, Clarke-Pearson DL. "Long and short gracilis myocutaneous flaps for vulvovaginal reconstruction after radical pelvic surgery: comparison of flap-specific complications." Gynecol Oncol. 1995;56(2):271-275. doi:10.1006/gyno.1995.1045
54. Soper JT, Larson D, Hunter VJ, Berchuck A, Clarke-Pearson DL. "Short gracilis myocutaneous flaps for vulvovaginal reconstruction after radical pelvic surgery." Obstet Gynecol. 1989;74(5):823-827. PMID 2812660
55. Gaertner WB, Burgess PL, Davids JS, et al. "The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Management of Anorectal Abscess, Fistula-in-Ano, and Rectovaginal Fistula." Dis Colon Rectum. 2022;65(8):964-985. doi:10.1097/DCR.0000000000002473
56. Maspero M, Otero Piñeiro A, Steele SR, Hull TL. "Gracilis Muscle Interposition for the Treatment of Rectovaginal Fistula: A Systematic Review and Pooled Analysis." Dis Colon Rectum. 2023;66(5):631-645. doi:10.1097/DCR.0000000000002739
57. Oner M, Tsay AT, Abbas MA. "The use of the gracilis flap in colorectal surgery: surgical technique, results, and review of the literature." Int J Colorectal Dis. 2025;40(1):133. doi:10.1007/s00384-025-04928-4.
58. Chidester JR, Leland HA, Navo P, Minneti M, Ghiassi A, Stevanovic M. "Redefining the Anatomic Boundaries for Safe Dissection of the Skin Paddle in a Gracilis Myofasciocutaneous Free Flap: An Indocyanine Green Cadaveric Injection Study." Plast Reconstr Surg Glob Open. 2018;6(12):e1994. doi:10.1097/GOX.0000000000001994
59. Long Depaquit T, Michel F, Madec FX, et al. "Comparison of rectourethral fistula repairs: york mason vs. transperineal repair with gracilis flap interposition." World J Urol. 2026;44(1):198. doi:10.1007/s00345-026-06316-1
60. European Association of Urology. "EAU Guidelines on Urethral Strictures: Disease Management in Males." EAU Guidelines. EAU Guidelines Office, Arnhem; 2026. ISBN 978-94-92761-32-5. Guideline
61. Pastier C, Loriau J, Denost Q, et al. "Rectovaginal Fistula: What Is the Role of Martius Flap and Gracilis Muscle Interposition in the Therapeutic Strategy?" Dis Colon Rectum. 2024;67(8):1056–1064. doi:10.1097/DCR.0000000000003148