Lotus Petal Flap
The lotus petal flap (LPF) is a fasciocutaneous flap based on perforators of the internal pudendal artery (IPA), harvested from the gluteal fold or perineal crease, and named for the cumulative bilateral flap designs that resemble the petals of a lotus flower.[1][2] First described by Yii and Niranjan in 1996, it is widely used for vulvoperineal reconstruction. Reported advantages are reliable vascularity, a hidden donor scar, thin pliable tissue, preserved sensation and primary donor-site closure.[3][4] Applications include vulvar cancer, ELAPE pelvic-floor reconstruction, scrotal reconstruction and neovagina creation.[3][4]
The closely related but distinct medial-thigh / posterior-labial-artery flap is covered separately on the Singapore (Pudendal Thigh) Flap page; lotus-petal use as a propeller variant is covered in the Propeller Flap page.
Nomenclature and Identity
Related pudendal-perforator flaps have overlapping historical names, but their harvest site, vascular dissection and movement pattern can differ:[1][2]
- Lotus petal flap (Yii and Niranjan, 1996). Named for the bilateral petal-like design
- Gluteal fold flap / gluteal sulcus flap. Named for the donor site
- Internal pudendal artery perforator (IPAP) flap. Named for the vascular pedicle
- "Singapore flap" is sometimes applied to either the lotus petal or the medial-thigh pudendal-thigh flap (Wee and Joseph 1989); WARWIKI keeps these separate pages because the donor sites and primary indications differ. The Wee-Joseph medial-thigh flap is the Singapore (Pudendal Thigh) Flap.
The flap can be configured as a transposition, propeller, or V-Y advancement, making it one of the most versatile local-flap concepts in the perineal region.[5]
Vascular Anatomy
The lotus petal flap is based on perforators from the internal pudendal artery that emerge in the anogenital triangle:[1][6]
- Hashimoto (2001, as cited by Giroux) described 3–5 perforators in the perineal anogenital triangle, with the ischial tuberosity as the landmark for the safe medial boundary of dissection.[1] Hashimoto 2014 reported 71 free-style IPAP flaps in 45 patients (67 survived completely, 4 partial necrosis, no total loss), located with handheld Doppler.[5]
- Giroux 2021. Color Doppler in 15 subjects identified 24 perforators, with a mean ischial-tuberosity-to-perforator distance of 27.3 mm. The indexed abstract prints a vessel-diameter threshold of “greater than 5 mm,” which needs checking against the original methods before using a threshold.[1] The authors concluded routine ultrasound mapping and formal perforator dissection are not always required for their landmark-based design.[1]
- Jin 2009. Cadaveric microdissection of the perineum (11 cadavers, 22 sides) found 4 relatively constant perforating arteries (branches of the superficial external pudendal, obturator and posterior scrotal or labial arteries; not all are internal pudendal branches). They overlap and form upper, middle and lower vascular networks in the deep fascia. Four cutaneous nerves were identified in the region, which supports the concept of sensate flaps.[6]
The dense, overlapping perforator network explains the flap's reliability. Multiple perforators can be captured within a single skin paddle, providing redundant supply.[1][6]
Design and Surgical Technique
Classic design (Yii and Niranjan)
Elliptical skin island centered over the gluteal fold, long axis parallel to the fold, base medial (toward the perineum); transposed into the vulvar or perineal defect.[3][7]
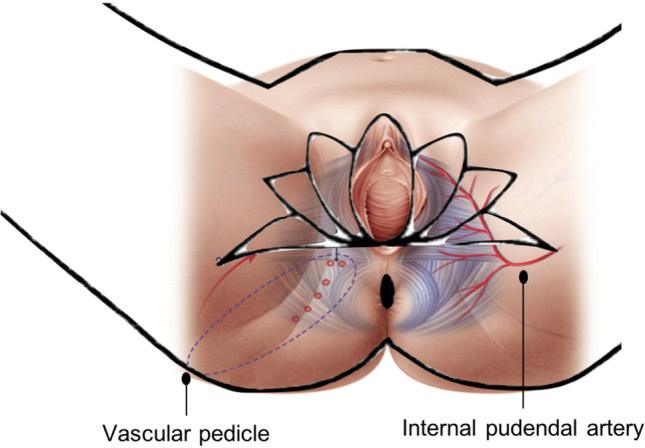
Schematic of lotus petal flap reconstruction: petal-shaped flap outlines arranged around the vulva and perineum, the internal pudendal artery branching toward the perineum (right) and the flap territory with its perforator-based vascular pedicle in the gluteal fold (left, dashed outline). From Grossi U, et al. Tech Coloproctol. 2021;25(1):141-142, Fig. 1 (CC BY 4.0).[24]
Modified (thinned) design — Warrier 2004
A thinned cutaneous flap harvested without formal identification of the blood supply, relying on the dense perforator territory:[3]
- Easier transposition due to reduced bulk
- Better aesthetic match to vulvar / perineal tissue
- No partial or complete failures in the initial 8-patient / 12-flap series
Supra-fascial variant — Bodin 2015
Raised above the fascia (rather than including it), further reducing bulk while maintaining perfusion through the dense subcutaneous perforator network. Particularly suited for posterior perineal cavity filling and skin resurfacing.[8]
Tunneled variant
The flap is passed through a subcutaneous tunnel to reach the defect, avoiding an external skin bridge. In a published tunneled design, the tunnel was made wide enough to admit the flap without compressing its pedicle.[27] Confalonieri 2017 reported the LPF, particularly the tunneled variant, to be superior to V-Y advancement in functional and cosmetic results for primary vulvar malignancies (retrospective, single center).[9]
Key design parameters
- Flap dimensions typically 3 × 4 cm to 13 × 12 cm depending on defect size[5]
- Harvested unilaterally or bilaterally. Bilateral flaps are used for total vulvectomy or neovagina[2][10]
- Donor site closes primarily in virtually all cases, with the scar hidden in the natural gluteal fold[7][8]
Urogynecologic Applications
Vulvar reconstruction after oncologic resection — primary indication
Vulvar reconstruction is the application with the largest LPF cohorts. In a cross-sectional survey, 22 of 38 contacted women completed questionnaires a median of 38.5 months after LPF reconstruction; sexual-function scores were lower than in age-matched healthy women, and respondents reported pain during sexual activity.[28]
- Hellinga 2018. Largest complications series: 93 patients, 137 lotus petal flaps:[11]
- 30.1% of patients had no complications; 51.7% had Clavien-Dindo I–II complications; 18.3% required intervention under general anesthesia (Clavien-Dindo IIIb), usually debridement (64.7% of the IIIb group).[11]
- Donor-site morbidity 14.0%
- Complication rates did not differ between vulvar, perineal, and vulvoperineal reconstruction
- Patients younger than 60 years had a significantly higher complication rate than older patients (p = 0.015; OR 0.235, 95% CI 0.073–0.754, for the older group)
- Argenta 2013. 59 consecutive patients, 80 lotus petal flaps for vulvar carcinoma / melanoma (66.1%), vulvar dysplasia (20.3%), colorectal disease (8.5%), hidradenitis suppurativa (5.1%). Mean defect 29 cm². Complications 36% (superficial wound separation 15% most common). No complete flap loss; partial loss occurred in 7/80 flaps (8.8%). Four patients required delayed revision, two for partial flap loss and two for stricture or stenosis.[4]
- Confalonieri 2017. Retrospective comparison reporting overall complications of V-Y 21% versus LPF 13%, without a significant overall difference (p = 0.588). The authors favored the tunneled variant for functional and cosmetic results in primary vulvar malignancies. The indexed abstract inconsistently lists 284 women, 234 V-Y plus 128 LPF recipients, and event fractions of 27/128 and 14/106; use neither apparent arm denominator as settled until the full table is checked.[9]
- Sawada 2004. 5 patients with mean vulvoperineal defects of 157.9 cm² covered with bilateral LPF. All flaps survived without fatal necrosis. No pain, abnormal sensation, or impact on excretion or hip mobility; donor scars hidden in the gluteal fold.[7]
Vulvar reconstruction algorithm — Negosanti 2015
A defect-based classification from 22 consecutive patients:[10]
| Type | Resection extent | Negosanti's proposed flap choice |
|---|---|---|
| IA | Half-vulvar resection, vagina preserved | Unilateral LPF |
| IB | Total vulvar resection, vagina preserved | Bilateral LPF |
| II | Vulvar + vaginal resection, large pelvic dead space | Pedicled DIEP (LPF insufficient for bulk) |
In Negosanti's proposed algorithm from 22 patients, unilateral or bilateral LPF can reconstruct vulvar-only defects (Types IA and IB); the authors preferred pedicled DIEP for type II defects with vaginal resection and substantial pelvic dead space.[10] The 2023 ESGO guideline bases reconstructive choice on patient and tumor characteristics and team experience (level IV, grade B), without naming a first-line flap.[26]
Pelvic-floor reconstruction after extralevator abdominoperineal excision (ELAPE)
- Hellinga 2016. 28 patients with LPF reconstruction after ELAPE; 89.3% had preoperative RT, 28.6% biological mesh augmentation. No total flap loss; 21.4% no complications; 46.4% minor (Clavien-Dindo I–II); 32.1% reoperation (Clavien-Dindo IIIb), 3 needing a second LPF. Median time to wound healing 14 weeks. The flap also enabled neovagina creation when needed.[12]
- Hellinga 2020. Cross-sectional QoL follow-up (15 of 23 eligible patients completed questionnaires; 11 examined; the authors advise caution given the small sample).[13] QoL scores did not differ significantly between the 15 LPF questionnaire respondents and 16 primary-perineal-closure controls. Among the 15 LPF respondents, 5 (33%) reported sexual activity postoperatively versus 13 (87%) preoperatively; no perineal hernia was found among the 11 examined, whose hip-joint ROM was bilaterally reduced versus reference values.[13]
Posterior perineal reconstruction
Bodin 2015. 10 supra-fascial LPF procedures (6 patients; unilateral in 2, bilateral in 4) for posterior perineal cavity filling and skin resurfacing. 4 patients had prior RT. No wound complications or flap necrosis occurred over 20.5 months of follow-up. Mean LOS 11.3 days; healing time 35.2 days.[8]
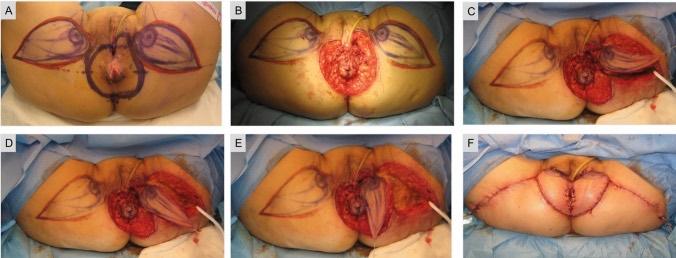
Bilateral lotus petal flaps for a perianal defect after excision of perianal Paget disease: (A) flap planning with handheld Doppler marking of internal pudendal artery perforators and a 2 cm excision margin around the perianal and posterior vulvar lesions; (B) defect after excision, with the outer 1.5 cm of the urethra mobilized and the transverse perineal muscles and external anal sphincter exposed; (C-E) fasciocutaneous flaps centred over the medial thigh crease, elevated posterior to anterior and rotated 90 degrees posteriorly into the defect, with a Foley catheter in place; (F) immediate result after inset and primary donor-site closure. From Grossi U, et al. Tech Coloproctol. 2021;25(1):141-142, Fig. 2 (CC BY 4.0).[24]
Perioperative mobility after IPAP flap reconstruction
In a randomized trial of 51 patients after IPAP flap reconstruction of irradiated abdominoperineal resection defects, an adapted early-mobilization program (n = 25) versus 5 days of bed rest (n = 26) improved independent ambulation on day 5 (68.0% versus 38.5%; p = 0.035). No statistically significant difference was detected in healing time (p = 0.06) or complication rates (68.0% versus 80.8%; p = 0.296); equivalence was not tested.[22]
Rectovaginal fistula
A modified IPAP flap interposition has been described for low rectovaginal fistula: in a retrospective series of 16 patients, all healed without recurrence over a mean follow-up of 14.1 months.[23]
Complex pelvic-perineal reconstruction (combined flaps)
For extensive defects requiring more tissue than a single LPF can provide:
- Contedini 2015. Pedicled ALT flap combined with bilateral lotus petal flaps for a complex pelvic-perineal defect after pelvic exenteration. The ALT provided bulk for pelvic dead-space obliteration; bilateral LPFs resurfaced the perineum. Good result with no major complications.[14]
- Bini & Stavrianos 2025. 34 patients with pelvic or perineal reconstruction after advanced tumor resection using VRAM, gracilis, IGAP, IPAP and LPFs. Wound dehiscence occurred in four patients (two gracilis, one IPAP, one LPF); surgical-site infection occurred in two (one gracilis, one ORAM). 15/34 achieved 5-yr disease-free survival; the authors attribute the low survival to tumor aggression and recurrence.[15]
Neovagina creation
Bilateral lotus petal flaps can be used for neovagina formation. Höckel and Dornhöfer noted that bilateral local axial-pattern flaps (including LPF) are needed for full neovagina formation, although tubularization of a single musculocutaneous flap may suffice in some cases.[2] The Hellinga ELAPE series confirmed LPF-enabled neovagina creation as part of pelvic-floor reconstruction.[12]
Urologic Applications
Scrotal reconstruction after Fournier's gangrene
Payne 2009 described lotus petal flaps for scrotal reconstruction in a single male patient following necrotizing fasciitis after circumcision:[16]
- Bilateral lotus petal flaps were transposed to create a neoscrotum with adequate volume for testicular cover
- Combined with Integra dermal regeneration template for penile-shaft resurfacing
- The LPF "integrated well with the remaining scrotal sac to produce a good volume neoscrotum"
- Erectile capability preserved with the Integra-covered penile shaft
The LPF was originally designed for vulvovaginal defects. In this case it provided tissue of appropriate thickness and pliability to recreate a scrotal pouch.
In the broader Fournier's literature, a 2026 SR of 619 patients / 625 flaps reported flap loss in 1.6% of cases, with medial-thigh, pudendal-thigh, ALT and gracilis flaps most commonly used.[17] The review identifies pudendal-thigh flaps among the common options; a separate report describes one LPF scrotal reconstruction.[17][16]
Perineal reconstruction — IPAT and IPAP variants
The internal pudendal artery turnover (IPAT) flap, a simplified IPAP (lotus petal) variant, was described by Nassar 2021 in 38 consecutive patients for perineal reconstruction:[18]
- Requires no visualization or dissection of perforating vessels
- At 3 months, 37 flaps in the 38-patient cohort were fully healed; no flap failures or partial losses.[18]
- Complications occurred in 10/38 patients (9 minor, 1 return to the operating room for washout after a urinary leak).[18]
- Effective for deep three-dimensional defects following perineal excisions
The authors describe it as simpler than perforator dissection and useful at the end of long oncologic resections; the series is retrospective and from one surgeon.
Loreti 2023 reported 11 IPAP-based flaps (8 rotation, 2 advancement island, 1 propeller) after abdominoperineal resection. All 11 flaps survived with no immediate postoperative major complications; 8/11 patients (73%) had previously irradiated tissues.[19]
Presacral defect reconstruction
Van der Meer 2014 described a partially de-epithelialized lotus petal perforator flap for an extended chronic presacral defect after radiotherapy and rectal cancer resection. Wound healing was achieved at 12 days (single case). The authors concluded the LPF is "a relatively simple and successful choice" for this indication.[20]
Complications
In Hellinga's single-center cohort of 93 patients receiving 137 flaps (patient-level complication categories):[11]
| Category | Rate |
|---|---|
| No complications | 30.1% |
| Minor (Clavien-Dindo I–II) | 51.7% |
| Major (Clavien-Dindo IIIb) | 18.3% |
| Donor-site morbidity | 14.0% |
| Flap loss | — |
Risk factors: patients younger than 60 had more complications than older patients in this cohort (p = 0.015); the OR of 0.235 describes the older group.[11]
A separate review of pelvic-exenteration reconstruction discusses VRAM and other choices, but differences in defect size, irradiated tissue and source populations prevent a direct LPF-versus-VRAM survival or donor-morbidity ranking from these observational series.[21] A 2025 APR review reported perineal hernia in 7/47 patients (14.9%) with hernia data in a mixed gluteal fasciocutaneous group.[29]
Comparison with Other Perineal / Vulvar Reconstruction Options
A 2024 systematic review placed conventional lotus-petal flaps among local fasciocutaneous flaps in its non-perforator group. Across 49 studies, short-term complication rates did not differ significantly between mixed perforator (276 patients) and non-perforator (1,564 patients) groups; long-term quality-of-life data were scarce.[25]
| Feature | Lotus petal | V-Y advancement | Propeller (IPAP) | VRAM | Gracilis |
|---|---|---|---|---|---|
| Vascular basis | IPA perforators (multiple) | Subcutaneous / perforator | Single skeletonized perforator | Deep inferior epigastric | Medial circumflex femoral |
| Tissue type | Fasciocutaneous (thin) | Fasciocutaneous | Fasciocutaneous (thin) | Musculocutaneous (bulky) | Musculocutaneous |
| Perforator dissection | No (landmark-based) | No | Yes (skeletonization) | No (named vessel) | No (named vessel) |
| Sensate | Potentially; postoperative sensory preservation was not measured in the cited outcome series[4][6] | Variable | Variable | No | No |
| Donor scar | Hidden in gluteal fold | Visible (perineal / thigh) | Hidden in gluteal fold | Abdominal (significant) | Medial thigh |
| Donor-site morbidity | 14.0% in a 93-patient LPF cohort[11] | Low | Low | Significant (hernia risk) | Moderate (thigh weakness) |
| Bulk for dead space | Limited | Limited | Limited–moderate | Excellent | Moderate |
| Neovagina creation | Yes (bilateral) | Limited | Yes | Yes (tubularized) | Yes (tubularized) |
| Best indication | Medium vulvar / perineal defects | Moderate vulvar defects | Extensive penoscrotal / vulvar | Large pelvic-floor defects | Moderate defects, vaginal reconstruction |
| Flap-loss comparison | Not established across matched defect populations | Not established | Not established | Not established | Not established |
Key Advantages
- Simplicity in selected designs. Giroux considered anatomic-landmark harvesting possible without routine ultrasound or formal perforator dissection; isolated-perforator designs use a different approach.[1][18] 2.[4][5][11] Useful vascular territory. The overlapping IPA perforator network permits varied designs.[4][5][11]
- Hidden donor scar in the natural gluteal fold.[7][8]
- Sensory anatomy. Cutaneous nerves traverse the perineal flap territory and may be preserved during harvest.[2][6][7]
- Tissue match. Gluteal-fold skin is described as closely matching vulvar / perineal skin in thickness, texture, color and pliability.[3][7]
- Versatility. Transposition, propeller, V-Y, or tunneled configurations; uni- or bilateral; combinable with distant flaps for complex defects.[5][10][14]
Key Limitations
- Limited bulk for some defects. Negosanti preferred pedicled DIEP for type II vulvovaginal defects with substantial pelvic dead space, while broader exenteration reconstructions require individualized flap selection. Selected ELAPE defects have been reconstructed with LPF, and the IPAT variant has been described for deep three-dimensional perineal defects.[10][21][12][18] 2.[4][5][11] Minor wound complications are common. About 50% of patients had Clavien-Dindo I–II complications, reflecting the challenging perineal wound-healing environment.[11][12]
- Prior radiotherapy. Assess gluteal-fold donor-tissue quality and pelvic dead-space volume when selecting a flap. In one ELAPE series, LPFs were used after preoperative radiotherapy in 25/28 patients; a flap with more bulk or a different donor site may be selected for a large defect or poor-quality local tissue.[15][12][21]
Technical Pearls
- Map the ischial tuberosity as the medial boundary of safe dissection (Hashimoto's anatomic landmark).[5]
- Select mapping to match the design and tissue. Giroux's landmark-based approach need not require routine ultrasound, whereas free-style isolated-perforator designs commonly use handheld Doppler; planning for irradiated and reoperative fields depends on the flap design and tissue condition.[1][5]
- Choose the variant by defect. Warrier-thinned for surface vulvar coverage, Bodin supra-fascial for posterior cavity filling, tunneled (Confalonieri) for primary vulvar malignancies, IPAT (Nassar) when avoiding perforator dissection altogether.
- Plan bilaterally for total vulvectomy, neovagina or large midline defects. Closure tension is shared and the bilateral petal design gives a midline result.
- Combine with distant flaps when bulk is required: bilateral LPF plus ALT (Contedini) or LPF as the surface-cover layer over a deep VRAM or gracilis.[14]
See Also
- Singapore (Pudendal Thigh) Flap: the related medial-thigh / posterior-labial-artery flap for bilateral neovagina (Wee-Joseph 1989); historically also called "Singapore flap"
- Propeller Flap: lotus-petal use as a propeller variant
- V-Y Advancement Flap
- Rhomboid (Limberg) Flap
- Bilobed Flap
- Gracilis Flap
- VRAM Flap
- Anterolateral Thigh Flap
- Pelvic and Perineal Flap Postoperative Care
- Flaps in GU Reconstruction
References
1. Giroux PA, Dast S, Assaf N, Lari A, Sinna R. "Internal Pudendal Perforator Artery Flap Harvesting Without Pre-Operative Imaging: Reliability and Approach." J Plast Reconstr Aesthet Surg. 2021;74(6):1355–1401. doi:10.1016/j.bjps.2020.12.017
2. Höckel M, Dornhöfer N. "Vulvovaginal Reconstruction for Neoplastic Disease." Lancet Oncol. 2008;9(6):559–568. doi:10.1016/S1470-2045(08)70147-5
3. Warrier SK, Kimble FW, Blomfield P. "Refinements in the Lotus Petal Flap Repair of the Vulvo-Perineum." ANZ J Surg. 2004;74(8):684–688. doi:10.1111/j.1445-1433.2004.03119.x
4. Argenta PA, Lindsay R, Aldridge RB, et al. "Vulvar Reconstruction Using the 'Lotus Petal' Fascio-Cutaneous Flap." Gynecol Oncol. 2013;131(3):726–729. doi:10.1016/j.ygyno.2013.08.030
5. Hashimoto I, Abe Y, Nakanishi H. "The Internal Pudendal Artery Perforator Flap: Free-Style Pedicle Perforator Flaps for Vulva, Vagina, and Buttock Reconstruction." Plast Reconstr Surg. 2014;133(4):924–933. doi:10.1097/PRS.0000000000000008
6. Jin B, Hasi W, Yang C, Song J. "A Microdissection Study of Perforating Vessels in the Perineum: Implication in Designing Perforator Flaps." Ann Plast Surg. 2009;63(6):665–669. doi:10.1097/SAP.0b013e3181999de3
7. Sawada M, Kimata Y, Kasamatsu T, et al. "Versatile Lotus Petal Flap for Vulvoperineal Reconstruction After Gynecological Ablative Surgery." Gynecol Oncol. 2004;95(2):330–335. doi:10.1016/j.ygyno.2004.07.038
8. Bodin F, Dissaux C, Seigle-Murandi F, et al. "Posterior Perineal Reconstructions With 'Supra-Fascial' Lotus Petal Flaps." J Plast Reconstr Aesthet Surg. 2015;68(1):e7–e12. doi:10.1016/j.bjps.2014.10.028
9. Confalonieri PL, Gilardi R, Rovati LC, et al. "Comparison of V-Y Advancement Flap Versus Lotus Petal Flap for Plastic Reconstruction After Surgery in Case of Vulvar Malignancies: A Retrospective Single Center Experience." Ann Plast Surg. 2017;79(2):186–191. doi:10.1097/SAP.0000000000001094
10. Negosanti L, Sgarzani R, Fabbri E, et al. "Vulvar Reconstruction by Perforator Flaps: Algorithm for Flap Choice Based on the Topography of the Defect." Int J Gynecol Cancer. 2015;25(7):1322–1327. doi:10.1097/IGC.0000000000000481
11. Hellinga J, Khoe PCKH, Stenekes MW, Eltahir Y. "Complications After Vulvar and Perineal Reconstruction With a Lotus Petal Flap." Ann Plast Surg. 2018;80(3):268–271. doi:10.1097/SAP.0000000000001271
12. Hellinga J, Khoe PC, van Etten B, et al. "Fasciocutaneous Lotus Petal Flap for Perineal Wound Reconstruction After Extralevator Abdominoperineal Excision: Application for Reconstruction of the Pelvic Floor and Creation of a Neovagina." Ann Surg Oncol. 2016;23(12):4073–4079. doi:10.1245/s10434-016-5332-y
13. Hellinga J, Stenekes MW, Werker PMN, et al. "Quality of Life, Sexual Functioning, and Physical Functioning Following Perineal Reconstruction With the Lotus Petal Flap." Ann Surg Oncol. 2020;27(13):5279–5285. doi:10.1245/s10434-020-08771-5
14. Contedini F, Negosanti L, Pinto V, et al. "Reconstruction of a Complex Pelvic Perineal Defect With Pedicled Anterolateral Thigh Flap Combined With Bilateral Lotus Petal Flap: A Case Report." Microsurgery. 2015;35(2):154–157. doi:10.1002/micr.22304
15. Bini A, Stavrianos S. "Pelvic and Perineal Reconstruction After Bowel, Gynecological or Sacral Tumor Resection: A Case Series." J Clin Med. 2025;14(9):3172. doi:10.3390/jcm14093172
16. Payne CE, Williams AM, Hart NB. "Lotus Petal Flaps for Scrotal Reconstruction Combined With Integra Resurfacing of the Penis and Anterior Abdominal Wall Following Necrotising Fasciitis." J Plast Reconstr Aesthet Surg. 2009;62(3):393–397. doi:10.1016/j.bjps.2007.09.015
17. Alammar A, Laing K, Somasundaram J, Wallace DL, Rogers AD. "Flap Reconstruction Following Fournier's Gangrene: A Systematic Review of Techniques and Outcomes." Burns. 2026;52(3):107888. doi:10.1016/j.burns.2026.107888
18. Nassar MK, Jordan DJ, Quaba O. "The Internal Pudendal Artery Turnover (IPAT) Flap: A New, Simple and Reliable Technique for Perineal Reconstruction." J Plast Reconstr Aesthet Surg. 2021;74(9):2104–2109. doi:10.1016/j.bjps.2020.12.074
19. Loreti A, Arelli F, Spallone D, Bruno E, Abate O. "The Use of the Internal Pudendal Artery Perforator Flap After Abdominoperineal Reconstruction: A Single Center Study." J Plast Reconstr Aesthet Surg. 2023;84:87–92. doi:10.1016/j.bjps.2023.05.015
20. van der Meer JG, Moerman E, van de Kar AL, Vermaas M, Gerhards MF. "Lotus Petal Perforator Flap for Reconstruction of an Extended Chronic Presacral Defect After Radiotherapy and Rectal Cancer Resection." Colorectal Dis. 2014;16(6):O220–O222. doi:10.1111/codi.12511
21. Witte DYS, van Ramshorst GH, Lapid O, Bouman MB, Tuynman JB. "Flap Reconstruction of Perineal Defects After Pelvic Exenteration: A Systematic Description of Four Choices of Surgical Reconstruction Methods." Plast Reconstr Surg. 2021;147(6):1420–1435. doi:10.1097/PRS.0000000000007976
22. Lima de Araujo CA, de Freitas Busnardo F, Thome Grillo VA, et al. "Effect of Early Postoperative Mobilization on Functional Recovery, Hospital Length of Stay, and Postoperative Complications After Immediate Internal Pudendal Artery Perforator Flap Reconstruction for Irradiated Abdominoperineal Resection Defects: A Prospective, Randomized Controlled Trial." Ann Surg Oncol. 2025;32(2):993-1004. doi:10.1245/s10434-024-16497-x
23. Yuan Y, Li S, Li F, et al. "Modified Internal Pudendal Artery Perforator Flap Interposition for Rectovaginal Fistula." Urogynecology (Phila). 2024;30(8):699-705. doi:10.1097/SPV.0000000000001447
24. Grossi U, Santoro GA, Antoniazzi E, Dell'Antonia F, Busato E, Berna G, et al. "Bilateral Lotus Petal Flap Reconstruction for Perianal Paget's Disease." Tech Coloproctol. 2021;25(1):141–142. doi:10.1007/s10151-020-02283-w
25. Wendelspiess S, Kouba L, Stoffel J, et al. "Perforator versus Non-Perforator Flap-Based Vulvoperineal Reconstruction-A Systematic Review and Meta-Analysis." Cancers (Basel). 2024;16(12):2213. doi:10.3390/cancers16122213
26. Oonk MHM, Planchamp F, Baldwin P, et al. "European Society of Gynaecological Oncology Guidelines for the Management of Patients with Vulvar Cancer - Update 2023." Int J Gynecol Cancer. 2023;33(7):1023–1043. doi:10.1136/ijgc-2023-004486
27. Buda A, Confalonieri PL, Rovati LCV, Signorelli M, Del Bene M. "Tunneled modified lotus petal flap for surgical reconstruction of severe introital stenosis after radical vulvectomy." Int J Surg Case Rep. 2012;3(7):299–301. doi:10.1016/j.ijscr.2012.03.024
28. Hellinga J, te Grootenhuis NC, Werker PMN, et al. "Quality of Life and Sexual Functioning After Vulvar Reconstruction With the Lotus Petal Flap." Int J Gynecol Cancer. 2018;28(9):1728–1736. doi:10.1097/IGC.0000000000001340
29. Calpin GG, Davey MG, Maguire B, et al. "Optimal approaches to flap reconstruction following abdominoperineal resection: A systematic review." Surgeon. 2025;23(3):155–161. doi:10.1016/j.surge.2025.01.010