Martius Flap
The modified Martius flap transfers vascularized labial fibrofatty tissue to a nearby urethral or vaginal repair. It can separate suture lines and supplement compromised tissue.[13][14]
This is the foundations-level harvest and selection page. The VVF, RVF and urethral-diverticulum pages cover the underlying condition and complete repair pathway.
Tissue and vascular anatomy
The historical Martius operation, as described by Heinrich Martius, used bulbocavernosus muscle. Cadaver dissection showed that the graft used today is fibroadipose tissue from the labium majus rather than muscle. Its prominent fibrous component arises from a superficial fibrous tunic similar to the male tunica dartos and from fibrous septa within the fat.[1] The modern labial fat-pad modification usually preserves the muscle. Older publications sometimes use “bulbocavernosus,” “graft” and “Martius” loosely; establish what tissue was actually transferred before comparing techniques.[1][13]
| Vascular contribution | Operative implication |
|---|---|
| Superior/anterior contribution from the external pudendal system | May support a superiorly based design |
| Inferior/posterior contribution from the internal pudendal system | Commonly preserved for an inferiorly based flap, including urethral and vaginal interposition |
The repair's anterior or posterior location alone does not determine which pedicle to preserve. Assess reach, scarring, prior operations and the actual vascular base. Preserve a broad pedicle and avoid a compressed or twisted tunnel.[13]
A ten-cadaver mapping study found the highest vascular density in the right lateral labium and the highest nerve density in the anterior and medial fat pad bilaterally; across sampled locations, vascular density was 8% greater and nerve density 9% greater in the right than the left labium.[3]
Harvest and inset
The following describes the fat-pad modification; adapt exposure and dissection to the patient's anatomy and the planned repair.[13]
- Select the donor side and intended pedicle after assessing the recipient defect and required reach.
- Open the labium majus and identify the fibrofatty pad while preserving the overlying skin and deeper structures.
- Mobilize the pad with its vascular base intact, preserving vestibular tissues rather than routinely including muscle. Keep dissection lateral to bulbospongiosus and ischiocavernosus: an overly medial plane can cause substantial bleeding, while an overly superficial plane risks scar deformity.[13]
- Create an atraumatic tunnel wide enough for the flap and its pedicle; pass it without torsion or constriction.
- Trim redundant flap length, secure the pad to perivaginal fascia over the completed repair without tension, and cover it completely with vaginal tissue. An exposed fat pad has been associated with a dragging sensation radiating from the labium to the vagina. Close the donor wound with careful hemostasis.[13]
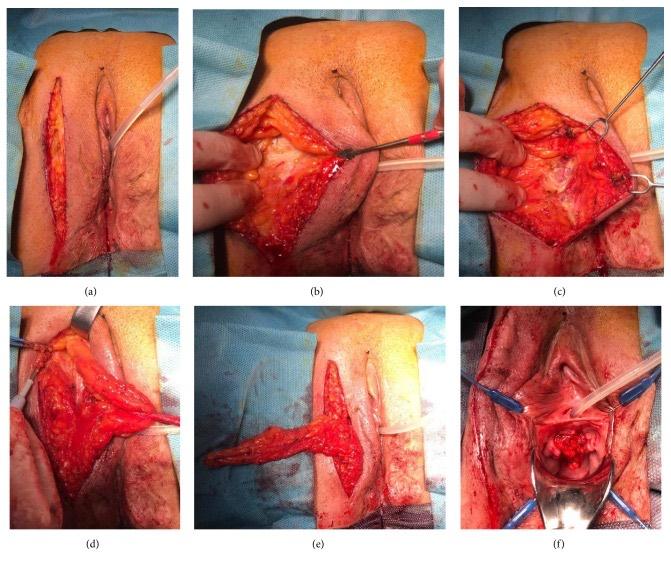
Martius flap after ventral urethral repair: (a) sagittal incision over the labium majus; (b) lateral dissection to the labiocrural fold; (c) medial dissection up to the bulbospongiosus muscle; (d) mobilization of the fat pad; (e) division of the anterior pedicle; (f) flap transposed to the ventrally reconstructed urethra. From Waterloos M, Verla W. Biomed Res Int. 2019;2019:6715257, Figure 12 (CC BY 4.0).[26]
Drain use depends on the dissection and dead space. Published techniques vary in drain use and include a temporary labial drain.[13][14]
Incision placement and labial contour. Placing the harvest incision over the lateral bulge of the labium majus, rather than more medially, and deliberately leaving fat medially beneath the labial skin can reduce medial retraction and postoperative distortion; a reported illustrative case had a barely visible scar without asymmetry at one year.[24]
In-situ harvest through the vaginal incision. When separate labial exposure is difficult, particularly during combined abdominal and vaginal surgery, the vaginal repair incision can be extended through the labia minora and the fat pad mobilized from that exposure: a subcutaneous plane is developed over the pad toward the adductors, the pad is separated from the bulbocavernosus muscle while retaining a broad inferior pedicle, its upper attachment is divided, and the anterior tissue is rotated into the prevaginal space. Because mobilization through this exposure is limited, this variant is best suited to lateral, distal defects, not posterior vaginal coverage, and is used only when a tension-free inset is achievable. Avoiding a separate labial incision is intended to reduce risk to the superficial pudendal nerve and posterior labial vessels, but this rationale has not been measured against the standard approach.[25]
Vesicovaginal fistula: use interposition selectively
For a simple VVF with healthy tissue and a sound closure, routine Martius interposition has not demonstrated an additional closure benefit. The 2024 systematic review found that interpositional flaps did not show significant improvement in fistula cure rates; its studies mixed flap types, fistula characteristics and study designs.[15]
| Evidence | Finding and application |
|---|---|
| Singh 2019 randomized comparison | Among 57 vaginal repairs of selected simple fistulas, closure occurred in 27/29 with Martius vs 27/28 without. Nine of 29 flap recipients reported labial numbness or pain. It included obstetric and gynecologic simple fistulas of 4 cm or less and excluded complex or complicated fistulas and malignancy-related fistulas.[14] |
| Eilber 2003 observational series | Of 207 vaginal repairs, 34 used Martius, 83 peritoneum and three a skin interposition. Reported 97% Martius closure after initial repair concerns the 34-patient subgroup; differences in defect location and selection preclude a head-to-head efficacy comparison.[5] |
| Safan 2009 randomized trial | In 40 patients with complicated obstetric VVF (recurrent, fibrotic, bladder-neck or larger than 1.5 cm), autologous fibrin glue as the interposition layer was compared with a Martius flap. 13 of 19 (68%) and 11 of 19 (58%) were dry, a difference that was not statistically significant. Follow-up was 3 months.[16] |
| Rangnekar 2000 retrospective series | Of 46 patients with mostly obstetric urinary-vaginal fistulas, none of 13 VVFs repaired with Martius recurred versus 4 of 21 (19%) with anatomic repair alone. Recurrence in patients with recurrent fistulas was 1 of 12 (8.3%) versus 4 of 7 (57.1%). Repair was not randomized.[17] |
| Pushkar 2009 radiation series | Of 216 patients, 210 underwent a vaginal approach, including 86 Martius repairs. First-attempt success was 48% and cumulative success after further attempts 80.4% across the vaginal cohort.[6] |
Sources: Singh, Safan, Rangnekar, Eilber and Pushkar.[14][16][17][5][6]
A 2026 randomized comparison of 64 transvaginal VVF repairs reported leak-free status at postoperative day 21 of 90.9% with fibrin glue, 81% with primary repair and 90.5% with Martius interposition (p = 0.541).[28]
Consider vascularized interposition when tissue loss, fibrosis or prior failure compromises reconstruction. For radiation-associated urinary fistula repair, the EAU 2026 guideline recommends an interposition graft without specifying a particular flap.[32] Choose tissue with adequate health, bulk and reach; severe radiation damage may require a different reconstruction or diversion. No flap makes an otherwise inadequate closure reliable.[4][13]
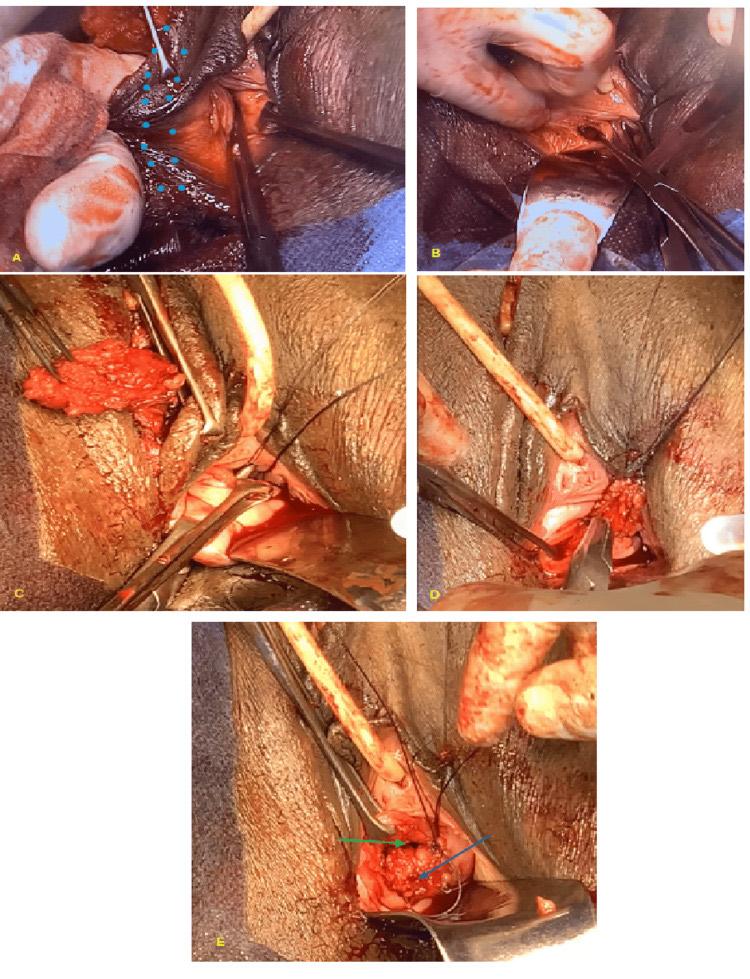
Martius flap inset after vaginal repair of a post-hysterectomy vesicovaginal fistula: (A) blunt tunnel from the vulvar incision beneath the bulbospongiosus muscle (dotted blue points) and the vaginal epithelium; (B) opening in the vaginal mucosa for access to the tunnel; (C) fat pad passed through a tunnel wide enough to avoid vascular compression; (D) flap positioned between the repaired fistula tract and the vaginal mucosa; (E) fat pad (blue arrow) secured to the vaginal muscularis (green arrow) with loose interrupted 3-0 polyglactin sutures. From Silva DO, et al. Cureus. 2026;18(6):e110195, Figure 4 (CC BY 4.0).[27]
Urethral diverticulectomy and urethral reconstruction
Martius interposition can support selected complex or recurrent diverticulectomy, urethroplasty and urethrovaginal-fistula repairs. It is an adjunct to urethral reconstruction, not a continence sling.[13]
In Malde's 70-patient diverticulectomy series, all patients received a Martius flap and one had symptomatic diverticulum recurrence.[7] Of 41 women without preoperative stress incontinence, ten developed it initially and five still reported symptoms at 12 months (overall mean follow-up 19 months): the reported persistent de novo rate is approximately 12% of those at risk.[7]
In Osman's retrospective series of 121 diverticulum excisions, a Martius flap was used in 36 (30%).[18] Overall symptomatic recurrence was 4%, de novo stress incontinence 13% and dyspareunia resolved by 6 months in the 5 women affected; follow-up was a mean of 10 months.[18] In Ko's series of 68 women, 8 of the 11 who underwent a second operation for recurrence were cured, 7 of them with Martius interposition.[19] Mobilizing and repositioning a previously placed Martius pad has been described in a single-patient video for recurrent diverticulum.[20]
Malde's 159-patient series shows the range of indications: urethral diverticulum excision (74), vaginal VVF repair (43), urethral erosion of a midurethral tape (24), female urethroplasty for stricture (12), vaginal bladder-neck closure for end-stage stress incontinence (4) and a prophylactic tape wrap for fragile urethras (2).[2] A single video case describes a Latzko repair of a urethrovaginal fistula with a Martius flap.[23]
For bladder-neck closure, interposition is part of selected salvage reconstruction of a devastated outlet, with a separate long-term bladder-drainage plan.[13]
Rectovaginal fistula
ASCRS 2022 recommends gracilis or Martius interposition for recurrent or otherwise complex RVF . Assess the fistula's cause, sphincter function, tissue quality, infection and previous repairs before selecting the operation.[8]
The 2024 Martius meta-analysis included 137 flaps in 12 nonrandomized studies: 44 primary and 93 recurrent RVFs. Pooled success was 91.4% for primary and 77.5% for recurrent fistulas.[9] The pooled complication estimate was 29%, with substantial heterogeneity and a wide 95% CI of 9.0–54.7%.[9] The review reported 94.6% pooled success in its radiotherapy-induced low-RVF subset.[9] A prospective series of 24 selected patients with low RVF (at least 1 cm, at least two prior repairs or chronically inflamed tissue) reported success in 22/24 patients with mean follow-up of 42 months, with improved SF-12 and FSFI scores.[21]
Pastier's retrospective multicenter cohort included 62 patients who underwent 55 Martius and 24 gracilis procedures. Success required absence of both fistula and stoma. Immediate success was 35% and 31%; both groups reached a reported 69% after further treatment at median 23-month follow-up. Repeated procedures and nonrandom selection prevent an equivalence conclusion or a universal “Martius first, gracilis second” rule. Hospital stay was 2 days shorter with Martius (p = 0.01), 27% of Martius repairs were done without a stoma without a measurable effect on morbidity, and smoking was the only negative predictor of success (p = 0.02).[10]
Diversion is individualized. ASCRS generally supports an adjunctive stoma for these complex flap repairs while acknowledging limited evidence.[8] Selected repairs without diversion have been reported. Control infection and address active inflammatory disease before definitive reconstruction.[8][10]
Mesh exposure versus erosion into the urinary tract
These require different decisions. ACOG/AUGS Committee Opinion 694 (2017) describes Martius coverage of a functioning but persistently vaginally exposed sling as an option supported by case reports when preservation remains the patient's preference. It is not a recommendation to cover mesh eroding into the urethra or bladder. The opinion uses the term "Martius graft transposition" and adds that, if preservation fails and the patient remains symptomatic, sling excision can be performed with a risk of recurrent stress incontinence; excision of the entire mesh usually is not necessary. It assigns no evidence grade to these statements.[11]
Urinary-tract erosion or a mesh-associated fistula requires assessment of the involved mesh and the necessary excision and reconstruction. Martius tissue may reinforce the repair after appropriate mesh management. In a 26-patient retrospective cohort of Martius repairs after incontinence or prolapse surgery, postoperative complications occurred in 15 (58%) and observed success was 61% after prior mesh surgery versus 85% after native-tissue surgery (p = 0.06) at median 30-month follow-up.[33] In Mortimer's retrospective series of five women with transobturator tape extrusion greater than 1 cm, a Martius graft was followed by no ipsilateral recurrence of extrusion, although two developed transient de novo sexual problems.[22] In Blaivas's small series, the 78% overall closure rate included several fistula types and reconstructions.[11][12]
Donor morbidity and counseling
Discuss hematoma, infection, wound problems, labial asymmetry, altered sensation, persistent pain and sexual symptoms. Complication estimates depend on how actively these outcomes are sought.[2][14]
Malde's mixed-indication series of 159 patients reported two hematomas, one infection and one cosmetic dissatisfaction report; 79% rated the appearance good or excellent.[2] In a separate long-term survey of 97 analyzed women at mean 85 months, five reported labial pain, 13 numbness and nine distortion; 25 of 122 eligible women were excluded because of missing follow-up or death.[34] In a 37-woman complex urethral-surgery series, flap-bed bleeding occurred in 7/37, labial lymphorrhea in 5/37, hematoma in 2/37 and labial wound infection in 2/37.[35] The 31% sensory-symptom finding in Singh's small randomized vaginal subgroup demonstrates why one series' low event count cannot be converted into a universal “less than 5% complications” guarantee.[2][14]
Document anatomical closure separately from continence, pain, sexual function and need for further procedures. Choose an alternative flap when the labial tissue or pedicle cannot safely reach the defect.[13][15]
Comparison with other interposition flaps
| Feature | Martius | Gracilis | Peritoneal | Omental |
|---|---|---|---|---|
| Harvest site | Labium majus | Medial thigh | Peritoneum reached vaginally | Abdomen |
| Tissue and blood supply | Fibroadipose; external and internal pudendal arteries | Muscle; dominant pedicle usually from deep femoral/adductor branches, with a medial circumflex origin in some patients[29][30] | Serosa | Fat and serosa; gastroepiploic vessels |
| Reported use | Distal VVF, RVF, urethral pathology | Complex or recurrent RVF | Proximal VVF (Eilber) | Transabdominal VVF |
| RVF comparison (Pastier) | Hospital stay 2 days shorter than gracilis | Longer stay; reserved by the authors as salvage after Martius | Not applicable | Not applicable |
| Donor-site issues | Labial numbness, pain, hematoma, asymmetry | Thigh numbness, hematoma | Donor defect; potential abdominal complications with transabdominal harvest, depending on approach[31] | Abdominal incision |
Flap choice depends on defect location, tissue quality, prior surgery and reach; head-to-head comparisons are limited to the retrospective RVF series above.[10]
Related reconstruction options
- Gracilis: additional vascularized tissue for selected complex perineal defects.
- Peritoneal flap: an option for suitably accessible vaginal repairs.
- Omental flap: abdominal interposition when viable omentum can reach.
- Blandy flap: vaginal-flap urethroplasty.
- Flaps in GU reconstruction: general flap selection and handling.
Videos
References
1. Elkins TE, DeLancey JO, McGuire EJ. "The Use of Modified Martius Graft as an Adjunctive Technique in Vesicovaginal and Rectovaginal Fistula Repair." Obstet Gynecol. 1990;75(4):727–733. PMID 2314794
2. Malde S, Spilotros M, Wilson A, et al. "The Uses and Outcomes of the Martius Fat Pad in Female Urology." World J Urol. 2017;35(3):473–478. doi:10.1007/s00345-016-1887-2
3. Rothenberger RW, Feroz R, Hogarth N, et al. "Neurovascular Mapping of the Labial Fat Pad: Implications for Optimal Martius Flap Harvest." Int Urogynecol J. 2026;37(7):1997–2003 (published online 2025). doi:10.1007/s00192-025-06383-9
4. Kapriniotis K, Loufopoulos I, Gresty HCM, Greenwell TJ, Ockrim JL. "The Utility of Martius Fat Pad in the Repair of Urogenital Fistulae: Review of Current Evidence." BJU Int. 2024;134(3):365–374. doi:10.1111/bju.16350
5. Eilber KS, Kavaler E, Rodríguez LV, Rosenblum N, Raz S. "Ten-Year Experience With Transvaginal Vesicovaginal Fistula Repair Using Tissue Interposition." J Urol. 2003;169(3):1033–1036. doi:10.1097/01.ju.0000049723.57485.e7
6. Pushkar DY, Dyakov VV, Kasyan GR. "Management of Radiation-Induced Vesicovaginal Fistula." Eur Urol. 2009;55(1):131–137. doi:10.1016/j.eururo.2008.04.044
7. Malde S, Sihra N, Naaseri S, et al. "Urethral Diverticulectomy With Martius Labial Fat Pad Interposition Improves Symptom Resolution and Reduces Recurrence." BJU Int. 2017;119(1):158–163. doi:10.1111/bju.13579
8. Gaertner WB, Burgess PL, Davids JS, et al. "The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Management of Anorectal Abscess, Fistula-in-Ano, and Rectovaginal Fistula." Dis Colon Rectum. 2022;65(8):964–985. doi:10.1097/DCR.0000000000002473
9. Swindon D, Izwan S, Ng J, et al. "Martius Flaps for Low Rectovaginal Fistulae: A Systematic Review and Proportional Meta-Analysis." ANZ J Surg. 2024;94(9):1471–1479. doi:10.1111/ans.18922
10. Pastier C, Loriau J, Denost Q, et al. "Rectovaginal Fistula: What Is the Role of Martius Flap and Gracilis Muscle Interposition in the Therapeutic Strategy?" Dis Colon Rectum. 2024;67(8):1056–1064. doi:10.1097/DCR.0000000000003148
11. American College of Obstetricians and Gynecologists; American Urogynecologic Society. Management of mesh and graft complications in gynecologic surgery. Committee Opinion No. 694. Obstet Gynecol. 2017;129:e102–e108. ACOG guidance. doi:10.1097/aog.0000000000002022
12. Blaivas JG, Mekel G. "Management of Urinary Fistulas Due to Midurethral Sling Surgery." J Urol. 2014;192(4):1137–1142. doi:10.1016/j.juro.2014.04.009
13. Wilson A, Pillay S, Greenwell T. How and why to take a Martius labial interposition flap in female urology. Transl Androl Urol. 2017;6(Suppl 2):S81–S87. doi:10.21037/tau.2017.04.38.
14. Singh V, Mehrotra S, Bansal A, Akhtar A, Sinha RJ. Prospective randomized comparison of repairing vesicovaginal fistula with or without the interposition flap: result from a tertiary care Institute in Northern India. Turk J Urol. 2019;45(5):377–383. doi:10.5152/tud.2019.85233.
15. Thompson JC, Halder GE, Jeppson PC, et al. Repair of vesicovaginal fistulae: a systematic review. Obstet Gynecol. 2024;143(2):229–241. doi:10.1097/AOG.0000000000005468.
16. Safan A, Shaker H, Abdelaal A, Mourad MS, Albaz M. "Fibrin Glue Versus Martius Flap Interpositioning in the Repair of Complicated Obstetric Vesicovaginal Fistula. A Prospective Multi-Institution Randomized Trial." Neurourol Urodyn. 2009;28(5):438–441. doi:10.1002/nau.20754
17. Rangnekar NP, Imdad Ali N, Kaul SA, Pathak HR. "Role of the Martius Procedure in the Management of Urinary-Vaginal Fistulas." J Am Coll Surg. 2000;191(3):259–263. doi:10.1016/s1072-7515(00)00351-3
18. Osman NI, Mangir N, Reeves FA, et al. "The Modified Prone Jack-Knife Position for the Excision of Female Urethral Diverticula." Eur Urol. 2021;79(2):290–297. doi:10.1016/j.eururo.2020.11.016
19. Ko KJ, Suh YS, Kim TH, et al. "Surgical Outcomes of Primary and Recurrent Female Urethral Diverticula." Urology. 2017;105:181–185. doi:10.1016/j.urology.2017.02.040
20. Dykes N, Dwyer P, Rosamilia A, Zilberlicht A. "Video and Review of the Surgical Management of Recurrent Urethral Diverticulum." Int Urogynecol J. 2020;31(12):2679–2681. doi:10.1007/s00192-020-04357-7
21. Trompetto M, Realis Luc A, Novelli E, et al. "Use of the Martius Advancement Flap for Low Rectovaginal Fistulas." Colorectal Dis. 2019;21(12):1421–1428. doi:10.1111/codi.14748
22. Mortimer A, Khunda A, Ballard P. "Martius Graft for TOT Extrusion: A Case Series." Int Urogynecol J. 2016;27(1):113–116. doi:10.1007/s00192-015-2799-1
23. Zilberlicht A, Lavy Y, Auslender R, Abramov Y. "Transvaginal Repair of a Urethrovaginal Fistula Using the Latzko Technique With a Bulbocavernosus (Martius) Flap." Int Urogynecol J. 2016;27(12):1925–1927. doi:10.1007/s00192-016-3085-6
24. Lee D, Dillon BE, Zimmern PE. "Martius Labial Fat Pad Procedure: Technique and Long-Term Outcomes." Int Urogynecol J. 2015;26(9):1395–1396. doi:10.1007/s00192-015-2648-2
25. Kowalik CG. Bulbocavernosus Muscle and Fat Pad Supplement. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:664–671.
26. Waterloos M, Verla W. "Female Urethroplasty: A Practical Guide Emphasizing Diagnosis and Surgical Treatment of Female Urethral Stricture Disease." Biomed Res Int. 2019;2019:6715257. doi:10.1155/2019/6715257
27. Silva DO, Almeida R, Lima D, Paiva MB, Sarmento R. "Vaginal Repair of Post-hysterectomy Vesicovaginal Fistula With a Martius Flap: A Case Report." Cureus. 2026;18(6):e110195. doi:10.7759/cureus.110195
28. Choudhury S, Biswas P, Patel P, Sasmal S, Ahmed S. "Use of fibrin glue versus martius flap interposition in Trans-vaginal vesicovaginal fistula repair: A prospective randomized trial." Urologia. 2026;93(3):519–526. doi:10.1177/03915603261418997
29. Macchi V, Vigato E, Porzionato A, et al. "The gracilis muscle and its use in clinical reconstruction: an anatomical, embryological, and radiological study." Clin Anat. 2008;21(7):696–704. doi:10.1002/ca.20685
30. Magden O, Tayfur V, Edizer M, Atabey A. "Anatomy of gracilis muscle flap." J Craniofac Surg. 2010;21(6):1948–1950. doi:10.1097/SCS.0b013e3181f4ed81
31. Robinson IS, Blasdel G, Bluebond-Langner R, Zhao LC. "The management of intra-abdominal complications following peritoneal flap vaginoplasty." Urology. 2022;164:278–285. doi:10.1016/j.urology.2022.01.036
32. European Association of Urology. "EAU Guidelines on Non-neurogenic Female LUTS: disease management." EAU Guidelines. 2026. Guideline chapter
33. Guérin S, Carmel M, Lemack G, Khene ZE, Zimmern PE. "Martius labial fat pad use in the treatment of complications associated with prior surgery for urinary incontinence or pelvic organ prolapse." Urology. 2024;194:105–110. doi:10.1016/j.urology.2024.09.027
34. Lee D, Dillon BE, Zimmern PE. "Long-term morbidity of Martius labial fat pad graft in vaginal reconstruction surgery." Urology. 2013;82(6):1261–1266. doi:10.1016/j.urology.2013.08.032
35. Kasyan G, Tupikina N, Pushkar D. "Use of Martius flap in the complex female urethral surgery." Cent European J Urol. 2014;67(2):202–207. doi:10.5173/ceju.2014.02.art20