Peritoneal Flap
Peritoneal flaps provide thin, locally available tissue for selected fistula repairs and vaginal reconstruction. They can often be harvested through the operative access already in use. They have limited bulk, and intra-abdominal dissection adds risks including bowel injury, adhesions and internal herniation. Vascularized flaps, free peritoneal grafts and peritoneum-covered fat flaps are distinct constructs with separate outcome data.[1][2][14][25]
See Flaps in GU Reconstruction, Omental Flap, Gracilis and VRAM for other tissue options.
Anatomy and Harvest Principles
Peritoneal perfusion depends on the harvest site and preserved attachments. Winters studied the deep inferior epigastric artery territory of anterior parietal peritoneum in 30 embalmed and 15 fresh cadavers. Three named branches were identified in 70% of the embalmed specimens, but additional small branches also contributed.[1]
- Plan the flap around the actual defect, available peritoneum and route of transfer. Prior surgery, adhesions, radiation and inadequate reach may limit availability.
- Preserve a broad, viable attachment for a local flap; avoid excessive thinning, thermal damage, twisting and tension.
- Mobilize under direct vision, protecting bladder, ureters, rectum and bowel. Check both perfusion and reach before inset.
- Manage the donor defect and final closure to avoid bowel entrapment or a narrow internal-herniation aperture.[15][24][25]
Experimental urinary-tract studies demonstrate urothelial coverage of some peritoneal constructs. Free grafts require integration with their recipient bed; they do not bring an intact vascular pedicle.[2][3][26]
Vesicovaginal Fistula Repair
Peritoneal interposition is an option for selected proximal vaginal repairs and abdominal or robotic repairs when healthy tissue can reach between the closed bladder and vagina. Flap choice depends on defect location, tissue quality, prior repairs, vaginal access and the need for additional bulk.[4][5][15] In six comparative vaginal-repair studies (n=924), mostly involving Martius flaps, a 2024 systematic review estimated closure RR 0.98 (95% CI 0.96–1.01) with versus without interposition; evidence remains insufficient to determine the role of peritoneal interposition for selected complex proximal defects.[41]
| Evidence | Finding and interpretation |
|---|---|
| Raz 1993 | Transvaginal peritoneal interposition closed 9/11 difficult fistulas. One patient developed a bladder diverticulum containing a stone. Small initial technique series.[4] |
| Eilber/Raz 2003 | Among 207 vaginal repairs, 83 used peritoneum and 34 used Martius; reported initial cure was 96% and 97%, respectively. Interposition was selected for complex or previously failed repairs, and flap choice depended on proximal versus distal location.[5] |
| Yang 2025 | All 15 selected robotic repairs using a posterior-bladder “rainbow-shaped” peritoneal flap closed at reported mean follow-up of 7.8 months. Seven had prior failed repair. This small, uncontrolled series supports feasibility.[15] |
Wang's 37-patient flap-transfer series used mobilized vaginal flaps, not peritoneal interposition. Its 34/37 initial closures must not be counted as a peritoneal-flap success series.[6]
The 2026 Cochrane VVF publication is a review protocol, without completed comparative results.[16] Use the VVF pathway and vaginal fistula flap selection for repair planning. Martius, peritoneum and omentum are selected according to anatomy and tissue needs; no single flap is preferred for all recurrent or irradiated defects.
Peritoneal Vaginoplasty
Distinguish the reconstruction
The Davydov family of procedures uses pelvic peritoneum for neovaginal reconstruction. MRKH reconstruction and gender-affirming peritoneal-flap augmentation have different anatomy and technique. In common robotic gender-affirming approaches, peritoneal flaps form the proximal canal and apex and are joined to inverted penile skin, sometimes with a scrotal graft.[21][23] They do not necessarily provide a hairless canal.[21][23]
For MRKH, patient-directed vaginal dilation is generally the initial treatment. Surgery is an option after unsuccessful dilation or informed preference, with appropriate expertise and readiness for postoperative care. Surgery does not remove the need to maintain the canal.[39]
Counseling and operative scope
Peritoneal tissue avoids a bowel segment and can provide additional lining when genital skin is insufficient. These advantages must be balanced against abdominal access, dissection near the rectum and urinary tract, and the risk of stenosis, fistula, bleeding, infection or internal hernia. In Allan et al.'s matched, single-center retrospective comparison (40 patients per group), median self-reported depth at six months was 18 cm after peritoneal-flap vaginoplasty versus 15 cm after penile inversion; the study did not measure patient satisfaction.[40] The authors noted fewer revision options after a primary peritoneal flap.[40] Serous secretion is not the same as arousal-related lubrication; even the full-length flap report advised lubricant for intercourse.[21][23][24][25]
The common robotic approach combines abdominal and perineal creation of the canal, harvests peritoneum from the posterior bladder and adjacent rectal or pararectal region, and joins it to the distal lining to form a closed apex. Flap design, apical closure and support vary. Use the dedicated peritoneal vaginoplasty page for technique-specific planning; MRKH steps should not simply be transferred to a patient with a prostate.[21][23]
Outcomes that inform counseling
| Population / study | Main finding | Limits |
|---|---|---|
| MRKH: Zhou 2010, 182 patients | Reported 80% cumulative sexual satisfactory activity at 15 years after transvestibular peritoneal vaginoplasty, mean neovaginal length 9 cm at 3 months; one rectovaginal fistula and 34 cases of vault granulation | Observational.[17] |
| MRKH: Zhao 2015, 83 patients | Anatomical success reported in all patients; 95.3% functional success at 12 months | Functional assessment involved sexually active participants; no randomized technique comparison.[18] |
| MRKH: Willemsen 2015, 68 surgical patients | Functional depth averaged 7.8 cm; granulation 23%, tendency to obliteration 12% | Historical cohort with variable follow-up.[19] |
| MRKH: Uncu 2018, 27 patients | Mean length 7.9 cm at one year | Bladder injury, rectovaginal fistula and complete introital closure were each reported in individual patients.[20] |
| Gender-affirming: Dy 2021, 100 with ≥6-month follow-up out of 145 operated | Mean depth 13.6 cm (Xi) and 14.1 cm (SP); vaginal stenosis 7%, transfusion 6%, bowel obstruction 2%, RVF 1% | Retrospective platform comparison; selection and follow-up affect estimates.[21] |
| Gender-affirming: Castanon 2022, 52 patients | Mean six-month depth 14.7 cm; approximately 96% reported satisfaction | Uncontrolled laparoscopic series.[22] |
| Gender-affirming: Blasdel 2026 (online 2025), 500 consecutive cases | 425/500 had ≥1-year follow-up; 4% had a complication requiring procedural intervention and 12% elective revision. Median self-reported one-year depth 14.5 cm; 8% no longer dilating and 8% anorgasmic at last follow-up | Single-center retrospective cohort; elective revision and complication intervention are distinct outcomes. No concurrent penile-inversion control group.[38] |
A full-length anterior turnover flap is a distinct, early technique. Ratanalert and Pobpan reported ten patients, with comparable immediate-to-three-month depth in eight; one needed partial scrotal grafting because of limited reach and one developed closure after stopping dilation. Short follow-up and incomplete baseline urinary assessment prevent conclusions about long-term functional or bladder safety.[24]
In a separate 274-patient robotic series, six patients (2.2%) developed intra-abdominal complications requiring readmission and/or operative assessment. These included hematoma, abscess, bowel obstruction and internal hernias at the closure or donor site.[25] These symptoms require prompt assessment.[25]
Bladder Augmentation and Upper-Tract Reconstruction
Autoaugmentation
Peritoneal coverage of detrusor myectomy has produced limited functional improvement. In Oge's 13-patient series, capacity increased by a mean 18.6%, six achieved continence and four required subsequent enteric augmentation. The authors did not find that adding peritoneum clearly improved capacity or compliance over classical autoaugmentation. The observation that failures had small initial capacities does not validate a universal “above 30% of expected capacity” selection rule.[7]
Muscle-backed peritoneum has also been explored in animals and small historical exstrophy series. These constructs differ from a thin local peritoneal flap.[8][9][10] See augmentation principles.
Renal pelvis and ureter
Thüroff's historical series reported good or excellent urographic results in 25/31 operations using free peritoneal patches for selected renal-pelvis or UPJ defects or wrapping. A free patch is not a vascularized flap.[2]
Peritoneum can provide coverage around a repaired ureter in selected circumstances. For upper- or middle-third iatrogenic ureteral injury after emergency digestive surgery, the 2023 WSES guideline recommends a stented ureteroureterostomy covered with peritoneum or other tissue when possible .[27] Tissue coverage is an adjunct to a viable, tension-free, appropriately drained repair.[27]
A canine mucosal-avulsion model using free grafts showed epithelialized lumens, whereas a six-pig tubularized-flap study showed shrinkage, collecting-system dilation and deteriorating renal function despite maintained vascularity and focal urothelial lining. Tubularized peritoneal ureteral replacement remains investigational.[3][26] Choose established repairs according to stricture length, location, tissue quality and renal function; see the upper-tract reconstruction atlas.[43] Transplant-ureter reconstruction has distinct vascular anatomy and repair choices.[11]
Other Pelvic Applications
Pelvic peritoneal closure after ELAPE
The bladder-peritoneum flap (BLAPER) was described for selected patients with a rigid irradiated pelvis in whom primary peritoneal closure was not possible. A three-patient initial report and a subsequent 27-patient prospective stage-II study support feasibility.[12][28] The stage-II study completed reconstruction in 26/27 patients and reported major pelvic wound complications in 7.7%.[28] Follow-up of the 26 technically successful cases at a median of 47 months found one small-bowel obstruction (1/26, 3.8%) and no perineal hernias.[42]
Sacrocolpopexy mesh coverage
Covering mesh from the bowel and inserting tissue between mesh and the vaginal cuff are different interventions. Peritonealization over mesh is commonly used to separate it from abdominal viscera. Small nonrandomized studies provide insufficient evidence to determine effects of peritonealization on adhesions, bowel obstruction, mesh complications, pain or dyspareunia.[30][31] In a retrospective cohort of 178 laparoscopic sacrocolpopexies without mesh peritonealization, four reviewers judged three serious complications possibly related to nonperitonealization.[31]
Yagur's video report describes a pedicled uterovesical-peritoneum barrier at the cuff together with altered colpotomy, cuff closure and mesh placement. One illustrated case plus ten additional patients had no reported exposure at the reported follow-up.[29]
Perivesical fat flap
Perivesical fat with overlying peritoneum can be rotated on a broad attachment when local anatomy permits. Hwang's three illustrative cases support a possible alternative when omentum is unavailable.[14]
Lymphocele Prevention After RARP and PLND
The evidence no longer supports the blanket instruction to avoid peritoneal flaps. Several randomized trials support fewer lymphoceles, although results differ by study and technique.[32][33][34][36] This evidence chiefly concerns transperitoneal robot-assisted radical prostatectomy with pelvic lymph-node dissection.[32][33][34][36]
| Study | Relevant findings |
|---|---|
| PIANOFORTE 2020, 232 patients | No statistically significant reduction at 90 days. The often-quoted 9.1% was the overall symptomatic-lymphocele frequency, not an identical rate in each arm.[13] |
| ProLy 2022, 530 randomized / 475 analyzed | Any lymphocele: 22% with flap versus 33% without; symptomatic: 3.3% versus 8.1%; requiring intervention: 1.3% versus 6.8%. Follow-up was 90 days; attrition and locally selected intervention thresholds limit interpretation.[32] |
| PELYCAN 2024 (online 2023), 551 randomized | Symptomatic lymphocele: 3.7% versus 9.1% at six months; operative time was 11 minutes longer. Survey-based follow-up is a limitation.[33] |
| Pose/Michl 2025, 1,080 randomized | Lymphocele requiring intervention: 7.2% versus 8.8%, without a significant difference; no observed difference in continence or other complications at one year.[34] |
| PIANOFORTE long-term follow-up 2024 | 176/232 assessed at median 43 months; no significant flap benefit. Late lymphoceles occurred, and loss to follow-up limits certainty.[35] |
| Baumann 2026, six-RCT analysis with individual data from five | Overall synthesis favored flaps for lymphoceles requiring intervention. Technique, follow-up and reporting differed. Subgroup analyses suggested the protective effect diminishes with increasing BMI.[36] |
The EAU 2026 prostate cancer guideline states that lymphocele complications "might be reduced" by a peritoneal interposition flap, citing a systematic review of RCTs and PELYCAN, and also reports the larger negative Pose/Michl trial; it gives no formal recommendation or strength rating for the flap. A studied flap technique is a reasonable option in transperitoneal RARP with PLND, chosen with attention to the operative anatomy and local expertise.[36][37]
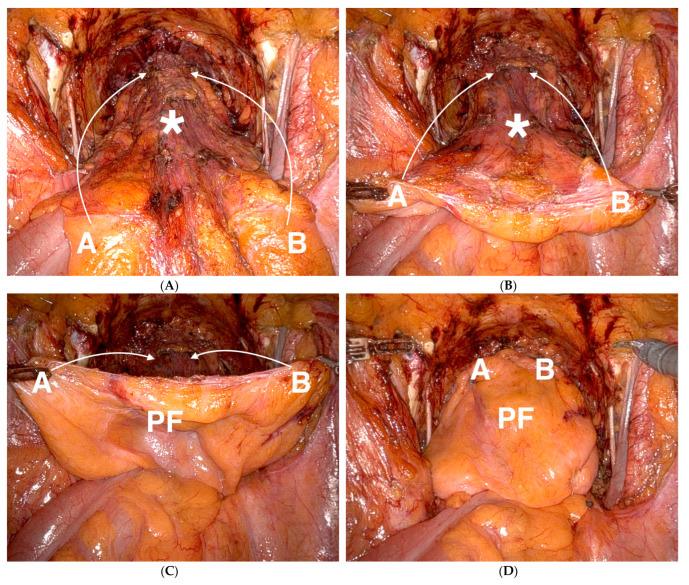
Peritoneal interposition flap after robot-assisted radical prostatectomy: (A to C) after the vesicourethral anastomosis (*) and bilateral pelvic lymph node dissection, the cranial margin of the future flap (points A and B) is fixed to the perivesical adipose tissue with clips; (D) the completed flap (PF) covers the anterior and lateral bladder surfaces facing the lymph node dissection bed. From Goßler C, et al. Cancers (Basel). 2024;16(10):1932, Figure 1 (CC BY).[35]
Practical Selection
| Need | Role of peritoneum |
|---|---|
| Thin interposition at a proximal VVF repair | Option if viable peritoneum reaches; select against Martius/omentum according to access and tissue needs |
| Additional neovaginal lining | Established specialist applications, with technique-specific counseling and ongoing canal maintenance |
| Large dead space or a skin-bearing perineal defect | Peritoneum alone usually lacks the bulk or skin required |
| Bladder capacity or a long missing ureteral segment | Experimental or limited historical constructs |
| Lymphocele prophylaxis during transperitoneal RARP with PLND | Supported by pooled randomized evidence, with differing individual-trial results |
References
1. Winters HA, Bouman MB, Boom F, Prosé LP. "The Peritoneal Free Flap — An Anatomic Study." Plast Reconstr Surg. 1997;100(5):1168–71. doi:10.1097/00006534-199710000-00015
2. Thüroff JW, Hutschenreiter G, Frohneberg D, Hohenfellner R. "Transplantation of a Free Peritoneal Patch in Surgery of the Renal Pelvis and Ureter." Eur Urol. 1981;7(5):304–11. doi:10.1159/000473246
3. Brandao LF, Laydner H, Akca O, et al. "Robot-Assisted Ureteral Reconstruction Using a Tubularized Peritoneal Flap — A Novel Technique in a Chronic Porcine Model." World J Urol. 2017;35(1):89–96. doi:10.1007/s00345-016-1840-4
4. Raz S, Bregg KJ, Nitti VW, Sussman E. "Transvaginal Repair of Vesicovaginal Fistula Using a Peritoneal Flap." J Urol. 1993;150(1):56–9. doi:10.1016/s0022-5347(17)35396-x
5. Eilber KS, Kavaler E, Rodríguez LV, Rosenblum N, Raz S. "Ten-Year Experience With Transvaginal Vesicovaginal Fistula Repair Using Tissue Interposition." J Urol. 2003;169(3):1033–6. doi:10.1097/01.ju.0000049723.57485.e7
6. Wang X, Gao Z, Li L, et al. "Clinical Efficacy of Flap Transfer Coverage in the Treatment of Vesicovaginal Fistula." Int Urogynecol J. 2023;34(8):1797–1802. doi:10.1007/s00192-023-05465-w
7. Oge O, Tekgul S, Ergen A, Kendi S. "Urothelium-Preserving Augmentation Cystoplasty Covered With a Peritoneal Flap." BJU Int. 2000;85(7):802–5. doi:10.1046/j.1464-410x.2000.00609.x
8. Weingarten JL, Cromie WJ, Paty RJ. "Augmentation Myoperitoneocystoplasty." J Urol. 1990;144(1):156–8. doi:10.1016/s0022-5347(17)39400-4
9. Büyükünal SN. "Interim Report in Humans of a Previously Described Technique in an Animal Model — Closure of Bladder Exstrophy With Rectus Abdominis Muscle Flap-II." J Urol. 1994;152(2 Pt 2):706–9. doi:10.1016/s0022-5347(17)32686-1
10. Carr MC, Docimo SG, Mitchell ME. "Bladder Augmentation With Urothelial Preservation." J Urol. 1999;162(3 Pt 2):1133–6. doi:10.1016/S0022-5347(01)68097-2
11. Novacescu D, Abol-Enein H, Latcu S, et al. "Ureteric Complications and Urinary Tract Reconstruction Techniques in Renal Transplantation — A Surgical Essay." J Clin Med. 2025;14(12):4129. doi:10.3390/jcm14124129
12. Yang T, Wei M, Deng X, Meng W, Wang Z. "A Novel Laparoscopic Technique With a Bladder Peritoneum Flap Closure for Pelvic Cavity for Patients With Rigid Pelvic Peritoneum After Neoadjuvant Radiotherapy in Laparoscopic Extralevator APE." Dis Colon Rectum. 2019;62(9):1136–1140. doi:10.1097/DCR.0000000000001435
13. Bründl J, Lenart S, Stojanoski G, et al. "Peritoneal Flap in Robot-Assisted Radical Prostatectomy." Dtsch Arztebl Int. 2020;117(14):243–250. doi:10.3238/arztebl.2020.0243
14. Hwang A, Watson M, Talluri S, Okafor H, Singh A. "A Novel Perivesical Fat Rotational Flap as an Alternative to Omental Interposition in Challenging Urological Reconstruction." Urology. 2023;182:e262–e263. doi:10.1016/j.urology.2023.08.023
15. Yang Y, Chenchen H, Shiliang W, Yuke C, Cheng S. "Robot-Assisted Vesicovaginal Fistula Repair With 'Rainbow-Shaped' Peritoneal Flap: A Single-Center Experience." Arch Gynecol Obstet. 2025;311(6):1697–1703. doi:10.1007/s00404-024-07919-y
16. Okada Y, Matsushita T, Hasegawa T, et al. "Surgical Interventions for Treating Vesicovaginal Fistula in Women." Review protocol. Cochrane Database Syst Rev. 2026;1:CD015413. doi:10.1002/14651858.CD015413
17. Zhou JH, Sun J, Yang CB, et al. "Long-Term Outcomes of Transvestibular Vaginoplasty With Pelvic Peritoneum in 182 Patients With Rokitansky's Syndrome." Fertil Steril. 2010;94(6):2281–2285. doi:10.1016/j.fertnstert.2010.02.010
18. Zhao XW, Ma JY, Wang YX, et al. "Laparoscopic Vaginoplasty Using a Single Peritoneal Flap: 10 Years of Experience in the Creation of a Neovagina in Patients With Mayer-Rokitansky-Küster-Hauser Syndrome." Fertil Steril. 2015;104(1):241–247. doi:10.1016/j.fertnstert.2015.04.014
19. Willemsen WN, Kluivers KB. "Long-Term Results of Vaginal Construction With the Use of Frank Dilation and a Peritoneal Graft (Davydov Procedure) in Patients With Mayer-Rokitansky-Küster Syndrome." Fertil Steril. 2015;103(1):220–227.e1. doi:10.1016/j.fertnstert.2014.10.014
20. Uncu G, Özerkan K, Ata B, et al. "Anatomic and Functional Outcomes of Paramesonephric Remnant-Supported Laparoscopic Double-Layer Peritoneal Pull-Down Vaginoplasty Technique in Patients With Mayer-Rokitansky-Küster-Hauser Syndrome: Uncu Modification." J Minim Invasive Gynecol. 2018;25(3):498–506. doi:10.1016/j.jmig.2017.10.015
21. Dy GW, Jun MS, Blasdel G, Bluebond-Langner R, Zhao LC. "Outcomes of Gender Affirming Peritoneal Flap Vaginoplasty Using the Da Vinci Single Port Versus Xi Robotic Systems." Eur Urol. 2021;79(5):676–683. doi:10.1016/j.eururo.2020.06.040
22. Castanon CDG, Matic S, Bizic M, et al. "Laparoscopy Assisted Peritoneal Pull-Through Vaginoplasty in Transgender Women." Urology. 2022;166:301–302. doi:10.1016/j.urology.2022.05.001
23. Jacoby A, Maliha S, Granieri MA, et al. "Robotic Davydov Peritoneal Flap Vaginoplasty for Augmentation of Vaginal Depth in Feminizing Vaginoplasty." J Urol. 2019;201(6):1171–1176. doi:10.1097/JU.0000000000000107
24. Ratanalert W, Pobpan P. "Full-Length Peritoneal Flap Vaginoplasty: A Feasible Approach for Hairless Neovaginal Reconstruction in Gender-Affirming Surgery." Plast Reconstr Surg. 2026;157(3):566–569. Published online 2025. doi:10.1097/PRS.0000000000012265
25. Robinson IS, Blasdel G, Bluebond-Langner R, Zhao LC. "The Management of Intra-Abdominal Complications Following Peritoneal Flap Vaginoplasty." Urology. 2022;164:278–285. doi:10.1016/j.urology.2022.01.036
26. Yifeng J, Shujie X, Hongbin S, et al. "Use of Free Peritoneal and Bladder Mucosal Grafts as Ureteral Mucosa Substitutes for Management of Avulsion of the Ureteral Mucosa in a Dog Model." J Endourol. 2008;22(4):729–734. doi:10.1089/end.2007.0136
27. de'Angelis N, Schena CA, Marchegiani F, et al. "2023 WSES Guidelines for the Prevention, Detection, and Management of Iatrogenic Urinary Tract Injuries (IUTIs) During Emergency Digestive Surgery." World J Emerg Surg. 2023;18(1):45. doi:10.1186/s13017-023-00513-8
28. Shen Y, Yang TH, Deng X, et al. "Closure of Pelvic Peritoneum With Bladder Peritoneum Flap Reconstruction After Laparoscopic Extralevator Abdominoperineal Excision: A Prospective Stage II Study." J Surg Oncol. 2023;128(5):851–859. doi:10.1002/jso.27382
29. Yagur Y, Kalantan A, Bukhari M, et al. "Intrafascial Colpotomy, Edge-to-Edge Closure, and Peritoneal Graft Technique for Minimizing Mesh Erosion in Concurrent Robotic Hysterectomy and Sacrocolpopexy." Int Urogynecol J. 2025;36(4):923–927. doi:10.1007/s00192-024-06012-x
30. Kulhan M, Kulhan NG, Ata N, et al. "Should the Visceral Peritoneum Be Closed Over Mesh in Abdominal Sacrocolpopexy?" Eur J Obstet Gynecol Reprod Biol. 2018;222:142–145. doi:10.1016/j.ejogrb.2018.01.027
31. van den Akker CM, Klerkx WM, Kluivers KB, et al. "Long-Term Safety, Objective and Subjective Outcomes of Laparoscopic Sacrocolpopexy Without Peritoneal Closure." Int Urogynecol J. 2020;31(8):1593–1600. doi:10.1007/s00192-019-04020-w
32. Gloger S, Ubrig B, Boy A, et al. Bilateral peritoneal flaps reduce incidence and complications of lymphoceles after robotic radical prostatectomy with pelvic lymph node dissection: the prospective randomized multicenter ProLy trial. J Urol. 2022;208:333–340. doi:10.1097/JU.0000000000002693.
33. Neuberger M, Kowalewski KF, Simon V, et al. Peritoneal flap for lymphocele prophylaxis following robotic-assisted radical prostatectomy with lymph node dissection: the randomised controlled phase 3 PELYCAN trial. Eur Urol Oncol. 2024;7:53–62. doi:10.1016/j.euo.2023.07.009.
34. Pose RM, Knipper S, Beyer B, et al. Impact of peritoneal bladder flap in robot-assisted radical prostatectomy patients on lymphoceles: a prospective randomised trial. World J Urol. 2025;43:148. doi:10.1007/s00345-025-05518-3.
35. Goßler C, May M, Weikert S, et al. Long-term follow-up of peritoneal interposition flap in symptomatic lymphocele reduction following robot-assisted radical prostatectomy: insights from the PIANOFORTE trial. Cancers. 2024;16:1932. doi:10.3390/cancers16101932.
36. Baumann G, Haney-Aubert CM, Wieland VLS, et al. Peritoneal flaps for the prevention of lymphoceles after robot-assisted radical prostatectomy: a systematic review and IPD-meta-analysis of randomized controlled trials. World J Urol. 2026;44:193. doi:10.1007/s00345-026-06254-y.
37. European Association of Urology. EAU Guidelines on Prostate Cancer. 2026. Diagnostic evaluation, sections 5.8.2.e.1–3: PLND complications and prevention. Guideline chapter.
38. Blasdel G, Hemal K, Dubach-Reinhold C, et al. Gender-affirming vaginoplasty using robotic peritoneal flap method: long-term outcomes of 500 cases. Ann Surg. 2026;283:1068–1074. Published online 2025. doi:10.1097/SLA.0000000000006621.
39. ACOG Committee Opinion No. 728. Müllerian agenesis: diagnosis, management, and treatment. 2018. ACOG guidance.
40. Allan CJ, Sljivich M, Kahan D, et al. "Robot-Assisted Peritoneal Flap Vaginoplasty Versus Penile Inversion Vaginoplasty for Gender Affirming Surgery." Andrology. 2026. Published online August 14, 2026. doi:10.1111/andr.70351
41. Thompson JC, Halder GE, Jeppson PC, et al. "Repair of Vesicovaginal Fistulae: A Systematic Review." Obstet Gynecol. 2024;143(2):229–241. doi:10.1097/AOG.0000000000005468
42. Shen Y, Yang T, Ren H, et al. "Long-term follow-up of pelvic peritoneum reconstruction with bladder peritoneum flap after extralevator abdominoperineal excision." Updates Surg. Published online July 7, 2026. doi:10.1007/s13304-026-02742-3
43. Xiong S, Wang J, Zhu W, et al. "Onlay Repair Technique for the Management of Ureteral Strictures — A Comprehensive Review." Biomed Res Int. 2020;2020:6178286. doi:10.1155/2020/6178286