Radial Forearm Free Flap (RFFF)
The radial forearm free flap (RFFF) is an option for total phallic reconstruction and a selected salvage option for complex urethral defects. Its radial-artery pedicle supplies thin, pliable tissue that can be designed for a neourethra and sensate shaft; hair distribution and eventual sensation vary by patient and design.[1][2][3] Originally described by Yang in 1981 for head-and-neck reconstruction and adapted for penile reconstruction by Chang and Hwang in 1984, it has long-term phalloplasty series.[1][4][5] Falcone and colleagues note that most authors consider it the gold standard for genital gender-affirming surgery.[9]
Flap Anatomy and Design
The RFFF is a fasciocutaneous free flap based on the radial artery and its venae comitantes, with additional superficial venous drainage via the cephalic vein:[6][7][8]
| Component | Detail |
|---|---|
| Arterial pedicle | Radial artery — large caliber (~2.5 mm), long pedicle (up to 20 cm), consistent anatomy |
| Recipient vessels | Plan recipient arterial reach, caliber and need for an interposed graft. A 2026 review of 1,976 mixed free-flap phalloplasties found higher arterial thrombosis with femoral anastomosis using a vein graft or AV loop (16.0%) than with direct femoral (0.1%) or deep inferior epigastric (1.2%) anastomosis; these observational groups differed in case complexity.[50] |
| Venous drainage | Deep (radial-artery venae comitantes) and superficial (often cephalic) systems. Plan reliable outflow and add another suitable anastomosis when indicated. Falcone's 25-patient series associated fewer than two veins with vascular complications. In a separate mixed-operation series of 38 free flaps (26 RFFF phalloplasties, 10 ALT phalloplasties, and 2 RFFF urethroplasties), 89.5% had at least two veins anastomosed and one early total flap loss (2.6%).[9][45] |
| Sensory innervation | LABCN and MABCN can be coapted to recipient sensory nerves (dorsal clitoral or penile and ilioinguinal nerves). PABC supplies much of the shaft territory and was proposed as an additional or alternative donor nerve; the cited PABC study did not test postoperative sensory benefit.[10][11][12] |
| Skin | Thin, pliable skin can support a tube-within-a-tube neourethra and shaft; hair-bearing areas need mapping and, when appropriate, hair removal before urethral use. Color match and thickness are patient-dependent.[4][8] |
| Bone | A vascularized radial-bone segment can provide rigidity in an osteocutaneous variant. Radial-bone harvest adds fracture risk: Swanson et al. reported one fracture among 13 osteocutaneous mandibular reconstructions.[13][14] |
Preoperative Assessment — the Allen Test
Before harvest, confirm ulnar collateral hand perfusion and ask about prior procedures involving the proposed donor radial artery. Prior transradial catheterization can compromise flap perfusion despite reassuring Allen and Doppler assessments; assess radial pedicle patency when this history is present.[16][17][18][49]
| Test | Notes |
|---|---|
| Clinical Allen Test (CAT) | Bedside test — compress both arteries, exsanguinate, release ulnar, observe reperfusion. Wood et al. classified reperfusion as sufficient (<5 s), indeterminate (6–10 s), or insufficient (>10 s).[18] |
| Doppler Allen Test (DAT) | In an 87-patient oral-cancer reconstruction cohort, DAT and the intraoperative surgical test agreed while CAT and DAT agreed weakly; Doppler findings changed the planned donor side or flap in 39%.[16] |
| Practical controversy | A 237-RFFF retrospective series reported no hand ischemia regardless of clinical test use. An abnormal clinical test may require further evaluation rather than automatic rejection, and ischemia has been reported even after apparently reassuring testing.[17][18] A 2023 German-speaking microsurgery expert consensus recommends an Allen test before RFFF and further vascular imaging when it is abnormal.[51] |
Application 1 — Total Phallic Reconstruction (Phalloplasty)
The primary urologic application and the most extensively studied.
Flap design techniques
- Chang and Hwang (1984). Original "tube-within-a-tube" design: a de-epithelialized strip separates inner tube (neourethra, ulnar portion) from outer tube (shaft, radial portion).[4][19]
- Gottlieb and Levine (1993). Modified design with a centrally located neourethra in continuity with a neoglans, designed to remove the circumferential meatal suture line and reduce the risk of meatal stenosis described with the Chang–Hwang design.[4][5]
- Spennato 2022. A retrospective comparison in 45 patients found no statistically significant difference in urologic complications between Chang–Hwang and Gottlieb–Levine, but reported significantly less partial flap necrosis with Gottlieb–Levine; urethral fistulas were the leading cause of revision.[19]
- Wirthmann 2018. A separate, earlier single-center series included 232 Gottlieb–Levine RFFF procedures in 229 patients. Total flap failure was 3%, and revision for urinary fistula or stricture averaged 1.3 procedures per patient; these are technique-specific observational results.[47]
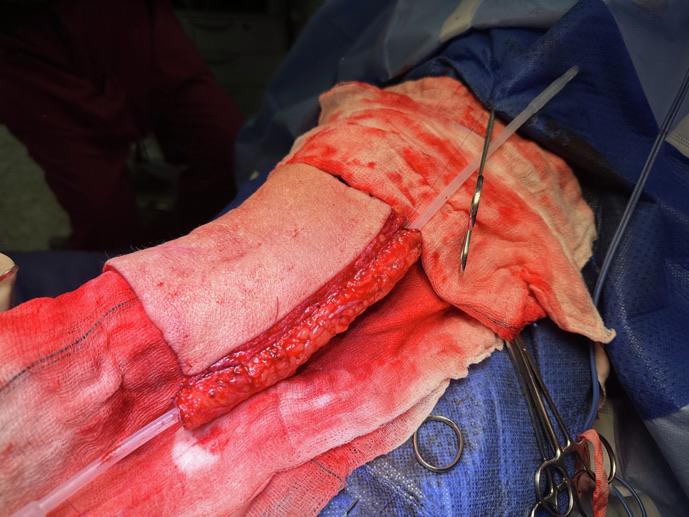
Urethra construction at the first stage: the urethral portion of the radial forearm flap is tubularized around a 16 Ch catheter after flap harvest. From Gobbo A, et al. Int J Impot Res. 2025;37(9):745-750, Fig. 4 (CC BY).[24]
Combined / modified configurations
- Modified tube-in-tube with combined flaps (Staud 2021). RFFF as the inner tube (neourethra) combined with a free ALT flap as the outer tube (shaft) in 21 patients: 100% flap survival at mean 4.4 yr; urethral fistula 38%, stricture 24%.[20]
- Single-tube phalloplasty without neourethra (Miller 2022). A two-case technical report for patients who do not seek urethral lengthening, with a cosmetic neomeatal pouch.[21]
Garaffa 2010 series (UCL, n = 115)
The landmark series:[1]
- 97% flap survival (3 total losses from venous thrombosis)[1]
- 97% patient satisfaction with cosmesis and size at median 26 months of follow-up (range 1–270 months)[1]
- 86% reported phallic sensation[1]
- Urethral strictures 7.8%; fistulae 17.4%[1]
- After revision surgery, 99% voided from the tip while standing[1]
Outcomes by indication
Gender-affirming surgery (FTM)
RFFF is often favored for phalloplasty when its skin, vascular and nerve properties fit the patient's goals. Donor-site comparisons are mostly observational; choice depends on patient goals and tissue properties.[2][3][15]
| Study | n | Flap survival | Fistula | Stricture | Satisfaction |
|---|---|---|---|---|---|
| Garaffa 2010[1] | 115 | 97% | 17.4% | 7.8% | 97% |
| Falcone 2021[9] | 25 | 96% (1 loss) | — | — | — |
| Spennato 2022[19] | 45 | — | Leading cause of revision | — | — |
| Staud 2021 (RFFF + ALT)[20] | 21 | 100% | 38% | 24% | — |
| Ascha 2018[22] | 149 RFFF vs. 64 pedicled ALT | 96.6% vs. 92.2% without partial or total neophallus loss | 10.1% (15/149) with RFFF versus 21.9% (14/64) with pALT with a minimum six-month follow-up (OR 2.50, p = 0.024); the difference was not significant in the subset followed at least one year | 14.1% (21/149) RFFF vs. 21.9% (14/64) pALT; any urethral complication 24.2% (36/149) vs. 32.8% (21/64) | — |
Netshiongolwe 2025. Most recent SR comparing RFFF versus pedicled ALT in 769 patients (614 RFFF, 155 pALT):[3]
- Flap failure: RFFF 1.9% versus pALT 0.6% (p = 0.348)[3]
- Patient satisfaction: RFFF 78% versus pALT 76.2% (NS)[3]
- Operative time: the abstract states that ALT was significantly shorter but lists 290 versus 516 minutes for RFFF versus pALT, so the direction of that comparison is unclear from the abstract.
- The authors favor RFFF, while grading comparative evidence low and identifying serious selection bias.
Wang 2026 offered a counterpoint in a 57-patient single-center retrospective cohort: RFFF had 80% overall complications versus 60% with ALT and 40.9% with pedicled abdominal flaps (all abdominal cases also had staged RFFF urethroplasty), with complications usually assessed at 90 days (minimum 30 days; p = 0.023). Urologic complications were 60% in the RFFF group; fistulas were 48%, while the 44% stricture rate was not significantly different across groups (p = 0.24).[23]
Penile cancer (post-penectomy)
-
Gobbo 2025. Narrative review of six post-penectomy studies (48 patients; follow-up 1–150 months). The authors favor RFFF and ALT as options. In one RFFF subgroup of 28 patients treated after penile cancer, 64.3% had a urethral complication. Standing urination, sexual activity and satisfaction were reported in selected patients.[24] Gobbo and colleagues describe assessing remnant urethral quality and vascularity after penectomy. They advise delaying anastomotic urethroplasty when remnant tissue is poor, particularly if graft augmentation is needed, and describe routine staging to reassess its quality.[24]
-
Falcone 2016. 10 patients with traumatic penile amputation (self-amputation, RTA, blast injury, donkey bite, Fournier's). All satisfied with size, cosmesis, and sensation at median 51 months. 6 received IPPs and engaged in penetrative sex; all with complete urethral reconstruction could void and ejaculate from the tip.[25]
Congenital penile inadequacy
- Spennato 2020. 23 patients undergoing phalloplasty for non-gender-affirming indications (DSD 34.8%, oncologic 34.8%, automutilation 8.7%, iatrogenic 8.7%, micropenis 8.7%). Total flap necrosis 8.7% (3 of 4 with any necrosis were heavy smokers). Despite high complication rates, satisfying results in experienced centers.[26]
- Massanyi 2013. 10 exstrophy patients; the flap survived in all 10; all reported protective and erogenous sensation with ability to achieve orgasm.[27]
- Harris 2021. Eleven patients with exstrophy-epispadias complex (6 RFFF, 5 pedicled ALT) had flap survival in all cases; one ALT patient died of acute pulmonary embolism, and the four surviving ALT patients required at least one debulking procedure.[44]
Application 2 — Complex Urethral Reconstruction
The RFFF is a salvage option for complex urethral defects when local tissue is unavailable or has failed:
- Dabernig 2007. 9 patients (3 post-penectomy, 6 failed GAS urethroplasty): 100% flap survival; 2 stenoses requiring revision (success 7/9 after first operation); no postoperative fistula; satisfactory uroflowmetry. RFFF is a good option "particularly when patients need extensive and long urethral reconstruction".[28]
- Lee and Khouri 1993. First description of RFFF for a 23 cm near-total urethral defect after trauma. Single-stage transfer enabled standing urination without strictures and maintained continence.[29]
- Morrison 1996. 7 patients with scarred urethras; one with hirsute forearm skin received a prefabricated hairless flap by applying a full-thickness skin graft from a non-hairy site onto the forearm fascia before flap transfer.[30]
- Erickson 2006. In one patient with anterior and posterior urethral strictures plus a rectourethral fistula after failed repairs, the anterior stricture received a buccal-mucosa ventral onlay, the fistula a York–Mason repair, and the posterior stricture an RFFF anastomosed to the inferior gluteal vessels. The authors emphasize relieving distal obstruction and using vascularized tissue to separate rectal and urethral repairs to protect fistula closure.[31]
Application 3 — Combined Flap Techniques
- RFFF with dorsalis pedis flap (Ma 2016). Fourteen patients underwent RFFF shaft and dorsalis-pedis glans reconstruction. The abstract reports 25 fully viable flaps in 11 patients and one partial dorsalis-pedis necrosis, without clearly accounting for all 14 patients' flap outcomes. It reports no urethral fistula or stenosis, sensory recovery at 3–6 months and high patient satisfaction, without clear denominators for those outcomes.[32]
- RFFF with vascularized appendix (Koshima 1999). A description in two cases using a vascularized appendix for neourethra with an osteocutaneous RFFF shaft. These two cases provide limited information on stricture rates.[33]
- Staged non-microsurgical forearm transfer (Mutaf 2001). A described reverse-flow island-flap alternative with delayed pedicle division.[13] It is not a free flap; assess hand perfusion, reach, staging and team experience for this technique.[13]
Sensory Outcomes and Nerve Coaptation
RFFF designs can include cutaneous nerves for coaptation, but the location and quality of eventual sensation vary:[10][11][12][34]
- LABCN to the dorsal nerve of the clitoris or penis (erogenous)
- MABCN to the ilioinguinal nerve (protective)
- PABC (posterior antebrachial cutaneous): recently proposed as an additional or alternative nerve innervating most of the phallic shaft, where sensation is most desired[10]
| Study | Finding |
|---|---|
| Ma 2011 (n = 45; 28 innervated, 17 non-innervated; mean 9.1-yr follow-up) | Pain perception and vibratory threshold were significantly better in innervated flaps in the distal neophallus (p < 0.01); temperature perception and two-point discrimination were also better in both proximal and distal parts[12] |
| Küenzlen 2020 (multimodal sensory evaluation, n = 20) | Fourteen of 20 patients perceived at least two tested sensory modalities, while two had no sensibility. Orgasm without difficulty was reported by 15 patients at 23 months and 20 at 54 months.[11] |
| Hu 2024 (pilot, prospective; 13 patients had neophallus testing) | Six of the 8 patients with at least two follow-up visits (75%) had sensation at the latest measurement, with an average of 73 days to regain sensation; pressure thresholds improved over time[34] |
Penile Prosthesis Implantation
An optional later stage for patients who desire prosthesis-assisted penetrative function; implantation adds device-specific risks:[35][36][37][38][39]
- Three-piece IPPs were the most commonly used devices in the 2020 nonsystematic review. In the authors’ preferred approach, cylinder wrapping with synthetic material or allograft and pubic-bone fixation are described technical steps.[35]
- 5-yr IPP retention 42–78%. Lower than in anatomic phallus.[35]
- Cohen 2017: 80% functioning at last follow-up; 70% required reoperation (mean 1.4 revisions).[36]
- Van der Sluis 2019: 32 transgender men (22 RFFF, 5 ALT, 4 combined ALT/RFFF, 1 fibular flap); 21 of 45 implanted prostheses, including revisions, were surgically replaced or removed; uneventful course in 10 of 32 (31.3%).[37]
- Pang 2025 SR (184 AMAB patients post-phalloplasty): complications up to 64.3% (infection ≤ 33.3%, mechanical failure ≤ 28.6%, malposition / migration ≤ 40%); explantation up to 40%; 80–100% satisfied with outcomes.[38]
- Young 2017 (9 prosthesis and 4 phalloplasty-only respondents): prosthesis patients scored higher in orgasmic function, intercourse satisfaction, and overall sexual satisfaction; penile perception and general and sexual quality of life scores were similar.[39]
Donor-Site Morbidity
The forearm is the principal disadvantage of the RFFF.
Motor function and strength
- Küenzlen 2022. 20 selected patients: no significant measured grip-strength difference from controls (p = 0.629), and several tested motions were preserved.[40]
- Ozturk 2024. In a cross-sectional study, 20 of 47 eligible patients participated at a median 39 months. Median Quick DASH was 7.1 (IQR 1.6–20.4), but 4/20 required donor-site reoperation, 2/20 reported chronic scar pain, and 7/20 scored 2/5 or below on SBSES, indicating an insufficient aesthetic result. Larger wound surface was associated with worse DASH sport/music scores (p = 0.037).[41]
Nerve morbidity
- Peters 2022. 37 patients: 83.8% had minimal-mild donor-site pain (VAS 0–3); 16.2% had moderate-severe pain with significant QoL impact (sleep interference, sadness, frustration, decreased hopefulness).[42]
- Küenzlen 2022. Superficial radial nerve irritation common: hypoesthesia 40%, neuroma 45%; dorsal ulnar nerve injury 0% hypoesthesia.[40]
Donor-site wound management
During flap elevation, preserve vascularized tissue over the tendons where feasible to provide a graft or dermal-template bed; Burger and colleagues describe this step in their phalloplasty donor-site series.[52]
Falcone 2023 compared FTSG with Integra plus STSG for donor closure in 34 selected patients:[43]
- The Integra-plus-STSG group had shorter reported healing time (24 versus 30 days), higher complete graft take (93.8% versus 27.8%) and higher cosmetic satisfaction (93.8% versus 66.7%).[43]
A separate 15-patient donor-site comparison (only two STSG-only recipients) found no significant improvement in patient-reported function, patient-reported scar scores or volume deficit with Integra/BTM plus STSG. A 2025 review of 15 studies and 933 RFFF donor closures found no significant major or minor wound-complication difference between full- and split-thickness grafts; certainty was low to very low, and most studies concerned head-and-neck reconstruction rather than phalloplasty.[48] A blinded clinician score differed across groups, but this very small, nonrandom comparison and the different closure timing prevent a universal matrix recommendation.[46]
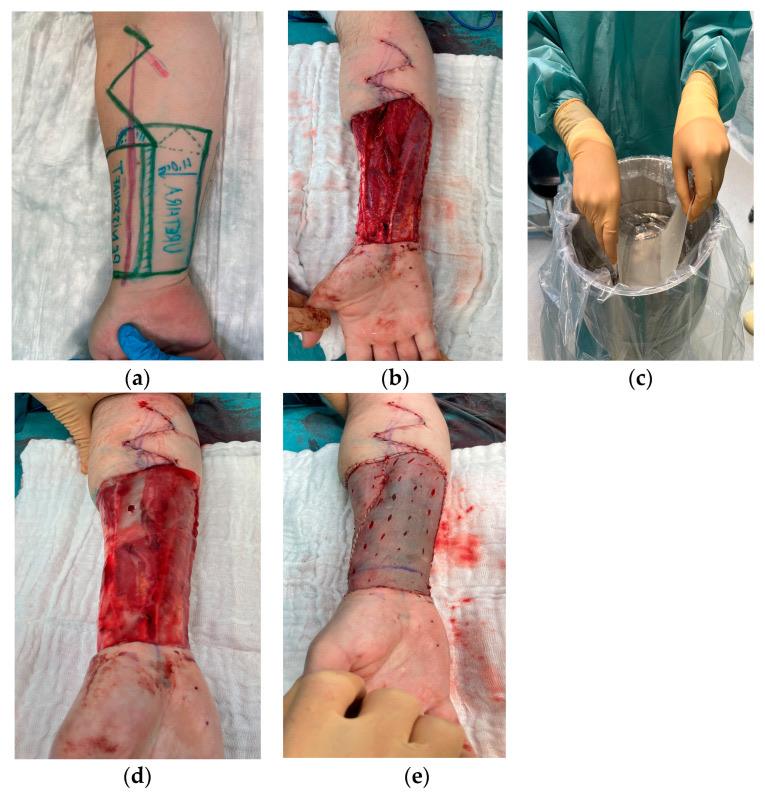
Radial forearm phalloplasty in a transmasculine patient. (a) Preoperative planning of the forearm flap with marked urethral and shaft segments. (b) Extensive donor-site surface with partially exposed tendons after flap elevation. (c) Preparation of the collagen sheet graft. (d, e) Donor site after inset of the collagen sheet and the sutured split-thickness skin graft from the lateral thigh. From Ozturk M, et al. J Clin Med. 2024;13(19):6004, Figure 1 (CC BY).[41]
Comparison with Other Phalloplasty Flaps
| Feature | RFFF | Pedicled ALT | Pedicled abdominal | Fibular osteocutaneous |
|---|---|---|---|---|
| Flap type | Free (microsurgical) | Pedicled | Pedicled | Free (microsurgical) |
| Tissue thickness | Thin | Thick (often debulked) | Variable | Thin–moderate |
| Sensory potential | Several cutaneous nerves can be coapted; result variable | LFCN can be used; result variable | Depends on design | Depends on nerve plan |
| Neourethra | Tube-in-tube flap design; native urethral lengthening and connection may be staged[5] | Tube-in-tube or staged | Staged | Tube-in-tube |
| Flap survival | Reported rates vary by cohort and follow-up | Reported rates vary by cohort and follow-up | Reported rates vary by design | Reported rates vary by cohort |
| Urethral complications | Depend on whether and how urethral lengthening is performed | Depend on urethral design and staging | Depend on urethral design and staging | Depend on urethral design and staging |
| Aesthetic outcome | Patient- and design-dependent | Patient- and design-dependent | Patient- and design-dependent | Patient- and design-dependent |
| Donor-site morbidity | Visible forearm scar, wound and sensory risks | Thigh wound and sensory risks | Abdominal wound and contour risks | Leg wound, weakness and fracture risks |
| Microsurgery required | Yes | No | No | Yes |
| Operative time | Technique and stage dependent | Technique and stage dependent | Technique and stage dependent | Technique and stage dependent |
| Patient satisfaction | Must be measured for the patient's chosen goals | Must be measured for the patient's chosen goals | Must be measured for the patient's chosen goals | Must be measured for the patient's chosen goals |
Key Takeaways
The RFFF remains a major phallic-reconstruction option because of thin pliable tissue, a useful pedicle and the opportunity for sensory nerve coaptation. Its principal applications are:
- Phalloplasty. Gender-affirming, post-penectomy, congenital penile inadequacy[1][2][3]
- Complex urethral reconstruction. Selected salvage option for extensive defects when local tissue is unavailable; no single length threshold defines its use[28][29][30]
- Combined reconstructions. RFFF neourethra with ALT shaft, or RFFF with dorsalis pedis glans[20][32]
The trade-offs include microsurgical complexity, a conspicuous donor site, possible sensory or wound morbidity and urethral complications when lengthening is undertaken. Published fistula and stricture rates vary markedly with technique, selection and follow-up. Staging, nerve coaptation and donor closure choices depend on the patient's anatomy and goals, and none has been proven to improve outcomes in every patient.[1][23][46]
See Also
- Anterolateral Thigh (ALT) Flap. Pedicled or free alternative; may be chosen for donor-site concealment, added bulk, or unsuitable forearm anatomy[22][44]
- Pedicled Penile / Preputial Skin Flap
- Buccal Mucosa Graft
- Masculinizing Procedures (GAS)
- Flaps in GU Reconstruction
References
1. Garaffa G, Christopher NA, Ralph DJ. "Total Phallic Reconstruction in Female-to-Male Transsexuals." Eur Urol. 2010;57(4):715–722. doi:10.1016/j.eururo.2009.05.018
2. Yao A, Ingargiola MJ, Lopez CD, et al. "Total Penile Reconstruction: A Systematic Review." J Plast Reconstr Aesthet Surg. 2018;71(6):788–806. doi:10.1016/j.bjps.2018.02.002
3. Netshiongolwe T, Mitchell S, Kathiravelupillai S, et al. "Pedicled Flaps Versus Free Radial Forearm Flap for Phalloplasty in Female to Male Gender-Confirming Surgery: A Systematic Review." Ann Plast Surg. 2025. doi:10.1097/SAP.0000000000004502
4. Gottlieb LJ, Levine LA. "A New Design for the Radial Forearm Free-Flap Phallic Construction." Plast Reconstr Surg. 1993;92(2):276–283. doi:10.1097/00006534-199308000-00012
5. Gottlieb L, Cripps C. "An Update on Gender-Affirming Phallus Construction Using the Radial Forearm Free-Flap." Neurourol Urodyn. 2023;42(5):963–972. doi:10.1002/nau.25103
6. Médard de Chardon V, Balaguer T, Chignon-Sicard B, et al. "The Radial Forearm Free Flap: A Review of Microsurgical Options." J Plast Reconstr Aesthet Surg. 2009;62(1):5–10. doi:10.1016/j.bjps.2008.06.053
7. Mühlbauer W, Herndl E, Stock W. "The Forearm Flap." Plast Reconstr Surg. 1982;70(3):336–344. doi:10.1097/00006534-198209000-00007
8. Hentz VR, Pearl RM, Grossman JA, Wood MB, Cooney WP. "The Radial Forearm Flap: A Versatile Source of Composite Tissue." Ann Plast Surg. 1987;19(6):485–498. doi:10.1097/00000637-198712000-00001
9. Falcone M, Preto M, Timpano M, et al. "The Surgical Outcomes of Radial Artery Forearm Free-Flap Phalloplasty in Transgender Men: Single-Centre Experience and Systematic Review of the Current Literature." Int J Impot Res. 2020;33(7):737–745. doi:10.1038/s41443-021-00414-x
10. Peters BR, Richards HW, Berli JU. "Optimizing Innervation in Radial Forearm Phalloplasty: Consider the Posterior Antebrachial Cutaneous Nerve." Plast Reconstr Surg. 2023;151(1):202–206. doi:10.1097/PRS.0000000000009771
11. Küenzlen L, Nasim S, van Neerven S, et al. "Multimodal Evaluation of Functional Nerve Regeneration in Transgender Individuals After Phalloplasty With a Free Radial Forearm Flap." J Sex Med. 2020;17(5):1012–1024. doi:10.1016/j.jsxm.2020.02.014
12. Ma S, Cheng K, Liu Y. "Sensibility Following Innervated Free Radial Forearm Flap for Penile Reconstruction." Plast Reconstr Surg. 2011;127(1):235–241. doi:10.1097/PRS.0b013e3181fad371
13. Mutaf M. "Nonmicrosurgical Use of the Radial Forearm Flap for Penile Reconstruction." Plast Reconstr Surg. 2001;107(1):80–86. doi:10.1097/00006534-200101000-00013
14. Swanson E, Boyd JB, Manktelow RT. "The Radial Forearm Flap: Reconstructive Applications and Donor-Site Defects in 35 Consecutive Patients." Plast Reconstr Surg. 1990;85(2):258–266. doi:10.1097/00006534-199002000-00016
15. Safer JD, Tangpricha V. "Care of Transgender Persons." N Engl J Med. 2019;381(25):2451–2460. doi:10.1056/NEJMcp1903650
16. Tousidonis M, Escobar JIS, Caicoya SO, et al. "Preoperative Doppler Ultrasonography Allen Test for Radial Forearm Free Flap in Oral Cancer Reconstruction: Implications in Clinical Practice." J Clin Med. 2021;10(15):3328. doi:10.3390/jcm10153328
17. Bula D, Opyrchał J, Walczak D, Krakowczyk Ł, Maciejewski A. "Does the Use of the Allen Test Is an Absolute Myth? A Novel Look at the Preoperative Evaluation of the Routine Procedure Before Harvesting Radial Forearm Free Flap." J Craniofac Surg. 2025;36(4):1124–1126. doi:10.1097/SCS.0000000000010979
18. Wood JW, Broussard KC, Burkey B. "Preoperative Testing for Radial Forearm Free Flaps to Reduce Donor Site Morbidity." JAMA Otolaryngol Head Neck Surg. 2013;139(2):183–186. doi:10.1001/jamaoto.2013.1357
19. Spennato S, Ederer IA, Borisov K, et al. "Radial Forearm Free Flap Phalloplasty in Female-to-Male Transsexuals — A Comparison Between Gottlieb and Levine's and Chang and Hwang's Technique." J Sex Med. 2022;19(4):661–668. doi:10.1016/j.jsxm.2022.01.004
20. Staud CJ, Zaussinger M, Duscher D, et al. "A Modified Microvascular 'Tube-in-Tube' Concept for Penile Construction in Female-to-Male Transsexuals: Combined Radial Forearm Free Flap With Anterolateral Thigh Flap." J Plast Reconstr Aesthet Surg. 2021;74(9):2364–2371. doi:10.1016/j.bjps.2021.01.016
21. Miller TJ, Saberski ER, Safa B, Watt AJ. "Modification of the Single-Tube Radial Forearm Phalloplasty Technique to Allow for Urinary Meatal Reconstruction: A Report of Two Cases." Microsurgery. 2022;42(7):728–731. doi:10.1002/micr.30950
22. Ascha M, Massie JP, Morrison SD, Crane CN, Chen ML. "Outcomes of Single Stage Phalloplasty by Pedicled Anterolateral Thigh Flap Versus Radial Forearm Free Flap in Gender Confirming Surgery." J Urol. 2018;199(1):206–214. doi:10.1016/j.juro.2017.07.084
23. Wang E, Cleff B, Basta A, et al. "Flap Choice in Gender Affirming Phalloplasty Affects Postoperative Complication Rates." Microsurgery. 2026;46(1):e70154. doi:10.1002/micr.70154
24. Gobbo A, Christopher AN, di Giovanni A, et al. "Sexual and Urological Reconstruction Following Penectomy for Penile Cancer: Phalloplasty." Int J Impot Res. 2025. doi:10.1038/s41443-025-01161-z
25. Falcone M, Garaffa G, Raheem A, Christopher NA, Ralph DJ. "Total Phallic Reconstruction Using the Radial Artery Based Forearm Free Flap After Traumatic Penile Amputation." J Sex Med. 2016;13(7):1119–1124. doi:10.1016/j.jsxm.2016.05.003
26. Spennato S, Burger AE, Schlosshauer T, et al. "Microsurgical Phalloplasty in Nontranssexual Patients — Considerations After a Retrospective Single-Center Analysis of 23 Cases." Urology. 2020;141:154–161. doi:10.1016/j.urology.2020.03.038
27. Massanyi EZ, Gupta A, Goel S, et al. "Radial Forearm Free Flap Phalloplasty for Penile Inadequacy in Patients With Exstrophy." J Urol. 2013;190(4 Suppl):1577–1582. doi:10.1016/j.juro.2012.12.050
28. Dabernig J, Shelley OP, Cuccia G, Schaff J. "Urethral Reconstruction Using the Radial Forearm Free Flap: Experience in Oncologic Cases and Gender Reassignment." Eur Urol. 2007;52(2):547–553. doi:10.1016/j.eururo.2007.01.004
29. Lee GW, Khouri RK. "Reconstruction of a Near Total Male Urethral Defect With a Microvascular Free Flap." J Urol. 1993;149(6):1548–1550. doi:10.1016/s0022-5347(17)36444-3
30. Morrison WA, Webster HR, Kumta S. "Urethral Reconstruction Using the Radial Artery Forearm Free Flap: Conventional and Prefabricated." Plast Reconstr Surg. 1996;97(2):413–419. doi:10.1097/00006534-199602000-00021
31. Erickson BA, Dumanian GA, Sisco M, et al. "Rectourethral Fistula Associated With Two Short Segment Urethral Strictures in the Anterior and Posterior Urethra: Single-Stage Reconstruction Using Buccal Mucosa and a Radial Forearm Fasciocutaneous Free Flap." Urology. 2006;67(1):195–198. doi:10.1016/j.urology.2005.08.002
32. Ma S, Cheng K, Liu Y, Chen F. "A New Surgical Procedure for Penile Reconstruction by Combined Free Radial Forearm Flap and Dorsalis Pedis Flap." Urology. 2016;97:232–237. doi:10.1016/j.urology.2016.03.076
33. Koshima I, Inagawa K, Okuyama N, Moriguchi T. "Free Vascularized Appendix Transfer for Reconstruction of Penile Urethras With Severe Fibrosis." Plast Reconstr Surg. 1999;103(3):964–969. doi:10.1097/00006534-199903000-00030
34. Hu S, Oles N, Reiche E, et al. "Early Penile and Donor Site Sensory Outcomes After Innervated Radial Forearm Free Flap Phalloplasty: A Pilot Prospective Study." Microsurgery. 2024;44(6):e31228. doi:10.1002/micr.31228
35. Kocjancic E, Jaunarena JH, Schechter L, Acar Ö. "Inflatable Penile Prosthesis Implantation After Gender Affirming Phalloplasty With Radial Forearm Free Flap." Int J Impot Res. 2020;32(1):99–106. doi:10.1038/s41443-019-0153-8
36. Cohen AJ, Bhanvadia RR, Pariser JJ, et al. "Novel Technique for Proximal Bone Anchoring of Penile Prosthesis After Radial Forearm Free Flap Neophallus." Urology. 2017;105:2–5. doi:10.1016/j.urology.2017.01.016
37. van der Sluis WB, Pigot GLS, Al-Tamimi M, et al. "A Retrospective Cohort Study on Surgical Outcomes of Penile Prosthesis Implantation Surgery in Transgender Men After Phalloplasty." Urology. 2019;132:195–201. doi:10.1016/j.urology.2019.06.010
38. Pang KH, Christopher N, Ralph DJ, Lee WG. "Insertion of Erectile Device Following Phalloplasty in Individuals Assigned Male at Birth: A Systematic Review." J Sex Med. 2025. doi:10.1093/jsxmed/qdaf019
39. Young EE, Friedlander D, Lue K, et al. "Sexual Function and Quality of Life Before and After Penile Prosthesis Implantation Following Radial Forearm Flap Phalloplasty." Urology. 2017;104:204–208. doi:10.1016/j.urology.2017.01.031
40. Küenzlen L, Nasim S, Neerven SV, et al. "Multimodal Evaluation of Donor Site Morbidity in Transgender Individuals After Phalloplasty With a Free Radial Forearm Flap: A Case-Control Study." J Plast Reconstr Aesthet Surg. 2022;75(1):25–32. doi:10.1016/j.bjps.2021.05.068
41. Ozturk M, Wellenbrock S, Wiebringhaus P, et al. "Functionality and Scar Evaluation of the Donor Site in Extended Radial Forearm Flap Phalloplasty: How Affected Is the Arm in Day-to-Day Life?" J Clin Med. 2024;13(19):6004. doi:10.3390/jcm13196004
42. Peters BR, Sikora Z, Timmins BH, Berli JU. "Nerve Morbidity at the Radial Forearm Donor Site Following Gender-Affirming Phalloplasty." J Plast Reconstr Aesthet Surg. 2022;75(10):3836–3844. doi:10.1016/j.bjps.2022.06.075
43. Falcone M, Preto M, Ciclamini D, et al. "Bioengineered Dermal Matrix (Integra®) Reduces Donor Site Morbidity in Total Phallic Construction With Radial Artery Forearm Free-Flap." Int J Impot Res. 2023. doi:10.1038/s41443-023-00775-5
44. Harris TGW, Manyevitch R, Wu WJ, et al. "Pedicled Anterolateral Thigh and Radial Forearm Free Flap Phalloplasty for Penile Reconstruction in Patients With Bladder Exstrophy." J Urol. 2021;205(3):880–887. doi:10.1097/JU.0000000000001404
45. Yuan N, Ray EC, Smith S, Garcia MM. "Primary Use of the Deep Inferior Epigastric Pedicle for Free-flap Phalloplasty: Rationale, Technique, and Outcomes." Plast Reconstr Surg Glob Open. 2022;10(6):e4307. doi:10.1097/GOX.0000000000004307. Full text.
46. Marquez JL, Nuckles B, Tausinga T, et al. "Analysis of the Radial Forearm Phalloplasty Donor Site: Do Dermal Matrices Improve Donor Site Morbidity?" Plast Reconstr Surg Glob Open. 2024;12(9):e6114. doi:10.1097/GOX.0000000000006114. Full text.
47. Wirthmann AE, Majenka P, Kaufmann MC, et al. "Phalloplasty in Female-to-Male Transsexuals by Gottlieb and Levine’s Free Radial Forearm Flap Technique—A Long-Term Single-Center Experience Over More than Two Decades." J Reconstr Microsurg. 2018;34(4):235–241. doi:10.1055/s-0037-1608656
48. Moors JJE, Xu Z, Xie K, et al. "Full-thickness skin graft versus split-thickness skin graft for fasciocutaneous radial forearm free flap donor site closure: a systematic review and meta-analysis." Syst Rev. 2025;14(1):118. doi:10.1186/s13643-025-02863-7
49. Zhang SL, Chung BZW, Ng HW. "Arterial occlusion secondary to prior cardiac catheterization in a radial forearm flap—lessons learnt from an unusual case." J Surg Case Rep. 2024;2024(6):rjae391. doi:10.1093/jscr/rjae391
50. Gaston J, Fodor R, Rampazzo A, Fascelli M, Bassiri Gharb B. "Recipient Vessel Selection in Free Flap Phalloplasty: A Systematic Review and Single-Arm Meta-Analysis." Microsurgery. 2026;46(5):e70251. doi:10.1002/micr.70251
51. Küenzlen L, Wallmichrath JC, Küntscher MV, et al. "Choice of flaps for phalloplasty: what is the contemporary standard? Consensus Statement of the German-Speaking Society for Microsurgery of Peripheral Nerves and Vessels." Handchir Mikrochir Plast Chir. 2023;55(6):427–436. doi:10.1055/a-2134-5891
52. Burger A, Kiehlmann M, Gruenherz L, et al. "Donor Site Defect Coverage of the Forearm with Dermal Substitute After Harvesting Radial Forearm Free Flap for Phalloplasty: Is MatriDerm® Worth the Effort?" Indian J Surg. 2023;85:1356–1361. doi:10.1007/s12262-023-03705-3