Rhomboid (Limberg) Flap
The rhomboid (Limberg) flap is a local transposition flap designed to redistribute closure tension when straight-line repair would be difficult or distort nearby structures. Limberg's geometric design is widely used in sacrococcygeal pilonidal surgery and can be adapted to selected vulvar, genital, and perineal defects when adjacent tissue and its perfusion are suitable.[1][2]
Geometric Principle
The Limberg flap is built around a rhombus (equilateral parallelogram) with angles of 60° and 120°. The defect is either created as or converted into a rhomboid shape, and the flap is designed as follows:[2][3][4]
- The short diagonal of the rhombus is extended by a length equal to one side of the rhombus.
- A second incision is made from the end of this extension, parallel to the adjacent side, also equal in length to one side.
- This creates a second rhombus adjacent to the defect.
- Elevate the flap at a depth matching the defect, preserve the dermal-subdermal vascular plexus during hemostasis, and test transposition for tension or distortion. Close the donor site first, then inset the flap with deep support as needed.[29]
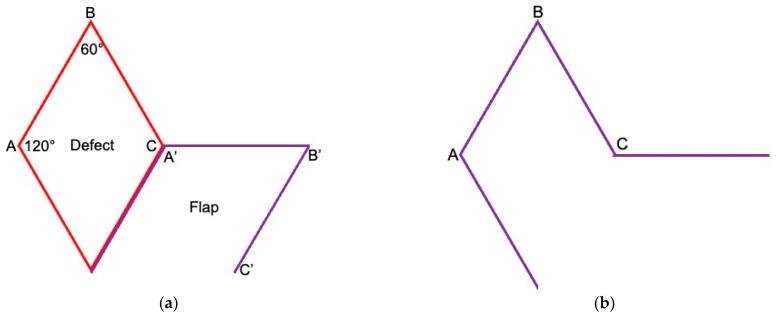
Principle of the Limberg rhombic flap. (a) The rhomboid defect (red) has equal sides and angles of 60° and 120°; the flap (purple) has the same dimensions, is planned as an extension of the short diagonal (A to C = A′ to B′), and its second incision (B′ to C′) runs parallel to the defect. The flap base is not incised; A′ is sutured to A, B′ to B and C′ to C. (b) Shape of the final scar after closure of the defect and donor site. From Fansa H, Linder S. Cancers (Basel). 2024;16(17):3101, Figure 2 (CC BY).[4]
Four possible Limberg flaps can be designed around a rhomboid defect. Select the donor site by available skin laxity, the line of maximal extensibility (LME), scar orientation, local perfusion, and the structures that must not be displaced.[2][3]
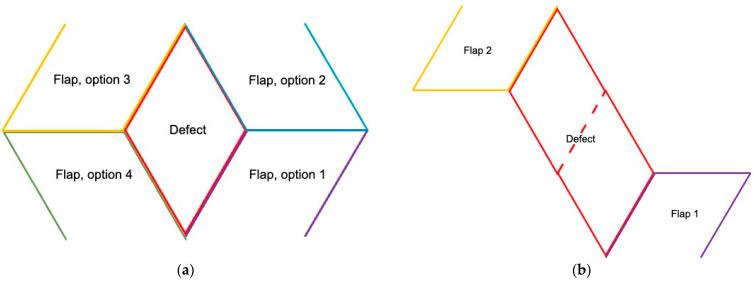
(a) Because the flap can be harvested at 90° intervals around the defect, four Limberg options (1 to 4) exist; the preferred option adds matching volume and leaves the best-concealed or most elastic donor site for primary closure. (b) A larger defect (red) divided into two rhombi (dotted line), each closed by a separate Limberg flap (flaps 1 and 2). From Fansa H, Linder S. Cancers (Basel). 2024;16(17):3101, Figure 3 (CC BY).[4]
Key geometric properties
| Property | Detail |
|---|---|
| Geometric proportions | In the standard design, flap sides are planned from the rhombus side length.[2][4] |
| Perfusion | The usual local cutaneous flap depends on its tissue base and local vascularity. Assess prior incisions, radiation, undermining, and inset tension.[5][6] |
| Stress redistribution | In a finite-element model, Rajabi and colleagues' optimized design reduced maximum von Mises stress by 43% versus standard Limberg for a 60° defect and by 53% on average versus Dufourmentel across modeled configurations.[7] |
Limberg vs. Dufourmentel
The Dufourmentel flap (1962) is the principal modification of the Limberg:[8][9]
- Uses a broader base than the classical Limberg design; actual perfusion still depends on the patient and operative field
- Accommodates defects with angles other than the strict 60° / 120° of the Limberg design
- A 2024 Cochrane review's direct modified-versus-standard Limberg comparison in pilonidal disease drew on one trial of 204 participants; estimates for recurrence and wound outcomes were imprecise.[10]
- Both are classified as "rhombic transposition flaps" and share the same fundamental geometric principle
Pilonidal Sinus Disease — the signature application
The Limberg flap is most extensively studied in sacrococcygeal pilonidal sinus disease (PSD), an off-midline closure application. The 2024 European Society of Coloproctology guideline favors off-midline closure after excisional surgery and advises against primary midline closure (moderate level of evidence); it does not prefer one off-midline flap over another.[26] After rhomboid excision, a neighboring cutaneous or fasciocutaneous transposition flap is moved into the defect; this is not a gluteus-maximus muscle rotation flap.[11][15]
Outcomes in PSD
| Outcome | Result |
|---|---|
| Network meta-analysis of 39 RCTs (5,061 patients) | Modified Limberg was among favorable PSD procedures for recurrence in an indirect treatment network.[12] |
| Recurrence synthesis (11,730 RCT patients across procedures) | Limberg/Dufourmentel recurrence was estimated at 0.6% at 12 months and 1.8% at 24 months in RCTs; 11,730 is the review-wide RCT sample, not the flap subgroup denominator. A separate synthesis of 139 non-RCTs (12,384 flap patients across follow-up intervals) estimated 11.4% recurrence at 120 months (95% CI 9.2–13.7%).[13] |
| Global series | Limberg / Dufourmentel recurrence 0.3% at 12 mo (95% CI 0.2–0.4)[14] |
| Arnous RCT (n = 60) | Limberg flap vs. primary midline closure: 0% vs. 20% recurrence (p = 0.02) at mean follow-up of 16.4 vs. 17.0 months, respectively; total complications were 43.3% (13/30) vs. 46.6% (14/30) (p = 0.79), while cosmetic satisfaction favored primary closure.[15] |
| Cochrane 2024: off-midline versus conventional midline closure (13 RCTs, 1,492 participants for recurrence) | Off-midline closure probably lowers recurrence (1.5% versus 6.8%, RR 0.22) and wound infection (3.8% versus 11.7%); moderate-certainty evidence[10] |
| Cochrane 2024: Karydakis versus Limberg flap (9 RCTs, 890 participants for recurrence) | Little to no difference in time to healing (6 RCTs), recurrence (5.1% versus 4.5%), infection, dehiscence or return to work; low- to moderate-certainty evidence[10] |
Wound-complication rates with Limberg flap in PSD range from 0% to 26.5%, primarily hematoma or seroma and dehiscence from the large area of tissue mobilization.[11]
PSD is a colorectal indication.
Urologic Applications
Epispadias-exstrophy complex — penile elongation and genital reconstruction
The earliest described urologic application is in the epispadias-exstrophy complex. Kramer and Jackson (1986) described bilateral rhomboid flaps for penile elongation and genital reconstruction in 10 young males:[16]
- The technique accurately defines the penopubic angle
- The authors described protection of deeper structures, including the verumontanum and ejaculatory ducts.
- The authors reported satisfactory cosmetic and functional results in their 10 cases, without a controlled comparison
Kramer and Jackson's technique combined partial release of the corpora cavernosa from the pubic rami with laterally based rhomboid flaps for dorsal penile skin coverage; lengthening was the combined operation.[16][25]
Scrotal and perineal reconstruction
The rhomboid flap is a possible local option for a selected scrotal or perineal skin defect when neighboring tissue can reach without undue tension.[17] A 2025 systematic review reported plastic-surgery involvement in 33% of scrotal SCC and 67% of extramammary Paget's disease Mohs cases.[17]
Perineal reconstruction after Fournier's gangrene
V-Y advancement and pudendal-thigh flaps are described more often in Fournier's reconstruction; a rhomboid flap may be considered when viable adjacent tissue permits low-tension inset. In one 29-man retrospective series, unilateral or bilateral Limberg flaps covered 21 hemiscrotal and eight defects involving >50% of the scrotal surface; 4/29 developed seroma with dehiscence and none had flap loss at mean 16-month follow-up.[28] The 1.6% pooled flap-loss figure in a 2026 review of 619 patients and 625 flaps combined several flap designs.[18]
Urogynecologic Applications
Vulvar reconstruction after oncologic resection
Local rhomboid flaps are among the options described for selected vulvar defects, especially when a neighboring donor site offers enough laxity and coverage without distorting the introitus or urethra.
Höckel and Dornhöfer proposed a defect-classification approach that includes Limberg flaps among multiple reconstructive choices. Höckel and Dornhöfer describe bilateral rhomboid configurations for selected commissural or peripheral defects.[6]
- Anterior or posterior commissural defects when local tissue movement preserves anatomy
- Peripheral vulvar defects with an appropriate adjacent donor site
- Unilateral or bilateral designs according to defect extent, prior treatment, perfusion, and the authors' scheme
Höckel et al.'s vulvar field resection trial enrolled 97 women; 94 were treated per protocol, and 46/97 women had moderate or severe postoperative complications in the intention-to-treat analysis.[19]
Local perfusion, donor-site laxity, previous operations and radiation, and the distance needed for transposition constrain the design.[6] Larger or compromised defects may call for a different local, regional, or perforator-based option.[6]
Comparative outcomes in vulvar cancer — rhomboid vs. V-Y vs. gluteal-thigh
A single-center nonrandomized retrospective by Tock et al. (2019) described flap outcomes in 61 women undergoing radical vulvar surgery. The groups differ by the defects and procedures for which each design was selected.[20]
| Parameter | Gluteal-thigh flap (GTF) | Rhomboid flap (RF) | V-Y flap (VYF) | p |
|---|---|---|---|---|
| Median hospital stay | 24 days | 17 days | 14 days | 0.002 |
| 60-day reoperation | 69% | 41% | 25% | 0.04 |
| Most common complication | Partial necrosis | Partial necrosis | Partial necrosis | — |
| Overall / recurrence-free survival | Comparable | Comparable | Comparable | NS |
The authors favored V-Y flaps for larger defects in their practice. The observed shorter stays and lower reoperation proportions are unadjusted comparisons. A rhomboid flap remains a possible option for a smaller, well-defined defect with suitable adjacent tissue.[20]
A prospective study of 136 locoregional flaps in 69 women reported 126/136 (92.6%) with no-to-mild complications at day 7 and 113/136 (83.1%) at days 8–30. Rhomboid flaps were only one design in the pooled cohort. The 12-month symptom results came from respondent subsets, not every enrolled woman.[21]
Defect-based vulvar reconstruction algorithm
Published location-based schemes, including a recent single-center Toulouse algorithm, offer planning examples; they should be adapted to the actual defect, perfusion, oncologic margins, prior radiation, and patient goals.[6][22][23] The 2023 ESGO guideline requires reconstructive expertise in the multidisciplinary team for early and advanced vulvar cancer and bases reconstruction choice on patient and tumor characteristics and team experience [IV, B].[27]
- Small posterior / commissure defects: local rhomboid, V-Y, or other nearby tissue may be feasible
- Lateral / hemivulvectomy defects: consider medial-thigh or pudendal-region tissue according to reach and perfusion
- Anterior defects: protect urethral and clitoral position; pubolabial options may be useful
- Total or extended defects: regional or musculocutaneous flaps may be needed to bring adequate tissue into the field
Comparison with Other Geometric Flap Techniques
| Feature | Rhomboid (Limberg) | Z-plasty | Y-V plasty | V-Y advancement |
|---|---|---|---|---|
| Mechanism | Transposition into a rhomboid defect | Transposition of two triangular flaps | Advancement along contracture axis | Advancement into a defect |
| Primary effect | Defect coverage with tension redistribution | Scar reorientation and ideal geometric length gain | In selected procedures, lengthening by advancing a Y-shaped flap | Tissue advancement into a defect |
| Lengthening | Not its primary goal | ~73% theoretical gain for a 60° design; actual gain varies[24] | Procedure- and tissue-dependent | Procedure- and tissue-dependent |
| Vascularization | Usually local cutaneous tissue-base perfusion | Local cutaneous tissue-base perfusion; tip compromise is possible | Depends on tissue and procedure | Subcutaneous, fasciocutaneous, or perforator-based |
| Best for | Small–moderate defects with adequate adjacent tissue | Circumferential contractures, scar reorientation | Stenotic segments (BNC, UPJ) | Perineal / vulvar defect filling, penile lengthening |
| Urologic niche | Epispadias-exstrophy, scrotal reconstruction | Hypospadias revision, phimosis, frenuloplasty | Bladder-neck contracture, UPJ obstruction | Penile lengthening, Fournier's reconstruction |
| Urogynecologic niche | Small posterior vulvar defects | Transverse vaginal septum, vaginal constriction | — | Vulvovaginal oncologic defects, perineal reconstruction |
The rhomboid flap is a useful geometric local transposition option when neighboring tissue can close the defect without excessive tension or distortion. It does not require microsurgical anastomosis, but the required donor-site closure and vascularity still need to be assessed for each patient. Larger or compromised vulvar, perineal, or genital defects may require other local, regional, or perforator-based designs; V-Y is a movement pattern, not one vascular category.[6][20][22]
Technical Pearls
- Compare the four possible donor sites against skin laxity, the line of maximal extensibility, perfusion, and the direction in which closure would pull structures that must not be displaced.[3]
- Plan a rhomboid defect deliberately when using classical Limberg geometry; do not extend an oncologic or functional resection solely to force an ideal drawing.
- Assess the flap base and final inset. Reconsider the design if closure would be tight or tissue perfusion is compromised.
- For commissural vulvar defects, assess whether one or two local flaps can preserve midline contour and introital function in the individual case.[6]
- In irradiated or scarred fields, assess viable donor tissue carefully and consider a regional or musculocutaneous option when local perfusion is inadequate.
- Rajabi's finite-element result is a design hypothesis about modeled stress without clinical outcome data.[7]
See Also
- Z-Plasty. The scar-reorientation counterpart
- Y-V Plasty. Single-axis lengthening
- V-Y Advancement Flap. Advancement into a defect
- Flaps in GU Reconstruction
- Plastic Surgery Principles
References
1. Goldman A, Wollina U. "The Limberg Rhomboid Flap: History, Creator, and Importance in Plastic Surgery." Clin Dermatol. 2026. doi:10.1016/j.clindermatol.2026.01.013
2. Borges AF. "The Rhombic Flap." Plast Reconstr Surg. 1981;67(4):458–466. doi:10.1097/00006534-198104000-00007
3. Hwang K, Yoon JM, Park TJ, Park CY. "Teaching Models for Correct Rhombic Flaps." J Craniofac Surg. 2023;34(7):2161–2162. doi:10.1097/SCS.0000000000009349
4. Fansa H, Linder S. "The Local Rhombus-Shaped Flap — An Easy and Reliable Technique for Oncoplastic Breast Cancer Surgery and Defect Closure in Breast and Axilla." Cancers. 2024;16(17):3101. doi:10.3390/cancers16173101
5. Calhoun KH, Seikaly H, Quinn FB. "Teaching Paradigm for Decision Making in Facial Skin Defect Reconstructions." Arch Otolaryngol Head Neck Surg. 1998;124(1):60–66. doi:10.1001/archotol.124.1.60
6. Höckel M, Dornhöfer N. "Vulvovaginal Reconstruction for Neoplastic Disease." Lancet Oncol. 2008;9(6):559–568. doi:10.1016/S1470-2045(08)70147-5
7. Rajabi A, Dolovich AT, Johnston JD. "From the Rhombic Transposition Flap Toward Z-Plasty: An Optimized Design Using the Finite Element Method." J Biomech. 2015;48(13):3672–3678. doi:10.1016/j.jbiomech.2015.08.021
8. Moreno-Casas G, Pereira-González A, Rodríguez-Nevado I, et al. "Triple Dufourmentel Hexagonal Flap for Scalp Reconstruction." Exp Dermatol. 2023;32(5):694–698. doi:10.1111/exd.14764
9. Fee WE, Gunter JP, Carder HM. "Rhomboid Flap Principles and Common Variations." Laryngoscope. 1976;86(11):1706–1711. doi:10.1288/00005537-197611000-00013
10. Cai Z, Zhao Z, Ma Q, et al. "Midline and Off-Midline Wound Closure Methods After Surgical Treatment for Pilonidal Sinus." Cochrane Database Syst Rev. 2024;1:CD015213. doi:10.1002/14651858.CD015213.pub2
11. Gil LA, Deans KJ, Minneci PC. "Management of Pilonidal Disease: A Review." JAMA Surg. 2023;158(8):875–883. doi:10.1001/jamasurg.2023.0373
12. Bi S, Sun K, Chen S, Gu J. "Surgical Procedures in the Pilonidal Sinus Disease: A Systematic Review and Network Meta-Analysis." Sci Rep. 2020;10(1):13720. doi:10.1038/s41598-020-70641-7
13. Stauffer VK, Luedi MM, Kauf P, et al. "Common Surgical Procedures in Pilonidal Sinus Disease: A Meta-Analysis, Merged Data Analysis, and Comprehensive Study on Recurrence." Sci Rep. 2018;8(1):3058. doi:10.1038/s41598-018-20143-4
14. Doll D, Orlik A, Maier K, et al. "Impact of Geography and Surgical Approach on Recurrence in Global Pilonidal Sinus Disease." Sci Rep. 2019;9(1):15111. doi:10.1038/s41598-019-51159-z
15. Arnous M, Elgendy H, Thabet W, et al. "Excision With Primary Midline Closure Compared With Limberg Flap in the Treatment of Sacrococcygeal Pilonidal Disease: A Randomised Clinical Trial." Ann R Coll Surg Engl. 2019;101(1):21–29. doi:10.1308/rcsann.2018.0144
16. Kramer SA, Jackson IT. "Bilateral Rhomboid Flaps for Reconstruction of the External Genitalia in Epispadias-Exstrophy." Plast Reconstr Surg. 1986;77(4):621–631. doi:10.1097/00006534-198604000-00019
17. Dagi AF, Jones NE, Bogue JT. "The Role of Plastic Surgery in Urologic Cancer and Trauma Reconstruction: A Systematic Review." Ann Plast Surg. 2025. doi:10.1097/SAP.0000000000004500
18. Alammar A, Laing K, Somasundaram J, Wallace DL, Rogers AD. "Flap Reconstruction Following Fournier's Gangrene: A Systematic Review of Techniques and Outcomes." Burns. 2026;52(3):107888. doi:10.1016/j.burns.2026.107888
19. Höckel M, Trott S, Dornhöfer N, et al. "Vulvar Field Resection Based on Ontogenetic Cancer Field Theory for Surgical Treatment of Vulvar Carcinoma: A Single-Centre, Single-Group, Prospective Trial." Lancet Oncol. 2018;19(4):537–548. doi:10.1016/S1470-2045(18)30109-8
20. Tock S, Wallet J, Belhadia M, et al. "Outcomes of the Use of Different Vulvar Flaps for Reconstruction During Surgery for Vulvar Cancer." Eur J Surg Oncol. 2019;45(9):1625–1631. doi:10.1016/j.ejso.2019.04.012
21. Kwong FL, Pounds R, Farah Y, Yap JKW. "Vulval Flap Reconstruction in Women With Benign, Preneoplastic and Malignant Vulval Conditions: A Prospective Study." BJOG. 2025;132(8):1156–1165. doi:10.1111/1471-0528.18156
22. Ricotta G, Russo SA, Ferron G, Meresse T, Martinez A. "The Toulouse Algorithm: Vulvar Cancer Location-Based Reconstruction." Int J Gynecol Cancer. 2025;35(4):100065. doi:10.1016/j.ijgc.2024.100065
23. Jędrasiak A, Juniewicz H, Raczek W, et al. "Reconstruction of the Vulva and Perineum — Comparison of Surgical Methods." J Clin Med. 2025;14(13):4456. doi:10.3390/jcm14134456
24. Furnas DW, Fischer GW. "The Z-Plasty: Biomechanics and Mathematics." Br J Plast Surg. 1971;24(2):144–160. doi:10.1016/s0007-1226(71)80034-6
25. Campbell J, Gillis J. "A review of penile elongation surgery." Transl Androl Urol. 2017;6(1):69–78. doi:10.21037/tau.2016.11.19
26. Ojo D, Gallo G, Kleijnen J, et al. "European Society of Coloproctology guidelines for the management of pilonidal disease." Br J Surg. 2024;111(10):znae237. doi:10.1093/bjs/znae237
27. Oonk MHM, Planchamp F, Baldwin P, et al. "European Society of Gynaecological Oncology Guidelines for the Management of Patients with Vulvar Cancer - Update 2023." Int J Gynecol Cancer. 2023;33(7):1023–1043. doi:10.1136/ijgc-2023-004486
28. Dadaci M, Yildirim MEC, Yarar S, Ince B. "Assessment of Outcomes After Limberg Flap Reconstruction for Scrotal Defects in Patients With Fournier's Gangrene." Wounds. 2021;33(3):65–69. PMID:33793411 PMID 33793411
29. Lamprou MP, Chrysikos D, Samolis A, et al. "Limberg’s Rhombic Flap: A Review of Embryological, Anatomical, and Clinical Considerations." Cureus. 2025;17(6):e85546. doi:10.7759/cureus.85546