Superficial Circumflex Iliac Artery Perforator (SCIP) Flap
The superficial circumflex iliac artery perforator (SCIP) flap provides thin, pliable tissue, often with primary donor-site closure and a potentially concealed groin scar; it can be pedicled or free. Some pedicled phalloplasty reports describe deeper SCIA-based groin flaps, whose thickness and dissection differ from a true suprafascial SCIP flap.[13][25] Reported urologic and urogynecologic uses include urethral and penile-shaft reconstruction in phalloplasty, male genital reconstruction after Fournier's gangrene, vulvoperineal reconstruction after vulvar cancer surgery, and vascularized lymph-node transfer for lymphedema; vesicocutaneous fistula repair is described in a single case.[1][2][3][4][5]
Vascular Anatomy
The SCIP is based on the superficial circumflex iliac artery (SCIA), which arises from the femoral artery (or occasionally the profunda femoris). The SCIA divides into two principal branches:[6][7]
| Branch | Course / role |
|---|---|
| Superficial branch | Runs in the subcutaneous fat ~2 cm caudal to the inguinal ligament; supplies the skin paddle. Axial pattern extending cephalically beyond the ASIS in 91.9% of cases[8] |
| Deep branch | Courses deep to the sartorius fascia toward the ASIS, giving branches to the sartorius muscle and iliac bone (osteocutaneous variants). Bifurcation point within 2 cm of a fixed landmark in 85% of specimens: 6 cm from the pubic tubercle along the line to the ASIS, and 3 cm caudal to that point[7] |
| Inferolateral branches | Perforators in an "F configuration" extending directly into the dermal plexus — enable superthin harvest without microdissection defatting[9] |
| Transverse branch (SCIAt) | Recently described variant enabling longer pedicles (mean 11.9 cm, range 8–17 cm) and double skin paddles, with flap areas up to 355 cm²[10] |
Anatomic parameters from cadaveric and clinical studies:[6]
- Major perforator of superficial branch: caliber approximately 2.0 mm
- Major perforator of deep branch: caliber approximately 2.1 mm
- Mean perforasome area: superficial 178.6 cm², deep 156.2 cm²
- Descending branches of the deep branch anastomose with the ascending branch of the lateral circumflex femoral artery in approximately 21% of cases
Preoperative mapping with high-frequency color-coded duplex sonography (CCDS) matched intraoperative anatomy in every patient of a 12-patient series, and ultrasound mapping of the SCIA course was successful in all cases of a prospective series.[8][11] For free transfer, assess venous outflow as well as arterial perforators: the superficial circumflex iliac vein can provide an independent drainage route and a usable anastomotic vein.[28]
Flap Configurations
| Variant | Composition | Notes |
|---|---|---|
| Fasciocutaneous SCIP | Thin skin + subcutaneous tissue (superficial branch) | Thinnest available skin flap[13] |
| Superthin SCIP | Inferolateral-branch perforators | Ultra-thin flaps without defatting[9] |
| Chimeric SCIP | External oblique fascia (deep branch) + fasciocutaneous (superficial) | Multi-layered reconstruction (e.g., vesicocutaneous fistula)[1] |
| Osteocutaneous SCIP | Vascularized iliac bone (deep branch) | Composite defects; one donor-site iliac-wing fracture occurred in a nine-patient extremity series, so bone-harvest morbidity should be considered separately from skin-only SCIP.[12][24] |
| SCIP + sartorius muscle | Skin + muscle on one pedicle | Dead-space obliteration[7] |
| SCIP + lymph nodes (LYST) | Superficial inguinal lymph nodes + afferent lymphatics | Lymphedema treatment[5][14] |
| Double-skin-paddle SCIP-t | Transverse-branch-based; two independent islands on one pedicle | Maximal versatility[10] |
Across three free-SCIP series, mean flap areas were 86 cm² (range 17.5–216 cm²) in Goh’s 210-flap series,[13] 90.5 cm² (25–212 cm²) in Pereira’s 101-flap extremity series,[15] and 129 cm² (35–355 cm²) in Yamamoto’s 57-flap transverse-branch SCIP-t series.[10] Mean width × length was 6.3 × 13.5 cm in Goh’s series and 7.0 × 18.8 cm in Yamamoto’s SCIP-t series.[13][10]
Application 1 — Urethral Reconstruction in ALT Phalloplasty
The SCIP flap is a pedicled option for urethral reconstruction in selected ALT phalloplasty patients, alongside the radial forearm free flap (RFFF). The later De Gelder series describes a change in that center's practice away from routinely combining an ALT shaft with a SCIP urethra after December 2019 because of urethral-flap loss; it now generally suggests an RFFF urethra with an ALT shaft unless a patient specifically requests SCIP and has suitable anatomy.[3]
- D'Arpa 2019. 93 ALT phalloplasties using several urethral designs; SCIP urethra in 38/93 (40.9%), with fistula or stricture reported in 26.3% of that subgroup, versus 37.9% with RFFF urethra and 87.5% with prelaminated ALT in differently selected subgroups.[16]
- De Gelder 2025. Dedicated retrospective 10-year SCIP series, 55 patients (47 unilateral SCIP and 8 bilateral procedures):[3]
- For urethral use, the authors now emphasize a donor-site pinch <1 cm to limit bulk, a paddle at least 4 cm wide, and tension-free ALT wrapping to reduce compression. Three urethral SCIP flaps required conversion to free transfer because the pedicle did not reach; all three were among the six complete unilateral urethral-flap losses.[3]
- 10 unilateral shaft flaps had no complete loss, but one partial tip loss; among 37 unilateral ALT-shaft and SCIP-urethra reconstructions, 6 complete urethral-flap losses (16%) and 4 partial losses (11%) were reported. Two bilateral urethral flaps were counted as complete losses; one was surgically removed at the patient's preference, and both patients received salvage perineal urethrostomy without a replacement flap.[3] The paper reports 8/55 (14%) across all patients, including ten shaft-only cases; among 45 patients who received a SCIP urethra, 8/45 (17.8%) were counted as complete losses (6/37 unilateral and 2/8 bilateral).[3]
- After further interventions, 32/37 in the unilateral urethral group and 5/8 (62.5%) in the bilateral group voided while standing; the abstract gives 82% overall.
- 8 bilateral SCIP for single-stage shaft and urethra: 38% urethral fistula or stricture rate
- All donor sites were closed primarily; 36/55 patients required additional plastic-surgery interventions and 25/55 additional urologic interventions.[3]
- Limitation: potentially lower shaft sensation than RFFF
- Wu 2022. 49 pedicled ALT penile reconstructions for micropenis (17), iatrogenic defects (3), or trauma (29); SCIAP urethra in 26 cases, with urethral complications in 46.2% of that subgroup. After revision procedures, all patients could urinate while standing.[17]
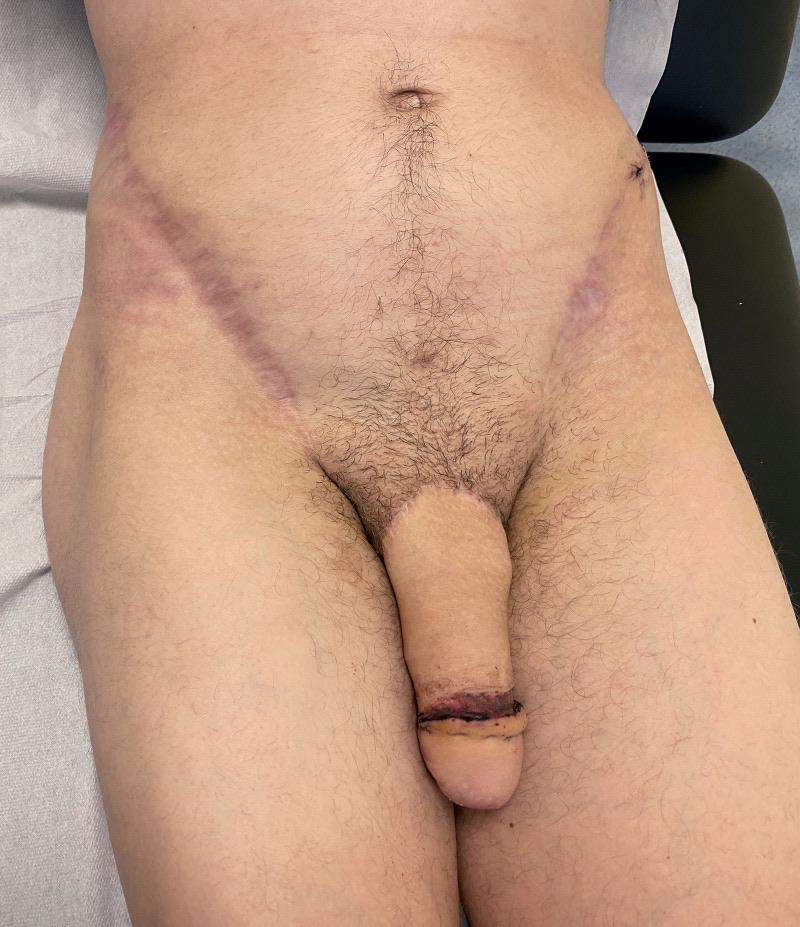
Result 6 months after bilateral SCIP flap reconstruction, showing the neophallus and both groin donor scars. A coronaplasty performed 2 weeks before the photograph is in the healing phase; the left-sided scar was used as a full-thickness skin graft for it. From De Gelder A, et al. Plast Reconstr Surg. 2025;155(6):1036e-1044e, Fig. 2 (CC BY).[3]
Application 2 — Penile Shaft Reconstruction
Thin, pliable tissue can be used for shaft coverage. In the De Gelder series, 10 unilateral shaft reconstructions had no complete flap loss, although one had partial tip loss.[3] In a separate retrospective shaft-only SCIA-based series of 47 transgender men, 45/47 (96%) achieved successful penile reconstruction with the SCIA-based flap alone at three months; one had total flap necrosis, while partial necrosis was reported as one case in the abstract and results text but three in Table 3 (one later needed a second flap), 20/47 had wound dehiscence (including three donor-only cases), and 5/47 had donor-site seromas requiring drainage.[23] The concealed groin donor scar may be preferable to a visible forearm scar for some patients; donor-site choice and expected sensation require individual discussion.
Application 3 — Male Genital Reconstruction (Fournier's, Oncologic, Congenital)
The pedicled SCIP has been reported for perineo-scrotal reconstruction in small series:[2][18]
- Scaglioni 2022. Six patients with genital defects (Fournier's, scrotal SCC, severe acne, testicular agenesis); defects 7 × 4 to 20 × 6 cm. All flaps survived with good cosmetic results, no urinary or sexual dysfunction, and one minor wound dehiscence at a mean 9.5-month follow-up (range 6–12 months).[2]
- B S 2023. 3 patients with perineo-scrotal defects after Fournier's (largest 22 × 10 cm); all flaps survived with good functional or aesthetic outcomes. The authors suggested the flap could be considered the gold standard for such defects on the basis of these three cases.
These small series describe a thin, pliable, vascularized flap for scrotal coverage and the potential for primary groin closure.[2][18]
Application 4 — Vesicocutaneous Fistula Repair
A novel application of the pedicled chimeric SCIP:[1]
- Chimeric design: external oblique fascia (deep branch) reinforces the bladder fistula suture line; fasciocutaneous component (superficial branch) inset over the fascial layer ("double-breasting")
- 26-year-old female with vesicocutaneous fistula complicating a suprapubic catheter: coverage with no recurrence at 24-month follow-up
A useful proof of concept for the chimeric SCIP in lower-abdominal or suprapubic urologic defects. See Vesicocutaneous Fistula for the clinical condition.
Application 5 — Vulvoperineal Reconstruction After Vulvar Cancer
The SCIP is one reported perforator-flap option for selected vulvar reconstructions:[4][19]
- Gentileschi 2022. 32 patients, 34 SCIP flaps after vulvar cancer surgery. The flap was always feasible (100%); mean flap size 128.8 cm². Three patients (9.4%) had wound complications. In every patient the defect involved vulva, perineum, and inguinal area; in 56% the mons pubis was also involved. Mean follow-up 30 months.[4]
The Toulouse algorithm describes location-based selection of perforator and musculocutaneous flaps for vulvar cancer reconstruction without establishing SCIP as a first-line option across defects.[19] The SCIP's arc can cover selected vulva-perineum-inguinal defects.
Application 6 — Vascularized Lymph Node Transfer (VLNT) for Lymphedema
The SCIP serves as the vascular carrier for inguinal lymph-node harvest in VLNT and Lymphatic System Transfer (LYST).[5][14][20] After excision of advanced male genital lymphedema, a 26-patient retrospective series used pedicled SCIP-lymphatic flaps for scrotal or penoscrotal reconstruction; the series reported 100% flap survival and lower postoperative cellulitis rates over mean 44.9-month follow-up.[29] Other reported applications include:
- Xu 2026 LYST with pedicled SCIP. 6 patients with lower-extremity lymphedema and concomitant chronic venous disease; 5 also had distal lymphovenous bypass. The pedicled SCIP LYST does not require microsurgical anastomosis of the flap. Mean outcomes at an average follow-up of 31 weeks: 15-point reduction in LLIS score and 30-unit decrease in L-dex bioimpedance.[5]
- Meroni & Scaglioni 2024 perforator-to-perforator SCIP-VLNT. 12 patients; all transplanted lymph nodes showed function on 6-month lymphoscintigraphy; no donor or recipient site complications.[20]
- Yoshimatsu 2025 SCIP-LYST long-term outcomes. 8 patients, mean 39-month follow-up: mean excess volume improvement 11.2% and significant reduction in cellulitis episodes (p = 0.025).[14]
Before groin lymph-node transfer, use reverse lymphatic mapping to avoid harvesting nodes that drain the donor leg: Broyles et al. found lower-extremity drainage to at least one superficial inguinal region in 38.1% of 84 mapped patients. Among 56 patients who proceeded to transplantation with mapped, limited harvest and intraoperative gamma-probe guidance, none developed donor-limb lymphedema over a mean of 34.5 months.[21]
Donor-Site Morbidity
Reported donor-site morbidity of the SCIP is low:
| Parameter | Finding |
|---|---|
| Primary closure rate | All donor sites closed primarily in the cited De Gelder phalloplasty cohort; larger designs and other populations must be assessed individually.[3] |
| Donor-site complications (de Haseth shaft-only phalloplasty) | Seroma requiring drainage occurred in 5/47; donor dehiscence affected 7/47 when four combined donor/recipient wounds are included.[23] |
| Donor-site complications (Gentileschi vulvar series) | The cited cohort included 32 patients and 34 flaps; its overall wound-complication count (three patients) should not be relabeled as a donor-site rate.[4] |
| Donor-site complications (Goh 210-flap series) | 2 patients (1.0%)[13] |
| Donor-site complications (Scaglioni 73 head-and-neck flaps) | 0 patients (0%)[22] |
| Debulking surgery | 2.4% (Goh) and 6.9% (Pereira)[13][15] |
| Scar concealment | Groin crease — easily hidden |
| Lymphedema risk with node harvest | Donor-leg lymphoedema has been reported after lymph node–SCIP transfer.[26] A separate mapped groin-VLNT series observed none in 56 patients over a mean 34.5 months with limited harvest and gamma-probe guidance.[21] |
| Abdominal-wall integrity | A skin-only, suprafascial SCIP spares abdominal-wall muscle and fascia; chimeric external-oblique-fascia harvest does not, and a sartorius variant also harvests thigh muscle.[1][7] |
| Total flap loss | 0–5.9% in non-urethral series (Scaglioni 0/73, Goh 4.8%, Pereira 5.9%); 8/55 (14%) complete urethral-flap losses among all De Gelder phalloplasty patients, comprising 6/37 unilateral urethral and 2/8 bilateral reconstructions[3][13][15][22] |
A skin-only SCIP avoids the rectus harvest of VRAM, the forearm donor wound of RFFF, the vastus lateralis harvest of ALT-VL, and the labial donor incision of Martius; chimeric SCIP designs and lymph-node harvest have separate donor-site risks.[1][7][21]
Comparison with Other Flaps
| Feature | SCIP | RFFF | ALT-VL | Gracilis |
|---|---|---|---|---|
| Tissue quality | Thinnest available; pliable | Thin; pliable | Moderate thickness | Moderate bulk |
| Donor scar | Concealed (groin crease) | Conspicuous (forearm) | Lateral thigh | Medial thigh |
| Primary closure | Achieved in all 55 De Gelder phalloplasty patients; assess planned width and local laxity with a pinch test for other designs.[3][13] | Donor-site closure may use STSG or FTSG[27] | Usually primary | Usually primary |
| Microsurgery required | No (pedicled) or Yes (free)[1][13] | Yes (always free)[27] | No (pedicled) or Yes (free)[16][31] | No (pedicled)[30] |
| Urethral fistula/stricture (phalloplasty) | 38% (14/37) requiring intervention in De Gelder's unilateral ALT-shaft/SCIP-urethra group; other series have different selection and definitions[3] | 37.9% fistula or stricture in D'Arpa's ALT-shaft/RFFF-urethra group[16] | 20% fistula or stricture in D'Arpa's selected tube-in-tube ALT group[16] | N/A |
| Standing voiding rate | 82% (37/45) after further interventions among De Gelder's SCIP-urethra patients[3] | Not reported separately in D'Arpa | 91.9% eventually across urethral techniques in D'Arpa's ALT series[16] | N/A |
| Shaft sensation | Proximal sensation reported in 4/7 assessed shaft cases at 3–25 months; comparative outcome uncertain[3] | Sensate reconstruction possible; no direct comparison in the cited SCIP cohort | Variable | N/A |
| Hernia risk | Not quantified in the cited SCIP series; chimeric designs may harvest external oblique fascia.[1] | Not quantified here | Not quantified here | Not quantified here |
| Chimeric options | Fascia, bone, lymph nodes, muscle | Limited | Fascia lata, VL muscle | Limited |
Key Takeaways
The SCIP is a thin-flap option derived from the groin vascular territory, offering a potentially concealed scar and avoiding sacrifice of abdominal muscle. Donor morbidity and flap thickness vary by design and patient anatomy. In urology and urogynecology, reported uses include:
- Selected urethral and shaft reconstruction in phalloplasty (D'Arpa reported 26.3% urethral complications for the SCIP subgroup; De Gelder reported 82% standing voiding across SCIP urethral recipients after interventions, but subsequently moved away from routine ALT-shaft and SCIP-urethra combination)[16][3]
- Perineo-scrotal reconstruction after Fournier's, scrotal SCC, or congenital indications
- Selected vulvar reconstruction after oncologic resection, with flap selection based on location
- Vesicocutaneous fistula repair via chimeric design with external-oblique fascia
- Vascularized lymph-node transfer for lymphedema (LYST or VLNT)
The chimeric capability, incorporating external oblique fascia, iliac bone, sartorius muscle, or lymph nodes on the same pedicle, expands its reconstructive versatility. Limitations include the relatively short pedicle of the standard design (though transverse-branch variants reach 8–17 cm), small vessel caliber requiring microsurgical expertise for free transfer, and potentially lower shaft sensation versus RFFF in phalloplasty. Preoperative ultrasound mapping is widely used in flap planning.
See Also
- Radial Forearm Free Flap. Alternative for phalloplasty
- Anterolateral Thigh Flap. Pairs with SCIP for ALT phalloplasty (SCIP urethra inside ALT shaft)
- Vastus Lateralis Flap
- Gracilis Flap
- Vesicocutaneous Fistula
- Masculinizing Procedures (GAS)
- Flaps in GU Reconstruction
References
1. Lichtenberg NJ, B S, Taylor DM. "Pedicled Chimeric Superficial Circumflex Iliac Artery Perforator (SCIP) Flap With External Oblique Fascia for Vesicocutaneous Bladder Fistula Repair: A Case Report and Literature Review on the Utility of Pedicled Chimeric SCIP." Microsurgery. 2024;44(2):e31138. doi:10.1002/micr.31138
2. Scaglioni MF, Meroni M, Fritsche E. "Pedicled Superficial Circumflex Iliac Artery Perforator Flap for Male Genital Reconstruction: A Case Series." Microsurgery. 2022;42(8):775–782. doi:10.1002/micr.30933
3. De Gelder A, Young-Afat D, Claes K, et al. "Use of the Superficial Circumflex Iliac Artery Perforator Flap for Urethra and / or Shaft Reconstruction in Gender-Diverse Persons: 10-Year Single-Center Experience." Plast Reconstr Surg. 2025;155(6):1036e–1044e. doi:10.1097/PRS.0000000000011830
4. Gentileschi S, Caretto AA, Servillo M, et al. "Feasibility, Indications and Complications of SCIP Flap for Reconstruction After Extirpative Surgery for Vulvar Cancer." J Plast Reconstr Aesthet Surg. 2022;75(3):1150–1157. doi:10.1016/j.bjps.2021.11.005
5. Xu KY, Finkelstein ER, Wu S, Tadisina K, Mella-Catinchi J. "Lymphatic System Transfer (LYST) With Pedicled SCIP for Patients With Lymphedema and Concomitant Chronic Venous Disease." Plast Reconstr Surg. 2026. doi:10.1097/PRS.0000000000012927
6. Gandolfi S, Postel F, Auquit-Auckbur I, et al. "Vascularization of the Superficial Circumflex Iliac Perforator Flap (SCIP Flap): An Anatomical Study." Surg Radiol Anat. 2020;42(4):473–481. doi:10.1007/s00276-019-02402-9
7. Yoshimatsu H, Steinbacher J, Meng S, et al. "Superficial Circumflex Iliac Artery Perforator Flap: An Anatomical Study of the Correlation of the Superficial and the Deep Branches of the Artery and Evaluation of Perfusion From the Deep Branch to the Sartorius Muscle and the Iliac Bone." Plast Reconstr Surg. 2019;143(2):589–602. doi:10.1097/PRS.0000000000005282
8. Jeong HH, Zaman SR, Oh SM, et al. "Visualization of Superficial Circumflex Iliac Artery Perforator Flap Pedicle With Ultrasound: Revealing the Concept of Pedicle Axiality." Plast Reconstr Surg. 2026. doi:10.1097/PRS.0000000000012902
9. Zhang Y, Zeng A. "An Easy Way to Harvest a Superthin SCIP Flap With Long Pedicle: Reappraisal of the Inferolateral Branches of the SCIA." Plast Reconstr Surg. 2023;152(5):1100–1104. doi:10.1097/PRS.0000000000010338
10. Yamamoto T, Fuse Y, Miyazaki T, et al. "Transverse Branch-Based Superficial Circumflex Iliac Artery Perforator (SCIP) Flap: Expanding Indication of SCIP Flap With a Longer Pedicle and / or Multiple Skin Paddles." Plast Reconstr Surg. 2025. doi:10.1097/PRS.0000000000012640
11. Schiltz D, Lenhard J, Klein S, et al. "Do-It-Yourself Preoperative High-Resolution Ultrasound-Guided Flap Design of the Superficial Circumflex Iliac Artery Perforator Flap (SCIP)." J Clin Med. 2021;10(11):2427. doi:10.3390/jcm10112427
12. Zubler C, Lese I, Pastor T, et al. "The Osteocutaneous SCIP Flap: A Detailed Description of the Surgical Technique and Retrospective Cohort Study of Consecutive Cases in a Tertiary European Centre." J Plast Reconstr Aesthet Surg. 2023;77:21–30. doi:10.1016/j.bjps.2022.10.056
13. Goh TLH, Park SW, Cho JY, Choi JW, Hong JP. "The Search for the Ideal Thin Skin Flap: Superficial Circumflex Iliac Artery Perforator Flap — A Review of 210 Cases." Plast Reconstr Surg. 2015;135(2):592–601. doi:10.1097/PRS.0000000000000951
14. Yoshimatsu H, Cho MJ, Karakawa R, et al. "The Role of Lymphatic System Transfer (LYST) for Treatment of Lymphedema: A Long-Term Outcome Study of SCIP Flap Incorporating the Lymph Nodes and the Afferent Lymphatic Vessels." J Plast Reconstr Aesthet Surg. 2025;101:15–22. doi:10.1016/j.bjps.2024.11.052
15. Pereira N, Venegas J, Oñate V, Camacho JP, Roa R. "Extremity Reconstruction With Superficial Circumflex Iliac Artery Perforator Free Flap: Refinements and Innovations After 101 Cases." J Plast Reconstr Aesthet Surg. 2023;85:1–9. doi:10.1016/j.bjps.2023.06.048
16. D'Arpa S, Claes K, Lumen N, et al. "Urethral Reconstruction in Anterolateral Thigh Flap Phalloplasty: A 93-Case Experience." Plast Reconstr Surg. 2019;143(2):382e–392e. doi:10.1097/PRS.0000000000005278
17. Wu Q, Yang Z, Ma N, Wang W, Li Y. "Urethra Reconstruction and Revision Urethroplasty in Pedicled Anterolateral Thigh Flap Penile Reconstruction." Ann Plast Surg. 2022;89(2):201–206. doi:10.1097/SAP.0000000000003100
18. B S, Khanna A, Taylor D. "Pedicled Superficial Circumflex Iliac Artery Perforator (SCIP) Flap for Perineo-Scrotal Reconstruction Following Fournier's Gangrene." ANZ J Surg. 2023;93(1–2):276–280. doi:10.1111/ans.18066
19. Ricotta G, Russo SA, Ferron G, Meresse T, Martinez A. "The Toulouse Algorithm: Vulvar Cancer Location-Based Reconstruction." Int J Gynecol Cancer. 2025;35(4):100065. doi:10.1016/j.ijgc.2024.100065
20. Meroni M, Scaglioni MF. "Perforator-to-Perforator SCIP-Based Vascularized Lymphnode Transfer to Reduce Morbidity and Increase Efficacy in Lymphedema Surgery: Preliminary Results With 12 Cases." Microsurgery. 2024;44(7):e31249. doi:10.1002/micr.31249
21. Broyles JM, Smith JM, Wong FC, et al. "Single-Photon Emission Computed Tomographic Reverse Lymphatic Mapping for Groin Vascularized Lymph Node Transplant Planning." Plast Reconstr Surg. 2022;150(4):869e–879e. doi:10.1097/PRS.0000000000009557
22. Scaglioni MF, Meroni M, Tomasetti PE, Rajan GP. "Head and Neck Reconstruction With the Superficial Circumflex Iliac Artery Perforator (SCIP) Free Flap: Lessons Learned After 73 Cases." Head Neck. 2024;46(6):1428–1438. doi:10.1002/hed.27760
23. de Haseth KB, Young-Afat DA, Mokken SE, et al. "Superficial Circumflex Iliac Artery (SCIA) Perforator Flap for Shaft-Only Phalloplasty: Surgical Technique and Outcomes." Int J Transgend Health. 2025;26(4):1377–1387. doi:10.1080/26895269.2024.2440854
24. Zubler C, Constantinescu MA, Lese I, Olariu R. "The Osteocutaneous Superficial Circumflex Iliac Artery (SCIP) Flap in Extremity Reconstruction." J Hand Microsurg. 2025;17(6):100337. doi:10.1016/j.jham.2025.100337
25. Peters BR. "The superficial circumflex iliac artery (SCIA) flap in Phalloplasty: Don't “SCIP” patient selection." BJU Int. 2026. doi:10.1111/bju.70358
26. Pons G, et al. "A Case of Donor-Site Lymphoedema After Lymph Node-Superficial Circumflex Iliac Artery Perforator Flap Transfer." J Plast Reconstr Aesthet Surg. 2014;67(1):119–123. doi:10.1016/j.bjps.2013.06.005
27. Moors JJE, Xu Z, Xie K, et al. "Full-Thickness Skin Graft Versus Split-Thickness Skin Graft for Fasciocutaneous Radial Forearm Free Flap Donor Site Closure: A Systematic Review and Meta-Analysis." Syst Rev. 2025;14(1):118. doi:10.1186/s13643-025-02863-7
28. Sun JM, Yamamoto T, Goh TLG. "Venous Anatomy of the Superficial Circumflex Iliac Artery Perforator Flap: A Cadaveric and Clinical Study." J Plast Reconstr Aesthet Surg. 2024;88:1–7. doi:10.1016/j.bjps.2023.10.096
29. Abdelfattah U, et al. "Treatment of Advanced Male Genital Lymphedema With a Complete Functional Lymphatic System Pedicled Transfer." Urology. 2023;175:190–195. doi:10.1016/j.urology.2023.02.006
30. Oner M, Tsay AT, Abbas MA. "The use of the gracilis flap in colorectal surgery: surgical technique, results, and review of the literature." Int J Colorectal Dis. 2025;40(1):133. doi:10.1007/s00384-025-04928-4
31. Mughal M, Baker RJ, Muneer A, Mosahebi A. "Reconstruction of perineal defects." Ann R Coll Surg Engl. 2013;95(8):539–544. doi:10.1308/003588413X13629960047155