Vertical Rectus Abdominis Myocutaneous (VRAM) Flap
The VRAM flap is an established abdominal-based pedicled option for pelvic and perineal reconstruction after extensive oncologic resection, including selected urologic exenteration and complex fistula repairs. It brings vascularized tissue and, when needed, a skin paddle into an irradiated field and can fill pelvic dead space. Its abdominal-wall donor morbidity and the size, route and tissue requirements of the defect must be weighed against other flaps.[1][2][3]
See the overview article for comparative context: Flaps in GU Reconstruction, and the anatomy references: Abdominal Wall and Pelvic Vascular Anatomy.
External technique atlas: microsurgeon.org — Rectus Muscle Flap.
Gross Anatomy
The paired rectus abdominis muscles provide abdominal flexion and support the intra-abdominal contents.
| Feature | Value |
|---|---|
| Origin | Pubic symphysis + pubic crest |
| Insertion | 5th–7th costal cartilages |
| Length | Up to 30 cm |
| Width | Up to 10 cm |
| Enclosed by | Rectus sheath (anterior + posterior) |
The Arcuate Line
A landmark for VRAM harvest: below the arcuate line, the posterior rectus sheath is absent (all aponeurotic layers pass anterior to the muscle). Above the arcuate line, the muscle is enclosed anteriorly and posteriorly. Two implications:
- Below the arcuate line, no posterior fascial defect is created at harvest; donor-site integrity here depends entirely on the intact anterior sheath.
- Above the arcuate line, careful anterior-sheath closure (with or without mesh) is needed to prevent incisional hernia.
Tendinous Inscriptions
Three to four transverse fibrous inscriptions tether the muscle to the overlying anterior sheath. At these points, the fascia is tightly adherent and must be sharply dissected during harvest to avoid damaging muscle fibers.
Vascular Anatomy
The rectus abdominis has a dual blood supply (inferior and superior epigastric systems) that communicate through choke vessels within the muscle. For pelvic and perineal reconstruction, the flap is inferiorly based on the deep inferior epigastric artery.
Dominant Pedicle — Deep Inferior Epigastric Artery (DIEA)
- Origin: external iliac artery, just above the inguinal ligament.
- Course: enters the deep surface of the rectus abdominis near its lower third, ascends along the deep muscle surface, anastomoses with the superior epigastric system.
- Artery caliber: 2–4 mm at origin.
- Pedicle length: 5–7 cm easily obtainable; additional length via intramuscular dissection.
- Venae comitantes: paired, merging at the external iliac; one typically larger and comparable to arterial caliber.
In Kim's retrospective series, postoperative imaging in 60 evaluable patients suggested preserved DIEA flow in 98.3%.[3]
Protecting the pedicle before harvest. Prolonged fixed abdominal-wall retraction during the extirpative operation that precedes flap harvest (for example, open pelvic exenteration) can traumatize the inferior epigastric pedicle needed for subsequent VRAM reconstruction. When the exenteration and VRAM are planned together, this is a pre-harvest planning hazard in addition to the intraoperative handling precautions described below; no incidence or retractor-duration threshold has been established.[29]
Superior Epigastric System
- Arises from the internal mammary artery as it crosses the costal margin.
- Supplies the superior rectus.
- Sacrificed during inferior-based VRAM harvest to mobilize the flap toward the pelvis.
Skin Paddle Perforators
The skin paddle is supplied by musculocutaneous perforators through the anterior rectus sheath, principally in the paraumbilical region (rich perforator zone). This is why the skin paddle typically extends in a vertical orientation along the rectus axis.
Flap Design
Inferiorly Based VRAM (Standard for Urologic Reconstruction)
- Skin paddle: vertical, 8–12 cm wide, extending from the costal margin down toward the pubis. Length adjusted to defect size.
- Muscle component: full rectus or a muscle-sparing variant (see below).
- Reach: perineum, pelvis, groin, proximal thigh via subcutaneous tunnel or through a prepared pelvic or retropubic corridor.
Superiorly Based
Rarely used in urology; primarily for chest-wall reconstruction.
Free VRAM
Rare urologic indication. Reserved for specific distant reconstruction needs.
Transverse Rectus Abdominis Myocutaneous (TRAM) Variant
The TRAM flap is the same parent flap with the skin paddle oriented transversely across the lower abdomen (rather than vertically). It shares the rectus muscle, DIEA and DSEA dual-pedicle anatomy with VRAM but has its own distinct historical lineage (Hartrampf 1982), zone classification (Hallock LDF; Holm clinical revision), muscle-sparing TRAM classification (MS-0, MS-1 and MS-2, with DIEP as MS-3), vascular-enhancement procedures (delay, supercharging and turbocharging), and comparative DIEP-versus-TRAM literature. See the dedicated TRAM flap foundations page for the full treatment.
Harvest Technique
Open Standard Harvest
- Incision. Vertical paramedian over the rectus muscle axis (or low transverse depending on surgeon preference). Length determined by the muscle segment required.
- Subcutaneous dissection. Expose the anterior rectus sheath, identify and preserve perforators supplying the planned skin paddle, and divide only vessels outside the flap design as needed. Use careful hemostasis near the paddle because cautery can injure its perforators.[34]
- Open the anterior rectus sheath while protecting skin-paddle perforators. For a skin-bearing VRAM, incise the sheath medial and lateral to the skin island, retaining perforator-bearing fascia with the flap; elevate the remaining sheath edges with Allis clamps.[34]
- Tendinous inscriptions. Tightly adherent to sheath; tease off muscle sharply with electrocautery.
- Identify the DIEA laterally at the inferior-lateral muscle border, in the areolar fat plane. Trace the pedicle down to its origin at the external iliac.
- Manage the pubic attachment according to the transfer route and needed reach. Published transpelvic techniques either preserve the inferior insertion or release part of it while retaining tissue that protects the deep inferior epigastric pedicle.[35][36]
- Divide the muscle superiorly (costal margin level). Ligate or cauterize superior epigastric vessels securely; they will retract and bleed if missed.
- Isolate the flap on the DIEA pedicle. Tunnel subcutaneously or directly via the pelvis to the recipient site.
- Reconstruct the donor abdominal wall with attention to fascial loss, closure tension, contamination, prior incisions and stoma position. Primary closure, reinforcement or a more complex repair may be appropriate.[3][26]
- Drain the donor site (suction), especially when a skin paddle creates dead space above the fascia.
Oblique Rectus Abdominis Myocutaneous (ORAM) Variant
The ORAM flap orients the skin paddle obliquely rather than vertically, offering a greater arc of rotation, thinner skin paddle, less bulk, and limited fascial harvest, with comparable complication rates to standard VRAM.[19] In a 24-patient two-center retrospective comparison after APR, ORAM and ALT-VL flaps had similar perineal complication rates (40% versus 28.6%); donor-site bulging occurred in 3 of 10 ORAM patients, whereas one ALT-VL patient had a seroma.[28]
Muscle-Sparing VRAM (MS-VRAM) Variants
Developed to reduce donor-site morbidity:[8]
- Modified long vertical flap. Extensive coverage with preserved muscle width.
- Wrapping flap. Circumferential defects.
- De-epithelialized flap. Fills dead space without external skin coverage.
- Cork flap. A limited-tissue variant described in the MS-VRAM series.
Extended VRAM (eVRAM)
Large pelviperineal defects where standard VRAM is insufficient. In a 44-patient series: 91% successful reconstruction, 3 flap failures, 39% perineal wound complications (8 requiring reoperation), 11% donor-site problems.[9]
Robotic Harvest
Robotic muscle-only rectus harvest is an emerging option in selected pelvic cases. Described approaches use abdominal ports, develop the posterior rectus plane, identify and preserve the inferior epigastric pedicle and deliver the muscle into the pelvic defect. Port placement, sheath harvest and need for reinforcement differ by technique. Preserving the anterior sheath may reduce incision-related morbidity.[18][20][21]
- Davila 2022 compared 16 robotic rectus muscle flaps with 20 traditional repairs (12 VRAM and eight gracilis). Major complications were similar; minor complications occurred in 55% with traditional repairs versus 31% with robotic harvest (P=0.15).[20] Six robotic patients received biologic mesh reinforcement.[20]
- Asaad 2021 described rectus muscle harvest after robotic extirpative surgery, with an anterior-sheath-sparing approach in selected patients.[21]
Critical Flap-Inset Considerations
Protecting the pedicle from twisting, compression and tension during transfer and inset is important.[3][10] Trapero and colleagues attribute compromised viability in their experience principally to inset or postoperative-care problems.[10]
One published technical proposal adapts rotation to the defect and patient position:[10]
| Defect location | Rotation | Result |
|---|---|---|
| Anterior perineum | 270° in the sagittal plane, as proposed by Trapero et al. | Positions the cranial flap toward the anterior defect in their method |
| Posterior perineum | 180° in the coronal plane, as proposed by Trapero et al. | Positions the cranial flap posteriorly in their method |
In either case, meticulous attention to pedicle orientation to avoid kinking, compression, or tension on the DIEA pedicle is needed.
GU Reconstructive Applications
Pelvic Exenteration and Radical Cystectomy
The principal urologic indication. Total or anterior pelvic exenteration creates a non-collapsible pelvic cavity particularly problematic in the irradiated field. VRAM addresses two issues:[3]
- Fills pelvic dead space, with the aim of reducing fluid collection and bowel descent.
- Introduces non-irradiated, well-vascularized tissue into the radiated field.
Empty-pelvis syndrome and enteric fistula. An empty, non-collapsed pelvic cavity after exenteration predisposes to empty-pelvis syndrome, whose complications can include enteric fistula presenting through the perineal or abdominal wound, with risk of progression to chronic abscess, additional fistulae, sepsis, or intestinal failure. A well-vascularized, bulky flap used to reconstitute the pelvic floor and perineal, vaginal, or perianal defect has been reported to offset this complication to some extent, but no study shows that a flap prevents fistula or infection outright.[30][31][32]
The published VRAM literature is heavily weighted toward colorectal or pelvic oncologic surgery.[1][3] In Kim's 60-patient imaging cohort, 75% of operations were for rectal cancer.[1][3]
Complex Urogenital Fistula Repair
Selected recurrent urogenital fistulas after failed repairs may require vascularized interposition. Paprottka's retrospective 12-patient series used five VRAM and eight gracilis flaps across the cases. Final fistula repair was achieved in the series; among ten living patients surveyed, three VRAM patients reported slight incontinence and seven gracilis patients reported restored continence.[4]
For complex or refractory urethrovaginal fistulas specifically (after failed Martius or other simpler interpositions), Bruce 2000 described rectus abdominis muscle flap interposition between the closed fistula and the vaginal suture line as a salvage technique; the rectus bulk provides vascularized tissue coverage where local options have already failed.[22]
Vaginoplasty After Anterior Exenteration
For radical cystectomy with partial or total vaginectomy for bladder or urethral carcinoma, the VRAM can be tubed or used as a skin paddle to reconstruct the vagina and perineum at the same setting. Parsons 2003 described this approach for urologic-malignancy anterior exenteration in four patients, achieving simultaneous defect coverage and neovaginal reconstruction.[23]
Bladder Neck Closure in Neurogenic Incontinence
The rectus abdominis muscle flap can be interposed between the bladder neck and urethral stump as an adjunct to bladder-neck closure to prevent vesicourethral fistula, as an alternative to omental interposition when omentum is unavailable or inadequate. In Smith's preliminary series of six patients with neurogenic bladder dysfunction, there were no intraoperative or postoperative complications associated with the flap procedure and no urinary fistulas related to its use; all six were continent at a mean follow-up of 45.5 months.[24]
Epispadias / Exstrophy Reconstruction
Rectus abdominis muscle and fascia have been used to provide abdominal-wall support, coverage of the bladder neck and proximal urethra, and mons reconstruction in epispadias and exstrophy. Horton 1988 described this application as part of the multistage exstrophy reconstruction.[25]
Urosymphyseal Fistula (USF)
A difficult indication where the extent of resection and availability of omentum affect flap selection. In Escandón's retrospective 56-patient series (34 omental, 11 VRAM, 11 primary repair):[5]
- Omental flap. 90-day sepsis 3%; adjusted early recurrence was lower than with primary repair, but not demonstrated to be lower than with VRAM[5]
- VRAM. 90-day sepsis 27%; recurrence 27.3% in the reported group[5]
- Primary repair. 90-day sepsis 18%; recurrence 30% in the reported group[5]
The groups were small and selected for different operations. See the omental flap discussion.
Genital Reconstruction
Inferiorly based VRAM has been used for phalloplasty under special circumstances. In Küntscher's 15-patient mixed series, seven inferiorly based flaps were used for defect coverage after tumor resection and for penile reconstruction; the report does not give a phalloplasty-specific denominator.[6]
Groin and Proximal Thigh Defects
After radical inguinal lymphadenectomy or tumor resection, VRAM can reach selected groin and proximal-thigh defects. In a retrospective cohort of 53 patients, 47.2% developed complications; a systematic review of 189 reconstructions pooled a complication rate of 31.2% and a failure rate of 2.1%. Hernia rates were similar with mesh (16.7%) and primary closure alone (15.1%).[7]
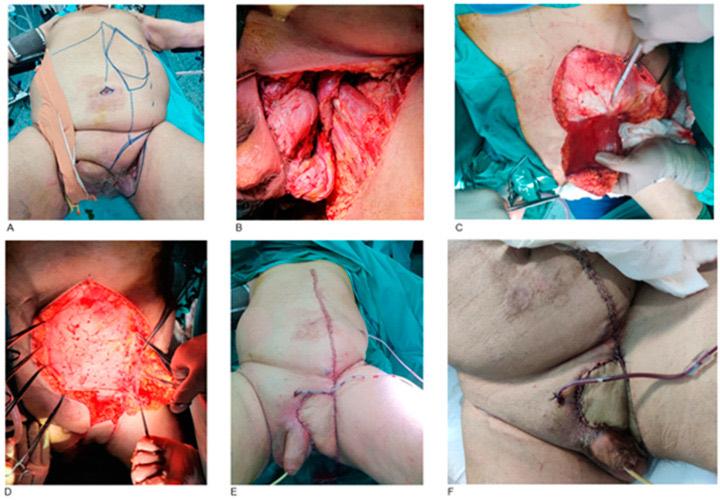
Left inguinal-fold reconstruction with a VRAM flap after resection of a cutaneous squamous cell carcinoma in a 67-year-old male patient. A, preoperative marking of the resection margins and of the left VRAM flap; B, defect after resection, exposing the left testis, epididymis and spermatic cord; C, harvest of the left VRAM myocutaneous flap; D, layered abdominal wall closure beginning with the posterior rectus sheath; E, postoperative result; F, surviving flap 10 days after surgery. From Bini A, Stavrianos S. J Clin Med. 2025;14(9):3172, Figure 4 (CC BY 4.0).[33]
Coverage of Major Vessels / Visceral Repairs
The rectus bulk is useful for covering major vessels or visceral repairs in the pelvic basin: obturator vessels after lymphadenectomy, visceral suture lines after complex resection, or pubectomy sites after osteomyelitis debridement.
Outcomes
Systematic Review — 1,827 Patients[1]
| Outcome | Rate |
|---|---|
| Mean perineal / recipient-site morbidity | 27% |
| Complete flap loss | 1.8% |
| Perineal hernia | 0.2% |
| Mean donor-site morbidity | 15% |
| Abdominal dehiscence | 5.5% |
| Incisional hernia (donor) | 3.3% |
These are means across heterogeneous reports; recipient and donor definitions and follow-up varied. A 2025 systematic review of 24 VRAM series reported incisional hernia in 226/2,200 (10.2%) and parastomal hernia in 219/1,143 (19.2%) at mean 31-month follow-up.[39] Ascertainment and operative techniques varied.[39] For APR defects amenable to either primary closure or flap reconstruction, a 2024 VRAM-specific meta-analysis found fewer overall perineal complications with VRAM (80/244 versus 263/688 after primary closure), whereas a broader 2026 myocutaneous-flap meta-analysis found no clear difference in overall perineal complications but fewer pelvic abscesses with flaps.[37][38][37][38]
10-Year Series (60 Evaluable of 77 Operated)[3]
- Donor-site hernia: 16.7%[3]
- Perineal hernia: 3.3%[3]
- DIEA flow suggested on available postoperative imaging: 98.3%[3]
Proctor Two-Centre Series (154 Patients, 2001 to 2017)[11]
- Clavien-Dindo ≥3 at donor site: 6%[11]
- Clavien-Dindo ≥3 at flap / perineal site: 18%[11]
- Smoking (P=0.003) and neoadjuvant radiotherapy (P=0.047) associated with flap complications in the reported analysis; applicability depends on cohort and adjustment
- Flap complications significantly prolonged hospital stay
Factors Associated With VRAM Use Rather Than Primary Closure[12]
In Nichols's 158-patient retrospective anorectal APR cohort, 29 received VRAM. The following were associated with selection for flap reconstruction:
- Current smoking
- Anal tumor location
- Larger perineal skin resection and neoadjuvant radiation
Prior abdominal surgery was associated with complications in Nelson's separate VRAM-versus-mixed-thigh series.[16]
Comparative Outcomes
VRAM vs Gracilis
Stein's 2019 multicenter retrospective comparison of 61 VRAM and 27 gracilis reconstructions:[13]
- No difference in minor complications (44% gracilis versus 48% VRAM, P=0.8)[13]
- No difference in major complications (19% versus 13%, P=0.53)[13]
- In this retrospective cohort, mean time to complete perineal wound healing was 72 days with gracilis and 120 days with VRAM before outlier removal (P = 0.04); after outliers were removed, median time was 68 versus 67 days, respectively (P = 0.19).[13]
- Muscle-only gracilis heals faster than musculocutaneous gracilis
Vulvo-perineal meta-analysis:[14]
- VRAM higher pooled donor-site complication proportions (57.6% versus 16.0% gracilis) across different vulvoperineal series[14]
- Similar recipient-site outcomes
- Overall recipient-site complication proportions did not differ significantly (33.9% VRAM versus 26.8% gracilis, P = 0.337), but pooled recipient-site dehiscence was 15.8% versus 27.6% (P < 0.05) across heterogeneous studies.[14]
Practical takeaway: both flaps are viable in selected defects. The comparative series found no statistically significant difference in its main complication outcomes; the proportional meta-analysis suggests more reported VRAM donor morbidity but combines heterogeneous cohorts. Paprottka's fistula series is too small to rank continence by flap.[4][13][14]
VRAM vs IGAM (Inferior Gluteal Artery Myocutaneous)
130-patient pelvic-exenteration series (97.7% previously irradiated):[15]
- IGAM had fewer recorded adverse outcomes than VRAM, including flap failure, return to theatre and wound dehiscence, in this center's retrospective comparison
- Defect characteristics and flap selection may confound this center's retrospective IGAM-VRAM comparison
VRAM vs Mixed Thigh Flaps[16]
- Thigh flaps had greater major complications (42% versus 15%)[16]
- Higher cellulitis, pelvic abscess, major dehiscence
- This was an observational 114-VRAM versus 19-thigh comparison. The thigh group was not an isolated ALT/VL cohort
VRAM vs IGAP (Inferior Gluteal Artery Perforator)[17]
- No significant difference in minor or major complications
- The retrospective comparator pooled 69 unilateral and bilateral IGAP reconstructions versus 47 VRAM flaps.[17]
- IGAP preserves abdominal wall integrity
Risk Factors and Patient Selection
- Smoking. Associated with flap complications on univariate analysis in Proctor's cohort (P=0.003); support cessation when feasible
- Neoadjuvant radiotherapy. Associated on univariate analysis in that cohort (P=0.047)
- Prior abdominal surgery. Assess for prior TRAM or DIEP harvest or vascular ligation, which may compromise the DIEA pedicle
Potential limitations requiring individual vascular and donor-wall assessment:
- Prior TRAM or DIEP harvest on the intended side or known injury to its epigastric supply
- Prior iliac or inferior epigastric vessel ligation
- Severe abdominal-wall weakness, major hernia or multiple prior laparotomies
Consider alternatives:
- IGAM or IGAP when donor-abdominal morbidity, positioning and defect geometry favor gluteal tissue
- Gracilis when its volume and reach meet the defect's needs
- Omental flap when viable omentum provides appropriate interposition for a urosymphyseal fistula
Donor-Site Management
The donor abdominal wall is an important source of morbidity, alongside recipient-site complications.
- Anterior-sheath or fascial repair. Plan around the actual harvested sheath, tension, prior incisions and stoma; suture and closure pattern are selected for the defect. PDS is an absorbable suture, not a nonabsorbable one.
- Mesh reinforcement. Assess case by case. A 58-patient randomized trial did not demonstrate prevention of one-year CT-detected hernia with collagen mesh (8/24 versus 12/24, P=0.38)[26]; in a retrospective 100-patient cohort, 69 achieved primary fascial closure; among them, hernia occurred in 0/25 with mesh versus 4/44 without (P = 0.289), while infection requiring intervention occurred in 3/25 versus 0/44 (P = 0.044).[27] Neither study decides every complex or bridged closure.[26][27]
- Drain: use according to the extent of dissection, dead space and local protocol.
- Anterior sheath below arcuate line. The only aponeurotic layer here; in Schellerer et al.'s VRAM technique, anterior rectus fascia is preserved to permit caudal primary closure.[35]
- Long-term hernia surveillance. In a 173-patient colorectal VRAM cohort with serial CT (median follow-up 49 months), five-year Kaplan–Meier estimates were 29.1% for donor-site incisional hernia and 53.3% for parastomal hernia; corresponding estimates accounting for death as a competing risk were 27.5% and 22.1%. All observed parastomal hernias occurred at rectus-transiting stomas, with none detected among 44 oblique-transiting urostomies.[40]
- See Pelvic and Perineal Flap Postoperative Care for shared recipient-site positioning, drain management and flap-monitoring principles.
Postoperative Imaging Findings
Normal VRAM appearance on CT/MRI:[2]
- Homogeneous soft-tissue density obliterating pelvic dead space
- Enhancement pattern following the DIEA
- Gradual fatty replacement of muscle over time (expected)
Complications to recognize:
- Fluid collections suggest infection or seroma
- Lack of enhancement suggests flap necrosis
- Herniation at donor or recipient sites
Key Takeaways
- VRAM is a commonly used pedicled flap for pelvic or perineal reconstruction after radical urologic oncology, particularly pelvic exenteration with radiation.
- Inferiorly based on the DIEA; confirm its integrity and flap reach in the individual patient. Kim's 98.3% imaging observation applied to a 60-person evaluable cohort.[3]
- Avoid pedicle torsion, compression and tension.
- Counsel about donor and recipient morbidity. Reported abdominal-wall hernia rates vary markedly with cohort, definition, imaging and follow-up; routine mesh benefit is unproven.
- Assess smoking, prior radiation, previous abdominal surgery, stomas and donor-wall integrity as part of defect-specific planning.
- Select the flap for needed skin, bulk, vascularity and reach.
- Muscle-sparing and robotic variants are described for selected patients; functional and donor-wall benefits still require technique-specific evaluation.
Operative Video
References
1. Radwan RW, Tang AM, Harries RL, et al. "Vertical Rectus Abdominis Flap (VRAM) for Perineal Reconstruction Following Pelvic Surgery — A Systematic Review." J Plast Reconstr Aesthet Surg. 2021;74(3):523–529. doi:10.1016/j.bjps.2020.10.100
2. Sagebiel TL, Faria SC, Balachandran A, et al. "Pelvic Reconstruction With Omental and VRAM Flaps — Anatomy, Surgical Technique, Normal Postoperative Findings, and Complications." Radiographics. 2011;31(7):2005–19. doi:10.1148/rg.317115112
3. Kim E, Fernando C, McCombie A, et al. "Abdominal and Perineal Hernia Rates Following VRAM Flap Reconstruction — A Supraregional Experience." J Plast Reconstr Aesthet Surg. 2022;75(3):1158–1163. doi:10.1016/j.bjps.2021.11.002
4. Paprottka FJ, Krezdorn N, Lohmeyer JA, et al. "Plastic Reconstructive Surgery Techniques Using VRAM or Gracilis Flaps in Order to Successfully Treat Complex Urogenital Fistulas." J Plast Reconstr Aesthet Surg. 2016;69(1):128–37. doi:10.1016/j.bjps.2015.08.026
5. Escandón JM, Kreutz-Rodrigues L, Fadel AE, et al. "Optimizing Flap Selection for Urosymphyseal Fistula Repair — A Comparative Analysis of Surgical Outcomes." Microsurgery. 2026;46(3):e70197. doi:10.1002/micr.70197
6. Küntscher MV, Mansouri S, Noack N, Hartmann B. "Versatility of Vertical Rectus Abdominis Musculocutaneous Flaps." Microsurgery. 2006;26(5):363–9. doi:10.1002/micr.20253
7. Banuelos J, Kreutz-Rodrigues L, Mills AM, et al. "VRAM to Reconstruct Thigh and Groin Defects — A Retrospective Cohort and Systematic Review." J Plast Reconstr Aesthet Surg. 2022;75(6):1893–1901. doi:10.1016/j.bjps.2022.01.015
8. Chen Q, Dong R, Zeng A, et al. "The Reconstructive Strategy for Pelvic Oncological Surgery With Various Types of MS-VRAM Flaps." J Plast Reconstr Aesthet Surg. 2022;75(7):2090–2097. doi:10.1016/j.bjps.2022.02.014
9. Pérez-García A, García-Granero Á, Thione A, et al. "Extended VRAM for Reconstruction of Large Pelviperineal Defects Following Oncologic Resection." J Surg Oncol. 2022;126(8):1383–1388. doi:10.1002/jso.27068
10. Trapero A, Pérez-García A, Thione A, et al. "VRAM Flap Transposition in Pelviperineal Reconstruction — A Technical Note." J Plast Reconstr Aesthet Surg. 2022;75(10):3877–3903. doi:10.1016/j.bjps.2022.08.060
11. Proctor MJ, Westwood DA, Donahoe S, et al. "Morbidity Associated With the Immediate VRAM Reconstruction After Radical Pelvic Surgery." Colorectal Dis. 2020;22(5):562–568. doi:10.1111/codi.14909
12. Nichols DS, Satteson E, Harbor P, et al. "Factors Associated With the Use of VRAM Reconstruction Following APR for Anorectal Cancer." J Surg Oncol. 2020;122(5):923–927. doi:10.1002/jso.26086
13. Stein MJ, Karir A, Ramji M, et al. "Surgical Outcomes of VRAM Versus Gracilis Flaps for the Reconstruction of Pelvic Defects Following Oncologic Resection." J Plast Reconstr Aesthet Surg. 2019;72(4):565–571. doi:10.1016/j.bjps.2018.12.044
14. Eseme EA, Scampa M, Viscardi JA, et al. "Surgical Outcomes of VRAM vs Gracilis Flaps in Vulvo-Perineal Reconstruction Following Oncologic Resection — A Proportional Meta-Analysis." Cancers. 2022;14(17):4300. doi:10.3390/cancers14174300
15. Read T, Morrison EJ, Lonie S, Sheikh R, Chauhan A. "Treatment Outcomes After Pelvic Exenteration With IGAM or VRAM Flap Reconstruction — Review of 130 Consecutive Cases." J Plast Reconstr Aesthet Surg. 2025;103:140–147. doi:10.1016/j.bjps.2025.01.087
16. Nelson RA, Butler CE. "Surgical Outcomes of VRAM Versus Thigh Flaps for Immediate Reconstruction of Pelvic and Perineal Cancer Resection Defects." Plast Reconstr Surg. 2009;123(1):175–183. doi:10.1097/PRS.0b013e3181904df7
17. Benedict KC, Songcharoen SJ, Stephens KL, et al. "Comparison of Inferior Gluteal Artery Perforator Flaps Versus VRAM Flaps in the Reconstruction of Perineal Wounds." J Plast Reconstr Aesthet Surg. 2023;84:514–520. doi:10.1016/j.bjps.2023.06.020
18. Guney G, Delara RM, Yi J, Erdemoglu E, Butler KA. "Robotic Rectus Muscle Flap Reconstruction After Pelvic Exenteration in Gynecological Oncology — Current and Future Perspectives." Cancers. 2026;18(3):375. doi:10.3390/cancers18030375
19. Combs PD, Sousa JD, Louie O, et al. "Comparison of Vertical and Oblique Rectus Abdominis Myocutaneous Flaps for Pelvic, Perineal, and Groin Reconstruction." Plast Reconstr Surg. 2014;134(2):315–323. doi:10.1097/PRS.0000000000000324
20. Davila AA, Goldman J, Kleban S, et al. "Reducing Complications and Expanding Use of Robotic Rectus Abdominis Muscle Harvest for Pelvic Reconstruction." Plast Reconstr Surg. 2022;150(1):190–195. doi:10.1097/PRS.0000000000009233
21. Asaad M, Pisters LL, Klein GT, et al. "Robotic Rectus Abdominis Muscle Flap Following Robotic Extirpative Surgery." Plast Reconstr Surg. 2021;148(6):1377–1381. doi:10.1097/PRS.0000000000008592
22. Bruce RG, El-Galley RE, Galloway NT. "Use of Rectus Abdominis Muscle Flap for the Treatment of Complex and Refractory Urethrovaginal Fistulas." J Urol. 2000;163(4):1212–1215. doi:10.1016/s0022-5347(05)67726-9
23. Parsons JK, Tufaro A, Chang B, Schoenberg MP. "Rectus Abdominis Vaginoplasty After Anterior Exenteration for Urologic Malignancy." Urology. 2003;61(6):1249–1252; discussion 1253. doi:10.1016/s0090-4295(03)00147-x
24. Smith EA, Kaye JD, Lee JY, Kirsch AJ, Williams JK. "Use of Rectus Abdominis Muscle Flap as Adjunct to Bladder Neck Closure in Patients With Neurogenic Incontinence: Preliminary Experience." J Urol. 2010;183(4):1556–1560. doi:10.1016/j.juro.2009.12.044
25. Horton CE, Sadove RC, Jordan GH, Sagher U. "Use of the Rectus Abdominis Muscle and Fascia Flap in Reconstruction of Epispadias / Exstrophy." Clin Plast Surg. 1988;15(3):393–397. doi:10.1016/s0094-1298(20)31415-2
26. Mortensen AR, Grossmann I, Rosenkilde M, et al. "Double-Blind Randomized Controlled Trial of Collagen Mesh for the Prevention of Abdominal Incisional Hernia in Patients Having a Vertical Rectus Abdominis Myocutaneous Flap During Surgery for Advanced Pelvic Malignancy." Colorectal Dis. 2017;19(5):491–500. doi:10.1111/codi.13552
27. Barnes LL, Holland MC, Lentz R, et al. "Abdominal Mesh Use in Pedicled Rectus Abdominis Flaps for Pelvic Reconstruction." Plast Reconstr Surg Glob Open. 2024;12(8):e6100. doi:10.1097/GOX.0000000000006100
28. Guillier D, Morelli Coppola M, Watfa W, et al. "Oblique Rectus Abdominis Myocutaneous Versus Anterolateral Thigh-Vastus Lateralis Flap for Perineal Reconstruction: A Retrospective Comparative Study." Plast Reconstr Surg Glob Open. 2026;e7686. doi:10.1097/GOX.0000000000007686
29. Barton DP, et al. Pelvic Exenteration for Central Pelvic Cancer. In: Hoffman M, Hull TL, Bochner BH, eds. Major Complications of Female Pelvic Surgery: A Multidisciplinary Approach. Springer; 2025:427–438. doi:10.1007/978-3-031-66772-5_38
30. Persson P, Chong P, Steele CW, et al. Prevention and management of complications in pelvic exenteration. Eur J Surg Oncol. 2022;48(11):2277–2283. doi:10.1016/j.ejso.2021.12.470
31. Johnson YL, West MA, Gould LE, et al. Empty pelvis syndrome: a systematic review of reconstruction techniques and their associated complications. Colorectal Dis. 2022;24(1):16–26. doi:10.1111/codi.15956
32. Sutton PA, Brown KGM, Ebrahimi N, et al. Long-term surgical complications following pelvic exenteration: operative management of the empty pelvis syndrome. Colorectal Dis. 2022;24(12):1491–1497. doi:10.1111/codi.16238
33. Bini A, Stavrianos S. Pelvic and perineal reconstruction after bowel, gynecological or sacral tumor resection: a case series. J Clin Med. 2025;14(9):3172. doi:10.3390/jcm14093172
34. Ong HS, Ji T, Zhang CP. "Rectus abdominis." AO Surgery Reference. AO Foundation. https://surgeryreference.aofoundation.org/cmf/reconstruction/basic-technique/rectus-abdominis
35. Schellerer VS, Bartholomé L, Langheinrich MC, et al. "Donor site morbidity of patients receiving vertical rectus abdominis myocutaneous flap for perineal, vaginal or inguinal reconstruction." World J Surg. 2021;45(1):132–140. doi:10.1007/s00268-020-05788-5
36. Horch RE, Ludolph I, Arkudas A, Cai A. "Personalized reconstruction of genital defects in complicated wounds with vertical rectus abdominis myocutaneous flaps including urethral neo-orifice." J Pers Med. 2021;11(11):1076. doi:10.3390/jpm11111076
37. Temperley HC, Shokuhi P, O’Sullivan NJ, et al. "Primary closure versus vertical rectus abdominis myocutaneous (VRAM) flap closure of perineal wound following abdominoperineal resection—a systematic review and meta-analysis." Ir J Med Sci. 2024;193(4):1721–1728. doi:10.1007/s11845-024-03651-3
38. Wu Y, Shen Y, Zhang Z, Yang T, Wang Z. "Flap reconstruction versus primary perineal closure after abdominoperineal resection: a systematic review and meta-analysis." Updates Surg. 2026;online ahead of print. doi:10.1007/s13304-026-02713-8
39. Vervaet C, Maeyaert C, Allaeys M, Berrevoet F, Eker HH, van Ramshorst GH. "Incisional and parastomal hernias after harvesting of vertical rectus abdominis myocutaneous (VRAM) flaps: incidence, treatment options and outcomes." Hernia. 2025;29(1):251. doi:10.1007/s10029-025-03406-8
40. Tang AM, Spencer N, Parkins K, et al. "Radiological Incidence of Donor-Site Incisional Hernia and Parastomal Hernia After Vertical Rectus Abdominus Myocutaneous Flap-Based Reconstruction Following Colorectal Surgery." Colorectal Dis. 2023;25(4):738–746. doi:10.1111/codi.16400