Buccal Mucosa Graft (BMG)
Buccal mucosa is the usual first-choice graft for substitution urethroplasty. Its hair-free, nonkeratinized epithelium, pliability and suitable lamina propria support use in a wet urinary environment. The choice still depends on donor health, recipient vascularity, defect geometry and the patient's priorities. A graft must revascularize after transfer; it is not a vascularized flap.[2][3][19]
See Grafts in GU Reconstruction for tissue selection and The Oral Cavity for harvest anatomy. For the adoption of buccal mucosa in urethroplasty, see the History of Urethral Surgery.
Tissue Biology and Selection
BMG is well suited to reconstruction, but it can scar, contract, become infected or fail.[3][4]
AUA 2023 recommends oral mucosa as the first graft choice and permits buccal or lingual mucosa as equivalent alternatives .[2] EAU 2026 recommends buccal or lingual mucosa when a graft is needed and available and a strong recommendation to inform patients about the different oral morbidity of buccal, lingual and lower-lip grafts.[19] Donor-site effects differ: cheek harvest can cause numbness, tightness and swelling; lingual harvest can affect speech and tongue movement.[2][19]
Inspect for oral disease, scars, restricted opening and previous harvests. Buccal mucosa is often available. For LS-associated urethral strictures, avoid genital skin; oral mucosa is generally preferred. LS strictures can recur after BMG.[2][19]
Harvest and Preparation
Exposure and protection
Coordinate airway access, oral exposure and local anesthesia with the anesthetic team. Identify and protect the parotid duct papilla opposite the upper second molar, oral commissure and relevant sensory structures. Mark the actual graft needed within the patient's available healthy mucosa; a fixed margin does not replace direct identification of the duct. When the papilla is difficult to see, stimulating salivary flow (for example, with drops of lemon juice on the tongue) can help visualize and mark it before the graft is outlined.[3][23]
Elevation and sizing
Submucosal infiltration can facilitate dissection and hemostasis; the agent, concentration and total dose follow the operative and anesthetic plan. Elevate mucosa with its lamina propria while avoiding unnecessary buccinator injury. Remove excess adherent fat and muscle without perforating or excessively thinning the graft. Secure the prepared graft in close contact with a suitable vascularized recipient bed, avoiding folds, hematoma and shear.[3][6]
Available dimensions vary with oral anatomy, prior harvests and graft design. A defect longer than 7 cm does not automatically mandate bilateral cheek harvest. Plan the total area and configuration needed, and discuss bilateral cheek, lingual or other appropriate donor options when one cheek is insufficient.[1][19]
Close the donor site or leave it open?
Both are accepted options. Consider hemostasis, defect size, tension, oral mobility and patient preference. A large defect may not permit a comfortable primary closure. EAU 2026 reviewed the randomized trials and gives no clear recommendation for or against closure (§9.5).[2][19]
- Soave's 135-patient RCT found nonclosure noninferior for oral pain intensity and affective quality during follow-up.[11]
- Hwang's systematic review based its main analysis on three randomized trials, with two quasi-randomized studies added in sensitivity analysis. Evidence for pain, numbness, salivation, mouth opening and further procedures was low or very low certainty.[20]
- Güler’s later review included seven studies, four using quasi-random allocation and one involving lingual grafts. It suggested less early pain with nonclosure, but mixed donor sites, sensitivity analyses and imprecise reporting limit a universal recommendation.[21]
The often-quoted pain scores 2.26 versus 3.68 came from Wood's small prospective comparison, separate from Soave's RCT. Wood's scores come from a separate prospective comparison.[12]
Applications and Placement
| Setting | Role and limitations |
|---|---|
| Bulbar/anterior stricture | Dorsal, dorsolateral, ventral and inlay configurations are selected according to the plate, spongiosum and graft support; no placement is universally best |
| Penile or panurethral stricture | One-sided dissection, multiple grafts or staged reconstruction may be appropriate |
| Focal near-obliteration within a longer bulbar stricture | Selected double-sided graft or augmented anastomotic techniques; a completely absent plate requires a different reconstruction than simple augmentation |
| Posterior stenosis after cancer treatment | Selected nonobliterative cases can undergo graft reconstruction; sphincter function, bladder capacity, radiation damage and fistula must be assessed |
| Distal/fossa navicularis stricture | Transurethral ventral inlay is one specialist option; disease extending proximally requires adequate assessment |
| Female urethral stricture | Dorsal or ventral oral-graft augmentation is used for selected recurrent strictures; assess the urethral bed, donor tissue and continence risk when choosing the approach.[26] |
| Complex/failed hypospadias | Staged oral graft reconstruction may be appropriate; later growth, curvature and long-term outcomes require follow-up |
| Ureteral reconstruction | Selected complex strictures may be augmented with BMG; viability, defect configuration and vascularized support determine suitability |
These applications have different evidence and operative requirements. EAU 2026 gives a strong recommendation against using grafts in a tubularized fashion in a single-stage approach; flaps are preferred when a one-stage tube is required.[19] Grafting a bed first and tubularizing it after healing in a later stage is a distinct operation.[3][19]
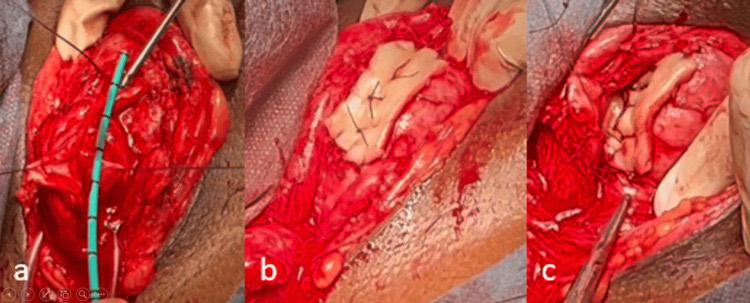
Augmented anastomotic urethroplasty with a buccal mucosa graft. a, 4-cm bulbar urethral stricture; b, buccal mucosa graft placement; c, anastomosis of both urethral ends with the graft. From Akjay A, et al. Cureus. 2026;18(3):e105255, Figure 6 (CC BY 4.0).[25]
Detailed technique pages: urethral reconstruction, BMG ureteroplasty, and omental support.
Selected outcomes: preserve the population and endpoint
- Posterior reconstruction (Doležel 2024). 38 patients with mixed posterior or VUAS pathology and open or endoscopic graft approaches. Three-year freedom from recurrence was 65%; it rose to 81% only when an additional “auxiliary” DVIU was allowed. New incontinence occurred in 2/18 initially continent patients. The 81% endpoint allows auxiliary DVIU.[7]
- Dorsal BMG after prostatectomy plus radiation (Sterling 2024). 45 selected patients with nonobliterative stenosis; seven recurrences, with median 21-month follow-up among those without recurrence. No new SUI was reported, but pre-existing incontinence was common and there was no randomized comparison with excision or transection. The study cannot establish a continence advantage or assess erectile safety in a generally potent population.[8]
- Distal transurethral ventral inlay (Sterling 2023). 44 patients in a retrospective single-center series, with approximately 95% patency without further intervention at mean 36 months.[9]
- Bracka repair (Manasherova 2020). Reported complications were 23/112 with buccal versus 33/108 with preputial grafts, but the groups came from different treatment eras.[10]
The GURS survey describes respondent preference: 134 of 350 invited members responded. BMG was preferred over a penile flap by 95% for circumcised and 84% for uncircumcised patients.[1]
Donor-Site Morbidity and Counseling
Discuss pain, bleeding, swelling, sensory change, difficulty opening the mouth, salivary or duct problems and temporary effects on eating or speaking. Some symptoms persist.[11][12][13][14]
| Evidence | What it contributes |
|---|---|
| Wood 2004 | Only 49/110 men returned the morbidity questionnaire, representing 57 harvests.High symptom rates in respondents.[12] |
| Barbagli 2014 | Retrospective 553-person cheek-harvest cohort with closed ovoid defects; reported satisfaction 98.2%. Bilateral harvest predicted dissatisfaction[13] |
| Castagnetti 2008 | Mixed oral-donor/age series of 78 patients; clinical examination found persistent sensory deficits in 28% of those formally examined at median 7.6 years, often with little perceived bother.[15] |
| Desai 2025 | Prospective 40-person series using oral-health questionnaires; 80% had at least one daily oral activity affected initially and 3/40 had long-term mouth-opening difficulty. Small size limits generalization[14] |
In Fichtner's series, 2 of 32 patients followed beyond five years had lower-lip scarring with transient impaired lip movement. The same series separately reported one urethral fistula, one graft infection or necrosis and four recurrent strictures; these are recipient-site outcomes, not oral donor-site events.[24]
Provide a plan for analgesia, oral hygiene, diet progression and review of persistent bleeding, swelling, sensory change or restricted opening.
Durability and Recurrence
Assess success using freedom from reintervention, symptoms and flow, appropriate anatomical testing and patient-reported function. Short follow-up, survivor-only questionnaires and inconsistent definitions can make percentages look more favorable than durable single-operation success.[2][5][6]
Previous repair: Vetterlein's 534-person retrospective series reported 87.4% initial, 87.5% repeat-BMG and 70.6% secondary-after-other-repair success at median 33 months.[16]
LS. The historical 50%-versus 80% single-stage versus staged comparison involved only eight versus five LS patients. Current guidance allows single-stage oral grafting when local conditions are favorable; extensive scarring or an unsuitable plate may require staging or another approach.[17][19]
Comorbidity and length. A 2025 systematic review found associations with diabetes, penile or penobulbar location and longer strictures, but the evidence was observational with variable definitions and follow-up.[22] The 7-cm subgroup result came from only two studies.[22]
Blood loss is not a graft-quality target. Meyer's selected 517-person retrospective analysis associated a larger hemoglobin drop with fewer recurrences. Preserve vascularity and use careful hemostasis; optimize the patient's actual risk factors.[18]
Discuss possible changes in erections, ejaculation, sensation, penile shape and dribbling.[5][6][8]
Comparison With Penile Skin Grafts
PeeBuSt and Alrefaey 2025 found no significant success difference in selected anterior-stricture patients. At 18 months in PeeBuSt, BMG met the study's composite success definition in 91%, versus 89% with penile skin; success required any one of Qmax >15 mL/s, 16-Fr urethral calibration or passage of a 17-Fr cystoscope.[6] Alrefaey reported success at 12 months in 97.9% with BMG versus 93.2% with penile skin.[5] These were not equivalence trials. A 2026 meta-analysis of 11 studies (1,018 patients) pooled higher reported success with penile-skin grafts (OR 0.52), but heterogeneous outcome definitions, follow-up and techniques prevent a definitive tissue ranking.[27] See the penile/preputial graft page for denominators, trial design and donor-site trade-offs.[5][6]
Oral mucosa remains the guideline-preferred graft when appropriate. A healthy penile-skin graft can be considered when oral tissue is unavailable, unsuitable or declined, outside LS-related reconstruction.[2][19]
Investigational Alternatives
Tissue-engineered mucosa, extracellular-vesicle approaches and organoid systems remain areas of research. EAU 2026 gives a strong recommendation against autologous tissue-engineered oral mucosa outside a clinical trial.[4][19]
Videos
References
1. Berg C, Singh A, Hu P, et al. "Current Trends in the Use of Buccal Grafts During Urethroplasty Among Society of Genitourinary Reconstructive Surgeons." Urology. 2024;191:139–143. doi:10.1016/j.urology.2024.06.019
2. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. "Urethral Stricture Disease Guideline Amendment (2023)." J Urol. 2023;210(1):64–71. doi:10.1097/JU.0000000000003482
3. Horiguchi A. "Substitution Urethroplasty Using Oral Mucosa Graft for Male Anterior Urethral Stricture Disease: Current Topics and Reviews." Int J Urol. 2017;24(7):493–503. doi:10.1111/iju.13356
4. Sterling J, Hecksher D, Hayden C, et al. "Buccal Mucosa a Narrative Review: How Does It Work, How Is It Used, What Is Coming Next." Urology. 2026:S0090-4295(26)00169-X. doi:10.1016/j.urology.2026.03.015
5. Alrefaey A, Anwar MA, Abdelmagid ME, et al. "Comparative Outcomes of Penile Skin Grafts Versus Buccal Mucosal Grafts in Urethroplasty for the Treatment of Extensive Anterior Urethral Strictures." Sci Rep. 2025;15(1):29508. doi:10.1038/s41598-025-14191-w
6. Tyagi S, Parmar KM, Singh SK, et al. "'Pee'BuSt Trial: A Single-Centre Prospective Randomized Study Comparing Functional and Anatomic Outcomes After Augmentation Urethroplasty With Penile Skin Graft Versus Buccal Mucosa Graft for Anterior Urethral Stricture Disease." World J Urol. 2022;40(2):475–481. doi:10.1007/s00345-021-03843-x
7. Doležel J, Hrabec R, Uher M, et al. "Substitution Urethroplasty With Buccal Mucosal Graft in the Management of Stricture of Vesicourethral Anastomosis or Membranous Urethra: Single-Institution Long-Term Experience With Perineal Approach and Endourethroplasty." Urology. 2024;192:126–132. doi:10.1016/j.urology.2024.05.034
8. Sterling J, Simhan J, Flynn BJ, et al. "Multi-Institutional Outcomes of Dorsal Onlay Buccal Mucosal Graft Urethroplasty in Patients With Postprostatectomy, Postradiation Anastomotic Stenosis." J Urol. 2024;211(4):596–604. doi:10.1097/JU.0000000000003848
9. Sterling J, Daneshvar M, Nikolavsky D. "Transurethral Ventral Inlay Buccal Mucosa Graft Urethroplasty: Technique and Intermediate Outcomes." BJU Int. 2023;132(1):109–111. doi:10.1111/bju.16007
10. Manasherova D, Kozyrev G, Nikolaev V, et al. "Bracka's Method of Proximal Hypospadias Repair: Preputial Skin or Buccal Mucosa?" Urology. 2020;138:138–143. doi:10.1016/j.urology.2019.12.027
11. Soave A, Dahlem R, Pinnschmidt HO, et al. "Substitution Urethroplasty With Closure Versus Nonclosure of the Buccal Mucosa Graft Harvest Site: A Randomized Controlled Trial With a Detailed Analysis of Oral Pain and Morbidity." Eur Urol. 2018;73(6):910–922. doi:10.1016/j.eururo.2017.11.014
12. Wood DN, Allen SE, Andrich DE, Greenwell TJ, Mundy AR. "The Morbidity of Buccal Mucosal Graft Harvest for Urethroplasty and the Effect of Nonclosure of the Graft Harvest Site on Postoperative Pain." J Urol. 2004;172(2):580–583. doi:10.1097/01.ju.0000132846.01144.9f
13. Barbagli G, Fossati N, Sansalone S, et al. "Prediction of Early and Late Complications After Oral Mucosal Graft Harvesting: Multivariable Analysis From a Cohort of 553 Consecutive Patients." J Urol. 2014;191(3):688–693. doi:10.1016/j.juro.2013.09.006
14. Desai D, Joshi S, Ravichandran K, et al. "Donor Site Morbidity and Impact on Oral Health Following Buccal Mucosal Graft Harvesting for Urethroplasty: A Prospective Study." World J Urol. 2025;43(1):531. doi:10.1007/s00345-025-05898-6
15. Castagnetti M, Ghirardo V, Capizzi A, Andretta M, Rigamonti W. "Donor Site Outcome After Oral Mucosa Harvest for Urethroplasty in Children and Adults." J Urol. 2008;180(6):2624–2628. doi:10.1016/j.juro.2008.08.053
16. Vetterlein MW, Stahlberg J, Zumstein V, et al. "The Impact of Surgical Sequence on Stricture Recurrence After Anterior 1-Stage Buccal Mucosal Graft Urethroplasty: Comparative Effectiveness of Initial, Repeat and Secondary Procedures." J Urol. 2018;200(6):1308–1314. doi:10.1016/j.juro.2018.06.067
17. Levine LA, Strom KH, Lux MM. "Buccal Mucosa Graft Urethroplasty for Anterior Urethral Stricture Repair: Evaluation of the Impact of Stricture Location and Lichen Sclerosus on Surgical Outcome." J Urol. 2007;178(5):2011–2015. doi:10.1016/j.juro.2007.07.034
18. Meyer CP, Lamp J, Vetterlein MW, et al. "Impact of Cardiovascular and Metabolic Risk Factors on Stricture Recurrence After Anterior One-Stage Buccal Mucosal Graft Urethroplasty." Urology. 2020;146:253–259. doi:10.1016/j.urology.2020.07.073
19. EAU. Urethral Strictures: Tissue Transfer and Disease Management in Males. 2026; tissue-transfer and LS reconstruction guidance.
20. Hwang EC, de Fazio A, Hamilton K, et al. A systematic review of randomized controlled trials comparing buccal mucosal graft harvest site non-closure versus closure in patients undergoing urethral reconstruction. World J Mens Health. 2022;40(1):116. doi:10.5534/wjmh.200175.
21. Güler Y. Comparison of closure versus non-closure of the intraoral buccal mucosa graft site in urethroplasties: a systematic review and meta-analysis. Arab J Urol. 2023;21(1):18. doi:10.1080/2090598X.2022.2097613.
22. Yoshikawa GB, Gomar GG, Gadens GC, et al. Re-stricture after buccal mucosal graft urethroplasty: a systematic review and meta-analysis. Acta Cir Bras. 2025;40:e403525. doi:10.1590/acb403525.
23. Ravichandran K, Harrison W, Desai D. Harvesting of Oral Mucosal Grafts. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:11–19. doi:10.1007/978-981-97-5196-9_2
24. Fichtner J, Filipas D, Fisch M, Hohenfellner R, Thüroff JW. Long-term outcome of ventral buccal mucosa onlay graft urethroplasty for urethral stricture repair. Urology. 2004;64(4):648–50. doi:10.1016/j.urology.2004.05.011
25. Akjay A, Ettoumi N, Ettoumi N, Jmil N, Bidan S, Nguema LD, et al. "Delayed Urethral Stricture Following Remote Electrocution: A Case Report." Cureus. 2026;18(3):e105255. doi:10.7759/cureus.105255
26. European Association of Urology. "Disease Management in Females." EAU Guidelines on Urethral Strictures. 2026. Guideline chapter.
27. Abbas SM, Farhan M, Khan A, et al. "Penile skin graft versus buccal mucosal graft for anterior urethral strictures in adult urethroplasty- a systematic review and meta-analysis." Int Urol Nephrol. 2026;58(6):1895–1910. doi:10.1007/s11255-025-04955-8