Lingual Mucosa Graft (LMG)
Lingual mucosa from the ventrolateral tongue is an alternative to cheek mucosa for substitution urethroplasty. AUA 2023 statement 19b permits buccal or lingual grafts as equivalent alternatives .[1] The thinner lingual profile may be useful in distal reconstruction.[1]
See Grafts in GU Reconstruction, The Oral Cavity, Buccal Mucosa and Oral-Lip Mucosa.
Anatomy and Graft Preparation
Harvest lining mucosa from the ventrolateral tongue. Preserve the frenulum, floor-of-mouth duct openings and underlying muscle; identify visible veins. General sensation travels in the lingual nerve (V3), with chorda tympani taste fibers (VII). Vascular supply comes from the lingual arterial system.[2][3][4][5] Cadaver studies describe variable intralingual branching.[2][3][4][5]
Campos-Juanatey's histological series analyzed 30 buccal and 22 lingual graft specimens from 33 patients. Median thickness was 1,693 µm for cheek and 1,347 µm for tongue; the 1,599 µm figure was pooled across donors. Lingual samples had thinner epithelium/submucosa and less fat, without a significant difference in vascular measurements. There was no clinical-outcome correlation. Preserve viable lamina propria during preparation; microscopic residual muscle does not justify deliberate deep muscle harvest.[6]
Harvest Principles
- Assess oral health, mouth opening, prior donor surgery, baseline speech/taste and the patient's functional priorities. Coordinate airway placement and oral access with anesthesia; nasotracheal intubation is one described approach.
- Measure the recipient defect before final donor marking. Retract the tongue and expose the ventrolateral mucosa. Protect the frenulum and submandibular duct openings.
- Mark a strip that can be harvested without excessive tension or deep dissection. Published techniques differ: separate bilateral strips can preserve the tip/frenulum.
- Elevate mucosa with its lamina propria, staying superficial to tongue muscle and protecting the neurovascular structures. Remove excess deep tissue without making the graft excessively thin or damaging its supporting layer.
- Obtain meticulous hemostasis and manage the donor defect according to its size and tension.
- Keep the graft moist, orient the epithelium toward the lumen and secure it to a vascular recipient bed according to the chosen urethroplasty.[7][6][8]
The original Simonato 2006 pilot included eight patients.[9]
Kumar's 2008 technique report describes the sequence used by many surgeons. The graft is taken from the lateral mucosal lining of the tongue, starting at the posterior landmark on one side and, when a longer graft is needed, continuing across the tip to the other side. The donor site is closed with a continuous running 4-0 polyglactin suture. In that 28-patient early series the mean graft length was 6.5 cm and mean harvest time 18 minutes. Follow-up averaged 4.2 months. On the first postoperative day, donor-site pain was reported by 23/25 (92%) assessed patients and slurred speech by 6/25 (24%).[8] Patients resumed oral fluids within 24 hours, a soft diet at 48–72 hours and a normal diet at 4–5 days.[7]
Comparative Evidence
The 2021 Wang meta-analysis included 632 patients in 12 comparative studies (four randomized, eight nonrandomized). Reported urethroplasty outcomes around one year were similar, while donor effects differed: lingual harvest produced more early speech/tongue-protrusion difficulty, and cheek harvest more swelling and numbness.[10]
The earlier Abrate 2019 review pooled six comparative studies for success: OR 1.65 (95% CI 0.95–2.87). Its random-effects estimate for late oral complications was OR 0.18 (0.03–1.26), with substantial heterogeneity. Both confidence intervals crossed 1; statistical superiority was not shown.[8]
| Clinical setting | Directly relevant evidence | Practical interpretation |
|---|---|---|
| Anterior stricture, cheek versus tongue | Lumen 2016: 29 per group; 24/29 cheek and 26/29 lingual successes, mean 30-month follow-up | Small prospective nonrandomized comparison; no significant difference, not an equivalence trial [11] |
| Long anterior strictures | Xu 2017: 81 men; 82.7% overall success, mean 41 months; 12 received combined cheek/lingual grafts [12] | — |
| Lichen sclerosus | Aldaqadossi 2020: 36 enrolled, 34 assessed; 88.2% success, median 66.5 months | Selected single-arm evidence [13] |
For long strictures, Xu reported 9–12 cm strips in 52 patients, longer strips in 17 and combined lingual/buccal harvest in 12. The 8–20 cm range was stricture length. Choose graft width and total donor burden as carefully as length.[12]
Failed Hypospadias and Female Reconstruction
Failed hypospadias: Li 2016 retrospectively selected 56 of 110 patients for one-stage LMG repair: 42 total-onlay and 14 modified Snodgrass/inlay procedures. Initial success was 44/56 (78.6%); 12 developed fistula or stricture. The abstract and main report give inconsistent follow-up summaries, so these results should not be assigned an unqualified follow-up duration.[14] Healthy retained plate and tissue coverage influenced selection.[14]
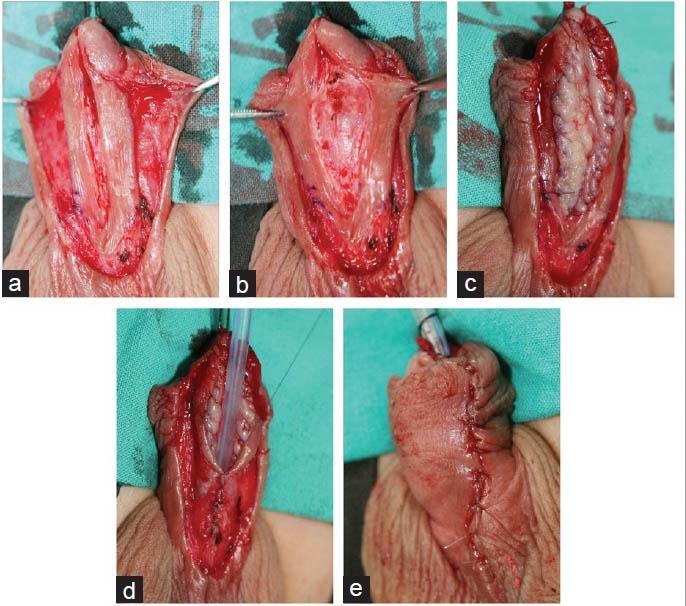
Lingual mucosal graft inlay for failed hypospadias repair. (a) Parallel incisions along the urethral plate from the hypospadiac meatus to the glans tip. (b) Longitudinal midline incision of the urethral plate. (c) The lingual mucosal graft is inserted into the split plate and sutured to the margins of the healthy urethra. (d) After glans-wing mobilization, the augmented plate is tubularized over a fenestrated silicone stent. (e) Subcutaneous tissue and skin are closed in layers over the neourethra. From Li HB, et al. Asian J Androl. 2016;18(3):467-470, Figure 2 (CC BY-NC-SA).[14]
Hongyong 2017 compared 33 lingual with 29 grafts labeled “buccal.” Its operative Methods and Figures 7–8 identify the comparator as lower-lip mucosa. Patients were treated in different eras, follow-up was only 5–12 months, and donor-site outcomes were not collected. Success was 28/33 versus 24/29. This is not a randomized cheek-versus-tongue trial or evidence of better oral morbidity with either donor.[15]
Female stricture: Sharma 2010 reported 15 women treated with dorsal-onlay LMG; one needed repeated dilation for submeatal stenosis. Richard 2021 included 19 women receiving either buccal or lingual grafts. Its primary outcome was early subjective LUTS improvement, not anatomical patency. De novo SUI was reported in 15.7% at 1–3 months and 9.1% among those assessed at one year.[17] These series support feasibility while leaving comparative donor, continence and long-term durability questions open.[16][17]
Situations Where Lingual Mucosa Is Chosen
| Situation | Rationale |
|---|---|
| Distal urethral or meatal reconstruction | The AUA guideline notes that the thinner lingual mucosa may restrict the lumen less.[1] |
| Long anterior stricture | Xu described 9–12 cm single strips and longer strips, with combined cheek and lingual grafts in 12 of 81 men.[12] |
| Cheek harvested previously or cheek mucosa unsuitable | The tongue is an additional oral donor site. This choice rests on surgeon judgment and donor availability. |
| Concern about cheek tightness or mouth opening | Cheek harvest caused more early oral tightness in the Lumen comparison. Lingual harvest caused more early speech and eating difficulty.[11] |
Lingual grafts have been used in the same urethroplasty configurations as cheek grafts, including dorsal onlay, ventral onlay and dorsal inlay, because the guideline treats the two donors as equivalent alternatives.[1]
Donor-Site Counseling
Discuss pain, eating/drinking difficulty, altered speech, tongue movement, taste and sensory change. Do not promise resolution by a fixed date or absence of salivary-duct risk.
Lumen's 29-versus-29 comparison found more lingual speech/eating difficulty on day 3 and more cheek tightness at two weeks. At six months, 31% of lingual and 44.8% of cheek patients still reported sensory symptoms; the difference was not significant. Median pain scores were zero in both groups at that visit.[11]
| Time after surgery | Lingual (n = 29) | Cheek (n = 29) | Comparison |
|---|---|---|---|
| Day 3, severe difficulty eating or drinking | 62.1% | 24.1% | p = 0.004 |
| Day 3, severe difficulty speaking | 93.1% | 55.2% | p = 0.001 |
| Day 3, dysgeusia | 48.3% | 13.8% | p = 0.01 |
| Week 2, speech impairment | 55.2% | 13.8% | p = 0.002 |
| Week 2, oral tightness | 6.9% | 41.4% | p = 0.005 |
| Month 6, sensitivity disorders | 31% | 44.8% | p = 0.279 |
| Median pain score (0–10) at day 3, week 2 and month 6 | 6, 3, 0 | 4, 2, 0 | No significant difference |
The pattern is more early speech and eating morbidity after lingual harvest and more oral tightness after cheek harvest.[11]
Xu 2011 included 110 patients, but only 96 had follow-up beyond 12 months. Among those 96, seven reported tongue numbness and three each reported altered taste and slurred speech. Use the followed denominator, and recognize that bilateral/long-strip harvest may carry different morbidity from a short unilateral graft.[18] In a retrospective series of 128 patients with long-segment anterior urethral stricture, harvested grafts >7 cm were associated with greater odds of oral morbidity than grafts <7 cm (OR 4.35; 95% CI 1.35–14.06).[20]
Buccal mucosa remains a common first donor: 99% of 134 respondents in the 350-member 2024 GURS survey selected cheek first.[19]
References
1. Wessells H, Morey A, Souter L, Rahimi L, Vanni A. Urethral stricture disease guideline amendment (2023). J Urol. 2023;210(1):64–71. doi:10.1097/JU.0000000000003482
2. Lopez R, Lauwers F, Paoli JR, Boutault F, Guitard J. Vascular territories of the tongue: anatomical study and clinical applications. Surg Radiol Anat. 2007;29(3):239–44. doi:10.1007/s00276-007-0202-8
3. Shangkuan H, Xinghai W, Zengxing W, et al. Anatomic bases of tongue flaps. Surg Radiol Anat. 1998;20(2):83–8. doi:10.1007/BF01628906
4. Rusu MC, Nimigean V, Podoleanu L, Ivaşcu RV, Niculescu MC. Details of the intralingual topography and morphology of the lingual nerve. Int J Oral Maxillofac Surg. 2008;37(9):835–9. doi:10.1016/j.ijom.2008.05.014
5. Yang HM, Woo YJ, Won SY, et al. Course and distribution of the lingual nerve in the ventral tongue region: anatomical considerations for frenectomy. J Craniofac Surg. 2009;20(5):1359–63. doi:10.1097/SCS.0b013e3181ae42fa
6. Campos-Juanatey F, Azueta Etxebarria A, Calleja Hermosa P, et al. Histological comparison of buccal and lingual mucosa grafts for urethroplasty: do they share tissue structures and vascular supply? J Clin Med. 2022;11(7):2064. doi:10.3390/jcm11072064
7. Kumar A, Das SK, Sharma GK, et al. Lingual mucosal graft substitution urethroplasty for anterior urethral strictures: our technique of graft harvesting. World J Urol. 2008;26(3):275–80. doi:10.1007/s00345-008-0255-2
8. Abrate A, Gregori A, Simonato A. Lingual mucosal graft urethroplasty 12 years later: systematic review and meta-analysis. Asian J Urol. 2019;6:230–241. doi:10.1016/j.ajur.2019.01.001
9. Simonato A, Gregori A, Lissiani A, et al. The tongue as an alternative donor site for graft urethroplasty: a pilot study. J Urol. 2006;175(2):589–92. doi:10.1016/S0022-5347(05)00166-7
10. Wang A, Chua M, Talla V, et al. Lingual versus buccal mucosal graft for augmentation urethroplasty: a meta-analysis of surgical outcomes and patient-reported donor site morbidity. Int Urol Nephrol. 2021;53:907–918. doi:10.1007/s11255-020-02720-7
11. Lumen N, Vierstraete-Verlinde S, Oosterlinck W, et al. Buccal versus lingual mucosa graft in anterior urethroplasty: a prospective comparison of surgical outcome and donor site morbidity. J Urol. 2016;195(1):112–7. doi:10.1016/j.juro.2015.07.098
12. Xu YM, Li C, Xie H, et al. Intermediate-term outcomes and complications of long segment urethroplasty with lingual mucosa grafts. J Urol. 2017;198(2):401–6. doi:10.1016/j.juro.2017.03.045
13. Aldaqadossi HA, Eladawy M, Shaker H, et al. Dorsal onlay urethroplasty using lingual mucosal grafts for lichen sclerosis anterior urethral strictures repair: long-term outcomes. Int J Urol. 2020;27(4):320–5. doi:10.1111/iju.14187
14. Li HB, Xu YM, Fu Q, et al. One-stage dorsal lingual mucosal graft urethroplasty for the treatment of failed hypospadias repair. Asian J Androl. 2016;18(3):467–70. doi:10.4103/1008-682X.157545
15. Hongyong J, Shuzhu C, Min W, Weijing Y, Yidong L. Comparison of lingual mucosa and buccal mucosa grafts used in inlay urethroplasty in failed hypospadias of pre-pubertal boys in a Chinese group. PLoS One. 2017;12(8):e0182803. doi:10.1371/journal.pone.0182803
16. Sharma GK, Pandey A, Bansal H, et al. Dorsal onlay lingual mucosal graft urethroplasty for urethral strictures in women. BJU Int. 2010;105(9):1309–12. doi:10.1111/j.1464-410X.2009.08951.x
17. Richard C, Peyronnet B, Drain A, et al. Dorsal onlay oral mucosa graft urethroplasty for female urethral stricture. Urology. 2021;158:215–21. doi:10.1016/j.urology.2021.09.001
18. Xu YM, Xu QK, Fu Q, et al. Oral complications after lingual mucosal graft harvesting for urethroplasty in 110 cases. BJU Int. 2011;108(1):140–5. doi:10.1111/j.1464-410X.2010.09852.x
19. Berg C, Singh A, Hu P, et al. Current trends in the use of buccal grafts during urethroplasty among Society of Genitourinary Reconstructive Surgeons. Urology. 2024;191:139–43. doi:10.1016/j.urology.2024.06.019
20. Zhang K, Wang T, Cao S, et al. "Multi-Factorial Analysis of Recurrence and Complications of Lingual Mucosa Graft Urethroplasty for Anterior Urethral Stricture: Experience from a Chinese Referral Center." Urology. 2021;152:96-101. doi:10.1016/j.urology.2021.03.017