Reconstructive Ladder
The reconstructive ladder is a teaching framework that organizes wound closure and tissue replacement strategies from simpler to more complex options. Mathes and Nahai helped popularize it in their 1982 textbook.[1] The later reconstructive elevator emphasizes selecting the option that best fits a particular defect, without obligatorily trying each lower rung first.[2]
The guiding principle remains to use the simplest solution that reliably achieves the reconstructive goals: adequate coverage, preserved function, acceptable donor site morbidity, and durability.
The Rungs
1. Healing by Secondary Intention
Allowing the wound to heal naturally by granulation, contraction, and epithelialization without surgical closure.
Appropriate when:
- Small, clean wounds in non-critical locations
- Wounds with significant contamination or infection where closure is premature
- Granulation tissue is developing and wound is contracting favorably
- Patient comorbidities preclude operative intervention
Limitations: Prolonged healing time; significant wound contraction (may cause functional deformity in unfavorable locations); cosmetically inferior; not appropriate for exposed vital structures (tendons, bone, vessels, nerves)
2. Primary Closure
Direct approximation and suture of wound edges when tissue can be brought together without undue tension.
Principle. Closure must be tension-free. Excessive tension impairs perfusion, increases dehiscence risk and produces a wider, more visible scar. Undermining adjacent tissue planes redistributes tension and is often necessary for clean primary closure.
Suture selection: Caliber should be the smallest that provides adequate tissue alignment; there is no benefit to suture stronger than the tissue it approximates.[3]
3. Delayed Primary Closure
Wound edges are temporarily left open and managed with debridement, dressings, and infection control, then closed days later once the wound is clean and conditions are optimized.
Appropriate when:
- Initial wound is contaminated or infected
- Tissue viability is uncertain at initial operation
- Patient was hemodynamically unstable at initial debridement (e.g., Fournier's gangrene, trauma)
Kopechek's review of Fournier's gangrene cites a series in which patients closed primarily underwent a median of 2.5 debridements and 6.5 days before closure.[4] In a single-center conference abstract, delayed primary closure was associated with a hospital stay of 14.3 versus 21.1 days among 18 versus 19 Fournier gangrene patients.[14] In a separate retrospective cohort of 84 patients, 48 underwent primary closure (sometimes with skin grafting) and 36 healed by secondary intention; adjusted wound convalescence was 64% shorter in the closure group.[13]
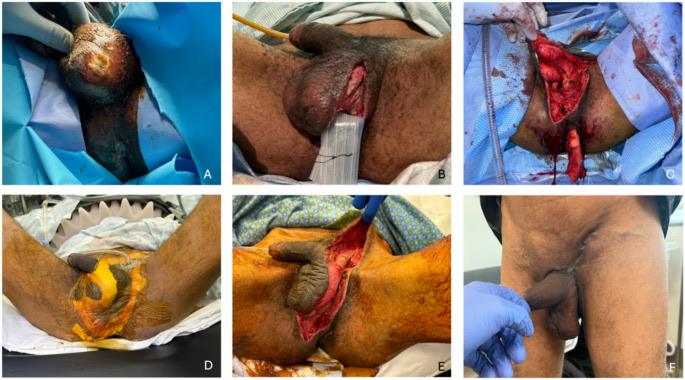
Fournier's gangrene managed by skin-sparing debridement and primary reconstruction. (A) Necrotic skin before debridement. (B) Limited debridement through small incisions at the outside hospital. (C) Repeat debridement at the tertiary center with extended incisions for exposure. (D) Vacuum-assisted closure between debridements. (E) Final wound closure after skin-sparing debridement. (F) Follow-up at one month. From Kopechek KJ, et al. Curr Urol Rep. 2025;26(1):47, Fig. 1 (CC BY).[4]
4. Negative Pressure Wound Therapy (NPWT) and Advanced Dressings
Negative-pressure wound therapy (NPWT) applies controlled subatmospheric pressure to a wound dressing. It can manage exudate and help prepare selected wounds for closure or grafting. A reduction in bacterial burden is not a reliable general effect, and NPWT does not replace debridement or infection treatment.[5][8]
Orgill and Bayer describe four primary mechanisms of action: macrodeformation, microdeformation, fluid removal and environmental control of the wound. Proposed effects include:[5]
- Microdeformation stretches cells and facilitates division and proliferation.
- Fluid removal from the extracellular space reduces edema in oedematous wounds.
- Localized hypoxia near the wound surface upregulates the HIF-1α–VEGF pathway, which promotes angiogenesis.
Advanced dressings (antimicrobial silver dressings, hypochlorous acid solutions, biofilm-disrupting agents) are often applied in combination with or as bridge to NPWT in infected or complex wound beds.
NPWT can be used as a bridge between debridement and definitive reconstruction when the wound and patient are suitable; reassess tissue viability, infection and the recipient bed before coverage. Do not place NPWT foam directly against exposed blood vessels, anastomoses, organs or nerves; when using NPWT around exposed vessels or organs, protect them with tissue or multiple nonadherent dressing layers.[5] After extensive debridement or in an anticoagulated patient, monitor for bleeding; if bleeding occurs, stop suction and inspect the wound to control the source.[5]
For Fournier wound-care context, see Fournier's Gangrene.
5. Skin Grafting
Transfer of epidermis ± dermis without its own blood supply, dependent on revascularization from the recipient wound bed.
| Type | Composition | Take Rate | Contraction | Donor Site |
|---|---|---|---|---|
| Split-thickness (STSG) | Epidermis + partial dermis | Bed- and patient-dependent | More secondary contraction | Usually re-epithelializes from retained dermis/adnexa |
| Full-thickness (FTSG) | Epidermis + full dermis | Requires an adequately vascularized bed | More immediate primary contraction, generally less later secondary contraction | Usually closed primarily for a small donor defect |
Requirements for graft take: A suitable vascularized bed, control of infection and shear, close contact and prevention of hematoma or seroma. A bolster or selected NPWT dressing can help maintain graft-bed contact.[9] In 16 adult randomized trials (411 NPWT, 401 conventional-dressing controls), a 2025 meta-analysis found higher pooled graft take with NPWT, with substantial heterogeneity (I²=85%); GU-specific benefit was not estimated.[21] Plasmatic imbibition, inosculation and neovascularization occur over overlapping early phases rather than a fixed universal 48–72-hour schedule.[9][16]
Common STSG applications in GU reconstruction: Scrotal reconstruction after Fournier's gangrene; penile shaft skin resurfacing; large perineal defects after oncologic resection. For Fournier scrotal defects, a low-quality case-series synthesis supports primary or secondary closure for selected losses of 50% or less, and graft or flap coverage for larger or extra-scrotal defects.[20]
FTSG applications: Small, cosmetically sensitive defects; genital skin replacement where contraction must be minimized (e.g., penile shaft after degloving in children).
6. Dermal Substitutes and Biologic Scaffolds
Acellular dermal matrices (ADMs) and synthetic wound matrices differ in composition, indication and whether and when a second graft is needed. Some provide a scaffold for vascular ingrowth before later skin grafting.
Examples: Integra® (bilayer matrix with silicone layer) and AlloDerm® (human acellular dermis) are different matrix products; Oasis® is an extracellular-matrix wound product, whereas Dermagraft® is a cellularized skin substitute.
Potential advantages: May help prepare selected difficult beds or improve coverage options; donor-site needs and functional benefit depend on the product and procedure.
Limitations: Product-specific staging and timing, cost, infection risk and the need for adequate perfusion.
7. Local Tissue Rearrangement (Local Flaps)
Recruitment of adjacent tissue, maintaining its blood supply, and moving it to fill a nearby defect.
| Type | Mechanism | Example Applications |
|---|---|---|
| Advancement | Tissue advanced in a straight line into defect | V-Y advancement; A-T advancement |
| Rotation | Tissue arc-rotated around a pivot point | Rotation flap for sacral pressure sore |
| Transposition | Adjacent flap pivots into a nearby defect, redistributing tension | Limberg (rhomboid) flap; Z-plasty |
| Interpolation | Tissue moved across intervening normal skin; pedicle divided at second stage | Forehead flap |
Z-plasty uses two triangular flaps that exchange positions along a central limb, reorienting a scar and potentially releasing contracture. A 60° design has a theoretical geometric lengthening of about 75%; actual tissue gain depends on elasticity, tension and scarring.[17]
8. Regional (Pedicled) Flaps
Flaps based on a named axial vascular pedicle, transferred from a nearby region while maintaining pedicle continuity.
Examples relevant to GU reconstruction:
- Gracilis flap. Pedicled muscle with an optional skin paddle; selected perineal, vaginal and scrotal reconstruction, and selected functional transfer
- Rectus abdominis or VRAM (vertical rectus abdominis myocutaneous). Based on inferior epigastric artery; used for pelvic floor, perineal, and vaginal reconstruction after oncologic resection
- Pudendal artery perforator flap. For perineal and vulvar defects
- Singapore flap (fasciocutaneous pudendal thigh flap). Vaginal reconstruction
Potential advantages: No microvascular anastomosis; may be suitable when a reliable regional pedicle reaches the defect. Operative time and reliability vary by flap, patient and team.
Limitation: Pedicle length constrains the arc of rotation, and muscle harvest can cause donor-site morbidity, including functional deficit. In a retrospective series of 546 pelvic VRAM reconstructions, abdominal donor-site hernia occurred in 9.9% and bulge in 6.4%.[15]
9. Perforator Flaps
Flaps based on perforating vessels (cutaneous perforators arising from named deep source vessels), allowing transfer of skin and fat without sacrificing the underlying muscle.
Principle: A skin-and-fat flap can be raised on a selected perforator while preserving underlying muscle. Some perforators traverse muscle and require intramuscular dissection; others run in a septum. Muscle preservation may reduce donor morbidity, but the magnitude depends on the donor and comparison.
Examples: DIEP flap (deep inferior epigastric perforator); ALT flap (anterolateral thigh); SGAP/IGAP flap (gluteal artery perforator)
Trade-off: Technically demanding dissection; longer operative time; learning curve
10. Free Tissue Transfer (Free Flaps)
Microvascular transfer of tissue from a distant site, in which the flap's arterial and venous pedicle is divided and anastomosed to recipient vessels at the defect site under microscope magnification.
Common free flaps in GU/pelvic reconstruction:
- Radial forearm free flap (RFFF). Thin, pliable fasciocutaneous flap; used for neourethroplasty and phalloplasty (sensate variant available via lateral antebrachial cutaneous nerve)
- Anterolateral thigh (ALT). Large, versatile; can be harvested as thin or bulky depending on body habitus; used for large perineal and vaginal defects
- Fibula osteocutaneous. Used in mandibular reconstruction and described for phalloplasty, where the bone component provides penile rigidity[12]
- Gracilis free flap. A thin muscle flap; free transfer as a urinary neosphincter has been studied in human cadavers and dogs, but clinical continence outcomes were not reported.[18]
Outcomes: Flap survival varies by indication, tissue, recipient vessels and center. Comparative data come from a breast TRAM series.[6]
Indications: Prior reconstruction failure; no suitable regional flap available; need for composite tissue (bone and skin); salvage of complex radiation wounds
11. Adjunctive and Regenerative Techniques (Emerging)
The reconstructive ladder continues to evolve with emerging biological and technological adjuncts:[7]
| Technique | Status |
|---|---|
| Tissue engineering / scaffold seeding | Research and small clinical series. Tissue-engineered bladders (7 patients with myelomeningocele) and urethras (5 boys) have been reported.[7][10] In a multicenter phase II trial of a cell-seeded bladder scaffold in 10 children and adolescents with neurogenic bladder from spina bifida, bladder capacity showed no clinical or statistical improvement at 12 or 36 months, compliance improved in 4 of 10 patients at 12 months and 5 of 10 at 36 months without reaching clinical or statistical significance, and serious adverse events (bowel obstruction and/or bladder rupture) occurred in 4 patients, exceeding the study's acceptable safety standard.[11] |
| Cell-based therapies (adipose-derived stem cells, platelet-rich plasma) | Adjunct; evidence evolving |
| Smart biomaterials (growth factor-eluting dressings) | Research |
| Vascularized composite allotransplantation (VCA) | Clinical (hand, face); expanding |
The Reconstructive Elevator Concept
Gottlieb and Krieger proposed the reconstructive elevator as an alternative to climbing each rung in sequence: the surgeon selects the option suited to the defect.[2]
A complex irradiated perineal wound may be best served by a well-vascularized flap such as a pedicled gracilis (rung 8) when its bed is unsuitable for grafting (rung 5); technique and timing depend on defect size, location and radiation injury.[19] Conversely, a clean post-traumatic scrotal defect may heal excellently with secondary intention (rung 1), making anything more complex unnecessary.
Core Principle. The goal is to match the reconstruction to the defect using the simplest reliable solution, not to start at the bottom. Overtreatment carries its own morbidity.
References
1. Mathes SJ, Nahai F. Clinical Applications for Muscle and Musculocutaneous Flaps. St. Louis: Mosby; 1982.
2. Gottlieb LJ, Krieger LM. From the reconstructive ladder to the reconstructive elevator. Plast Reconstr Surg. 1994;93(7):1503–1504. doi:10.1097/00006534-199406000-00027
3. Gurtner GC, Neligan PC, eds. Plastic Surgery. 4th ed. Elsevier; 2017. Chapter 1: Principles of Plastic Surgery.
4. Kopechek KJ, Patel HV, Koch GE. Modern Management of Fournier's Gangrene. Curr Urol Rep. 2025;26(1):47. doi:10.1007/s11934-025-01275-3. PMID 40455358
5. Orgill DP, Bayer LR. Negative pressure wound therapy: Past, present and future. Int Wound J. 2013;10(Suppl 1):15–19. doi:10.1111/iwj.12170. PMID 24251839
6. Serletti JM, Moran SL. Free versus the pedicled TRAM flap: a cost comparison and outcome analysis. Plast Reconstr Surg. 1997;100(6):1418–1424. doi:10.1097/00006534-199711000-00006
7. Atala A, Bauer SB, Soker S, Yoo JJ, Retik AB. Tissue-engineered autologous bladders for patients needing cystoplasty. Lancet. 2006;367(9518):1241–1246. doi:10.1016/s0140-6736(06)68438-9. PMID 16631879
8. Glass GE, Murphy GRF, Nanchahal J. Does negative-pressure wound therapy influence subjacent bacterial growth? A systematic review. J Plast Reconstr Aesthet Surg. 2017;70(8):1028–1037. doi:10.1016/j.bjps.2017.05.027
9. Patino G, Zheng MY, Breyer BN, Cohen AJ. Skin grafting applications in urology. Rev Urol. 2019;21(1):8–14. Full text.
10. Raya-Rivera A, Esquiliano DR, Yoo JJ, et al. Tissue-engineered autologous urethras for patients who need reconstruction: an observational study. Lancet. 2011;377(9772):1175-82. doi:10.1016/S0140-6736(10)62354-9
11. Joseph DB, Borer JG, De Filippo RE, et al. Autologous cell seeded biodegradable scaffold for augmentation cystoplasty: phase II study in children and adolescents with spina bifida. J Urol. 2014;191(5):1389-95. doi:10.1016/j.juro.2013.10.103
12. Sadove RC, McRoberts JW. Total phallic reconstruction with the free fibula osteocutaneous flap. Plast Reconstr Surg. 1992;89(5):1001. doi:10.1097/00006534-199205000-00064
13. Sandberg JM, Warner HL, Flynn KJ, et al. "Favorable outcomes with early component separation, primary closure of necrotizing soft tissue infections of the genitalia (Fournier's gangrene) debridement wound defects." Urology. 2022;166:250-256. doi:10.1016/j.urology.2022.03.042
14. Sam P, Zilavy A, Ice C, Gallegos M. "Primary closure is superior to secondary intention for treating Fournier gangrene." J Urol. 2022;207(Suppl 5):e507. doi:10.1097/JU.0000000000002577.09
15. Asaad M, Mitchell D, Slovacek C, et al. "Surgical outcomes of vertical rectus abdominis myocutaneous flap pelvic reconstruction." Plast Reconstr Surg. 2024;154(5):1105-1114. doi:10.1097/PRS.0000000000011233
16. Milner SM. "Skin Grafting of the Dorsum of the Hand." ePlasty. 2024;24:QA15. PMID 38915731. Full text.
17. Bae DS. "Z-plasties for the Pediatric Orthopaedic Surgeon: Master’s Surgical Technique." J Pediatr Orthop Soc N Am. 2023;5(3). doi:10.55275/JPOSNA-2023-700
18. Perez-Abadia G, Van Aalst VC, Palacio MM, et al. "Gracilis muscle neosphincter for treating urinary incontinence." Microsurgery. 2001;21(6):271–280. doi:10.1002/micr.1051
19. Kurul S, Dinçer M, Kizir A, Uzunismail A, Darendeliler E. "Plastic surgery in irradiated areas: analysis of 200 consecutive cases." Eur J Surg Oncol. 1997;23(1):48–53. doi:10.1016/S0748-7983(97)80142-4
20. European Association of Urology. "EAU Guidelines on Urological Infections." EAU Guidelines Office; 2026. §3.13.5. Guideline.
21. Lee SC, Bayan L, Sato A, et al. "Benefits of negative pressure wound therapy in skin grafts: A systematic review and meta-analysis of randomised controlled trials." J Plast Reconstr Aesthet Surg. 2025;102:204–217. doi:10.1016/j.bjps.2025.01.036