Quilting Stitch
The quilting stitch tacks an overlying flap, skin graft, or mucosal graft to the underlying tissue bed at multiple points, like the stitching of a quilt, to reduce dead space and hold a graft spread against its bed. In reconstructive urology it is used for flap fixation and graft fixation in urethroplasty (buccal mucosa or skin graft).[1][2][3][4]
Graft-bed contact and quiltingOriginal schematic · v2026-09-20 · Clinical review pendingFluid or shear separating a graft from its recipient bed threatens incorporation. Fixation brings the graft into close apposition and limits dead space.View: Generic free-graft interface, conceptual section. Scale: Conceptual schematic; not to scale. Units: No measured geometry; any dimensions are illustrative.Limits: Rat imbibition evidence supports a mechanism, not a human clinical success rate; bed vascularity, infection and graft handling also matter.Source check: 2026-09-20. This is an editorial check with the access limits below. No named clinician has signed off.Fukui et al.: plasmatic imbibition in rat grafts — 1992 animal experiment. Access: abstract checked. Mechanistic graft-bed exchange in a rat musculocutaneous model; clinical graft take is not guaranteed by quilting.Barbagli: bulbar urethroplasty using the dorsal approach — 2003 technical article. Access: abstract checked. Dorsal graft placement on the corporal tunical bed; no survey preference percentage used.WARWIKI original vector schematic; individual illustrator not recorded. No separate figure reuse license recorded; linked sources are concept references, not artwork licenses.Open original SVG with embedded source record ↗
Fluid or shear separating a graft from its recipient bed threatens incorporation. Fixation brings the graft into close apposition and limits dead space. Rat imbibition evidence supports a mechanism, not a human clinical success rate; bed vascularity, infection and graft handling also matter. (Original WARWIKI schematic)
Principles of Graft Survival
Free graft incorporation is commonly described in overlapping, approximate phases; timing varies with the graft and recipient bed:[5][6]
- Plasmatic imbibition (0–48 h). Graft absorbs plasma from recipient bed
- Inosculation (48–72 h). Graft vessels align with recipient bed vessels
- Neovascularization (days 4–7). Capillary ingrowth from recipient bed
- Maturation (weeks to months). Graft remodeling and epithelialization
Why quilting matters:[2][4][7]
- Reduces dead space and the opportunity for fluid to separate graft from bed
- Maintains graft–bed contact needed for early incorporation
- Holds the graft spread and limits folding or retraction ("hanging" the graft)[7]
- Adds fixation points across the graft instead of relying only on the graft edges
Suture Quilting in Urethroplasty
Urethroplasty is the main reconstructive urology application of graft quilting. Several named techniques define how the graft is placed and fixed.
Standard technique
- Graft preparation. Trim to size, remove excess submucosa to improve imbibition
- Apex fixation. Secure proximal and distal apices first
- Edge suturing. Continuous or interrupted sutures along lateral margins
- Quilting sutures. Place fixation sutures through the graft into its recipient bed, such as tunica albuginea in dorsal onlay urethroplasty or pubic periosteum in selected VUAS repair.[3][4][8]
Suture selection
Examples of absorbable sutures for fine graft fixation; choice and size depend on tissue, approach and surgeon preference.
| Material | Size | Application | Advantages |
|---|---|---|---|
| Polyglactin (Vicryl) | 4-0 to 5-0 | Edge and quilting | Braided; good handling; predictable absorption |
| Polydioxanone (PDS) | 5-0 to 6-0 | Spread fixation | Monofilament; longer tensile-strength retention |
| Poliglecaprone (Monocryl) | 5-0 to 6-0 | Delicate quilting | Monofilament; minimal tissue reaction |
Dorsal onlay — Barbagli technique
Urethra mobilized from the corpora cavernosa, opened dorsally, graft quilted to the tunica albuginea.[8][9]
- Quilting sutures pass through the graft, then the tunica albuginea, then back through the graft.
- Urethra rotated back to cover the graft
- Reported success varies with stricture site, case mix, outcome definition and follow-up; systematic reviews do not supply a single technique-specific 88%-at-42-month estimate applicable to all dorsal onlays.[9][10]
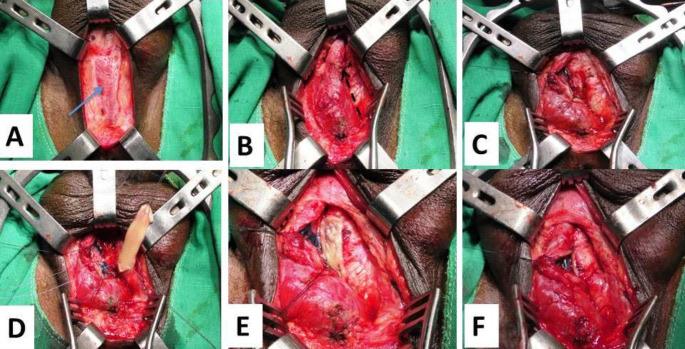
Dorsal onlay buccal mucosal graft urethroplasty. (A) Midline perineal incision exposing the bulbospongiosus muscle (blue arrow). (B) One-sided dissection between the urethra and the left corpus cavernosum (dotted arrow). (C) Dorsal urethrotomy. (D) Proximal anastomosis of the graft to the urethra with three interrupted sutures. (E) Quilting of the graft to the underlying corpora with three rows of sutures. (F) Completed anastomosis of the graft to the urethral edges over a 16 F catheter. From Mousa A, et al. World J Urol. 2025;43(1):87, Fig. 2 (CC BY).[15]
Dorsal inlay — Asopa technique
Urethra opened ventrally, then incised dorsally through the stricture without mobilization; graft quilted into the dorsal defect through the ventral approach.[11][12]
- The urethra is not mobilized.
- In one 47-patient prospective comparison (25 dorsal onlay, 22 dorsal inlay), mean operative time was 128 versus 205 min and mean blood loss 105 versus 228 mL for inlay versus onlay.[12]
- Success was 88% for onlay and 86.4% for inlay in that study, at mean follow-up of 22.6 versus 24.2 months by the authors' no-reintervention and flow criteria.[12]
Ventral onlay
Urethra opened ventrally for a ventral onlay buccal mucosal graft.[13][14] In Mousa and colleagues' series, the ventral graft was sutured to the urethral edges and covered with spongiosum; their dorsal arm used graft quilting.[15]
- Spongioplasty. Corpus spongiosum advanced and closed over the graft
- Pseudospongioplasty. When spongiosum is inadequate distally, periurethral tissue flaps are mobilized over the graft[16]
- In a retrospective series comparing two ventral coverage methods, pseudospongioplasty succeeded in 37/46 (80%) at mean follow-up 41 months versus 47/56 (84%) at mean follow-up 39 months with conventional spongioplasty.[16]
- In a 2025 meta-analysis of eight studies (655 patients), pooled stricture success did not differ significantly between ventral and dorsal onlay (RR 1.00, 95% CI 0.94–1.06), while transient erectile dysfunction was less frequent in ventral groups (RR 0.24, 95% CI 0.08–0.67).[13] In a retrospective comparison of sexually active men with primary nontraumatic proximal bulbar strictures, erectile dysfunction at 3 months occurred in 5% after ventral versus 25% after dorsal onlay (60 versus 73 men), and at 12 months in 1.7% versus 13.7%.[15] Overall success was similar (91.7% versus 90.4%).[15] The center switched from dorsal to ventral during the study period, so chronology and other confounding limit causal inference.[15]
Double graft — Palminteri technique
For tight bulbar strictures with a preserved but narrow urethral plate, dorsal inlay and ventral onlay grafts widen the lumen.[4][17]
- Urethra opened ventrally
- Dorsal urethra incised in midline to create raw area on tunica albuginea
- First graft quilted dorsally (dorsal inlay) to corpora
- Suture the ventral onlay graft to both urethral margins, then fix the spongiosum to the graft with a few inverted quilting stitches.[4]
- Spongiosum closed over ventral graft
In the two Palminteri series, success was 43/48 (89.6%) at mean 22 months (range 13–59) and 64/73 (88%) at mean 48.9 months; the latter was a buccal-graft subgroup with at least one year of follow-up among 105 operated men.[4][17] Success was defined as normal voiding without any postoperative procedure.[4][17]
Transurethral quilting — fossa navicularis
Sterling and colleagues described the transurethral ventral inlay and quilting maneuver below; Farrell and colleagues reported a separate transurethral dorsal inlay for fossa navicularis strictures.[1][18]
- Transurethral ventral urethrotomy to excise cicatrix
- Double-arm 6-0 PDS delivers triangular BMG to the proximal urethrotomy
- Graft secured to meatus with 5-0 polyglactin
- Additional 6-0 double-arm PDS sutures quilt the graft for spread fixation
- 16 Fr silicone catheter
In a 44-patient retrospective series with at least one year of follow-up, 95% were patent without further intervention at mean follow-up 36 months (IQR 22–50).[1]
Quilting to periosteum — VUAS repair
For vesicourethral anastomotic stricture after radical prostatectomy, the graft can be quilted to the pubic bone periosteum.[3]
- Dorsal BMG sutured to bladder neck at 11, 12, and 1 o'clock
- Interrupted dorsal quilting through periosteum over pubic bone using 4-0 Vicryl
- Graft sutured to urethra in continuous fashion
- In the reported four-patient series, all were patent at 3 months, but all remained incontinent.[3]
Fibrin Glue Fixation
Fibrin sealants combine fibrinogen and thrombin to form an adherent clot and have been used to supplement or partly replace suture quilting in small urethroplasty series.[19][20][21] The penile-glue series below used a cyanoacrylate adhesive, not fibrin glue.[22]
Avoiding central quilting sutures may simplify graft fixation.
Dorsal onlay BMG with fibrin glue (Barbagli)
- Urethra mobilized and opened dorsally
- 2 mL fibrin glue applied to corpora cavernosa (recipient bed)[19]
- BMG placed on glue bed
- Only 2 interrupted 5-0 polyglactin sutures fix graft apices to tunica albuginea
- Additional fibrin glue injected over urethra after rotation
In this six-patient series, mean operative time was 100 min and no anastomotic restrictures were detected at the reported 6- and 12-month assessments. Mean follow-up was 16 months (range 12–24); there was no suture-only comparison group.[19]
One-stage penile urethroplasty with cyanoacrylate glue
Barbagli and colleagues used Glubran 2 (N-butyl-2-cyanoacrylate/methacryloxy sulfolane), a different adhesive from fibrin sealant, to fix an oral graft without central quilting sutures:[22]
- Median operative time: 60 min
- Success was 85.7% (12/14) at median follow-up 16 months (IQR 12–32), in an uncontrolled retrospective series[22]
- No fistula or sacculation on the 2-week VCUG; three intraoperative tunica injuries and one postoperative UTI were reported
- No patient complained of chordee or sexual dysfunction in this small series
Experimental — fibrin glue + MSCs
In a 36-rabbit urethral injury study, fibrin glue alone and glue with autologous marrow mesenchymal stem cells both increased vessel density versus untreated injury; only the combination increased periurethral smooth-muscle thickness versus glue alone, and two untreated controls developed fistulae versus none in either treated group at days 10 or 30.[23] No human data exist.
Barbed Sutures
Unidirectional or bidirectional barbs grip tissue, allowing knotless fixation and helping retain applied tension.[24][25][26]
Vesicourethral anastomosis
This is the best-studied urologic application. A meta-analysis of three randomized trials and six observational studies (786 patients) found:[25]
- Anastomosis time was shorter by a weighted mean 3.98 min (p = 0.0001).[25]
- Operative time was shorter by 10.06 min (p = 0.0003).
- In four studies with cystography 5–12 days after RARP, pooled contrast extravasation did not differ significantly between barbed and conventional sutures (7.08% versus 3.37%; OR 2.17, 95% CI 0.86–5.50).[25] An included 81-patient randomized trial found day-8 extravasation in 9/45 (20.0%) barbed-suture versus 1/36 (2.8%) polyglactin repairs (p = 0.019); in its barbed arm, 8/29 cases leaked before and 1/16 after the surgeon modified the technique to avoid overtightening.[42]
- Continence rates did not differ significantly at 4–6 weeks, 3 months and 6–12 months.
In a single-surgeon randomized trial of 70 RARP cases (Zorn), reconstruction time was 13.1 min with barbed suture versus 20.8 min with monofilament, the need to readjust tension or add clips for watertight closure was 6% versus 24% (p = 0.03), and cost was CAN$48 versus CAN$70 per case.[24] Pad-free continence at 1, 3 and 6 months was similar.[24] A 64-patient randomized trial found a 26% shorter anastomosis time with barbed suture and equivalent 6-week functional outcomes.[28] A prospective cohort of 80 patients found urethral stenosis in 2.5% of each arm and 12-month continence of 97.5% with barbed suture versus 95% with interrupted polyglactin (no significant difference); its authors described the barbed technique as economical.[27] In a 100-patient comparison, barbed suture alone (without rhabdosphincter reconstruction) was associated with better immediate continence (76% versus 40%) and one-month continence (92% versus 76%) than poliglecaprone with rhabdosphincter reconstruction; three-month continence was similar (96% versus 94%).[29]
Barbed sutures for graft quilting
Graft-specific clinical benefit is unestablished.[26] Schardein and colleagues described knotless barbed-suture graft fixation with an improvised hollow needle in 13 mixed reconstructive cases.[41]
Staged Urethroplasty
First stage — graft inlay and maturation
Graft quilted to recipient bed and left to mature before tubularization.[30][31][32][33]
- Stricture excised or urethra opened ventrally
- Graft quilted to urethral bed / corporal bodies
- Lateral edges sutured to skin margins (marsupialization)
- Maturation: approximately 6–9 months before second-stage surgery (BMG)[31] or 8–12 weeks (mesh graft)[30]
In one nonrandomized comparison, triangular extension at the proximal and/or distal stoma was associated with fewer first-stage stomal revisions (0/23 versus 5/24 controls) and higher mean maximum flow after the second stage (21.5 versus 15.8 mL/s, p = 0.027). Both groups had 19/20 (95%) success among those reaching second-stage surgery, defined as 17-Fr cystoscope passage at 6 months after that stage without additional surgery or dilation.[34]
Second stage — tubularization
- Urethral plate mobilized from surrounding skin
- Plate rolled into tube over catheter
- Multi-layer closure (mucosa, dartos, skin)
- Additional graft inlay if needed
Long-term outcomes. In a 49-patient staged-repair series, long-term functional success among patients with at least 12 months of follow-up was 96.4% with BMG alone and 53% with any first-stage split-thickness skin graft; median follow-up in the cohort was 57 months.[33] All recurrences occurred after the 4-month cystoscopy, at a median of 78 months.[33]
Skin Graft Fixation
Tie-over bolster
Traditional method for irregular surfaces.[35][36][37][38]
- Graft sutured to wound edges with long suture tails
- Bolster material (gauze, foam, proflavine-soaked gauze) placed over graft
- Suture tails tied over the bolster to compress graft to bed
TODGA (Tie-Over Dressing for Graft Application, distal penectomy or glans resurfacing): in the authors' standardized 29-operation phase, a proflavine-soaked gauze bolster was left for 10 days and patients could mobilize immediately; one patient required re-grafting.[38] Modified extra-wound fixation variants aim to limit graft-edge trauma during dressing take-down.[39]
Negative pressure wound therapy (NPWT)
In a randomized trial of 86 skin-graft recipients (43 per arm), NPWT improved graft take at postoperative days 5–7 versus tie-over bolster, particularly at irregular or high-mobility sites.[36] A 2024 network meta-analysis of 27 adult skin-graft studies (1,937 patients) also found higher graft-take percentages with NPWT than with other fixation methods.[43]
- Overall graft take: 97.2% (NPWT) versus 90.2% (tie-over), p = 0.005[36]
- Irregular or high-mobility areas: 97.6% versus 81.7%, p < 0.001[36]
Eggcrate foam bolster — penile/genital reconstruction
A structured alternative for high-risk genital reconstruction:[40]
- Bacitracin on nonadherent dressing
- Saline-moistened silver dressing
- Gauze layer
- Eggcrate foam (spikes toward wound)
- Penis extended; cylindrical bolster placed and stapled
In a retrospective series of 21 men (median follow-up 50 days), median graft take was 100% through POD 14 and 95% at days 15–30; 95% had at least one impaired wound-healing risk factor.[40]
Flap Quilting — Scrotal and Perineal Reconstruction
Distinct from graft quilting but using a related mechanical principle, selected deep fixation can reduce flap–bed dead space and shear. The applicability and outcome benefit depend on flap design and recipient bed.
Technique. After flap inset, selected buried fixation sutures can attach its deep surface to suitable fascia or a recipient bed where dead space remains. An interrupted or running pattern and spacing and material should be adapted to flap thickness, perfusion, tissue strength and local protocol.
Uses:
- Scrotal reconstruction after Fournier debridement. Flaps and split-thickness skin grafts are options; Lucas and colleagues describe scrotal skin graft fixation with fibrin sealant, graft-edge sutures, and limited quilting.[45]
- Perineal reconstruction with local advancement flaps
- Phalloplasty urethral lengthening. In a reported pars-fixa technique, quilting and running sutures secure a labia-minora ring flap to align the tissue and address hematoma risk.[44]
- Abdominal wall reconstruction adjacent to complex urologic cases
- Groin / inguinal skin reconstruction where dead-space seroma is a known complication
Rationale: reduce dead space and shear at the flap–bed interface. These graft-fixation references give no quantified seroma benefit or basis to omit drains for scrotal or perineal flaps; drainage and perfusion decisions depend on the procedure.
Technical Pearls
- Trim excess submucosa to improve imbibition
- Fenestrate graft if seroma risk is high
- Keep graft moist during preparation
- Ensure adequate hemostasis
- Create a well-vascularized bed
- Excise obstructing scar as required for the planned reconstruction while preserving viable support and perfusion
- "Hanging" sutures. Anchor graft to surrounding tissue to prevent folding/retraction[7]
- Spread fixation. Multiple quilting sutures distribute graft evenly[1]
- Avoid excessive tension. Prevents graft ischemia
- Mattress sutures can be useful for selected tissue geometry, but avoid excess pressure
- Improvised hollow-needle quilting. Schardein and colleagues threaded absorbable 4-0 barbed suture through a 20-gauge hollow needle for BMG quilting in deep reconstructive fields, including posterior urethroplasty, transvesical bladder-neck reconstruction, and augmented perineal urethrostomy; their 13-patient mixed-procedure series reported graft survival at mean 46-week follow-up.[41]
- Catheter drainage 1–3 weeks depending on procedure
- Avoid pressure on graft site
- Monitor for hematoma or seroma
Summary — method selection
| Method | Best applications | Notes |
|---|---|---|
| Suture quilting | Selected urethroplasty grafts (Barbagli, Asopa, Palminteri); selected flap fixation | Direct spread fixation; tailor bite depth and spacing |
| Fibrin glue | Reported for dorsal onlay BMG | Small series; may pair with limited sutures; comparative benefit unproved |
| Cyanoacrylate glue | Reported for one-stage penile oral-mucosal graft inlay | Different chemistry from fibrin; uncontrolled 14-patient series |
| Barbed suture | Robotic VUA; hollow-needle graft quilting reported in 13 reconstructive cases | Uncontrolled mixed-procedure series: all grafts survived at mean 46-week follow-up[41] |
| Tie-over bolster (incl. TODGA) | Penile skin grafts; glans resurfacing | External compression |
| NPWT | Selected complex or irregular/high-mobility skin-graft wounds | Early take benefit in one 86-patient RCT versus tie-over |
| Eggcrate foam | Penile/genital reconstruction in a small series | Structured non-NPWT bolster; no direct comparison with NPWT |
See Also
- Grafts in GU Reconstruction
- Buccal Mucosa Graft
- Flaps in GU Reconstruction
- Barbed Sutures
- Fibrin Sealants
References
1. Sterling J, Daneshvar M, Nikolavsky D. "Transurethral Ventral Inlay Buccal Mucosa Graft Urethroplasty: Technique and Intermediate Outcomes." BJU Int. 2023;132(1):109-111. doi:10.1111/bju.16007
2. Gelman J, Siegel JA. "Ventral and Dorsal Buccal Grafting for 1-Stage Repair of Complex Anterior Urethral Strictures." Urology. 2014;83(6):1418-22. doi:10.1016/j.urology.2014.01.024
3. Shahrour W, Hodhod A, Kotb A, Prowse O, Elmansy H. "Dorsal Buccal Mucosal Graft Urethroplasty for Vesico-Urethral Anastomotic Stricture Postradical Prostatectomy." Urology. 2019;130:210. doi:10.1016/j.urology.2019.04.022
4. Palminteri E, Manzoni G, Berdondini E, et al. "Combined Dorsal Plus Ventral Double Buccal Mucosa Graft in Bulbar Urethral Reconstruction." Eur Urol. 2008;53(1):81-9. doi:10.1016/j.eururo.2007.05.033
5. Fukui A, Maeda M, Tamai S, Inada Y. "Proof of Plasmatic Imbibition in Rat Musculocutaneous Grafts: Enzymatic Proof Using Peroxidase." Plast Reconstr Surg. 1992;89(3):530-4. doi:10.1097/00006534-199203000-00022
6. El-Sherbiny MT, Abol-Enein H, Dawaba MS, Ghoneim MA. "Treatment of Urethral Defects: Skin, Buccal or Bladder Mucosa, Tube or Patch? An Experimental Study in Dogs." J Urol. 2002;167(5):2225-8. doi:10.1016/s0022-5347(05)65133-6
7. Djordjevic ML, Kojovic V, Bizic M, et al. "'Hanging' of the Buccal Mucosal Graft for Urethral Stricture Repair After Failed Hypospadias." J Urol. 2011;185(6 Suppl):2479-82. doi:10.1016/j.juro.2011.01.036
8. Barbagli G, Palminteri E, Rizzo M. "Dorsal Onlay Graft Urethroplasty Using Penile Skin or Buccal Mucosa in Adult Bulbourethral Strictures." J Urol. 1998;160(4):1307-9. doi:10.1016/s0022-5347(01)62522-9
9. Barratt R, Chan G, La Rocca R, et al. "Free Graft Augmentation Urethroplasty for Bulbar Urethral Strictures: Which Technique Is Best? A Systematic Review." Eur Urol. 2021;80(1):57-68. doi:10.1016/j.eururo.2021.03.026
10. Mangera A, Patterson JM, Chapple CR. "A Systematic Review of Graft Augmentation Urethroplasty Techniques for the Treatment of Anterior Urethral Strictures." Eur Urol. 2011;59(5):797-814. doi:10.1016/j.eururo.2011.02.010
11. Pisapati VL, Paturi S, Bethu S, et al. "Dorsal Buccal Mucosal Graft Urethroplasty for Anterior Urethral Stricture by Asopa Technique." Eur Urol. 2009;56(1):201-5. doi:10.1016/j.eururo.2008.06.002
12. Aldaqadossi H, El Gamal S, El-Nadey M, et al. "Dorsal Onlay (Barbagli Technique) Versus Dorsal Inlay (Asopa Technique) Buccal Mucosal Graft Urethroplasty for Anterior Urethral Stricture: A Prospective Randomized Study." Int J Urol. 2014;21(2):185-8. doi:10.1111/iju.12235
13. Hassan AA, Soliman AM, Shouman HA, et al. "Dorsal- Vs Ventral-Onlay Buccal Mucosal Graft Urethroplasty for Urethral Strictures: A Meta-Analysis." BJU Int. 2025;136(3):385-394. doi:10.1111/bju.16811
14. Vasudeva P, Nanda B, Kumar A, et al. "Dorsal Versus Ventral Onlay Buccal Mucosal Graft Urethroplasty for Long-Segment Bulbar Urethral Stricture: A Prospective Randomized Study." Int J Urol. 2015;22(10):967-71. doi:10.1111/iju.12859
15. Mousa A, Eissa A, Raheem AA, Zoeir A. "Ventral Versus Dorsal Onlay Buccal Mucosal Graft Urethroplasty for Non-Traumatic Proximal Bulbar Urethral Strictures in Sexually Active Men: Erectile and Urinary Functions." World J Urol. 2025;43(1):87. doi:10.1007/s00345-025-05441-7
16. Cordon BH, Zhao LC, Scott JF, Armenakas NA, Morey AF. "Pseudospongioplasty Using Periurethral Vascularized Tissue to Support Ventral Buccal Mucosa Grafts in the Distal Urethra." J Urol. 2014;192(3):804-7. doi:10.1016/j.juro.2014.03.003
17. Palminteri E, Berdondini E, Shokeir AA, et al. "Two-Sided Bulbar Urethroplasty Using Dorsal Plus Ventral Oral Graft: Urinary and Sexual Outcomes of a New Technique." J Urol. 2011;185(5):1766-71. doi:10.1016/j.juro.2010.12.103
18. Farrell MR, Campbell JG, Zhang L, Nowicki S, Vanni AJ. "Transurethral Reconstruction of Fossa Navicularis Strictures With Dorsal Inlay Buccal Mucosa Graft Urethroplasty." World J Urol. 2022;40(6):1523-1528. doi:10.1007/s00345-022-03994-5
19. Barbagli G, De Stefani S, Sighinolfi MC, et al. "Bulbar Urethroplasty With Dorsal Onlay Buccal Mucosal Graft and Fibrin Glue." Eur Urol. 2006;50(3):467-74. doi:10.1016/j.eururo.2006.05.018
20. Barbagli G, De Stefani S, Sighinolfi MC, et al. "Experience With Fibrin Glue in Bulbar Urethral Reconstruction Using Dorsal Buccal Mucosa Graft." Urology. 2006;67(4):830-2. doi:10.1016/j.urology.2005.10.033
21. Evans LA, Morey AF. "Hemostatic Agents and Tissue Glues in Urologic Injuries and Wound Healing." Urol Clin North Am. 2006;33(1):1-12, v. doi:10.1016/j.ucl.2005.10.004
22. Barbagli G, Pellegrini G, Corradini F, et al. "One-Stage Penile Urethroplasty Using Oral Mucosal Graft and Glue." Eur Urol. 2016;70(6):1069-1075. doi:10.1016/j.eururo.2016.04.025
23. Wang K, Guan Y, Liu Y, et al. "Fibrin Glue With Autogenic Bone Marrow Mesenchymal Stem Cells for Urethral Injury Repair in Rabbit Model." Tissue Eng Part A. 2012;18(23-24):2507-17. doi:10.1089/ten.TEA.2011.0359
24. Zorn KC, Trinh QD, Jeldres C, et al. "Prospective Randomized Trial of Barbed Polyglyconate Suture to Facilitate Vesico-Urethral Anastomosis During Robot-Assisted Radical Prostatectomy: Time Reduction and Cost Benefit." BJU Int. 2012;109(10):1526-32. doi:10.1111/j.1464-410X.2011.10763.x
25. Li H, Liu C, Zhang H, et al. "The Use of Unidirectional Barbed Suture for Urethrovesical Anastomosis During Robot-Assisted Radical Prostatectomy: A Systematic Review and Meta-Analysis of Efficacy and Safety." PLoS One. 2015;10(7):e0131167. doi:10.1371/journal.pone.0131167
26. Weld KJ, Ames CD, Hruby G, Humphrey PA, Landman J. "Evaluation of a Novel Knotless Self-Anchoring Suture Material for Urinary Tract Reconstruction." Urology. 2006;67(6):1133-7. doi:10.1016/j.urology.2005.12.022
27. Massoud W, Thanigasalam R, El Hajj A, et al. "Does the Use of a Barbed Polyglyconate Absorbable Suture Have an Impact on Urethral Anastomosis Time, Urethral Stenosis Rates, and Cost Effectiveness During Robot-Assisted Radical Prostatectomy?" Urology. 2013;82(1):90-4. doi:10.1016/j.urology.2013.02.002
28. Sammon J, Kim TK, Trinh QD, et al. "Anastomosis During Robot-Assisted Radical Prostatectomy: Randomized Controlled Trial Comparing Barbed and Standard Monofilament Suture." Urology. 2011;78(3):572-9. doi:10.1016/j.urology.2011.03.069
29. Cakici OU, Canda AE. "Bidirectional Barbed Only vs Poliglecaprone Suture With Rhabdosphincter Reconstruction for Urethrovesical Anastomosis During Robotic Radical Prostatectomy: Does It Make Any Difference?" J Endourol. 2018;32(10):944-949. doi:10.1089/end.2018.0386
30. Reichert M, Aragona M, Soukkar A, Olianas R. "Mesh Graft Urethroplasty—Still a Safe and Promising Technique in Mostly Unpromising Complex Urethral Strictures." J Clin Med. 2022;11(20):5989. doi:10.3390/jcm11205989
31. Figler BD, Gomella A, Hubbard L. "Staged Urethroplasty for Penile Urethral Strictures From Lichen Sclerosus and Failed Hypospadias Repair." Urology. 2018;112:222-224. doi:10.1016/j.urology.2017.10.020
32. Palminteri E, Lazzeri M, Guazzoni G, Turini D, Barbagli G. "New 2-Stage Buccal Mucosal Graft Urethroplasty." J Urol. 2002;167(1):130-2. doi:10.1016/s0022-5347(05)65397-9
33. Furr JR, Wisenbaugh ES, Gelman J. "Long-Term Outcomes for 2-Stage Urethroplasty: An Analysis of Risk Factors for Urethral Stricture Recurrence." World J Urol. 2021;39(10):3903-3911. doi:10.1007/s00345-021-03676-8
34. Azuma R, Horiguchi A, Ojima K, et al. "Triangular Extension of Hinge Flaps: A Novel Technique to Resolve Stomal Stenosis and Prevent Restenosis in Staged Buccal Mucosal Urethroplasty." Int J Urol. 2021;28(8):806-811. doi:10.1111/iju.14582
35. Patel BJ, Asher CM, Bystrzonowski N, Healy C. "Safeguarding Skin Grafts: An Evidence-Based Summary of Fixation Techniques." Ann Plast Surg. 2021;87(6):e180-e188. doi:10.1097/SAP.0000000000002937
36. Cao X, Hu Z, Zhang Y, et al. "Negative-Pressure Wound Therapy Improves Take Rate of Skin Graft in Irregular, High-Mobility Areas: A Randomized Controlled Trial." Plast Reconstr Surg. 2022;150(6):1341-1349. doi:10.1097/PRS.0000000000009704
37. Marsidi N, Boteva K, Vermeulen SAM, van Kester MS, Genders RE. "To Tie or Not to Tie-Over Full-Thickness Skin Grafts in Dermatologic Surgery: A Systematic Review of the Literature." Dermatol Surg. 2021;47(1):18-22. doi:10.1097/DSS.0000000000002549
38. Malone PR, Thomas JS, Blick C. "A Tie-Over Dressing for Graft Application in Distal Penectomy and Glans Resurfacing: The TODGA Technique." BJU Int. 2011;107(5):836-840. doi:10.1111/j.1464-410X.2010.09576.x
39. Liu Q, Liu X, Ho IH, Guan S. "Extra-Wound Fixation: A Modified Tie-Over Dressing Technique for Skin Graft." J Wound Care. 2020;29(Sup12):S23-S27. doi:10.12968/jowc.2020.29.Sup12.S23
40. Richards P, Yadav K, Coakes C, et al. "Rook to the Rescue: A Case Series on the Novel Use of Eggcrate Foam Bolsters for Skin Grafts in Penile and Genital Reconstruction." Ann Plast Surg. 2026;96(Suppl 5):S303-S312. doi:10.1097/SAP.0000000000004649
41. Schardein J, Scott KA, Bratslavsky G, Blakley S, Nikolavsky D. "A Surgical 'Sewing Machine' for Rapid Graft Quilting and Suturing in Challenging Spaces." Urol Video J. 2020;6:100027. doi:10.1016/j.urolvj.2020.100027
42. Williams SB, Alemozaffar M, Lei Y, et al. "Randomized Controlled Trial of Barbed Polyglyconate Versus Polyglactin Suture for Robot-Assisted Laparoscopic Prostatectomy Anastomosis: Technique and Outcomes." Eur Urol. 2010;58(6):875-881. doi:10.1016/j.eururo.2010.07.021
43. Seretis K, Bounas N. "Securing Skin Grafts: A Network Meta-Analysis." J Plast Reconstr Aesthet Surg. 2024;96:146-157. doi:10.1016/j.bjps.2024.07.005
44. Wang E, Cleff B, Basta A, et al. "Flap Choice in Gender Affirming Phalloplasty Affects Postoperative Complication Rates." Microsurgery. 2026;46(1):e70154. doi:10.1002/micr.70154
45. Lucas JW, Lester KM, Chen A, Simhan J. "Scrotal Reconstruction and Testicular Prosthetics." Transl Androl Urol. 2017;6(4):710-721. doi:10.21037/tau.2017.07.06