Bovine-Derived Grafts (Pericardium & Dermis)
Bovine pericardium and bovine dermis are different xenograft materials.
The reviewed Peri-Guard instructions describe a glutaraldehyde-crosslinked bovine pericardial patch for specified cardiovascular and thoracic repairs; they do not list Peyronie's grafting, urethroplasty or bladder augmentation as indications. The published urologic uses are outside those labeled indications. The US FDA's April 2019 stop-sale order for transvaginal POP devices included Xenform, a bovine-derived graft, as well as synthetic products.[1][2]
Material and handling
The reviewed Peri-Guard IFU describes tissue stored wet in a water/propylene-oxide solution, with glutaraldehyde processing and subsequent sterilization. It requires immersion and agitation in 500 mL of sterile normal saline for at least three minutes before use; do not pour the storage solution into the rinse basin, and keep the patch immersed in sterile saline until ready for use and moist at all times. Bovine-material hypersensitivity is a contraindication; reuse and resterilization are prohibited. Fibrosis, inflammation and calcification remain possible despite processing.[1]
Products named in the urologic literature include Peri-Guard and Veritas (bovine pericardium; Synovis/Baxter) and Xenform (non-crosslinked bovine dermis; Boston Scientific). Peri-Guard is described as glutaraldehyde-fixed and Xenform as non-crosslinked.[1][5] Glutaraldehyde fixation delays immune rejection but compromises regenerative potential, whereas unfixed scaffolds that keep native matrix architecture allow host-cell repopulation. In a rabbit implantation study, both SDS decellularization and glutaraldehyde fixation disrupted matrix architecture and provoked foreign-body response with fibrotic encapsulation, and an experimental amidosulfobetaine-14 (ASB-14) process that removed hydrophilic and lipophilic antigens avoided it. That process is investigational.[11] Fixed grafts are generally chosen for load-bearing use and unfixed grafts for remodeling.
Crosslinking changes durability and remodeling, but neither “crosslinked” nor “non-crosslinked” guarantees incorporation, freedom from infection or preservation of organ function. Use the actual package IFU and confirm its indication, preparation and fixation requirements. Historical papers may describe preparations differently from currently distributed products.
Peyronie's disease
Bovine pericardium is one of several materials used in tunical lengthening procedures. Current EAU guidance does not identify one graft material as best. Patient selection, baseline erectile function, the deformity and the operative technique determine the tradeoff between straightening and risks such as erectile dysfunction, recurrent curvature, sensory change and shortening. See the Peyronie's surgical atlas for procedure selection.[3]
In a rat model of tunica albuginea substitution, cadaveric pericardium, dermis, vein and Gore-Tex all preserved erectile function on nerve stimulation. Fibrosis was minimal with dermal and vein grafts, moderate to severe with Gore-Tex, and moderate at 4 months but minimal at 6 months with pericardium.[12] These are cadaveric human tissues in rats.[12]
Clinical cohorts:
| Source | What was observed | Population and co-interventions |
|---|---|---|
| Romero Otero et al., prospective single-surgeon series: 43 treated, 41 followed; mean 14 months | Complete straightening in 33/41 (80.5%); 31/41 reported intercourse without further ED treatment; 35/41 would choose surgery again. One glans ischemic event, one edema event and two sensory-loss events occurred. | The cohort was highly selected: age under 55, good baseline erectile function and limited vascular risk. Plaque excision, occasional plication and postoperative rehabilitation accompanied the graft.[4] |
| Caraceni et al., Xenform series: 28 treated, 16 assessed at one year or longer | Complete straightening in 75% of those assessed; ED in 25% and reduced glans sensitivity in 43.8%; one hematoma required surgical revision. | The outcomes are not based on all 28 treated patients.[5] |
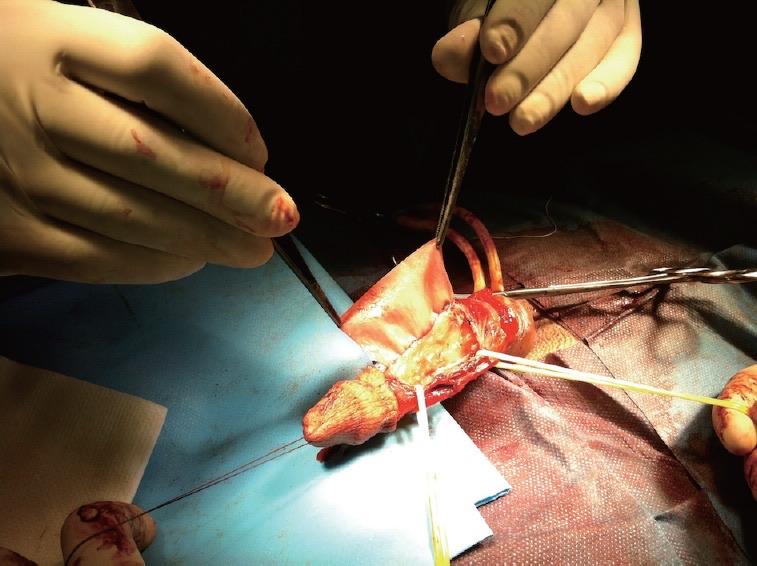
Lyophilized bovine pericardium patch sutured to the penis with absorbable suture to repair the tunical defect in Peyronie's surgery. From Romero Otero J, et al. Asian J Androl. 2017;19(3):316-320, Figure 5 (CC BY-NC-SA).[4]
A 21-man retrospective series used an H-shaped incision with a bovine pericardial graft for curvature above 60° in men without preoperative erectile dysfunction. At 1 year, curvature fell from a median 70° to 5° (p < 0.001); penile Doppler resistive index and erection hardness score showed no statistically significant change, and patient satisfaction was high.[13] Satisfaction correlated with the size of the intraoperative defect and inversely with residual curvature.[13] A retrospective comparison of 18 bovine pericardium and 15 testicular tunica vaginalis grafts (33 men, 30 months) found similar curvature correction, IIEF-5 and length change.[14] A 2024 systematic review found that buccal mucosa had the highest straightening rates and the least de novo erectile dysfunction, that TachoSil performed best when preoperative curvature was considered, and that most studies were single-arm with high risk of bias. Randomized comparisons are needed.[15]
Differences in populations, operations, outcome definitions and follow-up preclude ranking bovine pericardium against oral mucosa, porcine matrices or collagen patches.[3]
Pelvic organ prolapse and continence surgery
Transvaginal POP repair requires separate regulatory and clinical interpretation. Xenform is not a currently authorized US transvaginal POP option. The FDA's subsequent review of its completed postmarket study continued to find an unfavorable benefit–risk profile for transvaginal POP use.[2]
-
A 94-patient randomized anterior-repair trial found no statistically significant improvement from bovine collagen reinforcement; 72 patients were assessed at one year and 59 at two years.[6]
-
The 2022 Xenform study was nonrandomized, comparing 228 graft patients with 485 native-tissue repairs using propensity adjustment. At 36 months, reported composite success was 83.6% versus 80.5%. The specified noninferiority result provides no superiority finding and leaves the FDA's regulatory conclusion unchanged. Serious adverse events were reported in 12/228 versus 13/485, and exposure in 2/228 graft patients.[7]
-
The six-year PROSPECT follow-up found no symptom benefit from adding biological graft to primary vaginal wall repair. It studied a group of biological materials; 65% returned six-year questionnaires and there was no examination at that follow-up. The 2023 analysis included 1,348 women.[8]
-
The 2024 Cochrane review of transvaginal repair (51 trials, 7,846 women) found no difference between biological graft and native tissue repair in awareness of prolapse, repeat surgery or recurrence on examination. It concluded that data do not support biological grafts for transvaginal prolapse repair.[20] A 2024 narrative review found modest evidence for anterior-wall augmentation with biologic grafts and called for trials in recurrent prolapse.[21]
For sacrocolpopexy, published bovine-specific data are sparse. In the Deprest series of porcine SIS and dermis xenografts (50) vs polypropylene (100), 104/150 had anatomical evaluation at a mean follow-up of about 33 months; vault failure was more frequent with xenografts (21% vs 3%), and all six reoperations for prolapse occurred in that group.[22]
Porcine dermis/SIS sling and human cadaveric pericardium studies concern other graft materials. See Porcine Acellular Collagen Matrix and Autologous Rectus Fascia for those separate materials.
Urethral and bladder reconstruction
The AUA 2023 guideline states, as Expert Opinion, that surgeons should not perform substitution urethroplasty with allograft, xenograft or synthetic materials except under experimental protocols.[16] EAU guidance favors oral mucosa when available and advises against cell-free tissue-engineered grafts in extensive spongiofibrosis, after failed urethroplasty or for strictures longer than 4 cm; this is a weak recommendation.[9]
One canine urethral-patch experiment reported fistulas in 24/30 animals.[10] Bladder studies are animal experiments and case reports, and the results depend on preparation:
| Study | Model | Material | Outcome |
|---|---|---|---|
| Kambic 1992 | 10 dogs, 50% partial cystectomy: 8 ethanol-stored grafts and 2 controls | Biodegradable acetylated bovine pericardium; controls had primary closure or a fresh chemically treated patch | Adequate capacity on urodynamics for up to 36 months. The inner surface was epithelialized, but the bladder apex lacked a smooth-muscle layer. The graft acted as an epithelial template while it was gradually resorbed.[17] |
| Portis 2000 | 31 minipigs: 25 grafted, 6 controls | Bovine pericardium (6) versus porcine acellular matrix (6), human placental membrane (6) and porcine SIS (7) | All bovine pericardium grafts failed to incorporate. The other three graft types remained in place and had larger bladder capacity than baseline at 12 weeks; mucosal coverage at six weeks was reported for acellular matrix and SIS.[18] |
| Chee 2015 | Two cases in previously irradiated pelvises | Bovine pericardium in one, ileum in the other | Bladder defects were closed successfully in both.[19] |
Small bladder-repair reports and regenerative experiments remain insufficient to support routine bovine-graft augmentation.
See also: Porcine SIS, Decellularized ECM, and Polypropylene Mesh.
Videos
References
1. Baxter. Peri-Guard Repair Patch: instructions for use. MS0742145B, August 3, 2021; English section of the manufacturer-hosted document. IFU.
2. US Food and Drug Administration. FDA's activities: urogynecologic surgical mesh. April 2019 action and subsequent completed postmarket-study assessments. FDA.
3. European Association of Urology. Guidelines on Sexual and Reproductive Health, Limited Update March 2026, section 8.2.3.b (surgical treatment of Peyronie's disease). Guideline.
4. Romero Otero J, García Gómez B, Medina Polo J, et al. Use of a lyophilized bovine pericardium graft to repair tunical defect in patients with Peyronie's disease: experience in a clinical setting. Asian J Androl. 2017;19:316–320. doi:10.4103/1008-682X.171572.
5. Caraceni E, Leone L, Utizi L, Marronaro A. Use of a non-cross-linked xenograft (Xenform) in surgical treatment of Peyronie's disease. Urology. 2016;95:103–107. doi:10.1016/j.urology.2016.05.040.
6. Guerette NL, Peterson TV, Aguirre OA, et al. Anterior repair with or without collagen matrix reinforcement: a randomized controlled trial. Obstet Gynecol. 2009;114:59–65. doi:10.1097/AOG.0b013e3181a81b41.
7. Lipetskaia L, Gonzalez RR, Wu JM, et al. Thirty-six-month prospective study of transvaginal bovine graft vs native tissue repair for the treatment of pelvic organ prolapse. Urology. 2022;167:234–240. doi:10.1016/j.urology.2022.06.003.
8. Reid F, Aucott L, Glazener C, et al. PROSPECT: 4- and 6-year follow-up of a randomised trial of surgery for vaginal prolapse. Int Urogynecol J. 2023;34:67–78. doi:10.1007/s00192-022-05308-0.
9. European Association of Urology. Urethral Strictures Guidelines 2026: tissue transfer. Guideline.
10. Lara RC, Lucon AM, Arap S. Urethroplasty using a bovine pericardium graft: an experimental study using normal urethras from dogs. Braz J Med Biol Res. 2004;37:327–331. doi:10.1590/S0100-879X2004000300006.
11. Wong ML, Wong JL, Vapniarsky N, Griffiths LG. In vivo xenogeneic scaffold fate is determined by residual antigenicity and extracellular matrix preservation. Biomaterials. 2016;92:1–12. doi:10.1016/j.biomaterials.2016.03.024.
12. Leungwattanakij S, Bivalacqua TJ, Yang DY, Hyun JS, Hellstrom WJ. Comparison of cadaveric pericardial, dermal, vein, and synthetic grafts for tunica albuginea substitution using a rat model. BJU Int. 2003;92:119–124. doi:10.1046/j.1464-410x.2003.04279.x.
13. Choi JB, Lee DS. Efficacy of H-shaped incision with bovine pericardial graft in Peyronie's disease: a 1-year follow-up using penile Doppler ultrasonography. Int J Impot Res. 2021;33:541–547. doi:10.1038/s41443-020-0312-y.
14. Eslahi A, Ahmed F, Askarpour MR, et al. Outcomes of surgical correction of Peyronie's disease with plaque excision and grafting: comparison of testicular tunica vaginalis graft versus bovine pericardium graft. Asian J Urol. 2024;11:497–503. doi:10.1016/j.ajur.2023.03.005.
15. Natsos A, Tatanis V, Kontogiannis S, et al. Grafts in Peyronie's surgery without the use of prostheses: a systematic review and meta-analysis. Asian J Androl. 2024;26:250–259. doi:10.4103/aja202358.
16. Wessells H, Angermeier KW, Elliott S, et al. Urethral Stricture Disease: AUA Guideline (published 2016; amended 2023), statement 20.
17. Kambic H, Kay R, Chen JF, et al. Biodegradable pericardial implants for bladder augmentation: a 2.5-year study in dogs. J Urol. 1992;148:539–543. doi:10.1016/s0022-5347(17)36649-1.
18. Portis AJ, Elbahnasy AM, Shalhav AL, et al. Laparoscopic augmentation cystoplasty with different biodegradable grafts in an animal model. J Urol. 2000;164:1405–1411. doi:10.1016/s0022-5347(05)67207-2. PMID 10992423.
19. Chee JY, Durai P, Wu FM, Tiong HY. Bladder repair following iatrogenic cystotomy in irradiated small capacity bladders. Singapore Med J. 2015;56:e49–e52. doi:10.11622/smedj.2015052.
20. Yeung E, Baessler K, Christmann-Schmid C, et al. Transvaginal mesh or grafts or native tissue repair for vaginal prolapse. Cochrane Database Syst Rev. 2024;3:CD012079. doi:10.1002/14651858.CD012079.pub2.
21. Lorente K, Chang O. Biologic grafts for pelvic organ prolapse repairs: what have we learned in the last 20 years? Curr Opin Obstet Gynecol. 2024;36:439–443. doi:10.1097/GCO.0000000000000990.
22. Deprest J, De Ridder D, Roovers JP, et al. Medium term outcome of laparoscopic sacrocolpopexy with xenografts compared to synthetic grafts. J Urol. 2009;182:2362–2368. doi:10.1016/j.juro.2009.07.043.