Bulkamid — Polyacrylamide Hydrogel
Bulkamid, now part of Boston Scientific's product portfolio, is a permanent, nonparticulate hydrogel containing 2.5% cross-linked polyacrylamide and 97.5% water.[1][3] It improves urethral coaptation through submucosal volume augmentation. The US indication is SUI due to intrinsic sphincter deficiency in adult women with SUI or stress-predominant mixed incontinence; FDA approval was January 28, 2020.[1][2][3]
This is the material and device hub. For evaluation, injection workflow and follow-up, see Urethral Bulking Agents.
Composition and Mechanism
Bulkamid Hydrogel is a non-resorbable, transparent, hydrophilic gel. It consists of cross-linked polyacrylamide with loosely bound water, nominally 2.5% polyacrylamide and 97.5% non-pyrogenic water (w/w), supplied in pre-filled 1 mL syringes. The label describes it as biocompatible, non-biodegradable and non-migrational. Unlike the particulate agents Macroplastique and Coaptite, it is a homogeneous gel. It is injected into the submucosa of the proximal half of the urethra to improve coaptation, using a 23G, 12 cm needle through a rotatable sheath with a 2.7 mm, 0° cystoscope. It is not a mesh product.[3]
Role in Shared Decision-Making
Bulking can suit women who prioritize a less invasive procedure and shorter recovery, including selected women with persistent SUI after previous continence surgery. Counsel about lower cure rates than a sling and the frequent need for repeat treatment. The 2023 AUA/SUFU guideline does not establish one injectable as superior to another.[4] Its report of PAHG benefit persisting to 96 months is evidence of possible durability.[4]
Age, leakage severity and urethral mobility may influence outcomes. The 2024 AUGS Clinical Practice Statement concludes that ISD does not predict outcomes after urethral bulking; the US Bulkamid label still specifies SUI due to ISD.[25][2] The frequently quoted 90% response in older women with milder leakage (age 60 years or older with fewer than 2.5 daily stress episodes; 38% cured, versus 13% cured in younger women with 2.5 or more episodes) came from a post hoc analysis of 291 women combining PAHG and collagen recipients.[5] In the 130-woman single-center cohort, 101 underwent paired sonographic assessment; the 79 with normomobile urethras (linear dorsocaudal movement 6 to 24 mm) had the greatest mean ICIQ-UI SF reduction (3.8 points).[14] Women with hypomobile or hypermobile urethras also improved, to a lesser extent.[14]
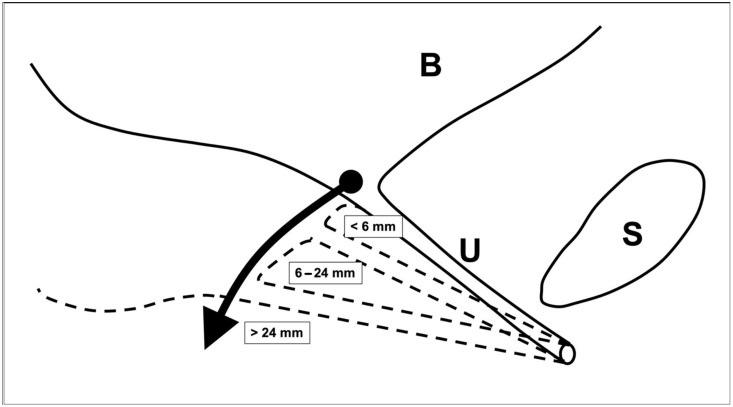
Urethral mobility assessed by linear dorsocaudal movement (LDM) of the internal urethral orifice relative to the edge of the symphysis pubis. The arrow shows increasing mobility: hypomobility is displacement of less than 6 mm, normomobility 6 to 24 mm and hypermobility more than 24 mm. From Nosal N, et al. J Clin Med. 2025;14(18):6555, Figure 1 (CC BY).[14]
The effect of treatment on pregnancy/delivery and the effect of pregnancy on treatment remain unknown.[2]
Labeling and Safety
Acute UTI is a contraindication. Assess for damaged urethral tissue and correct urethral or bladder-neck stricture before treatment. Overcorrection can cause obstruction. Do not inject intravascularly; vascular occlusion and embolism are possible. Stop injection if superficial mucosal capillaries fade, because this can indicate ischemia.[2]
The FDA labeling distinguishes events observed in the pivotal study from complications reported with other bulking agents that may also occur with Bulkamid.[3]
Other considerations include bleeding risk, impaired emptying, infection elsewhere, immunosuppression and tissue quality. The current US safety summary says to consider Bulkamid only in patients with well-controlled diabetes and to defer injection until full recovery from major surgery or dental work; safety and effectiveness have not been established in patients with active genital herpes, and safety has not been established in patients with autoimmune disease.[2] The US label identifies populations in which safety/effectiveness are not established, including neurogenic bladder, predominant urgency incontinence, detrusor overactivity, specified urethral hypermobility and higher-grade prolapse.[2]
Do not mix the hydrogel with other substances or inject it into a site previously treated with a different bulking agent. The gel kit is single-patient use; the separate cystoscope has its own processing instructions. The current US cystoscope warning specifically prohibits contact of patients with a bladder-cancer history with devices disinfected using Cidex OPA.[2]
Administration Boundaries
Injection uses endoscopic visualization and a dedicated sheath and needle system. Local anesthesia and an outpatient setting are feasible. Confirm infection status, the antimicrobial plan and the ability to empty the bladder after treatment.[3]
The 2020 FDA-posted instructions describe the following sequence.[3]
- Test the urine and do not proceed if a UTI is present. Position the patient in lithotomy. Place anesthetic gel in the urethra, or inject local anesthetic bilaterally along the urethral mucosa (3 and 9 o'clock) 5 to 10 minutes beforehand. Prophylactic antibiotics are advised per local protocol.
- Advance the sheath under vision, inspect the bladder and let it empty. Reinsert the optic, then introduce the needle until its tip is just visible without touching urethral tissue. Advance the sheath until the needle tip is adjacent to the bladder neck; align the needle with the first injection site, keep its bevel toward the urethral lumen and retract the system to about 2 cm from the bladder neck.[3]
- Press the sheath parallel to the urethral wall so the mucosa lies in front of the needle tip. Do not angle the system, which risks injecting too deep or too superficially.
- Insert the needle submucosally until the 1 cm marking on the needle is level with the mucosa.
- Inject at each site until the gel reaches the midline of the lumen, keeping the superficial mucosal vessels visible to avoid ischemia. Run water inflow to dilate the urethra.
- After an initial site (for example, 6 o'clock), repeat at either 2 and 10 o'clock or 3 and 9 o'clock for even circumferential bulking. Retract the needle before rotating or removing the sheath. Rotate only the rotatable part of the sheath so that all sites lie in one plane. Limit the number of punctures to reduce extravasation, and do not reinject the same site.
- Open the outflow between injections to avoid urgency. Empty the bladder afterward with a disposable 10 to 12 Fr catheter, not the sheath.
- Measure the residual volume after the first void. After the first void, the Bulkamid label permits discharge if post-void residual volume is 100 mL or less.[3] Patients who cannot void may perform intermittent catheterization with a 10 to 12 Fr catheter.
In a single-blinded randomized trial of in-office injection, adding a periurethral block to topical EMLA and intraurethral lidocaine gel lowered mean procedural pain (VAS 4.5 versus 7.4; p < 0.01) and reduced postprocedure catheterization (0% versus 33%). The trial stopped at 23 of 52 planned women after three topical-only patients needed an unplanned block.[23]
The label gives 1.5 to 2.0 mL as the typical total volume per session. In the pivotal trial the Bulkamid arm received a mean 1.6 mL initially and 3.3 mL across all sessions, and 52 of 228 (22.8%), 95 (41.7%) and 81 (35.5%) had one, two and three sessions.[3]
The FDA-posted 2020 physician instructions specify a maximum 2 mL per session, top-up no earlier than four weeks, and evidence for up to three treatment sessions. Use the current supplied IFU for exact positioning, injection plane, equipment and discharge criteria; avoid a universal per-site volume that could exceed the total limit.[3]
Main Comparative Evidence
North American Pivotal Trial — Comparison With Collagen
The FDA analysis included 228 Bulkamid and 117 collagen recipients. At 12 months, its composite endpoint of at least 50% reduction in both pad-test leakage and daily incontinence episodes was met by 107/228 (46.9%) versus 50/117 (42.7%), using the specified intention-to-treat analysis with last observation carried forward. [3] Bulkamid met the trial's noninferiority criterion. This comparison was against Contigen collagen, not a sling; the original journal report used somewhat different reported analysis figures.[3][6]
In the journal report of the same trial, 53.2% of hydrogel and 55.4% of collagen recipients had a 50% or greater decrease in leakage and incontinence episodes at 12 months, 47.2% versus 50% reported zero stress incontinence episodes, and 77.1% versus 70% considered themselves cured or improved. [6] Major adverse events were rare in each group. In the FDA complete-case analysis, cured, dry, much improved or improved responders were 144/187 (77.0%) versus 71/101 (70.3%).[3][6]
Repeat treatment was common: 176/228 received two or three injection sessions. In the FDA clinical data, 60/228 (26.3%) had at least one treatment-related adverse event, 64.2% of events were mild, and 93.8% had resolved at study closure. Treatment-related acute retention occurred in 13/228 (5.7%), implant-site pain in 28/228 (12.3%) and UTI in 8/228 (3.5%). One serious hematuria event was considered probably procedure-related.[3]
Short- and Medium-Term Series
| Study | Population and follow-up | Findings |
|---|---|---|
| Lose 2010 (open multicenter) | 135 treated (67 stress, 68 mixed); 98 completed 12 months | Subjective response was 66% with last observation carried forward. Median daily episodes fell from 3.0 to 0.7 and 24-hour pad weight from 29 to 4 g. Reinjection occurred in 47 (35%); two serious treatment-related urinary retentions resolved within nine days.[15] |
| Toozs-Hobson 2012 | Same open-label cohort; 86/135 attended at 24 months | Subjective response was 64% in an imputed 116-person analysis (20/116 [17%] cured), versus 67% at 12 months. Sixteen new nonserious and four serious adverse events occurred between years one and two; none was judged treatment-related.[16] |
| Lamblin 2025 (French multicenter cohort) | 320 women; median follow-up 24 months | At last follow-up 204 (63.7%) cured, 70 (21.9%) improved and 46 (14.4%) reported failure. Acute retention 3.1%, urinary infection 2.2%, transient hematuria 7.2%.[17] |
| Sze 2026 (retrospective) | 284 women; median follow-up 6.7 months | Median pad use fell from 2.0 to 1.0 per day. Among UDI-6 questionnaire completers (31% preprocedure, 32% postprocedure), the median score fell from 45.8 to 16.7 over a median 5.85 months between questionnaires. Repeat injection in 16.5% at a median 7.6 months, and 17 women (6.0%) progressed to a sling. Procedures without general anesthesia or sedation were associated with repeat injection (OR 2.82, 95% CI 1.33 to 5.79).[18] |
A systematic review of eight studies (767 women) reported reinjection in 186 (24.3%, range 12 to 35%), injection-site pain in 4 to 14% and UTI in 3 to 7%.[19] A separate review of 26 Bulkamid and Macroplastique studies reported subjective success of 66 to 89.7% at 12 months and objective success of 25.4 to 73.3%.[20] The EAU 2026 female LUTS guideline summarizes long-term effectiveness of 42 to 70% for Bulkamid, with minimal erosion or migration reported.[21]
Helsinki Randomized Trial — Five-Year TVT Comparison
The 2025 follow-up provides a long-term randomized comparison with a retropubic tension-free vaginal tape (TVT). 223 women were randomized, 212 received treatment as assigned and 195 attended at five years—92% of those treated.[7]
| Five-year outcome (randomized groups) | Assigned PAHG | Assigned TVT |
|---|---|---|
| Satisfaction score at least 80/100 | 74/99 (74.7%) | 89/96 (92.7%) |
| Median satisfaction score | 90 | 98 |
| Peri-/postoperative complication before crossover | 22/99 (22.2%) | 42/96 (43.8%) |
At five years, PAHG did not meet the prespecified 20-percentage-point noninferiority margin for the proportion with a satisfaction score of at least 80/100: among the 195 five-year follow-up attendees, 74.7% (74/99) in the PAHG-assigned group versus 92.7% (89/96) in the TVT-assigned group, a between-group difference of 18.0 percentage points (95% CI 7.7–28.0).[7] The complication outcome included events before crossover. At five years, satisfaction remained high in the PAHG-assigned arm, which had crossover to TVT by year three; median satisfaction and the proportion scoring at least 80/100 were higher in the TVT-assigned arm.[7][8]
Stress-test negativity, combined objective cure and patient-reported improvement are different endpoints. Among women attending the three-year visit, the intention-to-treat analysis by assigned arm found a negative cough stress test in 75/96 (78.1%) women assigned PAHG and 88/92 (95.7%) assigned TVT; 30 women assigned PAHG had crossed over to TVT. In the per-protocol analysis excluding crossover, both cough stress and pad tests were negative in 22/66 (33.3%) PAHG recipients versus 74/89 (83.1%) TVT recipients.[8]
Retreatment and Previous Sling Surgery
In a Finnish observational cohort of 391 primary procedures, two-year retreatment was 27.0% after PAHG versus 0.9% after TVT. In that cohort, PAHG complications were grades I–II[9]; higher-grade complications remain possible.
A systematic review after failed midurethral sling reported a pooled 80% cure/improvement estimate for the Bulkamid subgroup (95% CI 74 to 85%). [10] The estimate for all agents was 75%, with a pooled failure rate of 32% and a reoperation rate of 25%. [10] “Cure or improvement” is broader than dryness.[10] A 2025 meta-analysis of 20 studies of bulking agents for recurrent SUI reported a pooled objective cure or improvement of 56% and a pooled subjective satisfaction of 77%, with re-intervention after salvage bulking ranging from 9.8 to 42%.[24] In the Norwegian registry, 57 women received Bulkamid after retropubic TVT with insufficient improvement or recurrence. The stress test was negative in 72.9%, 73.7% were satisfied, and there was 1 complication in 67 injections. [22] De novo urgency incontinence occurred in five women (8.8% of the group, 26.3% of those without preoperative urgency incontinence).[22]
Office-based delivery can improve cost-effectiveness, but the often-cited 58% office-use threshold comes from a particular economic model.[11]
Guideline Position
The AUA/SUFU 2023 female SUI guideline states that bulking agents are viable treatments, that retreatment is common, and that there are inadequate data to recommend one injectable over another.[4] Calcium hydroxyapatite, polydimethylsiloxane and PAHG have longer-term data showing persistence of effect at 73.2, 83 and 96 months, respectively. The guideline notes that erosion was not present in PAHG patients versus other agents in multiple studies. It considers bulking for women who wish to avoid more invasive surgery, are concerned about a longer recovery, or have insufficient improvement after a previous anti-incontinence procedure.[4] The EAU 2026 guideline recommends offering bulking to women requesting a low-risk procedure after counseling that efficacy is lower than with other operations, repeat injections are likely, and long-term durability and safety remain unestablished .[21]
Male Use and Pediatric Reflux
The current US Bulkamid label warns not to use it in male patients. More broadly, the AUA/GURS/SUFU guideline recommends that clinicians counsel patients that efficacy is low and cure is rare with urethral bulking agents for incontinence after prostate treatment .[2][12]
PAHG has been studied for pediatric vesicoureteral reflux. A prospective study of 76 children (123 refluxing units) reported 71% success 3 months after a single injection and a median injected volume of 1.0 mL per renal unit.[13] At a median follow-up of 36 months, no upper-tract deterioration or bulking-agent calcification was reported; ultrasound follow-up covered 68/70 eligible children at 12 months and 40/46 at 36 months.[13] Urinary infections occurred in 9 (12%) nonfebrile and 2 (3%) febrile cases. [13] This is outside the US Bulkamid indication.[2]
See also: Macroplastique, Coaptite, Durasphere.
References
1. Boston Scientific. Bulkamid Urethral Bulking System. Current US product identity and specifications. Product resource.
2. Boston Scientific. Bulkamid Urethral Bulking System and Cystoscope: US indications, safety and warnings. Brief summary referencing IFU 110-0303rB. Current US safety information.
3. FDA. Bulkamid Urethral Bulking System: Instructions for Use. Original US approval labeling, January 2020, 10078-001. Physician labeling; PMA record and supplements.
4. Kobashi KC, Vasavada S, Bloschichak A, et al. Updates to Surgical Treatment of Female Stress Urinary Incontinence (SUI): AUA/SUFU Guideline (2023). The Journal of Urology. 2023;209(6):1091-1098. doi:10.1097/JU.0000000000003435
5. Elmelund M, Sokol ER, Karram MM, Dmochowski R, Klarskov N. Patient Characteristics That May Influence the Effect of Urethral Injection Therapy for Female Stress Urinary Incontinence. The Journal of Urology. 2019;202(1):125-131. doi:10.1097/JU.0000000000000176
6. Sokol ER, Karram MM, Dmochowski R. Efficacy and Safety of Polyacrylamide Hydrogel for the Treatment of Female Stress Incontinence: A Randomized, Prospective, Multicenter North American Study. The Journal of Urology. 2014;192(3):843-849. doi:10.1016/j.juro.2014.03.109
7. Itkonen Freitas AM, Isaksson C, Rahkola-Soisalo P, Mentula M, Mikkola TS. Tension-Free Vaginal Tape versus Polyacrylamide Hydrogel Injection for Stress Urinary Incontinence — 5-Year Follow-Up. NEJM Evidence. 2025;4(5):EVIDoa2400216. doi:10.1056/EVIDoa2400216
8. Itkonen Freitas AM, Isaksson C, Rahkola-Soisalo P, et al. Tension-Free Vaginal Tape and Polyacrylamide Hydrogel Injection for Primary Stress Urinary Incontinence: 3-Year Followup From a Randomized Clinical Trial. The Journal of Urology. 2022;208(3):658-667. doi:10.1097/JU.0000000000002720
9. Särkilahti L, Isaksson C, Mikkola TS. Tension-Free Vaginal Tape Versus Polyacrylamide Hydrogel Bulking Agent for Stress Urinary Incontinence: Patient Choice and Outcomes in Finland. International Urogynecology Journal. 2025;36(4):895-902. doi:10.1007/s00192-025-06119-9
10. Braga A, Caccia G, Papadia A, et al. Urethral Bulking Agents for the Treatment of Recurrent Stress Urinary Incontinence: A Systematic Review and Meta-Analysis. Maturitas. 2022;163:28-37. doi:10.1016/j.maturitas.2022.05.007
11. Chang OH, Shepherd JP, Cadish LA, et al. Urethral Bulking With Polyacrylamide Hydrogel Compared With Other Treatments for Stress Urinary Incontinence: A Cost-Effectiveness Analysis. Obstetrics and Gynecology. 2024;143(3):428-430. doi:10.1097/AOG.0000000000005503
12. AUA/GURS/SUFU. Incontinence After Prostate Treatment Guideline, amended 2024. Statement 25. Official guideline.
13. Ramsay S, Blais AS, Morin F, et al. Polyacrylamide Hydrogel as a Bulking Agent for the Endoscopic Treatment of Vesicoureteral Reflux: Long-Term Results and Safety. The Journal of Urology. 2017;197(3 Pt 2):963-967. doi:10.1016/j.juro.2016.08.093
14. Nosal N, Gerling A, Kuhn A, et al. Predictive Measurement of Urethral Mobility for Successful Transurethral Bulkamid Application in Women With Stress Urinary Incontinence. Journal of Clinical Medicine. 2025;14(18):6555. doi:10.3390/jcm14186555
15. Lose G, Sørensen HC, Axelsen SM, et al. An Open Multicenter Study of Polyacrylamide Hydrogel (Bulkamid) for Female Stress and Mixed Urinary Incontinence. International Urogynecology Journal. 2010;21(12):1471-1477. doi:10.1007/s00192-010-1214-1
16. Toozs-Hobson P, Al-Singary W, Fynes M, Tegerstedt G, Lose G. Two-Year Follow-Up of an Open-Label Multicenter Study of Polyacrylamide Hydrogel (Bulkamid) for Female Stress and Stress-Predominant Mixed Incontinence. International Urogynecology Journal. 2012;23(10):1373-1378. doi:10.1007/s00192-012-1761-8
17. Lamblin G, Boix S, Moret S, et al. Effectiveness and Safety Profile of Urethral Bulking With Bulkamid for Stress Urinary Incontinence: A French Multi-Center Cohort Study. International Urogynecology Journal. 2025;36(1):205-211. doi:10.1007/s00192-024-06005-w
18. Sze C, Advano D, Fernandez CM, et al. Symptom Relief and Practice Setting Variation in Bulkamid Injections for Stress Urinary Incontinence. Neurourology and Urodynamics. 2026. doi:10.1002/nau.70289
19. Kasi AD, Pergialiotis V, Perrea DN, Khunda A, Doumouchtsis SK. Polyacrylamide Hydrogel (Bulkamid) for Stress Urinary Incontinence in Women: A Systematic Review of the Literature. International Urogynecology Journal. 2016;27(3):367-375. doi:10.1007/s00192-015-2781-y
20. Siddiqui ZA, Abboudi H, Crawford R, Shah S. Intraurethral Bulking Agents for the Management of Female Stress Urinary Incontinence: A Systematic Review. International Urogynecology Journal. 2017;28(9):1275-1284. doi:10.1007/s00192-017-3278-7
21. EAU Guidelines on Management of Non-Neurogenic Female Lower Urinary Tract Symptoms (LUTS), limited update March 2026, section 4.2.4.c.2.c (urethral bulking agents). EAU guidelines.
22. Myhr SS, Rakovan M, Schiøtz HA. Periurethral Injection With Polyacrylamide After Previous TVT Surgery. International Urogynecology Journal. 2022;33(4):1017-1022. doi:10.1007/s00192-021-04891-y
23. Gaddam NG, Marantidis J, Ahmed NT, et al. Optimal Anesthesia for Polyacrylamide Hydrogel Injection: A Randomized Trial. Urogynecology. 2026;32(8):919-927. doi:10.1097/SPV.0000000000001757
24. Hoffman O, Jiang J, Rashid S, et al. Urethral Bulking Agent as a Salvage Procedure for Female Stress Urinary Incontinence: A Systematic Review and Meta-Analysis. International Urogynecology Journal. 2025;36(10):1921-1933. doi:10.1007/s00192-025-06373-x
25. Fleischmann N, Chughtai B, Plair A, et al. "Urethral Bulking." Urogynecology (Phila). 2024;30(8):667-682. doi:10.1097/SPV.0000000000001548